Carcinoma of the Cervix Epidemiology for women aged





























































































































































- Slides: 196
Carcinoma of the Cervix
Epidemiology �for women aged 20 to 39 years, cervical cancer remained the second leading cause of cancer deaths after breast cancer, accounting for about 10% of cancer deaths. �Despite the declining death rates in developed countries cervical cancer remains the leading cause of cancer deaths among women in many medically underserved countries, including many countries of Latin America, Africa, Asia, and eastern Europe.
کﺎﻫﺶ ﻣﺮگ ﺩﺭ ﺍﺛﺮ کﺎﻧﺴﺮ ﺳﺮﻭیکﺲ routine screening programs, including pelvic examinations and cervical cytologic evaluation 2. the death rates from cervical cancer had begun to decrease before the implementation of Papanicolaou (Pap) screening, suggesting that other unknown factors may have played some role. 1.
International incidences �cultural attitudes �screening programs �liberal attitudes toward sexual behavior
ﺍﺗیﻮﻟﻮژی �HPV �prostitutes � first coitus at a young age �multiple sexual partners �bear children at a young age � Promiscuous sexual behavior in male partners �a lower incidence of HPV infection in circumcised than uncircumcised males, with a correspondingly lower incidence of cervical cancer in their female partners.
prophylactic HPV vaccine �a prophylactic HPV vaccine for women between the ages of 9 and 26 years; this quadrivalent vaccine has been demonstrated to be highly effective in preventing benign warts and neoplasia caused by the most common HPV types (6, 11, 16, and 18).
ﻋﻠﻞ ﻋﺪﻡ کﺎﻫﺶ ﺍﻧﺴیﺪﺍﻧﺲ ﺍﺩﻧﻮکﺎﺭﺳیﻨﻮﻣﺎ ﺳﺮﻭیکﺲ A. an increase in recognition of cases with glandular elements as adenocarcinomas B. cytologic screening methods may be less effective in detecting adenocarcinomas at a preinvasive stage
ﺍﺭﺗﺒﺎﻁ ﻧﻘﺺ ﺍیﻤﻨی ﻭ کﻨﺴﺮ ﺳﺮﻭیکﺲ �The relationship between immunosuppression (particularly HIV-related immunosuppression) and the risk of HPV-related disease is complex and incompletely understood. � Current data strongly suggest that HIV-related immunosuppression is correlated with an increased risk of cervical HPV infection. �an inverse correlation between CD 4+ level and the risk of HPV infection, and patients with low CD 4+ levels tend to have higher HPV DNA levels.
�(HIV) infection also appears to be associated with a higher prevalence of CIN and a faster rate of progression to high-grade CIN. �Iatrogenic immunosuppression is also associated with an increased prevalence of CIN. � risk of progression from CIN to invasive disease and on the virulence of invasive cervical cancer is less certain � Antiretroviral therapy does not appear to affect HPV levels, and rarely produces regression of CIN 2 or CIN 3 lesions, even with increases in CD 4+ levels.
HIV-positive �Overlapping risk factors tend to confound studies of the association between HIV and HPV-related cancers. However, because of the increased risk of HPV infection in HIV-positive women, vigilant surveillance with Pap smears, pelvic examinations, and colposcopy (when indicated) should be part of the routine care of these women.
Natural History and Pattern of Spread �Most arise at the junction between the primarily columnar epithelium of the endocervix and the squamous epithelium of the ectocervix. �This junction is a site of continuous metaplastic change, which is greatest in utero, at puberty, and during first pregnancy, and declines after menopause. The greatest risk of neoplastic transformation coincides with periods of greatest metaplastic activity. Virally induced atypical squamous metaplasia developing in this region can progress to higher-grade squamous intraepithelial lesions (SILs).
�The mean age of women with CIN is about 15 years younger than that of women with invasive cancer, suggesting a slow progression of CIN to invasive carcinoma.
Natural History and Pattern of Spread �CIN 3 disease progressed in only 14%, whereas it remained the same in 61% and disappeared in the others �spontaneous regression in 38% of high-grade HPVassociated SILs. �mean times to development of carcinoma in situ of 58, 38, and 12 months for patients with mild, moderate, or severe dysplasia, respectively, and predicted that 66% of all cases of dysplasia would progress to carcinoma in situ within 10 years.
Natural History and Pattern of Spread �exophytic growths �endocervical lesions �Tumor may become fixed to the pelvic wall by direct extension or by coalescence of central tumor with regional adenopathy. �bladder mucosal invasion. �Rectum invasion
Three groups of lymphatics �The upper branches: follow the uterine artery, and terminate in the uppermost hypogastric nodes. � The middle branches drain to deeper hypogastric (obturator) nodes. �The lowest branches follow a posterior course to the inferior and superior gluteal, common iliac, presacral, and subaortic nodes.
�The incidence of pelvic and para-aortic node involvement is correlated with tumor stage and with other tumor characteristics, such as size, histologic subtype, depth of invasion, and presence of LVSI �stage I disease treated with radical hysterectomy, most investigators report an incidence of positive pelvic nodes of 15% to 20% and an incidence of paraaortic nodes of 1% to 5%. Reported incidences are higher for patients with stage I disease treated with radiation: 10% to 25% of such patients are reported to have positive para-aortic nodes, reflecting the more advanced stage I tumors that are usually selected for treatment with radiation.
pattern of metastas �Cervical cancer usually follows a relatively orderly pattern of metastatic progression, initially to primaryechelon nodes in the pelvis and then to para-aortic nodes and distant sites. �Even patients with locoregionally advanced disease rarely have detectable hematogenous metastases at initial diagnosis of their cervical cancer. � The most frequent sites of distant recurrence are lung, extrapelvic nodes, liver, and bone
Pathology
Cervical Intraepithelial Neoplasia cervical cytologic findings (important characteristics ): �cellular immaturity �cellular disorganization � nuclear abnormalities �increased mitotic activity.
degree of neoplasia �extensiveness of the mitotic activity �immature cell proliferation �nuclear atypia � If mitoses and immature cells are present only in the lower third of the epithelium, the lesion is usually designated CIN 1. Lesions involving only the lower and middle thirds are designated as CIN 2, and those involving the upper third are designated as CIN 3.
The term cervical intraepithelial neoplasia, refers only to a lesion that may progress to invasive carcinoma. Although CIN 1 and CIN 2 are sometimes referred to as mild-to-moderate dysplasia, CIN is now preferred over dysplasia. The Bethesda system of classification, designed to further standardize reporting of cervical cytologic findings, was developed
Squamous intraepithelial lesions SILs include �Condyloma �dysplasia, � CIN The Bethesda system divides SILs �low grade � high grade(higher likelihood of progressing to invasive cancer)( CIN 2, CIN 3)
Bethesda system �atypical squamous cells of undetermined significance (ASCUS). � most common abnormal Pap smear result in United States laboratories, �most cases of ASCUS reflect a benign process, about 5% to 10% are associated with an underlying HSIL, and one third or more of HSILs are heralded by a finding of ASCUS on a Pap smear.
three methods of management ASCUS or LSIL �immediate colposcopy � cytologic follow-up �HPV DNA testing (ASCUS ) LSIL ASCUS, HPV DNA testing had a sensitivity in the detection of HSIL similar to that of immediate colposcopy and reduced the number of referrals for colposcopy by 50%.
Adenocarcinoma In Situ �About 20% to 50% of women with cervical adenocarcinoma in situ also have squamous CIN, and adenocarcinoma in situ is often an incidental finding in patients operated on for squamous carcinoma. �is frequently multifocal, cone biopsy margins are unreliable.
Microinvasive Carcinoma �definition of microinvasive carcinoma is based on the maximum depth (no more than 5 mm) and linear extent (no more than 7 mm) of involvement. � This requires a cervical cone biopsy � With the advent of cytologic screening, the proportion of invasive carcinomas that invade less than 5 mm has increased more than tenfold to about 20% in the United States
Microinvasive Carcinoma �The importance of LVSI remains somewhat controversial �the risk of metastatic regional disease appears to be exceedingly low for any tumor that invades less than 3 mm, even in the presence of LVSI. �many think that the risk of regional spread from tumors that have invaded 3 to 5 mm is sufficiently high to warrant treatment of the parametria and regional nodes.
Microinvasive adenocarcinoma �measuring the depth of invasion can be difficult. �a subset of patients with very small adenocarcinomas have a low likelihood of lymph node metastases or recurrence. In the absence of a consensus definition of microinvasion for adenocarcinoma, decisions are usually guided by specific descriptions of the depth and extent of invasion and other features that have been correlated with increased risk, such as high grade and the presence of LVSI.
Invasive Squamous Cell Carcinoma A number of systems have been used to grade and classify squamous cell carcinomas, but none have consistently been demonstrated to predict prognosis �large cell keratinizing � large cell nonkeratinizing � small cell carcinoma (poorer prognosis) �Papillary variants of squamous carcinoma 1. well differentiated (occasionally confused with immature condylomata) 2. very poorly differentiated (resembling high-grade transitional carcinoma) � Verrucous carcinoma (DDx benign condyloma ) �Sarcomatoid squamous carcinoma
Adenocarcinoma �pure or mixed with squamous cell carcinoma (adenosquamous carcinoma). � 80% of cervical adenocarcinomas are of the endocervical type �Minimal-deviation adenocarcinoma (adenoma malignum) is a rare, extremely well-differentiated adenocarcinoma that is sometimes associated with Peutz-Jeghers syndrome.
Adenocarcinoma Other rare variants of adenosquamous carcinoma include � adenoid basal carcinoma (favorable prognosis) � adenoid cystic carcinoma(aggressive behavior ) � endometrioid, serous, or clear cells; mixtures of these cell types
Anaplastic Small Cell/Neuroendocrine Carcinoma � Anaplastic small cell carcinoma resembles oat cell carcinoma of the lung � About 30% to 50% of anaplastic small cell carcinomas display neuroendocrine features. � Widespread hematogenous metastases
Other Rare Neoplasms �A variety of neoplasms may infiltrate the cervix from adjacent sites, and this makes differential diagnosis difficult. Although endometrioid histology suggests endometrial origin and mucinous tumors in young patients are most often of endocervical origin, both histologic types can arise in either site. �Metastatic tumors from the colon, breast, or other sites may involve the cervix secondarily. �Malignant mixed mullerian tumors, adenosarcomas, and leiomyosarcomas occasionally arise in the cervix but more often involve it secondarily. �Primary lymphomas and melanomas of the cervix are extremely rare.
Clinical Manifestations �Preinvasive disease during routine cervical cytologic screening. �Early invasive disease usually detected during screening examinations �abnormal vaginal bleeding, often following coitus or vaginal douching. �a clear or foul-smelling vaginal discharge � Pelvic pain �Flank pain (hydronephrosis complicated by pyelonephritis) The triad of sciatic pain, leg edema, and hydronephrosis is almost always associated with extensive pelvic wall involvement by tumor. �hematuria or incontinence from a vesicovaginal fistula � External compression of the rectum by a massive primary tumor may cause constipation
Diagnosis �an ideal target for cancer screening � cervical cytologic examination and pelvic examination has led to a decrease in the mortality rate � Only nations with well-developed screening programs have experienced substantial decreases in cervical cancer death rates
Screening (The American Cancer Society) � 3 years after the onset of vaginal intercourse, but no later than 21 years of age �annually with conventional cervical cytology smears �every 2 years using liquid-based Pap cytology ( until age 30 years) � Starting at age 30 years, women who have had three consecutive, technically satisfactory negative test results may be screened every 2 to 3 years.
ﻣﻮﺍﺭﺩ ﻗﻄﻊ ﺍﺳکﺮیﻨیﻨگ Women age 70 years and more who have had three consecutive negative 2. no abnormal test result within 10 years 3. who have had a total hysterectomy for benign gynecologic disease. 4. Women with a history of CIN 2 or CIN 3 prior to or as an indication for hysterectomy should be screened until they have had three consecutive normal test results and no abnormal test results for 10 years. 1.
Women with a history of cervical cancer, women exposed in utero to diethylstilbestrol (DES), and women who are immunocompromised should continue regular screening as long as they are in reasonably good health.
The rate of false-negative findings on the Pap test is about 1. 20% to 30% in women with high-grade CIN 2. 10% to 15% in women with invasive cancer.
Dx �Detection of high endocervical lesions may be improved when specimens are obtained with a cytobrush. � Because hemorrhage, necrosis, and intense inflammation may obscure the results, the Pap smear is a poor way to diagnose gross lesions; these should always be biopsied.
�the sensitivity of a screening program is usually increased by repeated annual testing. The sensitivity of individual tests may be improved by ensuring adequate sampling of the squamocolumnar junction and the endocervical canal; smears without endocervical or metaplastic cells are inadequate, and in such cases the test must be repeated. Because adenocarcinoma in situ originates near or above the transformation zone, it may be missed with conventional cervical smears.
liquid-based Pap methods � greater sensitivity than conventional Pap smears. � the likelihood of drying artifact is reduced, �cellular sampling tends to be better �the cells are more evenly distributed on the slide. ü Greater sensitivity comes at the cost of somewhat poorer specificity, which is balanced by the less frequent need for repetition of the study to achieve adequate screening.
HPV testing �although it is not yet recommended for routine screening, HPV testing of ASCUS smears followed by colposcopy in patients with HPV-positive lesions appears to provide a highly accurate and cost-effective means of detecting HSIL in equivocal smears.
Patients with abnormal findings on cytologic examination who do not have a gross cervical lesion must be evaluated with colposcopy and directed biopsies. Following application of a 3% acetic-acid solution, the cervix is examined under 10 - to 15 -fold magnification with a bright, filtered light that enhances the acetowhitening and vascular patterns characteristic of dysplasia or carcinoma. The skilled colposcopist can accurately distinguish between lowand high-grade dysplasia, but microinvasive disease cannot consistently be distinguished from intraepithelial lesions on colposcopy.
In a patient with an atypical Pap smear finding, if no abnormalities are found on colposcopic examination or if the entire squamocolumnar junction cannot be visualized, endocervical curettage should be performed. Some authorities advocate the routine addition of endocervical curettage to colposcopic examination to minimize the risk of missing occult cancer within the endocervical canal. However, it is probably reasonable to omit this step in previously untreated women if the entire squamocolumnar junction is visible with a complete ring of unaltered columnar epithelium in the lower canal
Cervical cone biopsy 1. is used to diagnose occult endocervical lesions 2. is an essential step in the diagnosis and management of microinvasive carcinoma of the cervix.
v. Cervical cone biopsy yields an accurate diagnosis and decreases the incidence of inappropriate therapy when (1) the squamocolumnar junction is poorly visualized on colposcopy and a high-grade lesion is suspected, (2) high-grade dysplastic epithelium extends into the endocervical canal, (3) the cytologic findings suggest high-grade dysplasia or carcinoma in situ, (4) a microinvasive carcinoma is found on directed biopsy, (5) the endocervical curettage specimens show highgrade CIN, (6) the cytologic findings are suggestive of adenocarcinoma in situ.
Clinical Evaluation of Patients with Invasive Carcinoma 1. detailed history 2. physical examination, 3. complete blood cell count and renal function and liver function tests 4. chest radiography 5. intravenous pyelography (or computed tomography [CT]) 6. Cystoscopy and either a proctoscopy or a barium enema study should be done in patients with bulky tumors. 7. CT S or MRI 8. PET
CT S or MRI to evaluate regional nodes, but these studies have suboptimal accuracy because they fail to detect small metastases and because patients with bulky necrotic tumors often have enlarged reactive lymph nodes that may be free of metastasis. PET appears to be a very sensitive noninvasive method of evaluating the regional nodes of patients with cervical cancer 74 and a useful method for following response to treatment, 80 although its high cost has prevented widespread routine use. MRI can provide useful information about the distribution and depth of invasion of tumors in the cervix but tends to yield less accurate assessments of the parametrium.
International Federation of Gynecology and Obstetrics Staging of Carcinoma of the Cervix (1994) 0 Carcinoma in situ, intraepithelial carcinoma. I The carcinoma is strictly confined to the cervix (extension to the corpus should be disregarded) IA microscopically Invasion is limited to measured stromal invasion with a maximum depth of 5 mm and no wider than 7 mm. Vascular space involvement, either venous or lymphatic, should not alter the staging). IA 1 Measured invasion of stroma no greater than 3 mm in depth and no wider than 7 mm. IA 2 Measured invasion of stroma greater than 3 mm and no greater than 5 mm in depth and no wider than 7 mm. IB Clinical lesions confined to the cervix or preclinical lesions greater than IA IB 1 Clinical lesions no greater than 4 cm in size IB 2 Clinical lesions greater than 4 cm in size
II The carcinoma extends beyond the cervix, but has not extended onto the pelvic wall; the carcinoma involves the vagina, but not as far as the lower third IIA No obvious parametrial involvement IIB Obvious parametrial involvement. III carcinoma has extended onto the pelvic wall; on rectal examination there is no cancer-free space between the tumour and the pelvic wall; the tumour involves the lower third of the vagina; all cases with a hydronephrosis or nonfunctioning kidney should be included, unless they are known to be due to other cause. IIIA No extension onto the pelvic wall, but involvement of the lower third of the vagina IIIB Extension onto the pelvic wall or hydronephrosis or nonfunctioning kidney.
IV The carcinoma has extended beyond the true pelvis or has clinically involved the mucosa of the bladder or rectum IVA Spread of the growth to adjacent organs IVB Spread to distant organs.
Up todate �TNM stage �FIGO stage �T 1 b =IB : Clinically visible lesion confined to the cervix or microscopic lesion greater than IA 2 �AJCC stage grouping �adenocarcinoma in situ
Clinical Staging �FIGO stage is based on careful clinical examination and the results of specific radiologic studies and procedures. �The clinical stage should never be changed on the basis of subsequent findings. �When it is doubtful , case should be assigned to the earlier stage.
Clinical Staging �According to FIGO, growth fixed to the pelvic wall by a short and indurated, but nodular, parametrium should be allotted to stage IIb. �A case should be classified as stage III only if the parametrium is nodular to the pelvic wall or if the growth itself extends to the pelvic wall.
FIGO rules for clinical staging, �Palpation � Inspection �Colposcopy � endocervical curettage � hysteroscopy � cystoscopy �Proctoscopy � intravenous urography �radiographic examination of the lungs and skeleton .
�Suspected bladder or rectal involvement should be confirmed by biopsy � Findings of bullous edema or malignant cells in cytologic washings from the urinary bladder are not sufficient to diagnose bladder involvement
�FIGO specifically states that findings on examinations such as 1. lymphangiography 2. Laparoscopy 3. CT, and MRI : are of value for planning therapy but because these are not yet generally available and the interpretation of results is variable should not be the basis for changing the clinical stage � Examination under anesthesia is desirable but not required.
�The rules and notes outlined in the FIGO staging system are integral parts of the clinical staging system and should be strictly observed to minimize inconsistencies in staging between institutions.
�Although surgically treated patients are sometimes classified according to a TNM pathologic staging system, this practice has not been widely accepted because it cannot be applied to patients who are treated with primary radiotherapy.
Surgical Evaluation of Regional Spread �transperitoneal �extraperitoneal dissection �laparoscopic lymph node dissection ? �sentinel node ?
surgical staging(controversial) �identifies patients with microscopic para-aortic or common iliac node involvement who can benefit from extended-field irradiation. �debulking of large pelvic nodes before radiotherapy may improve outcome. Because patients with radiographically positive pelvic nodes are at greatest risk for occult metastasis to para-aortic nodes, these patients may have the greatest chance of benefiting from surgical staging �Some authors have advocated pretreatment blind biopsy of the scalene node in patients with positive para-aortic nodes and in patients with a central recurrence who are being considered for pelvic exenteration. The reported incidence of supraclavicular metastasis varies widely (5% to 20% or more) for patients with positive para-aortic lymph nodes.
Prognostic Factors �FIGO stage �Clinical tumor diameter �presence of medial versus lateral parametrial involvement �presence of unilateral versus bilateral parametrial or pelvic wall involvement �Lymph node metastasis �LVSI �deep stromal invasion (10 mm or more than 70% invasion) �parametrial extension �inflammatory response �Uterine-body involvement ( distant metastases ) �histologic features �histologic grade (adenocarcinomas) �HGB(locally advanced )
�Operative findings often do not agree with clinical estimates of parametrial or pelvic wall involvement, and some authors have found that the predictive power of stage diminishes or is lost when comparisons are corrected for differences in clinical tumor diameter.
Other clinical and biologic features that have been investigated for their predictive power, with variable results, include : �Age �peritoneal cytology �platelet count �tumor vascularity �DNA ploidy or S phase �cyclooxygenase-2 expression �growth factor receptors. �HPV DNA
Treatment depended on �tumor size � stage � histologic features � evidence of lymph node metastasis �risk factors for complications of surgery or radiotherapy �patient preference.
�HSILs : loop electroexcision procedure (LEEP) �stage IA 1: conservative surgery (excisional conization or extrafascial hysterectomy [type I]) �stage IA 2 and IB 1 and some small stage IIA tumors: modified radical (type II) or radical (type III) hysterectomy or radiotherapy �stages IB 2 through IVA: radiotherapy � Selected patients with centrally recurrent disease after RT may be treated with radical exenterative surgery � isolated pelvic recurrence after hysterectomy is treated with irradiation. � the routine addition of concurrent cisplatin-containing chemotherapy to radiotherapy for patients whose cancers have a high risk of locoregional recurrence.
Preinvasive Disease (Stage 0) 1. 2. 3. 4. 5. HSILs : (LEEP, LEEP conization, or excisional [cold knife] conization with a scalpel) LEEP Conization: suspicion of occult invasion on cytologic or colposcopic examination ablative therapy ( cryotherapy or CO 2 laser ablation )has declined low-grade dysplasias are often followed without treatment vaginal or type I abdominal hysterectomy for other gynecologic conditions not for invasive cancer
LEEP �excise the entire transformation zone and distal canal. �control rates are similar to those achieved with cryotherapy or laser ablation. � LEEP is an outpatient office procedure that preserves fertility. �patients require careful post-LEEP surveillance
LEEP conization or excisional conization with a scalpel �microinvasive suspected � invasive cancer suspected �adenocarcinoma in situ.
Microinvasive Carcinoma (Stage IA 1) �conization or total (type I) or vaginal hysterectomy. � pelvic lymphadenectomy is not usually recommended. �Patients without LVSI and who wish to maintain fertility may be adequately treated with a therapeutic cervical conization if the margins of the cone are negative. �patients who have this conservative treatment must be followed closely with periodic cytologic evaluation, colposcopy, and endocervical curettage.
residua �The likelihood of residual invasive disease after cone biopsy is correlated with the status of the internal cone margin and the results of an endocervical curettage performed after cone biopsy. �The authors did not find any correlation between the depth of invasion or the number of invasive foci and residual invasion.
Therapeutic conization for microinvasive disease �is usually performed with a scalpel while the patient is under general or spinal anesthesia � entire specimen must be sectioned
�Complications occur in 2% to 12% of patients, are related to the depth of the cone, and include hemorrhage, sepsis, infertility, stenosis, and cervical incompetence. The width and depth of the cone should be tailored to produce the least amount of injury while providing clear surgical margins.
�For (FIGO stage IA 2), the risk of nodal metastases is approximately 5%. Therefore, in such patients, a bilateral pelvic lymphadenectomy should be performed in conjunction with a modified radical (type II) hysterectomy. �Although surgical treatment is standard for in situ and microinvasive cancer, patients with severe medical problems or other contraindications to surgical treatment can be successfully treated with radiotherapy.
Stage IB and IIA Disease �Early stage IB cervical carcinomas can be treated effectively with combined external-beam irradiation and brachytherapy or with radical hysterectomy and bilateral pelvic lymphadenectomy. The goal of both treatments is to destroy malignant cells in the cervix, paracervical tissues, and regional lymph nodes. Patients who are treated with radical hysterectomy whose tumors are found to have high-risk features may benefit from postoperative radiotherapy or chemoradiation.
stage IB �Overall survival rates between 80% and 90%, ( with surgery =radiation ) �surgery or radiotherapy?
stage IB 1 choice of treatment is based �patient preference, �anesthetic and surgical risks � physician preference, � an understanding of the nature and incidence of complications with radiotherapy and hysterectomy.
stage IB 1 �For patients with similar tumors, the overall rate of major complications is similar with surgery and radiotherapy, although urinary tract complications tend to be more common after surgical treatment and bowel complications are more common after radiotherapy. �Surgical treatment tends to be preferred for young women with small tumors because it permits preservation of ovarian function and may cause less vaginal shortening. Radiotherapy is often selected for older, postmenopausal women to avoid the morbidity of a major surgical procedure.
stage IB 2 (bulky) �radical hysterectomy �radical radiotherapy However, patients who have tumors measuring more than 4 cm in diameter usually have deep stromal invasion and are at high risk for lymph node involvement and parametrial extension. Because patients with these risk factors have an increased rate of pelvic disease recurrence, surgical treatment is usually followed by postoperative irradiation, which means that the patient is exposed to the risks of both treatments. Consequently, many gynecologic and radiation oncologists believe that patients with stage IB 2 carcinomas are better treated with radical radiotherapy.
concurrent administration of cisplatin-containing chemotherapy �bulky stage I cancers �lymph node metastasis �involved surgical margins � IB 2<=
�Patients who have stage IB 1 cancers without evidence of regional involvement have excellent pelvic control rates (about 97% at 5 years) with radiotherapy alone and probably do not require chemotherapy when they are treated with primary radiotherapy
Radical Hysterectomy �The standard surgical treatment for stage IB and IIA cervical carcinomas is radical (type III) hysterectomy and bilateral pelvic lymphadenectomy �Modified radical (type II) hysterectomy may be used for selected, small (less than 2 -cm diameter) stage IB lesions. �For premenopausal women (i. e. , younger than 50 years), the ovaries usually are not removed. Ovarian metastases are rare in the absence of metastases to lymph nodes or other sites. If intraoperative findings suggest a need for postoperative pelvic irradiation, the ovaries may be transposed out of the pelvis.
postoperative complications �blood loss (mean, 0. 8 liter) � ureterovaginal fistula (1% to 2%) � vesicovaginal fistula (less than 1%) �pulmonary embolus (1% to 2%) �small bowel obstruction (1% to 2%) �postoperative fever (25% to 50%) secondary to: deep vein thrombosis pulmonary infection pelvic cellulitis urinary tract infection wound infection
Subacute complications �lymphocyst formation and lower-extremity edema Lymphocysts may obstruct a ureter, but hydronephrosis usually improves with drainage of the lymphocyst. The risk of complications may be increased in patients who undergo preoperative or postoperative irradiation.
Bladder complications 1. decreased bladder sensation 2. chronic bladder hypotonia or atony (3% to 5% ) 3. Bladder dysfunction 4. stress incontinence(influenced by RT) 5. bladder contraction and instability(RT post s) Bowel complications �constipation and, rarely, chronic obstipation �small bowel obstruction(RT post s)
The use of radical vaginal or abdominal trachelectomy and laparoscopic lymphadenectomy has been advocated in carefully selected women with small IB 1 (2 cm or less) lesions who are eager to preserve fertility.
Radiotherapy After Radical Hysterectomy �irradiation decreases the risk of pelvic recurrence in patients whose tumors have high-risk features �it has been difficult to determine the impact of adjuvant irradiation on survival. �adenocarcinomas or adenosquamous carcinomas: post op RT less recurrence
CHRT �Although pelvic irradiation reduces the risk of recurrence for patients with pelvic lymph node metastases or parametrial involvement, the risk of pelvic and distant recurrence remains high for these women �CHRT significantly improved rates of pelvic disease control and survival
�Table 42. 2. 3 Prospective Randomized Trials that Investigated the Role of Concurrent Radiotherapy and Chemotherapy for Patients with Locoregionally Advanced Cervical Cancer �Adj cht?
Radical Radiotherapy �excellent survival and pelvic disease control rates in patients with stage IB cervical cancer. �Survival rates for patients with FIGO stage IIA disease treated with radiation alone range between 70% and 85% and are also strongly correlated with tumor size. � for patients with bulky tumors, results may be improved further with concurrent administration of chemotherapy
Radical radiotherapy �goal of radical radiotherapy =cervix, paracervical tissues, and regional LN � ERT+BT � Even small tumors that involve multiple quadrants of the cervix are usually treated with total doses of 80 to 85 Gy to point A. The dose may be reduced by 5% to 10% for very small superficial tumors. Although patients with small tumors may be treated with somewhat smaller fields than patients with more advanced locoregional disease, care must still be taken to adequately cover the obturator, external iliac, low common iliac, and presacral nodes.
Irradiation Followed by Hysterectomy �low pelvic recurrence rates after concurrent treatment with chemotherapy and radiation, suggest that there is little role for routine treatment with adjuvant hysterectomy.
adjuvant hysterectomy 1. uterine fibroids or other anatomic variations 2. involvement of the uterine fundus In these cases, an extrafascial (type I) hysterectomy is usually performed, in which the uterus, cervix, adjacent tissues, and a small cuff of the upper vagina in a plane outside the pubocervical fascia are removed. This procedure involves minimal disturbance of the bladder and ureters.
Chemotherapy Followed by Radical Surgery? �A number of investigators have investigated the use of neoadjuvant chemotherapy followed by radical hysterectomy to treat patients with bulky stage IB or stage II cervical carcinomas. � Neoadjuvant chemotherapy has usually included cisplatin and bleomycin plus one or two other drugs.
Stage IIB, III, and IVA Disease �With appropriate chemoradiotherapy, even patients with massive locoregional disease have a significant chance for cure. �The success of treatment depends on a careful balance between external-beam radiotherapy and brachytherapy that optimizes the dose to tumor and normal tissues and the overall duration of treatment.
Stage IIB, III, and IVA Disease �EBRT shrinking bulky tumor and bringing it within the range of the high-dose portion of the brachytherapy dose distribution. �Subsequent brachytherapy exploits the inverse square law to deliver a high dose to the cervix and paracervical tissues while minimizing the dose to adjacent normal tissues.
Stage IIB, III, and IVA Disease �complete the entire treatment in less than 7 to 8 weeks. �longer treatment courses are associated with decreased pelvic disease control and survival rates.
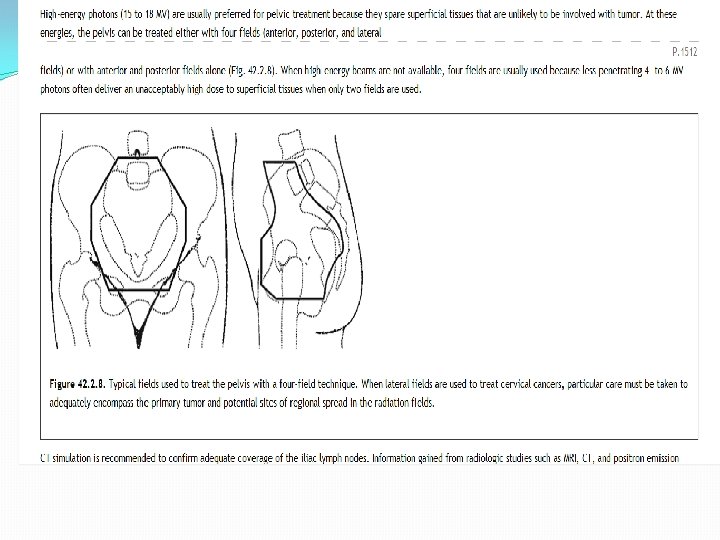
External-Beam Radiotherapy Technique �High-energy photons � 4 - to 6 -MV photons, four fields are usually used
External-Beam Radiotherapy Technique �CT simulation (iliac lymph nodes. ) �Information gained from radiologic studies such as MRI, CT, and PET improve estimates of disease extent and assist in localization of regional nodes and paracervical tissues that may contain microscopic disease. �The caudad extent of disease (radiopaque markers )
organ motion �positions of the uterus and cervix can vary by as much as 4 cm from day to day. �it is usually wise to cover the entire presacrococcygeal region when locally advanced cancers are treated. �some clinicians prefer to use the simpler technique for patients with bulky tumors.
�Tumor response should be evaluated with periodic pelvic examinations to determine the best time to deliver brachytherapy. �a central block after 40 Gy?
Central block �it can result in overdoses to medial structures such as the ureters or underdosage of posterior uterosacral disease. For these reasons, other clinicians prefer to give an initial dose of 40 to 45 Gy to the whole pelvis, believing that the ability to deliver a homogeneous distribution to the entire region at risk for microscopic disease and the additional tumor shrinkage achieved before brachytherapy
�more than 40 to 45 Gy to the central pelvis tend to compromise the dose deliverable to paracentral tissues and increase the risk of late complications.
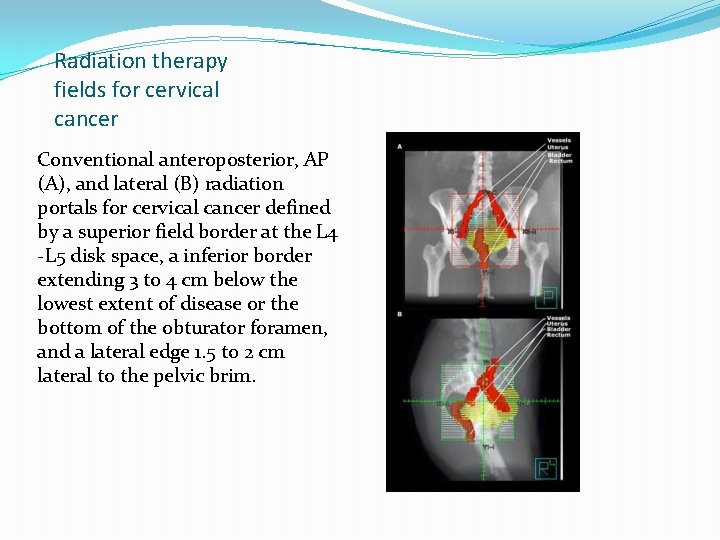
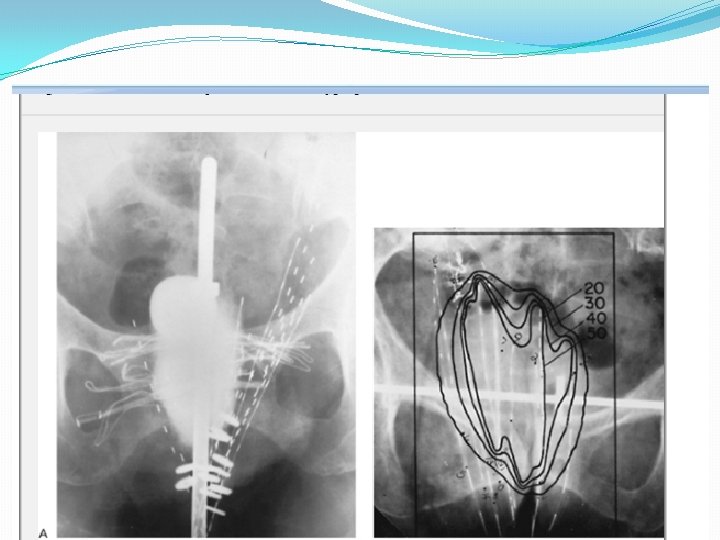
Radiation therapy fields for cervical cancer Conventional anteroposterior, AP (A), and lateral (B) radiation portals for cervical cancer defined by a superior field border at the L 4 -L 5 disk space, a inferior border extending 3 to 4 cm below the lowest extent of disease or the bottom of the obturator foramen, and a lateral edge 1. 5 to 2 cm lateral to the pelvic brim.
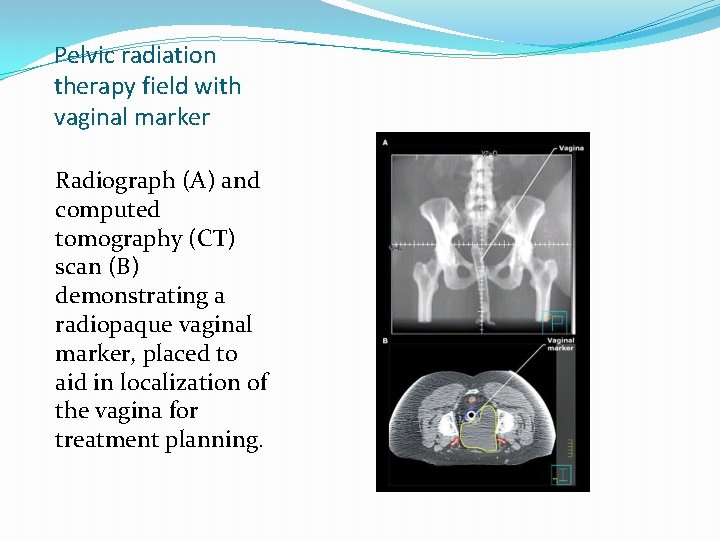
Pelvic radiation therapy field with vaginal marker Radiograph (A) and computed tomography (CT) scan (B) demonstrating a radiopaque vaginal marker, placed to aid in localization of the vagina for treatment planning.
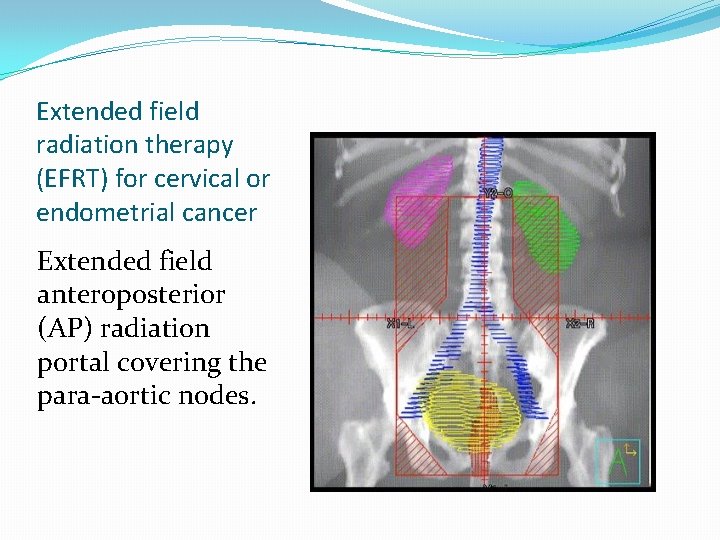
Extended field radiation therapy (EFRT) for cervical or endometrial cancer Extended field anteroposterior (AP) radiation portal covering the para-aortic nodes.
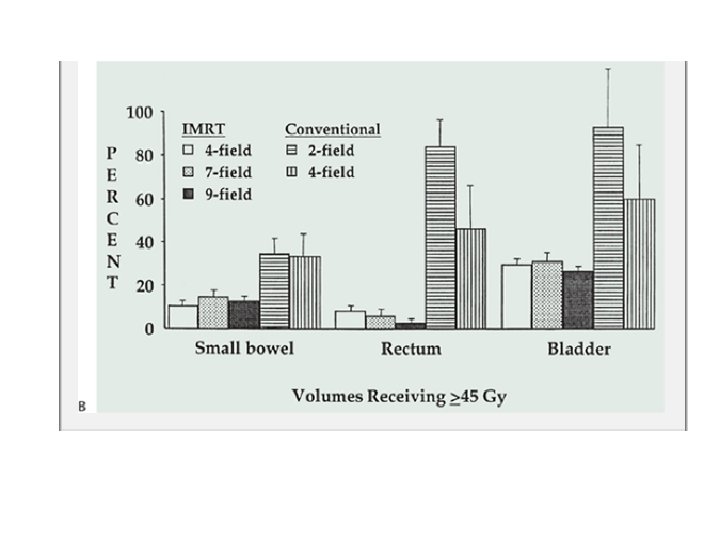
IMRT �Unlike standard two-field and four-field techniques, IMRT makes it possible to deliver a lower daily dose to the intrapelvic contents than to surrounding pelvic lymph nodes. �reduced bone marrow toxicity and acute gastrointestinal side
IMRT �IMRT is less sparing of bowel. �IMRT allows delivery of doses exceeding 60 Gy with relative sparing of adjacent critical structures. � increase error �influence of internal organ motion and intratreatment tumor response on the doses to tumor and critical structures.
�There is no evidence that IMRT can safely be used as an alternative to brachytherapy for routine treatment of intact cervical cancer. �IMRT cannot accurately reproduce the high-dose gradients produced with intracavitary therapy. �unpredictable variations mandate the use of large treatment margins
Role of Para-Aortic Irradiation �para-aortic node involvement : 25% to 50% enjoy long-term survival after extended-field irradiation. �even 10% to 15% of patients with gross lymphadenopathy appear to be curable with aggressive management. � Survival is also strongly correlated with the bulk of central disease. �patients who had small primary disease that could be controlled with radiotherapy demonstrates that extensive regional spread can occur without distant metastases and that patients with para-aortic node metastases can often be cured if their primary disease can be sterilized.
�occult disease can be cured if the para-aortic nodes are included in the radiation fields �concurrent chemotherapy ? �PET and minimally invasive surgery add to the expense of treatment and are still infrequently performed in patients with locally advanced cervical cancer, these methods may provide better means of identifying patients with regional metastases who can benefit from extended regional irradiation
Radiation Therapy Techniques(Preze) �External irradiation is used to treat the whole pelvis and the parametria including the common iliac and para-aortic lymph nodes �central disease (cervix, vagina, and medial parametria) is primarily irradiated with intracavitary sources.
External-beam pelvic irradiation is delivered before intracavitary insertions in patients with: �Bulky cervical lesions or tumors beyond stage IIA to improve the geometry of the intracavitary application �Exophytic, easily bleeding tumors; �Tumors with necrosis or infection �Parametrial involvement.
high-risk features need ERT �parametrial involvement, deep stromal invasion, or positive nodes, positive or close operative margins,
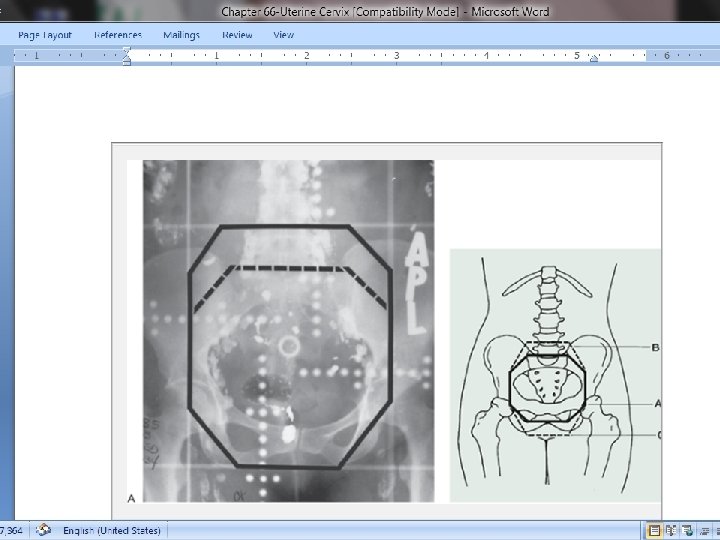
Volume Treated �the primary tumor and the pelvic lymph nodes �superior border at the L 4 -5 (external iliac and hypogastric lymph node) �inferior border at the inferior edge of the ischium �This margin must be extended to the L 3 -4 interspace if common iliac nodal coverage is indicated. � 1. 5 -cm -2. 5 cm margin on the pelvic rim; �Posterior extension of the cardinal ligaments in their attachment to the pelvic side wall was consistently posterior to the rectum and extended to the sacral hollow. The uterosacral ligaments also extended posteriorly to the sacrum. These anatomic landmarks must be kept in mind in the correct design of lateral pelvic portals.
�A: Ap simulation film. The 15 by 15 cm portals at SSD are used for stage IB (broken line), and 18 by 15 cm portals are used for more advanced disease (solid line). This allows better coverage of the common iliac lymph nodes. The distal margin is usually placed at the bottom of the obturator foramina. B: Standard portal for stage IB tumors is outlined (solid line indicated as A). When the common iliac nodes are to be covered, the upper margin is extended to the L 4 -5 space? (indicated in section B). If there is vaginal tumor extension, the lower margin of the field is drawn at the introitus (indicated in section C).
lateral field �the anterior border of the lateral fields over the anterior edge of the pubic symphysis �the posterior margin usually is designed to cover at least 50% of the rectum in stage IB tumors, and it should extend to the sacral hollow in patients with more advanced tumors �Three-dimensional treatment planning for pelvic irradiation of cervical carcinoma may reduce the treated volume, but further research must be done to determine whether the complication rate can be decreased as well.
�For stage IB disease, : 15 by 15 cm at the surface ( �For patients with stage IIA, IIB, III, and IVA carcinoma, (18 by 15 cm at surface) are required to cover all of the common iliac nodes in addition to the cephalad half of the vagina �If there is no vaginal extension, the lower margin of the portal is at the inferior border of the obturator foramen. �When there is vaginal involvement, the entire length of this organ should be treated down to the introitus
�In patients with tumor involving the distal half of the vagina, the portals should be modified to cover the inguinal lymph nodes because of the increased probability of metastases
Midline Shielding in Ap–PA Portals �Depending on the institution and brachytherapy dose administered, midline shielding with rectangular or specially designed blocks are used for a portion of the external beam dose delivered with the Ap–PA ports
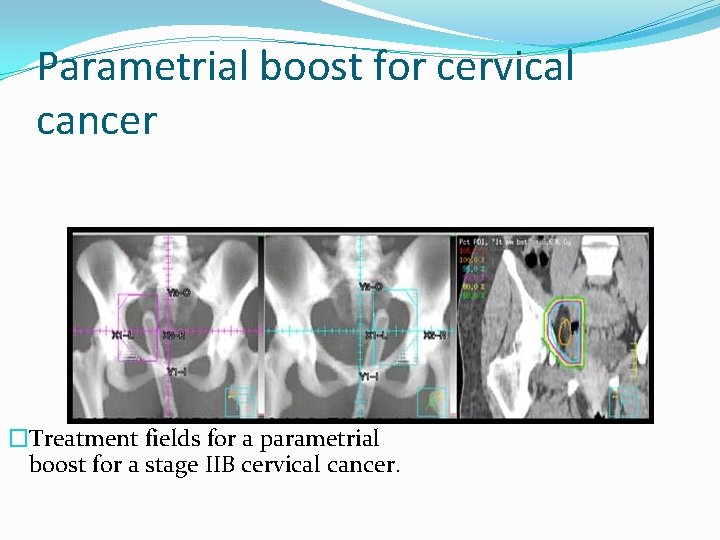
Parametrial Boost �When parametrial tumor persists after 50 to 60 Gy is delivered to the parametria, an additional 10 Gy in five or six fractions may be delivered with reduced AP-PA portals (8 by 12 cm for unilateral and 12 by 12 cm portals for bilateral parametrial coverage). The central shield should be in place to protect the bladder and rectum.
Parametrial boost for cervical cancer �Treatment fields for a parametrial boost for a stage IIB cervical cancer.
Para-Aortic Lymph Node Irradiation �an extended field or through a separate portal � 45 to 50 Gy to the para-aortic area plus a 5 to 10 Gy boost to enlarged lymph nodes
separate portal �a “gap calculation( excessive dose to the small intestines) � The upper margin = T 12 -L 1 �lower margin at L 5 -S 1 � The width of the para-aortic portals can be determined by CT scans, MRI, lymphangiography, FDG-PET scans, or IV pyelography outlining the ureters.
�The spinal cord dose (T 12 to L 2 -3) should be kept below 45 Gy by interposing a 2 -cm wide 5–half-value layer (HVL) shield on the posterior portal (usually after 40 -Gy tumor dose) or using lateral ports and the kidneys below 1, 800 c. Gy
Beam Energies � 10 MV or higher �They decrease the dose of radiation delivered to the peripheral normal tissues (particularly bladder and rectum) and provide a more homogeneous dose distribution in the central pelvis. � With lower-energy photons (Cobalt-60 or 4 - to 6 -MV x-rays), higher maximum doses must be given, and more complicated field arrangements should be used to achieve the same midplane tumor dose (3 or 4 field pelvic box or rotational techniques) while minimizing the dose to the bladder and rectum and to avoid subcutaneous fibrosis
�a metallic prosthesis when using lateral fields or a box pelvic irradiation technique may result in a dose decrease of approximately 2% for 25 -MV x-rays and average increases of 2% for 10 -MV x-rays and 5% for 60 Co.
Hyperfractionated Radiation Therapy for Locally Advanced Cervix Cancer 1. 2 Gy to the whole pelvis twice daily at 4 - to 6 -hour intervals, 5 days per weeka total pelvic dose of 57. 5 Gy. A boost dose with brachytherapy
Concomitant Boost �On Monday, Wednesday, and Friday of the last 3 weeks, an additional 1. 6 -Gy boost was given 6 hours after the whole pelvis treatment (14. 4 Gy) through lateral fields encompassing the parametria and primary tumor, for a total tumor dose of 59. 4 Gy.
Three-Dimensional or IMRT �patients with stage IIB or IVA cervical cancer with medical illness or severe tumor-related anatomic distortion that limited delivery of brachytherapy. � The toxicity of IMRT was acceptable, and early tumor responses were encouraging.
IMRT �Although not as critical in older patients, it is important to keep in mind that while IMRT has dosimetric advantages over conventional RT, IMRT exposes a greater amount of normal tissues to lower irradiation levels, which has the potential to increase the incidence of radiation-induced second cancers.
Brachytherapy Ø intracavitary techniques � (137 Cs) � (192 Ir)
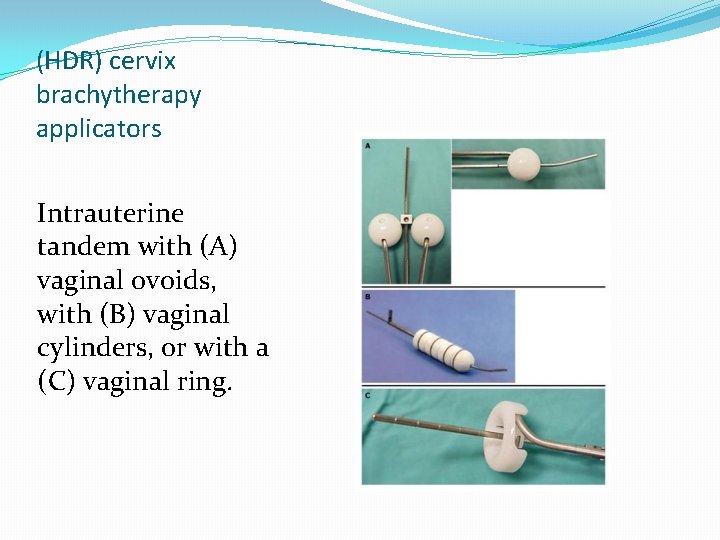
Remote afterloader for(HDR) brachytherapy A remote afterloader stores a single (HDR) radioactive source, typically Ir-192, and through a computer controlled mechanism advances it within the catheter or applicator that has been placed in the patient.
(HDR) cervix brachytherapy applicators Intrauterine tandem with (A) vaginal ovoids, with (B) vaginal cylinders, or with a (C) vaginal ring.
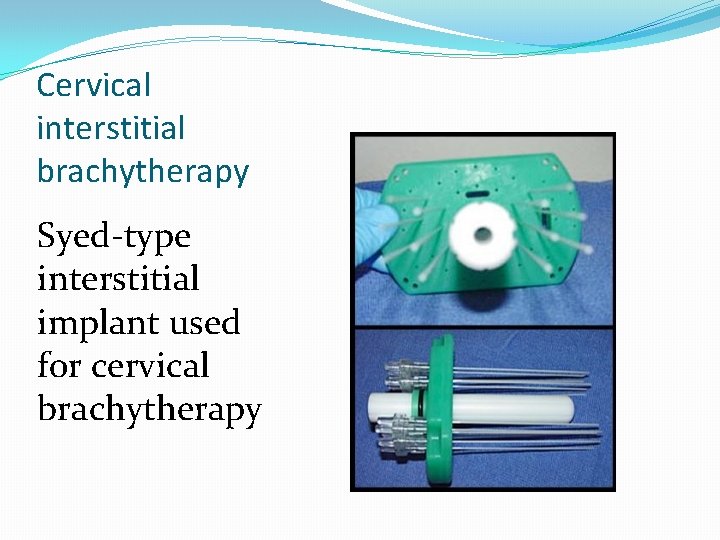
Cervical interstitial brachytherapy Syed-type interstitial implant used for cervical brachytherapy
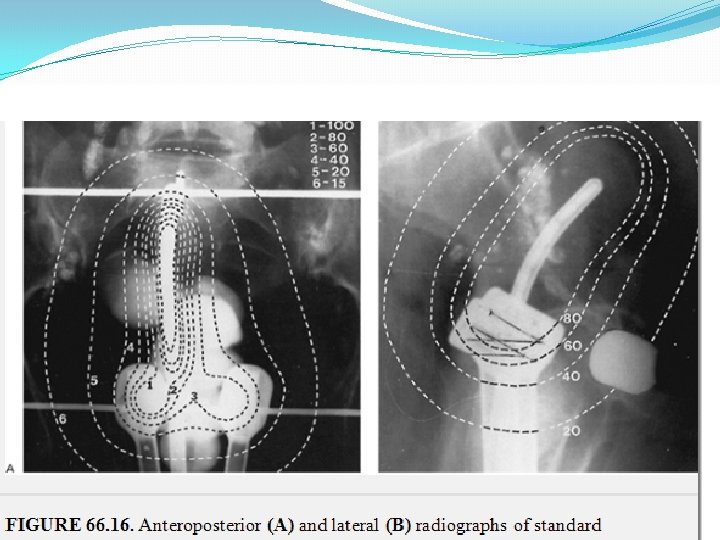
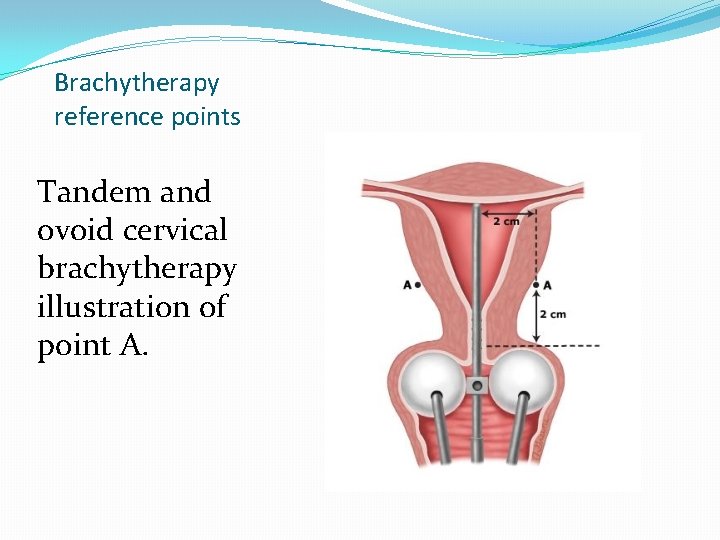
Brachytherapy reference points Tandem and ovoid cervical brachytherapy illustration of point A.
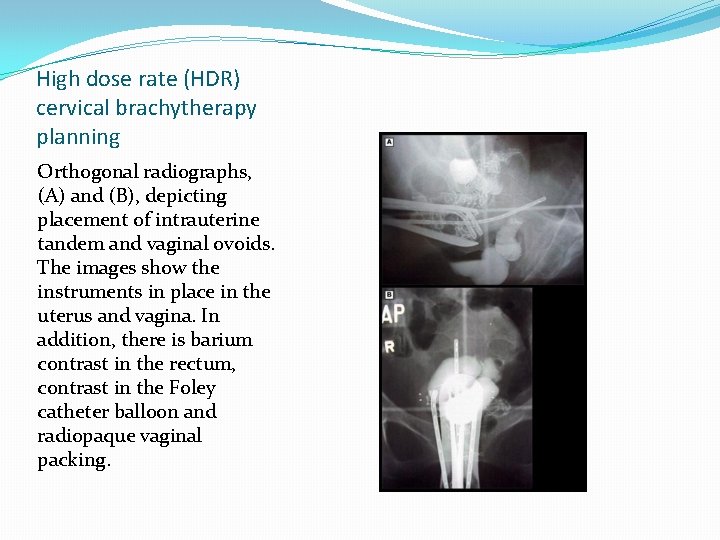
High dose rate (HDR) cervical brachytherapy planning Orthogonal radiographs, (A) and (B), depicting placement of intrauterine tandem and vaginal ovoids. The images show the instruments in place in the uterus and vagina. In addition, there is barium contrast in the rectum, contrast in the Foley catheter balloon and radiopaque vaginal packing.
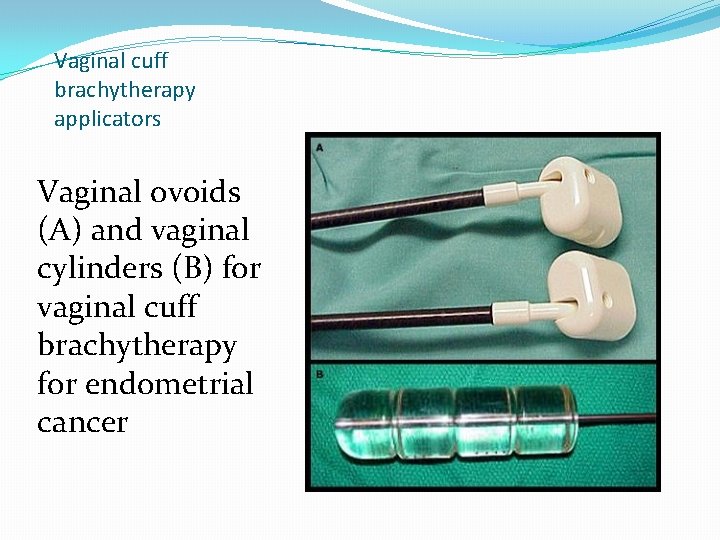
Vaginal cuff brachytherapy applicators Vaginal ovoids (A) and vaginal cylinders (B) for vaginal cuff brachytherapy for endometrial cancer
For LDR treatments: �EBRT dose : 45 to 50 Gy �LDR brachytherapy dose : 42 and 45 Gy for early and advanced cancers For HDR treatments �EBRT dose : 48 to 50 Gy �HDR dose : 29 and 30 Gy for early and advanced cancers. �The median HDR dose per fraction was 6 Gy with a median of five fractions.
�computer-generated dose distributions provide the best means of determining the doses to point A, point B, bladder, and rectum �In general, an intrauterine tandem with three or four sources [15 or 20 -10 -10 -(10) m. Ci mg. Ra. Eq with LDR] is inserted in the uterus and two colpostats (2 cm in diameter, loaded with 20 m. Ci mg. Ra. Eq LDR sources) are placed in the vaginal vault and packed with iodoform gauze to deliver 0. 6 to 0. 8 Gy per hour to point A.
�With HDR intracavitary applicators the use of a rectal retractor has been shown to substantially reduce the rectal dose �Interstitial implants with radium (226 Ra), 137 Cs needles, or 192 Ir afterloading plastic catheters to limited tumor volumes are helpful in specific clinical situations (e. g. , localized residual tumor, parametrial extension.
�As Fletcher emphasized, conditions for an adequate intracavitary insertion include the following 1. The geometry of the insertion must prevent underdosing around the cervix; 2. Sufficient dose must be delivered to the paracervical areas 3. Vaginal mucosal (and, we add, bladder and rectal) tolerance doses must be respected.
Biology of High–Dose-Rate Brachytherapy for Cervical Carcinoma �Late damage rises sharply as the number of HDR fractions is decreased. �Displacing the bladder and rectum away from the HDR sources for the short duration of therapy may offset the radiobiologic disadvantage of using a few brachytherapy fractions
At Washington University �HDR brachytherapy with sedation and without anesthesia. �bladder catheter and gentle packing of the vagina with iodoform gauze �anteroposterior and lateral pelvic radiographs �The usual dose per fraction prescribed at 0. 5 -cm depth is 3 to 6 Gy, and three to six fractions are given once or twice weekly
HDR �four fractions of EBRT per week with one HDR treatment per week �The number of HDR fractions : two to more than 10. �The optimal time–dose–fractionation ?
�In vivo bladder and rectal dosimetry is performed during the HDR procedure �Other centers obtain normal tissue doses from points located on dosimetry films and dose distribution curves
�Treatment planning for HDR brachytherapy can be accomplished by a variety of techniques: 1. use of an atlas of applications and source loadings, to planning of only the initial insertion followed by replicating the insertion for subsequent treatments 2. customized optimization of source loading for each HDR insertion 3. Computer treatment planning and a reconstruction system used to achieve individual dosimetry.
Three-Dimensional Brachytherapy Treatment Planning �The advantages of in vivo dosimetry are easy practicability and the possibility to determine rectal dose during radiation. �The advantages of computer-aided planning at ICRU reference points are that calculations are available before radiation and they can be taken into account for treatment planning.
�The CT-based planning provides information on target and organ volumes and dose–volume histograms. �The radiography-based planning provides dimensions and doses only at selected points.
HDR �Each institution should follow a consistent treatment policy, including complete documentation of treatment parameters and correlation with clinical outcome (pelvic tumor control, survival, and complications).
�They predicted that, using therapeutic gain ratio, similar results would be obtained with either brachytherapy modality with two to four fractions of LDR and four to seven fractions of HDR.
The American Brachytherapy Society published recommendations for HDR brachytherapy for carcinoma of the cervix point A to at least a total LDR equivalent of 80 to 85 Gy for early stage disease and 85 to 90 Gy for advanced-stage disease. 2. The pelvic sidewall : 50 to 55 Gy for early lesions and 55 to 65 Gy for advanced ones. 3. As with LDR BT, every attempt should be made to keep the bladder and rectal doses below 80 Gy and 75 Gy LDR-equivalent doses, respectively. 1.
4. Interstitial brachytherapy should be considered when the tumor cannot be optimally encompassed by intracavitary brachytherapy. 5. It was emphasized that the responsibility for the medical decisions ultimately rests with the treating radiation oncologist.
Doses of Radiation �Stage IA (microinvasive) tumors are treated with intracavitary therapy only (LDR 60 Gy in one insertion or 75 to 80 Gy in two insertions to point A, or HDR 35 to 42 Gy in five to six insertions of 7 Gy to point A, one or two fractions per week). �The optimal dose for invasive carcinoma of the cervix is delivered with a combination of EBRT whole pelvis, intracavitary, and, at times, interstitial therapy.
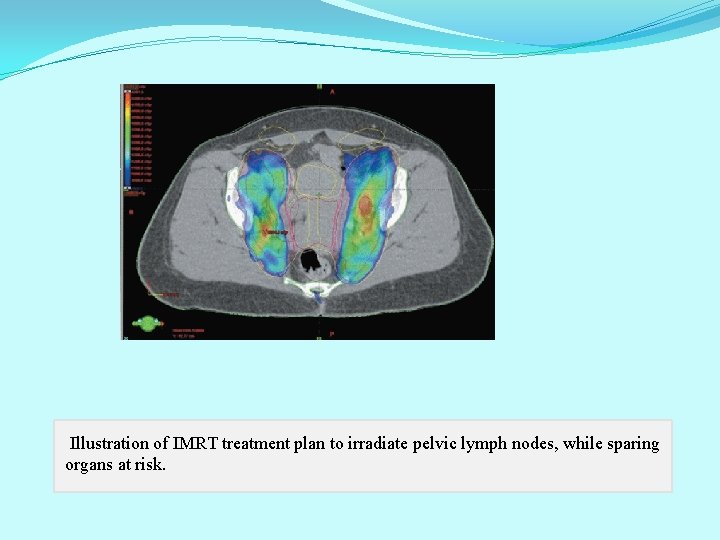
Illustration of IMRT treatment plan to irradiate pelvic lymph nodes, while sparing organs at risk.
Brachytherapy D �Fletcher described three conditions that should be met for successful cervical brachytherapy: � (1) the geometry of the radioactive sources must prevent underdosed regions on and around the cervix � (2) an adequate dose must be delivered to the paracervical areas �(3) mucosal tolerance must be respected.
verify accurate placement �Radiographs should be obtained at the time of insertion to verify accurate placement, and the system should be repositioned if positioning can be improved.
Brachytherapy Dose �Paracentral doses are most frequently expressed at a single point, usually designated Point A. This reference point has been calculated in a number of different ways.
The most accepted definition of Point A is a point 2 cm lateral to the cervical collar and 2 cm above the top of the colpostats, measured at their intersection with the tandem midpoint on the lateral radiograph 2. an alternative definition places Point A 2 cm lateral and vertical to the external cervical os. These definitions can produce quite different dose estimates. Point A usually lies approximately at the crossing of the ureter and the uterine artery, but it bears no consistent relationship to the tumor or target volume. 1.
Optimized source placement can rarely correct for a poorly positioned applicator.
�an effort should always be made to deliver at least 85 Gy (with LDR brachytherapy) to Point A for patients with bulky central disease. �without exceeding a dose of 75 Gy to the bladder reference point or 70 Gy to the rectal reference point, �The dose to the surface of the lateral wall of the apical vagina should not usually exceed 120 to 140 Gy.
�A total dose (external-beam and intracavitary) of 50 to 55 Gy appears to be sufficient to sterilize microscopic disease in the pelvic nodes in most patients. �Gross disease : a total dose of 60 to 65 Gy (including the contribution from brachytherapy treatments).
Concurrent Chemoradiation �addition of concurrent cisplatin-containing chemotherapy to standard radiotherapy reduces the risk of disease recurrence by as much as 50%, thereby improving the rates of pelvic disease control and survival �stage IIB-IVA disease
RT , CHRT �highly significant differences were detected in the rates of local control, distant metastasis, overall survival, and disease-free survival favoring the treatment arm that included chemotherapy.
�All of the studies explicitly excluded patients with evidence of para-aortic lymph node metastases, poor performance status, or impaired renal function. . ﻣﻘﺎیﺴﻪ ﻧﺸﺪﻩ ﺍﺳﺖ CHRT ﻭ RT ﺩﺭ ﺍیﻦ ﺳﻪ ﻣﻮﺭﺩ ﺑیﻦ
radiosensitizing effects �cisplatin �epirubicin �mitomycin � 5 -FU are being studied : �Paclitaxel �carboplatin, �and several biologic response modifiers
Chemotherapy: Stage IVB Disease 1. Single-Agent Chemotherapy 2. Combination Chemotherapy
Single-Agent Chemotherapy �Cisplatin �Ifosfamide �, carboplatin, � irinotecan �, paclitaxel response rates of 10% to 20%
Combination Chemotherapy �combination chemotherapy can improve both progression-free survival (cisplatin plus paclitaxel vs. single-agent cisplatin, cisplatin plus topotecan vs. single-agent cisplatin) and overall survival (cisplatin plus topotecan) when it is administered as treatment for recurrent or metastatic carcinoma of the cervix.
Palliative Radiotherapy �Localized radiotherapy can provide effective relief of pain caused by metastases in bone, brain, lymph nodes, or other sites. A rapid course of pelvic radiotherapy can also provide excellent relief of pain and bleeding for patients who present with incurable disseminated disease
Special Treatment Problems �Locally Recurrent : if, in irradiated patients, the cervix remains bulky or nodular or cervical cytologic findings are abnormal 3 months or more after RT ; or if symptoms of leg edema, pain, or bleeding develop after initial treatment. �The diagnosis must be confirmed with a tissue biopsy, and the extent of disease should be evaluated with appropriate radiographic studies, cystoscopy, proctoscopy, and serum chemistry studies before treatment is administered.
Treatment of Locally Recurrent Carcinoma of the Cervix After Radical Surgery �aggressive radiotherapy.
�TX for patients with an isolated vaginal recurrence is similar to that for patients with a primary carcinoma of the vagina. � Most patients are treated with external-beam radiotherapy with or without brachytherapy. Implants may need to be inserted under laparoscopic or laparotomy guidance.
After Radical Surgery �TX Pelvic wall recurrences are often treated with external-beam irradiation alone, although surgery and intraoperative therapy may contribute to local control in selected patients. �Reported survival rates usually range between 20% and 40% for patients treated with radical radiotherapy. 2
After Definitive Irradiation �an isolated central recurrence can be cured with surgical treatment. � Less extensive operations, such as radical hysterectomy or anterior exenteration, are reserved for selected patients with small tumors confined to the cervix or lesions that do not encroach on the rectum, respectively.
After Definitive Irradiation contraindication for pelvic exenteration 1. involvement of the pelvic sidewall 2. The triad of unilateral leg edema, sciatic pain, and ureteral obstruction 3. advanced age
quality of patients' lives after surgical salvage �At all points of evaluation, the patients' quality of life was most affected by worries about the progression of the tumor. �Ostomies �vaginal reconstruction �urostomy or colostomy. �Vaginal dryness and vaginal discharge
Unresectable disease �Intraoperative irradiation ( involves the pelvic wall) �chemotherapy alone (previously discussed); response rates and prognosis are generally poor.
Treatment After Simple Hysterectomy that Reveals Unsuspected Invasive Cancer �invasion of less than 3 mm without LVSI usually require no treatment after simple hysterectomy. �more extensive disease : with postoperative radiotherapy or, in selected cases, with radical parametrectomy and lymphadenectomy.
�posthysterectomy treatment (1) microinvasive cancer, (2) tumor confined to the cervix with negative surgical margins, (3) positive surgical margins but no gross residual tumor, (4) gross residual tumor by clinical examination documented by biopsy (5) patients referred for treatment more than 6 months after hysterectomy (usually for recurrent disease).
posthysterectomy treatment �more extensive involvement who have negative margins are treated with 45 to 50 Gy of pelvic radiotherapy to treat the pelvic nodes and paracolpal tissues. Most clinicians follow this with vaginal intracavitary therapy, delivering an additional vaginal surface dose of 30 to 50 Gy. ERT+BT �positive margins : higher dose of ERTthrough reduced fields designed to include the region at highest risk (e. g. , parametria and posterior bladder wall). �RT+CHT should probably be considered for patients with group 3 or 4 disease(M+)
Carcinoma of the Cervical Stump �The natural history, staging, and workup of cervical stump carcinomas are the same as for carcinomas of the intact uterus
Carcinoma of the Cervical Stump 1. stage IA 1: simple trachelectomy 2. selected patients with stage IA 2 or small stage IB tumors : radical trachelectomy and pelvic lymph node dissection 3. most patients with irradiation alone using a combination of ERT+ BT.
Carcinoma of the Cervical Stump �endocervical canal is 2 cm or longer, and after ERT, patients can be adequately treated with intracavitary therapy. � If the endocervical cannot accommodate any sources, aboost dose may be delivered to the tumor with interstitial therapy or transvaginal irradiation. �Vaginal ovoids alone rarely deliver an adequate dose to the cervix.
� When brachytherapy is used, most investigators have reported survival rates similar to those for patients with carcinomas of the intact cervix.
Carcinoma of the Cervix During Pregnancy �Delayed in Diagnosis �a careful pelvic examination and Pap smear at their first antenatal visit � Any suspicious lesion should be biopsied �A diagnostic conization may be necessary.
delay definitive treatment 1. Carcinoma in situ or stage IA disease 2. whose disease invades less than 3 mm and no LVSI A vaginal hysterectomy 6 weeks after childbirth 3. Patients whose disease invades 3 to 5 mm and those with LVSI may also be followed to term
�IB 1 : classic cesarean section followed by radical hysterectomy with pelvic lymph node dissection �stage II-IV , bulky stage IB : radiotherapy.