Venous Access Matthew L Paden MD Emory University


















- Slides: 90
Venous Access Matthew L. Paden, MD Emory University Children’s Healthcare of Atlanta at Egleston
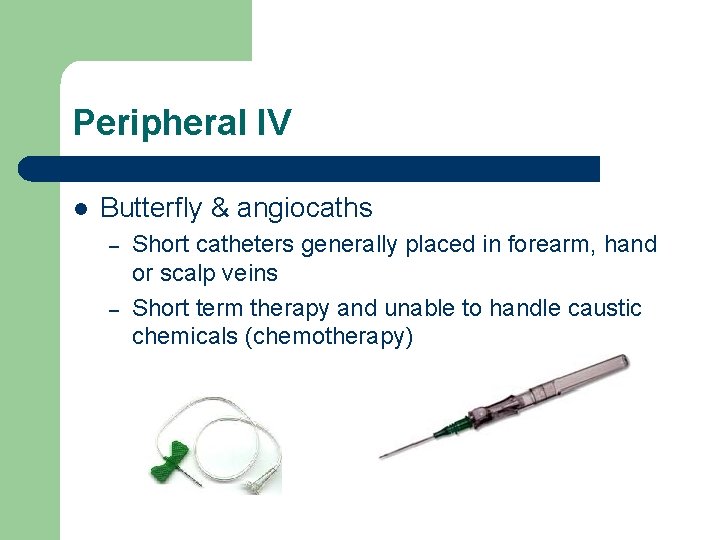
Peripheral IV l Butterfly & angiocaths – – Short catheters generally placed in forearm, hand or scalp veins Short term therapy and unable to handle caustic chemicals (chemotherapy)
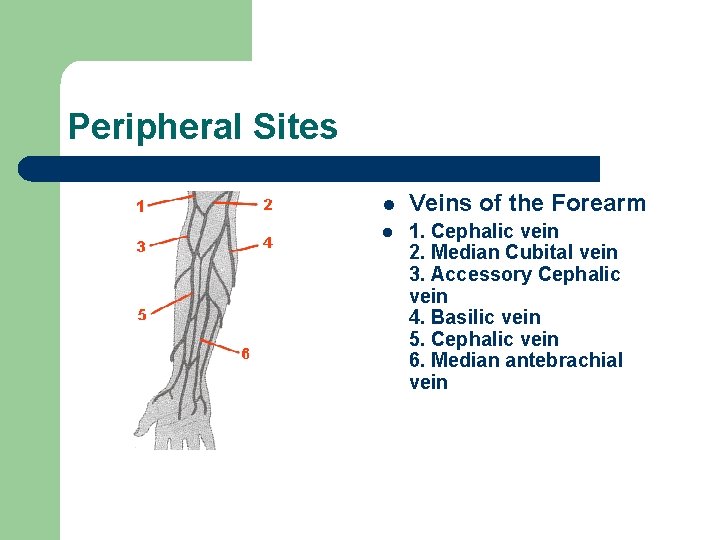
Peripheral Sites l Veins of the Forearm l 1. Cephalic vein 2. Median Cubital vein 3. Accessory Cephalic vein 4. Basilic vein 5. Cephalic vein 6. Median antebrachial vein
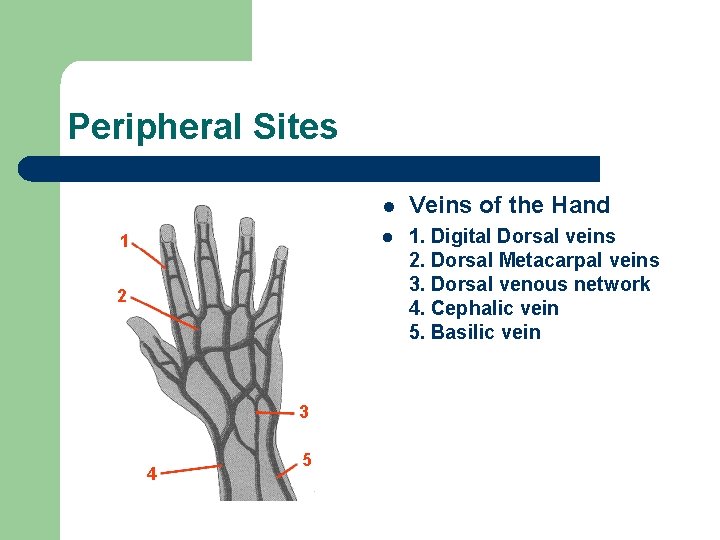
Peripheral Sites l Veins of the Hand l 1. Digital Dorsal veins 2. Dorsal Metacarpal veins 3. Dorsal venous network 4. Cephalic vein 5. Basilic vein
Peripheral IVs l Try to cannulate the most distal veins first – l l Drugs or fluids put through the cannula may extravasate at the upstream failed cannula site Transillumination Topical nitropaste
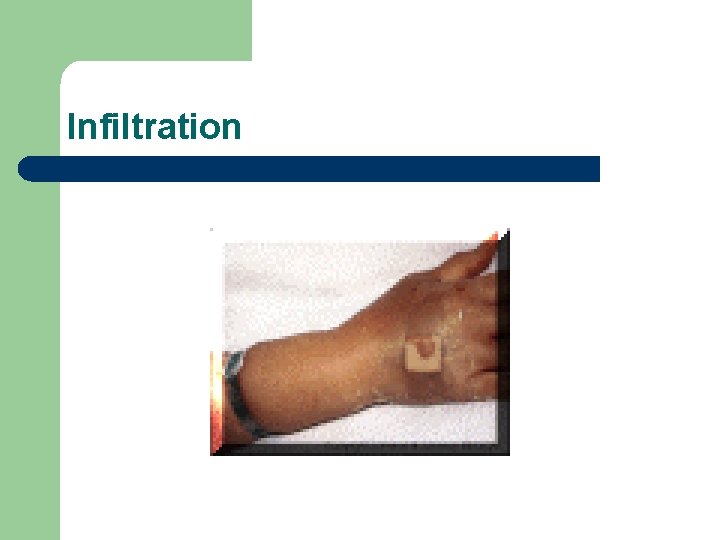
Infiltration
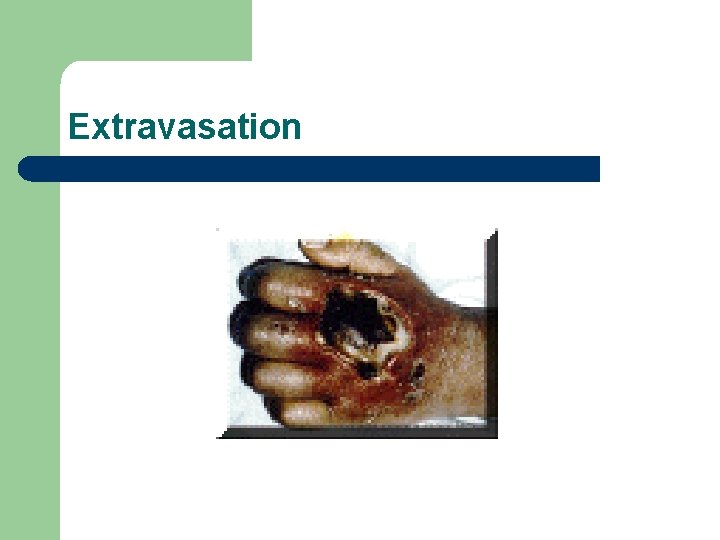
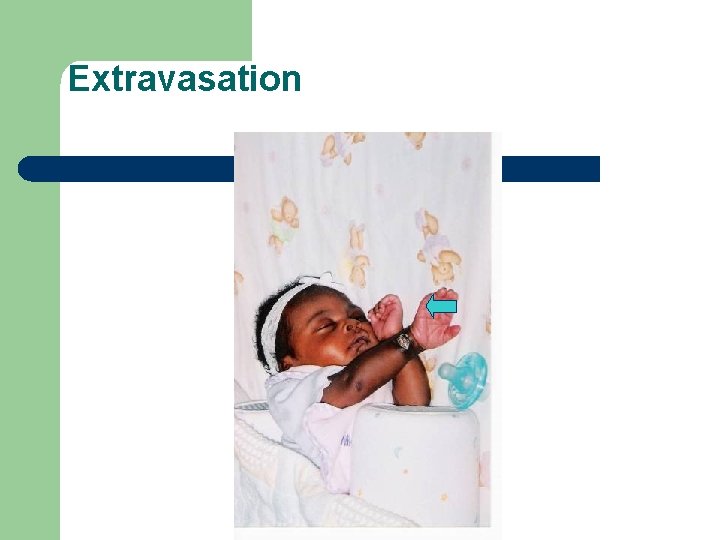
Extravasation
Extravasation
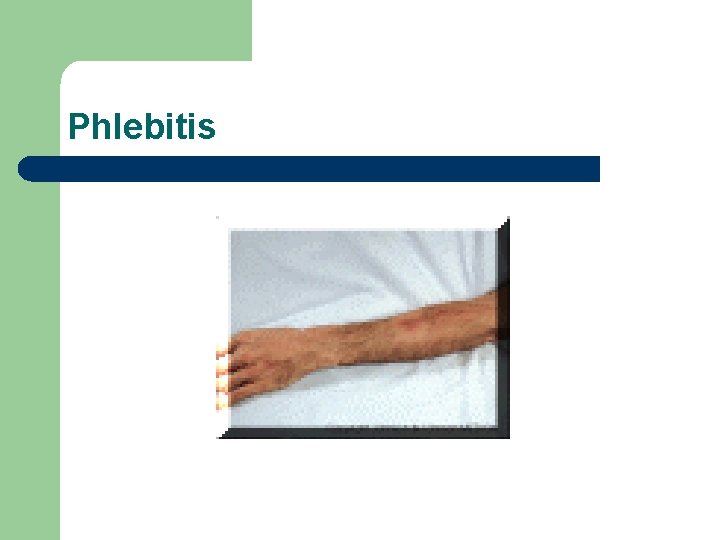
Phlebitis
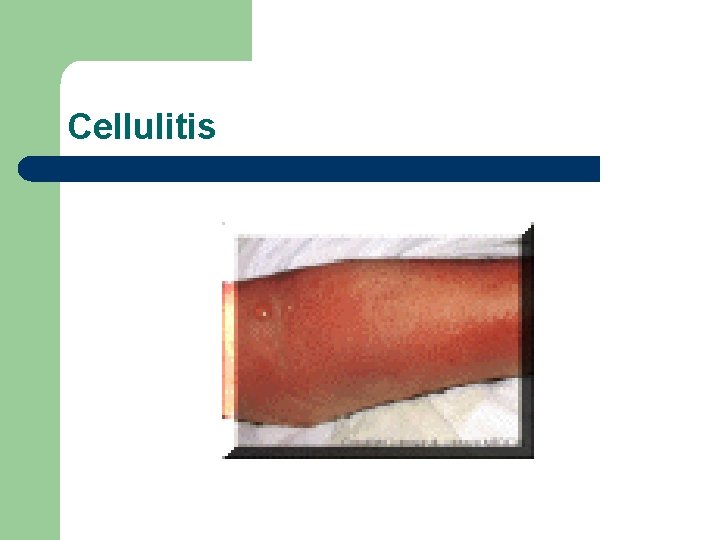
Cellulitis
Types of Central Vascular Access Devices l l l Non-tunneling Tunneling Implanted
Non-Tunneling l Direct venipuncture through the skin into a selected vein. – – – Peripheral IV Peripherally inserted central catheter Percutaneous catheters
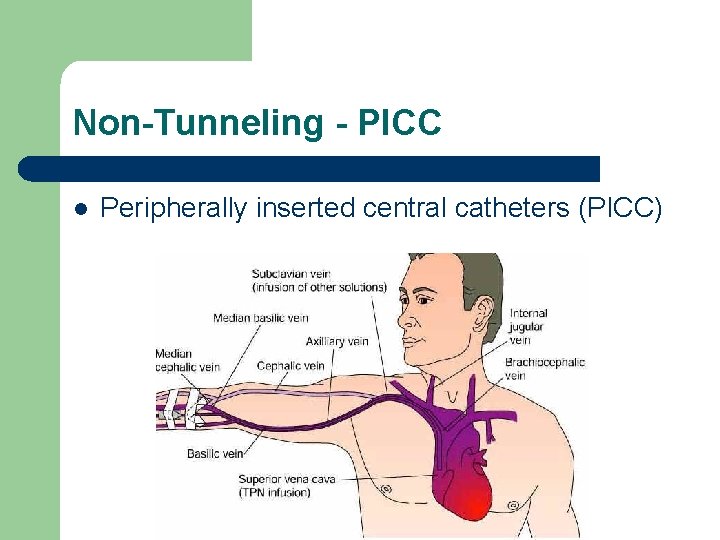
Non-Tunneling - PICC l Peripherally inserted central catheters (PICC) – l Midline Central venous catheter inserted at or above the antecubital space and then advanced until the distal tip of the catheter is positioned at the superior vena cava or superior vena cava and right atrial junction.
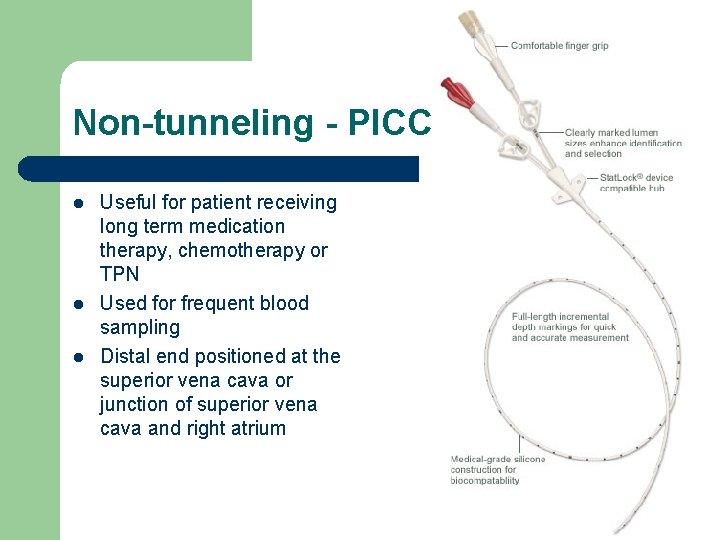
Non-tunneling - PICC l l l Useful for patient receiving long term medication therapy, chemotherapy or TPN Used for frequent blood sampling Distal end positioned at the superior vena cava or junction of superior vena cava and right atrium
Non-Tunneling - PICC l Peripherally inserted central catheters (PICC)
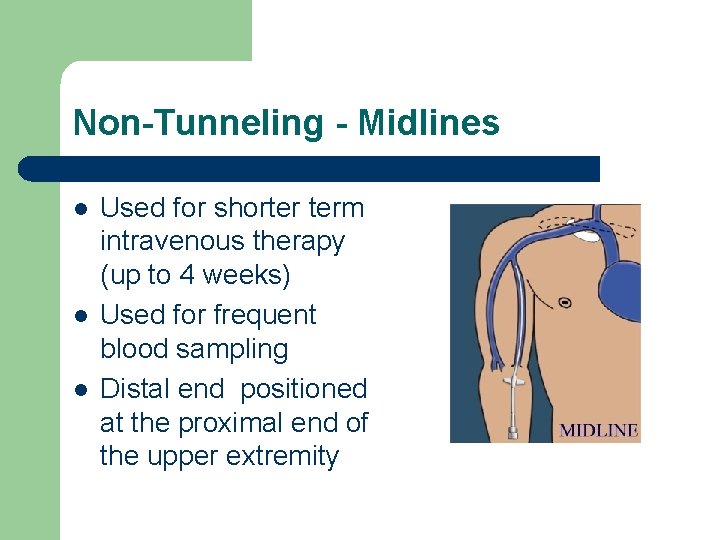
Non-Tunneling - Midlines l l l Used for shorter term intravenous therapy (up to 4 weeks) Used for frequent blood sampling Distal end positioned at the proximal end of the upper extremity
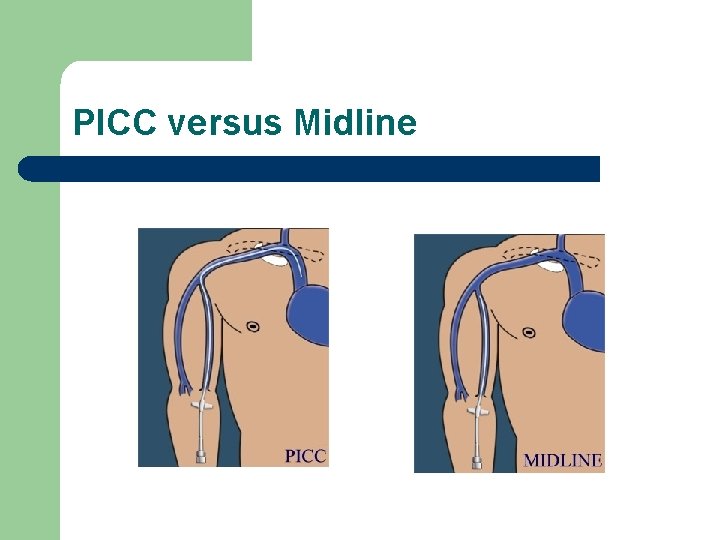
PICC versus Midline
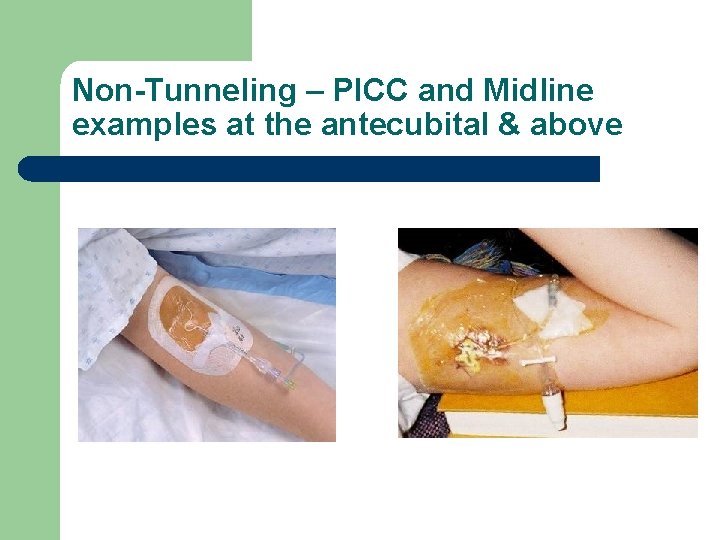
Non-Tunneling – PICC and Midline examples at the antecubital & above
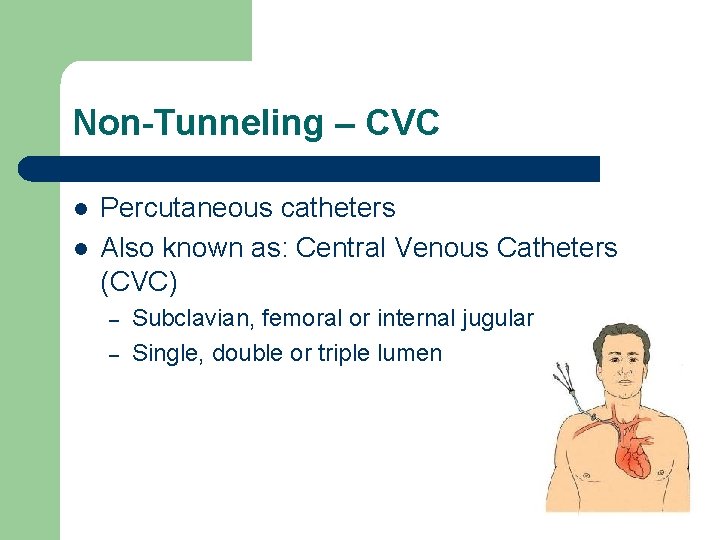
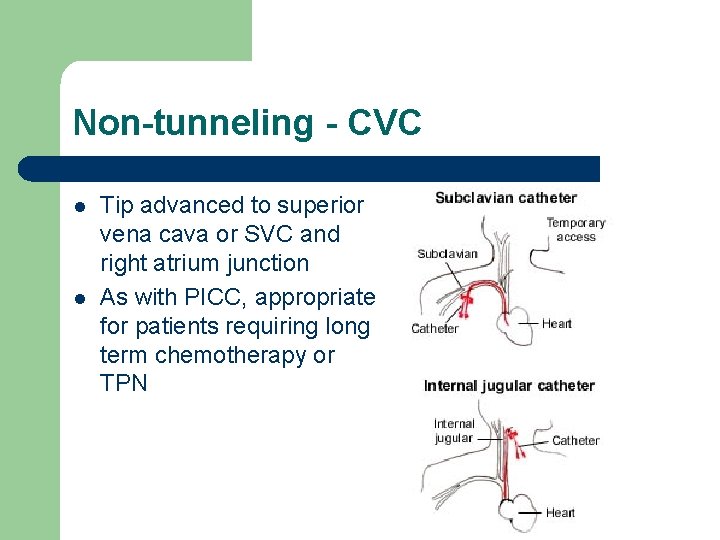
Non-Tunneling – CVC l l Percutaneous catheters Also known as: Central Venous Catheters (CVC) – – Subclavian, femoral or internal jugular Single, double or triple lumen
Non-tunneling - CVC l l Tip advanced to superior vena cava or SVC and right atrium junction As with PICC, appropriate for patients requiring long term chemotherapy or TPN
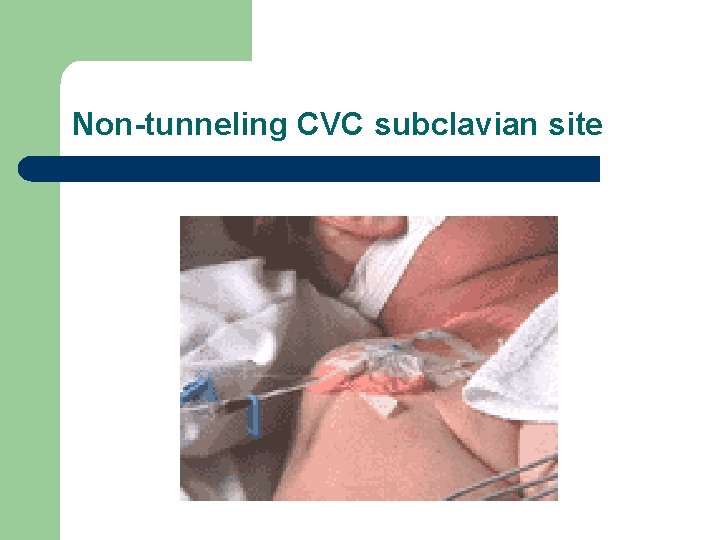
Non-tunneling CVC subclavian site
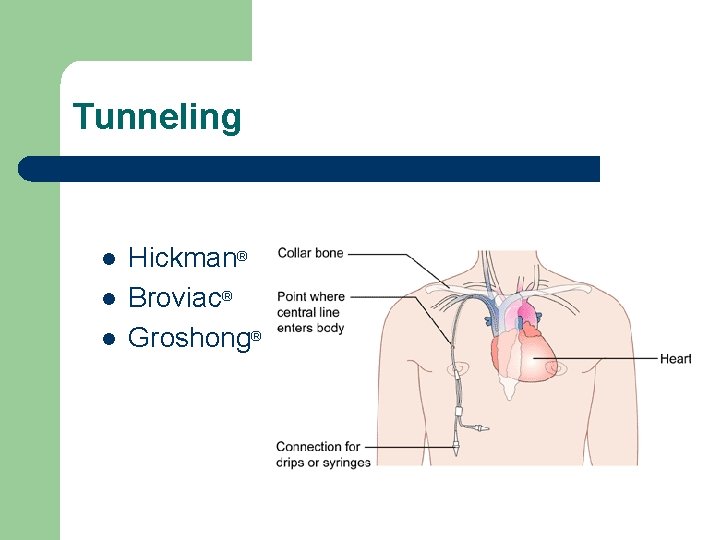
Tunneling l l l Hickman® Broviac® Groshong®
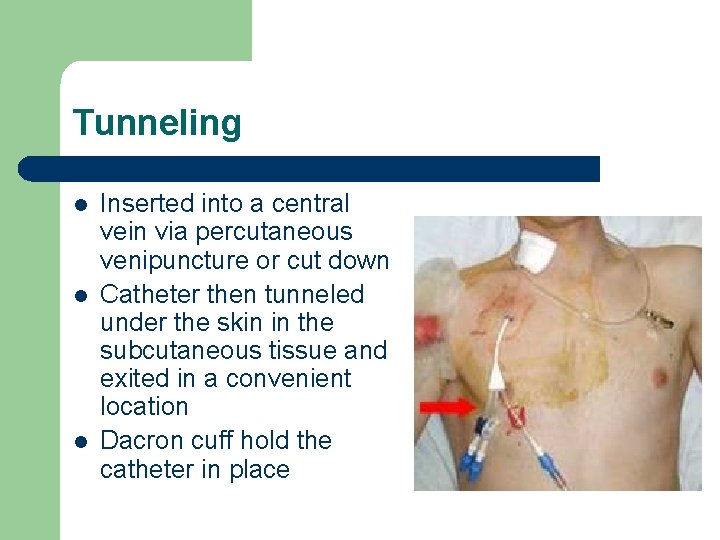
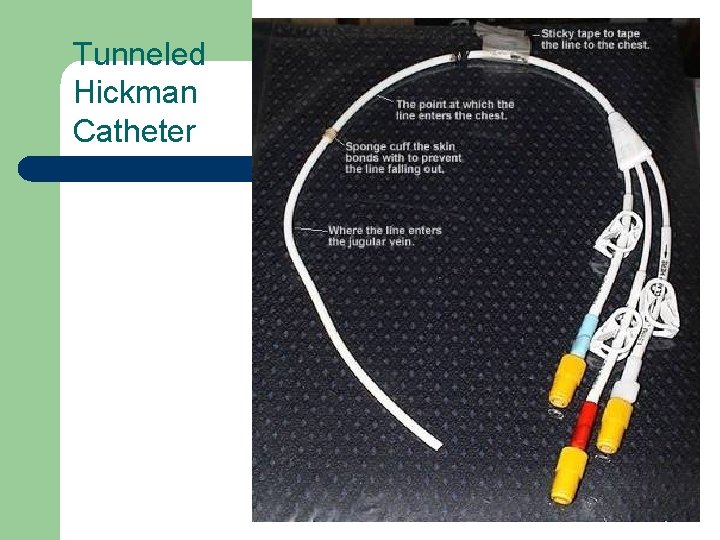
Tunneling l l l Inserted into a central vein via percutaneous venipuncture or cut down Catheter then tunneled under the skin in the subcutaneous tissue and exited in a convenient location Dacron cuff hold the catheter in place
Tunneled Hickman Catheter
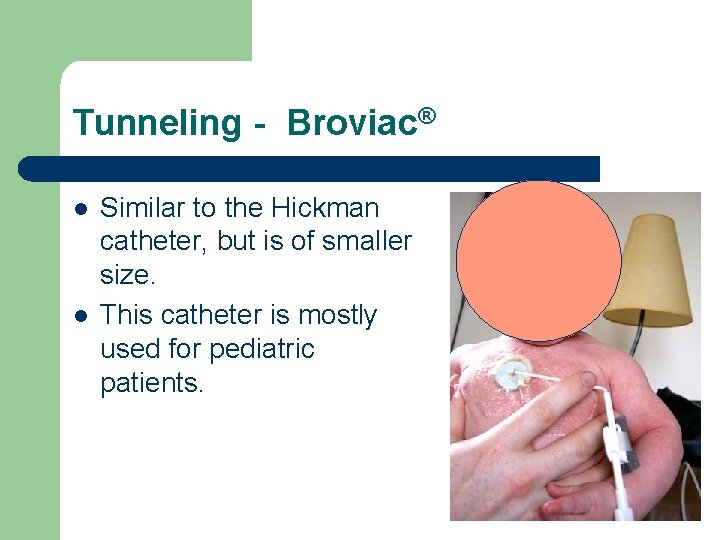
Tunneling - Broviac® l l Similar to the Hickman catheter, but is of smaller size. This catheter is mostly used for pediatric patients.
Tunneling - Groshong® l Similar to Hickman® and Broviac® with closed ended patented 3 -way valve.
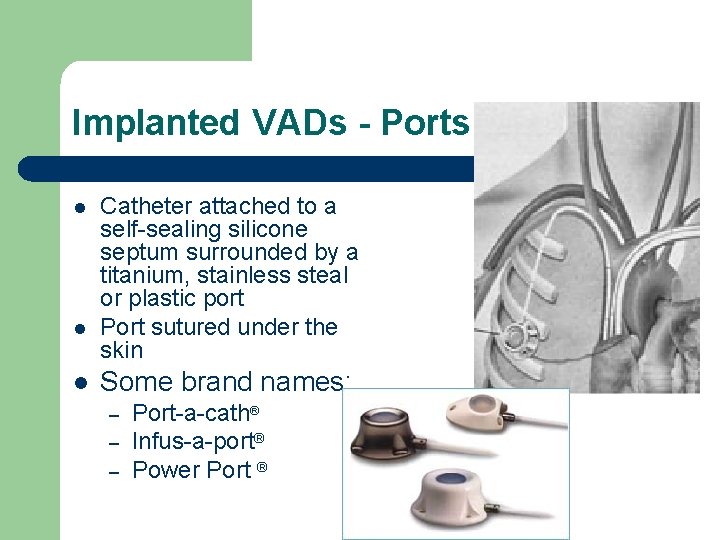
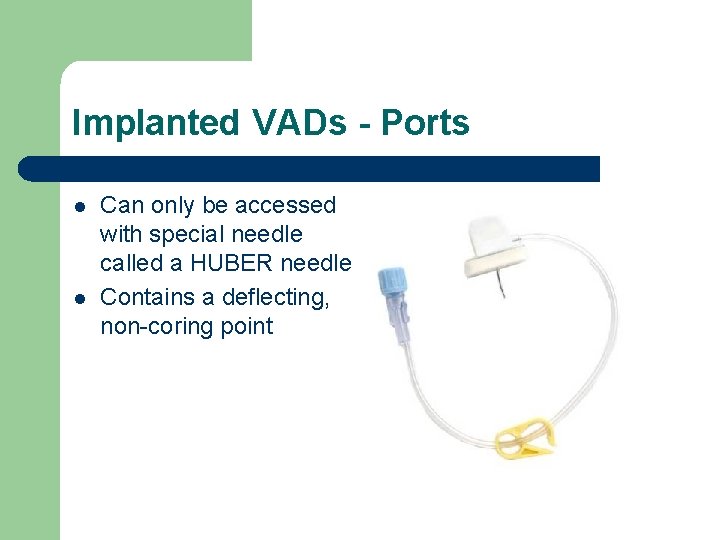
Implanted VADs - Ports l l l Catheter attached to a self-sealing silicone septum surrounded by a titanium, stainless steal or plastic port Port sutured under the skin Some brand names: – – – Port-a-cath® Infus-a-port® Power Port ®
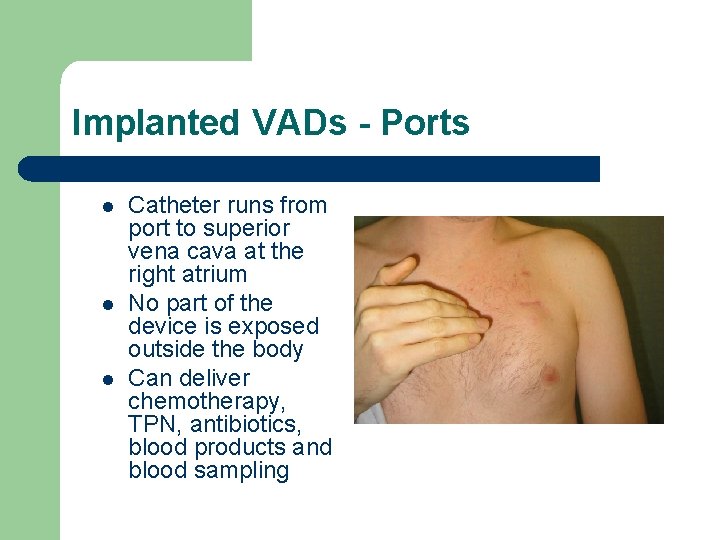
Implanted VADs - Ports l l l Catheter runs from port to superior vena cava at the right atrium No part of the device is exposed outside the body Can deliver chemotherapy, TPN, antibiotics, blood products and blood sampling
Implanted VADs - Ports l l Can only be accessed with special needle called a HUBER needle Contains a deflecting, non-coring point
Insertion Complications l l l Inadvertent Arterial Puncture Hematoma Formation Extravasation Infection Phlebitis Pneumothorax
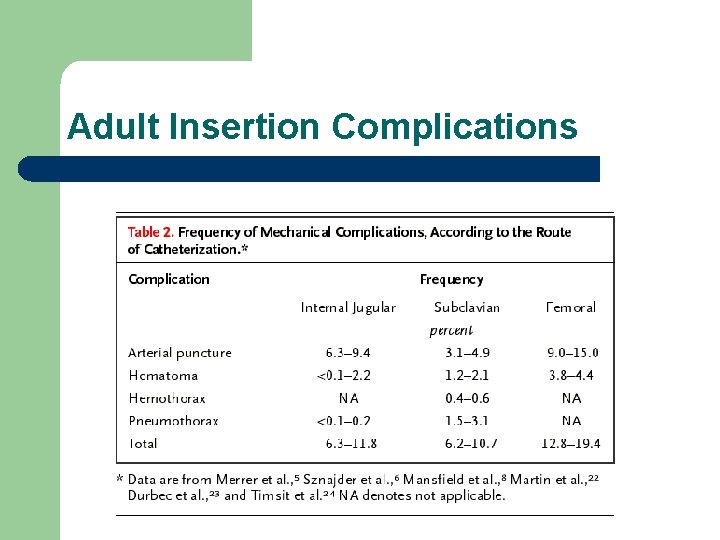
Adult Insertion Complications
Systemic Complications l l Infection Deep Vein Thrombosis Pulmonary Embolism Superior Vena Cava Syndrome
Mechanical Complication l l l Catheter tip migration Broken or damaged catheter Catheter occlusion
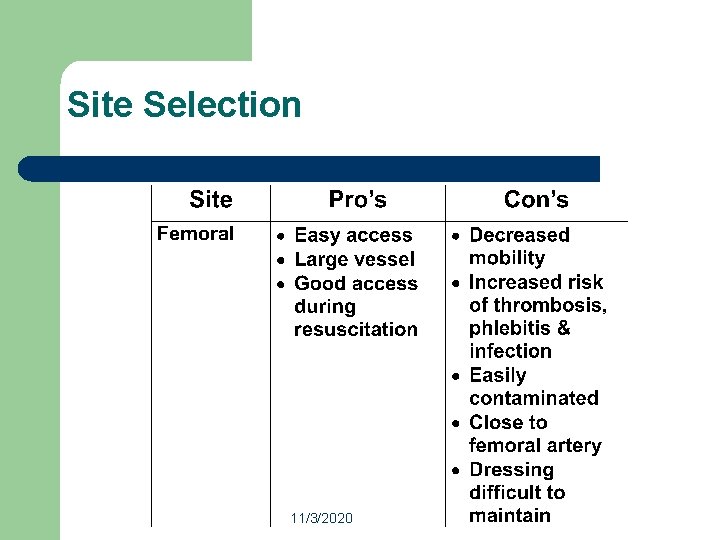
Femoral Vein l Adults – – DVT Excess infection risk “Potentially inaccurate CVP”
Femoral Vein l Kids – – – Better risk profile Ease of insertion, compressible No difference in DVT – ref 1 -2 Same infection risk (maybe lower) – ref 3 -5 Accurately reflects RAP if no increase in abdominal pressures – ref 6 -8 1. Beck C, et al. J Ped 1998; 133: 237 -41. 2. Jacobs B, et al. Crit Care Med 1999; 27: A 29 3. Casado-Flores J, et al. Ped Crit Care Med 2001; 2: 5762. 4. Richards M, et al. NNIS Pediatrics 1999; 103: 103 -9 5. Stenzel JP, et al. J Ped 1989; 114: 411 -5. 6. Fernendez E, et al. Ped Crit Care Med 2004; 5: 14 -18 7. Lloyd R, et al. Pediatrics 1992; 89: 506 -8. 8. Ho K, et al. Crit Care Med 1998; 26: 461 -4.
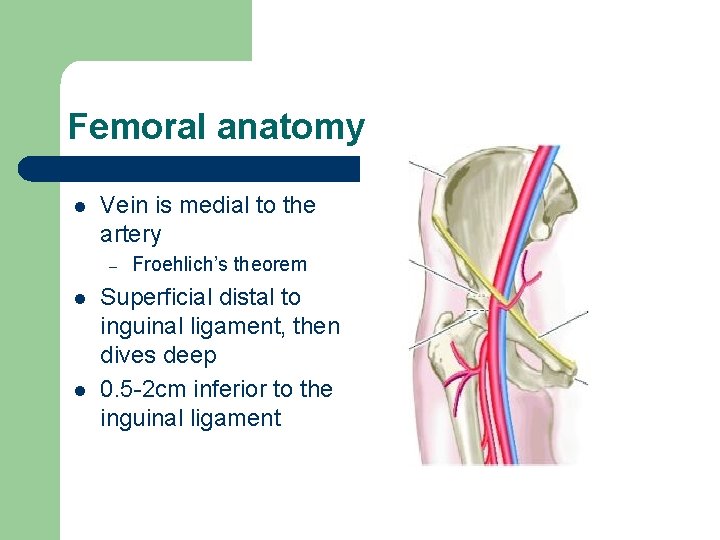
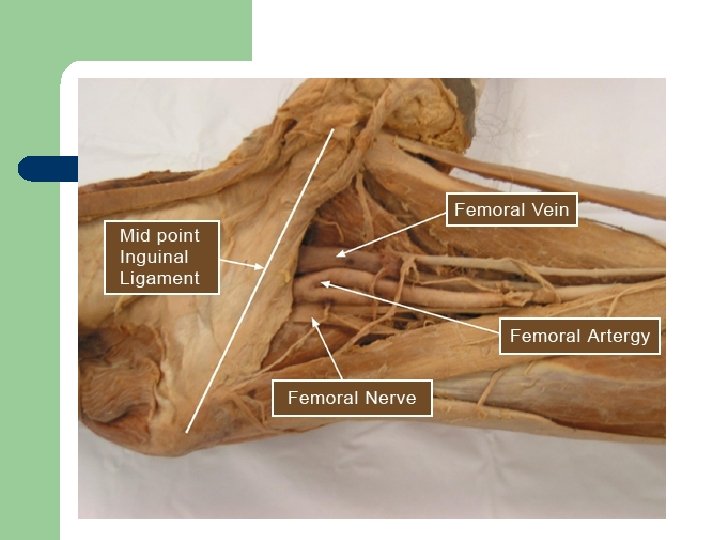
Femoral anatomy l Vein is medial to the artery – l l Froehlich’s theorem Superficial distal to inguinal ligament, then dives deep 0. 5 -2 cm inferior to the inguinal ligament
Quiz Question l What are the anatomic landmarks to determine where to stick for the femoral vein in a pulseless patient? – – A. 1/3 of the distance from the anterior superior iliac spine to the pubic tubercle B. ½ the distance between the pubic tubercle and the anterior superior iliac spine C. 1/3 of the distance from the pubic tubercle and the anterior superior iliac spine D. None of the above
Quiz answer l l l D. None of the above The femoral ARTERY lies ½ the distance between the pubic tubercle and the anterior superior iliac spine. The femoral vein is 0. 5 -1. 5 cm medial to this depending on the size of the patient.
Straight vs. Frog leg l “The optimal positioning of the leg can vary according to the preference of the operator. ” – Discuss
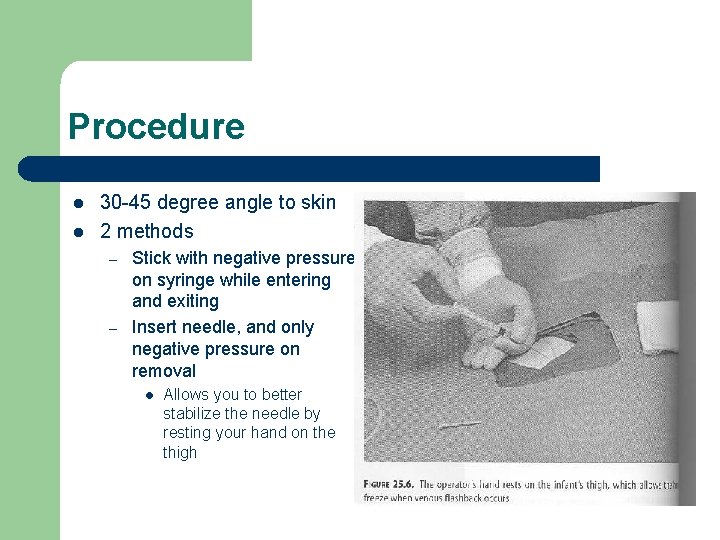
Procedure l l 30 -45 degree angle to skin 2 methods – – Stick with negative pressure on syringe while entering and exiting Insert needle, and only negative pressure on removal l Allows you to better stabilize the needle by resting your hand on the thigh
Procedure l Blood flash - Insert wire – Wire not going smoothly l l l Needle no longer in vessel False tracking in subcutaneous tissue Thrombus Advancing into lumbar veins Small incision – Blade directed away from wire
Procedure l l l l Twisting motion of dilation Remove dilator Advance catheter Remove wire Aspirate and flush all ports Secure line with sutures Sterile dressing
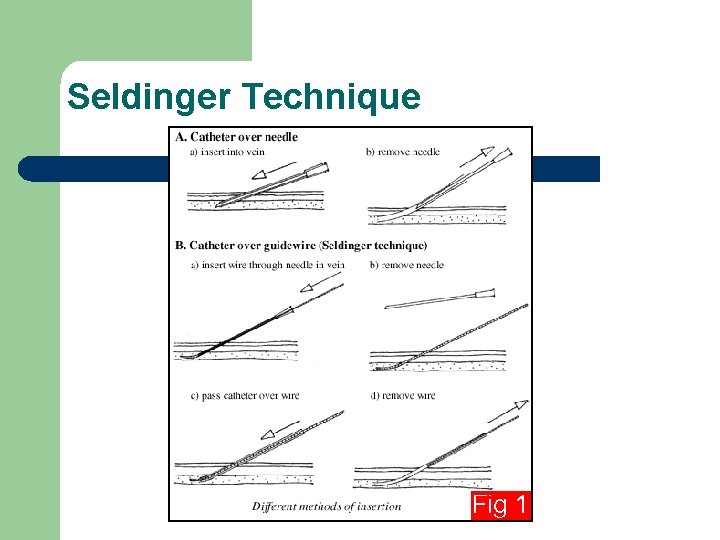
Seldinger Technique
Procedure l Wheeler – “Confirmation of proper CVC position is required after placement of all CVC’s”
Warnings l l l If you hit the artery – pressure until hemostatic Wire should float – should never have resistance If can’t pull the wire through the needle – remove both wire and needle together so you don’t sheer off the wire Never let go of the wire Catheter tip “pointing too cephalad” – in lumbar veins
Complications l l 74 of 89 (83%) – no complications Other 15 – minor bleeding/hematoma 94. 4% success rate Median duration 5 days – – l 21% <3 days 43% 4 -7 days 26% 7 -14 days 10% >14 days Long term – 8 leg swelling, 11 BSI Venkataraman, et al. Clin Ped 1997; 36: 311 -9.
Complications l l 45 months – 395 CVL – 162 femoral No insertion complications Mean duration 8. 9 days 9 noninfectious complications – l 4 thrombosis, 1 perforation, 1 embolism, 2 bleeding “The low incidence of complications in this study suggests that the femoral vein is the preferred site in most critically ill children when CVC is indicated. ” Stenzel JP, et al. J Ped 1989; 114: 411 -5
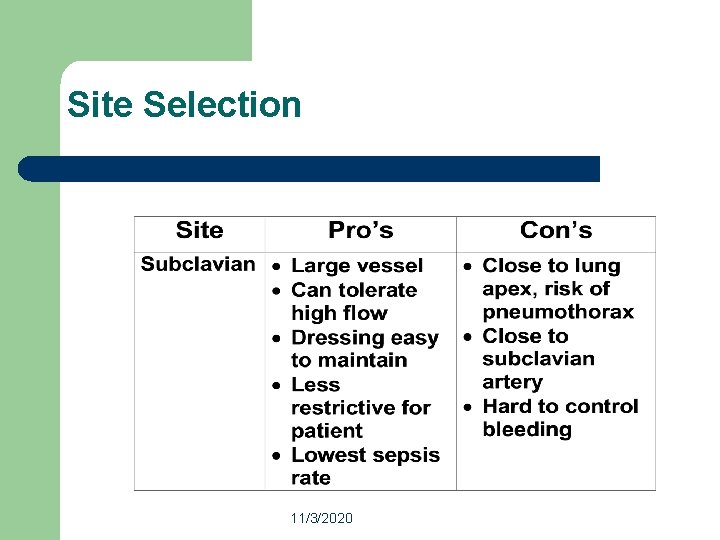
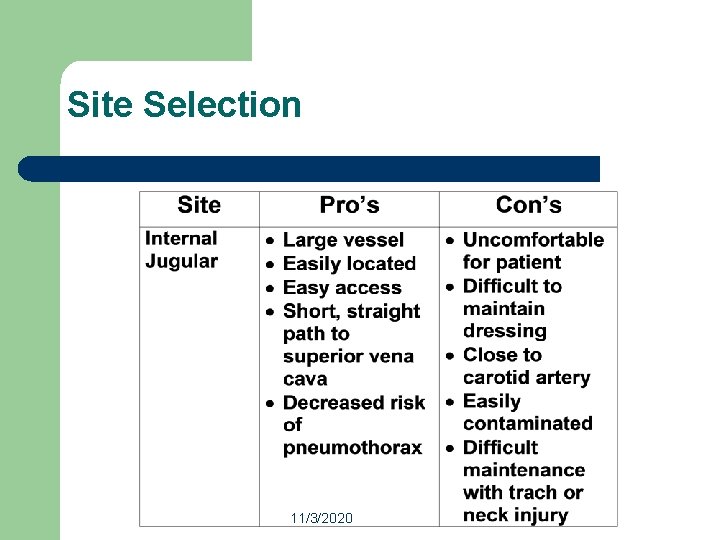
Site Selection 11/3/2020
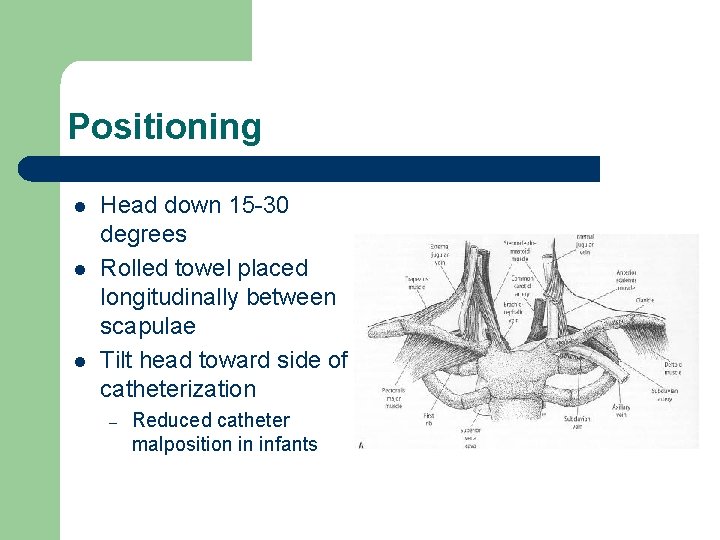
Subclavian Vein l When to use it – – – l May be better for long term access Obese – clavicle gives you a landmark Shock – less likely to collapse Relative contraindications – – Trauma to the area Coagulopathic
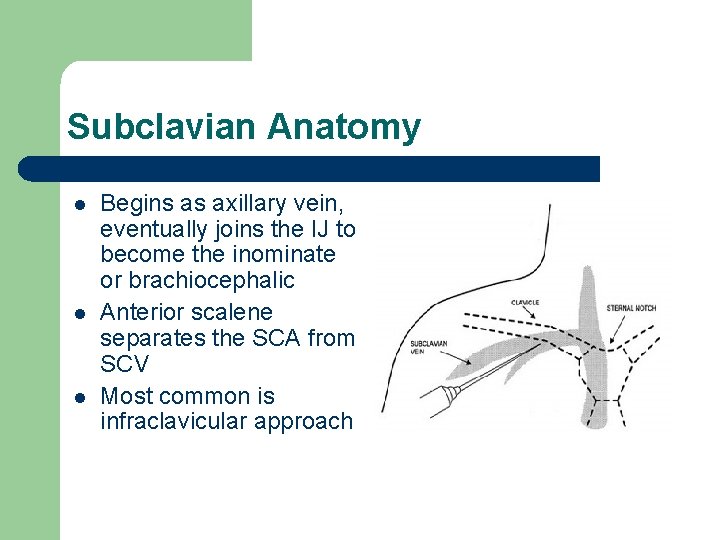
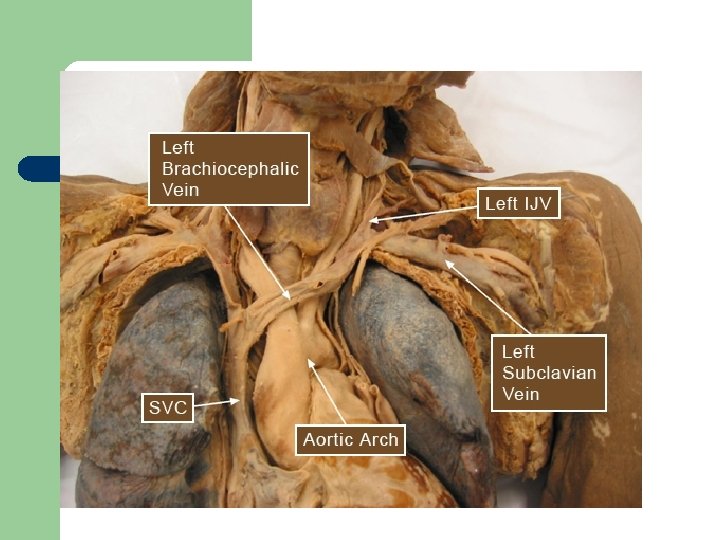
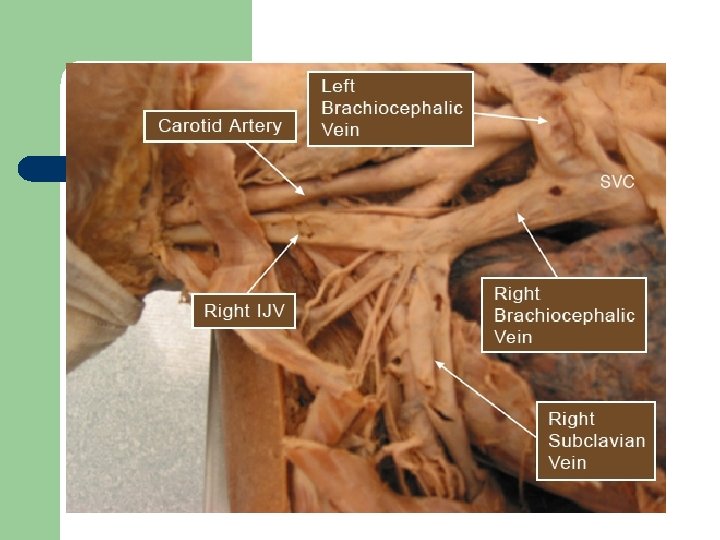
Subclavian Anatomy l l l Begins as axillary vein, eventually joins the IJ to become the inominate or brachiocephalic Anterior scalene separates the SCA from SCV Most common is infraclavicular approach
Positioning l l l Head down 15 -30 degrees Rolled towel placed longitudinally between scapulae Tilt head toward side of catheterization – Reduced catheter malposition in infants
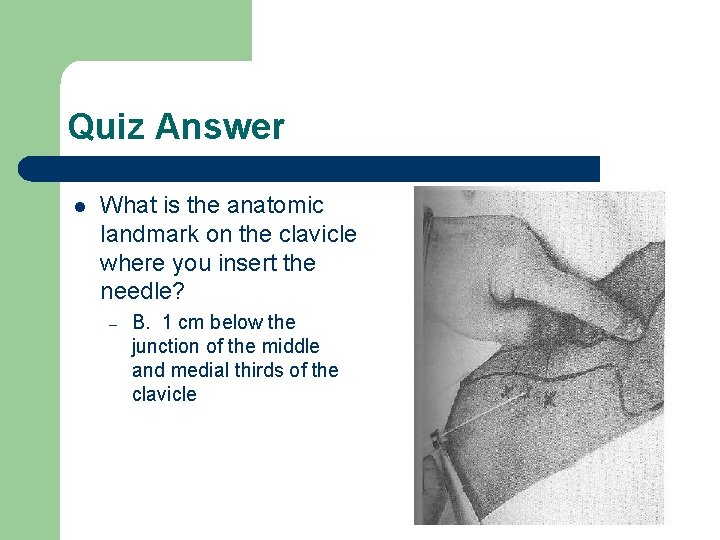
Quiz Question l What is the anatomic landmark on the clavicle where you insert the needle? – – A. 1 cm below the junction of the middle and lateral thirds of the clavicle B. 1 cm below the junction of the middle and medial thirds of the clavicle C. 1 cm below the middle third of the clavicle D. 1 cm below the lateral third of the clavicle
Quiz Answer l What is the anatomic landmark on the clavicle where you insert the needle? – B. 1 cm below the junction of the middle and medial thirds of the clavicle
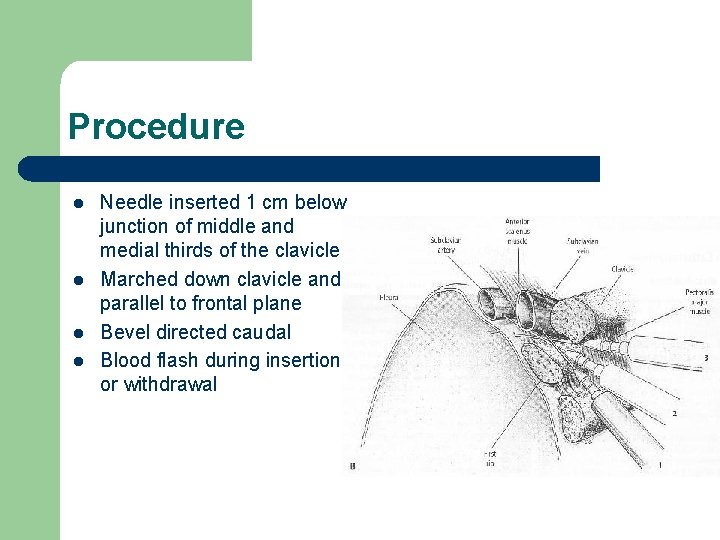
Procedure l l Needle inserted 1 cm below junction of middle and medial thirds of the clavicle Marched down clavicle and parallel to frontal plane Bevel directed caudal Blood flash during insertion or withdrawal
Procedure l Regular Seldinger technique l Watch for dysrhythmias with wire insertion
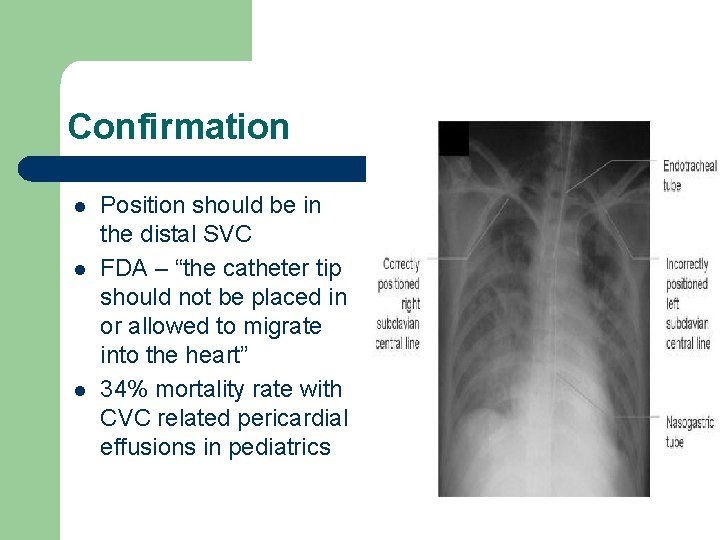
Confirmation l l l Position should be in the distal SVC FDA – “the catheter tip should not be placed in or allowed to migrate into the heart” 34% mortality rate with CVC related pericardial effusions in pediatrics
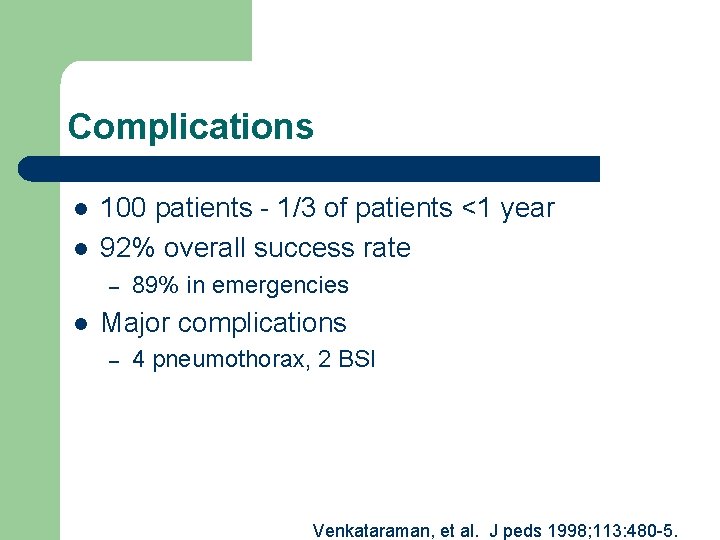
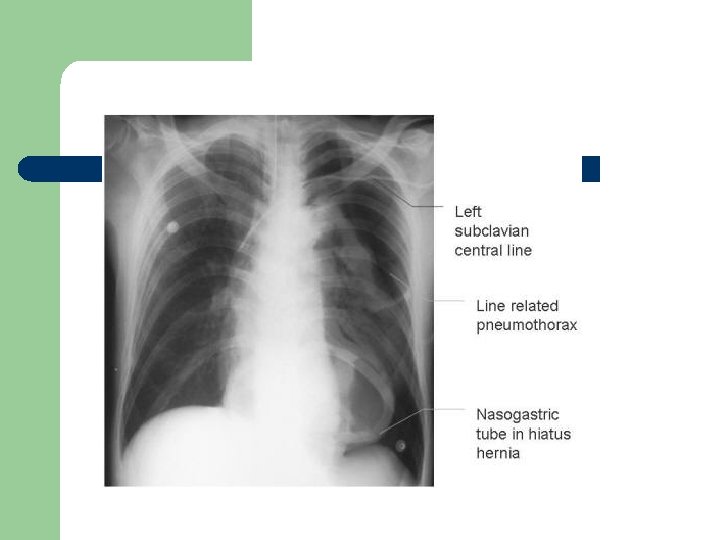
Complications l l l Inability to cannulate SCA puncture/cannulation Catheter misplacement Pneumothorax Hemothorax Nerve injury
Complications l l 100 patients - 1/3 of patients <1 year 92% overall success rate – l 89% in emergencies Major complications – 4 pneumothorax, 2 BSI Venkataraman, et al. J peds 1998; 113: 480 -5.
Site Selection 11/3/2020
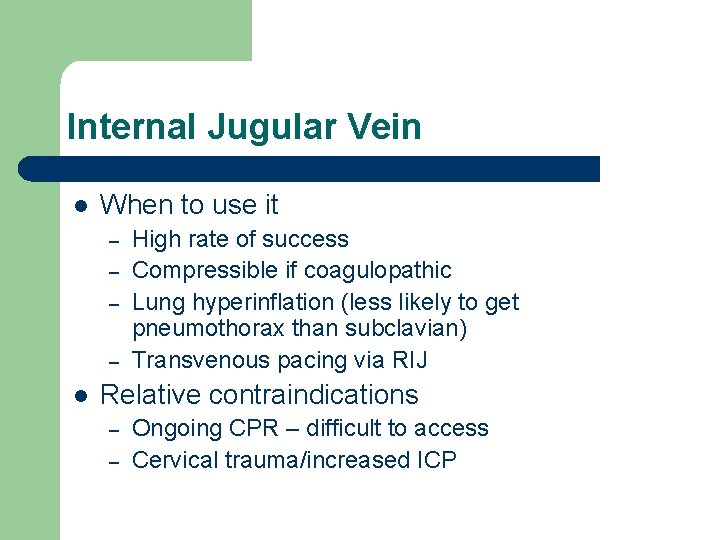
Internal Jugular Vein l When to use it – – l High rate of success Compressible if coagulopathic Lung hyperinflation (less likely to get pneumothorax than subclavian) Transvenous pacing via RIJ Relative contraindications – – Ongoing CPR – difficult to access Cervical trauma/increased ICP
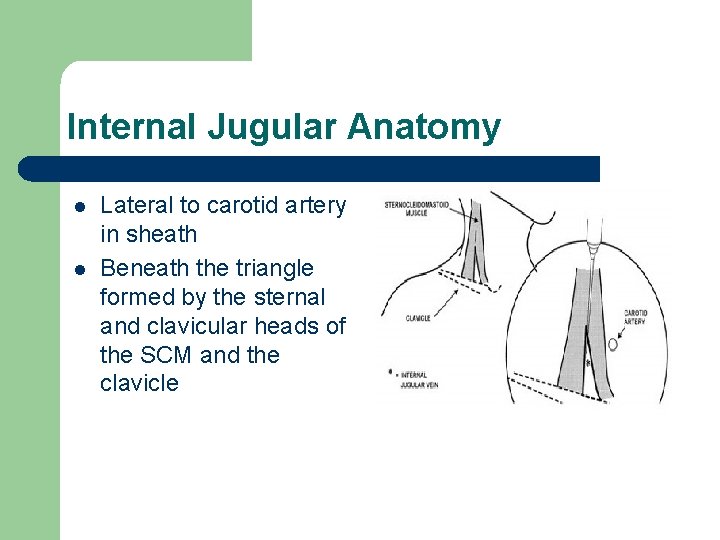
Internal Jugular Anatomy l l Lateral to carotid artery in sheath Beneath the triangle formed by the sternal and clavicular heads of the SCM and the clavicle
Quiz Question l All of the following are correct about a left internal jugular cannulation EXCEPT: – – A. LIJ has a more acute angle at connection with subclavian B. Lower pneumothorax risk compared to right because right pleural dome is higher C. Lymphatic duct adjacent to junction of LIJ and innominate vein D. Reduced risk of carotid puncture because of its caudocephalad structure
Quiz answer l l l B is the correct answer to the question Reasons to go right – The left has : – – – More acute angle at connection with subclavian Left pleural dome is higher (more pneumothorax risk) Lymphatic duct adjacent to junction of LIJ and innominate
Internal Jugular Positioning l l l Trendelenberg 15 -30 degrees Shoulder roll Head turned away from side of insertion
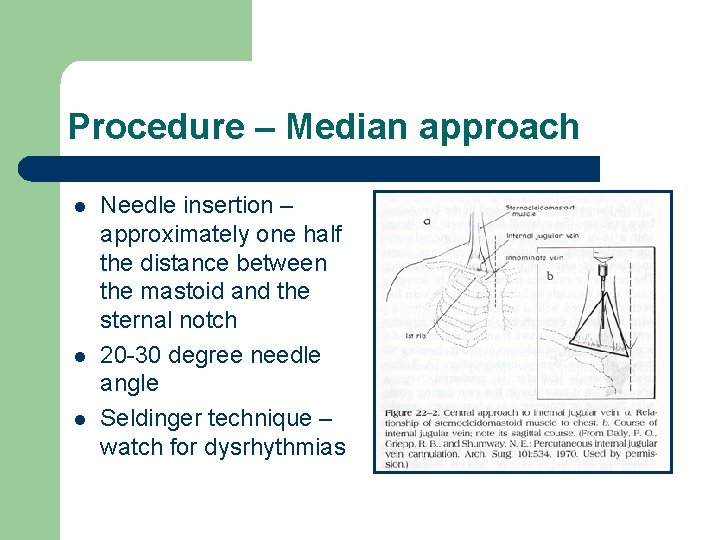
Procedure – Median approach l l l Needle insertion – approximately one half the distance between the mastoid and the sternal notch 20 -30 degree needle angle Seldinger technique – watch for dysrhythmias
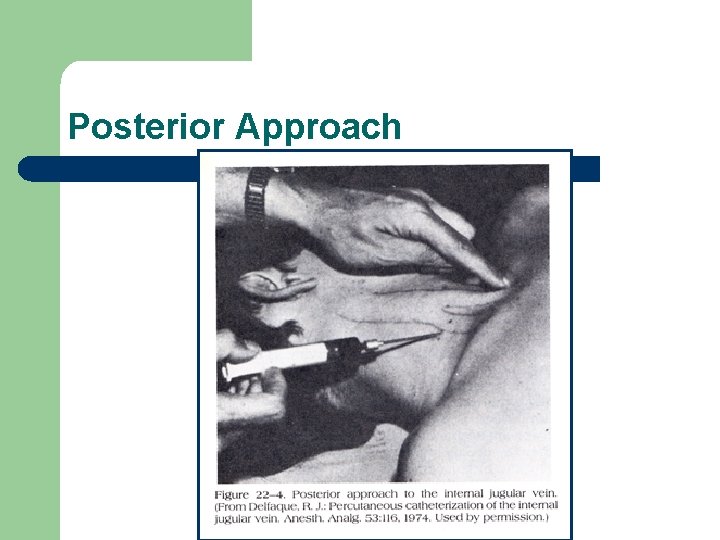
Posterior Approach
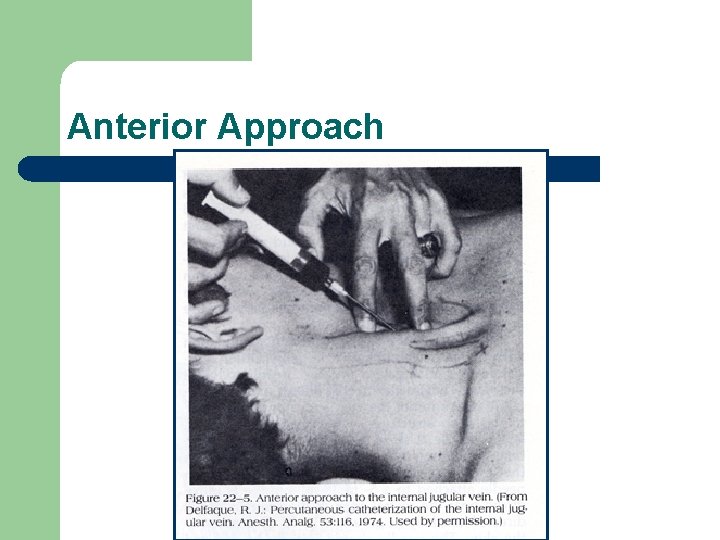
Anterior Approach
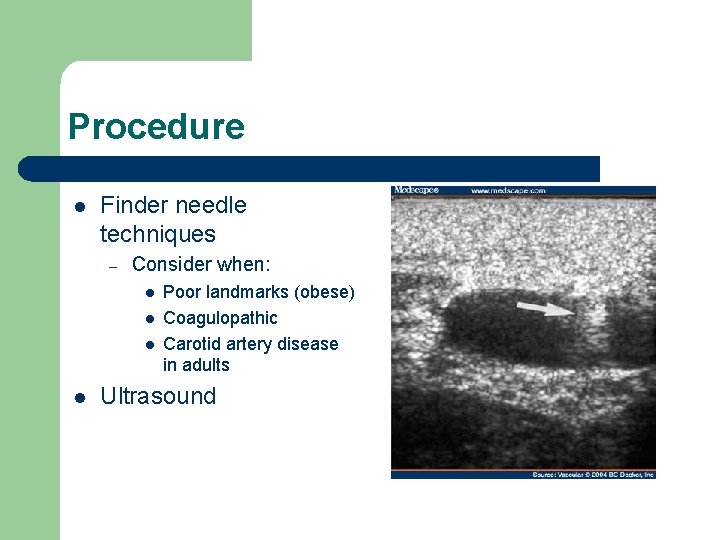
Procedure l Finder needle techniques – Consider when: l l Poor landmarks (obese) Coagulopathic Carotid artery disease in adults Ultrasound
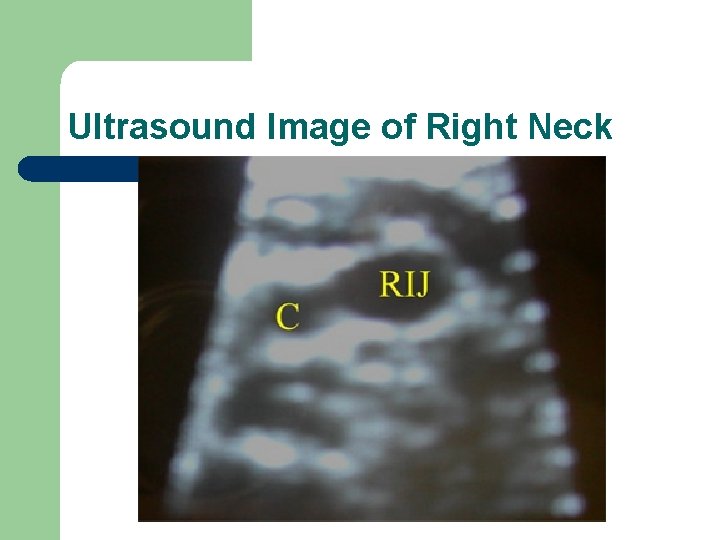
Ultrasound Image of Right Neck
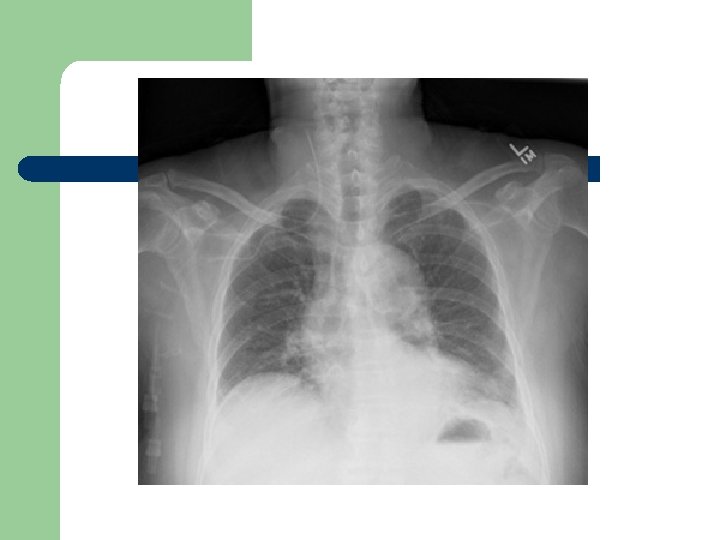
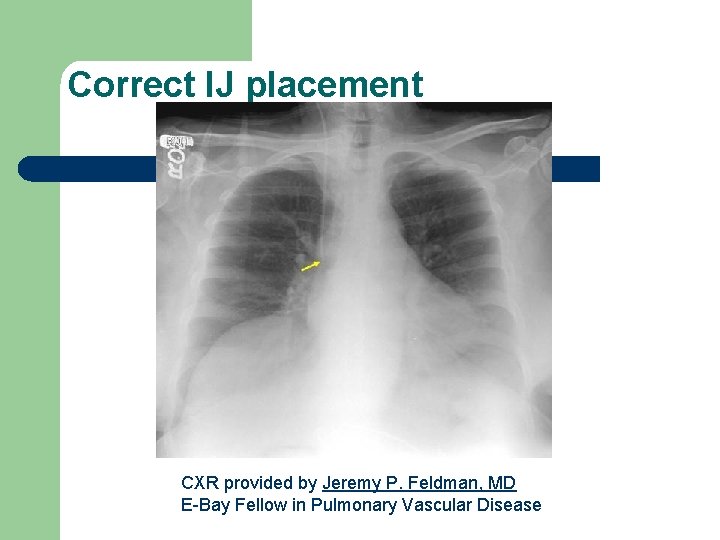
Correct IJ placement CXR provided by Jeremy P. Feldman, MD E-Bay Fellow in Pulmonary Vascular Disease
Complications l l l Arterial puncture more common than subclavian Pneumo/hemo thorax very rare Catheter malpositioning similar to subclavian
Site Selection 11/3/2020
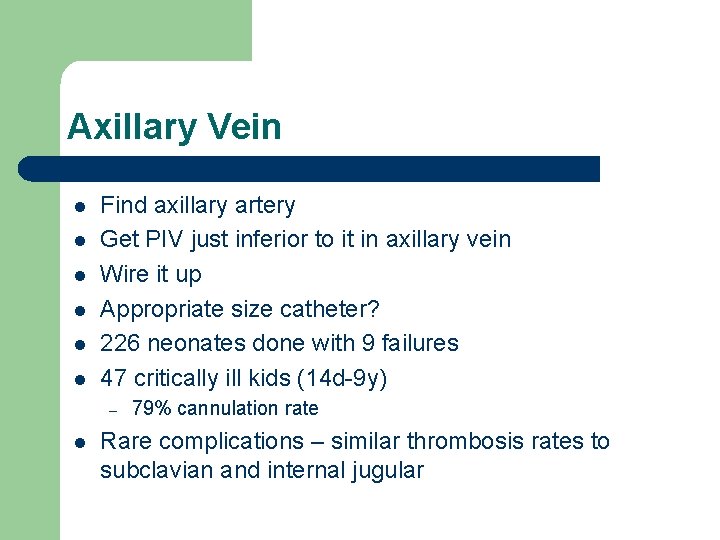
Axillary Vein l l l Find axillary artery Get PIV just inferior to it in axillary vein Wire it up Appropriate size catheter? 226 neonates done with 9 failures 47 critically ill kids (14 d-9 y) – l 79% cannulation rate Rare complications – similar thrombosis rates to subclavian and internal jugular
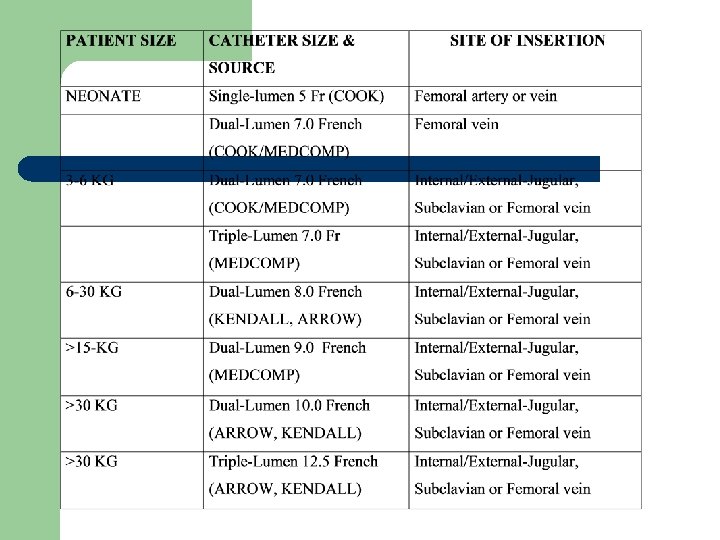
Temporary Dialysis Catheters l We have available : – – – 7 French Triple Lumen regular CVL 7 French 10 cm Double Lumen Medcomp 8 French 9 cm Double Lumen Mahurkar 12 French 13 cm Triple Lumen Mahurkar 12 French 20 cm Triple Lumen Mahurkar
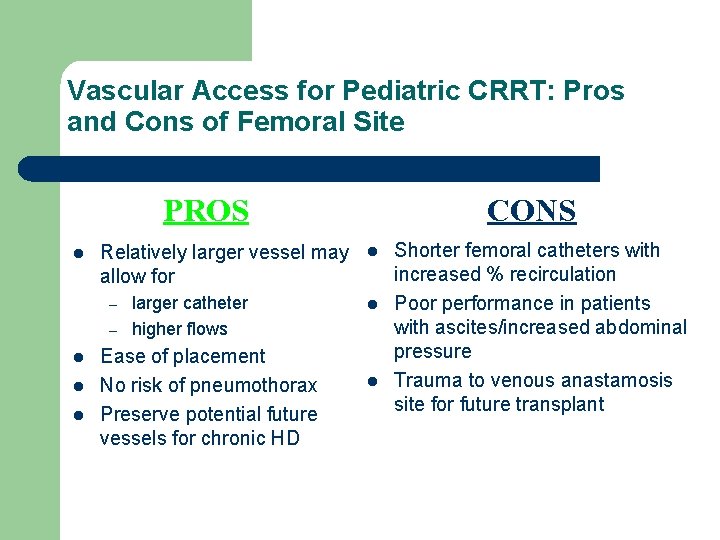
Vascular Access for Pediatric CRRT: Pros and Cons of Femoral Site PROS l Relatively larger vessel may allow for – – l larger catheter higher flows Ease of placement No risk of pneumothorax Preserve potential future vessels for chronic HD CONS l l l Shorter femoral catheters with increased % recirculation Poor performance in patients with ascites/increased abdominal pressure Trauma to venous anastamosis site for future transplant
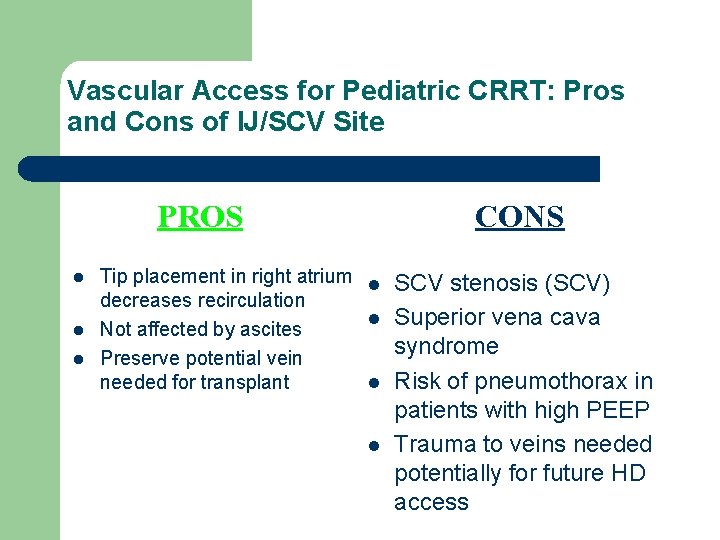
Vascular Access for Pediatric CRRT: Pros and Cons of IJ/SCV Site PROS l l l CONS Tip placement in right atrium l decreases recirculation l Not affected by ascites Preserve potential vein needed for transplant l l SCV stenosis (SCV) Superior vena cava syndrome Risk of pneumothorax in patients with high PEEP Trauma to veins needed potentially for future HD access
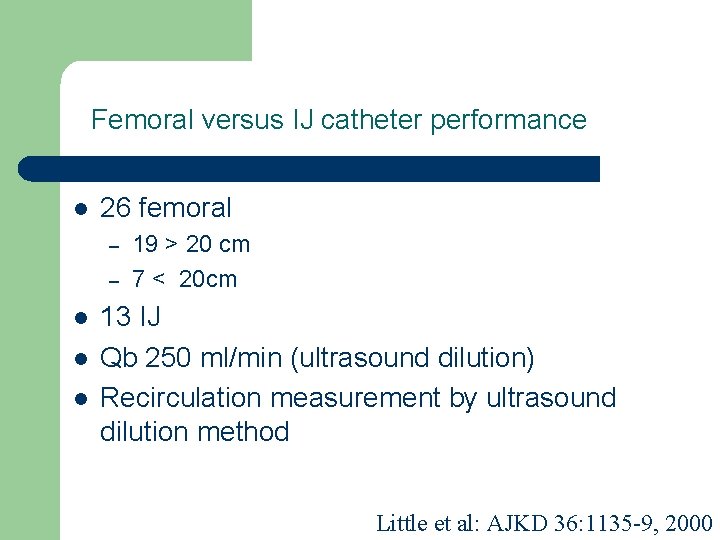
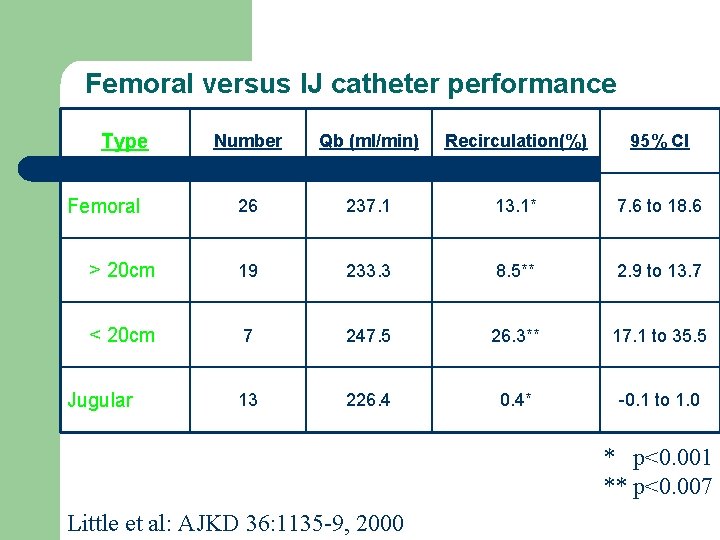
Femoral versus IJ catheter performance l 26 femoral – – l l l 19 > 20 cm 7 < 20 cm 13 IJ Qb 250 ml/min (ultrasound dilution) Recirculation measurement by ultrasound dilution method Little et al: AJKD 36: 1135 -9, 2000
Femoral versus IJ catheter performance Type Number Qb (ml/min) Recirculation(%) 95% CI Femoral 26 237. 1 13. 1* 7. 6 to 18. 6 > 20 cm 19 233. 3 8. 5** 2. 9 to 13. 7 < 20 cm 7 247. 5 26. 3** 17. 1 to 35. 5 Jugular 13 226. 4 0. 4* -0. 1 to 1. 0 * p<0. 001 ** p<0. 007 Little et al: AJKD 36: 1135 -9, 2000
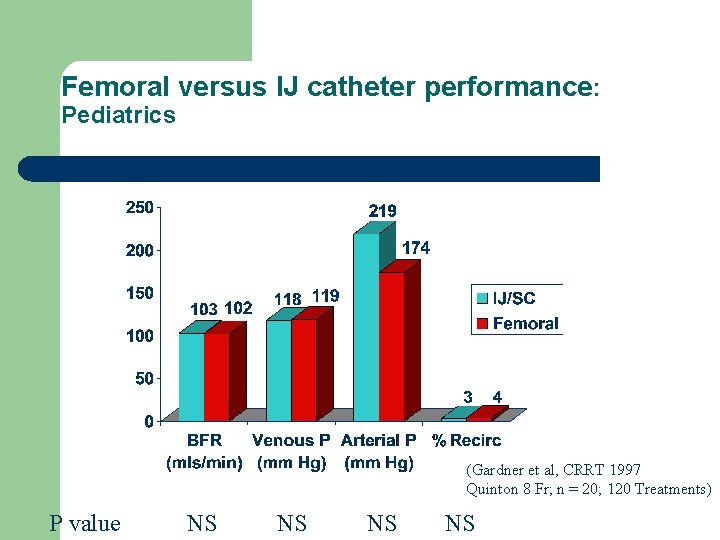
Femoral versus IJ catheter performance: Pediatrics (Gardner et al, CRRT 1997 Quinton 8 Fr; n = 20; 120 Treatments) P value NS NS