DIFFERENTIAL DIAGNOSIS OF CYSTIC SWELLINGS OF NECK AND



























- Slides: 81
DIFFERENTIAL DIAGNOSIS OF CYSTIC SWELLINGS OF NECK AND MANAGEMENT By CIGIA PAUL
Swellings of neck ÆMidline ÆLateral
MIDLINE ¬Ludwig's angina ¬Enlarged sub mental lymph node ¬Sublingual dermoid ¬Sub hyoid bursitis ¬Pyramidal lobe ¬Pretracheal, paratrachael lymph nodes ¬Lipoma in suprasternal space of burns ¬Retrosternal goitre
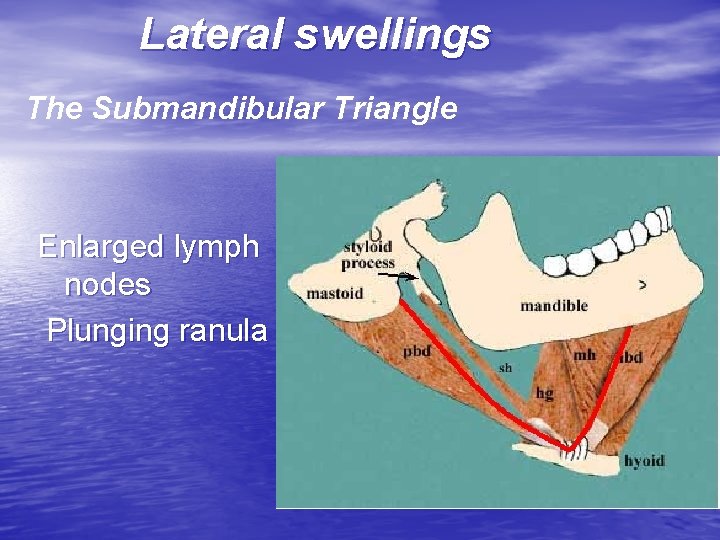
Lateral swellings The Submandibular Triangle Enlarged lymph nodes Plunging ranula
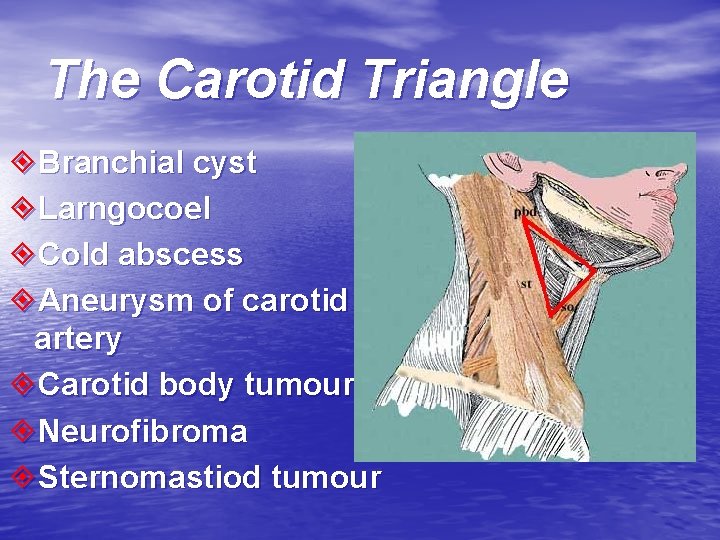
The Carotid Triangle ◈Branchial cyst ◈Larngocoel ◈Cold abscess ◈Aneurysm of carotid artery ◈Carotid body tumour ◈Neurofibroma ◈Sternomastiod tumour
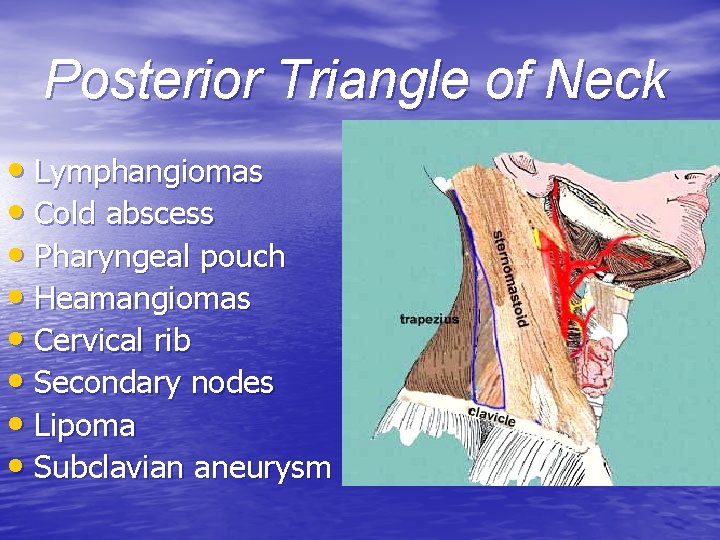
Posterior Triangle of Neck • Lymphangiomas • Cold abscess • Pharyngeal pouch • Heamangiomas • Cervical rib • Secondary nodes • Lipoma • Subclavian aneurysm
Common cystic swellings are • Thyroglossal cyst • Branchial cyst • Cystic hygroma • Dermoid cyst • Cold abscess • Plunging ranula • Pharyngeal pouch • Laryngocele • Sub hyoid bursitis
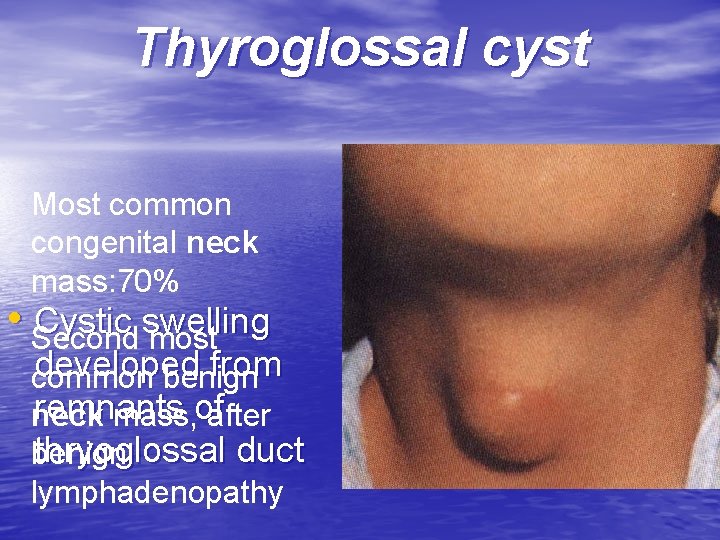
Thyroglossal cyst Most common congenital neck mass: 70% • Second Cystic swelling most developed from common benign remnants neck mass, of after thryoglossal duct benign lymphadenopathy
Embryology §The thyroid gland begins to develop in the 3 rd week of fetal life as a median outgrowth from the floor of the primitive pharynx called Thyroglossal duct §Distal bilobed ends lobes of thyroid §This duct normally involutes by the 8 th– 10 th gestational week.
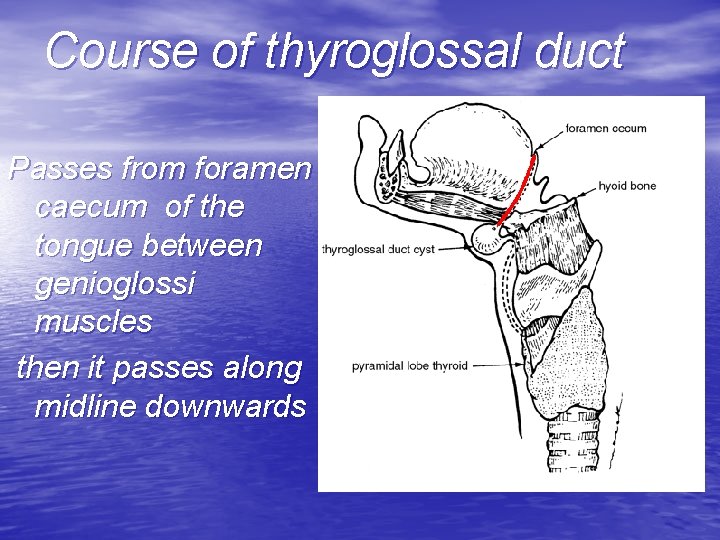
Course of thyroglossal duct Passes from foramen caecum of the tongue between genioglossi muscles then it passes along midline downwards
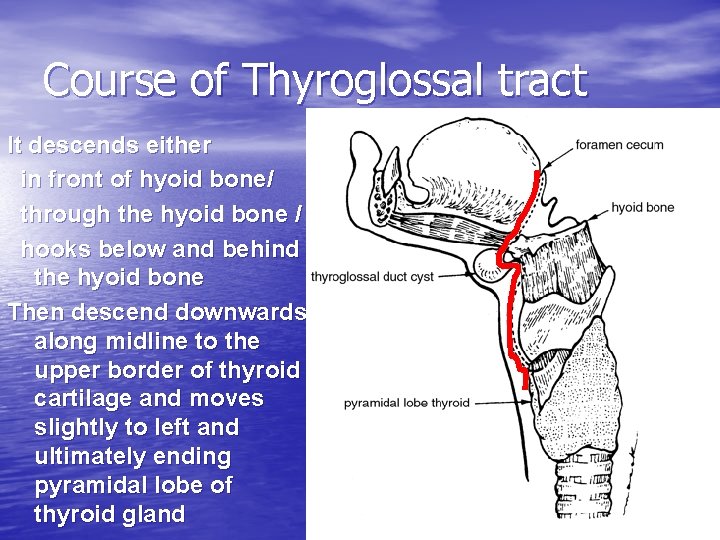
Course of Thyroglossal tract It descends either in front of hyoid bone/ through the hyoid bone / hooks below and behind the hyoid bone Then descend downwards along midline to the upper border of thyroid cartilage and moves slightly to left and ultimately ending pyramidal lobe of thyroid gland
Fate of thryoglossal duct ¯Duct usually disappears except for the lower portion > thyroid gland ¯ While the tract disappears , a portion may remain patent which gives rise to cystic swelling due to accumulation of secretions in it > thyroglossal cyst
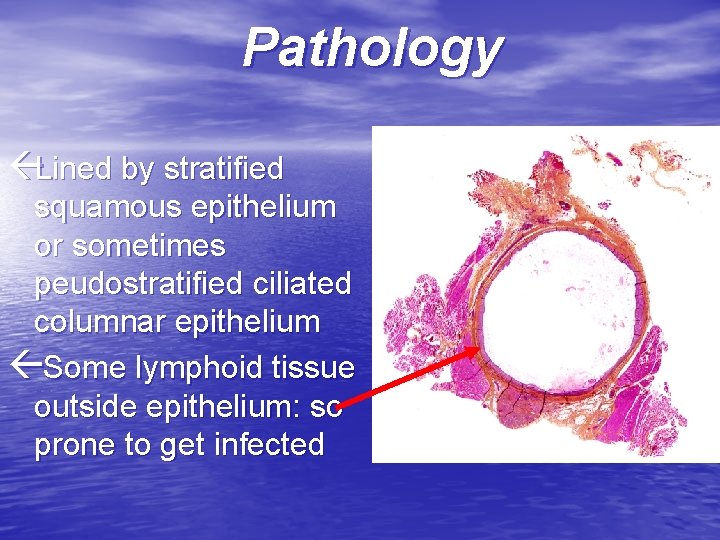
Pathology ßLined by stratified squamous epithelium or sometimes peudostratified ciliated columnar epithelium ßSome lymphoid tissue outside epithelium: so prone to get infected
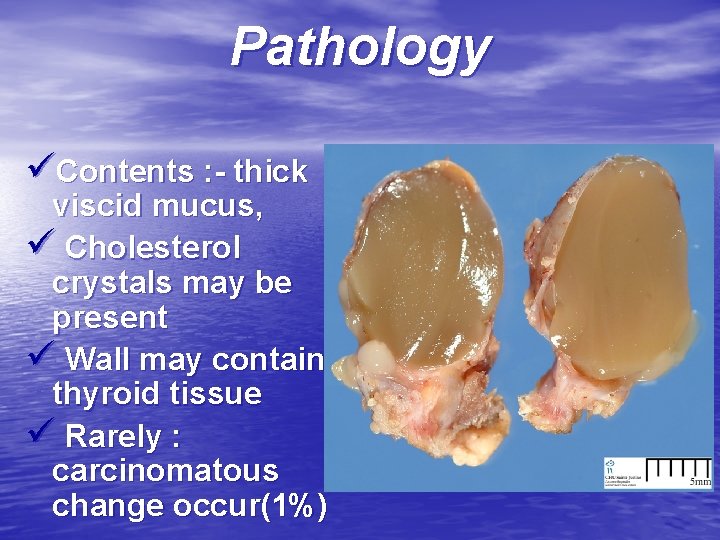
Pathology üContents : - thick viscid mucus, ü Cholesterol crystals may be present ü Wall may contain thyroid tissue ü Rarely : carcinomatous change occur(1%)
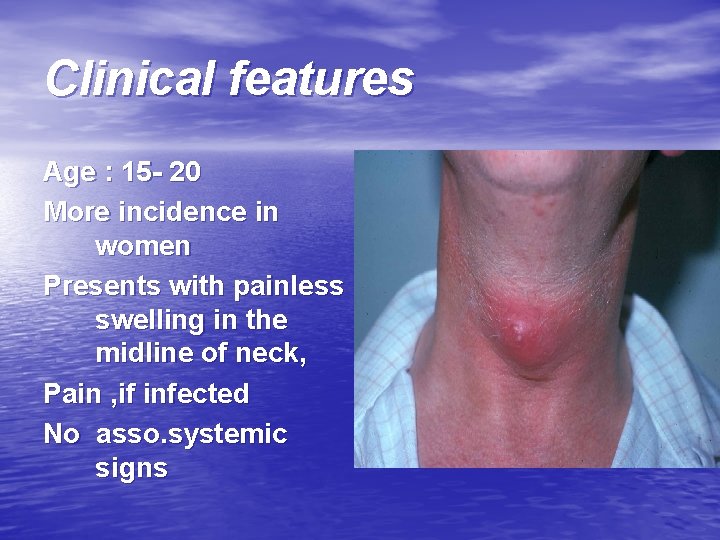
Clinical features Age : 15 - 20 More incidence in women Presents with painless swelling in the midline of neck, Pain , if infected No asso. systemic signs
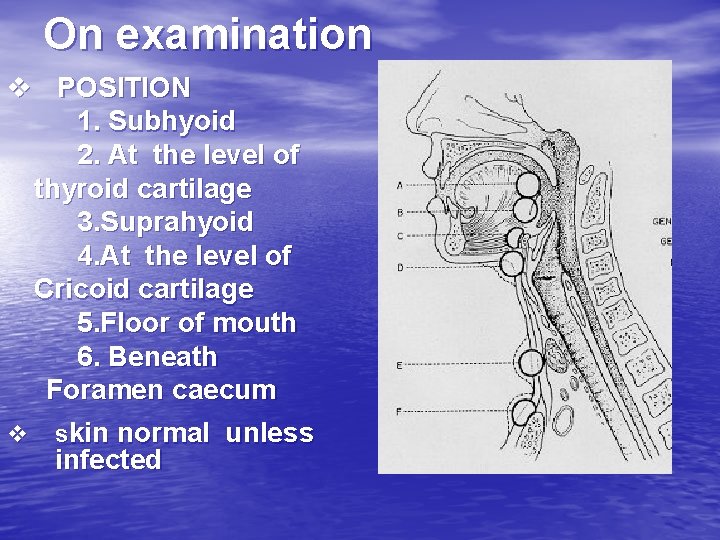
On examination v POSITION 1. Subhyoid 2. At the level of thyroid cartilage 3. Suprahyoid 4. At the level of Cricoid cartilage 5. Floor of mouth 6. Beneath Foramen caecum v skin normal unless infected
spherical /oval with long axis vertically along tract q Soft, cystc, fluctuant q Transilumination rarely positive q DON’T FORGET TO EXAMINE BASE OF TONGUE for ectopic thyroid q q. Mobility: 3 types with deglutition protrusion of tongue horizontal
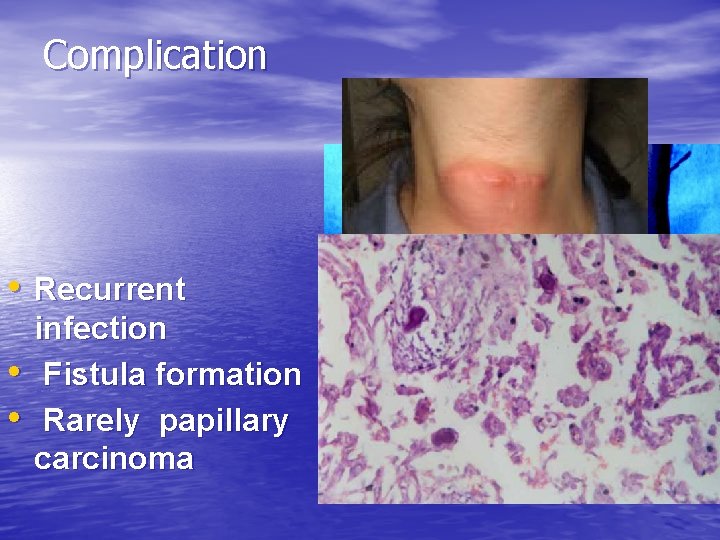
Complication • Recurrent • • infection Fistula formation Rarely papillary carcinoma
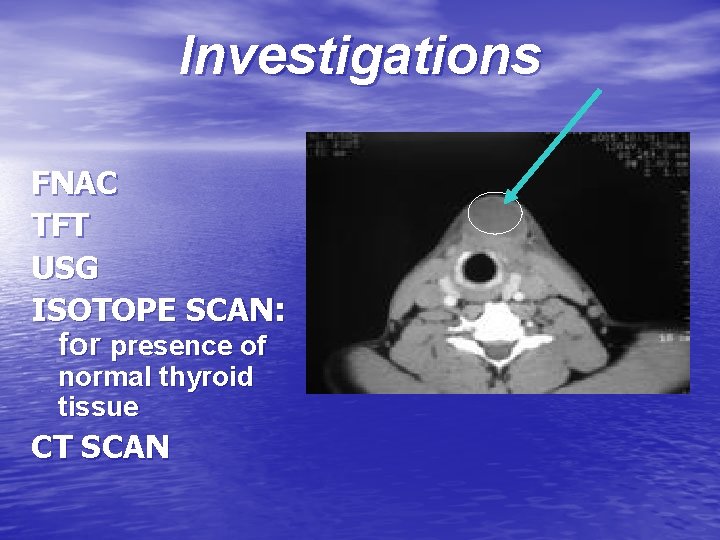
Investigations FNAC TFT USG ISOTOPE SCAN: for presence of normal thyroid tissue CT SCAN
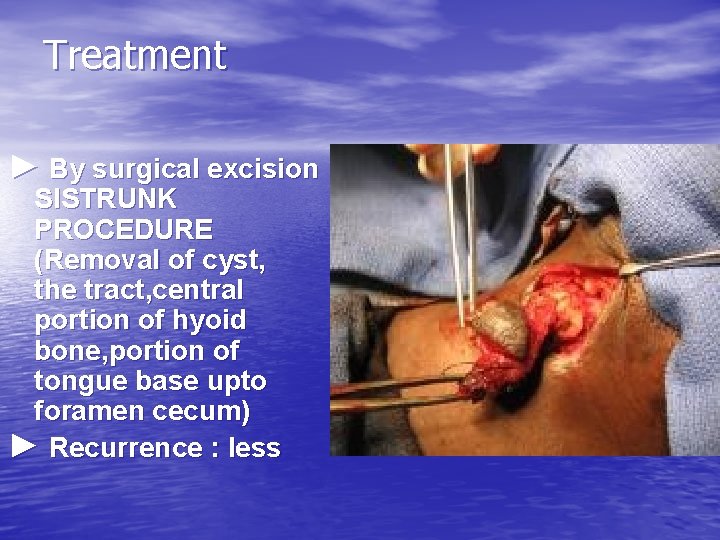
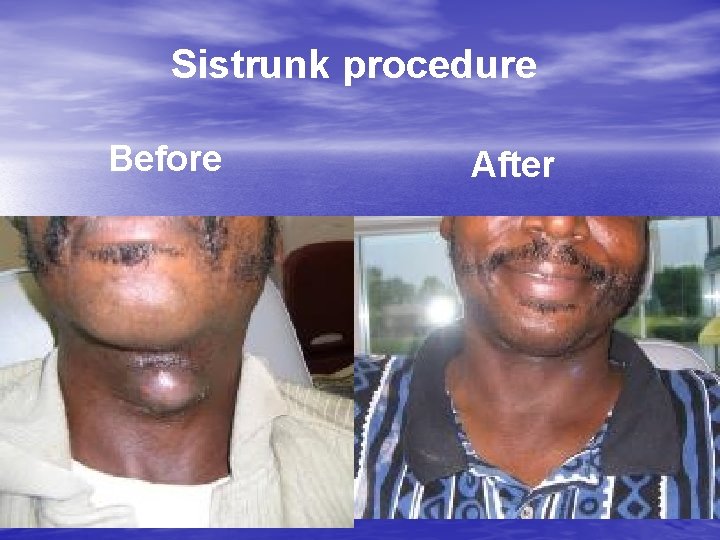
Treatment ► By surgical excision SISTRUNK PROCEDURE (Removal of cyst, the tract, central portion of hyoid bone, portion of tongue base upto foramen cecum) ► Recurrence : less
Sistrunk procedure Before After
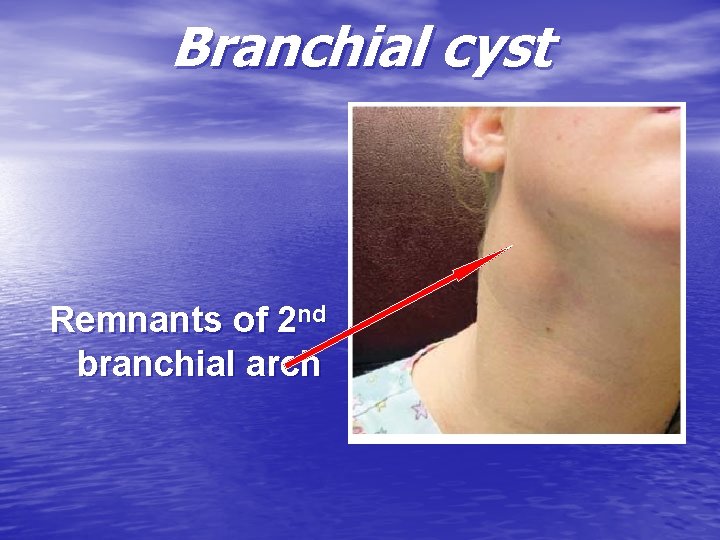
Branchial cyst Remnants of 2 nd branchial arch
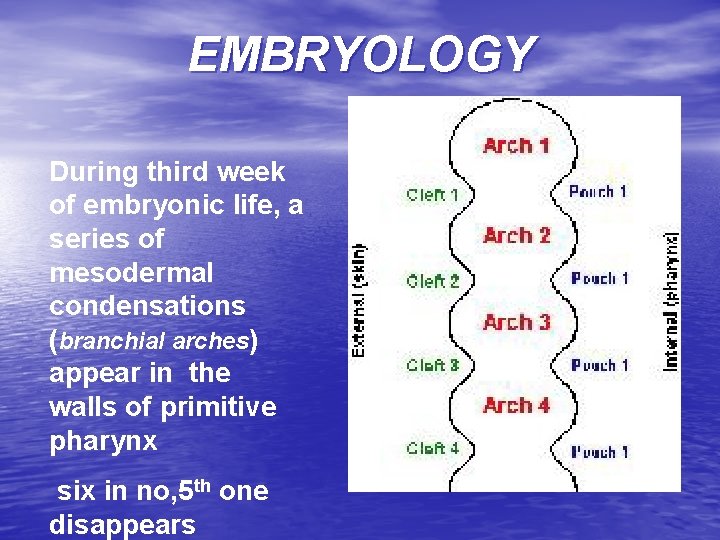
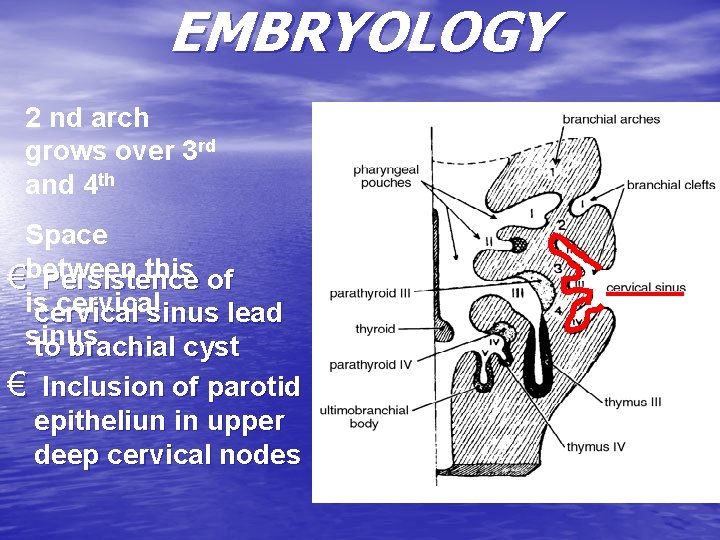
EMBRYOLOGY During third week of embryonic life, a series of mesodermal condensations (branchial arches) appear in the walls of primitive pharynx six in no, 5 th one disappears
EMBRYOLOGY 2 nd arch grows over 3 rd and 4 th Space this of €between Persistence is cervical sinus lead sinus to brachial cyst € Inclusion of parotid epitheliun in upper deep cervical nodes
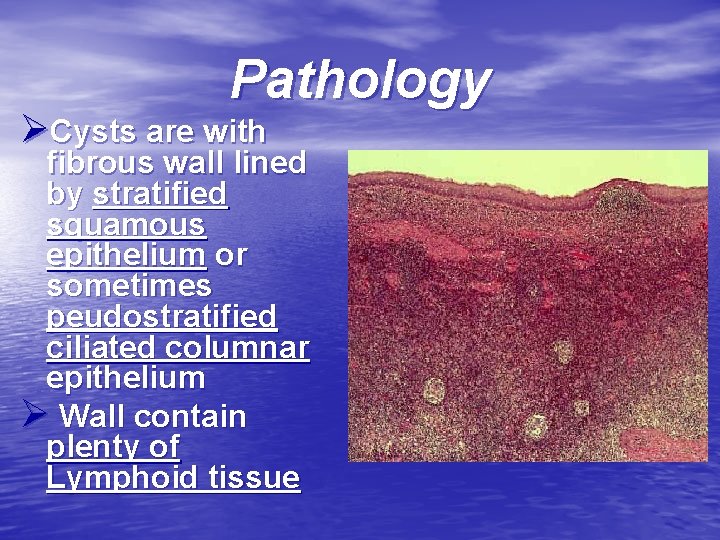
Pathology ØCysts are with fibrous wall lined by stratified squamous epithelium or sometimes peudostratified ciliated columnar epithelium Ø Wall contain plenty of Lymphoid tissue
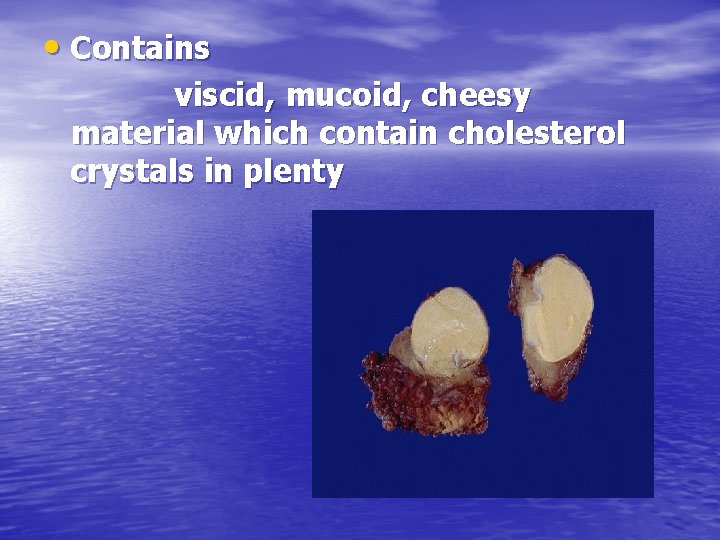
• Contains viscid, mucoid, cheesy material which contain cholesterol crystals in plenty
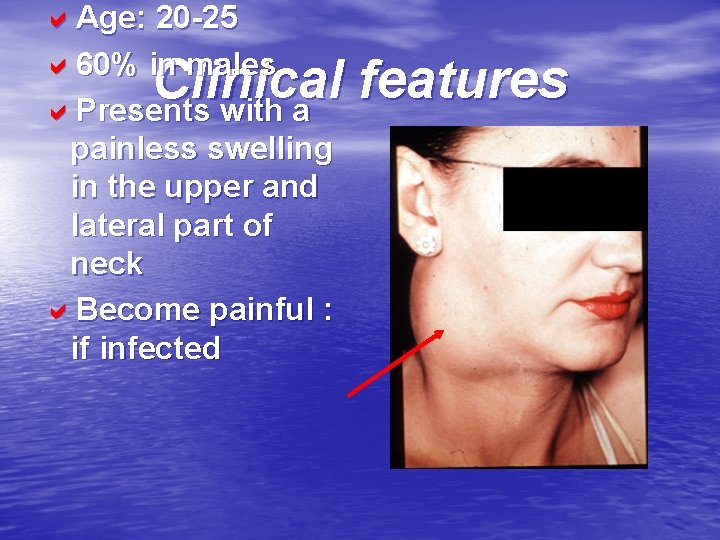
a. Age: 20 -25 a 60% in males a. Presents with a painless swelling in the upper and lateral part of neck a. Become painful : if infected Clinical features
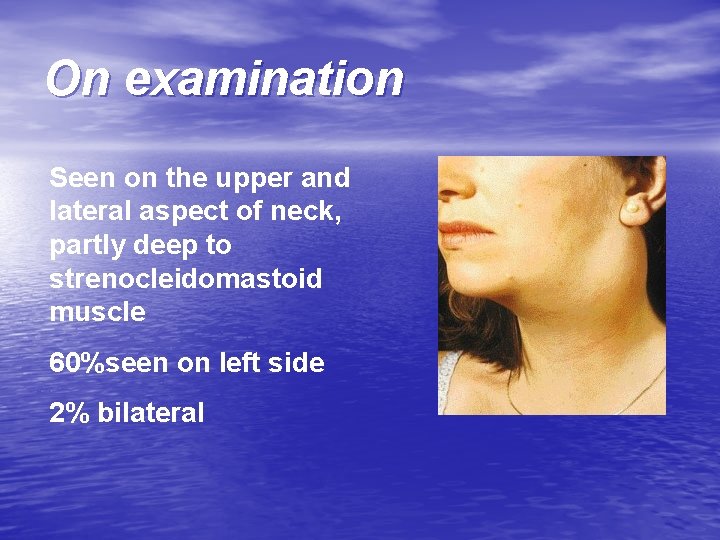
On examination Seen on the upper and lateral aspect of neck, partly deep to strenocleidomastoid muscle 60%seen on left side 2% bilateral
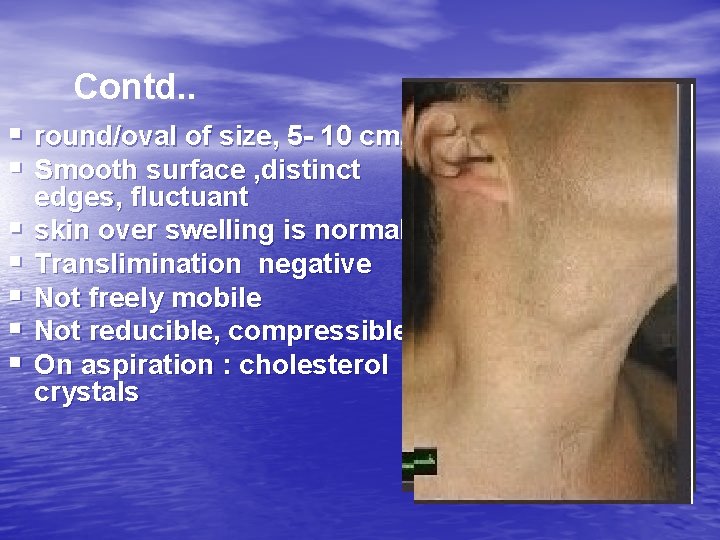
Contd. . § round/oval of size, 5 - 10 cm, § Smooth surface , distinct § § § edges, fluctuant skin over swelling is normal Translimination negative Not freely mobile Not reducible, compressible On aspiration : cholesterol crystals
Complication • Recurrent infection • Brachial fistula formation
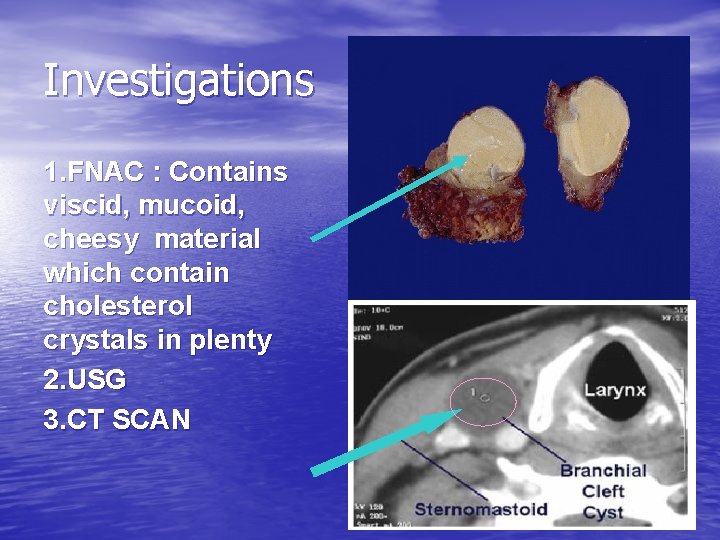
Investigations 1. FNAC : Contains viscid, mucoid, cheesy material which contain cholesterol crystals in plenty 2. USG 3. CT SCAN
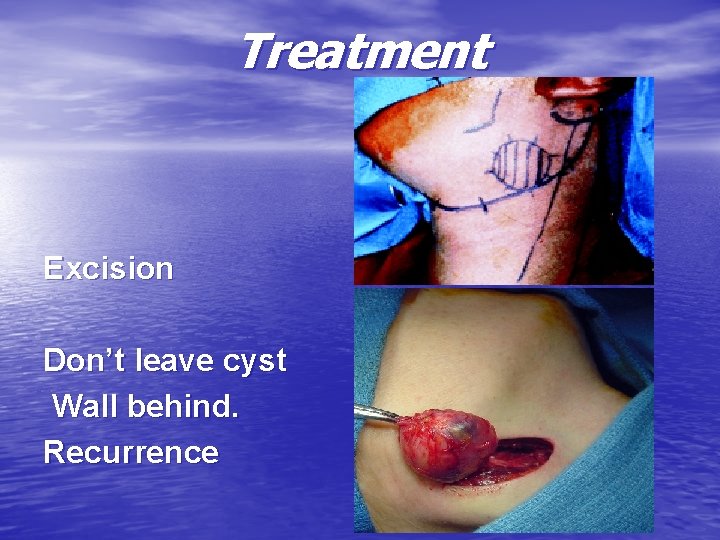
Treatment Excision Don’t leave cyst Wall behind. Recurrence
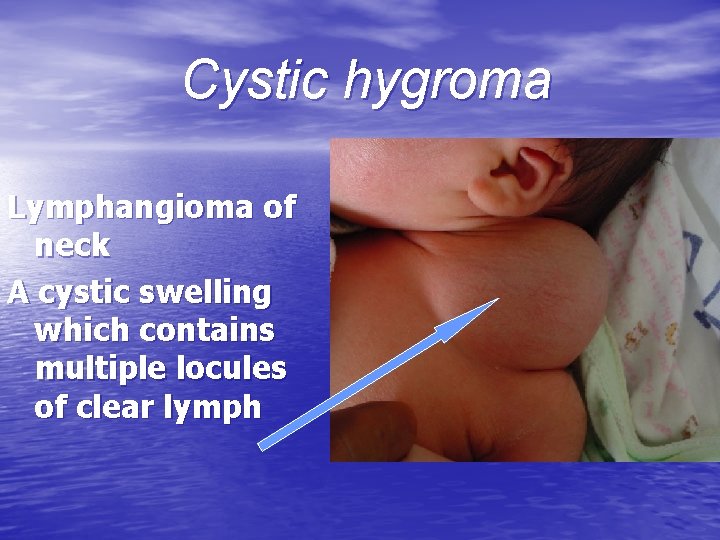
Cystic hygroma Lymphangioma of neck A cystic swelling which contains multiple locules of clear lymph
Embryology _ During embryonic life , by sixth week lymph sacs develop: 6 in number _ They are 1 pair jugular lymph sac 1 pair posterior cisterna chyli Retroperitoneal Sequestration of a portion of jugular sac
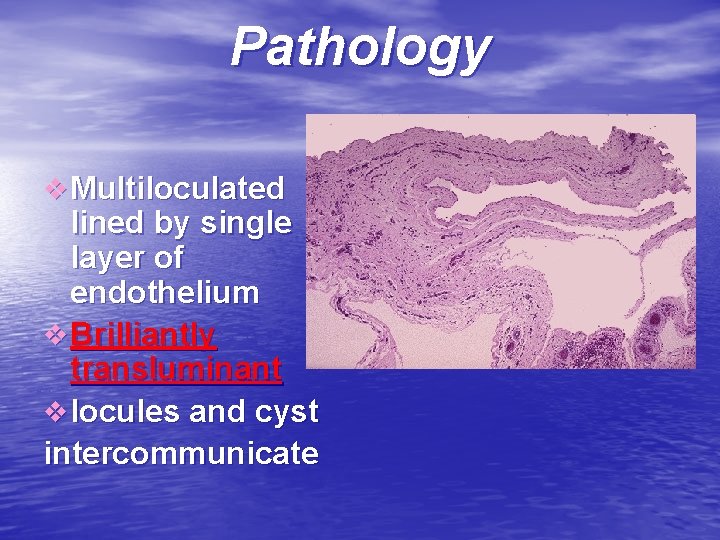
Pathology v Multiloculated lined by single layer of endothelium v Brilliantly transluminant v locules and cyst intercommunicate
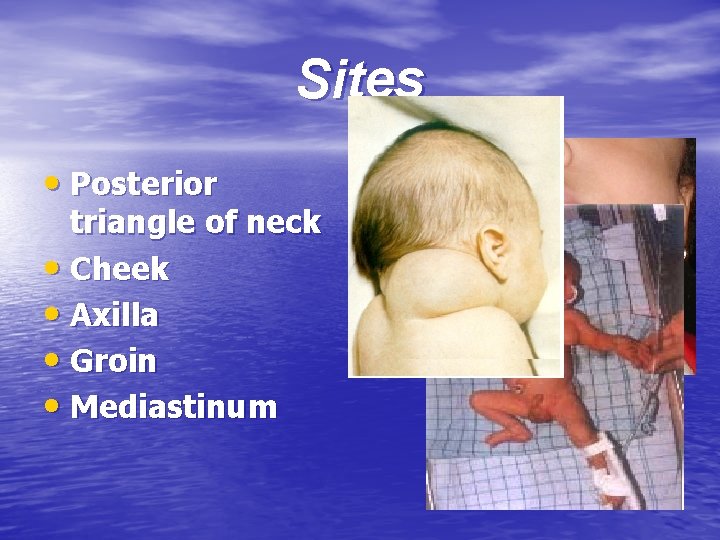
Sites • Posterior triangle of neck • Cheek • Axilla • Groin • Mediastinum
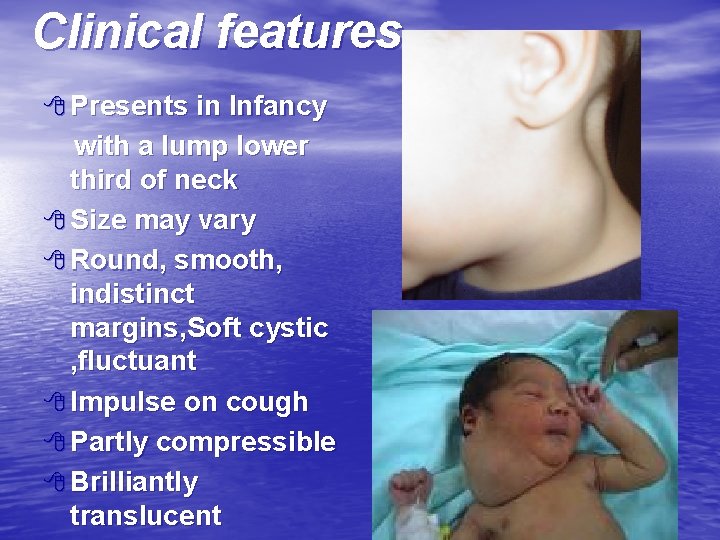
Clinical features 8 Presents in Infancy with a lump lower third of neck 8 Size may vary 8 Round, smooth, indistinct margins, Soft cystic , fluctuant 8 Impulse on cough 8 Partly compressible 8 Brilliantly translucent
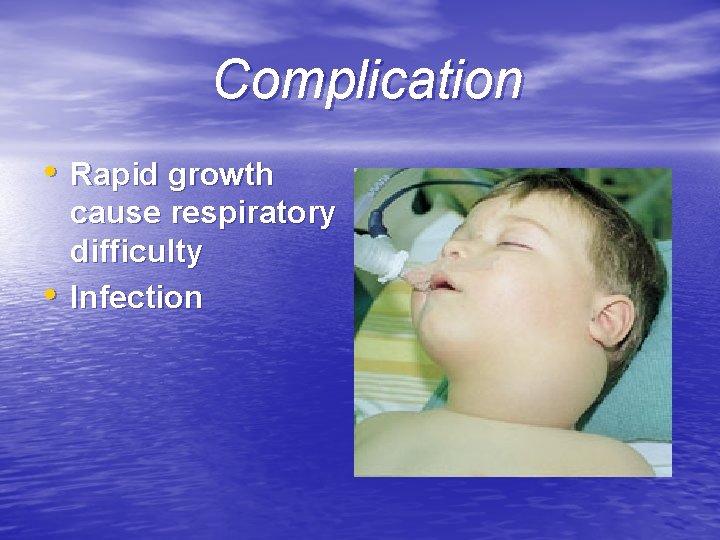
Complication • Rapid growth • cause respiratory difficulty Infection
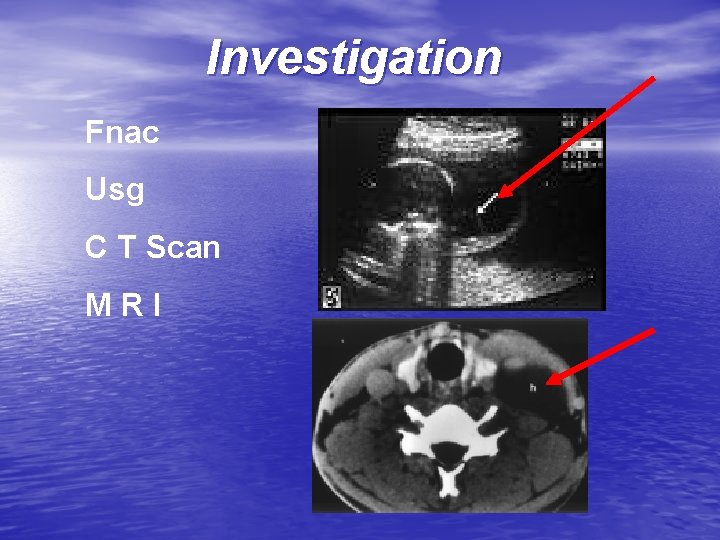
Investigation Fnac Usg C T Scan MRI • usg
Treatment µ Excision µ Previously sclerosants advised: now CI Newer therapy: Streptococcal product : OK 432 µ Recurrence >if incompletely removed µ
Sublingual dermoid cyst • Congenital sequestration dermoid
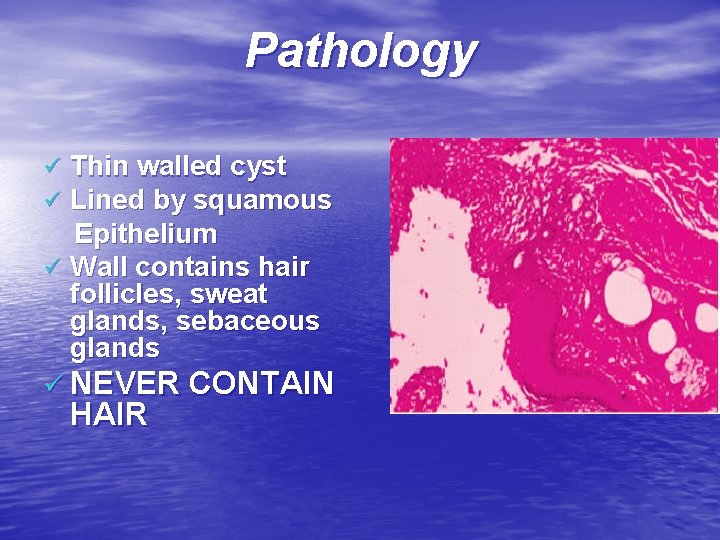
Pathology Thin walled cyst Lined by squamous Epithelium ü Wall contains hair follicles, sweat glands, sebaceous glands ü ü ü NEVER CONTAIN HAIR
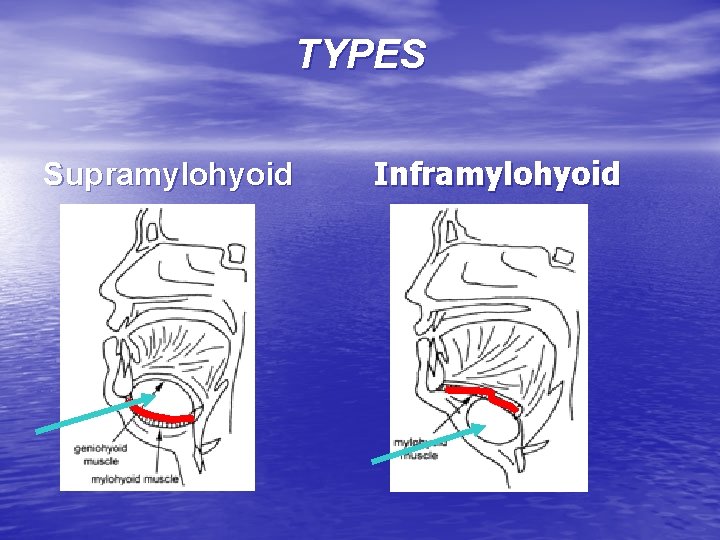
TYPES • MIDLINE: inclusion of • ectoderm in line of fusion of 1 st branchial arch LATERAL : These usually derive from 2 nd branchial cleft
TYPES Supramylohyoid Inframylohyoid
Supramylohyoid • • Midline or to one side of floor of mouth Mucous membrane over is normal Smooth, definite edge, cystic swelling, fluctuation +, No transluminant
Inframylohyoid Occupy submental region or submandibular region _ Bimanually palpable _ Fluctuation + _ No transluminant _ No movement with protrusion of tongue , _
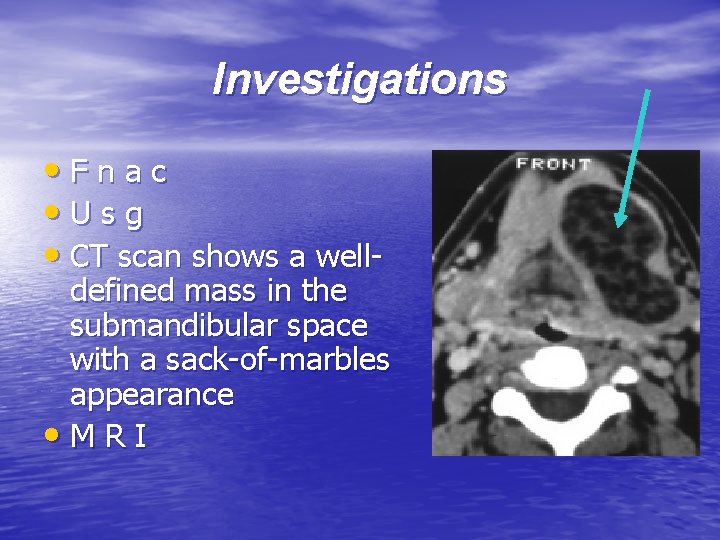
Investigations • Fnac • Usg • CT scan shows a well- defined mass in the submandibular space with a sack-of-marbles appearance • MRI
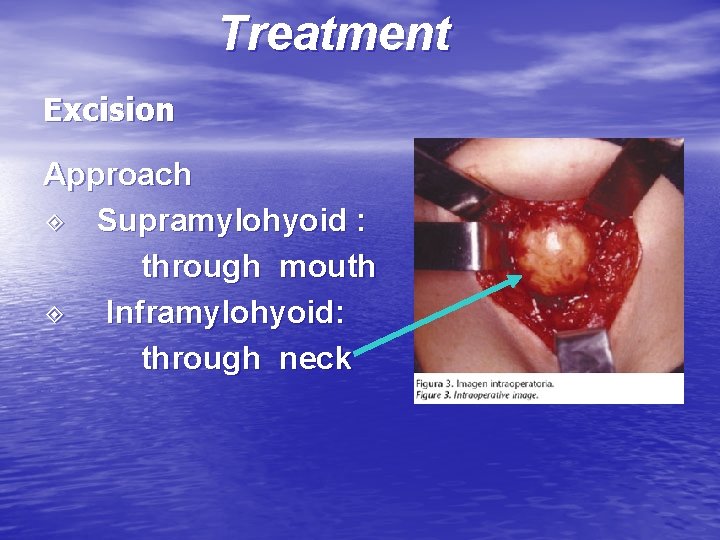
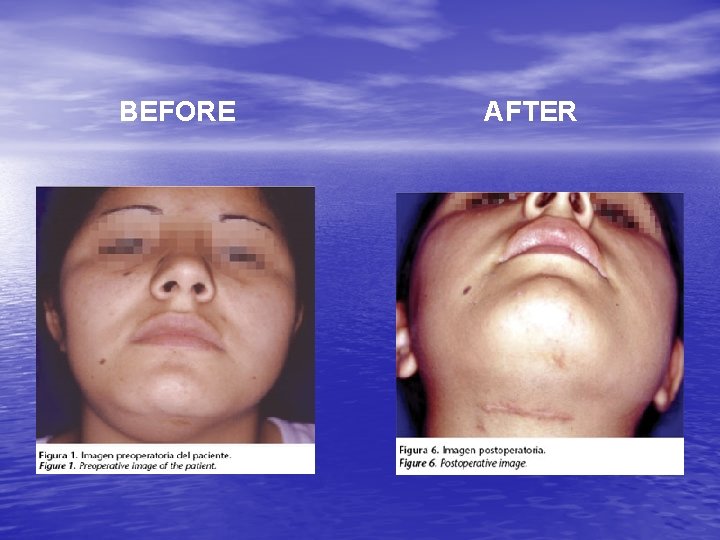
Treatment Excision Approach ◈ Supramylohyoid : through mouth ◈ Inframylohyoid: through neck
BEFORE AFTER
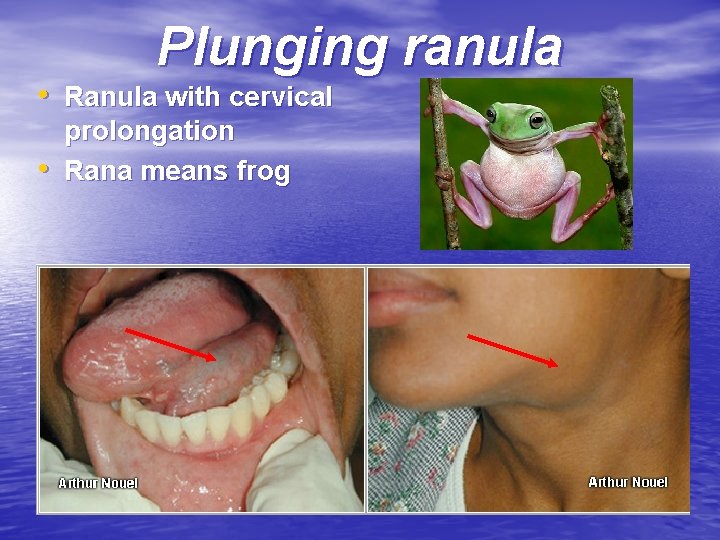
Plunging ranula • Ranula with cervical • prolongation Rana means frog
Etiology ÊObstruction of sublingual salivary glands/ mucous glands Ê usually unilateral
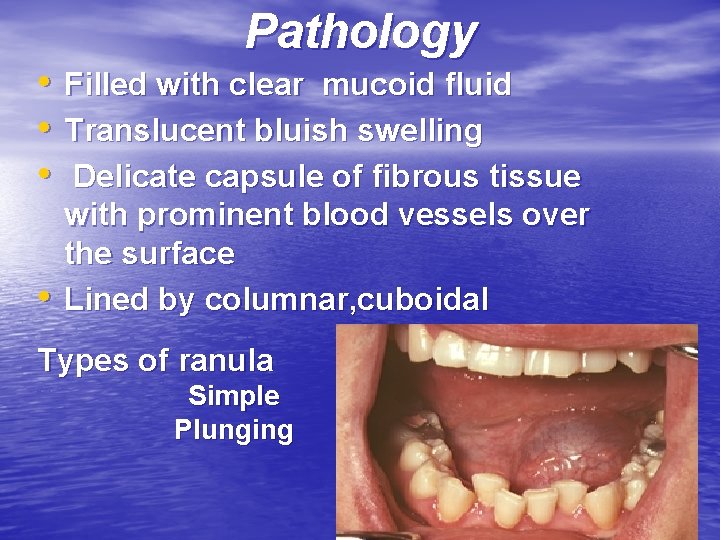
• • Pathology Filled with clear mucoid fluid Translucent bluish swelling Delicate capsule of fibrous tissue with prominent blood vessels over the surface Lined by columnar, cuboidal Types of ranula Simple Plunging
Clinical features • Seen in Children & young adults • Complains of swelling in the floor of • • • mouth, on one side Bluish in colour , blood vessels running over surface Spherical, soft Fluctuation&Translumination positive Mucous membrane can moved over swelling BIDIGITAL PALPATION: cross fluctuation
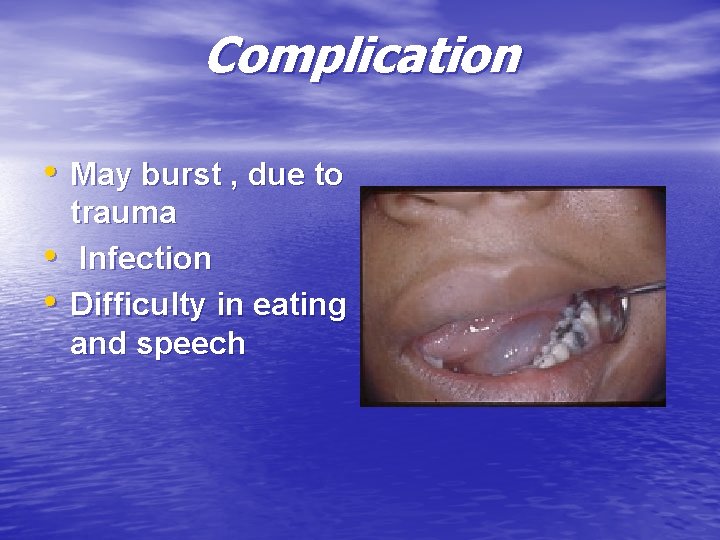
Complication • May burst , due to • • trauma Infection Difficulty in eating and speech
Treatment • Excision • Approach : Through neck/ oral cavity
Cold abscess Abscess which is of tuberculous in origin SOURCE 1. Tuberculous lymphadenitis 2. Tb of cervical spine
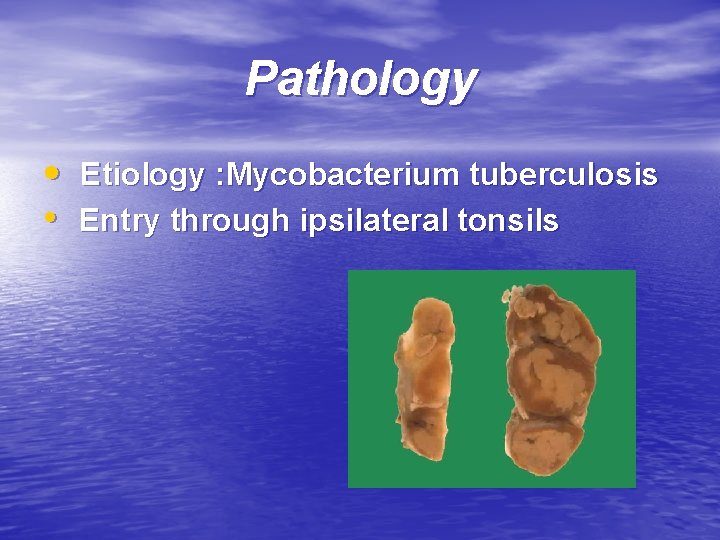
Pathology • Etiology : Mycobacterium tuberculosis • Entry through ipsilateral tonsils
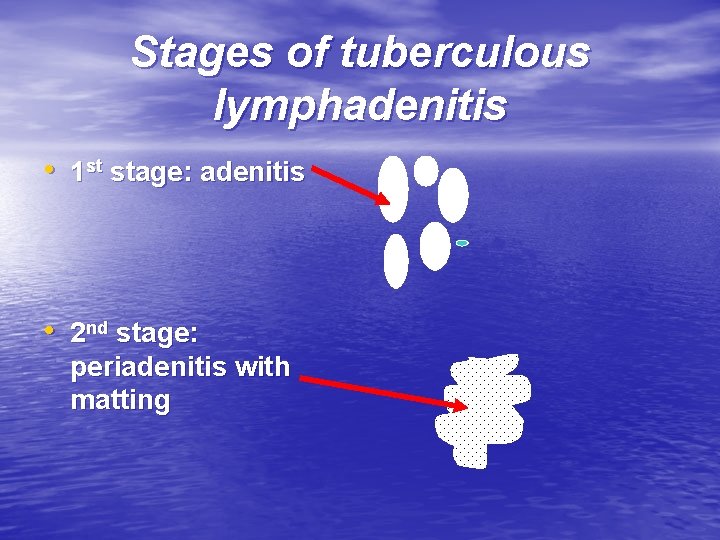
Stages of tuberculous lymphadenitis • 1 st stage: adenitis • 2 nd stage: periadenitis with matting
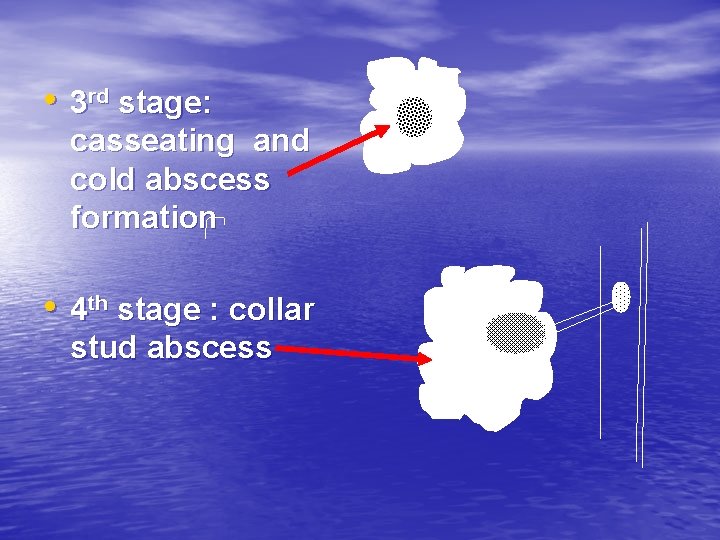
• 3 rd stage: casseating and cold abscess formation • 4 th stage : collar stud abscess
Clinical features • Occur in all age groups more in younger • Previous h/o neck ache • Systemic features: evening rise of temperature, Loss of weight, anemia cough. • Family history+
On examination • Site : • • • anterior triangle: TB lympahadenitis Posterior triangle: TB spine Soft, cystic with indistinct margins Fluctuation+ Other matted nodes may be palpable Skin over swelling: normal Spine examination : must Examine for systemic features
Investigations • Blood • • • Hb: anaemia TC , DC: leucocytosis with lymphocytic predominance ESR Sputum AFB+ Aspiration of abscess: casseous material , no cholesterol crystals 1. Ziehl Niehlson stain 2. culture
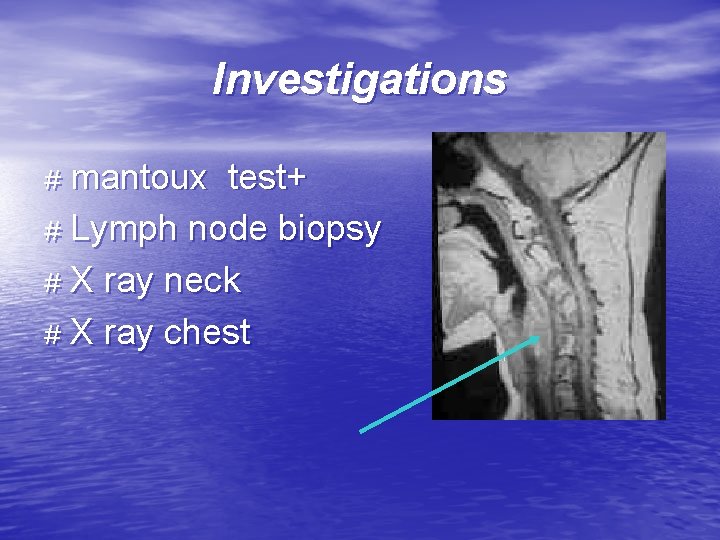
Investigations # mantoux test+ # Lymph node biopsy # X ray neck # X ray chest
Treatment • General management’ • Anti tuberculous treatment Good nutritious food Local management Small abscess: resolve with treatment Large ones : I& D
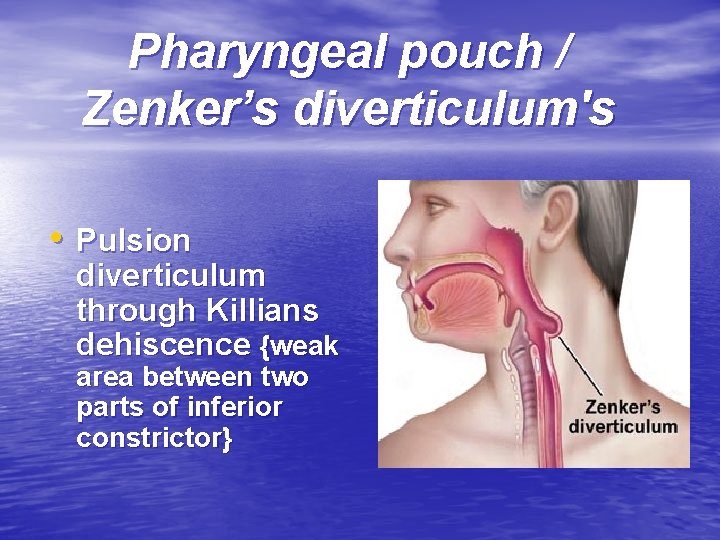
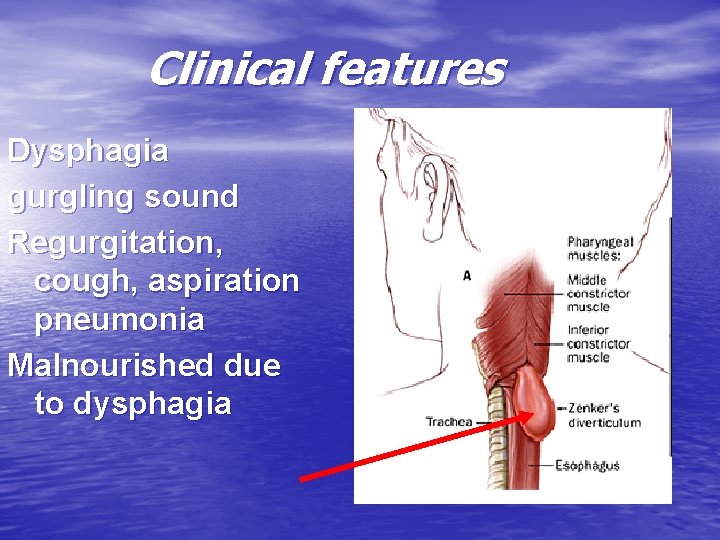
Pharyngeal pouch / Zenker’s diverticulum's • Pulsion diverticulum through Killians dehiscence {weak area between two parts of inferior constrictor}
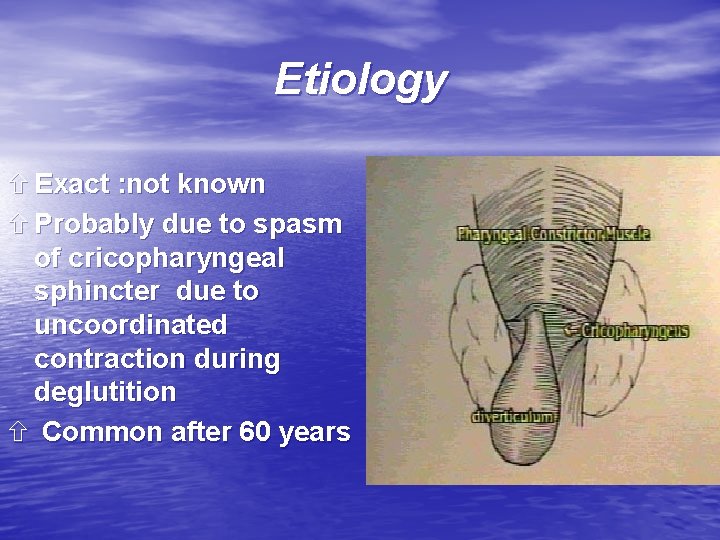
Etiology ñ Exact : not known ñ Probably due to spasm of cricopharyngeal sphincter due to uncoordinated contraction during deglutition ñ Common after 60 years
Pathology • Herniation Starts in midline , first • behind the esophagus , then to left Mouth of sac is wider than esophagus, food enters the sac
Clinical features Dysphagia gurgling sound Regurgitation, cough, aspiration pneumonia Malnourished due to dysphagia
On examination 4 Swelling lies in posterior triangle 4 Globular in shape 4 Soft , cystic, with smooth surface and indistinct margins 4 Can be reduced 4 Fluctuation + 4 Not Transluminant 4 Not mobile
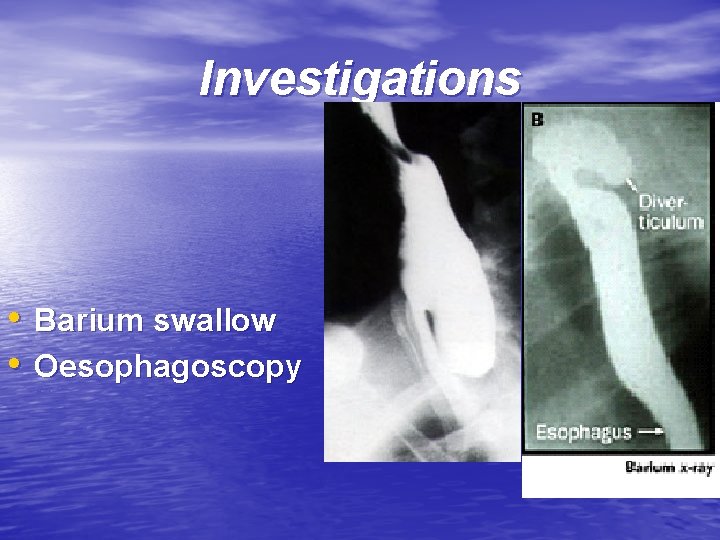
Investigations • Barium swallow • Oesophagoscopy
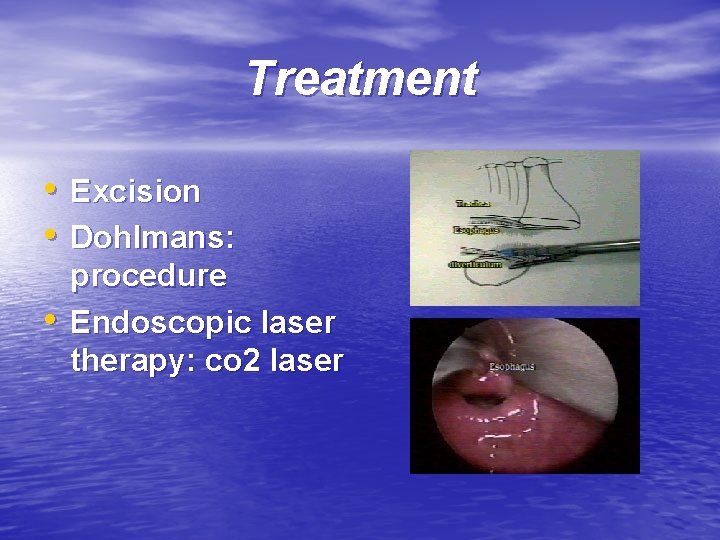
Treatment • Excision • Dohlmans: • procedure Endoscopic laser therapy: co 2 laser
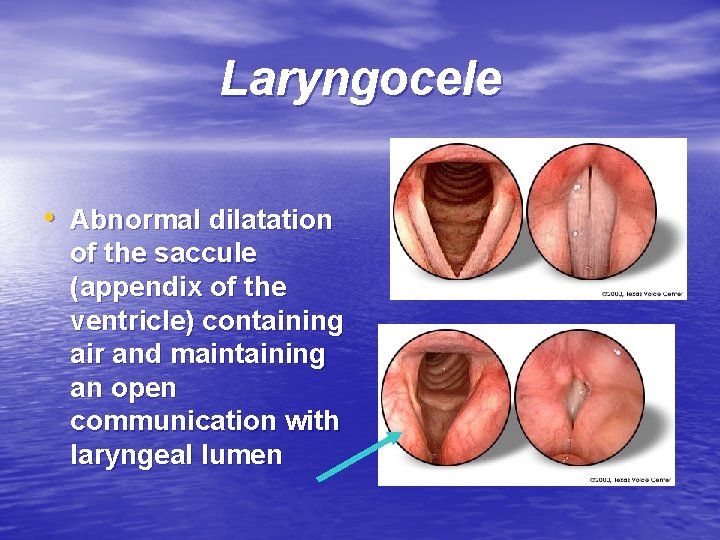
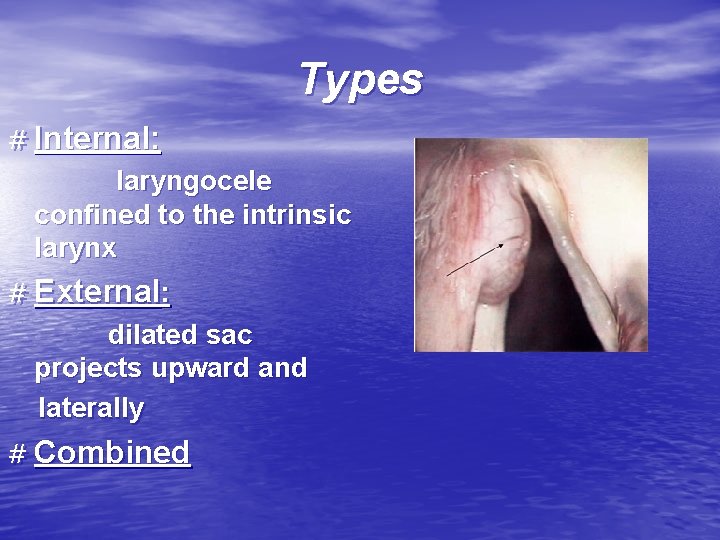
Laryngocele • Abnormal dilatation of the saccule (appendix of the ventricle) containing air and maintaining an open communication with laryngeal lumen normal
Types # Internal: laryngocele confined to the intrinsic larynx # External: dilated sac projects upward and laterally # Combined
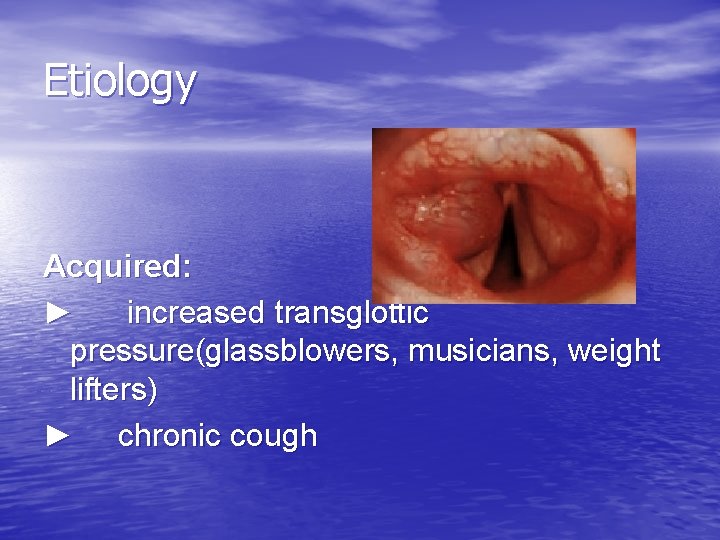
Etiology Acquired: ► increased transglottic pressure(glassblowers, musicians, weight lifters) ► chronic cough
Clinical features # Men >women # Bilateral -25% # Complaints of hoarseness, lateral neck mass, dyspnea, dysphagia, # o/e smooth, soft , ovoid swelling # Become prominent on cough/blow/ valsalva maneuver # Expansile cough impulse + # Moves with swallowing # Tympanic note
Investigation • Indirect laryngoscopy • X-ray soft tissue , lateral and AP with valsalva’s maneuver • CT scan to know the extend of lesion
Treatment • Excision
Subhyoid bursitis • Enlargement of sub hyoid bursa with • • • accumulation of inflammatory fluid Presents as oval swelling in transverse direction Moves up , no movement with protrusion of tongue Soft, cystic, fluctant Not transluminant Treatment is by complete excision
Summary • Cystic swellings of neck can be midline or lateral • Most of cystic swellings are congenital occurring due to the abnormality in the branchial apparatus. They are thyroglossal cyst, branchial cyst, dermoid cyst • Cystic hygroma is due to the sequestration of jugular lymph sac
Summary • Treatment of choice in case of a thyroglossal cyst is SISTRUNK Procedure • Acquired swellings are cold abscess, pharyngeal pouch, laryngocoel, plunging ranula • Surgical excision is the treatment in most of the cases
Thank you