
Peptic Ulcer Disease DR M TALEBI Definition Peptic

Peptic Ulcer Disease DR. M. TALEBI
Definition Peptic Ulcer A benign, localized defect in the mucosa of any part of the gastrointestinal tract which is exposed to acid and pepsin. & Differentiate ulcer from erosion * Erosion is superficial mucosal defect. distinguish * Ulcer extend through the muscularis mucosa into the submucous or muscularis layer.

Occurs: Peptic Ulcer . Duodenum ( commonly). Stomach (commonly). Oesophagus (occasionally). Jejunum (occasionally) after surgical anastomosis to the stomach. Meckel’s diverticulum with ectopic gastric mucosa.

Epidemiological aspects Peptic ulcer * It occurs in up to 15% of the population at some time. * It is commoner in men. * The incidence increases with age. * The frequency of ulcer disease has marked temporal, geographical and racial variations. . Fallen over the last few decades – in most Western countries. . Increased incidence of ulcer complications
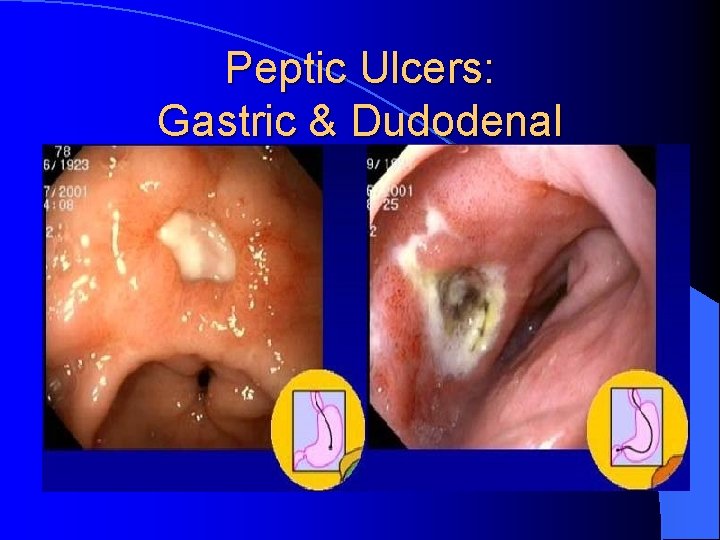
Peptic Ulcers: Gastric & Dudodenal
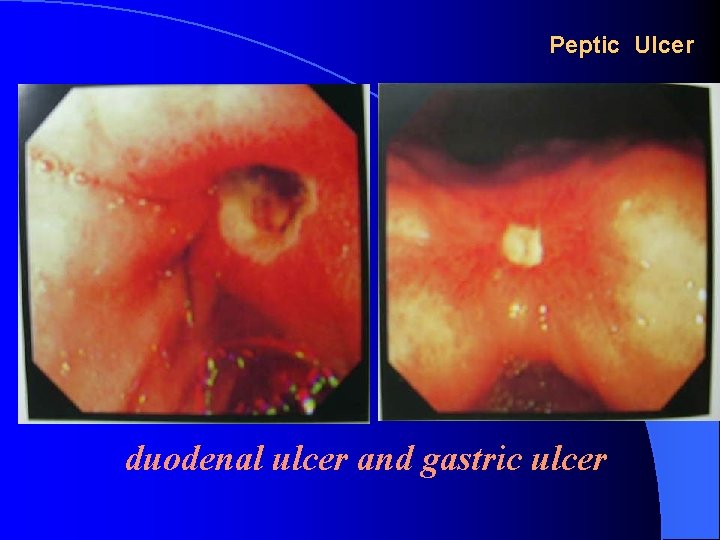
Peptic Ulcer duodenal ulcer and gastric ulcer
Epidemiological aspects Peptic ulcer * In most countries: . DU > GU. But in Japan, GU are more common. . DU, GU are more common in men than women. . But in Australia, women are more prone than men to develop GU. * The prevalence of both GU and DU. Increases with age. On average, patients with GU are ten years older than ones of DU. There is often a positive family history of peptic ulcer.

Causes Peptic ulcer l The formation of peptic ulcer require the presence of increased aggressive factors ( including H. p, acid and pepsin, NSAID, alcohol, et. )and reduced defensive factors (including mucus/bicarbonate barrier, mucosal blood flux, prostaglandin, cellular metabolism) for its formation. l In normal situation, the gastroduodenal mucosa can resist the aggressive factors and keep the mucosal integrity. But if there is an imbalance between aggressive factors and defensive factors, peptic ulcers would occur.

Causes Peptic ulcer * Common forms of peptic ulcer. Helicobacter pylori. NSAID (no-steroidal anti-inflammatory drugs). Acid and pepsin. Stress * Uncommon specific forms of peptic ulcer. Heredity. Abnormal gastroduodenal locomotion. Other risk factors: Smoking Viral infection Diet
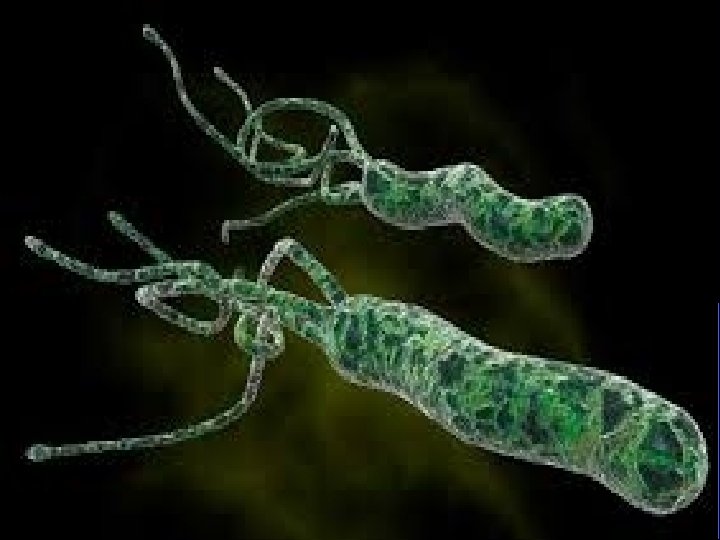
1. Helicobacter pylori (H. p) ü the most important factors peptic ulcer . approximately 70% of all GU. approximately 90% of all DU. Deracination of H. p would boost the healing of ulcer. ü How can H. p destroy local mucosal defective/repaired mechanism? 1. colonize the gastric mucosa. 1) urease 2) motility 2. increased acid secretion

peptic ulcer ü Why? 1)urease H. p can excrete urease, which produces ammonia from urea and raises the p. H around the bacterium. So urease may be very important in the early colonization by creating a protective nonacid microenvironment shielding the organism from gastric juice. 2)motility The flagella can help H. p penetrate the mucosa layer and adhere to the gastric epithelial layer.

peptic ulcer 2. increased acid secretion First, the H. p infection would stimulate the local inflammatory reaction and immune reaction, that can reduce the quantity of D cells, which is a kind of secretion cells. It can secrete somatostatin that can inhibit the secretion of gastric juice. Secondly, the urea increases the p. H level around the gastric mucosa, local gastric cells would secrete overfull acid to decrease the local p. H. So the total secretion of acid is increased. Finally, the p. H level is decreased, and the gastric or duodenal will suffer from overfull acid.

2. NSAID peptic ulcer After H. p infection, NSAID is the next important cause of altered mucosal defence leadimg to peptic ulceration in the presence of activated pepsin. Because NSAID can reduce the secretion of prostaglandin. Prostaglandin of series E can accelerate blood flux. Only enough blood supply can assure the normal protective effect. So it also play a major role in the maintenance of gastroduodenal defence mechanism. With the decreased defensive factor, the aggressive factor of acid is increased. So the ulceration occurs.

3. Acid and pepsin peptic ulcer Finally, the formation of peptic ulcers would rely on the digestive effect of acid and pepsin. Pepsin can decompose protein molecule, so H. p can invade mucus. The biologic activity of pepsin is depended on the p. H value. When local p. H value elevates to 4, pepsin can’t work well. So we often say that “No acid-peptic active, no ulcer. ” Gastric acid is the keyword of the formation of peptic ulcer. " Duodenal ulcer: increased " Gastric ulcer: normal or decrease 4. stress High stress can stimulate vagus nerve, which can result in high secretion of acid.
5. Heredity peptic ulcer Patients with peptic ulcer often have a family history of ulcer, particularly the patient with DU that develop below the age of 20 years. Some studies show that blood group O have a high risk to developing peptic ulcer, but the pathogenic significant of these finding is uncertain. 6. Abnormal gastroduodenal locomotion DU— quick gastric empty → overfull acid load food storage GU— movement obstruction → reflux digestive liquid 1. High acid secretion 2. Aggravating H. p infection 3. Increased bad effect of NSAID

7. Other risk factors: peptic ulcer 1) Smoking is an increased risk of peptic ulcer. Smoking can induce the formation of ulcer, affect the healing of ulcer, accelerate ulcer recurrence, and increased complication of ulceration. But the mechanism isn’t clear. Maybe it has a relation with acid secretion, bile reflux, and decreased prostaglandin. 2) Diet Tea, coffee, alcohol can result in high secretion of acid. 3) Viral infection

Pathology peptic ulcer 1. Location The localization of ulcers impacts pathophysiologic and clinical features. * DU,95% occuring in the duodenal bulb, anterior > posterior * GU, occurs anywhere in the stomach. Commonly GU occurs in the antrum near the angularis, just distal to the junction of the body and antral mucosa on the lesser curve. . Frequently proximal GU associated with active gastritis.

2. Quantity and size ü ü ü peptic ulcer QUANTITY: Usually single, although 5 -20% may be multiple SHAPE: Round or elliptical SIZE: Usually diameter of ulcer is under 10 mm, GU >DU. giant ulcer ---DU >2 cm, GU>3 cm 3. Character Benign ulcer: yellow or grayer fibrous exudation the bottom ----- clean the side ------ regular Malign ulcer: black fibrous exudation the bottom-----dirty the side ------atactic

Clinical features ü Common characters of peptic ulcer: Peptic ulcer chronicity periodicity rhythmicity * Symptoms: . Abdominal pain and discomfort (the most important symptoms). Vomiting. Other: may be present, but of less clinical significance. – weight loss (GU or suspicion of GC) or gain (DU, eats to ease the pain) – nausea or anorexia – heartburn (common) – acid regurgitation – constipation

Clinical features & . . peptic ulcer The history is unreliable for separating DU from GU Abdominal pain or discomfort (very important) Epigastric pain, often quite localized, is a frequent symptom. Site – usually epigastric or the right or left of the midline. DU – related to meals: being hungry, ½ to 3 hours after meals be relieved by food, milk, antacids. pain again , before next meal – often nocturnal: to wake the patient up at night. GU – pain is worse during the day – pain is precipitated by food relieved before next meal

Clinical features Peptic ulcer * Abdominal pain or discomfort (very important). Persistent and severe pain should be considered complications of perforation or penetration into other organs. Initially: localized and the patient points a single finger to the site of the pain. As the pain becomes more severe: it becomes more diffuse and radiates to the back in the interscapular region. . Radiation - an index of the severity of pain - imply the penetration of the ulcer through the gastric or duodenal wall and invasion of other organs - pancreatic involvement Back

Clinical features Peptic ulcer Some questions will be noticed: * The majority of patients with abdominal pain will turn out not to have ulcer disease. * Many ulcer patients present with atypical pains or without pains. * If no special investigations, ulcer is impossible to be diagnosed. * Although DU patients have typically pain (e. g. hunger, after meals, better responses to medical treatment), the nature of the symptoms does not differentiate between DU ? GU
Clinical features Peptic ulcer *Vomiting: the vomiting with ulcer may have one of three causes. . Induced by the pain, especially GU. . Due to gastric outlet obstruction. . Self-induced, if patient’s vomiting eases the pain. Atypical ulcers. Giant ulcers. Postbulbar ulcers. Peptic ulcers in the elderly . Pyloric channel ulcers. Multiple ulcers. Silence peptic ulcers
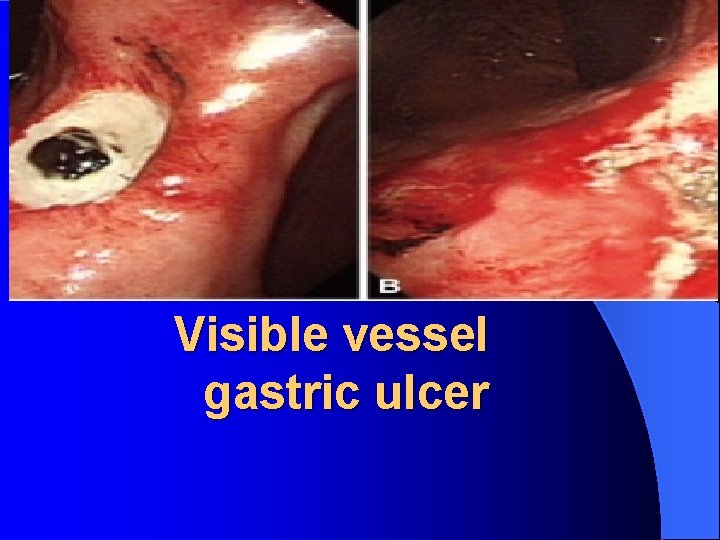
Visible vessel gastric ulcer
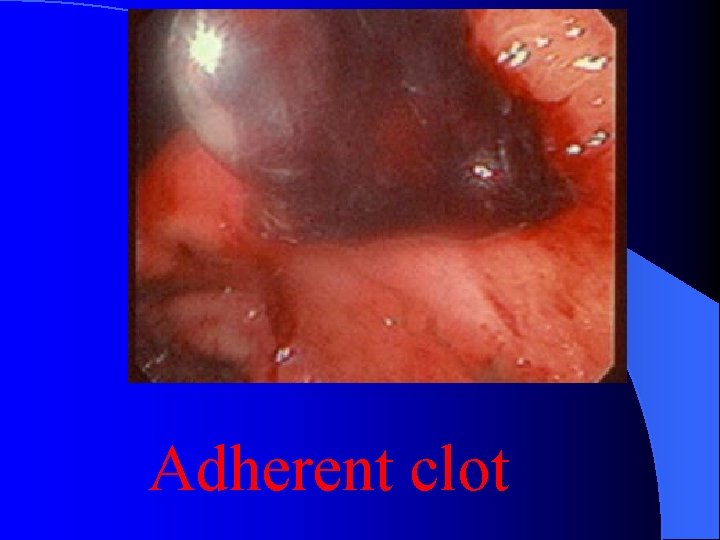
Adherent clot
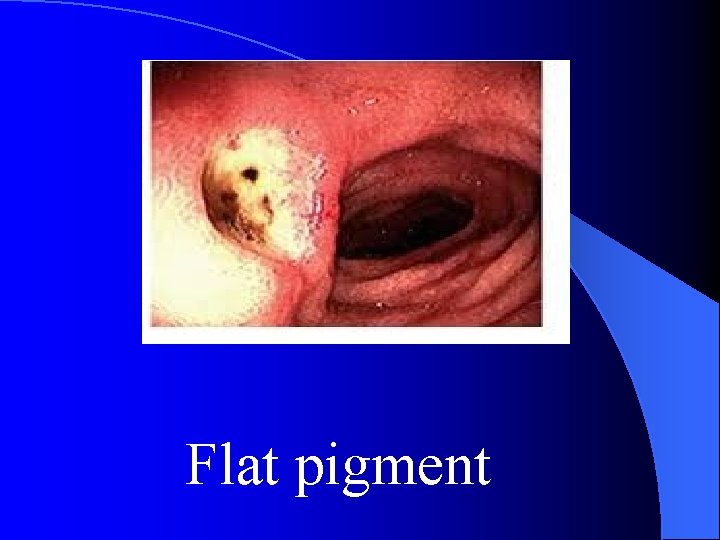
Flat pigment
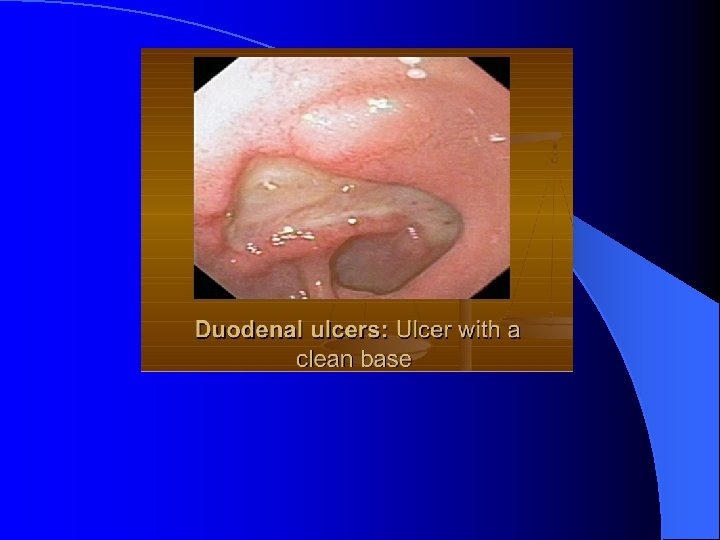
Atypical ulcers Peptic ulcer Giant ulcer - DU > 2 cm, GU > 3 cm * Having a prolonged, typical history, or few previous symptoms. * No distinguishing pathophysiologic features. * Commonly it occurs in association with NSAID consumption. * Giant DU or prepyloric ulcers are associated with end-stage renal failure. * Character of giant DU: . On the posterior wall. It’s often associated with pain radiating to the back. Frequently it is complicated by bleeding, posterior penetration, pyloric obstruction * Giant GU: May carry an increased risk of harboring carcinoma

Atypical ulcers Peptic ulcer Pyloric channel ulcers Pain: It hasn’t typical periodical and rhythmicity abdominal pain. It occurs shortly after eating, It is poor alleviative by antacids * It has a high risk of vomiting, pyloric obstruction, penetration, and perforation. • 图
Atypical ulcers Peptic ulcer Postbulbar ulcers * They were found in 10 % of a necropsy series。 * It beyonds the second portion of the duodenum。 * It has a higher rate of bleeding. * The symptoms are same with DU, but frequently pain is nocturnal and can radiate to back. * It has poorly response to the medical therapy. * Both endoscopy and radiography may miss diagnosis; only finding an area of narrowing or apparent spasm.
Atypical ulcers Peptic ulcer Multiple ulcers * Multiple, simultaneous ulcers occur in 2% to 20% of cases * Several features have been associated with multiple DU, which may be markers of an increased ulcer diathesis, including. cigarette smoking. deformity of the duodenal bulb. Zollinger-Ellison syndrome * Aspirin use is another cause of multiple ulcers * They are often clustered together
Atypical ulcers Peptic ulcer in elderly patients Peptic ulcer * The proportion of GU catches up with DU in the elderly. * Consumption NSAIDs increased the risk of complications * The manifestation of peptic ulcer is more likely to be silent. * The atypical character : atactic epigastric pain, nausea, vomiting, weight loss, anemia * Their ulcers tend to heal more slowly with ulcer therapy than younger counterparts. * We need differentiate it from gastric cancer.

Atypical ulcers Peptic ulcer Silence ulcer * 15 -35% peptic ulcers may be silence ulcers. * Found only. by gastroscopy or barium meal. Complications of bleeding or perforation * It can take place in every age, but it is common in the elderly. * Consumption of aspirin may cause silence ulcer (30 -40%).
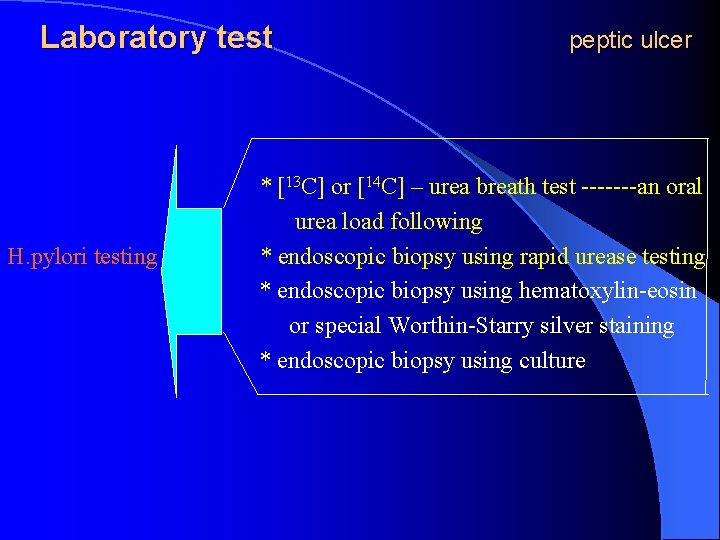
Laboratory test H. pylori testing peptic ulcer * [13 C] or [14 C] – urea breath test -------an oral urea load following * endoscopic biopsy using rapid urease testing * endoscopic biopsy using hematoxylin-eosin or special Worthin-Starry silver staining * endoscopic biopsy using culture
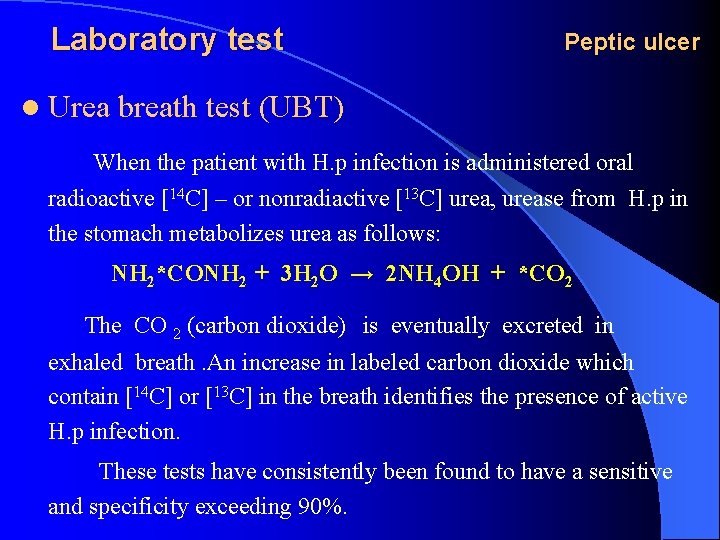
Laboratory test l Urea Peptic ulcer breath test (UBT) When the patient with H. p infection is administered oral radioactive [14 C] – or nonradiactive [13 C] urea, urease from H. p in the stomach metabolizes urea as follows: NH 2*CONH 2 + 3 H 2 O → 2 NH 4 OH + *CO 2 The CO 2 (carbon dioxide) is eventually excreted in exhaled breath. An increase in labeled carbon dioxide which contain [14 C] or [13 C] in the breath identifies the presence of active H. p infection. These tests have consistently been found to have a sensitive and specificity exceeding 90%.

Laboratory test l Rapid urease testing (RUT) Peptic ulcer As mentioned earlier, H. p produces large amounts of the enzyme urease, which lead to a p. H change in the microenvironment of the organism. Biopsies obtained at the time of endoscopy are placed on the reaction stripe. If H. p is present, urease causes an increase in environment p. H and a consequent color change in the test medium. l Endoscopic biopsy using hematoxylin-eosin or special Worthin-Starry silver staining and culture are not sensitive or specificity, especially the culture which is slow and expensive, so they are not very useful in clinical.

Diagnosis peptic ulcer Analyse of the history is very important. If the patient has a typical epigastric pain, it’s a very important clue. But when the clinical feature isn’t typical, we should use some examine methods to diagnose. Upper gastrointestinal radiography * using double-contrast barium meal * Barium is within an ulcer Niche (round, oval, surrounded by smooth mound of edema) * Folds radiating to the crater * Attention: 1. Shallow lesions < 0. 5 cm are difficult to detect. 2. Active or acute gastrointestinal haemorrhage is the tabu of it.

Diagnosis Endoscopy. peptic ulcer * Application: It can diagnose the benign or malignant ulcer, H. p infection, upper gastrointestinal haemorrhage and obtain the biopsy specimens * Virtue: It’s a sensitive, specific, safe method and allowing direct inspection and biopsy. * DUs are nearly always benign * How to differentiate benign GU from gastric cancer? 1. multiple biopsy specimens are necessary 98% of cancers can be detected 2. the showing of them under the endoscopy are different. .

Differential diagnosis Functional dyspepsia (indigestion) peptic ulcer . It’s common in young women. . It doesn’t has structural or biochemical cause, the patient is normal or only has slight gastritis. . Clinical features: 1. Nausea, belching, premature satiety, bloating and abdominal distension 2. Sometimes it likes ulcers. . Only endoscppy and radiography can differentiate ulcers from functional dyspepsia.
Differential diagnosis peptic ulcer Chronic cholecystitis and cholelithiasis. Pain – at the right upper quant – radiating to the right upper back – attacks induced by heavy or fat food – associated with fever or jaundice. Differential approach by – B type ultrasonography – Endoscopic retrograde cholangiopancreatography (ERCP)

Differential diagnosis peptic ulcer Gastric carcinoma. Clinical features: 1. Elderly patient is often with shorter presenting history 2. Complain of a continuous pain is increased by food. 3. In later stage , the patient will have weight loss, early satiety, anorexia, nausea, vomiting. . It’s difficult for us to differentiate GU from gastric ulcers, the only useful way is endoscppy and radiography , especially endoscppy, which can take biopsy. . Key way: Endoscopy (repeat, follow-up)
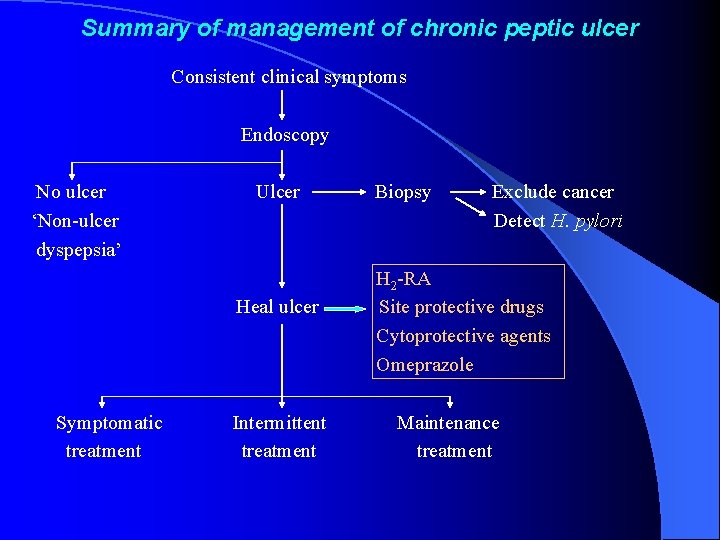
Summary of management of chronic peptic ulcer Consistent clinical symptoms Endoscopy No ulcer ‘Non-ulcer dyspepsia’ Ulcer Heal ulcer Symptomatic treatment Intermittent treatment Biopsy Exclude cancer Detect H. pylori H 2 -RA Site protective drugs Cytoprotective agents Omeprazole Maintenance treatment

Complications Peptic ulcer l Hemorrhage l Perforation l Obstruction l Canceration * Hemorrage is the most common complication * Perforation is the most lethal complication.

Complications Peptic ulcer Hemorrhage * Haemtemesis: Patients with haematemesis are more severe than ones with melaena alone. * Melaena: The black tarry melaenic stools distinguish from bright red rectal bleeding colonic or perianal lesions the greyish-greenish stool by using of iron supplements
Complications Peptic ulcer Management * Assessment of severity * Resuscitation * Diagnosis of the cause of haemorrhage * Observation * Specific treatment
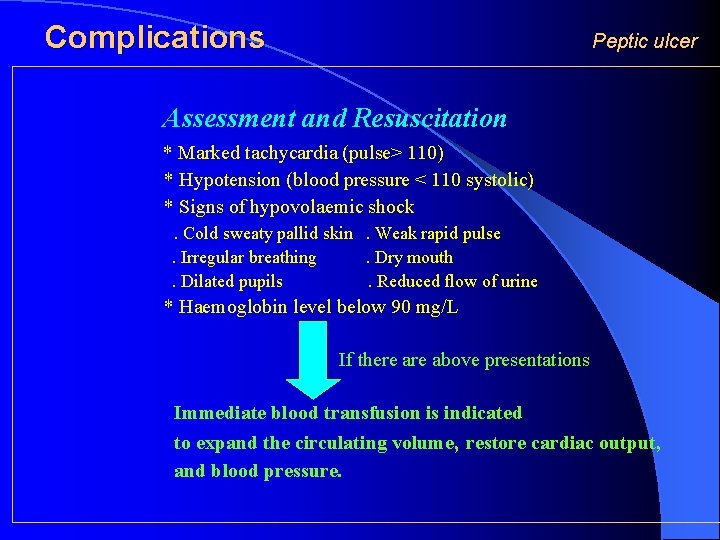
Complications Peptic ulcer Assessment and Resuscitation * Marked tachycardia (pulse> 110) * Hypotension (blood pressure < 110 systolic) * Signs of hypovolaemic shock. Cold sweaty pallid skin. Weak rapid pulse. Irregular breathing. Dry mouth. Dilated pupils. Reduced flow of urine * Haemoglobin level below 90 mg/L If there above presentations Immediate blood transfusion is indicated to expand the circulating volume, restore cardiac output, and blood pressure.

Complications Peptic ulcer Only when the haemodynamic status of the patient is stable, we should attempt to diagnose the cause of the bleeding. Causes * Duodenal ulcer - approximately 40% * Chronic gastric ulcer - 20% * Acute ulcers - 20% with analgesic ingestion (NSAID) * Oesophageal varices - 10% * Other 10% causes. Mallory-Weiss lesions: Violent vomiting causes the tearing of the tissues around the junction of the gastric-oesophagus resulting in bleeding. Reflux oesophagitis. Gastric tumours Diagnosis Exact diagnosis using endoscopy is essential

Complications Peptic ulcer Observation * All patients should be in an intensive care ward of hospital * Noting any further haematemesis or melaena * Vital signs should be monitored at least hourly * Haemoglobin level estimated twice daily until the patient is stable * Central venous monitoring is indicated in elderly subjects * Continuous gastric aspiration is helpful in detecting continued or recurrent bleeding * Indications continued bleeding or rebleeding: - haematemesis - the aspiration of fresh blood from the stomach - significant changes in the pulse, blood pressure, central venous pressure - a marked drop in haemoglobin level
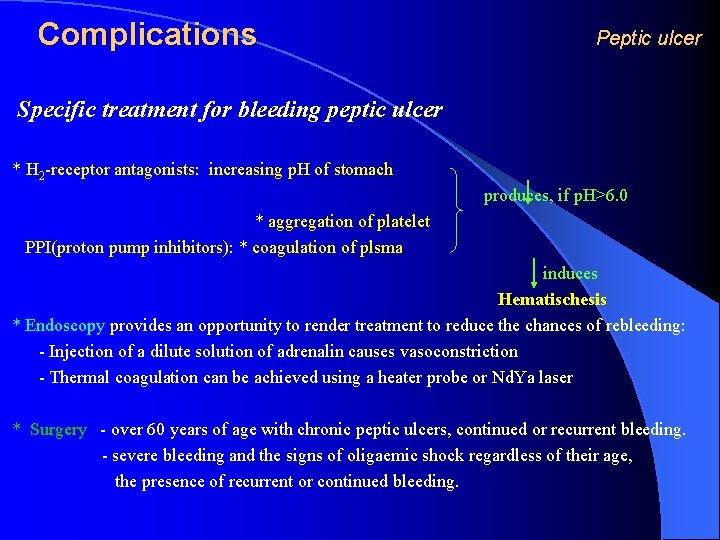
Complications Peptic ulcer Specific treatment for bleeding peptic ulcer * H 2 -receptor antagonists: increasing p. H of stomach produces, if p. H>6. 0 * aggregation of platelet PPI(proton pump inhibitors): * coagulation of plsma induces Hematischesis * Endoscopy provides an opportunity to render treatment to reduce the chances of rebleeding: - Injection of a dilute solution of adrenalin causes vasoconstriction - Thermal coagulation can be achieved using a heater probe or Nd. Ya laser * Surgery - over 60 years of age with chronic peptic ulcers, continued or recurrent bleeding. - severe bleeding and the signs of oligaemic shock regardless of their age, the presence of recurrent or continued bleeding.
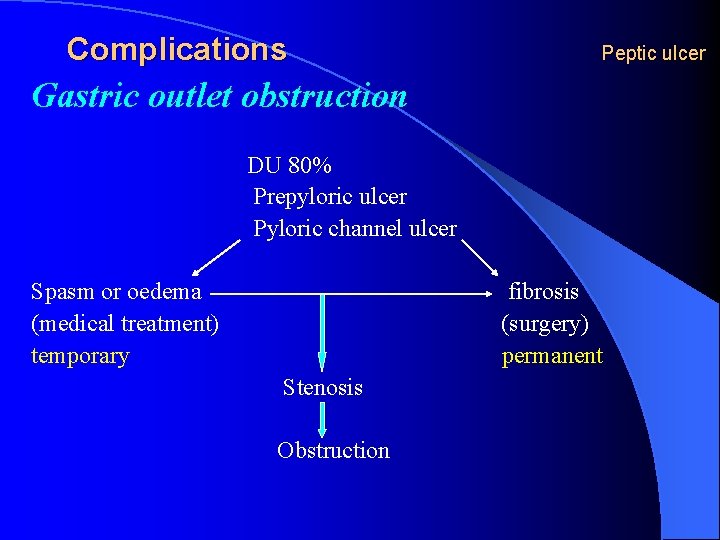
Complications Peptic ulcer Gastric outlet obstruction DU 80% Prepyloric ulcer Pyloric channel ulcer Spasm or oedema (medical treatment) temporary fibrosis (surgery) permanent Stenosis Obstruction

Complications Peptic ulcer Gastric outlet obstruction Clinical presentation * Symptoms . Vomiting: stale food recognized which consumed > 5 hours. Alkalosis. Sodium and potassium depletion. Weight loss * Physical signs . Succussion splash and visible peristalsis (by distended stomach) * Diagnosis . endoscopy gastrointestinal. radiography
Complications Peptic ulcer Gastric outlet obstruction Treatment. Initial treatment includes fluid and electrolyte replacement . Normal saline supplemented with potassium is given intravenously. Gastric distension is alleviated by nasal gastric suction. H 2 -RA or Omeprazole are given intravenously. If obstruction due to severe fibrotic strictures and carcinoma require surgery

Complications Peptic ulcer Perforation The sudden pouring of acid content into the peritoneal cavity . severe abdominal pain. shock. vomiting. marked abdominal rigidity. absent bowel sound. air under the diaphragm shown by X-ray examination Treatment- operation should be performed as soon as possible after perforation

Complications Peptic ulcer Gastric carcinoma * 1 -2% GU only * Warning. Long and chronic history of GU. Refractory GU. > 45 y. Ulcerated cancer can heal just only ulcer area but cancer; therefore, endoscopy+biopsy+follow up * Notice !. Up to 5% of GU being benign on radiological and endoscopic criteria turn out to be malignant. . All GU should be biopsied. . All GU must follow up to healing.

Treatment peptic ulcer * * * Symptom relief Initial healing The refractory ulcer Long – term treatment Management of complications Surgery Medical treatment. H 2 -RA (Histamine 2 – receptor antagonits). PPI (Proton pump inhibitors). Protective drugs: Sulcralfate, Bismuth, Prostaglandins. Therapy of H. pylori

Treatment - Symptom relief peptic ulcer * Pain relieved by antacids or H 2 – RA occasionally * Diet. No dietary restrictions are required. Milk – relieves ulcer pain , likely antacid – stimulates further acid secretion – excessive milk ingestion can theoretically be harmful. Smoking, NSAID, Aspirin, Alcohol, and Paracetamol should be avoided if possible * Stress or hard work have no an adverse influence on peptic ulcer * Modify exacerbating factors such as alcohol, NSAID, et al.
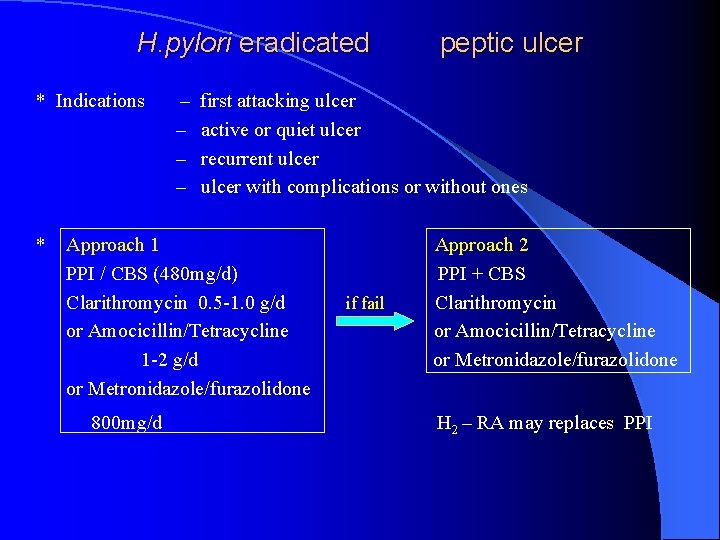
H. pylori eradicated * Indications – – first attacking ulcer active or quiet ulcer recurrent ulcer with complications or without ones * Approach 1 PPI / CBS (480 mg/d) Clarithromycin 0. 5 -1. 0 g/d or Amocicillin/Tetracycline 1 -2 g/d or Metronidazole/furazolidone 800 mg/d peptic ulcer if fail Approach 2 PPI + CBS Clarithromycin or Amocicillin/Tetracycline or Metronidazole/furazolidone H 2 – RA may replaces PPI

Treatment - PPI peptic ulcer * PPI (Proton Pump Inhibitors) block H+ - K+ - ATPase of the gastric parietal cell (GPC) (hydrogen/potassium adenosine triphosphate enzyme) inhibit H+ in exchange for K+ of the gastric parietal cell * Omeprazole Lansoprazole Pantoprazole Rabeprazole * Side effections 20 mg 30 mg 40 mg 10 mg p. o. Bid Bid bid . Headaches. Pruritus H+ of GPC X gastric lumen decrease gastric acid 7 d 7 d. Diarrhoea. Dizziness . Rashes. Others
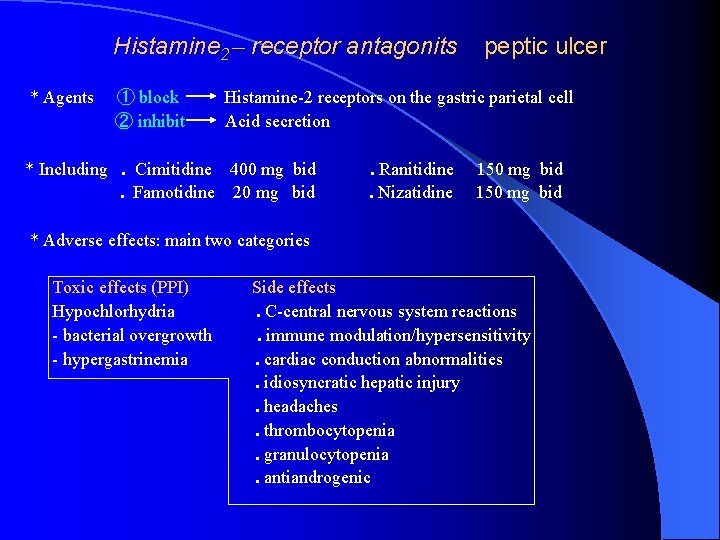
Histamine 2 – receptor antagonits * Agents ① block ② inhibit peptic ulcer Histamine-2 receptors on the gastric parietal cell Acid secretion * Including. Cimitidine 400 mg bid. Famotidine 20 mg bid . Ranitidine. Nizatidine 150 mg bid * Adverse effects: main two categories Toxic effects (PPI) Hypochlorhydria - bacterial overgrowth - hypergastrinemia Side effects. C-central nervous system reactions. immune modulation/hypersensitivity. cardiac conduction abnormalities. idiosyncratic hepatic injury. headaches. thrombocytopenia. granulocytopenia. antiandrogenic
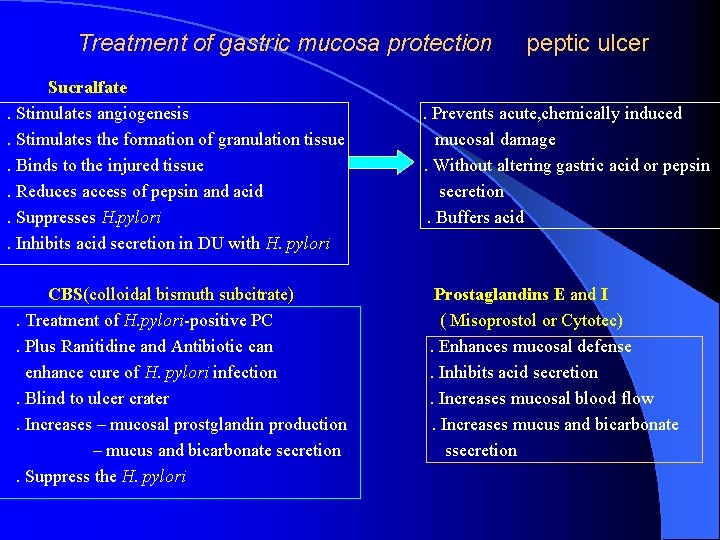
Treatment of gastric mucosa protection Sucralfate. Stimulates angiogenesis. Stimulates the formation of granulation tissue. Binds to the injured tissue. Reduces access of pepsin and acid. Suppresses H. pylori. Inhibits acid secretion in DU with H. pylori CBS(colloidal bismuth subcitrate). Treatment of H. pylori-positive PC. Plus Ranitidine and Antibiotic can enhance cure of H. pylori infection. Blind to ulcer crater. Increases – mucosal prostglandin production – mucus and bicarbonate secretion. Suppress the H. pylori peptic ulcer . Prevents acute, chemically induced mucosal damage. Without altering gastric acid or pepsin secretion. Buffers acid Prostaglandins E and I ( Misoprostol or Cytotec). Enhances mucosal defense. Inhibits acid secretion. Increases mucosal blood flow. Increases mucus and bicarbonate ssecretion
Causes of refractory and recurrent ulcer Persisting Helicobactor pylori infection. Poor compliance. Resistant organism. Inadequate H. pylori regimen Persisting Symptoms, No Ulcer. Another diagnosis. Irritable gut. Cancer, Crohn’s, other infections Persisting or recurrent ulcer, No H. pylori. False-negative H. pylori. Delayed healing. Continued or undiscovered NSAID use. Uncommon forms of ulcer Causes Delayed Healing. Dense fibrosis. Heavy smoking. Giant ulcer. Inadequate inhibition of acid secretion * H 2 -RA tolerance? or PPI resistance? . Hypersecretory states – gastrinoma – antral G cell hyperfuction – idiopathic hypersecretory DU

Pathology Peptic ulcer Chronic peptic ulcers * Usually single, although 5 -20% may be multiple * Healing ulcers covered with. a single layer of undifferentiated epithelial cells. Followed by variable resolution of the underlying inflammation * Described four histologic zones by microscope: . A superficial layer of fibrin and exudate. Underlying zones of fibrinoid necrosis. Granulation tissue. Fibrosis
Location * Aspirin injury * Stress ulcer Peptic ulcer acute lesions: . multiple. shallow. minimal surrounding inflammation. fibrosis acute not generally surrounded by fibrosis * Ulcers in the gastric cardia or in a hiatal hernia pouch. * Jejunum, occur rarely. If they do, they follow. The creation of a surgical stoma. The occurrence of the Zollinger – Ellision syndrome

Peptic ulcer Causes * Common forms of peptic ulcer. Helicobacter pylori. NSAID (no-steroidal. Acid and pepsin. Stress anti-inflammatory drugs) * Uncommon specific forms of peptic ulcer. Heredity: Gastrinoma - inherited multiple endocrine neoplasia I - sporadic increased mast cells/basophils. Basophilic leukemias. Antral G cell hyperfuction/hyperplasia(H. pylori-induced and non-H. pylori). Hypersecretory (non-H. pylori DU)
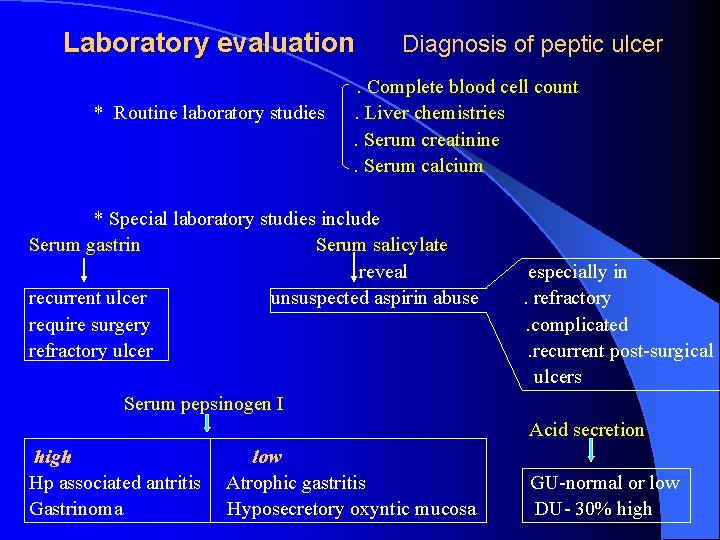
Laboratory evaluation * Routine laboratory studies Diagnosis of peptic ulcer . Complete blood cell count. Liver chemistries. Serum creatinine. Serum calcium * Special laboratory studies include Serum gastrin Serum salicylate reveal recurrent ulcer unsuspected aspirin abuse require surgery refractory ulcer especially in. refractory. complicated. recurrent post-surgical ulcers Serum pepsinogen I Acid secretion high Hp associated antritis Gastrinoma low Atrophic gastritis Hyposecretory oxyntic mucosa GU-normal or low DU- 30% high
Causes • • Peptic ulcer Viral infection - herpes simplex virus type I. - Cytomegalovirus * Duodenal obstruction/disruption (congenital annular pancreas) * Vascular insufficiency – associated perforations * Induced factors-. Radiation • . Chemotherapy( hepatic artery infusions) * Rare genetic subtypes * Idiopathic
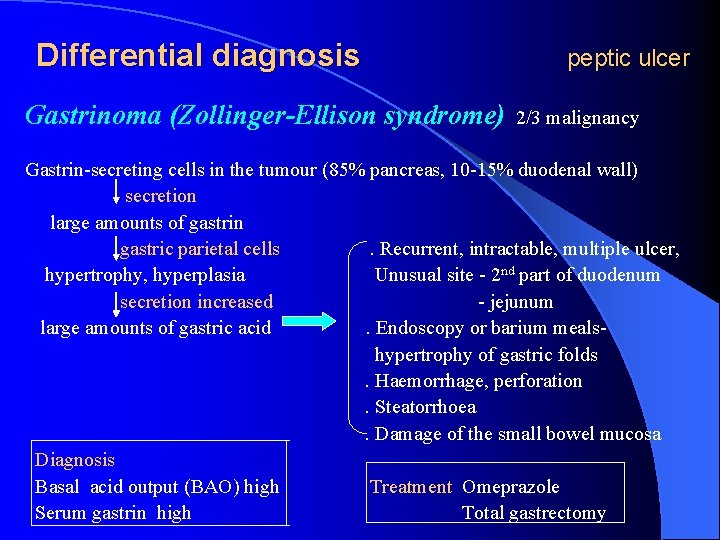
Differential diagnosis Gastrinoma (Zollinger-Ellison syndrome) peptic ulcer 2/3 malignancy Gastrin-secreting cells in the tumour (85% pancreas, 10 -15% duodenal wall) secretion large amounts of gastrin gastric parietal cells. Recurrent, intractable, multiple ulcer, hypertrophy, hyperplasia Unusual site - 2 nd part of duodenum secretion increased - jejunum large amounts of gastric acid. Endoscopy or barium mealshypertrophy of gastric folds. Haemorrhage, perforation. Steatorrhoea. Damage of the small bowel mucosa Diagnosis Basal acid output (BAO) high Treatment Omeprazole Serum gastrin high Total gastrectomy
- Slides: 68