
CF Is not just CF Cystic Fibrosis CRMS

CF Is not just CF

Cystic Fibrosis • • • CRMS (CF related metabolic syndrome) CFRD (diabetes) CFRLD (Liver disease) PS (pancreatic sufficient) PI (pancreatic insufficient)

• 1981 average age: 18 • 2016 average age: 39 (oldest 86) • Not just a pediatric illness – 3000 at the last NACF meeting – Majority of caregivers in adult centers

Role of pediatric team Diagnosis Early interventions Ensure growth (weight % at age 4 may effect long term prognosis) • Workup drops in weight • Address sinopulmonary disease • Address infections aggressively • •

Early diagnosis • Earliest can be in utero • May need to see before birth • (especially meconium ileus may see surgery before delivery)

Diagnosis • • NB screen includes IRT (all states since 2007) If IRT abnormal will trigger DNA evaluation If DNA abnormal will be referred from State Screen to CHOA (SR/EG) depending on zip code 2 mutations, relatively simple and easy to explain 1 mutation still needs referral and likely will have full sequencing STILL needs SWEAT CL Should have fecal elastase (will be normal by 2 weeks of age)

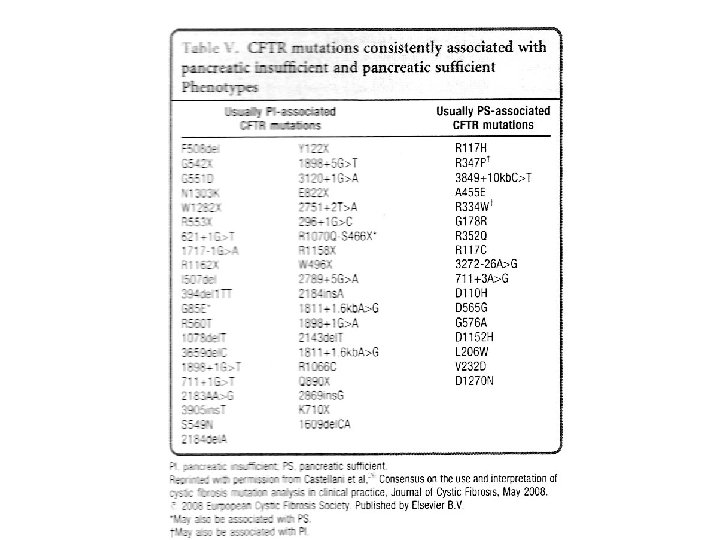
• Mutation essential • Directs discussion and management • Directs meds now and in the future as some are CAN specific • www. cftr 2. org • (will give mutation defect and enable one to decide PI vs PS, though 90% PI)
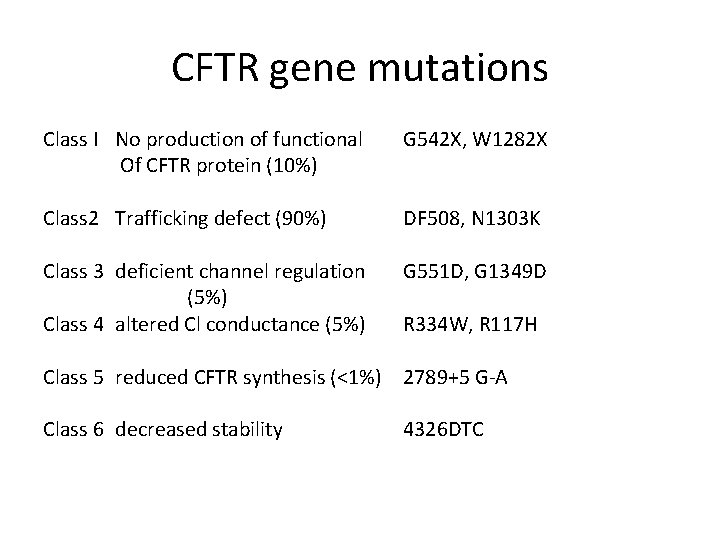
CFTR gene mutations Class I No production of functional Of CFTR protein (10%) G 542 X, W 1282 X Class 2 Trafficking defect (90%) Class 3 deficient channel regulation (5%) Class 4 altered Cl conductance (5%) Class 5 reduced CFTR synthesis (<1%) Class 6 decreased stability DF 508, N 1303 K G 551 D, G 1349 D R 334 W, R 117 H 2789+5 G-A 4326 DTC

Nutrition • Infants may need 150 cal/kg or more • Regular/standard formula or breast milk • Specialized formulas with meconium ileus if bowel resection • 1/8 tsp salt/day

PERT (Pancreatic enzyme replacement therapy) • Creon (Solvay) 3, 000, 6, 000, 12, 000, 24, 000, 36, 000 • Zenpep (Allergan) 5, 000, 10, 000, 15, 000, 20, 000 • Pancreaze 4, 200, 16, 800, 21, 000 (no phthalein) • Pertzye (with added bicarb) (like previous pancrecarb) 8/16, 000 • Viokase 10, 440 and 20, 880 • All related to IU of lipase/pill • Only creon 3000 able to go into the g tube

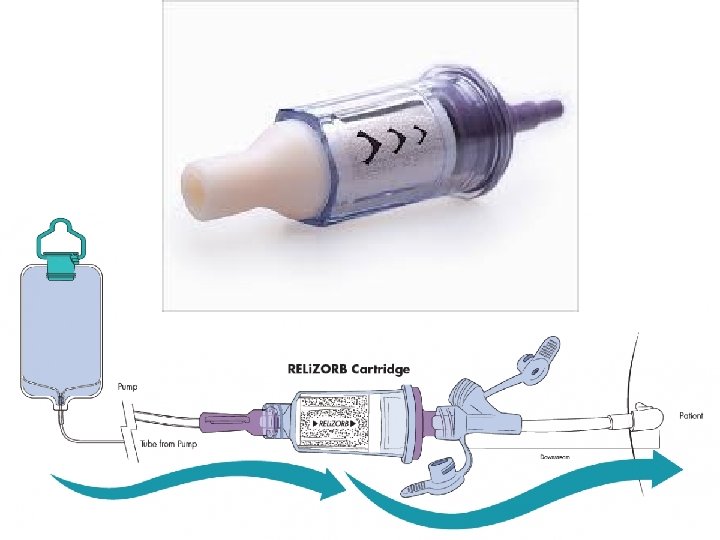
Relizorb External lipase cartridges One cartridge can handle 500 cc formula (NO FIBER) Rate 24 cc/hr to 125 cc/hr Not yet approved at CHOA though using at CHOA Goal is to avoid standard enzymes with drip/night feeds but NO protease/amylase • Samples available and programs to help defray costs • Insurances are approving (though really to date approved for 18 yo+) • • •

Abdominal pain • • Think DIOS (old meconium ileus equivalent) Enema alone likely not effective Typically ileocecal Try miralax Water soluble Ba. E +/- mucomyst If vomiting surgical consult If DIOS to stay on miralax

Malabsorption 1. Inadequate enzymes, remember 1000 -2500 iu/kg/meal or feed) 2. Think concompliance especially in adolescence 3. SBBO – – – Increased E coli and decreased bifidobacteria Can have increased calprotectin Can order glucose Br H 2 test Can have high baseline level Can manage with miralax, probiotics, ATB

• C diff – Chronic ATB use • Celiac, can have more than 1 problem • Gallstones • GER – Can use PPI for absorption and GER – Can’t use PPI with intraconizole – PPI will increase tacrolimus level

Growth • Expect 50% weight and BMI • Expect normal growth depending on the family • If HT < 10% at age 7 refer to endocrinology

• • CFTR in biliary epithelium Alternative Cl channels in the liver Height of the enzymes is not related to the degree of liver disease Bx: – 10 -60% steatosis – 11 -70% focal biliary fibrosis – 4 -40% multilobular cirrhosis • By age 10, 60% will have increased LFTs once, 20% persist • 40% adolescence have abnormal liver u/s • 5 -7% will develop cirrhosis, though typically will develop by 15 years of age • Bile acid loss is 3 X normal related to CFTR

If LFTs elevated • If 1. 5 X normal repeat in a year • If 1. 5 -2 X normal repeat in 3 months – If still Hep B/C. alpha 1 antitrypsin, autoimmune, Celiac, ceruloplasmin, ultrasound may need to check essential FA and carnitine • Use of actigall still controversial • Liver transplantation used to be thought to improve lung function but this is not the case

Diabetes • • • OGTT annually starting age 10 Fasting >100 abnormal 2 H glucose >140 abnormal 1 H glucose >200 s abnormal Need to monitor glucoses some with using night feeds, esp in the older child There is CGM (continuous glucose monitoring) though typically not in the hospital and some insurances won’t cover Some g-tube fed patients will increase glucoses and need insulin coverage CFRD typically not acidotic CFRD common reason for unexplained weight loss 1981 5% expected to be diabetic (average 18) 2017 35 -40%
- Slides: 20