Pacemaker Supparerk Prichayudh M D Normal EKG P








































- Slides: 80
Pacemaker Supparerk Prichayudh M. D
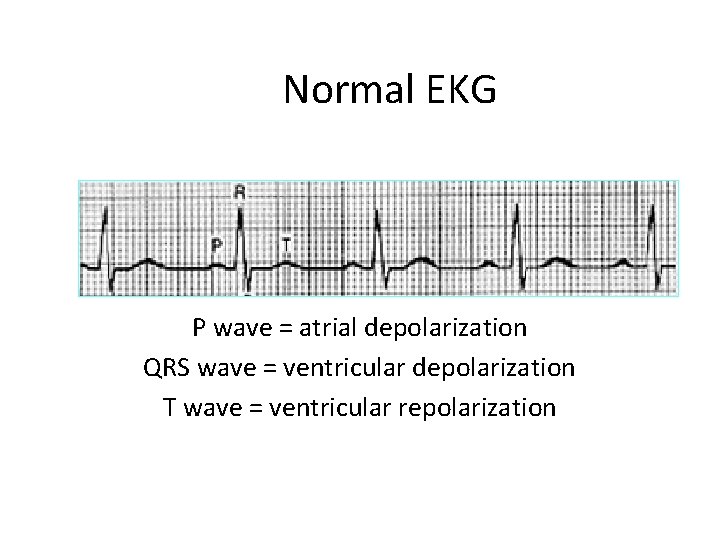
Normal EKG P wave = atrial depolarization QRS wave = ventricular depolarization T wave = ventricular repolarization
Outline 1. 2. 3. 4. 5. 6. Indications Types Modes of pacemaker Temporary pacemaker Problems with pacemakers Surgical diathermy and pacemakers
Indications
Indication: Symptomatic bradycardia • Sinus node dysfunction • 3° and advanced 2° AV block • Bradycardia associated with AMI
Prophylactic Implant • Patients with LBBB requiring Swan-Ganz catheter placement • Cardioversion in the setting of SSS • New BBB in the setting of acute endocarditis • Peri-operatively
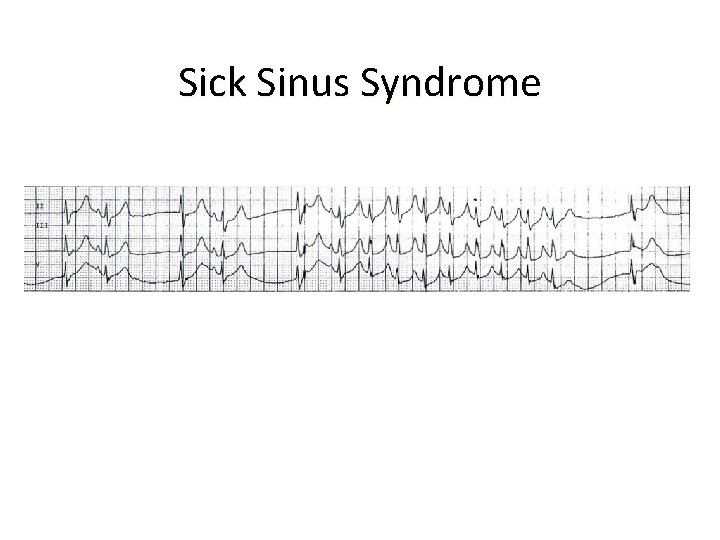
Sick Sinus Syndrome
Types 1. Temporary 2. Permanent
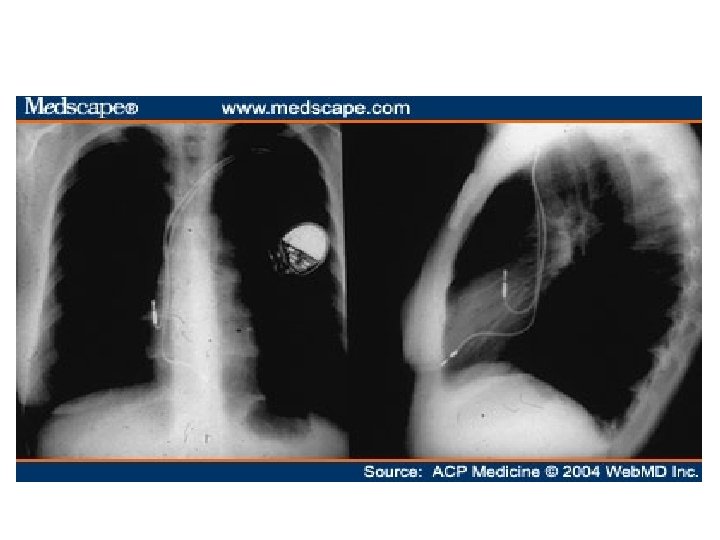
Permanent pacemaker Box = pulse generator
Pacemaker Leads • Pacemaker leads are the conduits from the generator to the myocardium. Most leads are implanted transvenously.
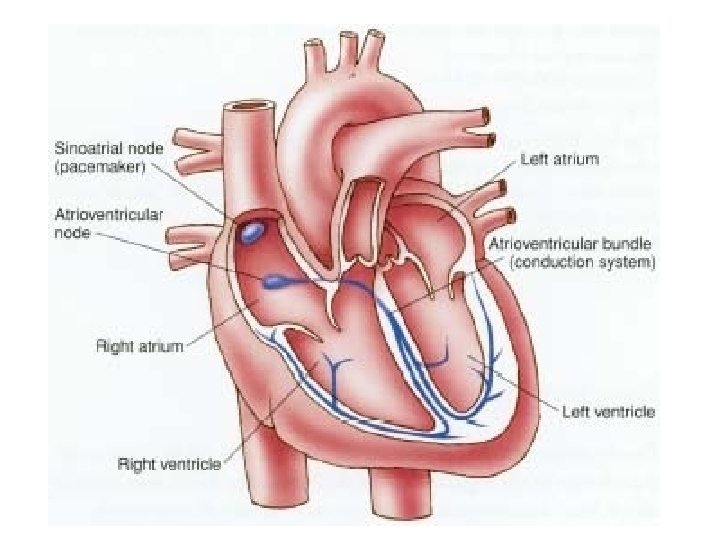
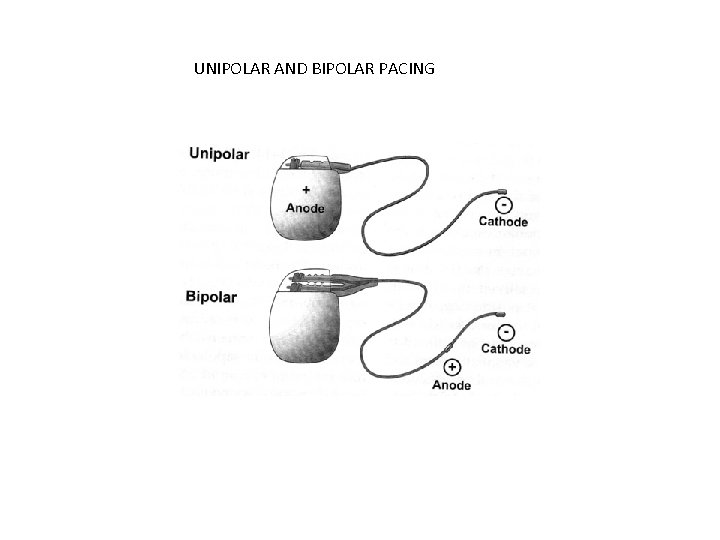
• Wiring systems – Unipolar • One electrode on the heart (-) • Signals return through body fluid and tissue to the pacemaker (+) – Bipolar • Two electrodes on the heart (- & +) • Signals return to the ring electrode (+) above the lead ( -) tip
UNIPOLAR AND BIPOLAR PACING
Modes of pacemaker
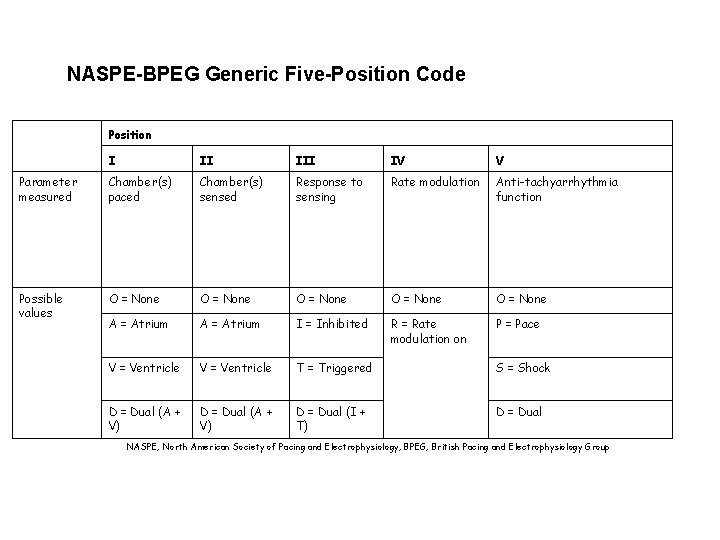
NASPE-BPEG Generic Five-Position Code Position I II IV V Parameter measured Chamber(s) paced Chamber(s) sensed Response to sensing Rate modulation Anti-tachyarrhythmia function Possible values O = None O = None A = Atrium I = Inhibited R = Rate modulation on P = Pace V = Ventricle T = Triggered S = Shock D = Dual (A + V) D = Dual (I + T) D = Dual NASPE, North American Society of Pacing and Electrophysiology; BPEG, British Pacing and Electrophysiology Group
• First letter: Chamber Paced • • V- Ventricle A- Atrium D- Dual (A & V) O- None
• Second letter: Chamber Sensed • • V- Ventricle A- Atrium D- Dual (A & V) O- None
• Third letter: Sensed Response • • T- Triggers Pacing I- Inhibits Pacing (demand) D- Dual (synchronous) O- None (asynchronous)
Chamber Paced – Atrial pacing • Intact AV conduction system required – Ventricular pacing • Loss of atrial kick – Atrial/Ventricular pacing • Natural pacing • Atrial-ventricular synchrony
Commonly used modes • • • AAI - atrial demand pacing VVI - ventricular demand pacing DDD – Dual chamber pacemaker – AOO - atrial asynchronous pacing VOO - ventricular asynchronous pacing
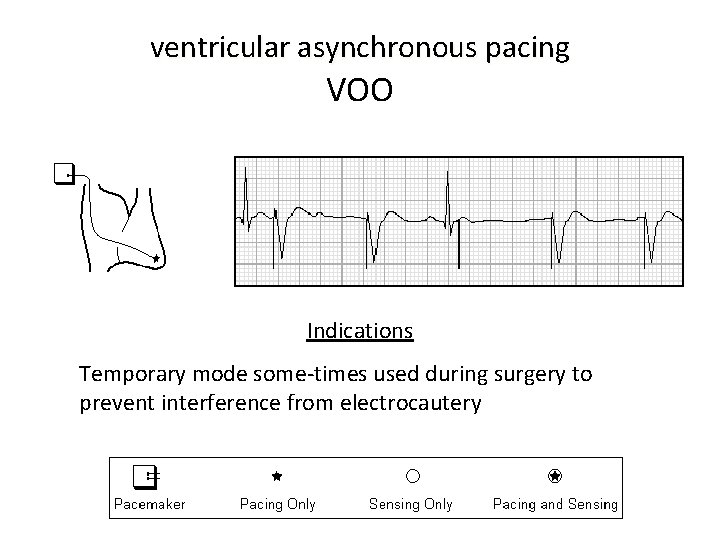
ventricular asynchronous pacing VOO Indications Temporary mode some-times used during surgery to prevent interference from electrocautery
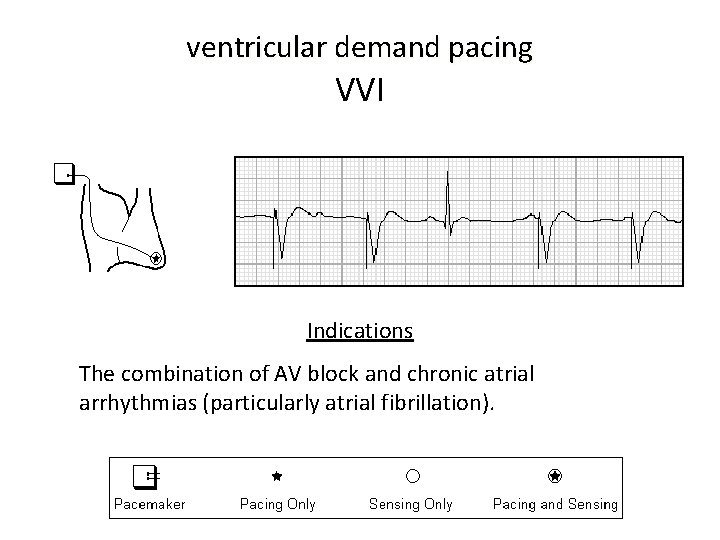
ventricular demand pacing VVI Indications The combination of AV block and chronic atrial arrhythmias (particularly atrial fibrillation).
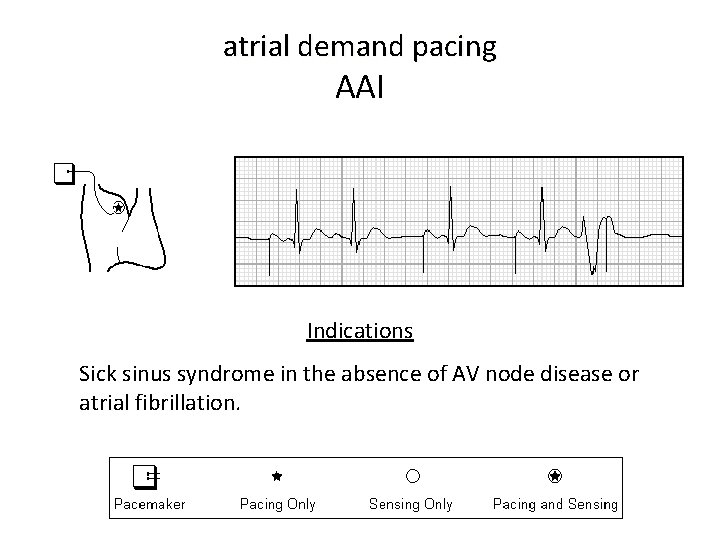
atrial demand pacing AAI Indications Sick sinus syndrome in the absence of AV node disease or atrial fibrillation.
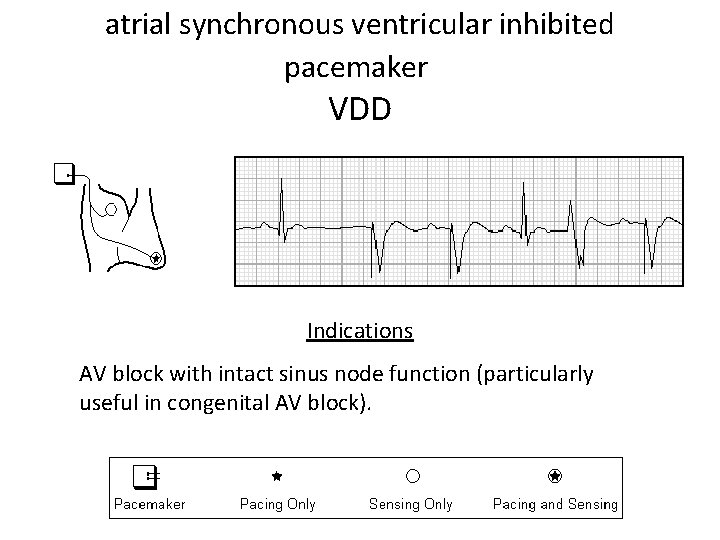
atrial synchronous ventricular inhibited pacemaker VDD Indications AV block with intact sinus node function (particularly useful in congenital AV block).
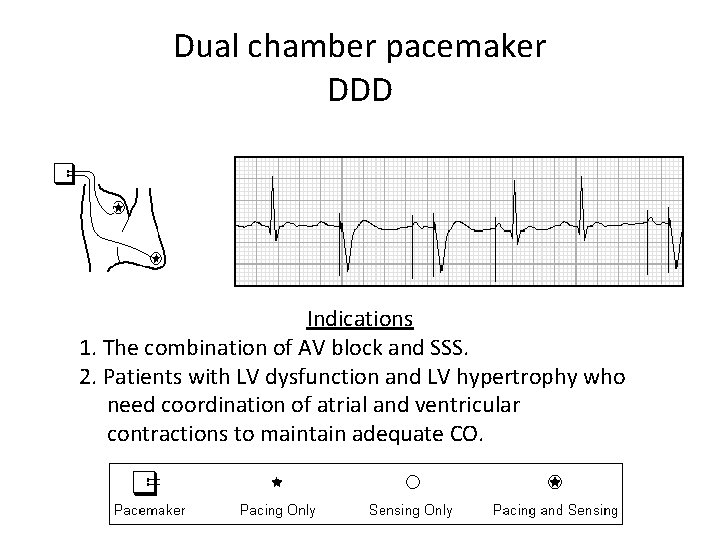
Dual chamber pacemaker DDD Indications 1. The combination of AV block and SSS. 2. Patients with LV dysfunction and LV hypertrophy who need coordination of atrial and ventricular contractions to maintain adequate CO.
Temporary pacemaker
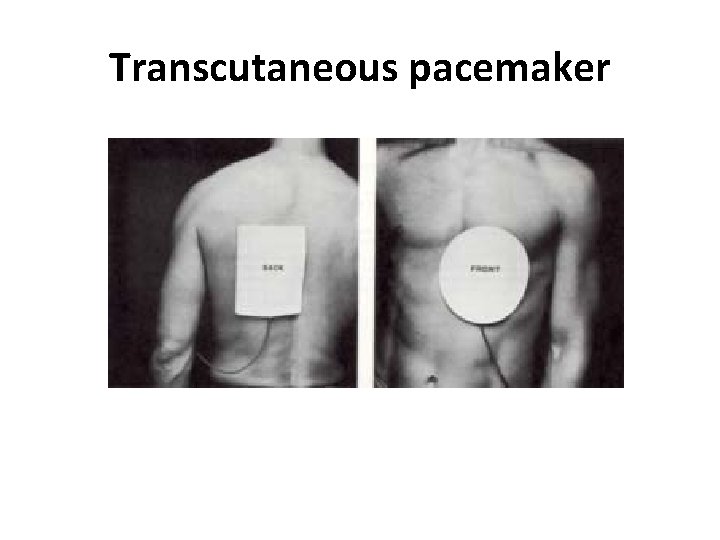
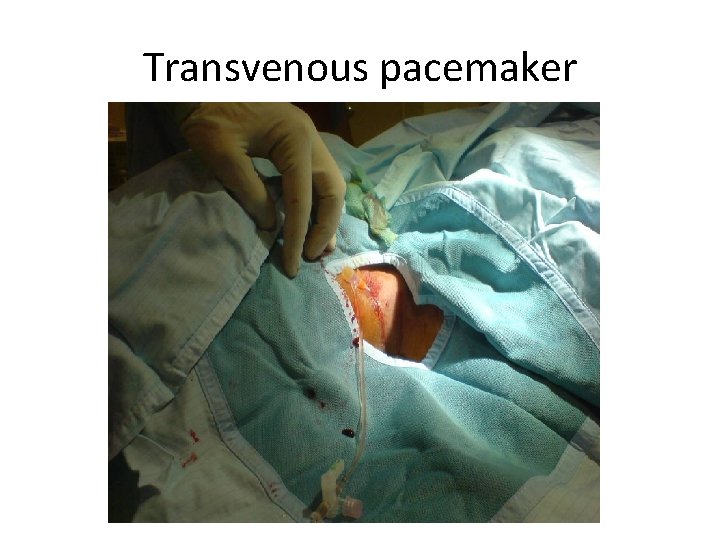
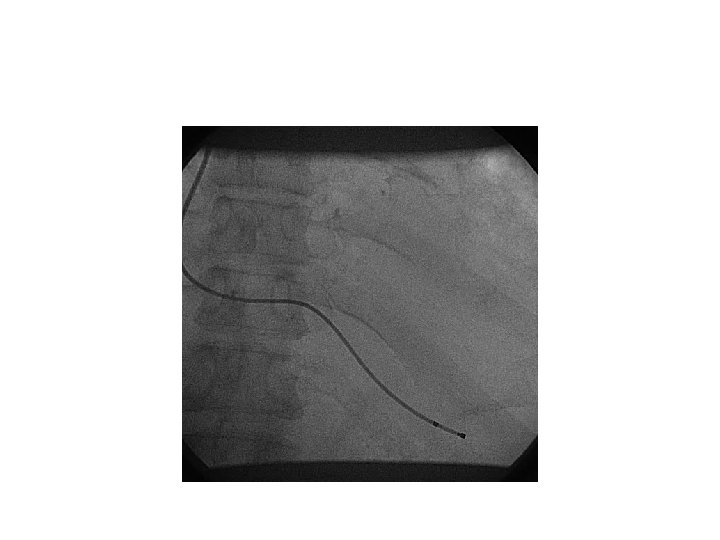
Types – Transvenous- pacing wire via central line to RV under X ray, usually bipolar i. e. , with 2 electrodes at the end of wire – Transthoracic (epicardial lead) post op pacer wires. – Transcutaneous one electrode over cardiac apex, other over right scapula or clavicle. – Transesophageal
Transcutaneous pacemaker
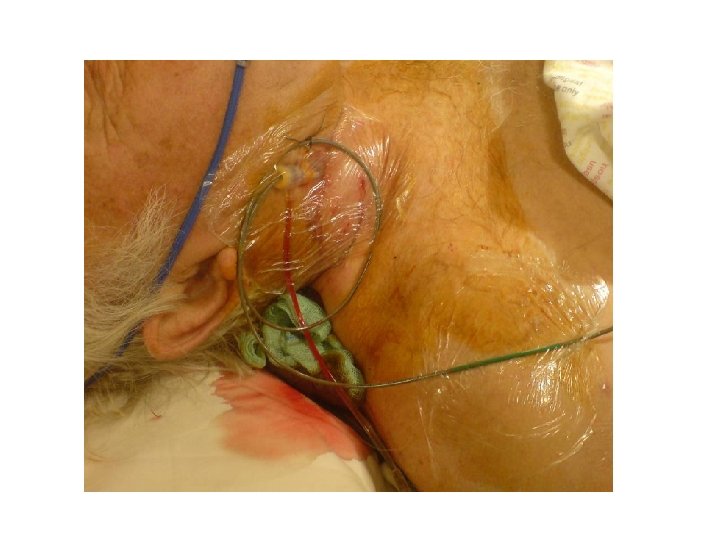
Transvenous pacemaker
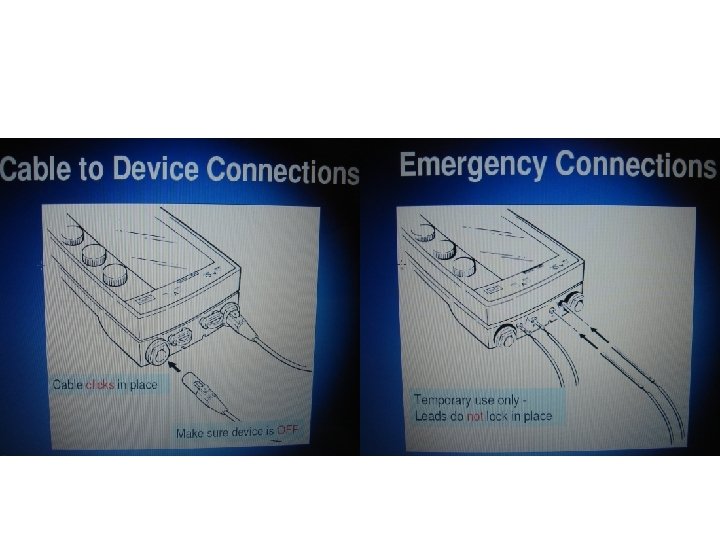
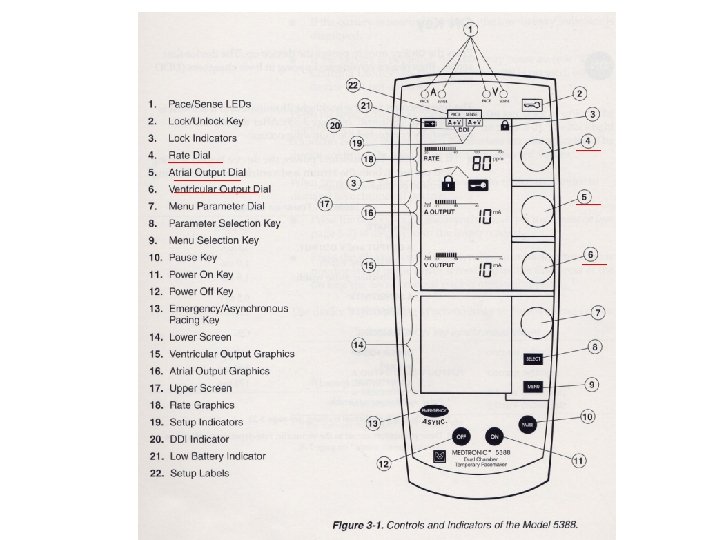
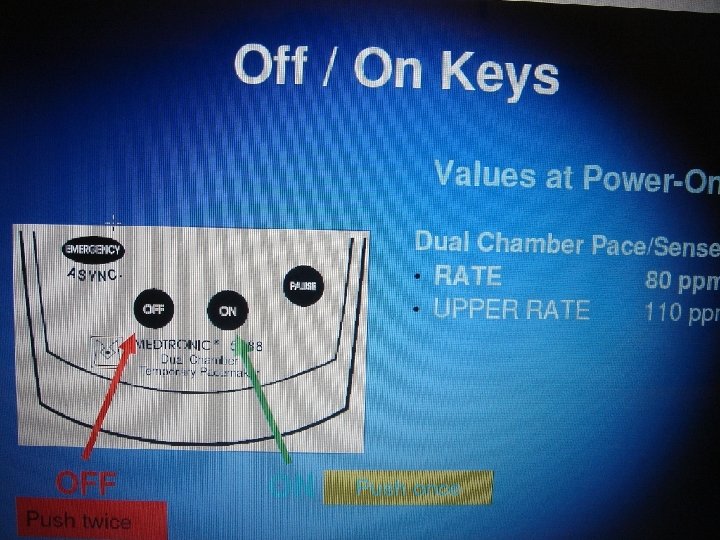
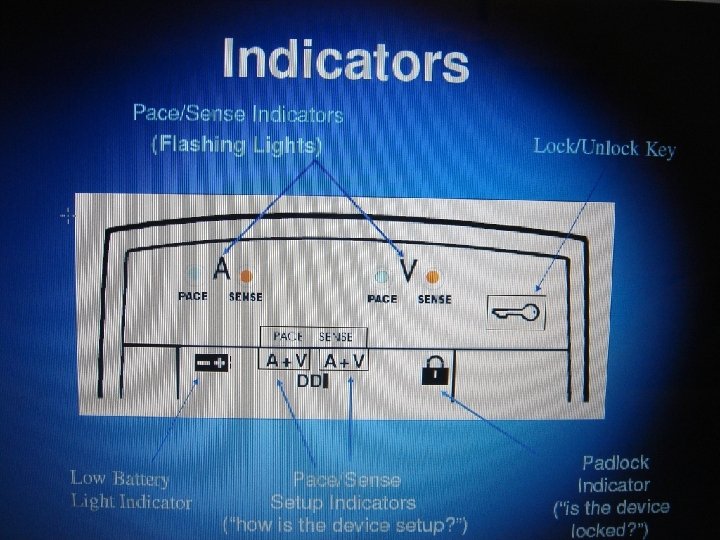
• Medtronic 5388 Dual Chamber
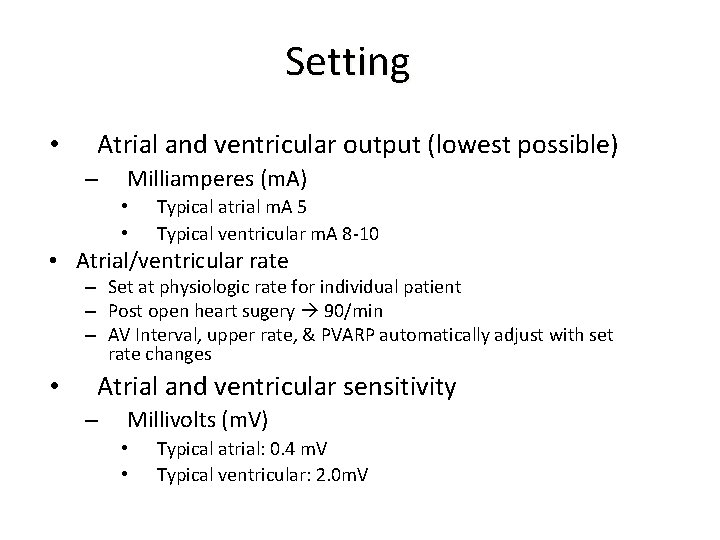
Setting • Atrial and ventricular output (lowest possible) – Milliamperes (m. A) • • Typical atrial m. A 5 Typical ventricular m. A 8 -10 • Atrial/ventricular rate – Set at physiologic rate for individual patient – Post open heart sugery 90/min – AV Interval, upper rate, & PVARP automatically adjust with set rate changes • Atrial and ventricular sensitivity – Millivolts (m. V) • • Typical atrial: 0. 4 m. V Typical ventricular: 2. 0 m. V
Setting (cont. ) • AV Interval – Milliseconds (msec) • • Time from atrial sense/pace to ventricular pace Synonymous with “PR” interval • Upper rate – Automatically adjusts to 30 bpm higher than set rate – Prevents pacemaker mediated tachycardia from unusually high atrial rates – Wenckebach-type rhythm results when atrial rates are sensed faster than the set rate • Refractory period – PVARP: Post Ventricular Atrial Refractory Period • Time after ventricular sensing/pacing when atrial events are ignored
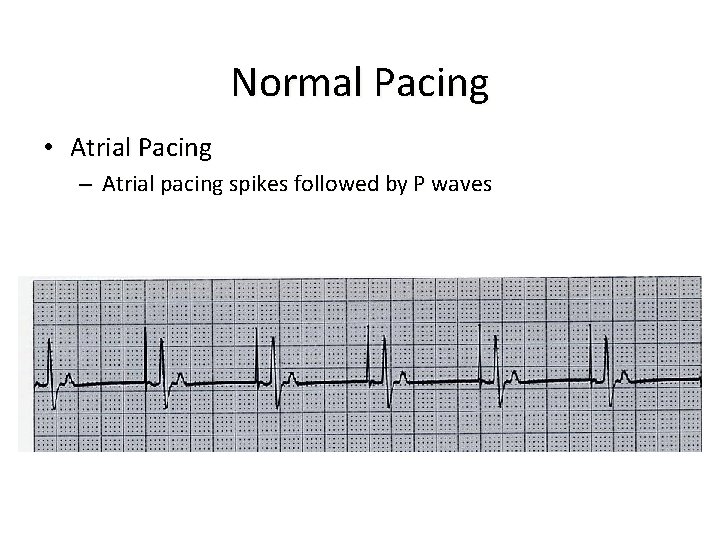
Normal Pacing • Atrial Pacing – Atrial pacing spikes followed by P waves
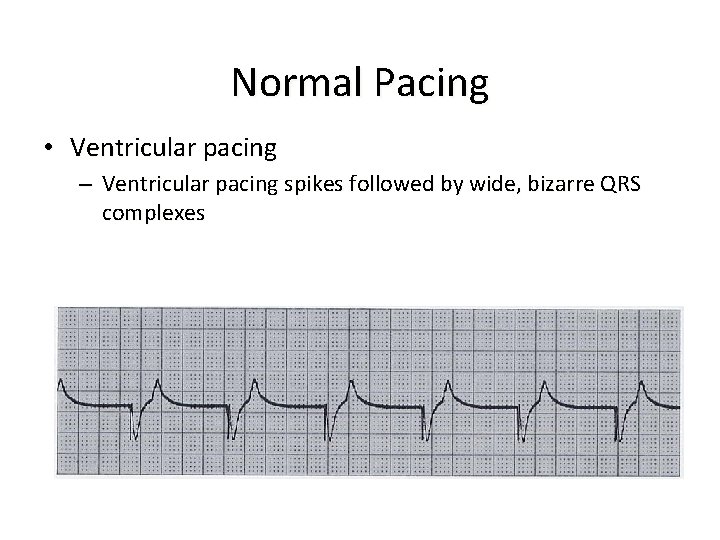
Normal Pacing • Ventricular pacing – Ventricular pacing spikes followed by wide, bizarre QRS complexes
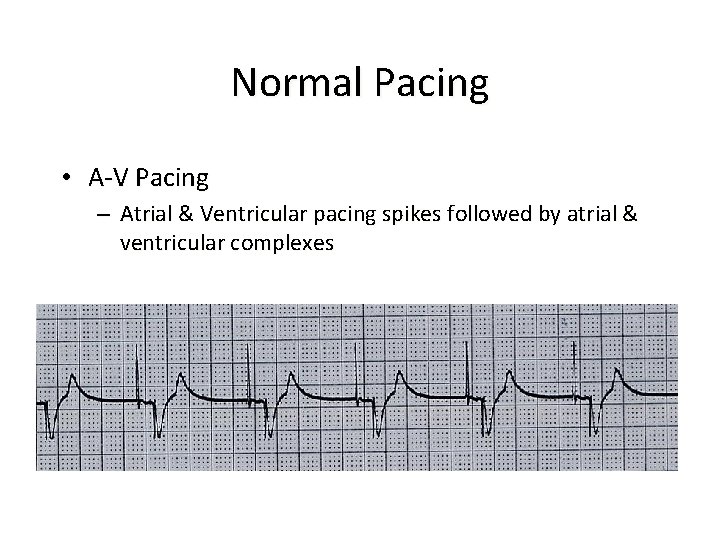
Normal Pacing • A-V Pacing – Atrial & Ventricular pacing spikes followed by atrial & ventricular complexes
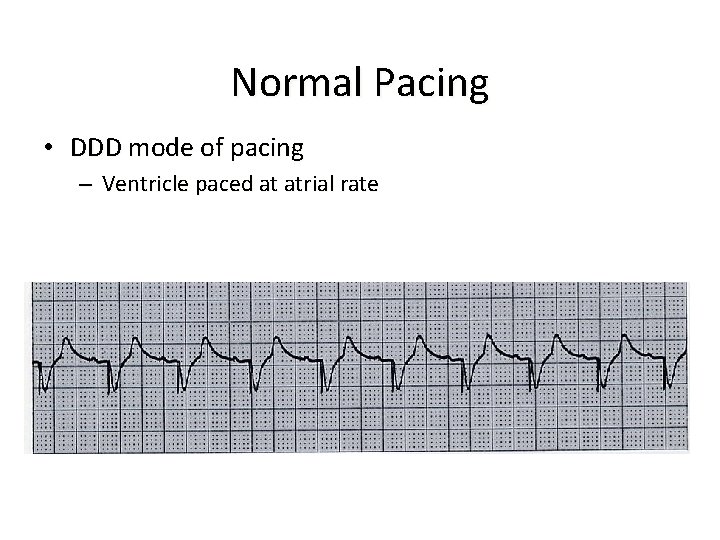
Normal Pacing • DDD mode of pacing – Ventricle paced at atrial rate
Assessing Underlying Rhythm
Problems with pacemakers
Problems with pacemakers 1. 2. 3. 4. 5. Failure to pace Failure to capture Failure to sense (overpacing) Wenkebach Pacemaker syndrome
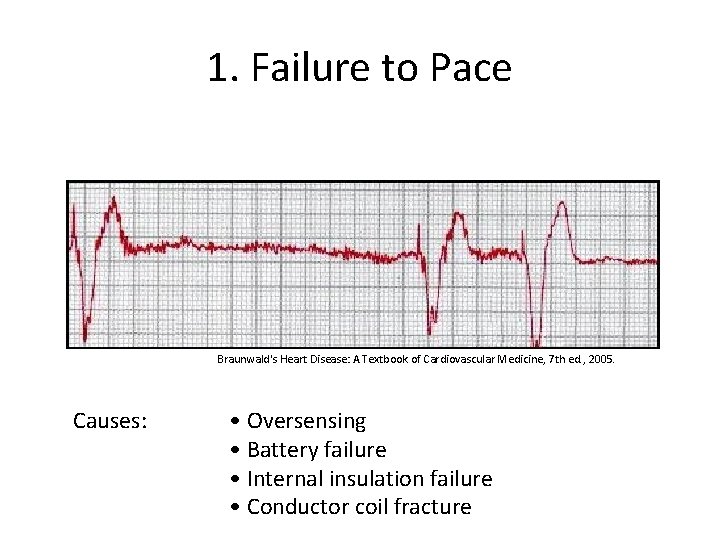
1. Failure to Pace Braunwald's Heart Disease: A Textbook of Cardiovascular Medicine, 7 th ed. , 2005. Causes: • Oversensing • Battery failure • Internal insulation failure • Conductor coil fracture
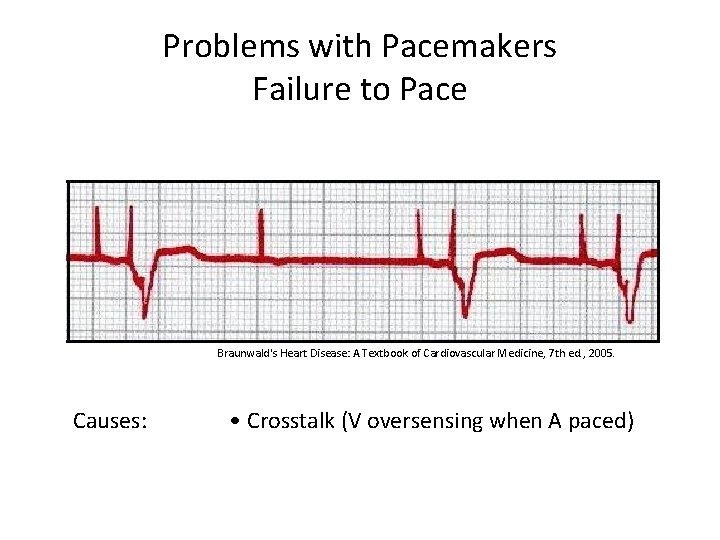
Problems with Pacemakers Failure to Pace Braunwald's Heart Disease: A Textbook of Cardiovascular Medicine, 7 th ed. , 2005. Causes: • Crosstalk (V oversensing when A paced)
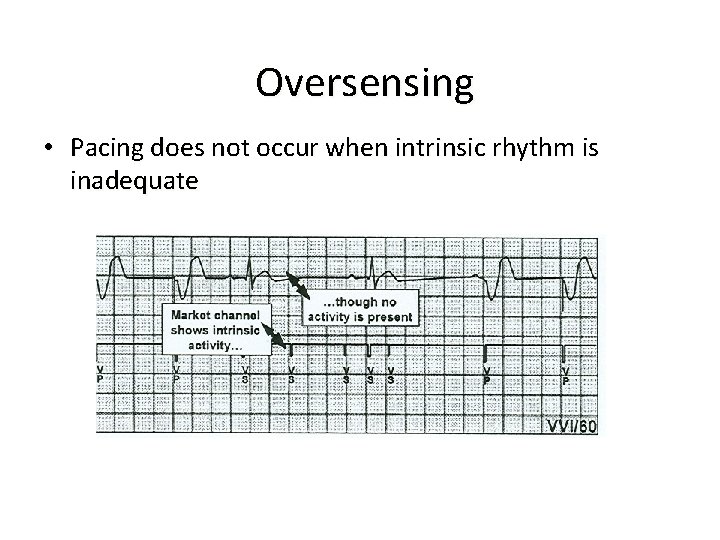
Oversensing • Pacing does not occur when intrinsic rhythm is inadequate
Oversensing • Causes – Pacemaker inhibited due to sensing of “P” waves & “QRS” complexes that do not exist – Pacemaker too sensitive – Possible wire fracture, loose contact – Pacemaker failure • Danger - heart block, asystole
Oversensing • Solution – – – – View rhythm in different leads Change electrodes Check connections Decrease pacemaker sensitivity (↑m. V) Change cables, battery, pacemaker Reverse polarity Check electrolytes Unipolar pacing with subcutaneous “ground wire”
Reversing polarity • Changing polarity – Requires bipolar wiring system – Reverses current flow – Switch wires at pacing wire/bridging cable interface
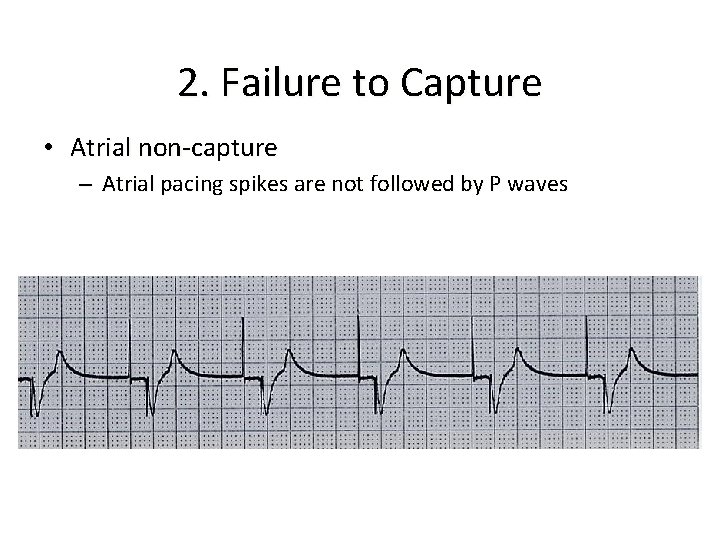
2. Failure to Capture • Atrial non-capture – Atrial pacing spikes are not followed by P waves
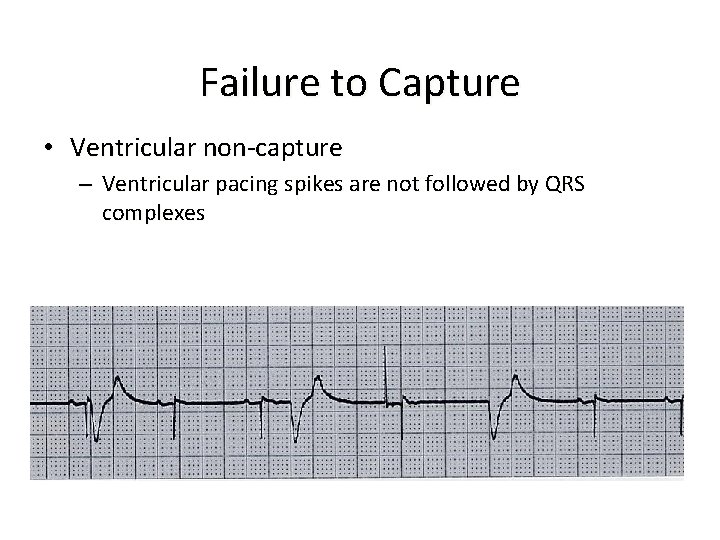
Failure to Capture • Ventricular non-capture – Ventricular pacing spikes are not followed by QRS complexes
Failure to Capture • Causes – – Insufficient energy delivered by pacer Low pacemaker battery Dislodged, loose, fibrotic, or fractured electrode Electrolyte abnormalities • Acidosis • Hypoxemia • Hypokalemia • Danger - poor cardiac output
Failure to Capture • Solutions – View rhythm in different leads – Change electrodes – Check connections – Increase pacer output (↑m. A) – Change battery, cables, pacer – Reverse polarity
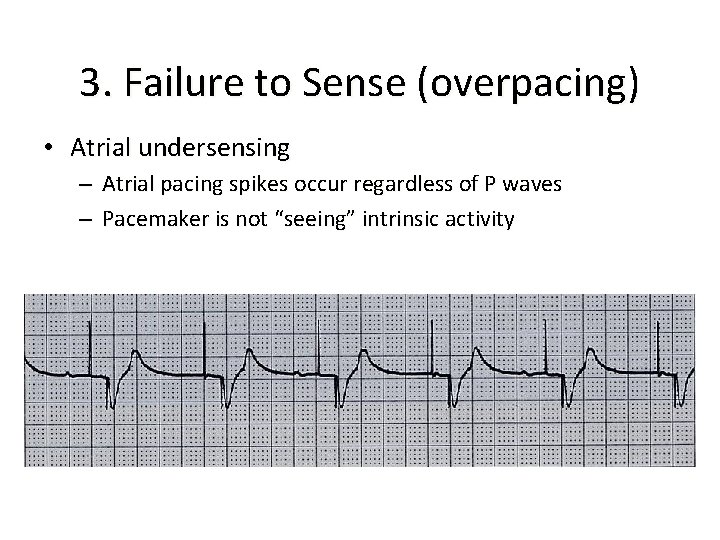
3. Failure to Sense (overpacing) • Atrial undersensing – Atrial pacing spikes occur regardless of P waves – Pacemaker is not “seeing” intrinsic activity
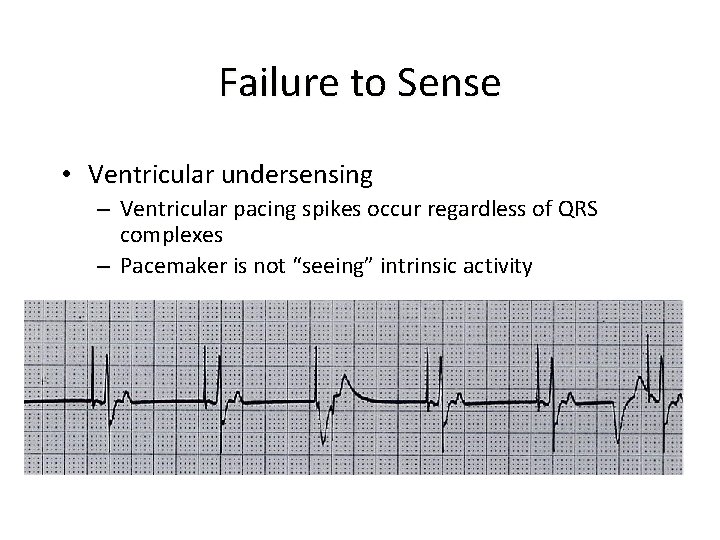
Failure to Sense • Ventricular undersensing – Ventricular pacing spikes occur regardless of QRS complexes – Pacemaker is not “seeing” intrinsic activity
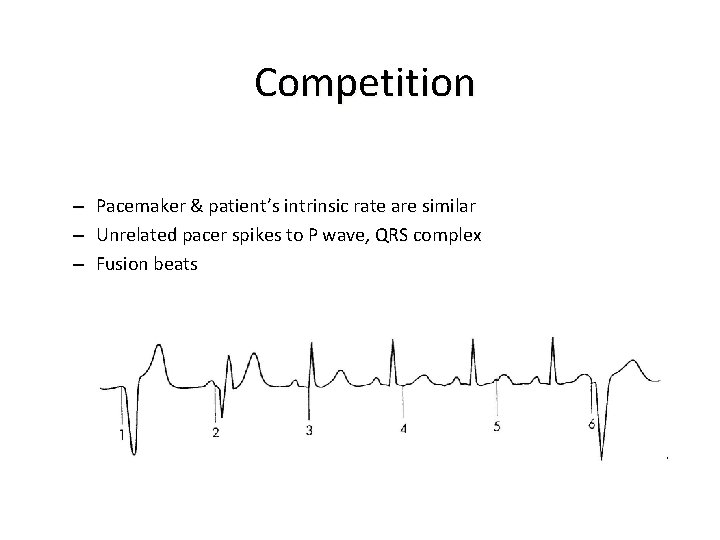
Competition – – – Pacemaker & patient’s intrinsic rate are similar Unrelated pacer spikes to P wave, QRS complex Fusion beats
Failure to Sense • Causes – Pacemaker not sensitive enough to patient’s intrinsic electrical activity (m. V) – Insufficient myocardial voltage – Dislodged, loose, fibrotic, or fractured electrode – Electrolyte abnormalities – Low battery – Malfunction of pacemaker or bridging cable
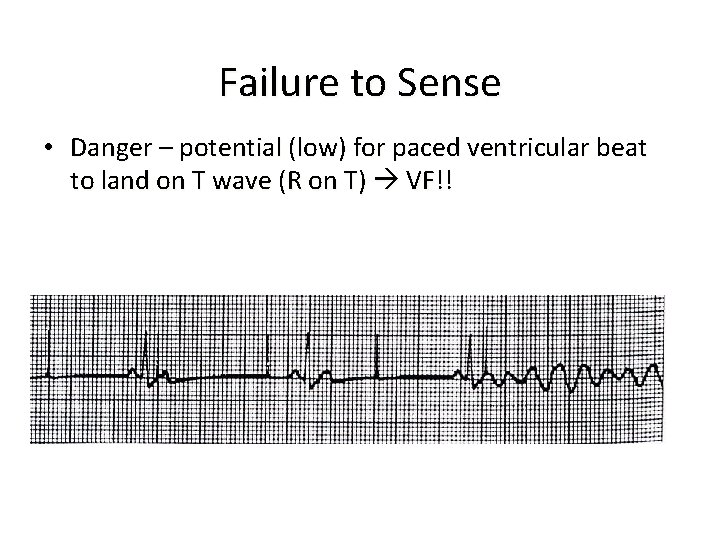
Failure to Sense • Danger – potential (low) for paced ventricular beat to land on T wave (R on T) VF!!
Failure to Sense • Solution – – – – View rhythm in different leads Change electrodes Check connections Increase pacemaker’s sensitivity (↓m. V) Change cables, battery, pacemaker Reverse polarity Check electrolytes Unipolar pacing with subcutaneous “ground wire”
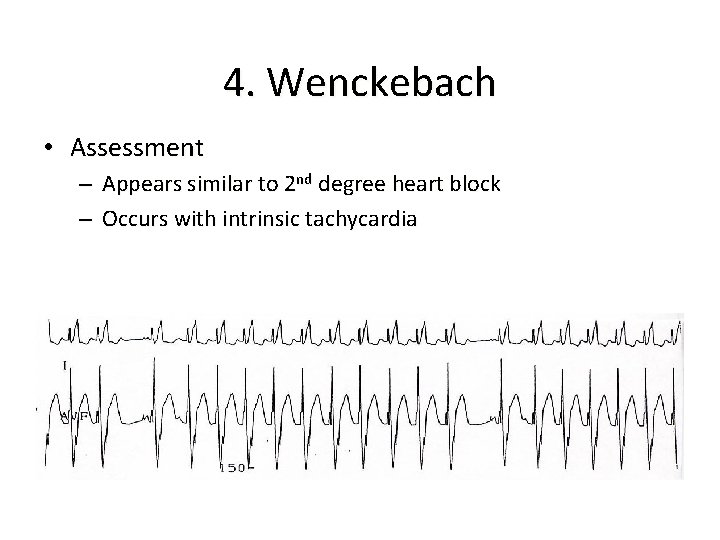
4. Wenckebach • Assessment – Appears similar to 2 nd degree heart block – Occurs with intrinsic tachycardia
Wenckebach • Causes – DDD mode safety feature – Prevents rapid ventricular pacing impulse in response to rapid atrial rate • • Sinus tachycardia Atrial fibrillation, flutter Prevents pacer-mediated tachycardia Upper rate limit may be inappropriate
Wenckebach • Solution – Treat cause of tachycardia • • Fever: Cooling Atrial tachycardia: Anti-arrhythmic Pain: Analgesic Hypovolemia: Fluid bolus – Adjust pacemaker upper rate limit as appropriate
5. Pacemaker syndrome • Ventricular pacing sacrifice the atrial contribution to ventricular output – Loss of AV synchrony Atrium contracts against closed TV, MV ↓ CO, ↓ ↑ JVD – Retrograde ventriculoatrial (VA) conduction inverted P, ↑ PR, AV dissociation – Absence of rate response to physiologic need • 14 -57% in VVI • Patients with intact VA conduction are at greater risk
• Rx – VVI Add A-lead, ↓ Rate ↓ – Other interrogation and reprogramming to fix loss of AV synchrony
Surgical diathermy and pacemakers
• Ventricular fibrillation – most common if pacemaker unit is older type • Inhibition of demand function- sensing may be triggered, with resultant chamber inhibition or arrhythmias induced • Unpredictable setting of programmable types • Asystole • Unit failure
Recommendations • Place indifferent electrode on same side as operation & as far from pacemaker unit as possible • Limit use of diathermy • Use lowest current setting possible • Use bipolar diathermy • Careful monitoring of pulse, pulse oximetry & arterial pressure • Transcutaneous pacing should be available • Isoprenaline should be available • Interrogation before Sx • Magnet – Reset PM to asynchronous – Inactivate defribillation feature in AICD
Post operative care • Full telemetric check • Reprogramming back to original setting
THANK YOU