Echo Assessment of The Tricuspid Valve Steven A


















- Slides: 47
Echo Assessment of The Tricuspid Valve Steven A. Goldstein MD FACC, FASE Director, Noninvasive Cardiology Med. Star Heart Institute Washington Hospital Center Sunday, February 21, 2016
DISCLOSURE I have N O relevant financial relationships
TV Disease - Role of Echo • Primary vs secondary TR • Severity of tricuspid regurgitation • Degree of dilatation of the TV annulus • Pulmonary artery systolic pressure • RV dimensions and function* (despite existing limitations) * When available, CMR preferred method
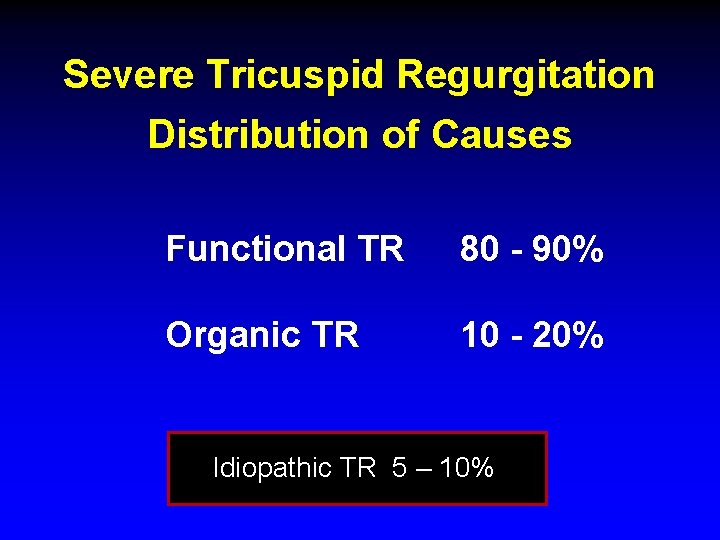
Severe Tricuspid Regurgitation Distribution of Causes Functional TR 80 - 90% Organic TR 10 - 20% Idiopathic TR 5 – 10%
Functional TR
Functional Tricuspid Regurgitation Normal TV leaflets, Leaflet tethering, RV Remodeling, and Dilated TV annulus Restricted closure • Pulmonary hypertension with. RV pressure overload (due to left-sided heart disease, or less commomly cor pulmonale or idiopathic pulmonary arterial hypertension) • RV volume overload (eg ASD) • RV myocardial disease: (eg infarction, RV dysplasia)
Mechanisms of Functional TR • TV leaflet tethering (apical displacement) • Tricuspid annular dilatation • Tricuspid annular geometry (more planar, more circular) • Trans-tricuspid pressure gradient • Ventricular interaction (LV ejection fraction)
Organic Tricuspid Regurgitation Intrinsic abnormality of TV leaflets and/or support apparatus • Degenerative • Endocarditis • Traumatic • Congenital (Ebstein anomaly) • Rheumatic • Radiation Rx • Carcinoid • Hypereosinophilia • Drug-induced: (ergots, anorectics) • PPM or ICD lead • EM biopsy
TV Anatomy
Tricuspid Valve Anatomy • TV is largest valve • Average area 10. 5 cm 2 • Average diameter 36 4. 5 mm (up to 21 mm/m 2)
Tricuspid Valve Anatomy • Anterior leaflet - Commony attaches to single pap muscle • Septal leaflet - Generally attaches to RV wall via chordae - Conduction tissue system penetrates base of septal leaflet - Thus, this part of annulus should not be sewn into with annuloplasty • Posterior leaflet - Smallest leaflet
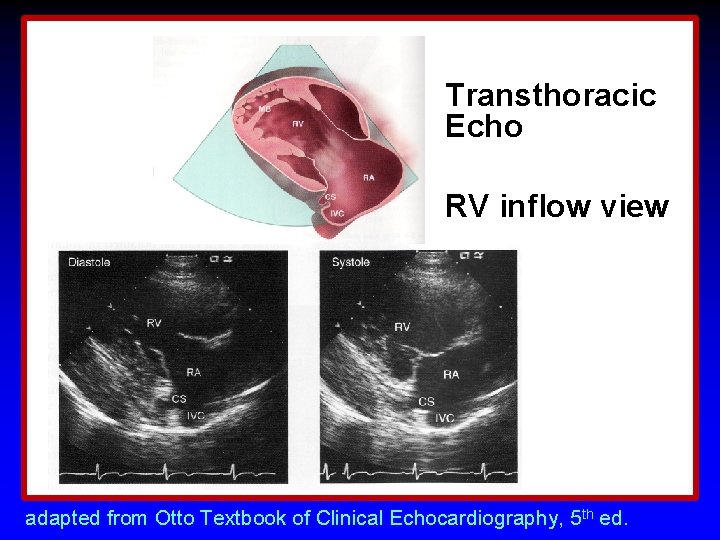
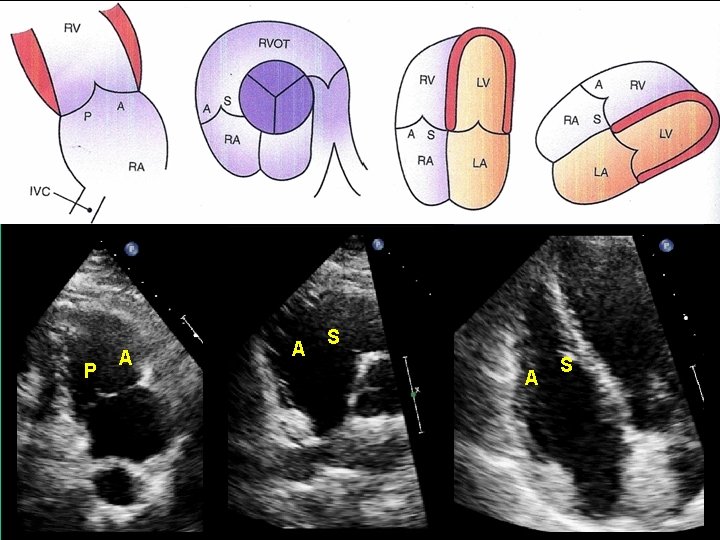
Transthoracic Echo RV inflow view adapted from Otto Textbook of Clinical Echocardiography, 5 th ed.
P A A S
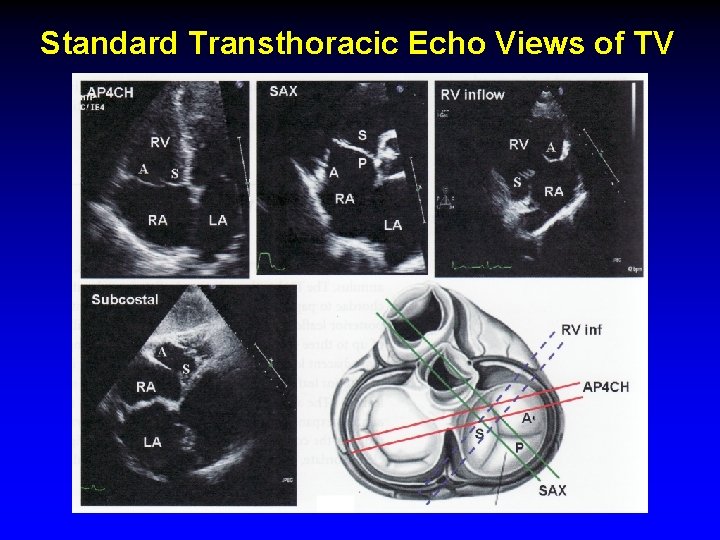
Standard Transthoracic Echo Views of TV
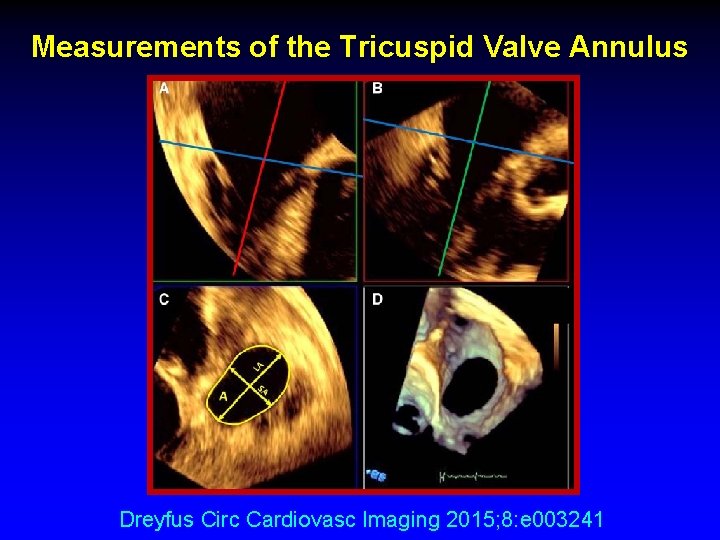
Measurements of the Tricuspid Valve Annulus Dreyfus Circ Cardiovasc Imaging 2015; 8: e 003241
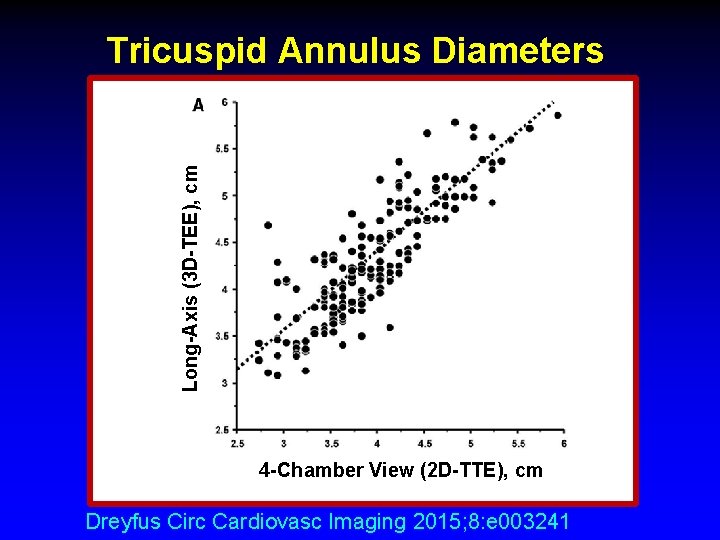
Long-Axis (3 D-TEE), cm Tricuspid Annulus Diameters 4 -Chamber View (2 D-TTE), cm Dreyfus Circ Cardiovasc Imaging 2015; 8: e 003241
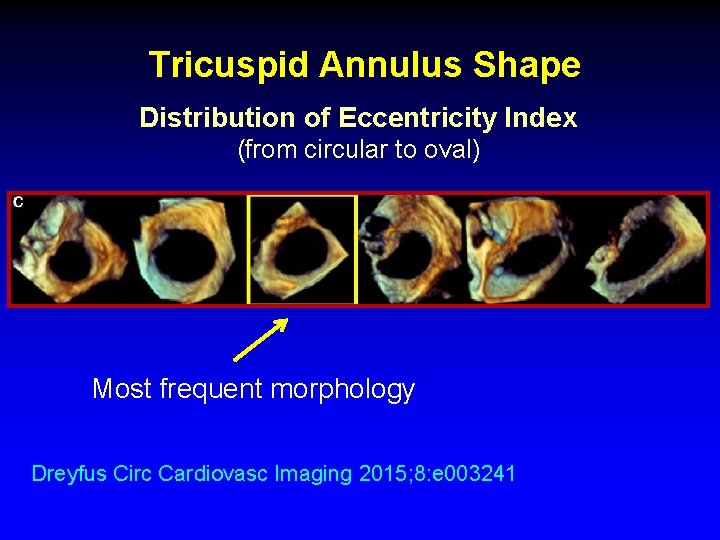
Tricuspid Annulus Shape Distribution of Eccentricity Index (from circular to oval) Most frequent morphology Dreyfus Circ Cardiovasc Imaging 2015; 8: e 003241
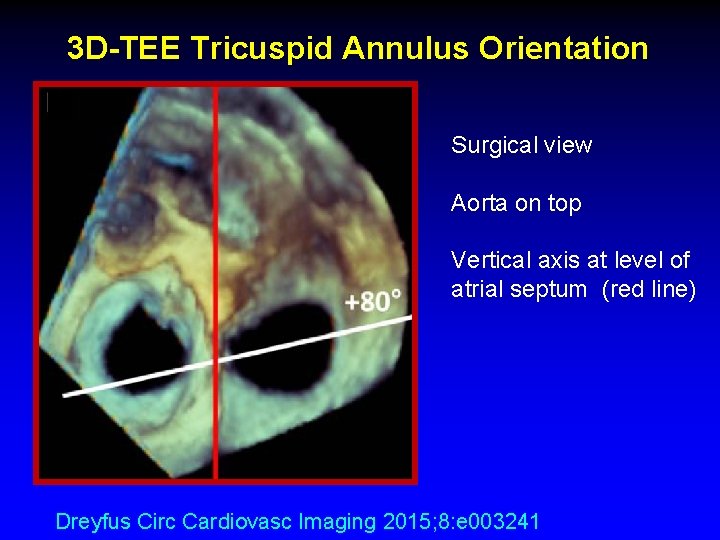
3 D-TEE Tricuspid Annulus Orientation Surgical view Aorta on top Vertical axis at level of atrial septum (red line) Dreyfus Circ Cardiovasc Imaging 2015; 8: e 003241
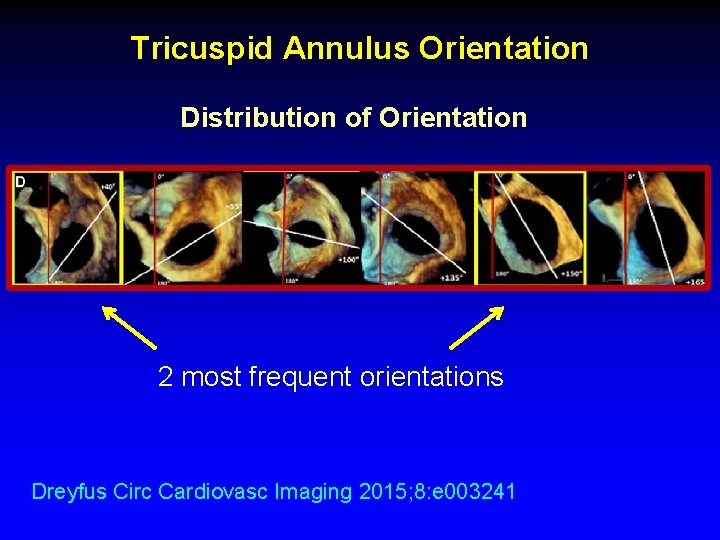
Tricuspid Annulus Orientation Distribution of Orientation 2 most frequent orientations Dreyfus Circ Cardiovasc Imaging 2015; 8: e 003241
Reconstruction of Tricuspid Annulus Brown end-diastole; Green end-systole Owais Ann Thorac Surg 2014; 98(5): 1536 -42
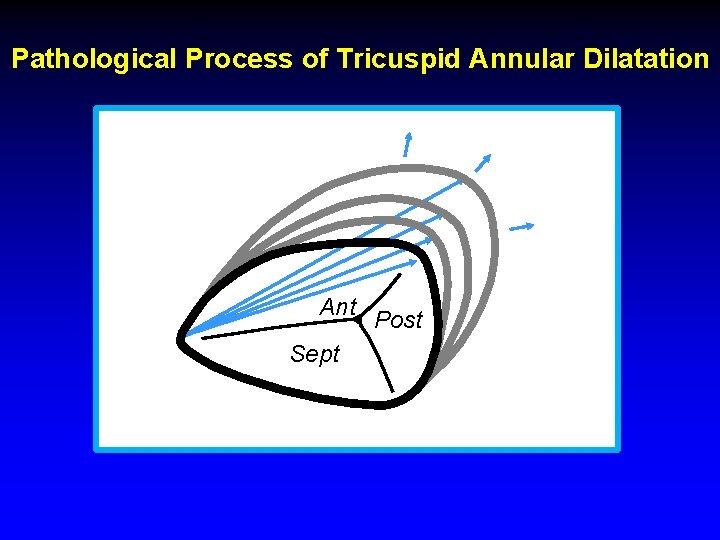
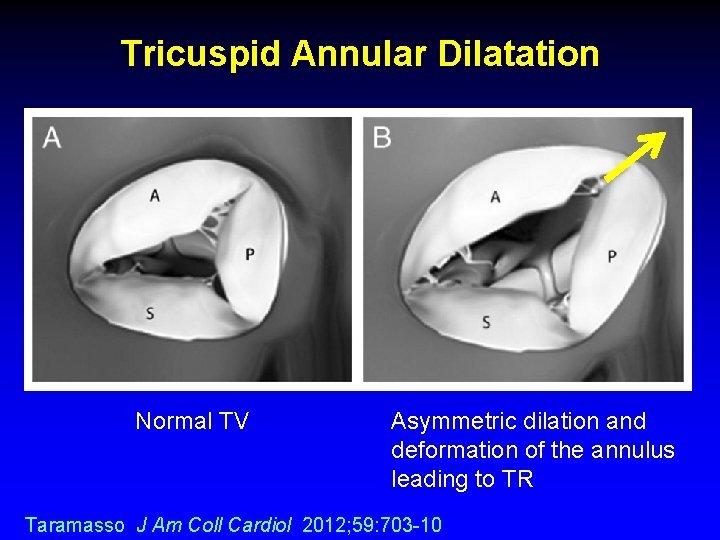
Pathological Process of Tricuspid Annular Dilatation Ant Sept Post
Tricuspid Annular Dilatation Normal TV Asymmetric dilation and deformation of the annulus leading to TR Taramasso J Am Coll Cardiol 2012; 59: 703 -10
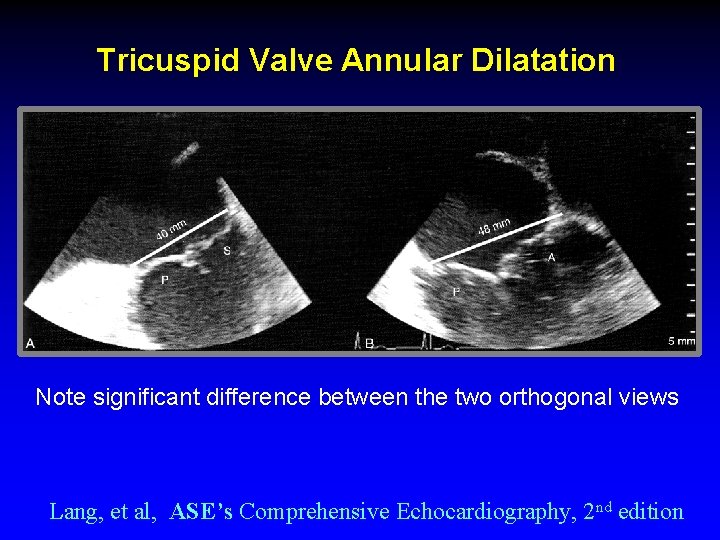
Tricuspid Valve Annular Dilatation Note significant difference between the two orthogonal views Lang, et al, ASE’s Comprehensive Echocardiography, 2 nd edition
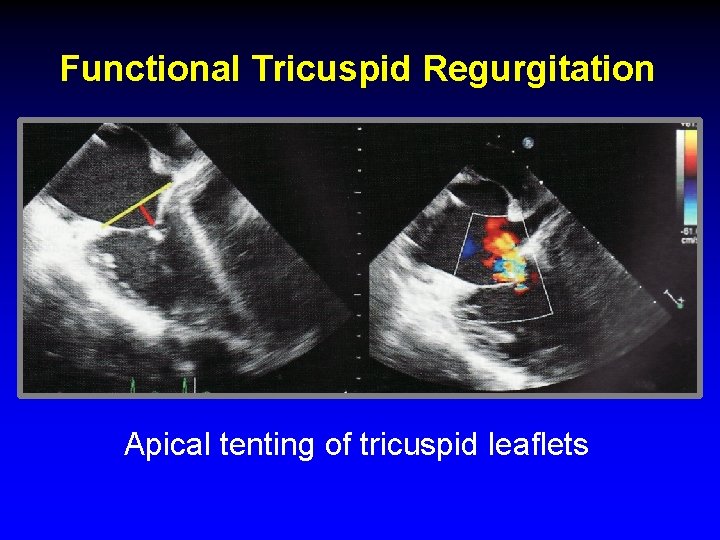
Functional Tricuspid Regurgitation Apical tenting of tricuspid leaflets
Quantitation of TR
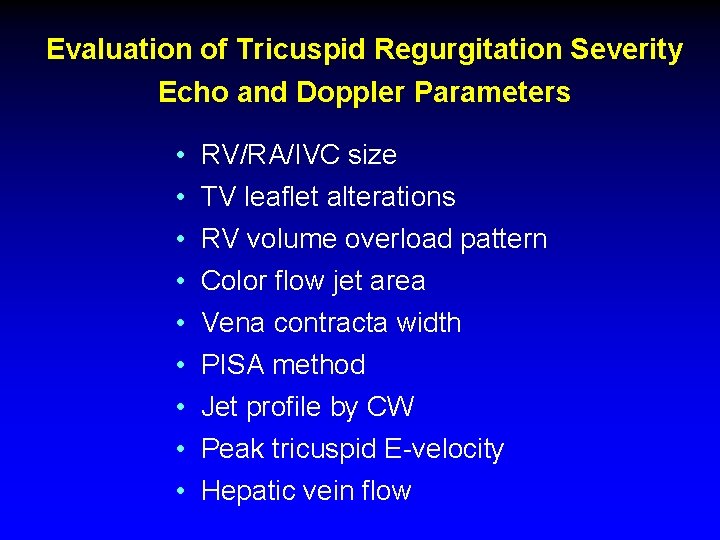
Evaluation of Tricuspid Regurgitation Severity Echo and Doppler Parameters • • • RV/RA/IVC size TV leaflet alterations RV volume overload pattern Color flow jet area Vena contracta width PISA method Jet profile by CW Peak tricuspid E-velocity Hepatic vein flow
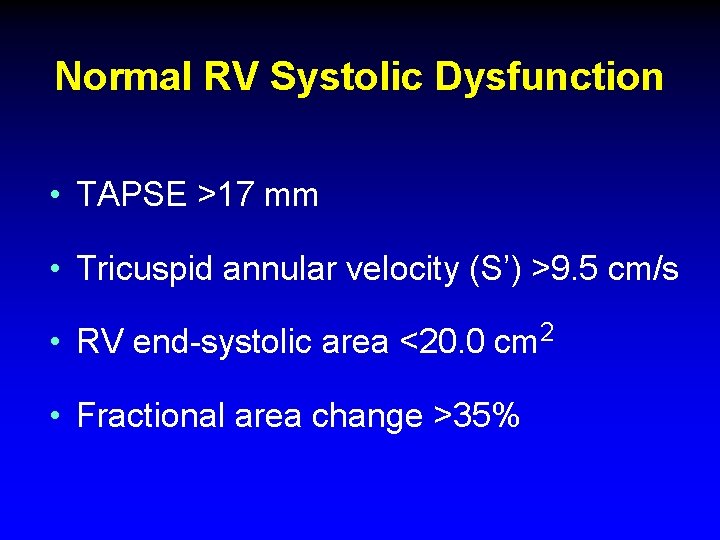
Normal RV Systolic Dysfunction • TAPSE >17 mm • Tricuspid annular velocity (S’) >9. 5 cm/s • RV end-systolic area <20. 0 cm 2 • Fractional area change >35%
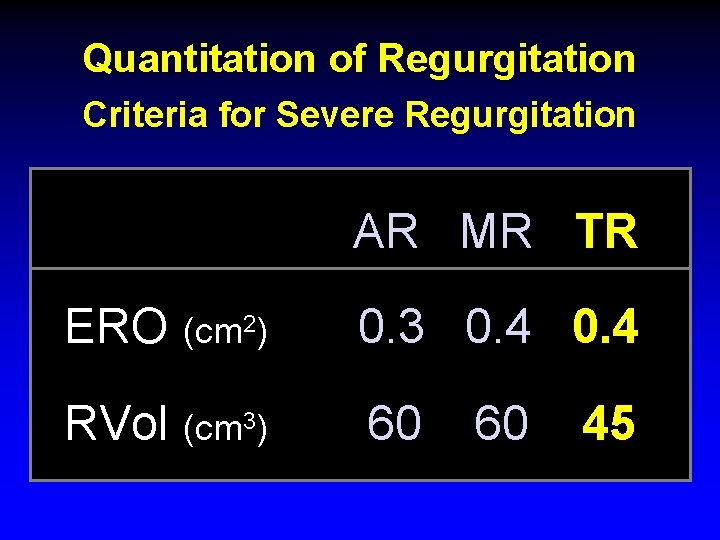
Quantitation of Regurgitation Criteria for Severe Regurgitation AR MR TR ERO (cm 2) 0. 3 0. 4 RVol (cm 3) 60 60 45
Functional TR
Functional Tricuspid Regurgitation Paradigm Shift • Erroneous belief that TR would improve once L-sided disease is resolved • Recent publications provides evidence that favors surgical approach • Thus, careful echo assessment mandated
“TV annuloplasty during MV repair should be considered in pts with tricuspid annular dilatation despite the absence of important tricuspid regurgitation at baseline. . . ” J Thorac Cardiovasc Surg 2011; 1431 -9
J Am Coll Cardiol 2012; 59: 703 -10
“Over the past few years, many investigators have reported evidence in favor of a more aggressive surgical approach to secondary TR” J Am Coll Cardiol 2012; 59: 703 -10
Guidelines
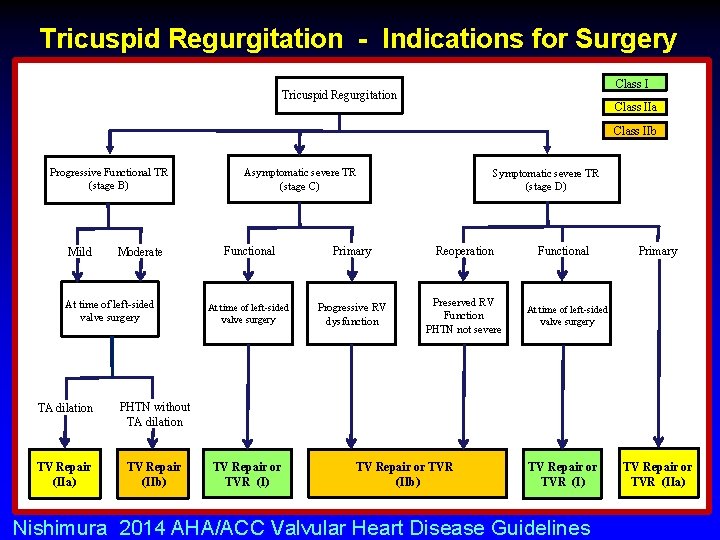
Tricuspid Regurgitation - Indications for Surgery Class I Tricuspid Regurgitation Class IIa Class IIb Progressive Functional TR (stage B) Mild Moderate At time of left-sided valve surgery TA dilation PHTN without TA dilation TV Repair (IIa) TV Repair (IIb) Asymptomatic severe TR (stage C) Symptomatic severe TR (stage D) Functional Primary Reoperation At time of left-sided valve surgery Progressive RV dysfunction Preserved RV Function PHTN not severe TV Repair or TVR (I) TV Repair or TVR (IIb) Functional Primary At time of left-sided valve surgery TV Repair or TVR (I) Nishimura 2014 AHA/ACC Valvular Heart Disease Guidelines TV Repair or TVR (IIa)
Tricuspid Regurgitation Surgical Approaches
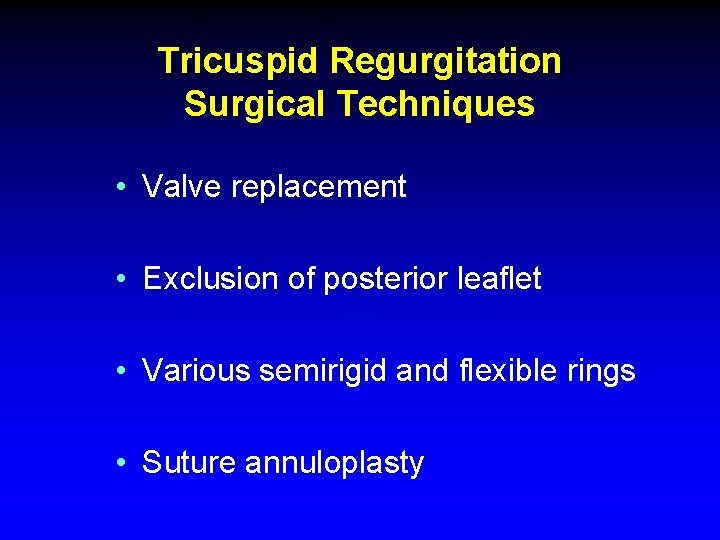
Tricuspid Regurgitation Surgical Techniques • Valve replacement • Exclusion of posterior leaflet • Various semirigid and flexible rings • Suture annuloplasty
De Vega Repair
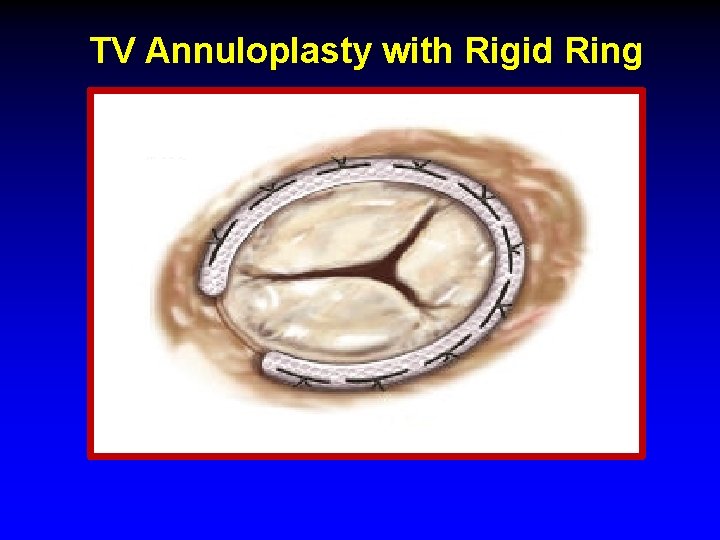
TV Annuloplasty with Rigid Ring
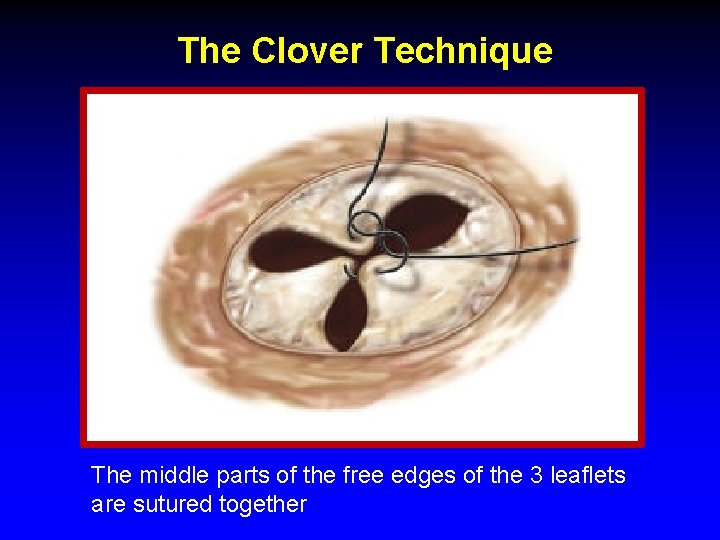
The Clover Technique The middle parts of the free edges of the 3 leaflets are sutured together
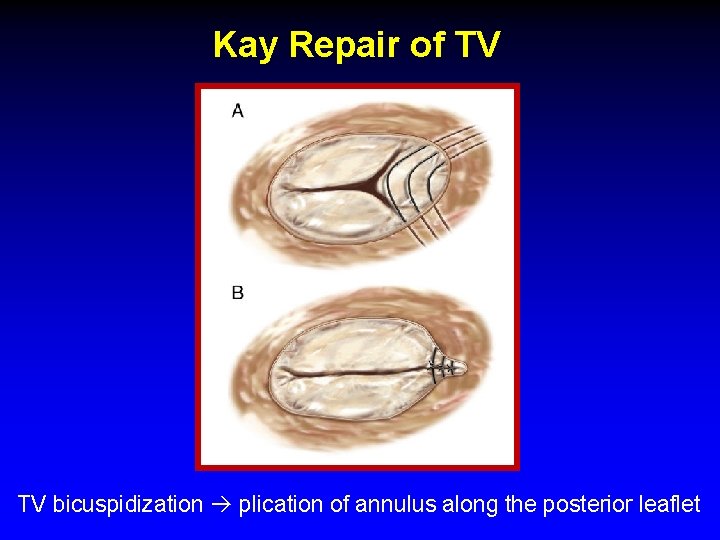
Kay Repair of TV TV bicuspidization plication of annulus along the posterior leaflet
Tricuspid Valve Interventions
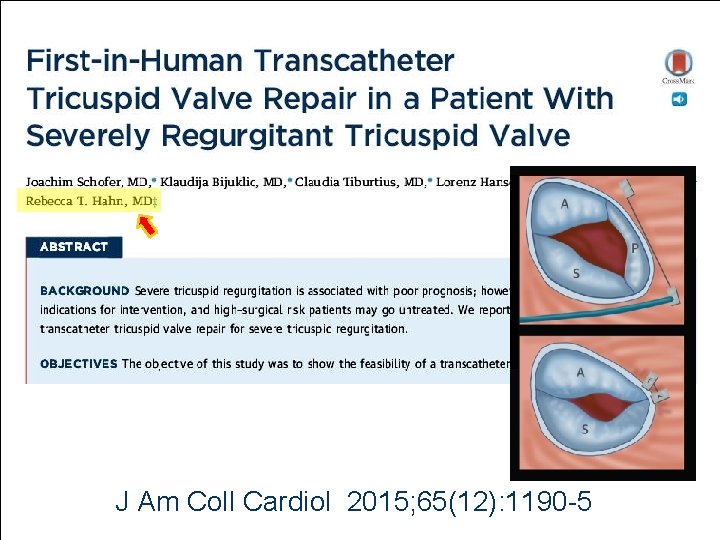
J Am Coll Cardiol 2015; 65(12): 1190 -5
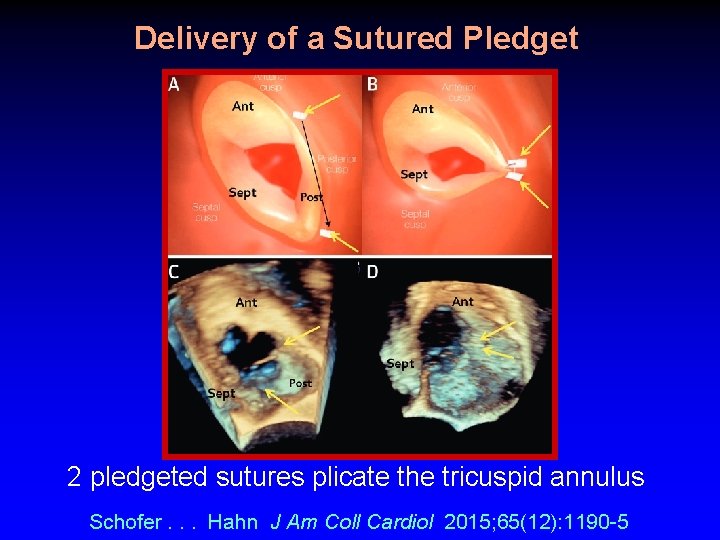
Delivery of a Sutured Pledget 2 pledgeted sutures plicate the tricuspid annulus Schofer. . . Hahn J Am Coll Cardiol 2015; 65(12): 1190 -5
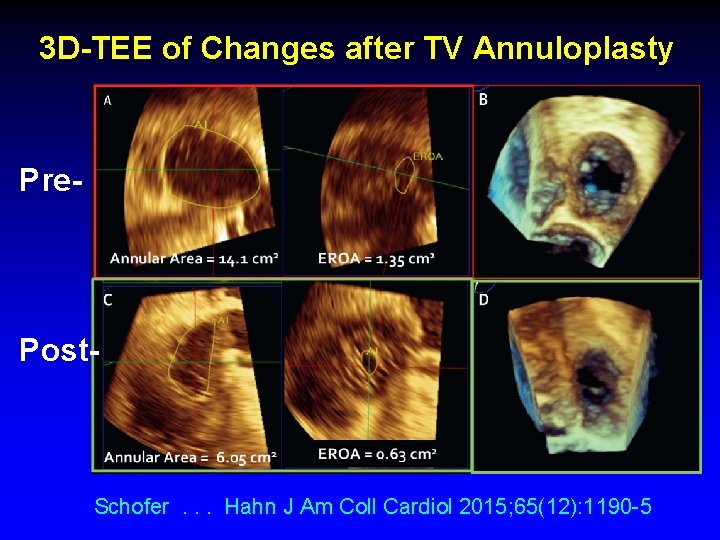
3 D-TEE of Changes after TV Annuloplasty Pre- Post- Schofer. . . Hahn J Am Coll Cardiol 2015; 65(12): 1190 -5
Wánghòu Structural Heart Disease Queen of Columbia