Chest Radiography Interpretation M Chadi Alraies MD Chief






















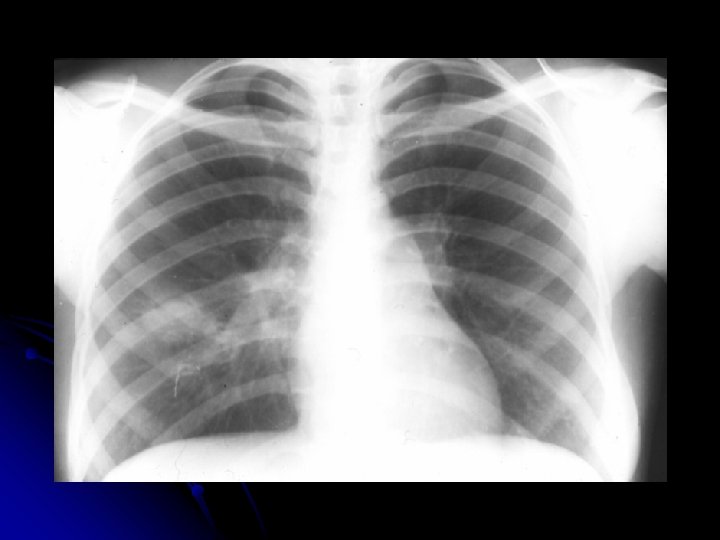
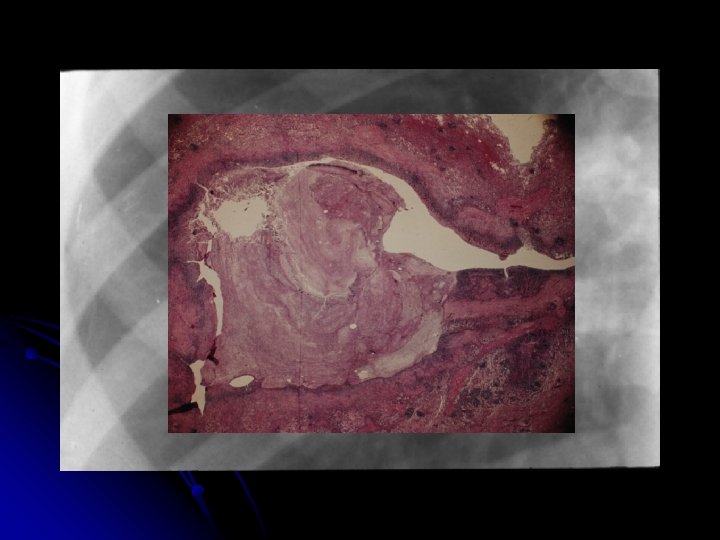
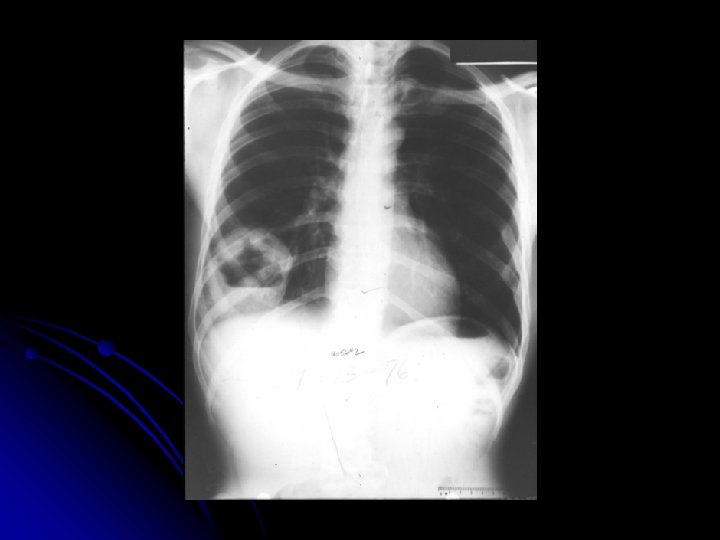
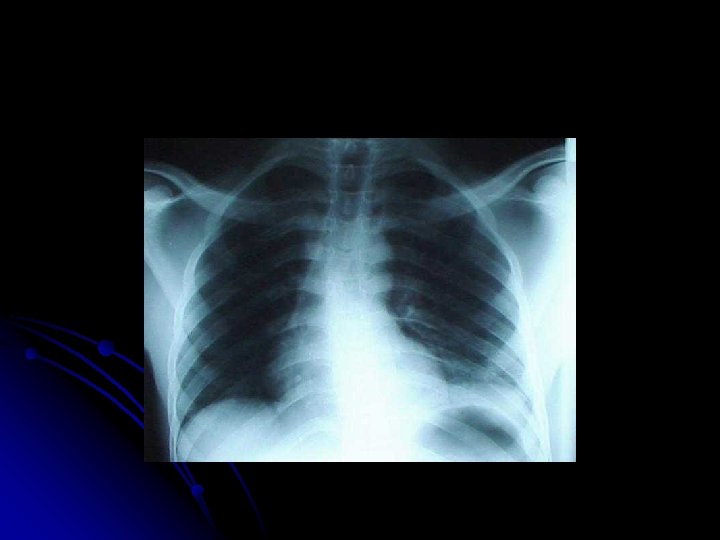
- Slides: 103
Chest Radiography Interpretation M Chadi Alraies, MD Chief Medical Resident Case Western Reserve University SVCH M C Alraies 1
Reading CXR’s Have a structured method! l Be consistent with that method l Don’t take short cuts l LOOK AT ALL YOUR PATIENTS XRAYS YOURSELF (and with your resident of course!) l PRACTICE… PRACTICE l
What is a Chest Radiograph? SHADOW
Start at the beginning l. Identification ! l l l Correct patient Correct date and time Correct examination Are old films available? DO THIS EVERYTIME – It buys you time and is
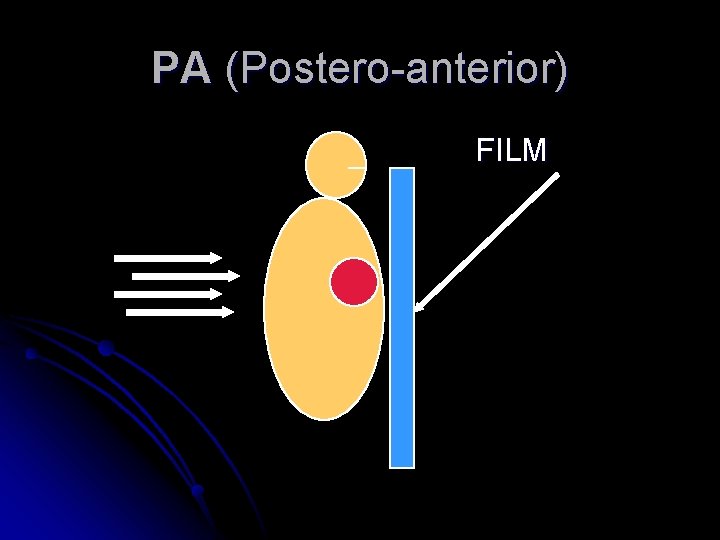
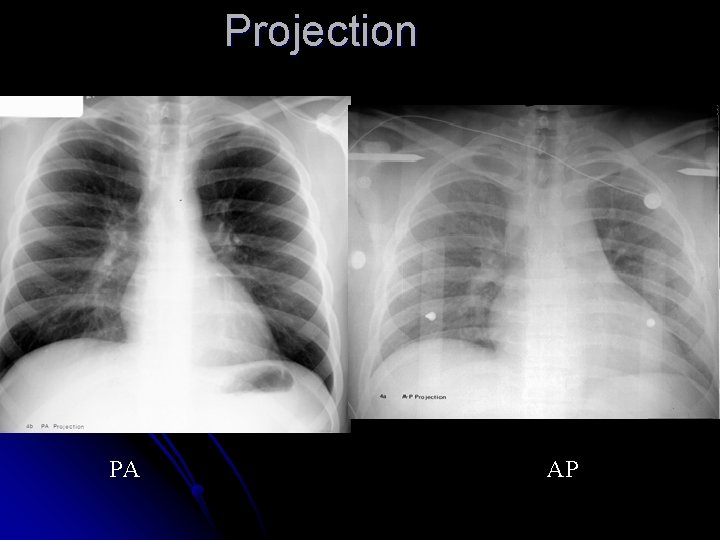
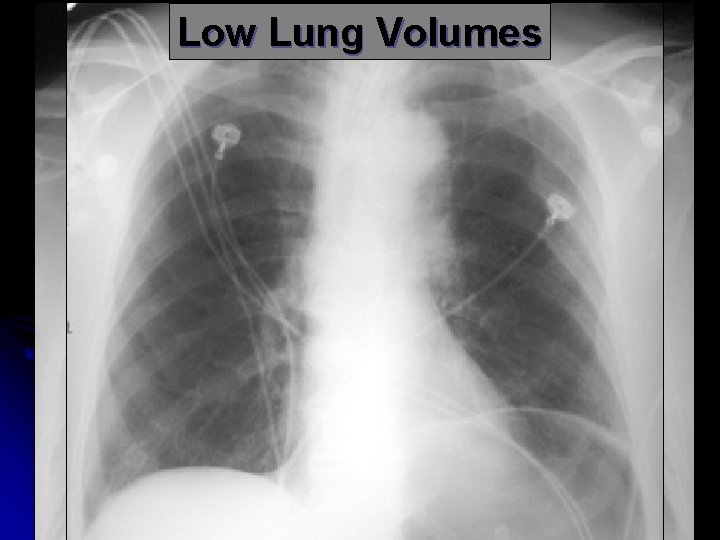
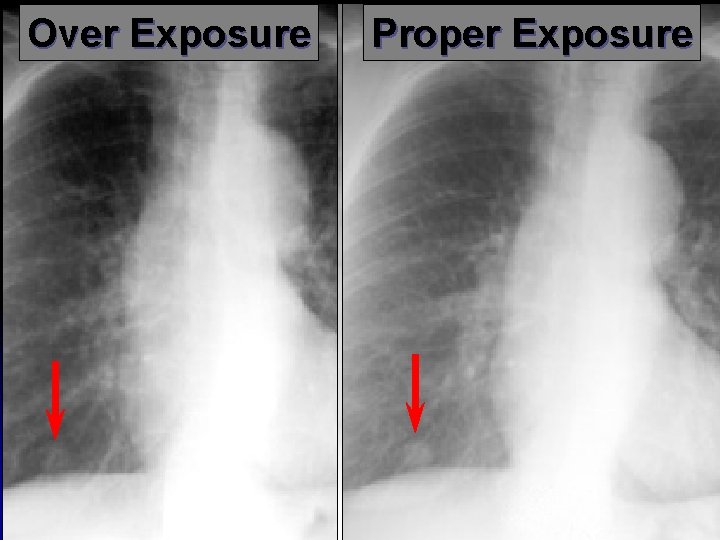
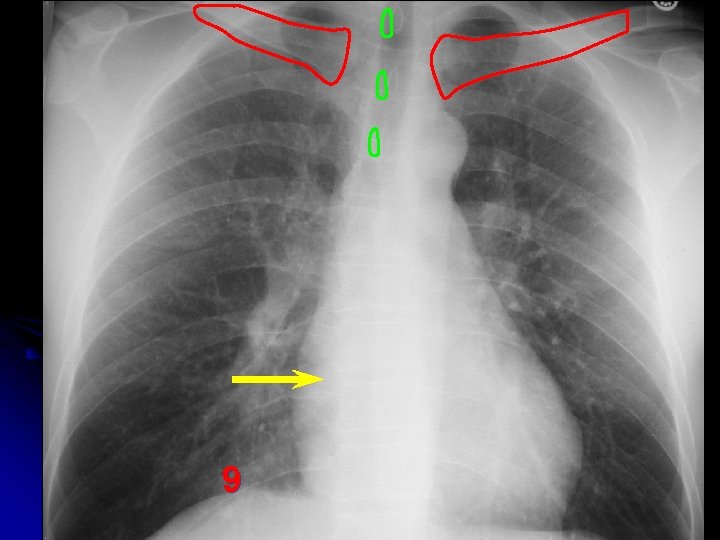
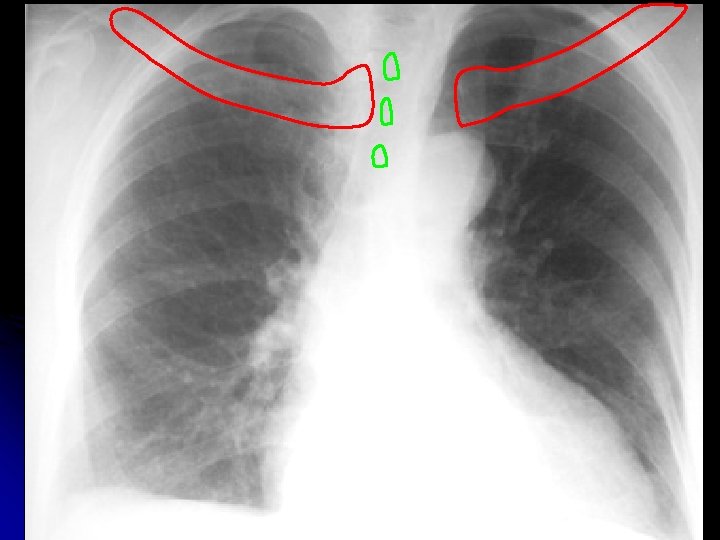
Approach to the CXR: Technical Aspects l l l Projection – PA or AP Position – Upright or Supine (Supine folks are sick) Inspiratory effort l l Penetration l l 9 -10 posterior ribs thoracic intervertebral disc space just visible Positioning/rotation l medial clavicle heads equidistant to spinous process
Projection
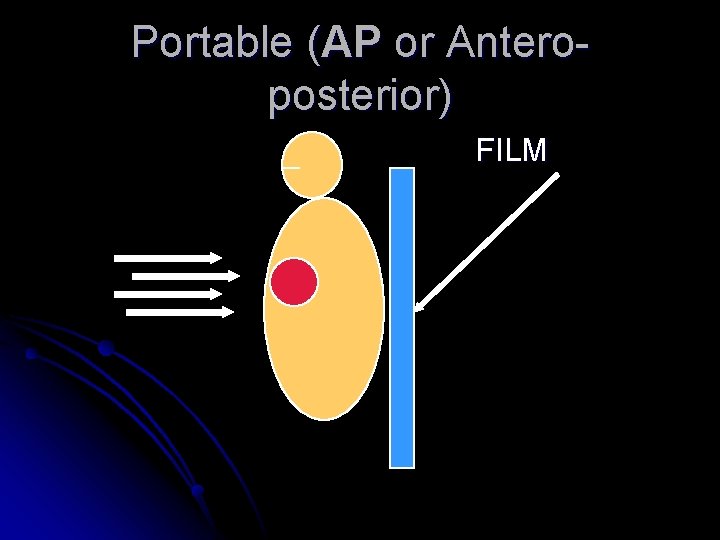
Portable (AP or Anteroposterior) FILM
PA (Postero-anterior) FILM
Projection PA AP
Low Lung Volumes
Over Exposure Proper Exposure
9
Mental Break
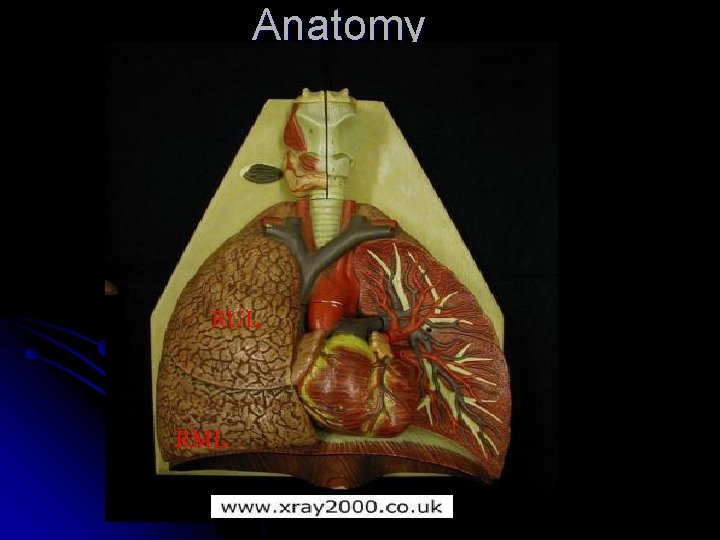
Anatomy RUL RML
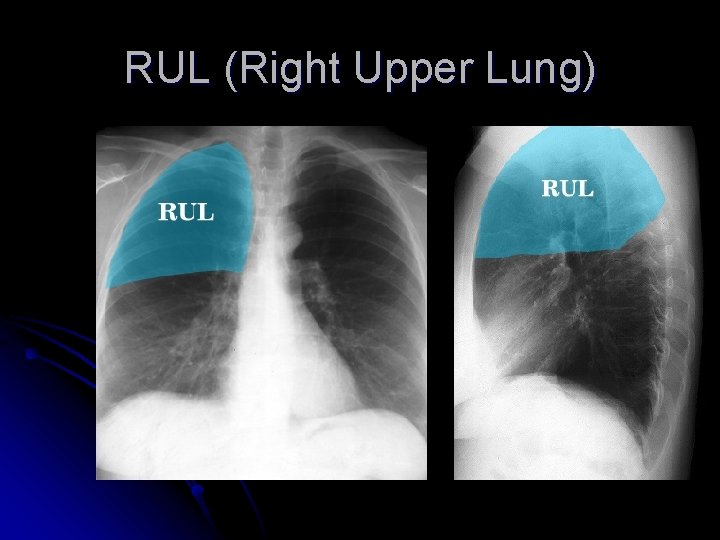
RUL (Right Upper Lung)
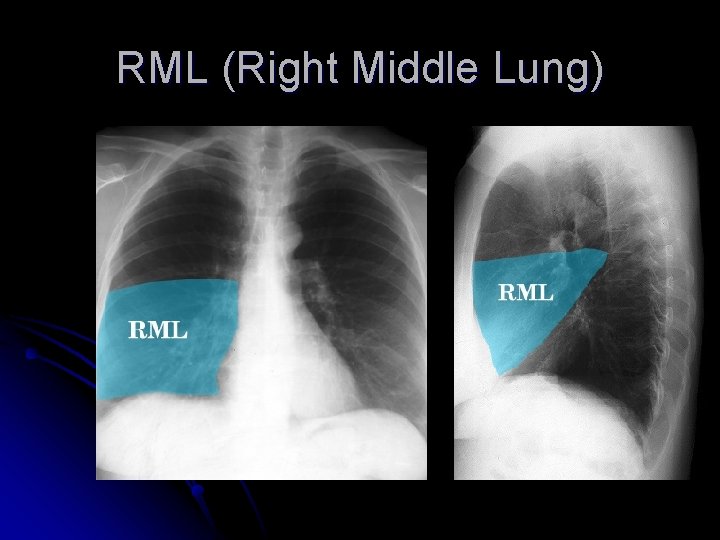
RML (Right Middle Lung)
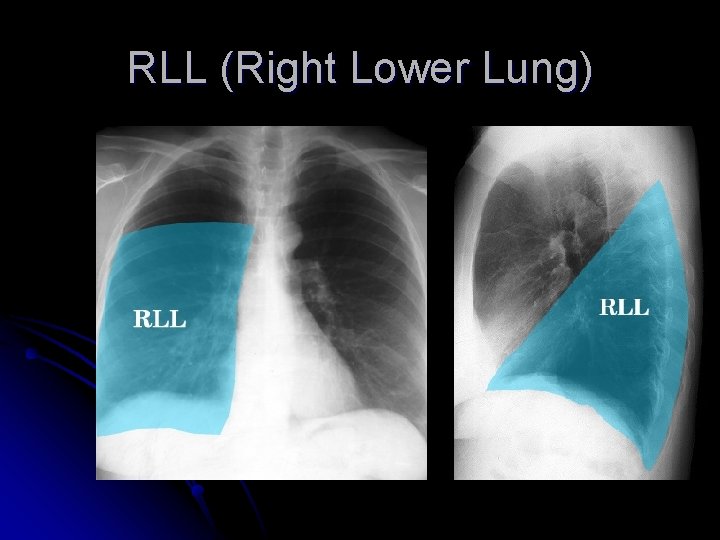
RLL (Right Lower Lung)
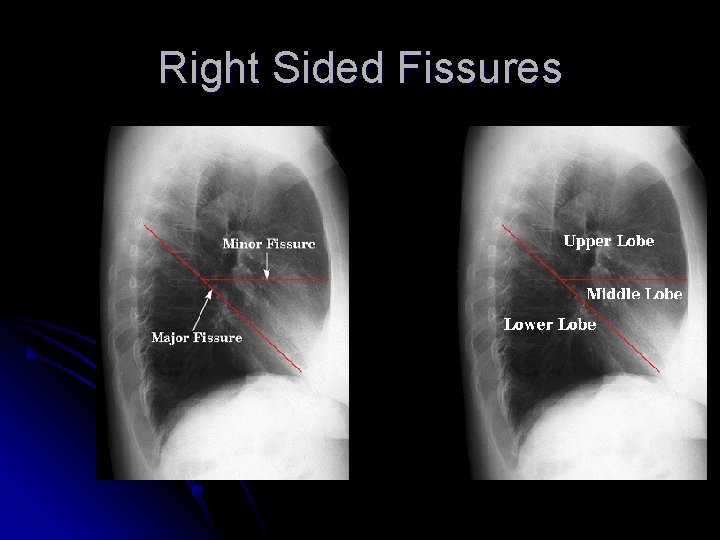
Right Sided Fissures
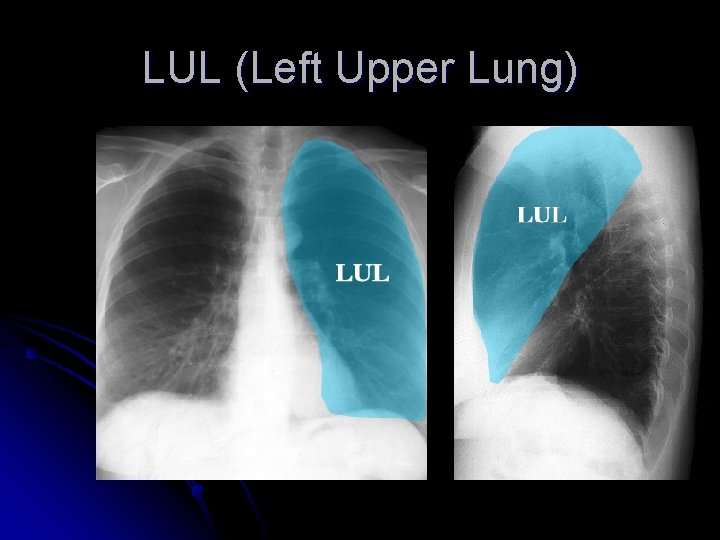
LUL (Left Upper Lung)
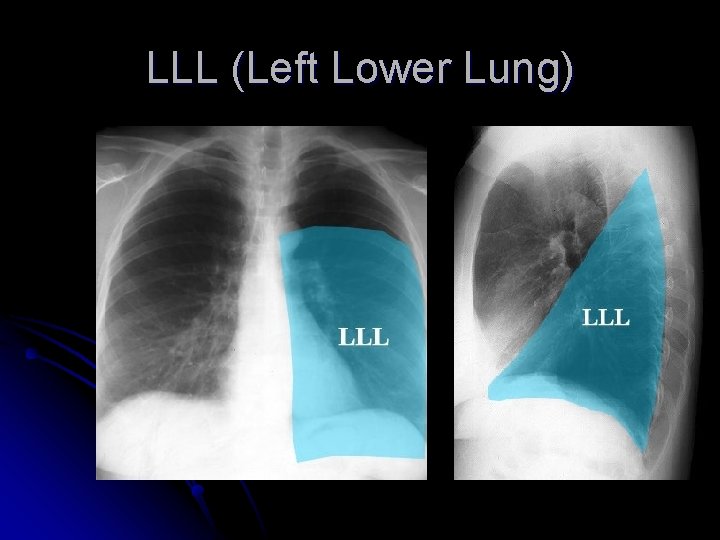
LLL (Left Lower Lung)
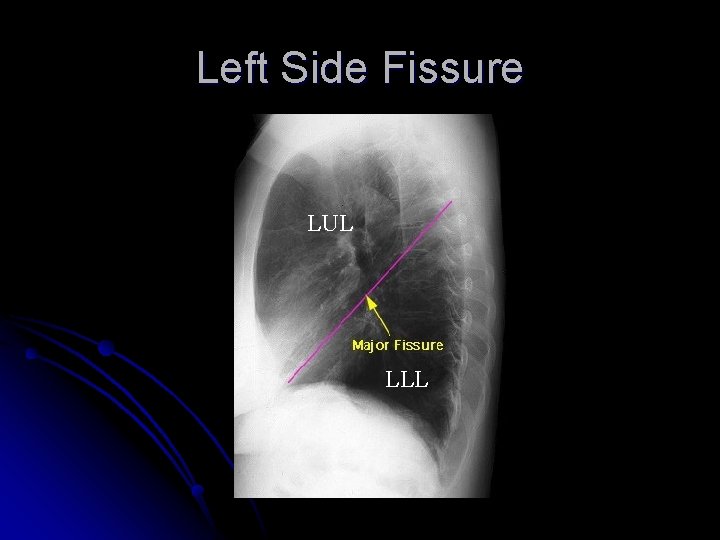
Left Side Fissure LUL LLL
What to Evaluate Lungs l Pleural surfaces l Cardiomediastinal contours l Bones and soft tissues l Abdomen l
Where to Look Apices l Retrocardiac areas (left and right) l Below diaphragm l
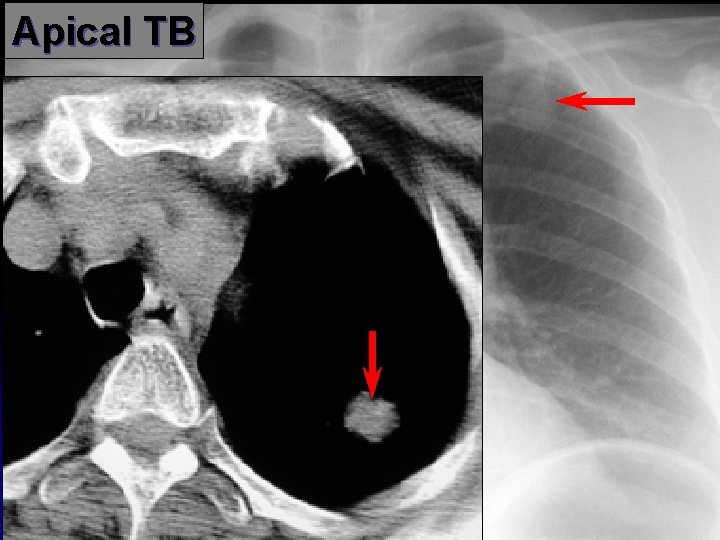
Apical TB
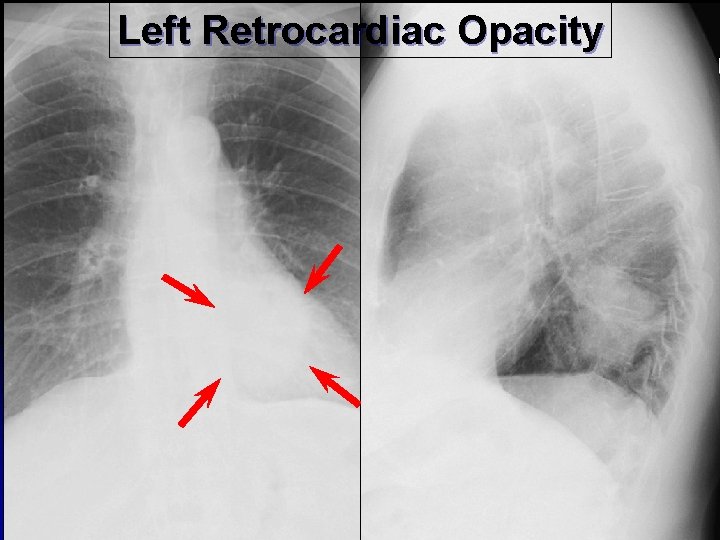
Left Retrocardiac Opacity
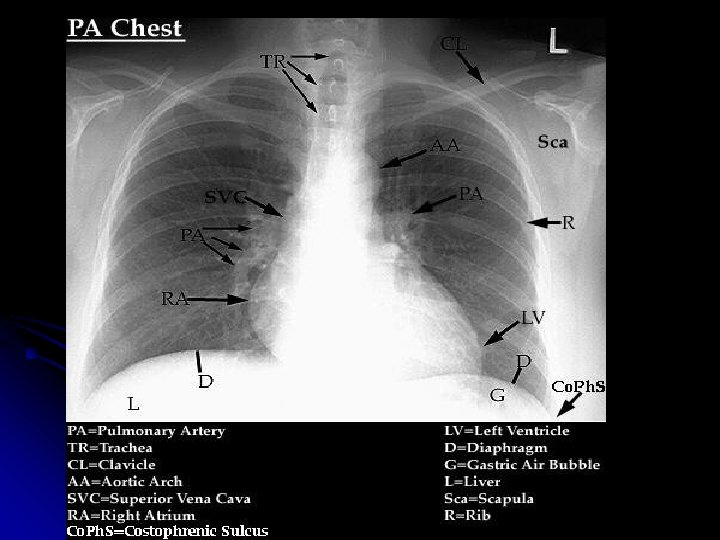
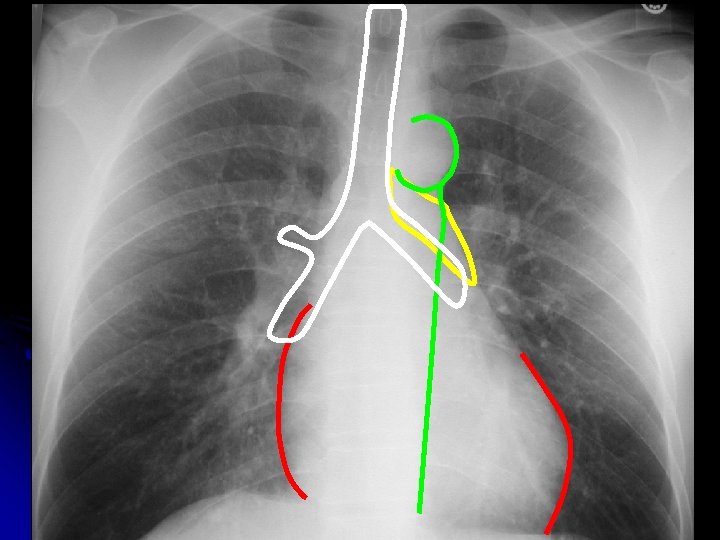
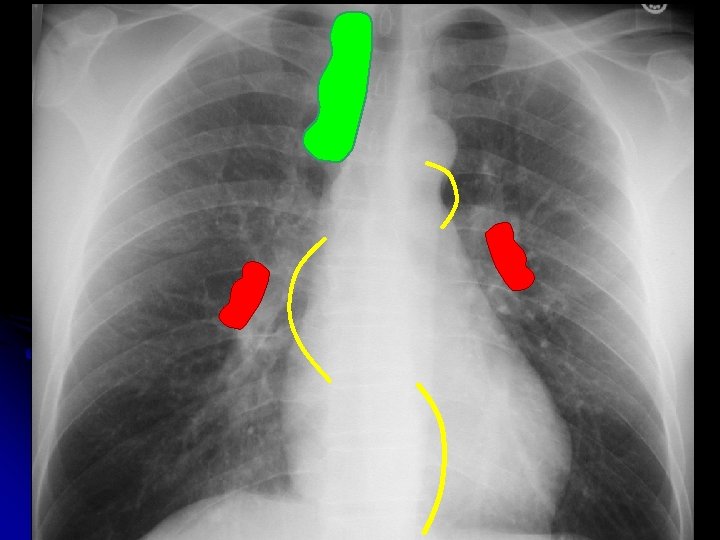
Normal Anatomy: Frontal CXR Heart l Aorta l Pulmonary arteries l Airways l Diaphragm/costophrenic sulci l
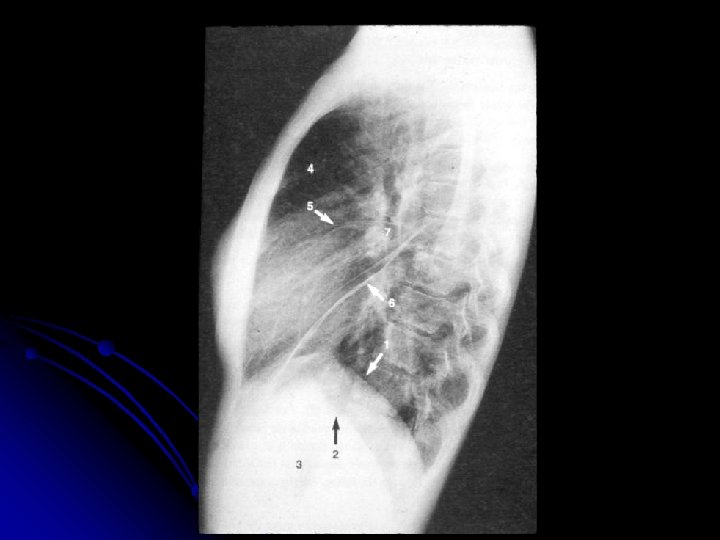
Normal Anatomy: Lateral Heart l Aorta l Pulmonary arteries l Airways l Spine l
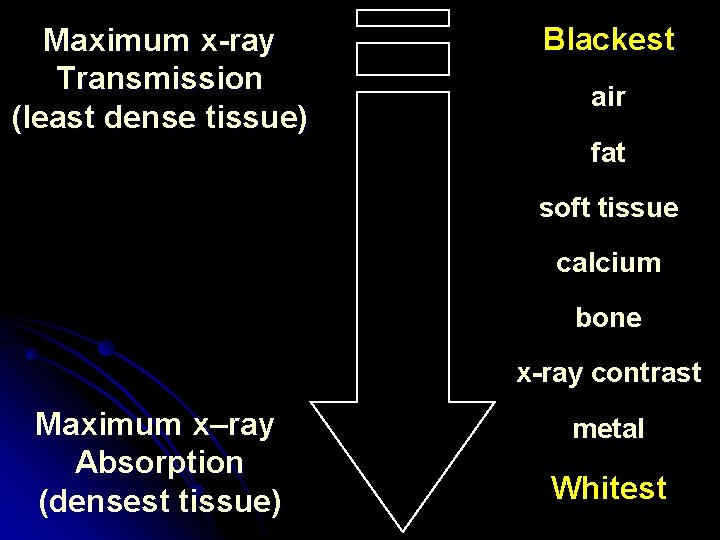
Maximum x-ray Transmission (least dense tissue) Blackest air fat soft tissue calcium bone x-ray contrast Maximum x–ray Absorption (densest tissue) metal Whitest
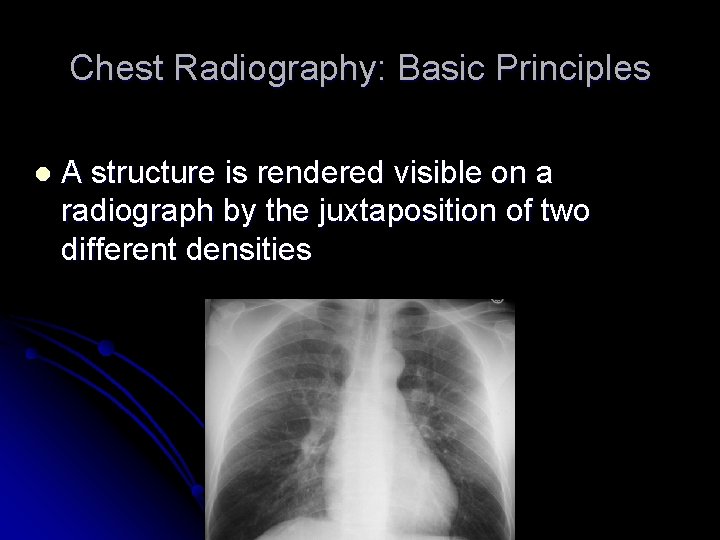
Chest Radiography: Basic Principles l A structure is rendered visible on a radiograph by the juxtaposition of two different densities
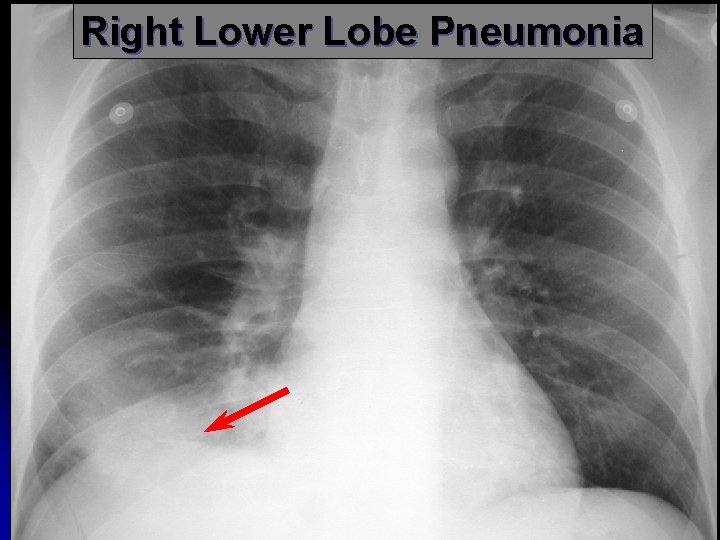
Silhouette Sign Loss of the expected interface normally created by juxtaposition of two structures of different density l No boundary can be seen between two structures of similar density l
Right Lower Lobe Pneumonia
Differential X-Ray Absorption The absence of a normal interface may indicate disease; l The presence of an unexpected interface may also indicate disease l The presence of interfaces can be used to localize abnormalities l
Chest Radiographic Patterns of Disease Air space opacity l Interstitial opacity l Nodules and masses l Lymphadenopathy l Cysts and cavities l Lung volumes l Pleural diseases l
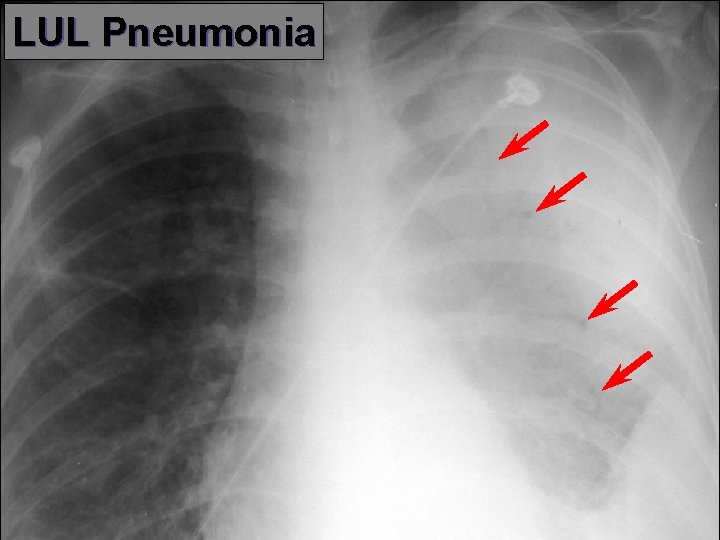
LUL Pneumonia
Air Space Opacity l Components: l air bronchogram: air-filled bronchus surrounded by airless lung l confluent opacity extending to pleural surfaces l segmental distribution
Air Space Opacity: DDX Blood (hemorrhage) l Pus (pneumonia) l Water (edema) l l hydrostatic or non-cardiogenic Cells (tumor) l Protein/fat: alveolar proteinosis and lipoid pneumonia l
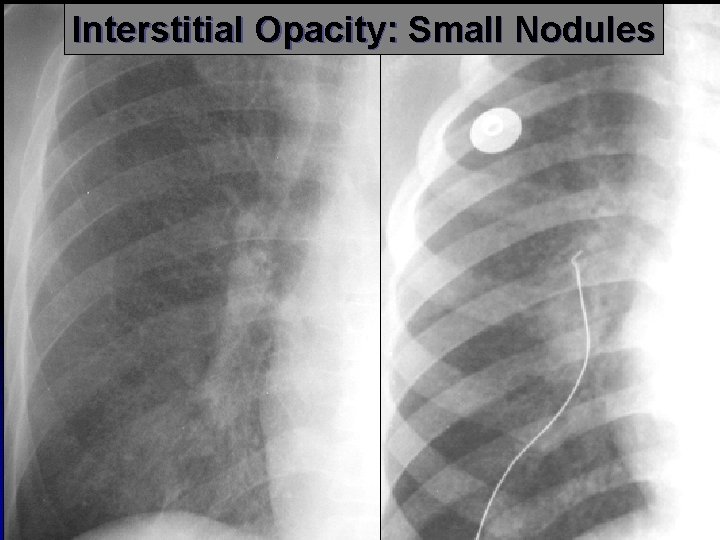
Interstitial Opacity: Small Nodules
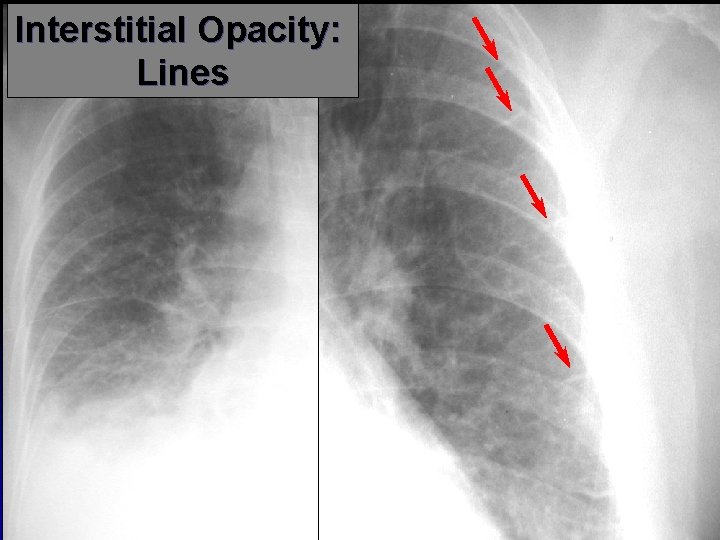
Interstitial Opacity: Lines
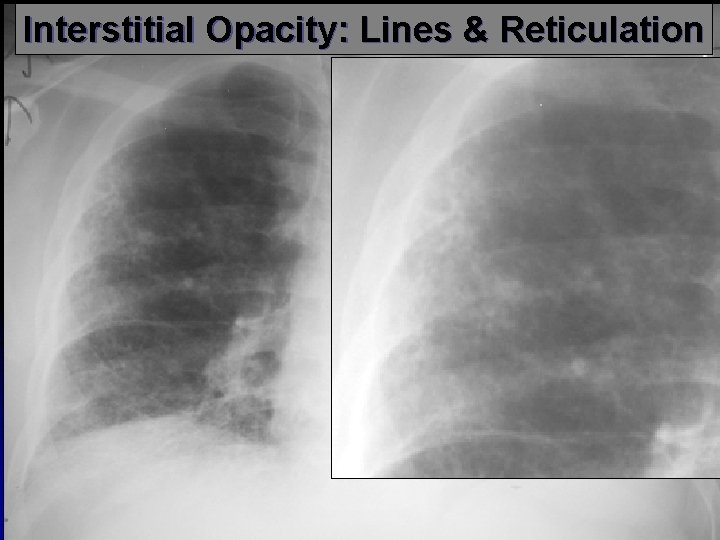
Interstitial Opacity: Lines & Reticulation
Interstitial Opacity l Hallmarks: l small, well-defined nodules l lines l l interlobular septal thickening fibrosis l reticulation
Interstitial Opacity: DDX Idiopathic interstitial pneumonias l Infections (TB, viruses) l Edema l Hemorrhage l Non–infectious inflammatory lesions l l sarcoidosis l Tumor
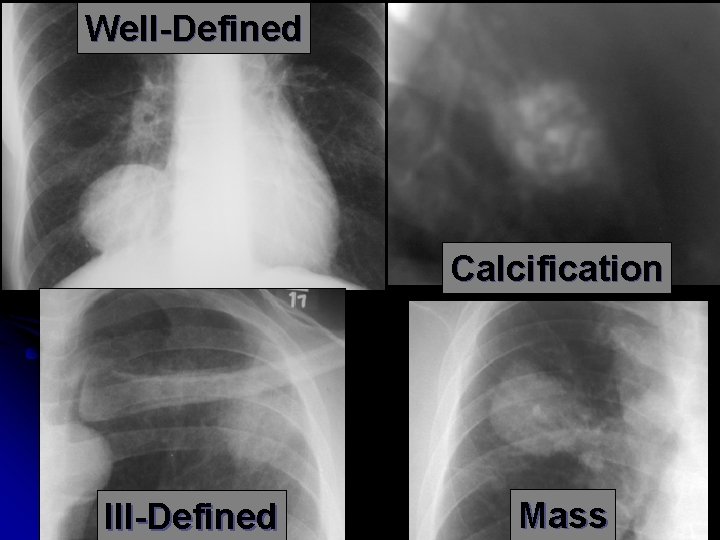
Well-Defined Calcification Ill-Defined Mass
Nodules and Masses Nodule: any pulmonary lesion represented in a radiograph by a sharply defined, discrete, nearly circular opacity 2 -30 mm in diameter l Mass: larger than 3 cm l
Nodules and Masses l Qualifiers: l single or multiple l size l border definition l presence or absence of calcification l location
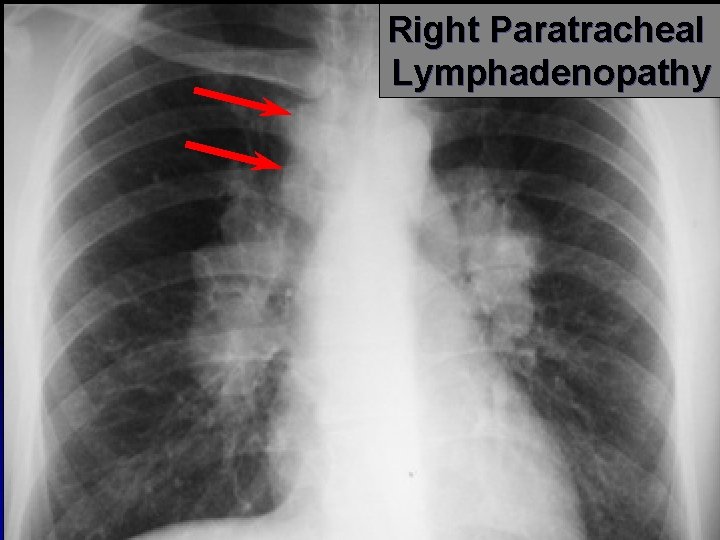
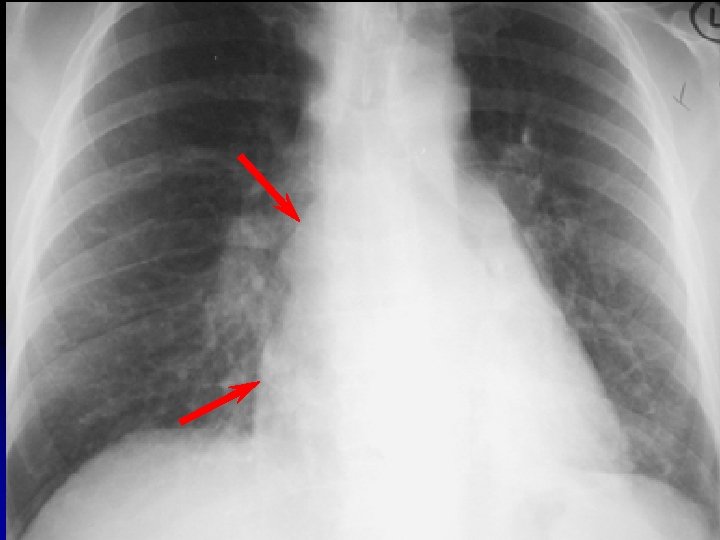
Right Paratracheal Lymphadenopathy
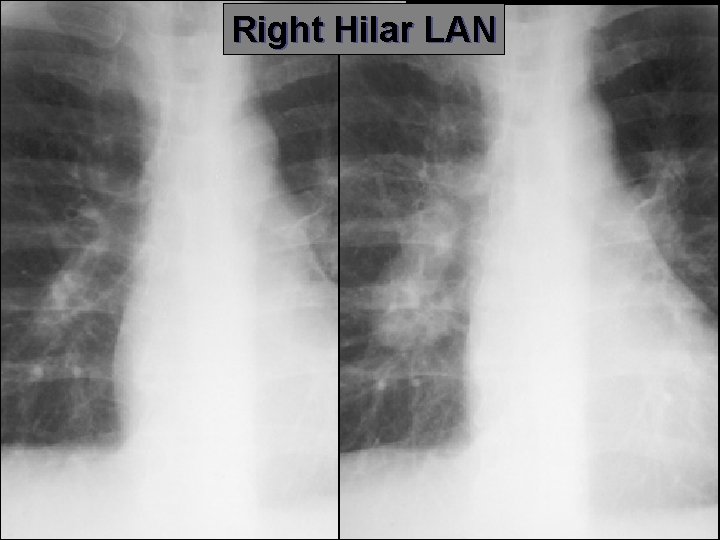
Right Hilar LAN
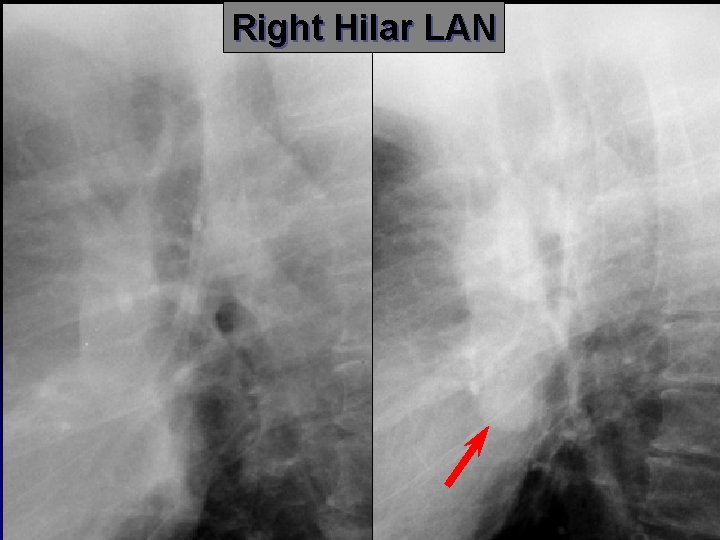
Right Hilar LAN
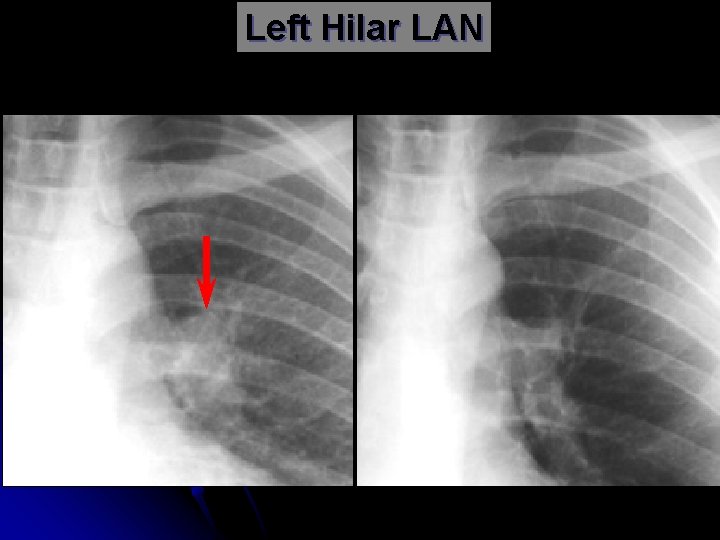
Left Hilar LAN
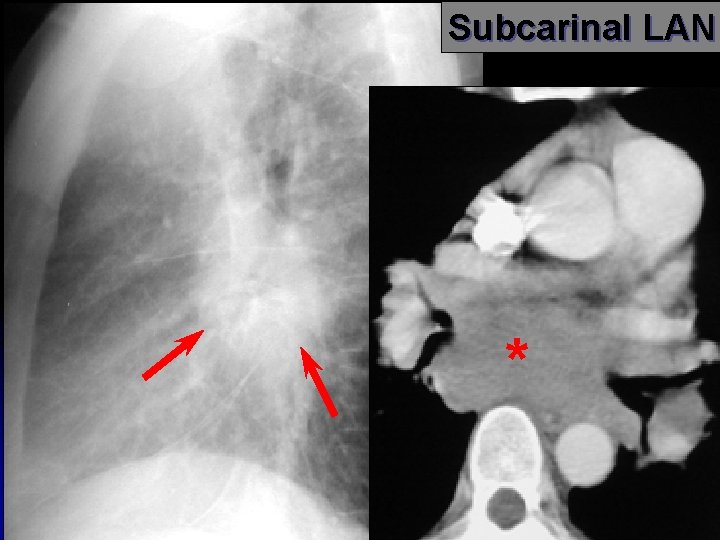
Subcarinal LAN *
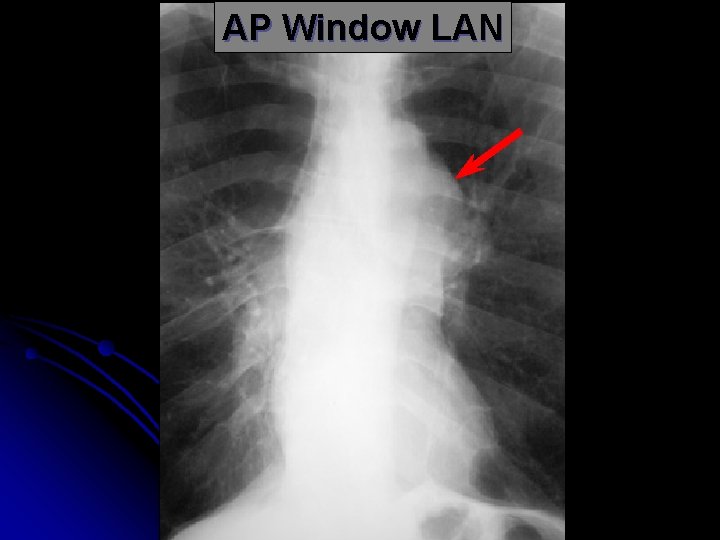
AP Window LAN
Lymphadenopathy l Non-specific presentations: l mediastinal widening l hilar prominence l Specific patterns: l particular station enlargement
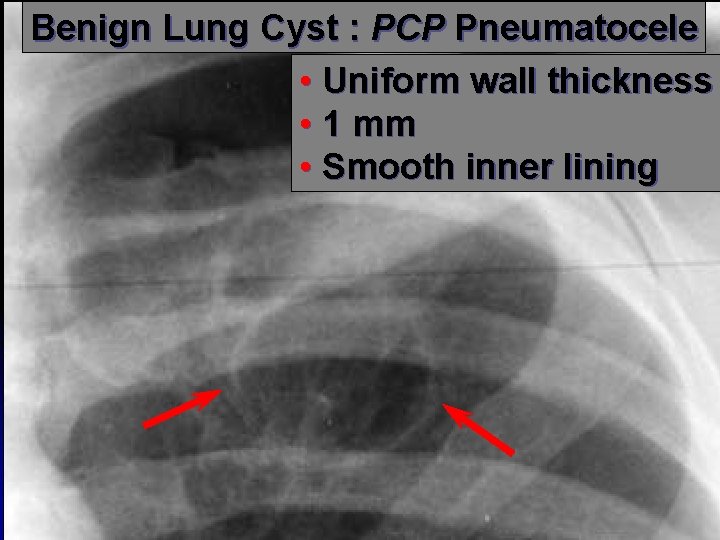
Cysts & Cavities Cyst: abnormal pulmonary parenchymal space, not containing lung but filled with air and/or fluid, congenital or acquired, with a wall thickness greater than 1 mm l epithelial lining often present l
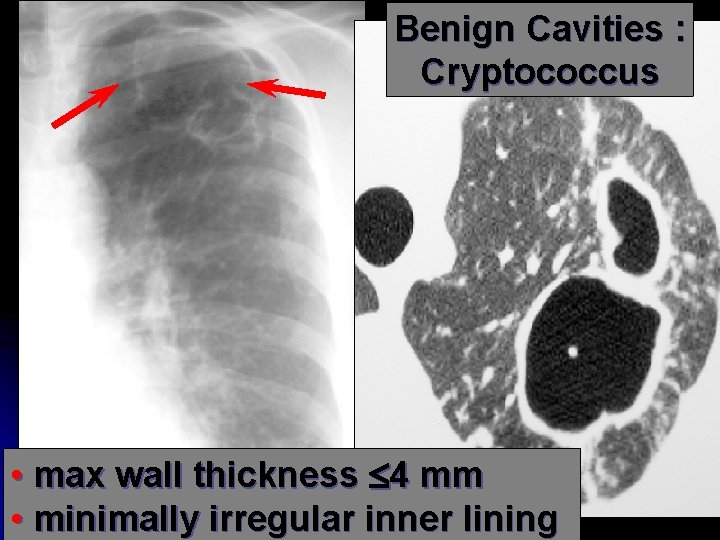
Cysts & Cavities l Cavity: abnormal pulmonary parenchymal space, not containing lung but filled with air and/or fluid, caused by tissue necrosis, with a definitive wall greater than 1 mm in thickness and comprised of inflammatory and/or neoplastic elements
Benign Lung Cyst : PCP Pneumatocele • Uniform wall thickness • 1 mm • Smooth inner lining
Benign Cavities : Cryptococcus • max wall thickness 4 mm • minimally irregular inner lining
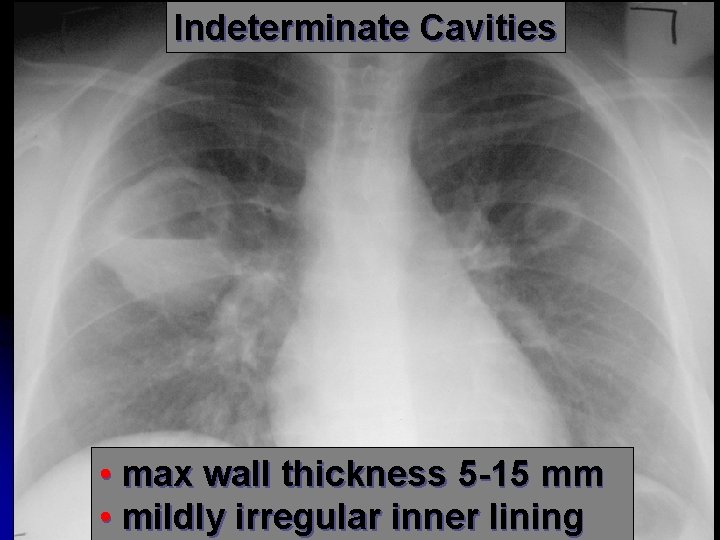
Indeterminate Cavities • max wall thickness 5 -15 mm • mildly irregular inner lining
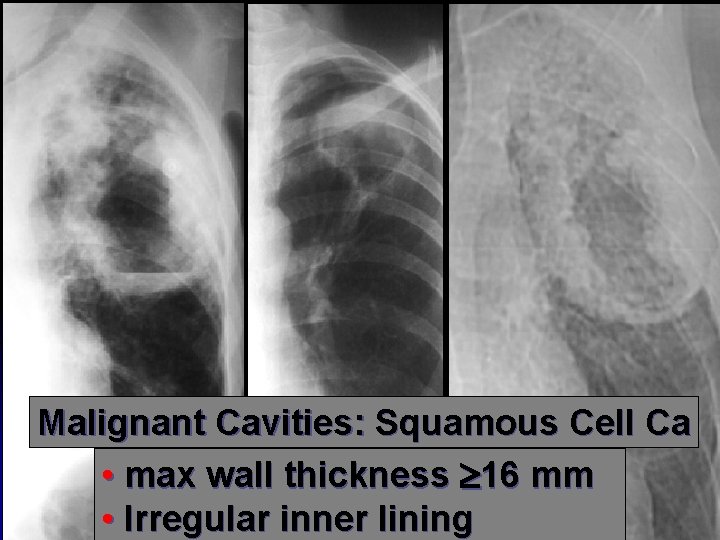
Malignant Cavities: Squamous Cell Ca • max wall thickness 16 mm • Irregular inner lining
Cysts & Cavities l Characterize: l wall thickness at thickest portion l inner lining l presence/absence of air/fluid level l number and location
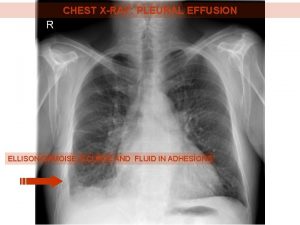
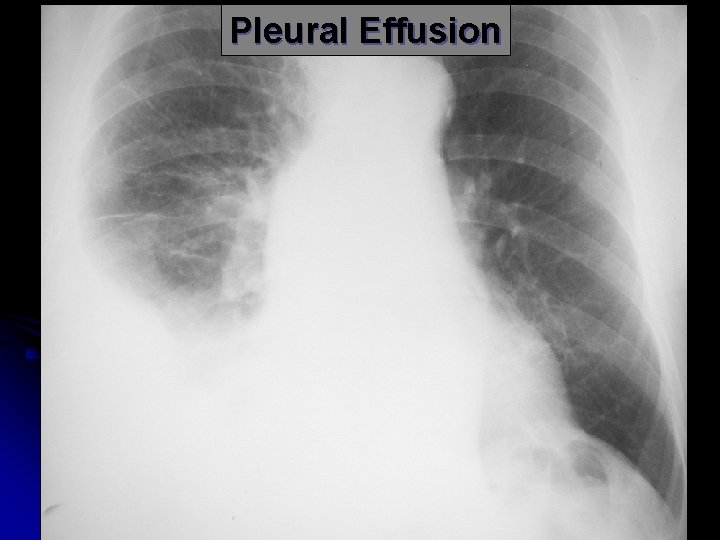
Pleural Effusion
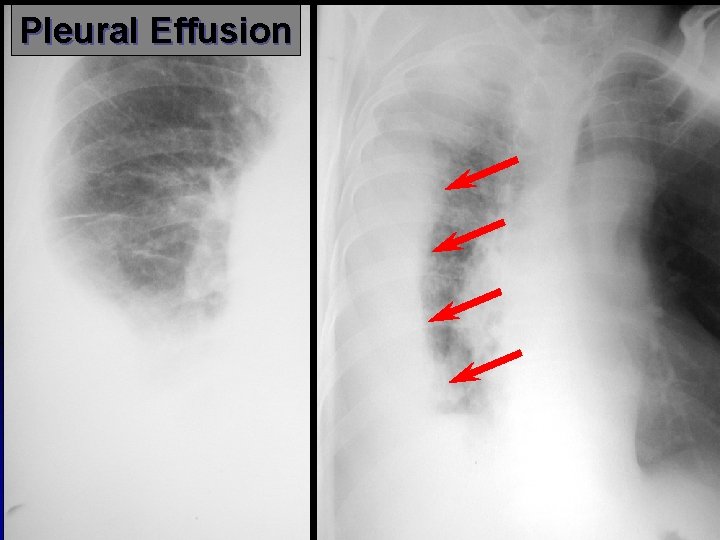
Pleural Effusion
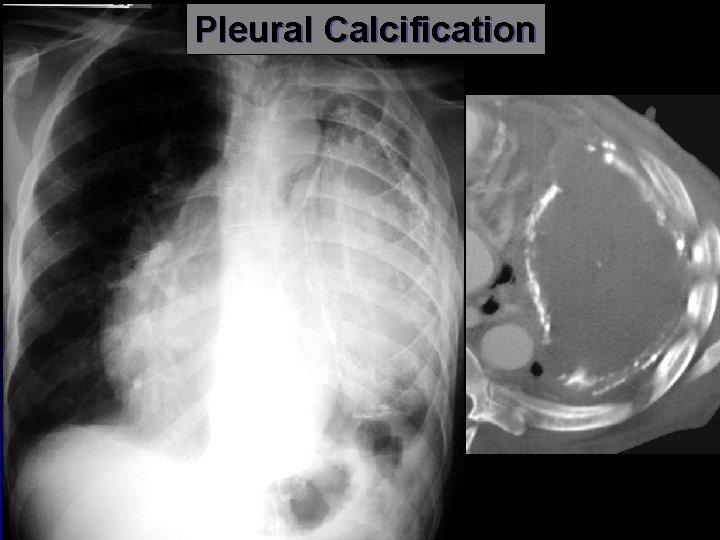
Pleural Calcification
Pleural Disease: Basic Patterns l Effusion l angle blunting to massive l mobility l Thickening l distortion, no mobility Mass l Air l Calcification l
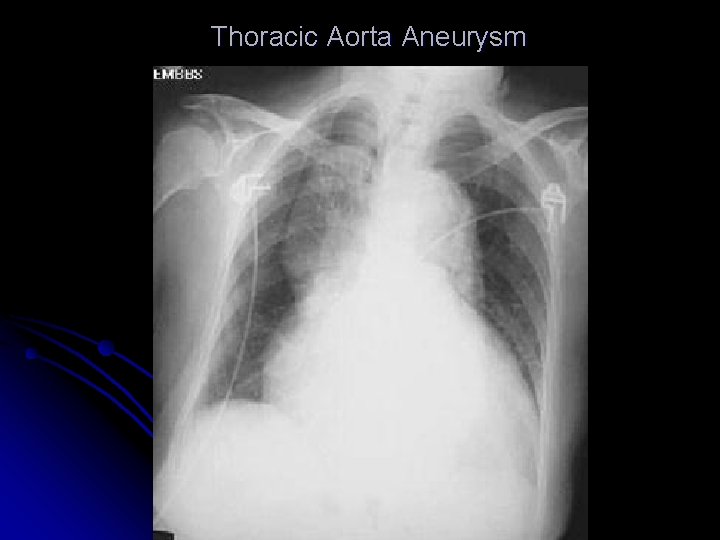
Thoracic Aorta Aneurysm
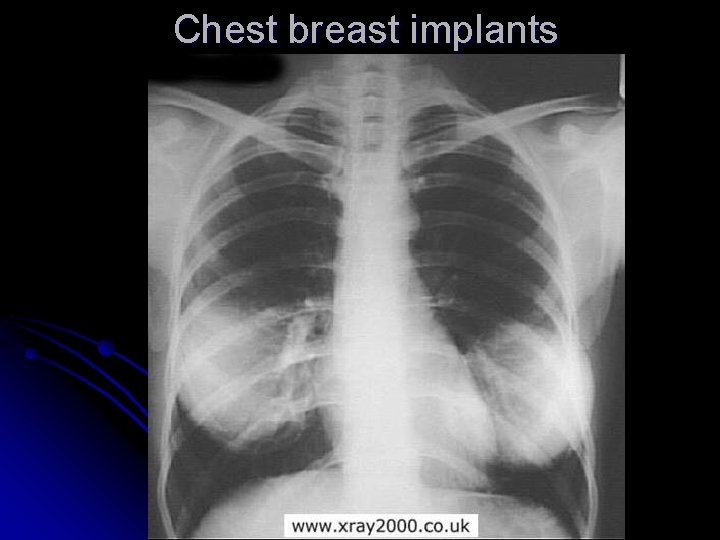
Chest breast implants
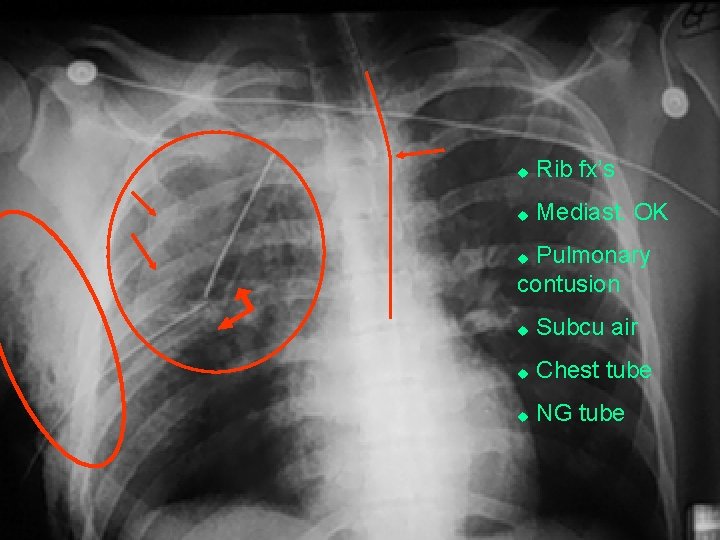
u Rib fx’s u Mediast. OK Pulmonary contusion u u Subcu air u Chest tube u NG tube
MVC victim
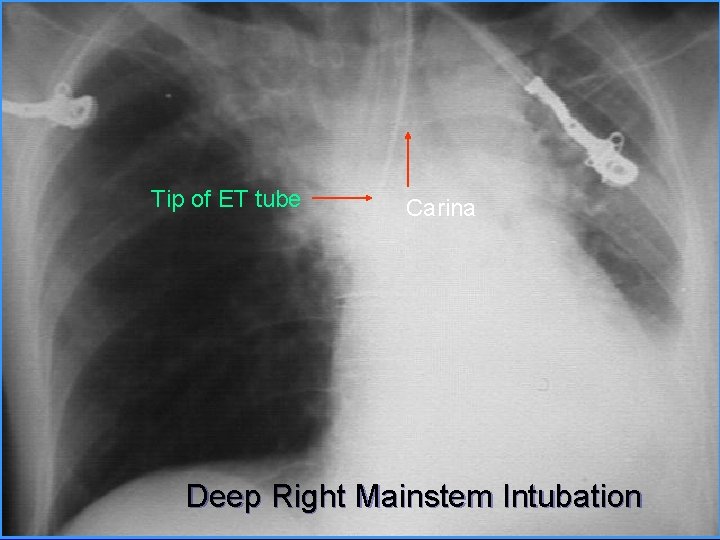
Tip of ET tube Carina Deep Right Mainstem Intubation
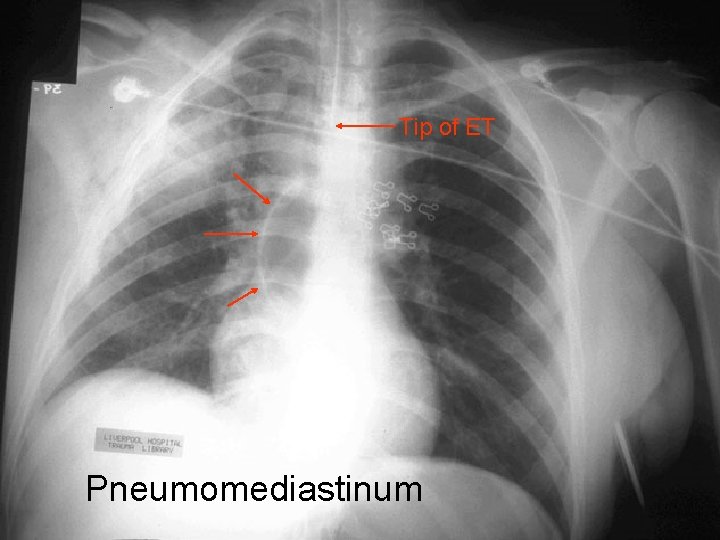
Tip of ET Pneumomediastinum
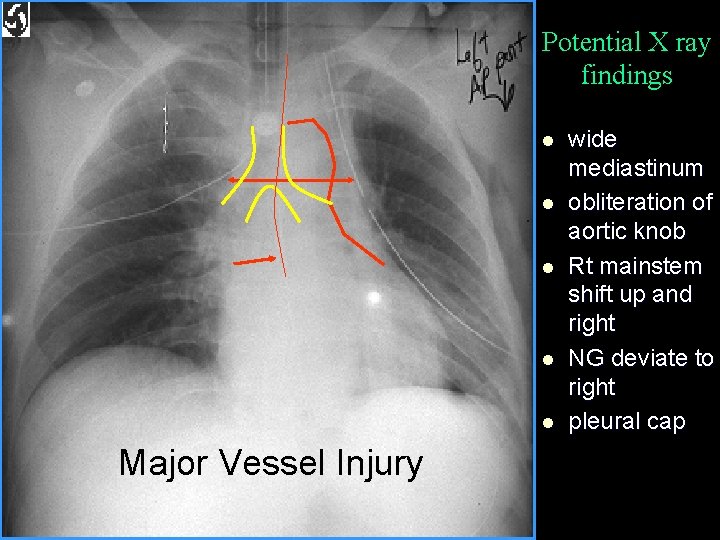
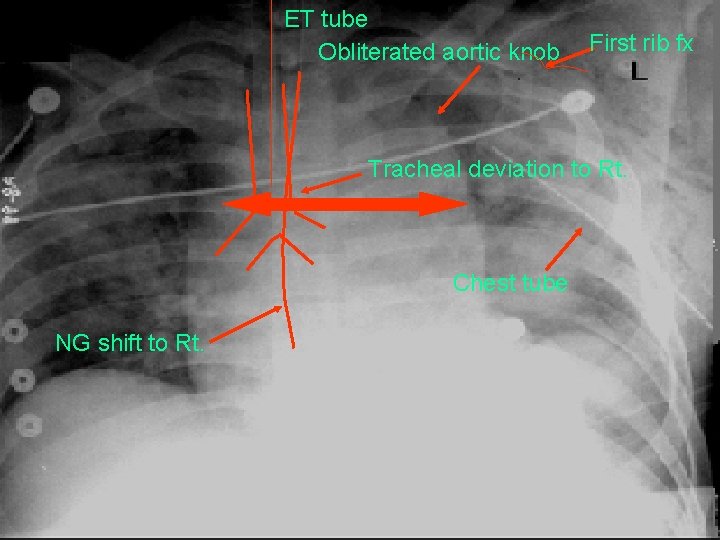
Potential X ray findings l l l Major Vessel Injury wide mediastinum obliteration of aortic knob Rt mainstem shift up and right NG deviate to right pleural cap
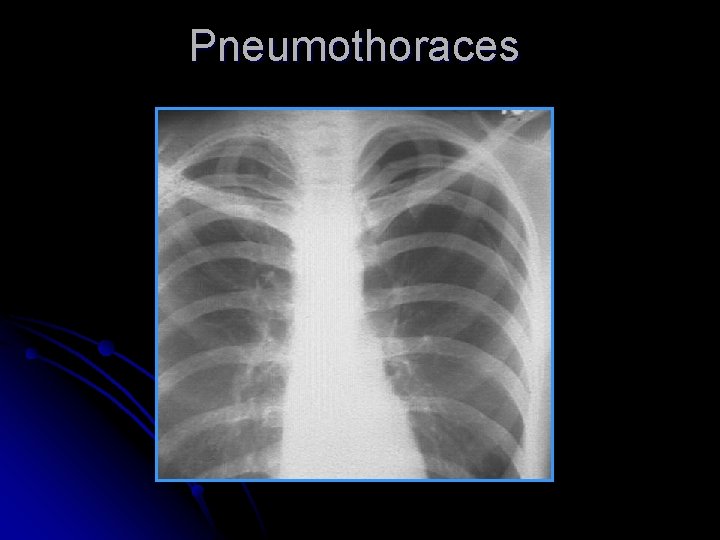
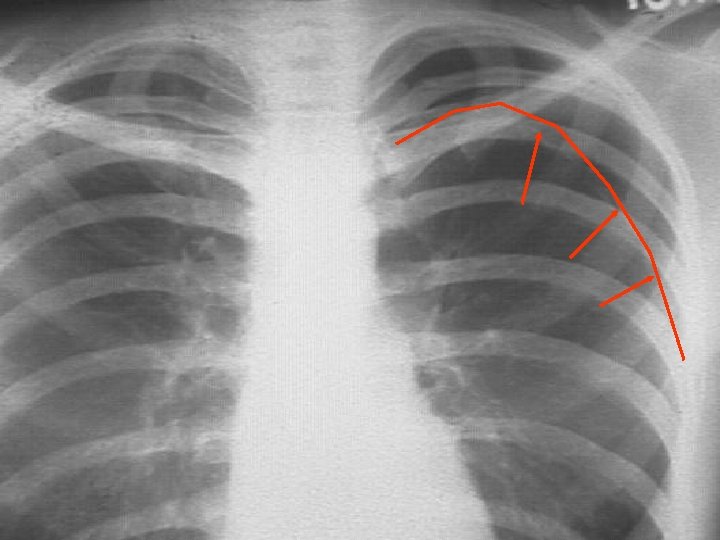
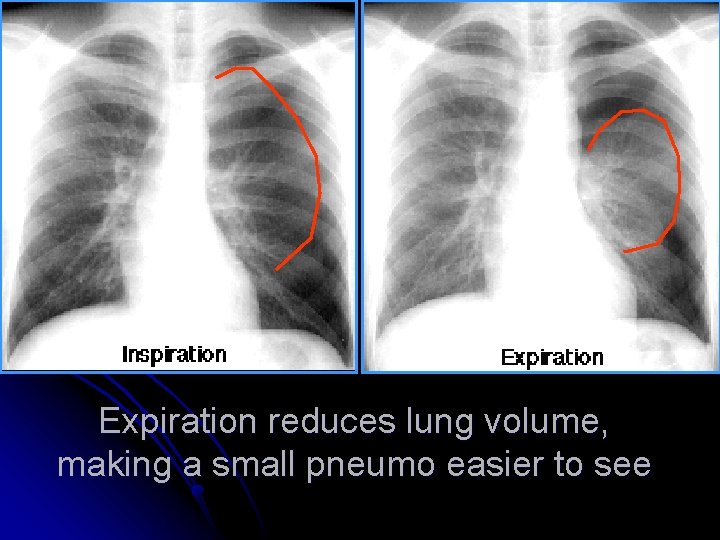
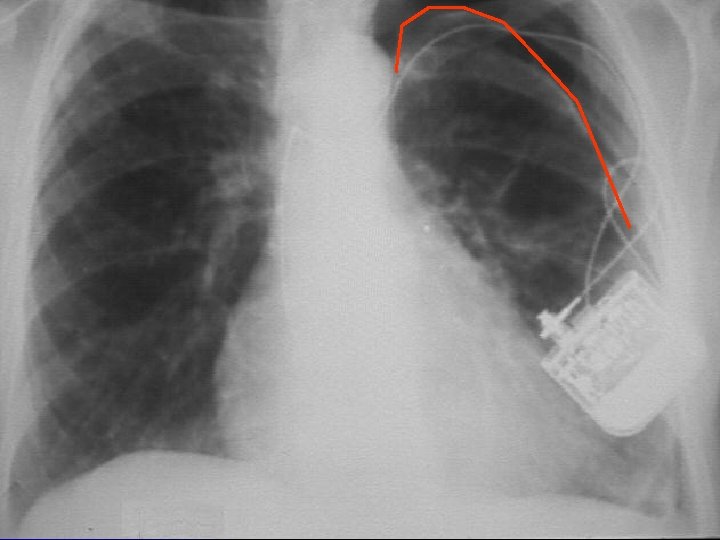
Pneumothoraces
Expiration reduces lung volume, making a small pneumo easier to see
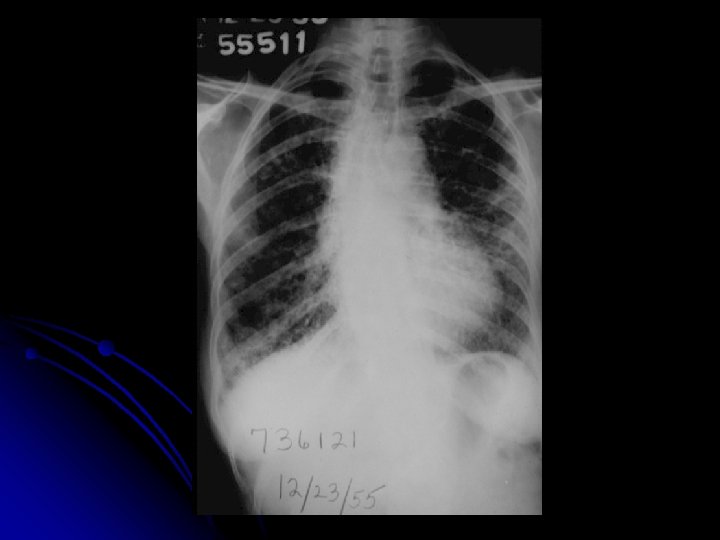
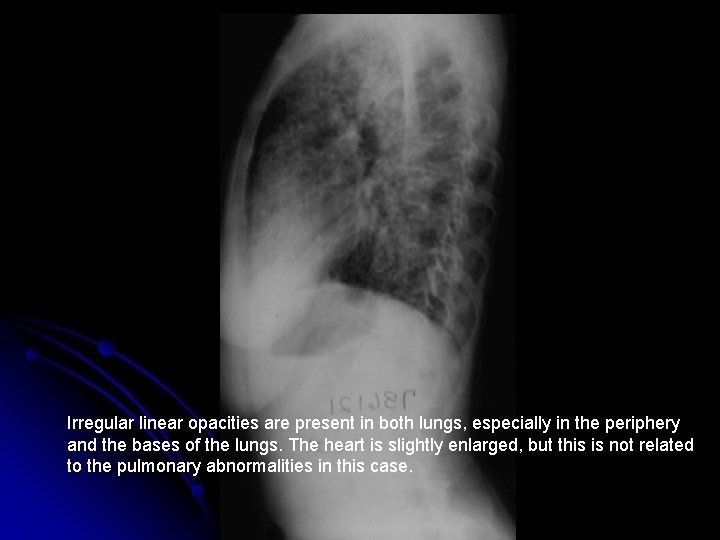
Irregular linear opacities are present in both lungs, especially in the periphery and the bases of the lungs. The heart is slightly enlarged, but this is not related to the pulmonary abnormalities in this case.
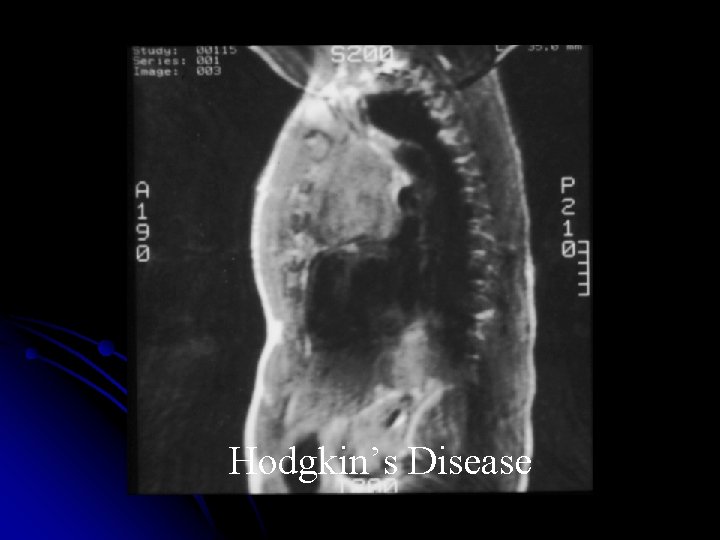
Hodgkin’s Disease
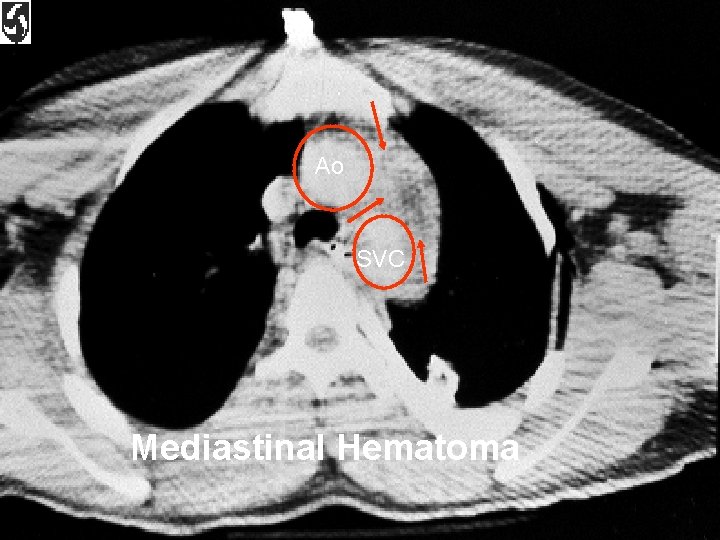
Ao SVC Mediastinal Hematoma
ET tube Obliterated aortic knob First rib fx Tracheal deviation to Rt. Chest tube NG shift to Rt.
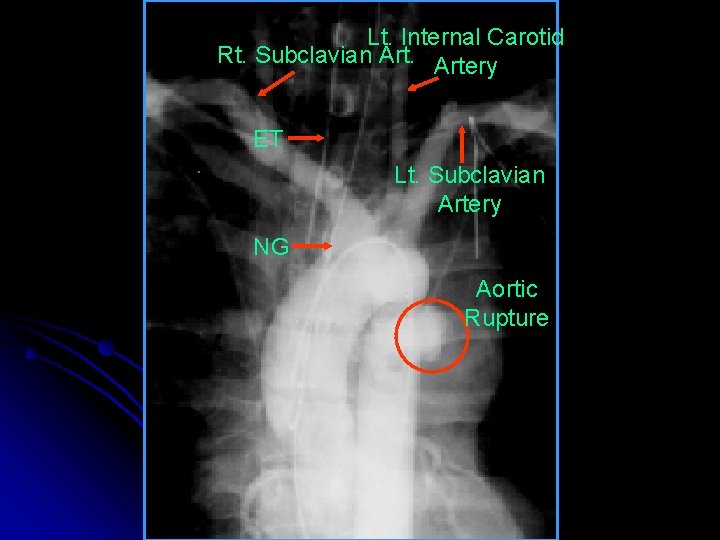
Lt. Internal Carotid Rt. Subclavian Artery ET Lt. Subclavian Artery NG Aortic Rupture
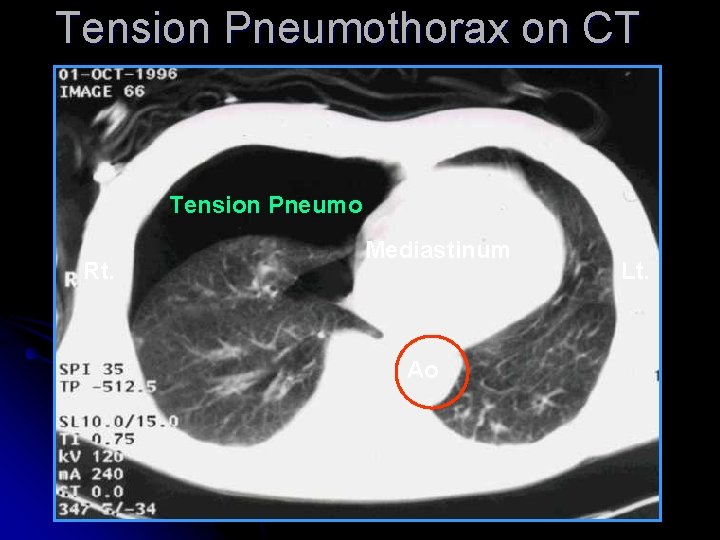
Tension Pneumothorax on CT Tension Pneumo Rt. Mediastinum Ao Lt.
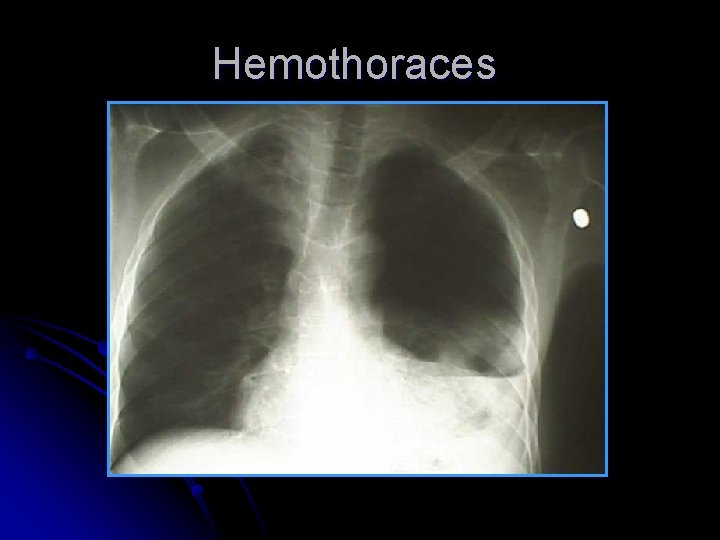
Hemothoraces
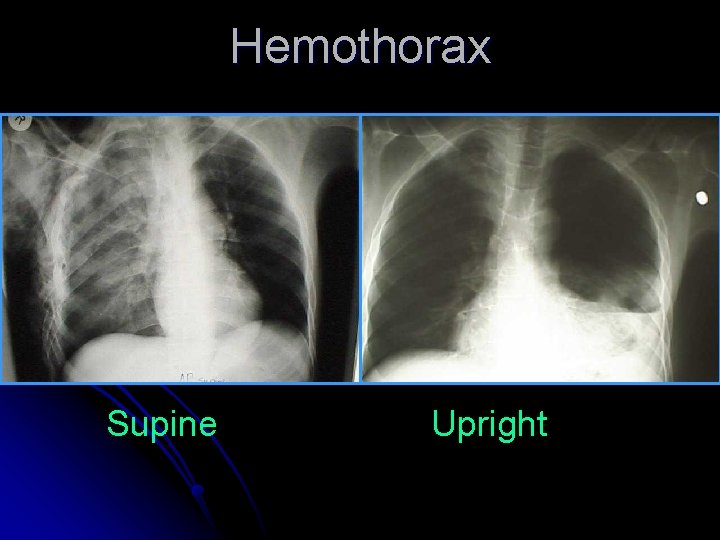
Hemothorax Supine Upright
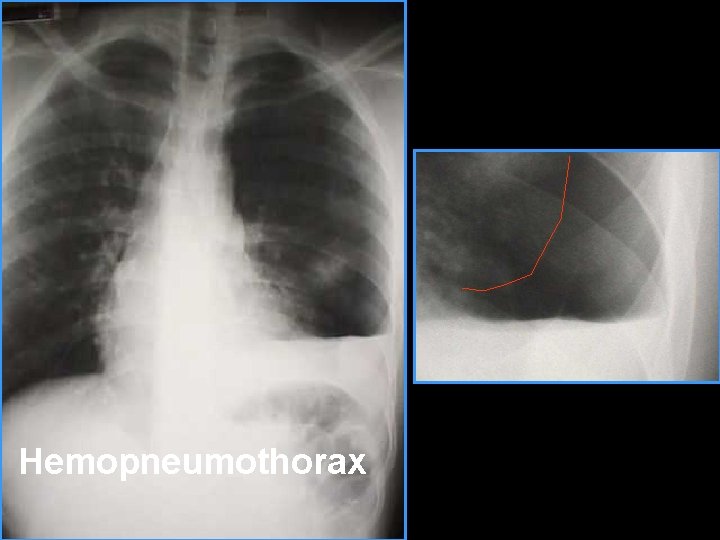
Hemopneumothorax
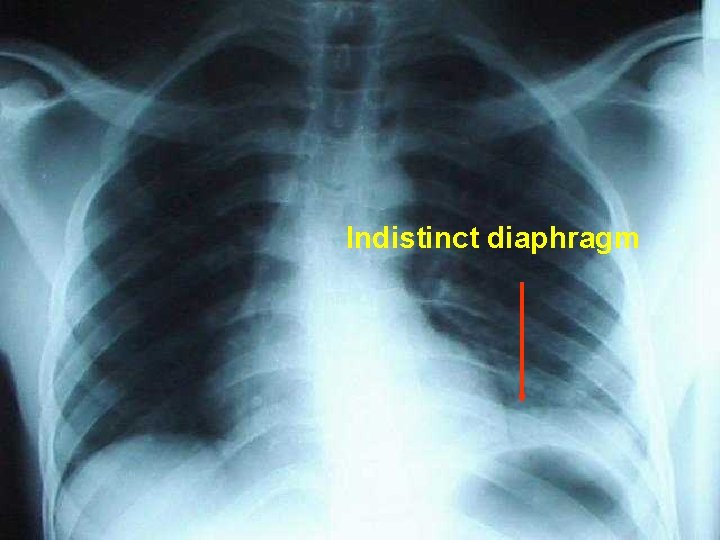
Indistinct diaphragm
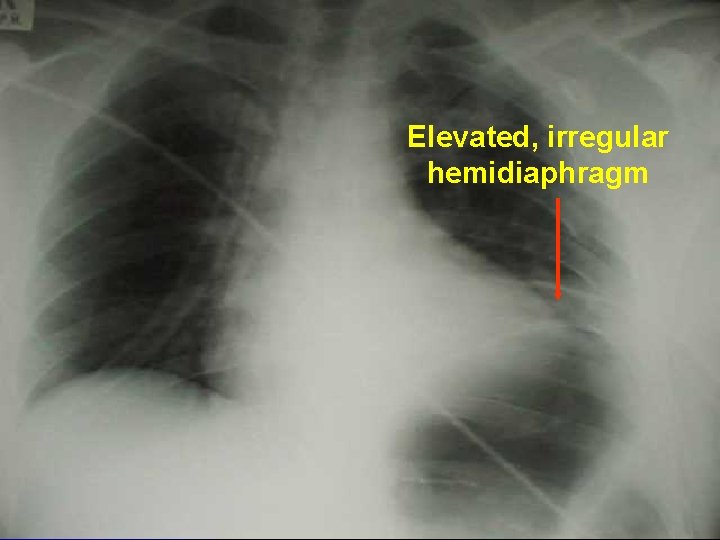
Elevated, irregular hemidiaphragm
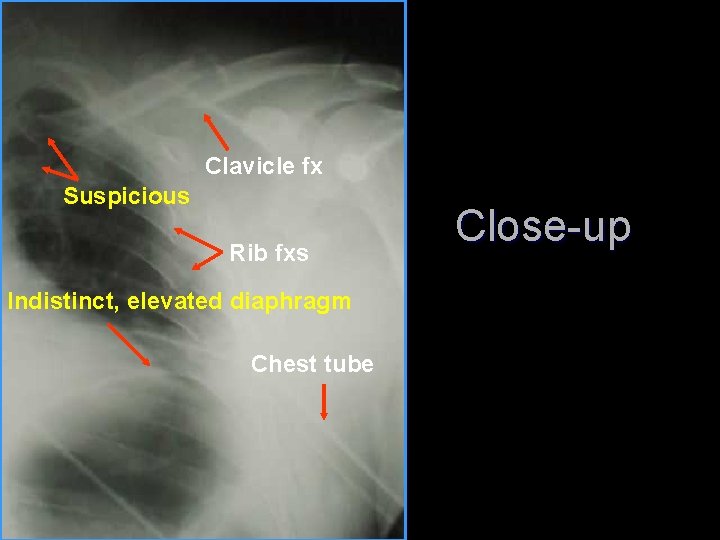
Clavicle fx Suspicious Rib fxs Indistinct, elevated diaphragm Chest tube Close-up
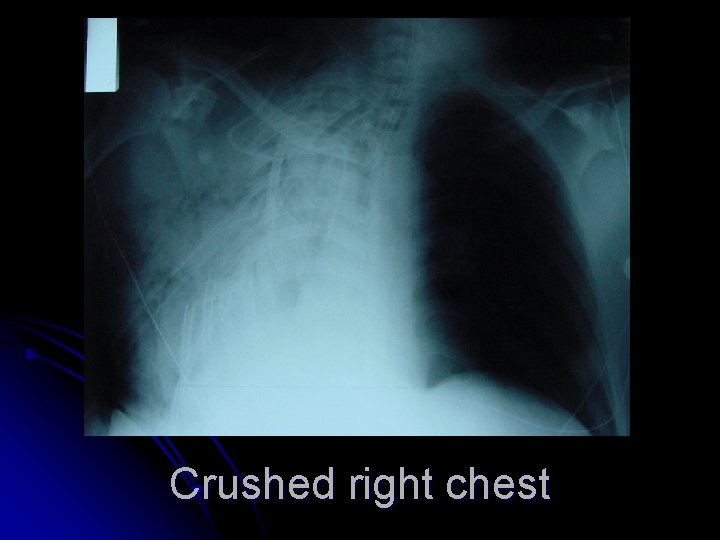
Crushed right chest
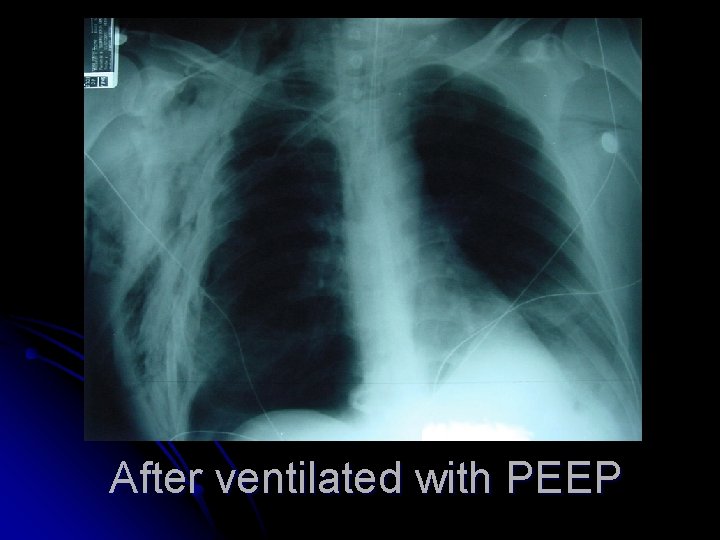
After ventilated with PEEP