Sleep Apnea the Eye Rick Trevino OD VA
























- Slides: 55
Sleep Apnea & the Eye Rick Trevino, OD VA Outpatient Clinic Evansville, IN rtrevino@gmail. com
Sleep Apnea & the Eye n Sleep Apnea n n n Sleep physiology Clinical consequences Diagnosis Treatment Ocular Manifestations n n n Asthenopia CPAP-assoc red eye Floppy eyelid syndrome NAION Papilledema Normal tension glaucoma
Online Resources n Lecture Notes n n Powerpoint Slides n n http: //richardtrevino. net/sleepapnea http: //www. slideshare. net/rhodopsin Free Texts n n http: //jfponline. com (Aug 2008) http: //pubs. nrc-cnrc. gc. ca/cjo Can J Ophthalmol 2007; 42(2): 23843
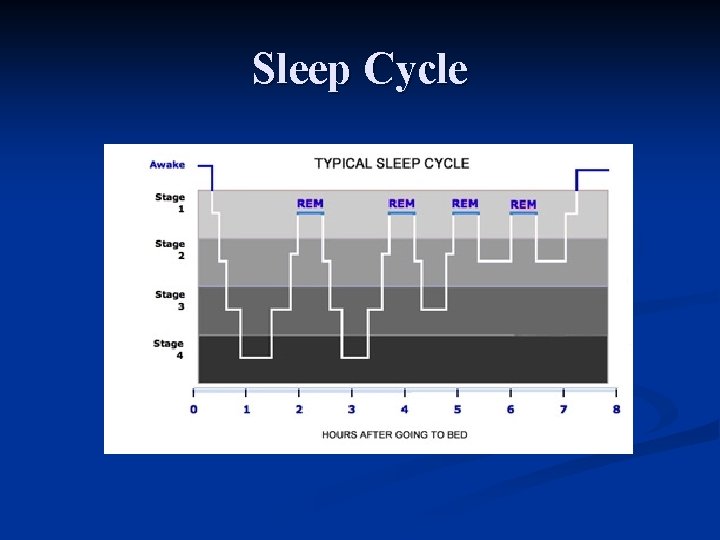
Sleep Cycle
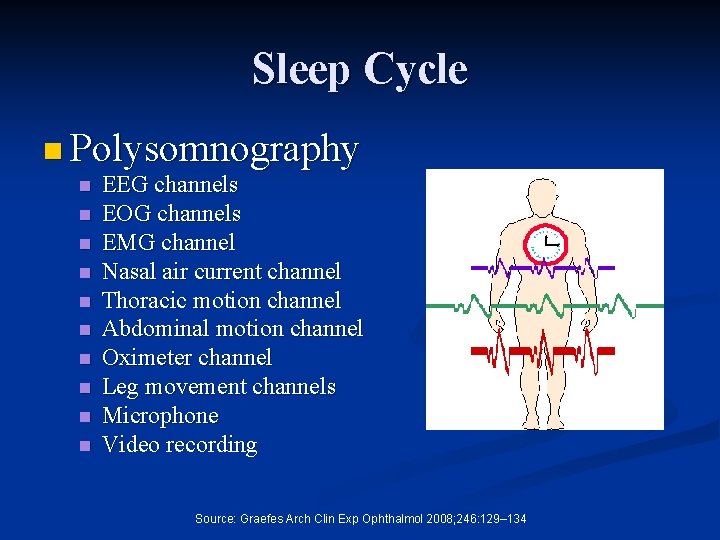
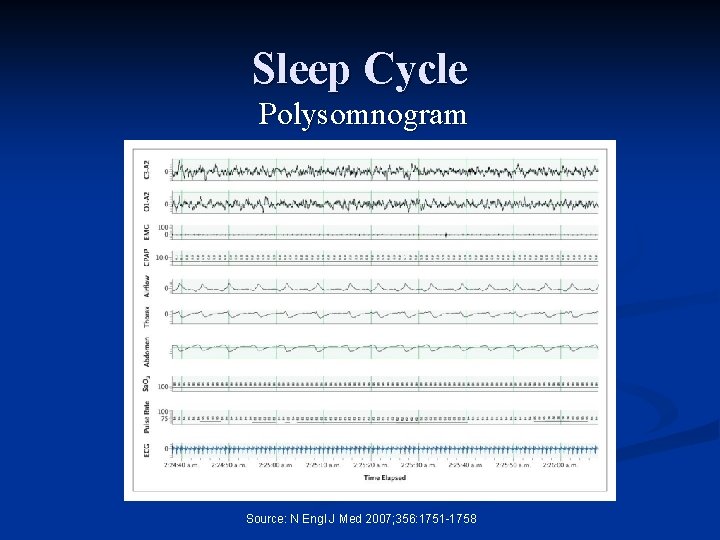
Sleep Cycle n Polysomnography n n n n n EEG channels EOG channels EMG channel Nasal air current channel Thoracic motion channel Abdominal motion channel Oximeter channel Leg movement channels Microphone Video recording Source: Graefes Arch Clin Exp Ophthalmol 2008; 246: 129– 134
Sleep Cycle Polysomnogram Source: N Engl J Med 2007; 356: 1751 -1758
Sleep Disorders OSA is the “most physiologically disruptive and dangerous of the sleep-related disorders. ” n n n n Sleep apnea Insomnia Narcolepsy Restless leg syndrome Parasomnias Circadian disorders Drug side effects Shift work Source: J Am Board Fam Med. 2007; 20: 392 -398
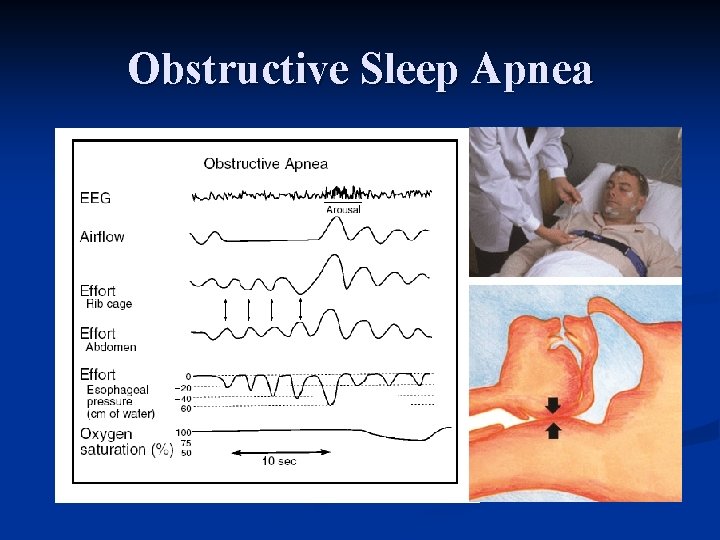
Obstructive Sleep Apnea
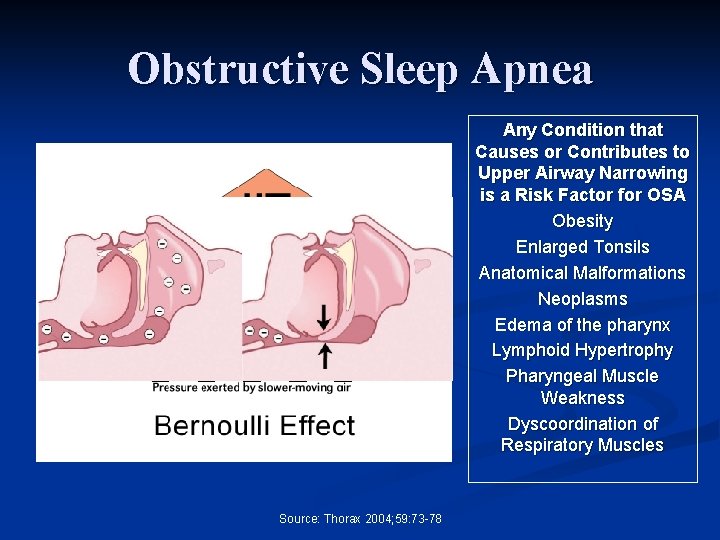
Obstructive Sleep Apnea Any Condition that Causes or Contributes to Upper Airway Narrowing is a Risk Factor for OSA Obesity Enlarged Tonsils Anatomical Malformations Neoplasms Edema of the pharynx Lymphoid Hypertrophy Pharyngeal Muscle Weakness Dyscoordination of Respiratory Muscles Source: Thorax 2004; 59: 73 -78
Obstructive Sleep Apnea Clinical Characteristics n Excessive daytime sleepiness n n Obesity n Most common symptom Disruptive snoring n n Apneic events witnessed by bed partner n n Disruptive snoring + witnessed apneas: 94% specificity n ≥ 40 cm had a sensitivity of 61% and a specificity of 93% for OSA Correlates better than BMI Male n n 30% of pts with a BMI > 30 have OSA, and 50% of pts with a BMI > 40 have OSA. Neck circumference Also gasping/snorting during arousals n n n 2 -3 x more common than female Family history of OSA n Relatives have 2 -4 fold risk Source: e. Medicine (http: //www. emedicine. com/med/topic 163. htm)
Obstructive Sleep Apnea n Pickwickian Syndrome Obesity, daytime somnolence, loud snoring n Charles Dicken’s “Pickwick Papers” (1837) n n Prevalence increasing in parallel with prevalence of obesity 30 -60 yo: 9%F, 24%M n Under-diagnosed n Source: Postgrad Med 2002; 111(3): 70 -6.
Obstructive Sleep Apnea Clinical Consequences n Cardiovascular Disease n n n HTN, CAD/MI, CHF, Arrhythmia Stroke Obesity Metabolic Syndrome Other Diseases n n Morning headache, Eye, Liver, Kidney, others Cognitive and Emotional n n Effects on bed partners n n Impaired mental functioning Depression Mood alteration Disruptive snoring Accidents Drowsy driving n Workplace Source: How Stuff Works (http: //healthguide. howstuffworks. com/sleep-apnea-in-depth. htm) n
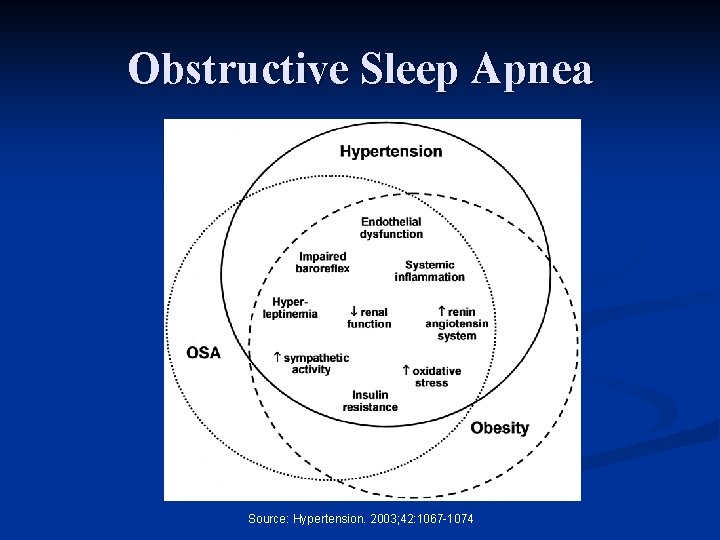
Obstructive Sleep Apnea Source: Hypertension. 2003; 42: 1067 -1074
Obstructive Sleep Apnea Clinical Evaluation n History n n Physical n n Sleepiness assessment Disruptive snoring Witnessed apneas Obesity Neck circumference Throat/Mouth exam PSG n n Gold Standard Respiratory Disturbance Index Source: J Fam Prac. 2008; 57(8) Suppl (http: //www. jfponline. com)
Obstructive Sleep Apnea Epworth Sleepiness Scale How likely are you to doze off or fall asleep in the following situations? 0 = No chance, 1 = Slight chance, 2 = Moderate chance, 3 = High Chance 1. Sitting and reading 2. Watching TV 3. Sitting inactive in a public place (theater, meeting) 4. As a passenger in a car for an hour without a break 5. Lying down to rest in the afternoon when circumstances permit 6. Sitting and talking to someone 7. Sitting quietly after a lunch without alcohol 8. In a car, while stopped for a few minutes in traffic Source: Sleep 1994; 17: 160– 167
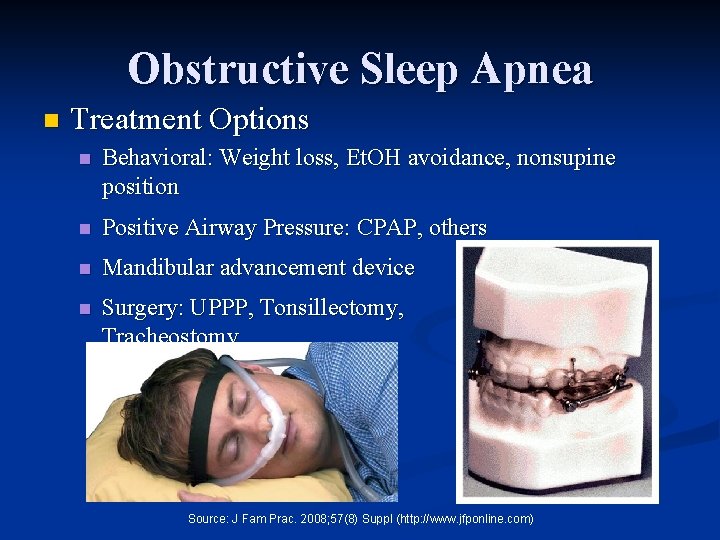
Obstructive Sleep Apnea n Treatment Options n Behavioral: Weight loss, Et. OH avoidance, nonsupine position n Positive Airway Pressure: CPAP, others n Mandibular advancement device n Surgery: UPPP, Tonsillectomy, Tracheostomy Source: J Fam Prac. 2008; 57(8) Suppl (http: //www. jfponline. com)
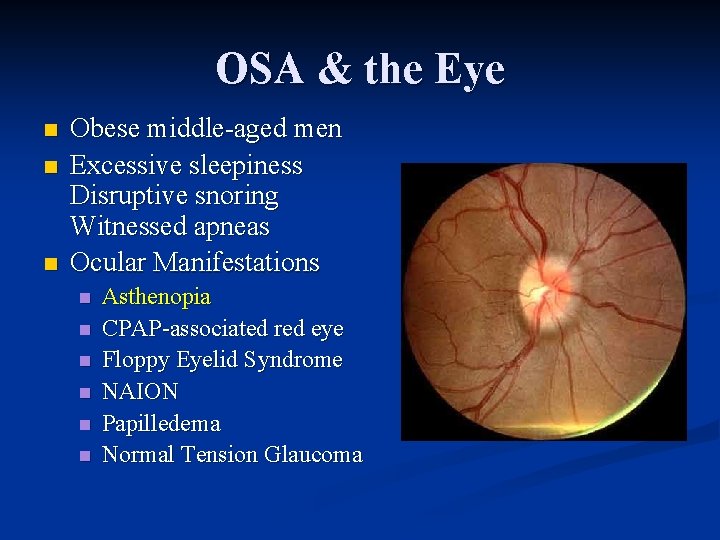
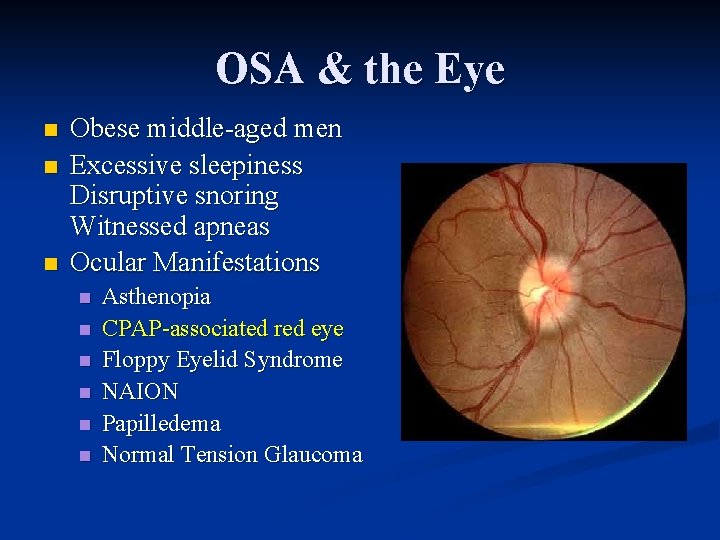
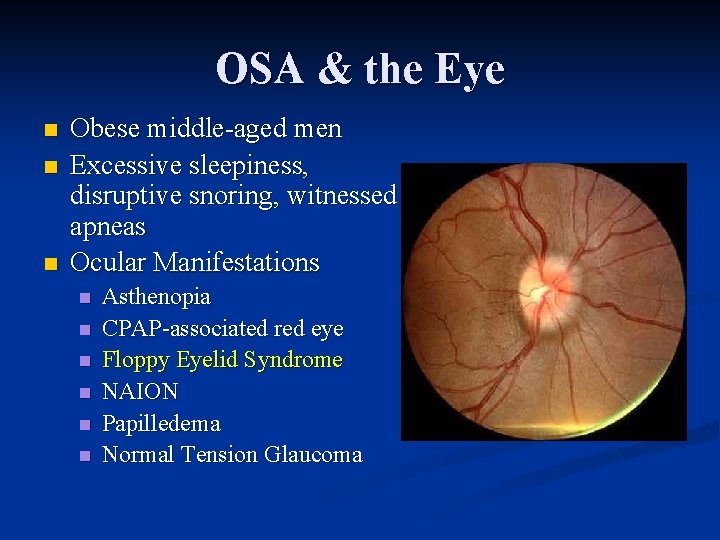
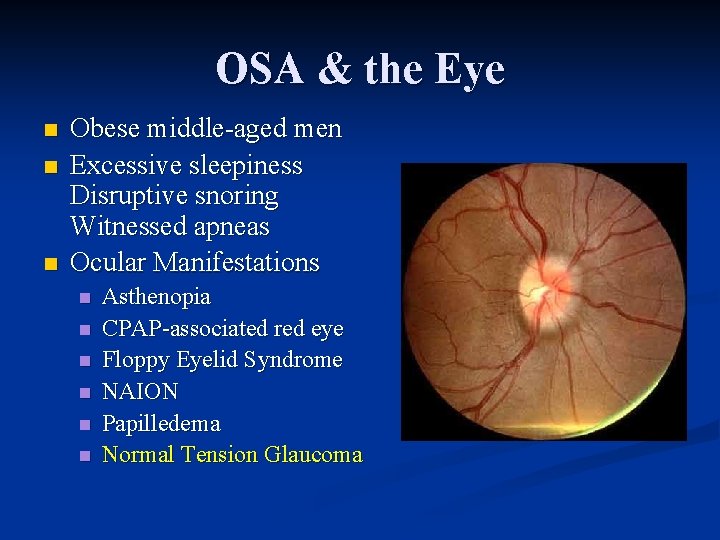
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness Disruptive snoring Witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
Asthenopia n Common OSA Symptoms Include: “Tiredness” n “Fatigue” n “Lack of energy” n Morning headache n n These OSA symptoms may be misinterpreted as “eye strain” Source: J Fam Prac. 2008; 57(8) Suppl (http: //www. jfponline. com)
Asthenopia Common OSA-associated asthenopic symptoms n Unexplained symptoms of blur n Vision is 20/20 but the patient is c/o blur n Misinterpreting what is seen n Incorrect recording or copying Eye strain and/or fatigue n Headaches n n Worse in the morning
Asthenopia 42 yo WM presents with c/o eye fatigue at near. LEE: <1 yr with current eyeglasses MH: 1. 2. 3. 4. 5. 6. OSA (noncompliant with CPAP) Frequent HA Overweight Hyperlipidemia GERD Smokes 1 PPD Optometric Exam: Unremarkable Plan: 1. 2. 3. OSA management Visual hygiene Smoking cessation
Asthenopia OSA Supportive Management n Encourage compliance with CPAP n n Quit smoking n n n 10% increase in weight results in 6 x greater risk of developing OSA Weight loss decreases OSA severity Avoid sleeping on back n n Smokers 3 times more likely to have OSA Reversible with smoking cessation Weight reduction n n 50% compliance rate, high drop-out rate Sew golf ball into pocket on back of shirt Avoid alcohol within 4 hours of bedtime Avoid sleeping pills Source: JAMA 2004; 291: 2013 -2016
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness Disruptive snoring Witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
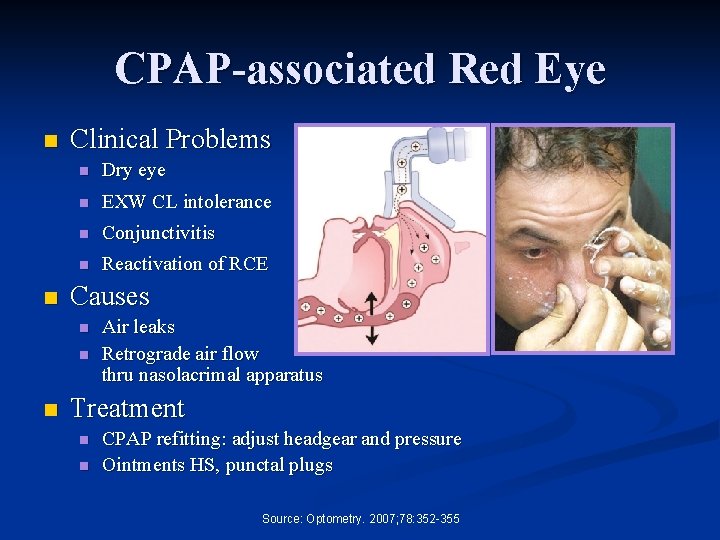
CPAP-associated Red Eye n n Clinical Problems n Dry eye n EXW CL intolerance n Conjunctivitis n Reactivation of RCE Causes n n n Air leaks Retrograde air flow thru nasolacrimal apparatus Treatment n n CPAP refitting: adjust headgear and pressure Ointments HS, punctal plugs Source: Optometry. 2007; 78: 352 -355
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness, disruptive snoring, witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
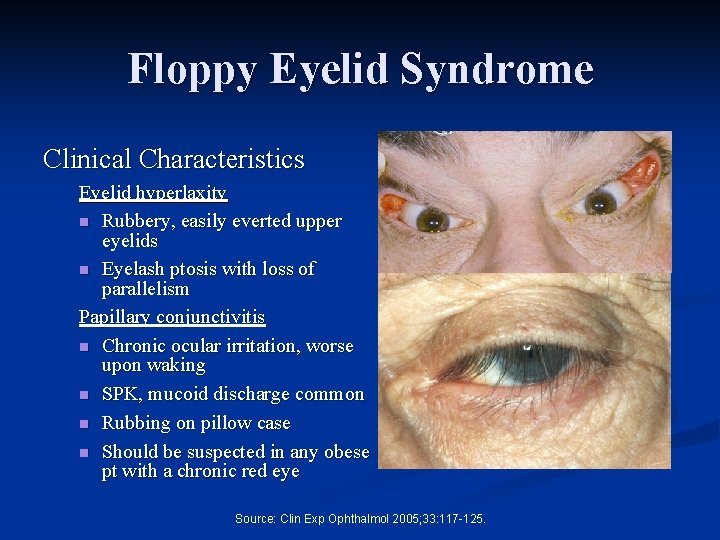
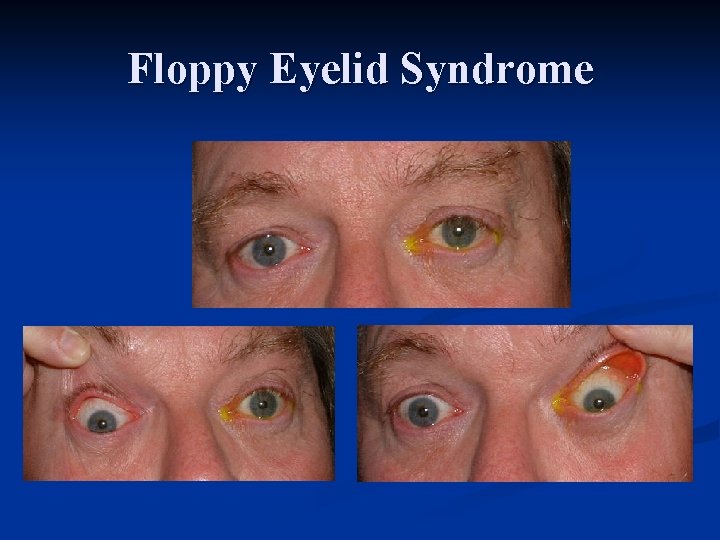
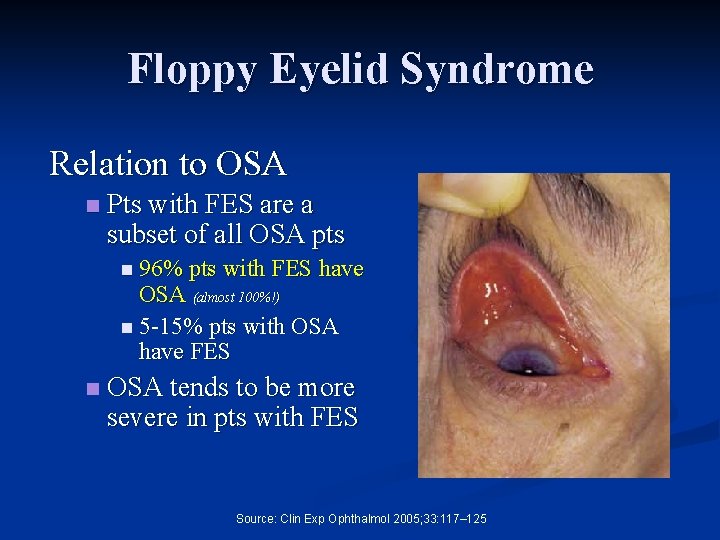
Floppy Eyelid Syndrome Clinical Characteristics Eyelid hyperlaxity n Rubbery, easily everted upper eyelids n Eyelash ptosis with loss of parallelism Papillary conjunctivitis n Chronic ocular irritation, worse upon waking n SPK, mucoid discharge common n Rubbing on pillow case n Should be suspected in any obese pt with a chronic red eye Source: Clin Exp Ophthalmol 2005; 33: 117 -125.
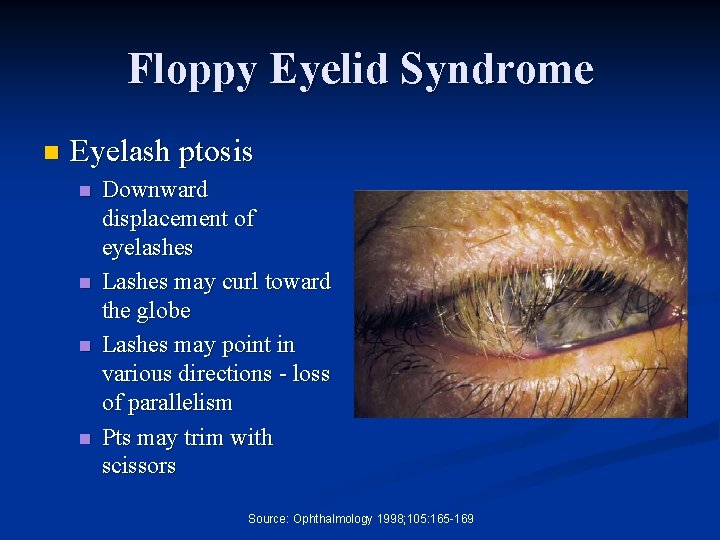
Floppy Eyelid Syndrome n Eyelash ptosis n n Downward displacement of eyelashes Lashes may curl toward the globe Lashes may point in various directions - loss of parallelism Pts may trim with scissors Source: Ophthalmology 1998; 105: 165 -169
Floppy Eyelid Syndrome
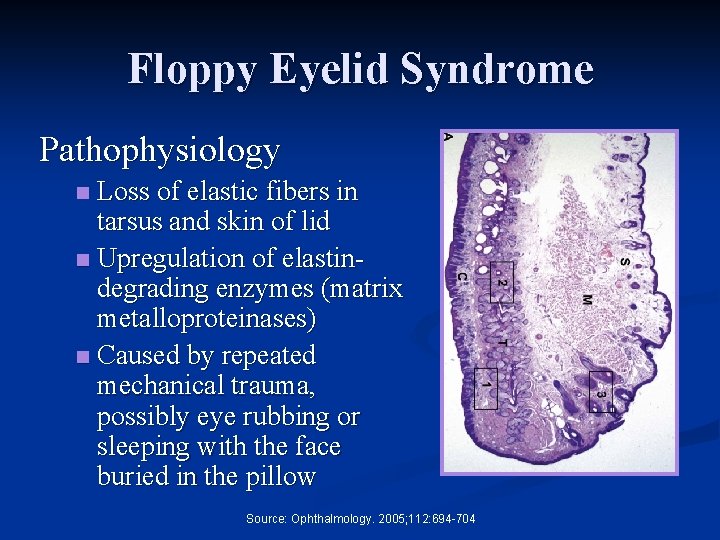
Floppy Eyelid Syndrome Pathophysiology Loss of elastic fibers in tarsus and skin of lid n Upregulation of elastindegrading enzymes (matrix metalloproteinases) n Caused by repeated mechanical trauma, possibly eye rubbing or sleeping with the face buried in the pillow n Source: Ophthalmology. 2005; 112: 694 -704
Floppy Eyelid Syndrome Treatment n Lubrication therapy n n n Protect eye during sleep n n Poor lid-eye contact Inadequate tear distribution Ointments HS Fox shield, patching, taping May improve or resolve with CPAP Surgical therapy deferred until OSA treated n Horizontal lid shortening Source: Curr Opin Ophthalmol. 2007; 18: 430 -433
Floppy Eyelid Syndrome Relation to OSA n Pts with FES are a subset of all OSA pts n 96% pts with FES have OSA (almost 100%!) n 5 -15% pts with OSA have FES n OSA tends to be more severe in pts with FES Source: Clin Exp Ophthalmol 2005; 33: 117– 125
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness Disruptive snoring Witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
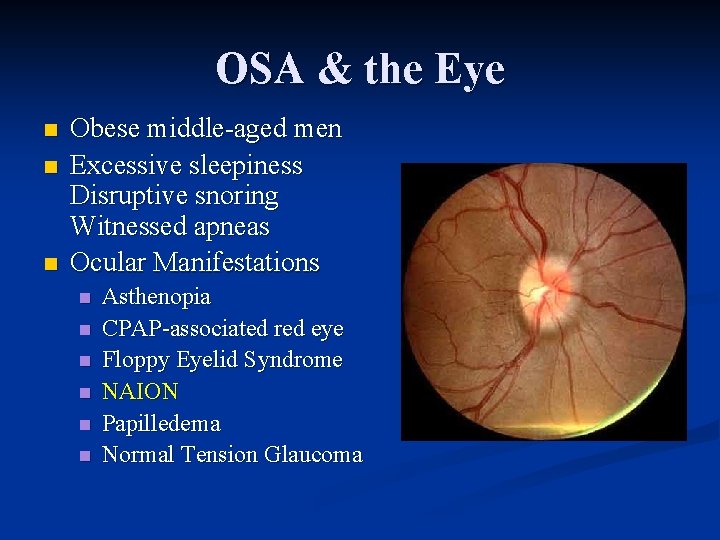
NAION Clinical Characteristics n Most common acute optic neuropathy in pts >50 yo n Sudden painless visual loss, usually upon awaking n Nerve fiber bundle VF defects n Diffuse or sectoral disc edema n Disc at risk: small, crowded n n Mean C/D = 0. 2 All ≤ 0. 4 Source: Rev Ophthalmol (http: //www. revophth. com/index. asp? page=1_13156. htm)
NAION Pathophysiology n Idiopathic ischemic process n Disorder of posterior ciliary artery circulation n Transient poor circulation in the ONH n Trigger Event: Fall in blood pressure below a critical level? n There is no actual blockage of the posterior ciliary arteries n Cascade Effect n Mechanical crowding caused by small crowded disc n Ischemia Swelling Compression Ischemia Source: http: //webeye. ophth. uiowa. edu/dept/AION/Index. htm
NAION Diagnosis: Must exclude GCA in every case ESR n C-Reactive Protein n n Positive acute-phase protein n Levels increase in presence of inflammation n Upper limit normal does not rise with age n Platelets n Secondary thrombocytosis due to chronic inflammation
NAION Treatment n Aspirin n n Surgical decompression n n No benefit (Ischemic Optic Neuropathy Decompression Trial) Control of predisposing systemic disease n n n Decreases incidence in fellow eye at 2 years, but not at 5 years May slow progression or reduce incidence in fellow eye Hypertension, Diabetes, Hyperlipidemia Avoid phosphodiesterase 5 inhibitors (Viagra, Levitra, Cialis) n May increase risk of NAION in fellow eye
NAION Medicolegal obligation to inform pts of risk to fellow eye
NAION Relation to OSA n Mojon (2002) n Behbehani (2005) n Palombi (2006) n Li (2007)
NAION Mojon (2002) n Matched case-control study with 17 NAION cases and 17 controls n 71% of patients with NAION have OSA compared with 18% of controls n Can CPAP prevent NAION in predisposed individuals with OSA? Source: Arch Ophthalmol 2002; 120: 601 -605
NAION Behbehani (2005) n Report of 3 patients that developed NAION while using CPAP for OSA n Concluded that CPAP does not prevent NAION in patients with OSA n Questions role of OSA in development of NAION Source: Am J Ophthalmol 2005; 139: 518– 521
NAION Palombi (2006) n 24 of 27 (89%) NAION patients had OSA n OSA was the most frequent disorder associated with NAION n n n HTN: 59% DM: 37% Recommend all NAION pts be screened for OSA n Daytime sleepiness, noisy sleep, witnessed apneas n Pickwickian habitus (obese middle-aged men) Source: Br J Ophthalmol 2006; 90: 879– 882
NAION Li (2007) n Matched case-control study of 73 NAION cases and 73 controls n Administered questionnaire that included the SA-SDQ n 22 (30. 1%) cases and 13 (17. 8%) controls had scores consistent with OSA n Conclude that patients with OSA are at increased risk of NAION Source: Br. J. Ophthalmol. 2007; 91: 1524 -1527
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness Disruptive snoring Witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
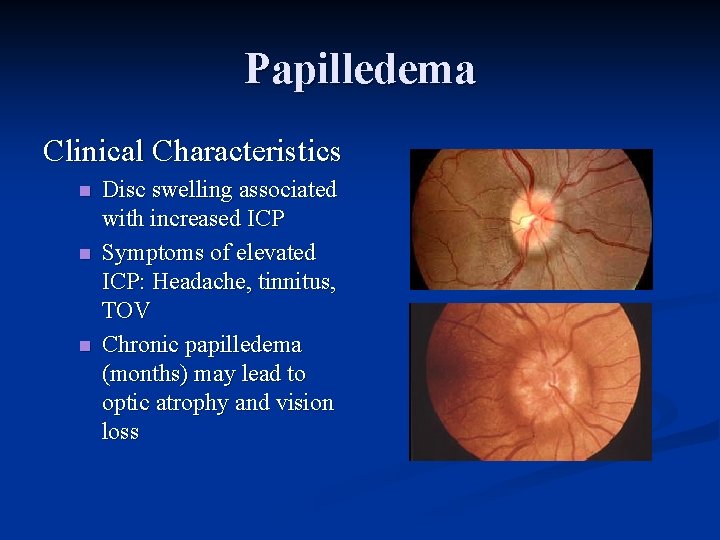
Papilledema Clinical Characteristics n n n Disc swelling associated with increased ICP Symptoms of elevated ICP: Headache, tinnitus, TOV Chronic papilledema (months) may lead to optic atrophy and vision loss
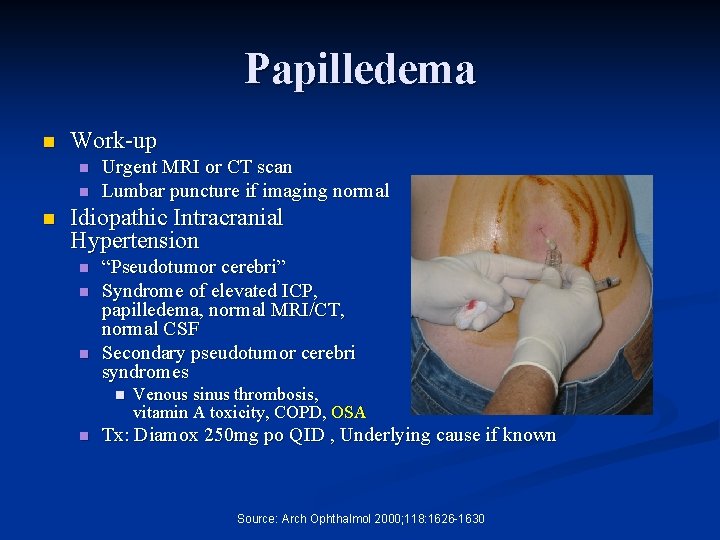
Papilledema n Work-up n n n Urgent MRI or CT scan Lumbar puncture if imaging normal Idiopathic Intracranial Hypertension n “Pseudotumor cerebri” Syndrome of elevated ICP, papilledema, normal MRI/CT, normal CSF Secondary pseudotumor cerebri syndromes n n Venous sinus thrombosis, vitamin A toxicity, COPD, OSA Tx: Diamox 250 mg po QID , Underlying cause if known Source: Arch Ophthalmol 2000; 118: 1626 -1630
Papilledema Relation to OSA n n 4 pts with vision loss, unexplained disc edema and OSA ICP is normal during the day but elevated at night n n Hypercapnia-induced cerebral vasodilatation elevates ICP n n Apneas were occurring despite CPAP – require surgical tx Intermittent ↑ ICP can cause sustained papilledema Papilledema resolved with successful tx of OSA Source: Arch Ophthalmol 2000; 118: 1626 -1630
OSA & the Eye n n n Obese middle-aged men Excessive sleepiness Disruptive snoring Witnessed apneas Ocular Manifestations n n n Asthenopia CPAP-associated red eye Floppy Eyelid Syndrome NAION Papilledema Normal Tension Glaucoma
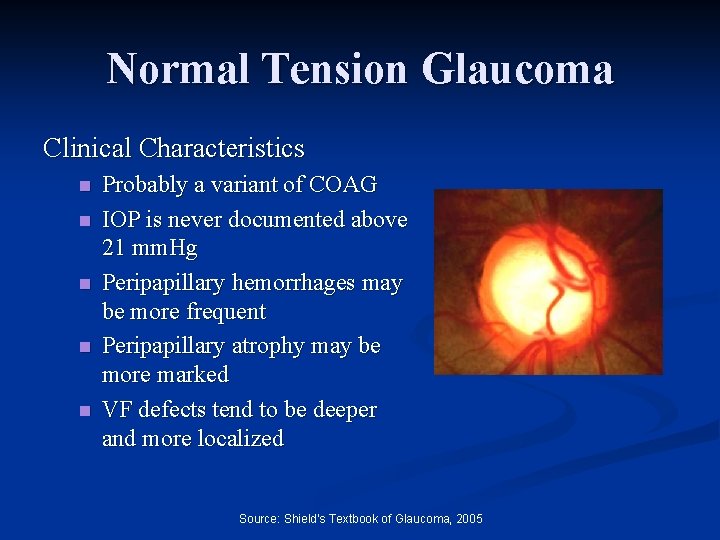
Normal Tension Glaucoma Clinical Characteristics n n n Probably a variant of COAG IOP is never documented above 21 mm. Hg Peripapillary hemorrhages may be more frequent Peripapillary atrophy may be more marked VF defects tend to be deeper and more localized Source: Shield's Textbook of Glaucoma, 2005
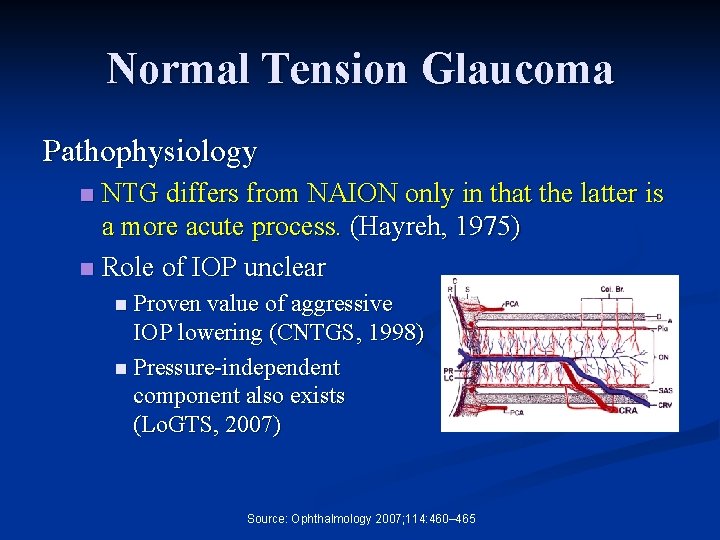
Normal Tension Glaucoma Pathophysiology NTG differs from NAION only in that the latter is a more acute process. (Hayreh, 1975) n Role of IOP unclear n n Proven value of aggressive IOP lowering (CNTGS, 1998) n Pressure-independent component also exists (Lo. GTS, 2007) Source: Ophthalmology 2007; 114: 460– 465
Normal Tension Glaucoma Diagnosis n R/O other glaucomas n n n Diurnal IOP fluctuation IOP normalization (Burnt-out glaucoma, pseudophakia, steroids) R/O other optic neuropathies n n NAION, space-occupying lesions, congenital anomalies When to order neuroimaging: n n Younger age (<50 yrs) Reduced VA (< 20/40) Vertically aligned VF defects Neuroretinal rim pallor Source: Ophthalmology 1998; 105: 1866 -1874
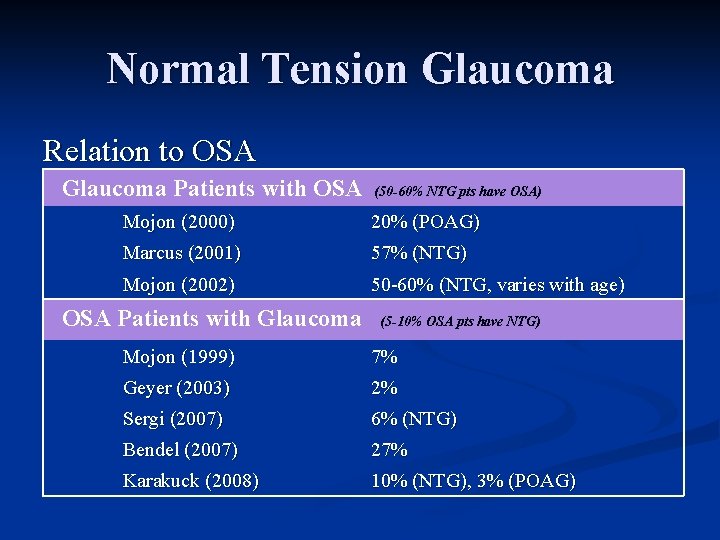
Normal Tension Glaucoma Relation to OSA Glaucoma Patients with OSA (50 -60% NTG pts have OSA) Mojon (2000) 20% (POAG) Marcus (2001) 57% (NTG) Mojon (2002) 50 -60% (NTG, varies with age) OSA Patients with Glaucoma (5 -10% OSA pts have NTG) Mojon (1999) 7% Geyer (2003) 2% Sergi (2007) 6% (NTG) Bendel (2007) 27% Karakuck (2008) 10% (NTG), 3% (POAG)
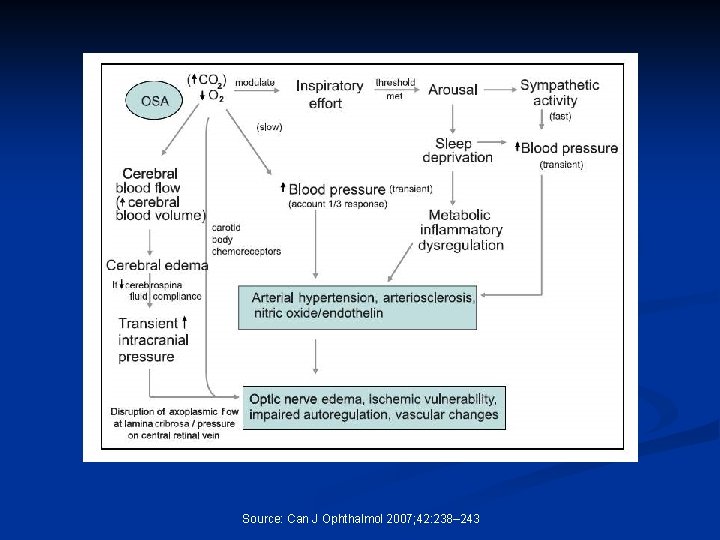
Normal Tension Glaucoma OSA May Cause VF Loss Without Glaucoma n n VF loss may occur due to optic nerve damage caused by cerebral ischemia and intermittent ICP elevation Batisse (2004) n n n Tsang (2006) n n n Eye exam on 35 consecutive patients undergoing PSG VF mean deviation correlated with RDI Compared VF and ONH changes between 41 pts with moderate-severe OSA with 35 age-matched controls In OSA pts the VF indices were significantly subnormal Karakucuk (2008) n n Eye exams and orbital blood flow studies on 31 pts with OSA and 25 normal control subjects VF defects were detected in 10 pts despite normal eye exam.
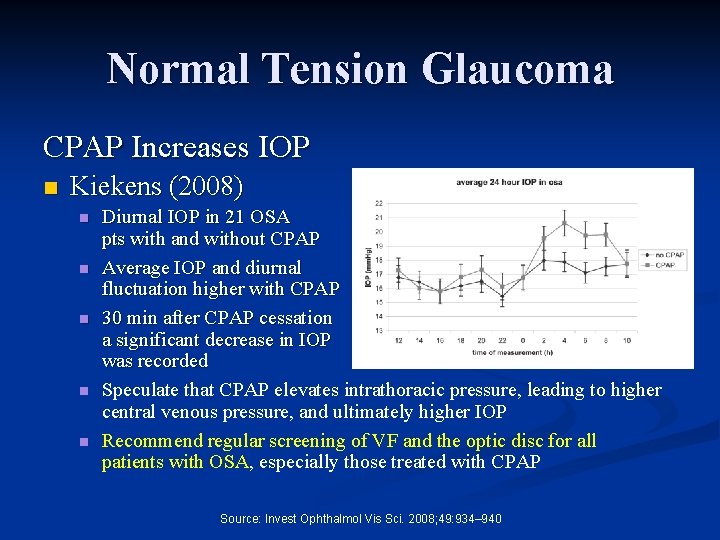
Normal Tension Glaucoma CPAP Increases IOP n Kiekens (2008) n n n Diurnal IOP in 21 OSA pts with and without CPAP Average IOP and diurnal fluctuation higher with CPAP 30 min after CPAP cessation a significant decrease in IOP was recorded Speculate that CPAP elevates intrathoracic pressure, leading to higher central venous pressure, and ultimately higher IOP Recommend regular screening of VF and the optic disc for all patients with OSA, especially those treated with CPAP Source: Invest Ophthalmol Vis Sci. 2008; 49: 934– 940
Source: Can J Ophthalmol 2007; 42: 238– 243
Thank You!