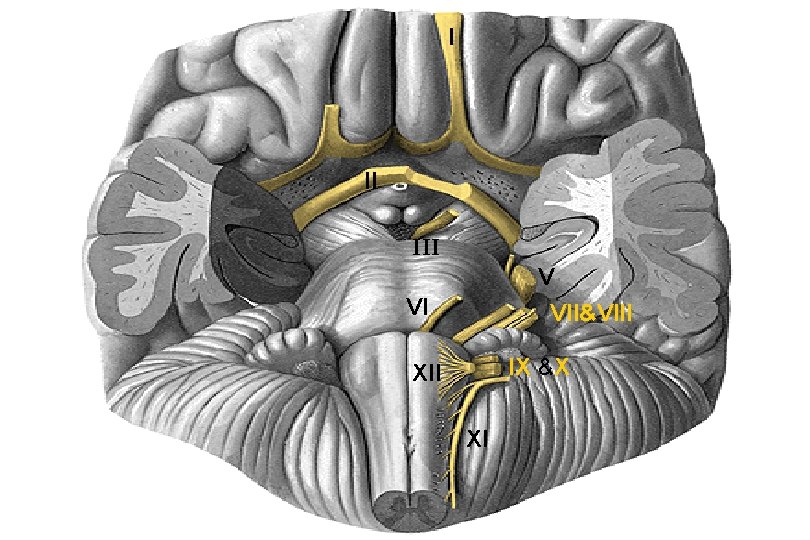
I II III V VIIVIII VI IX X
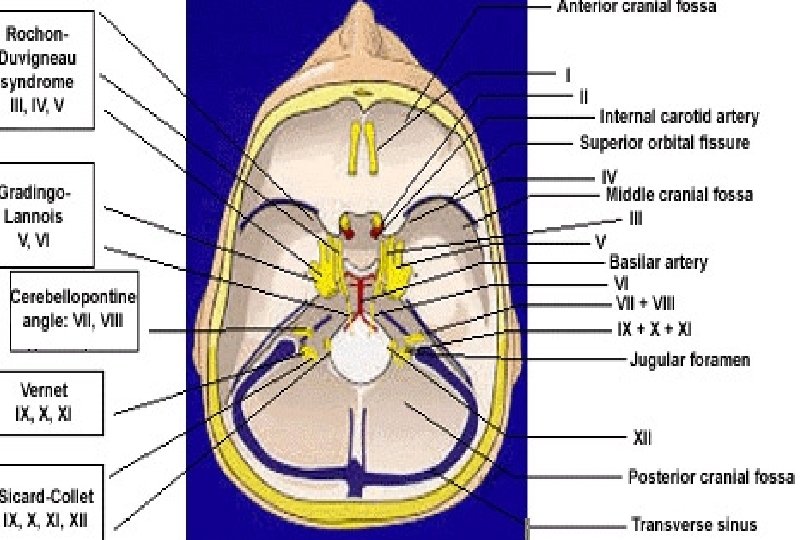












- Slides: 82
I II III V VII&VIII VI IX &X XII XI
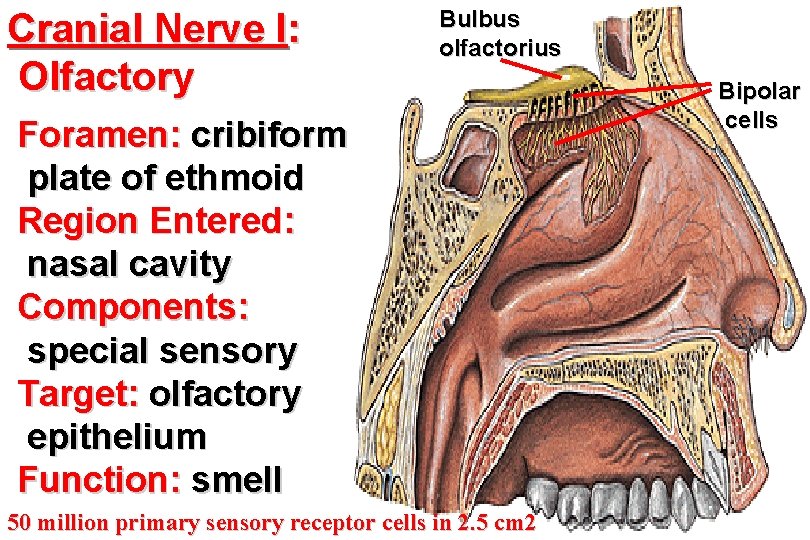
Cranial Nerve I: Olfactory Bulbus olfactorius Foramen: cribiform plate of ethmoid Region Entered: nasal cavity Components: special sensory Target: olfactory epithelium Function: smell 50 million primary sensory receptor cells in 2. 5 cm 2 Bipolar cells
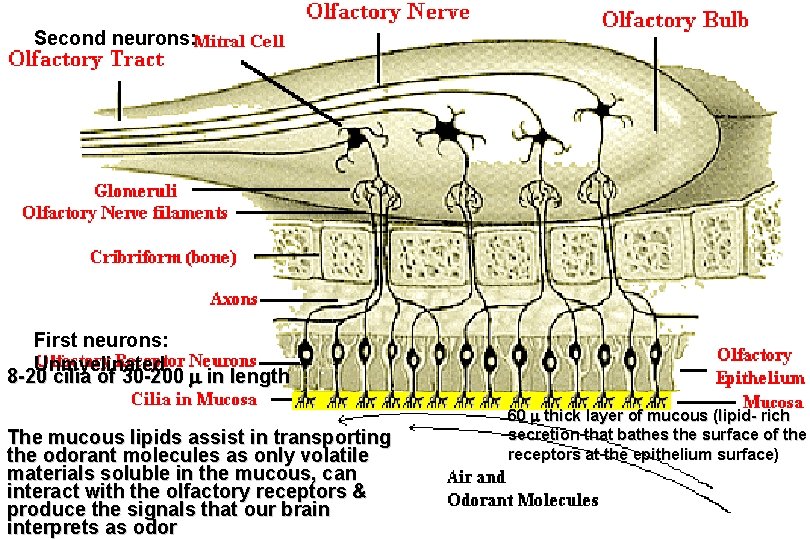
Second neurons: First neurons: Unmyelinated 8 -20 cilia of 30 -200 in length The mucous lipids assist in transporting the odorant molecules as only volatile materials soluble in the mucous, can interact with the olfactory receptors & produce the signals that our brain interprets as odor 60 thick layer of mucous (lipid- rich secretion that bathes the surface of the receptors at the epithelium surface)
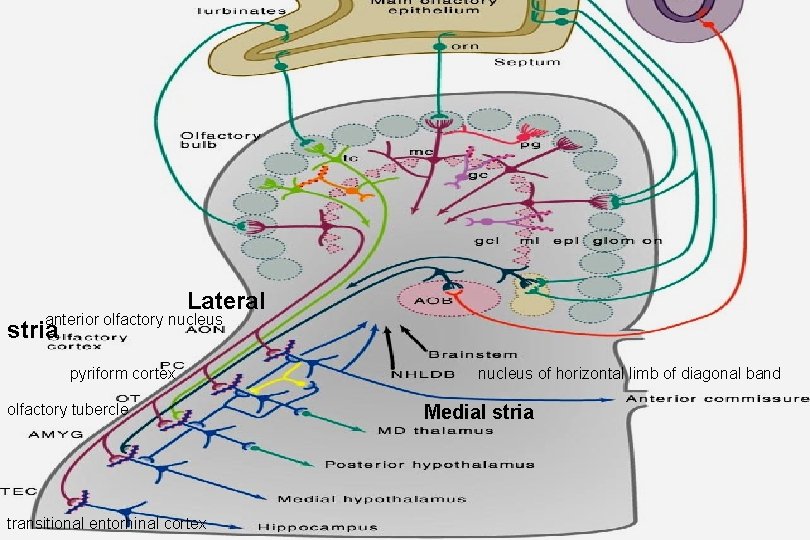
Lateral anterior olfactory nucleus stria pyriform cortex olfactory tubercle transitional entorhinal cortex nucleus of horizontal limb of diagonal band Medial stria
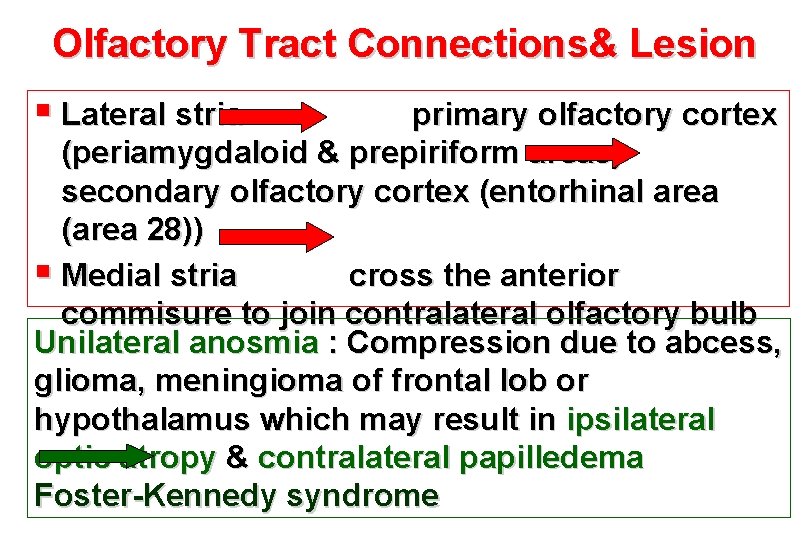
Olfactory Tract Connections& Lesion § Lateral stria primary olfactory cortex (periamygdaloid & prepiriform areas) secondary olfactory cortex (entorhinal area (area 28)) § Medial stria cross the anterior commisure to join contralateral olfactory bulb Unilateral anosmia : Compression due to abcess, glioma, meningioma of frontal lob or hypothalamus which may result in ipsilateral optic atropy & contralateral papilledema Foster-Kennedy syndrome
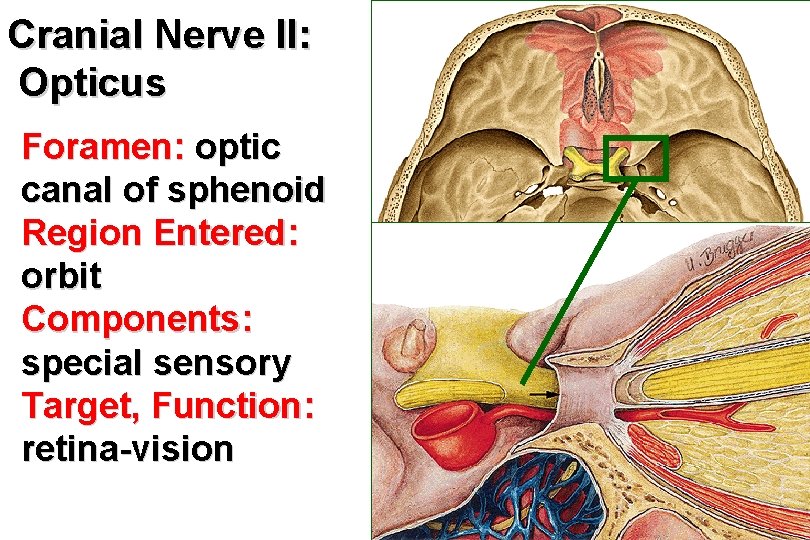
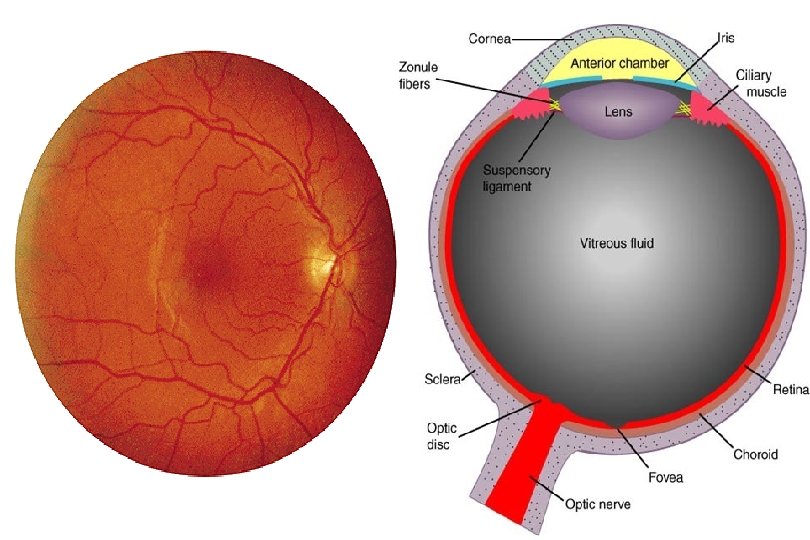
Cranial Nerve II: Opticus Foramen: optic canal of sphenoid Region Entered: orbit Components: special sensory Target, Function: retina-vision
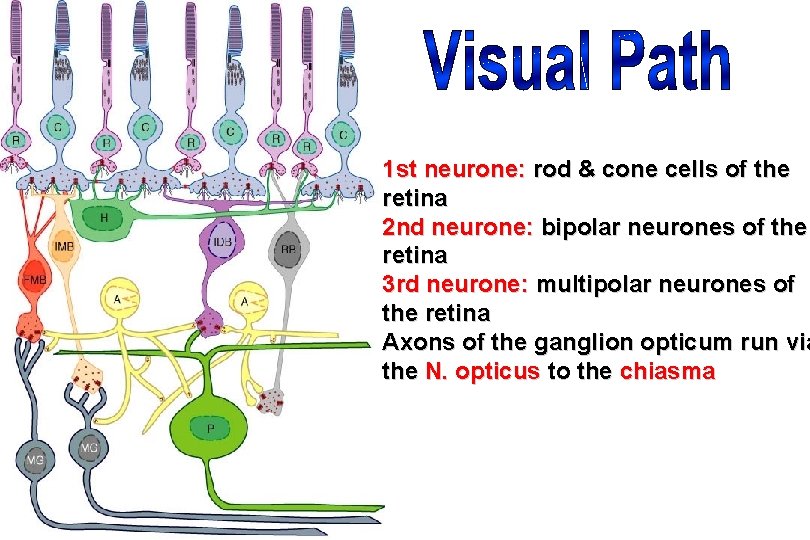
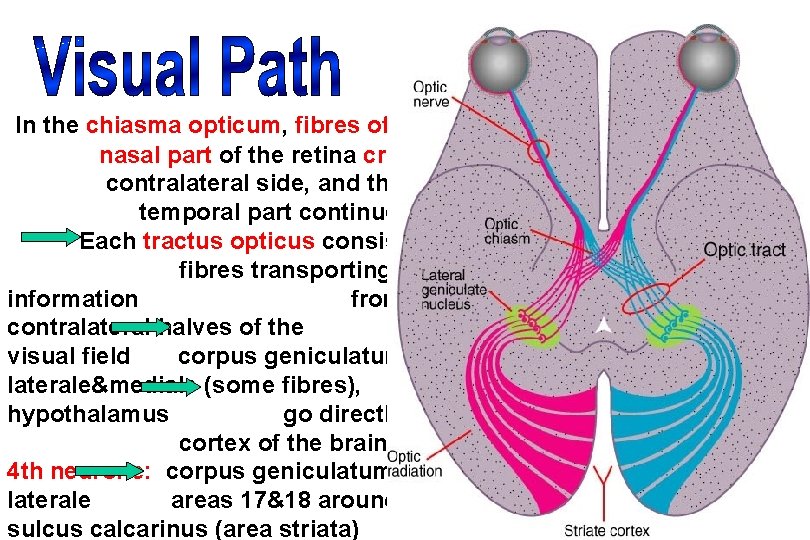
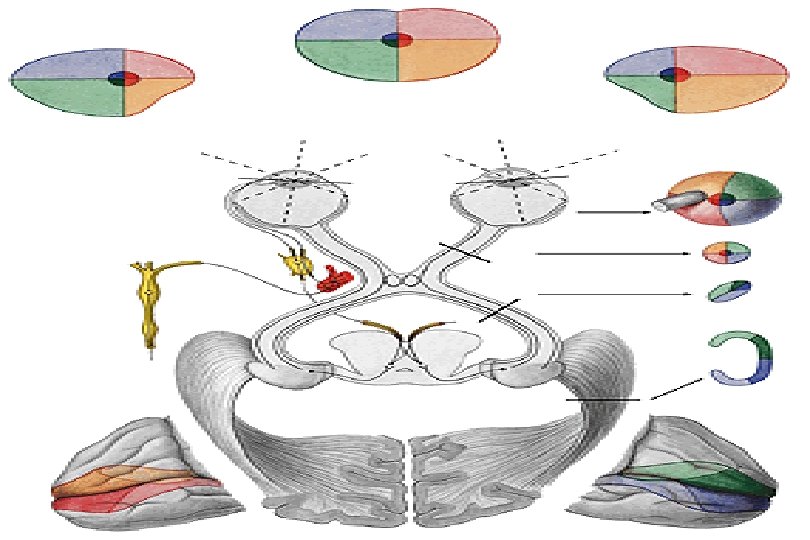
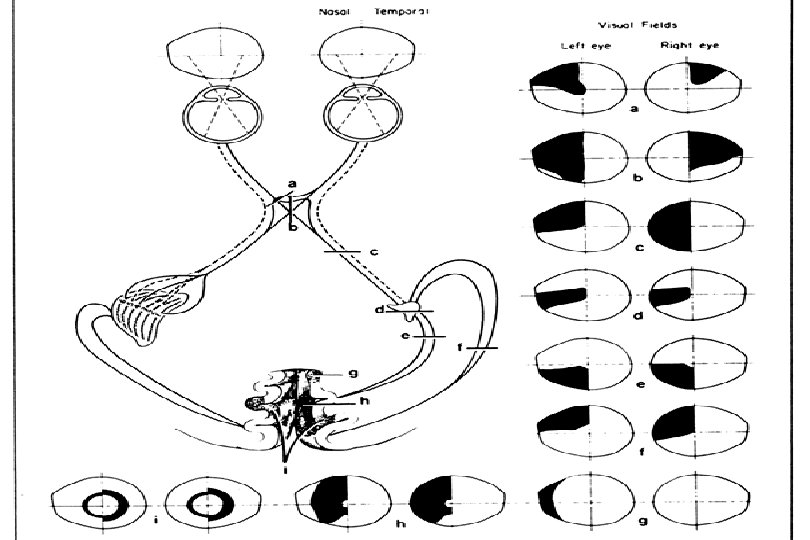
1 st neurone: rod & cone cells of the retina 2 nd neurone: bipolar neurones of the retina 3 rd neurone: multipolar neurones of the retina Axons of the ganglion opticum run via the N. opticus to the chiasma
In the chiasma opticum, fibres of the nasal part of the retina cross to the contralateral side, and those of the temporal part continue ipsilaterally Each tractus opticus consists of fibres transporting the information from the contralateral halves of the visual field corpus geniculatum laterale&mediale (some fibres), hypothalamus go directly to the cortex of the brain 4 th neurone: corpus geniculatum laterale areas 17&18 around the sulcus calcarinus (area striata)
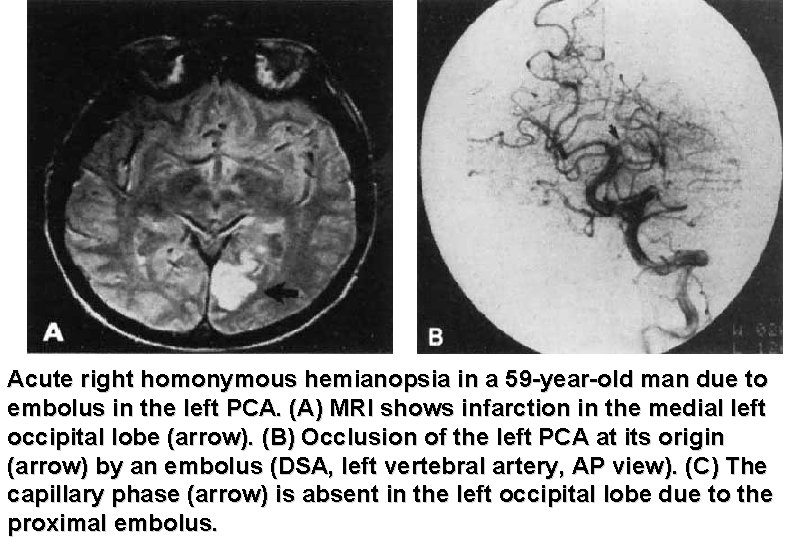
Acute right homonymous hemianopsia in a 59 -year-old man due to embolus in the left PCA. (A) MRI shows infarction in the medial left occipital lobe (arrow). (B) Occlusion of the left PCA at its origin (arrow) by an embolus (DSA, left vertebral artery, AP view). (C) The capillary phase (arrow) is absent in the left occipital lobe due to the proximal embolus.
Causes of Papillitis&Retrobulbar Neuritis § Multiple sclerosis § Viral illness; Syphilis § Temporal arteritis & other kinds of inflammation of the arteries (vasculitis) § Poisoning by chemicals: lead, methanol. . . § Tumors that have spread to the optic n. § Allergic reactions to beestings § Meningitis § Uveitis § Arteriosclerosis
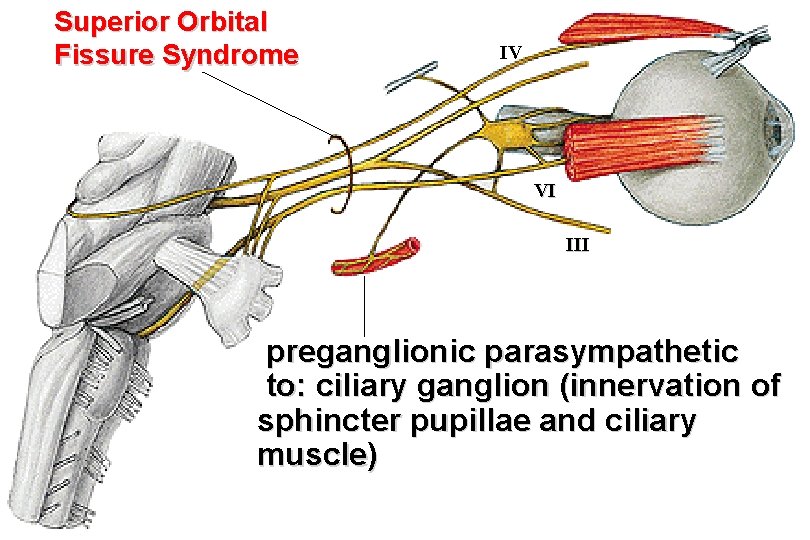
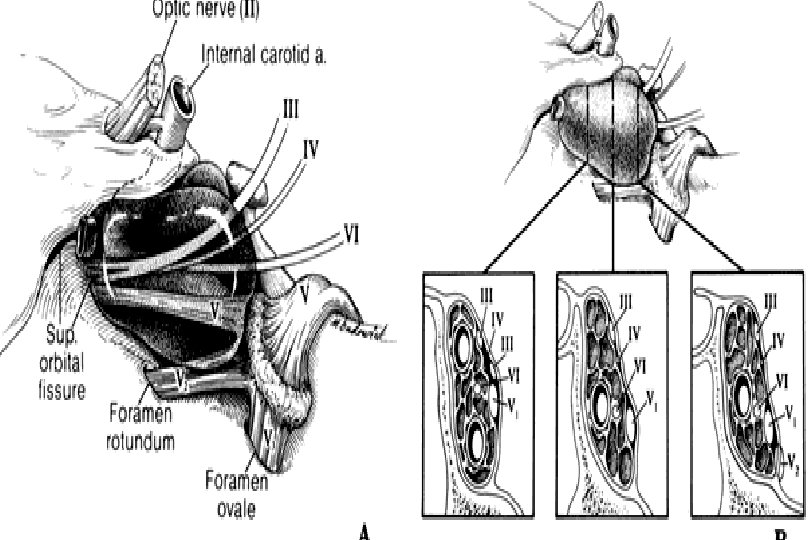
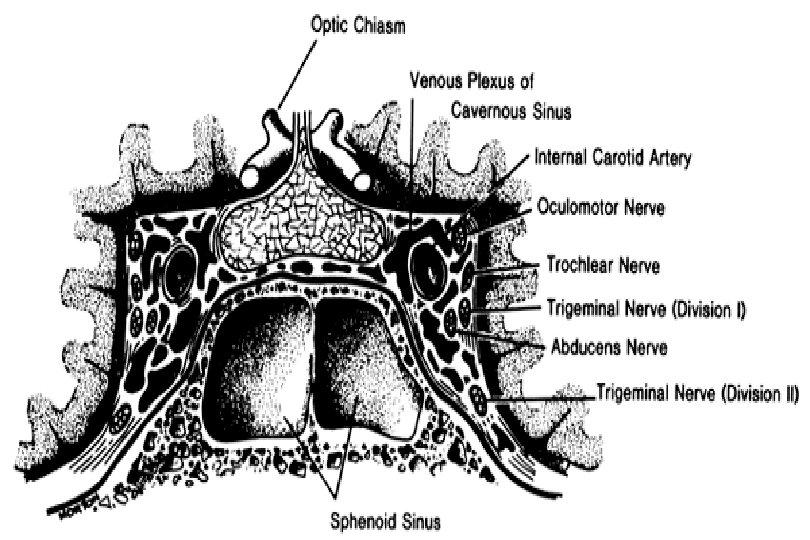
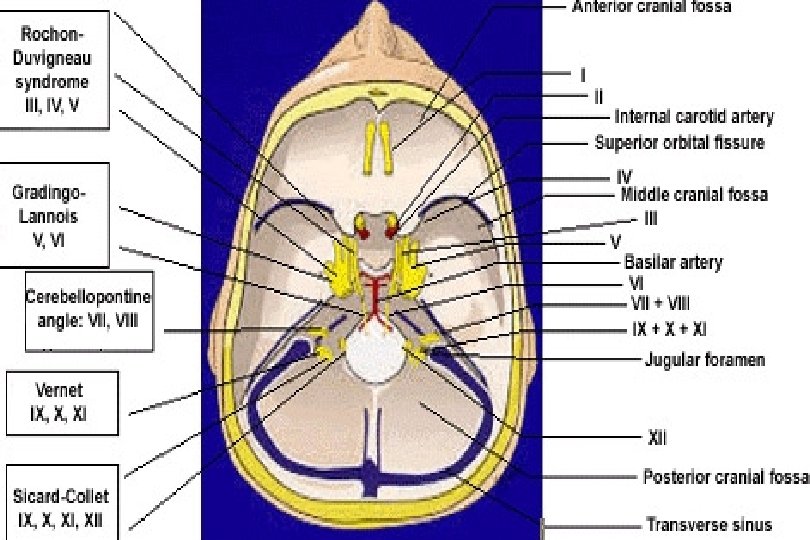
Superior Orbital Fissure Syndrome IV VI III preganglionic parasympathetic to: ciliary ganglion (innervation of sphincter pupillae and ciliary muscle)
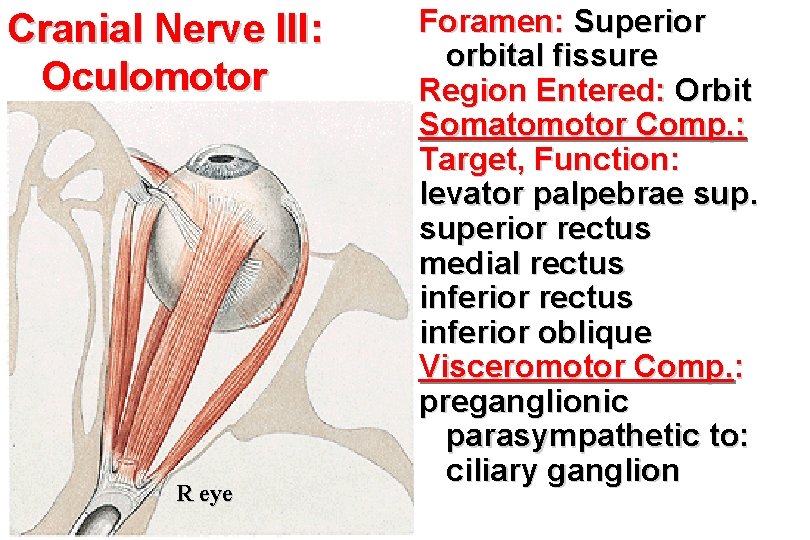
Cranial Nerve III: Oculomotor R eye Foramen: Superior orbital fissure Region Entered: Orbit Somatomotor Comp. : Target, Function: levator palpebrae superior rectus medial rectus inferior oblique Visceromotor Comp. : preganglionic parasympathetic to: ciliary ganglion
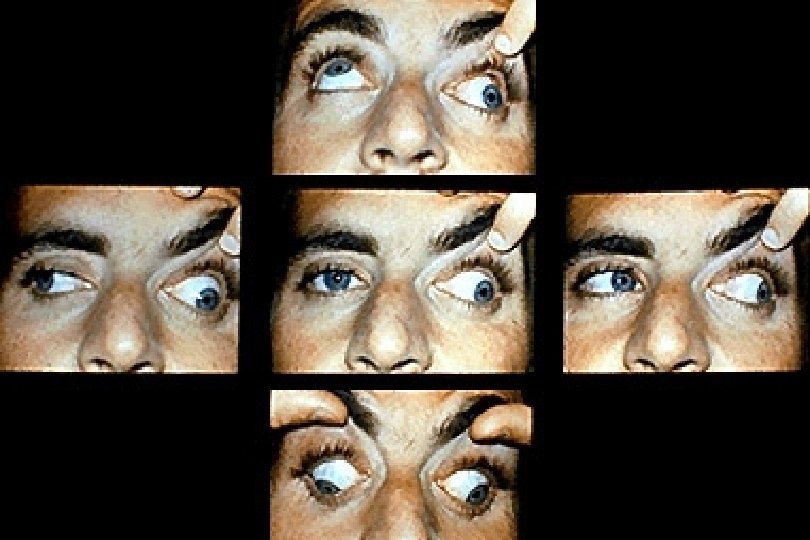
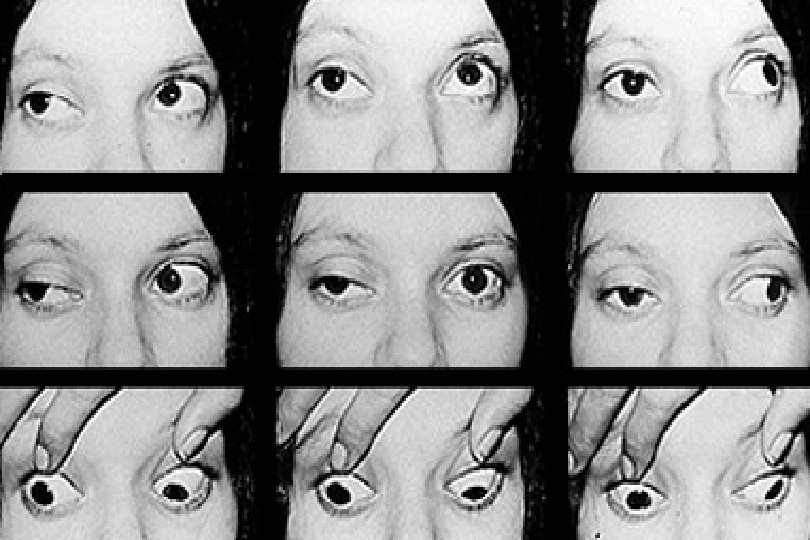
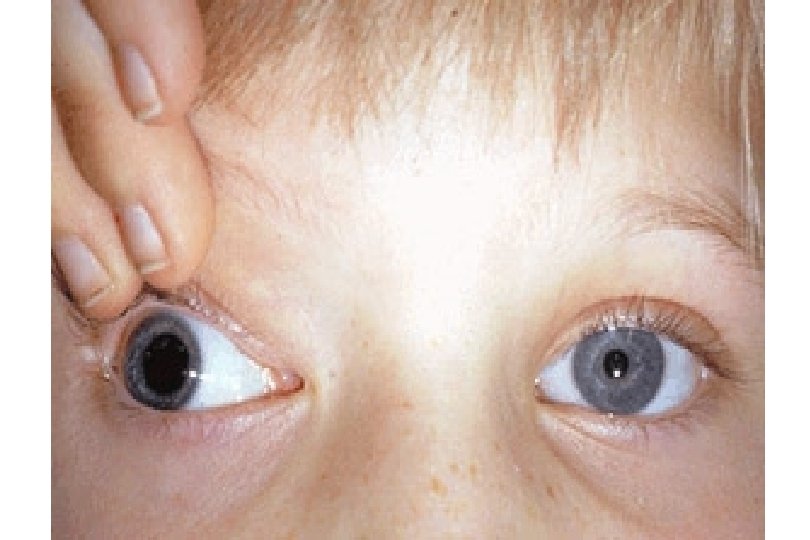
THIRD CRANIAL NERVE PALSIES During primary gaze, weakness of the muscles innervated by, result in: § Ptosis of the lid § Mydriasis § Outwardly turned eye Pupil is completely spared: • Myopathy • but all other muscles innervated by the 3 rd nerve are affected: diabetic 3 rd nerve paresis (ischemic process)
Fixed dilated pupils: 3 rd nerve compression - Aneurysm of the post. communicating art - Trauma - Intracranial mass lesion - Increasingly unresponsive patient with 3 rd n. palsy: transtentorial herniation Neurologic examination with CT or MRI • When CT does not show blood: Lumbar puncture (suspected SAH) • Cerebral angiography: if aneurysm is suspected
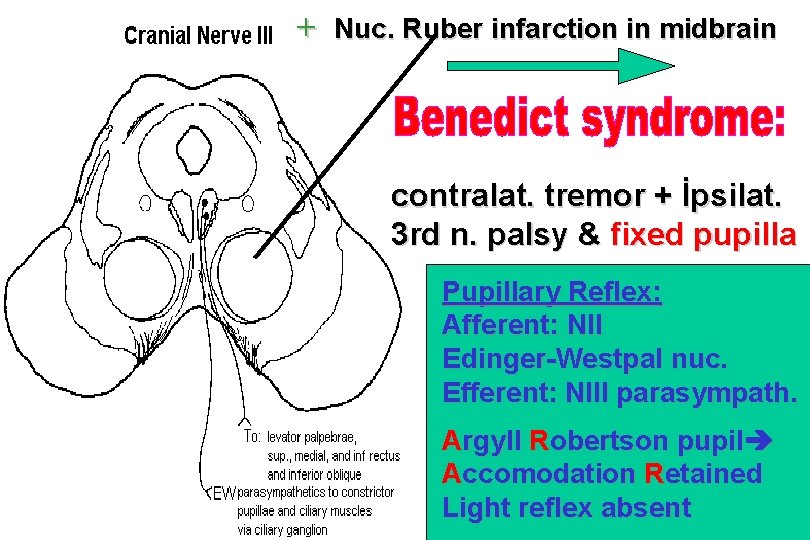
+ Nuc. Ruber infarction in midbrain contralat. tremor + İpsilat. 3 rd n. palsy & fixed pupilla Pupillary Reflex: Afferent: NII Edinger-Westpal nuc. Efferent: NIII parasympath. Argyll Robertson pupil Accomodation Retained Light reflex absent
• Ptosis • Myosis • Enophthalmus • Loss of sweating on the affected side of the face From hypothalamus, sympathetic nn. descend ipsilat. through the brainstem & cervical cord & riches the sympathetic chain via the motor root of T 1. From there, fibers pass along the outer sheath of the internal carotid artery&its opht. branch &to the pupilla. Fibers to the face travel with the ext. carotid artery
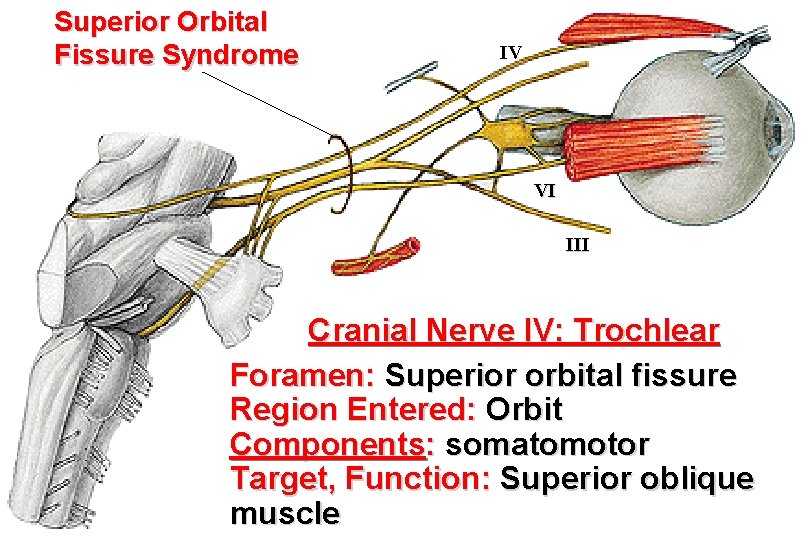
Superior Orbital Fissure Syndrome IV VI III Cranial Nerve IV: Trochlear Foramen: Superior orbital fissure Region Entered: Orbit Components: somatomotor Target, Function: Superior oblique muscle
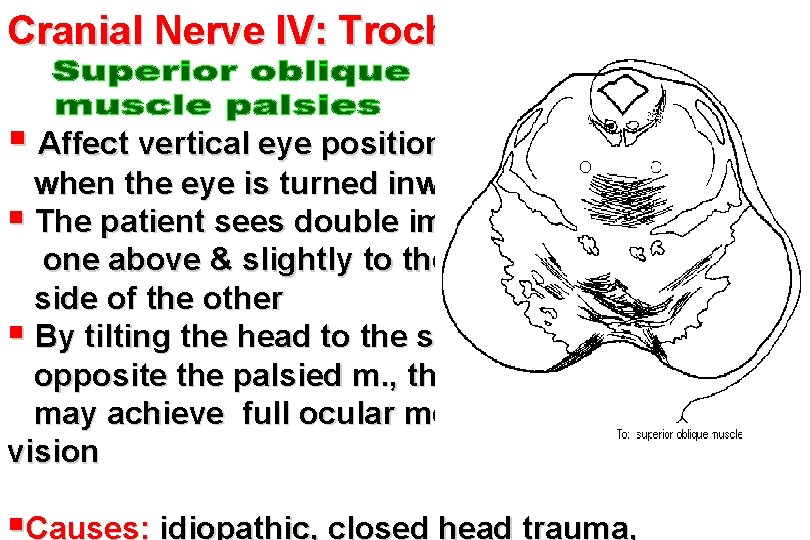
Cranial Nerve IV: Trochlear § Affect vertical eye position when the eye is turned inward § The patient sees double images: one above & slightly to the side of the other § By tilting the head to the side opposite the palsied m. , the pt may achieve full ocular motility without double vision §Causes: idiopathic, closed head trauma,
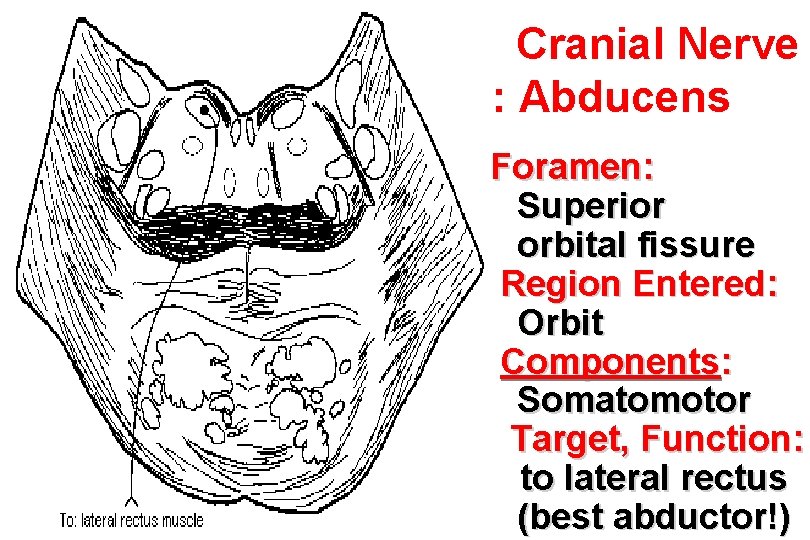
Cranial Nerve VI: Abducens Foramen: Superior orbital fissure Region Entered: Orbit Components: Somatomotor Target, Function: to lateral rectus (best abductor!)
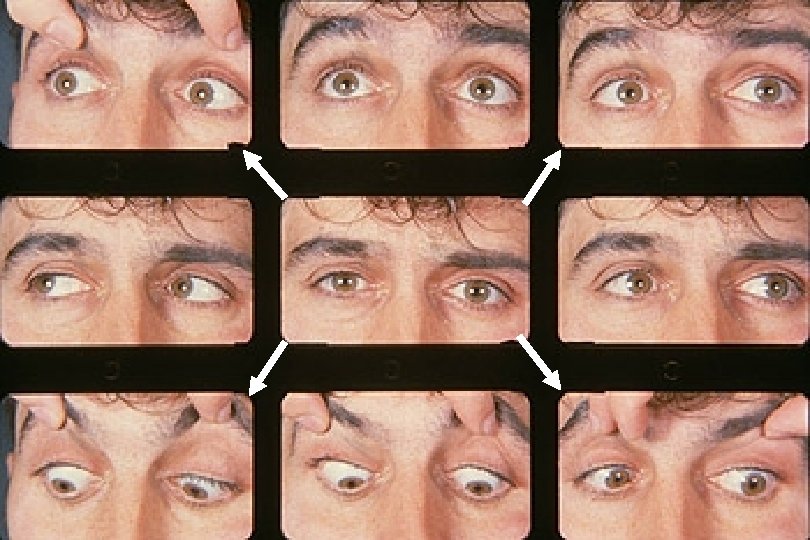
• Idiopathic: improvement within 2 mo • Elderly or diabetic pts: small vessel disease • Compression in cavernous sinus: severe headache & anesthesia in the area of n. V 1 • Increased intracranial pressure: shift in the brain stretch the 6 th n. • Trauma (basilar skull fracture) • Infections & tumors affecting the meninges • Aneurysm, MS • Wernicke's encephalopathy
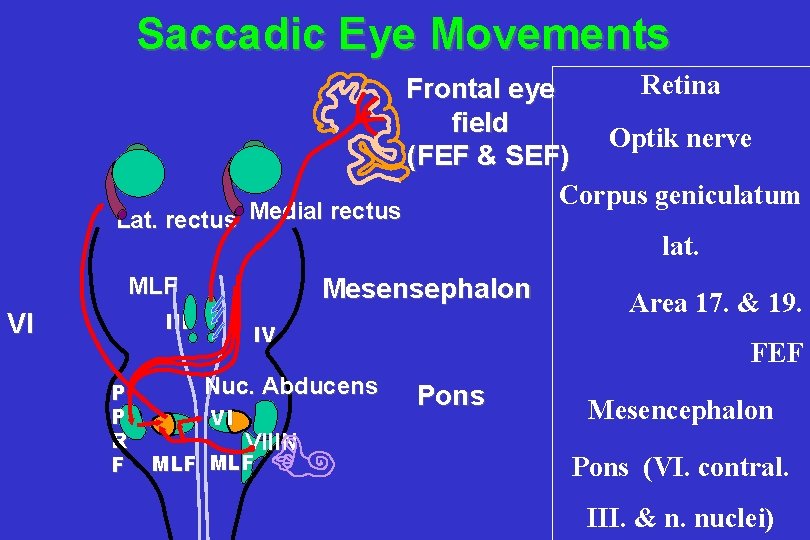
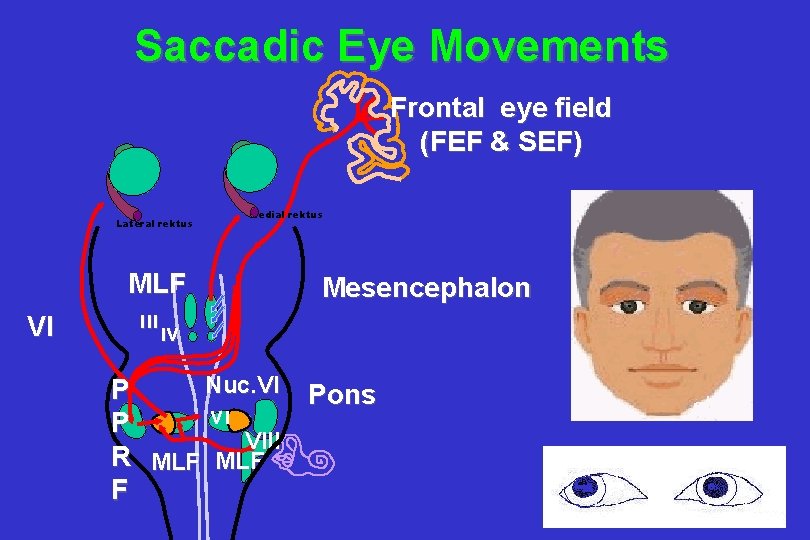
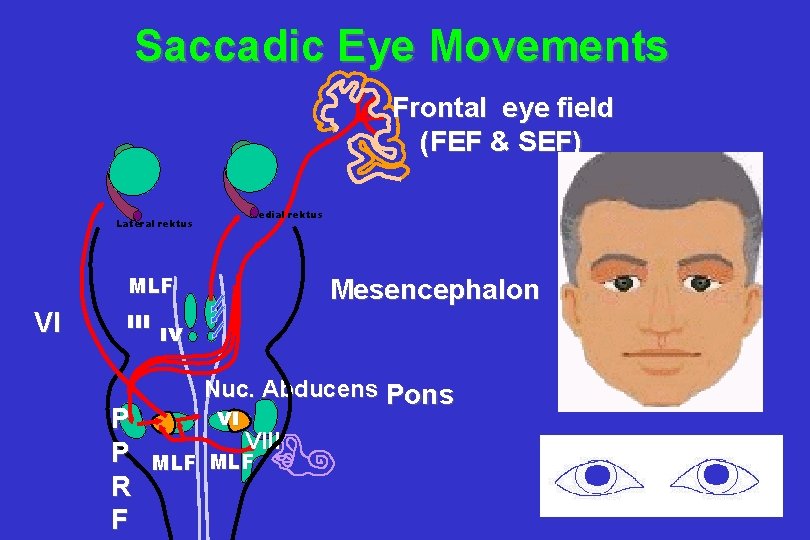
Saccadic Eye Movements Lat. rectus Medial rectus ııı P P R F lat. Mesensephalon MLF VI Retina Frontal eye field Optik nerve (FEF & SEF) Corpus geniculatum ıv Nuc. Abducens vı VIIIN MLF Area 17. & 19. FEF Pons Mesencephalon Pons (VI. contral. III. & n. nuclei)
Saccadic Eye Movements Frontal eye field (FEF & SEF) Lateral rektus MLF VI Medial rektus Mesencephalon ııı ıv Nuc. VI Pons P vı P VIII R MLF F
Saccadic Eye Movements Frontal eye field (FEF & SEF) Lateral rektus Medial rektus MLF VI Mesencephalon ııı ıv P P R F Nuc. Abducens Pons vı VIII MLF
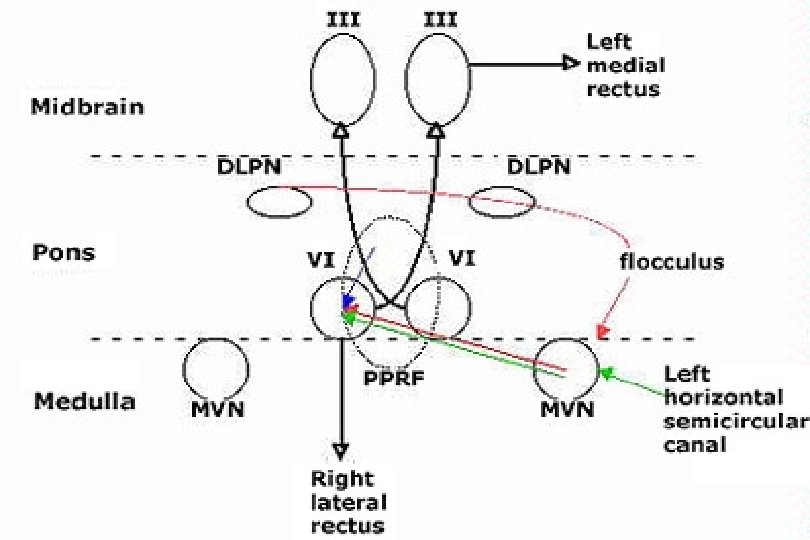
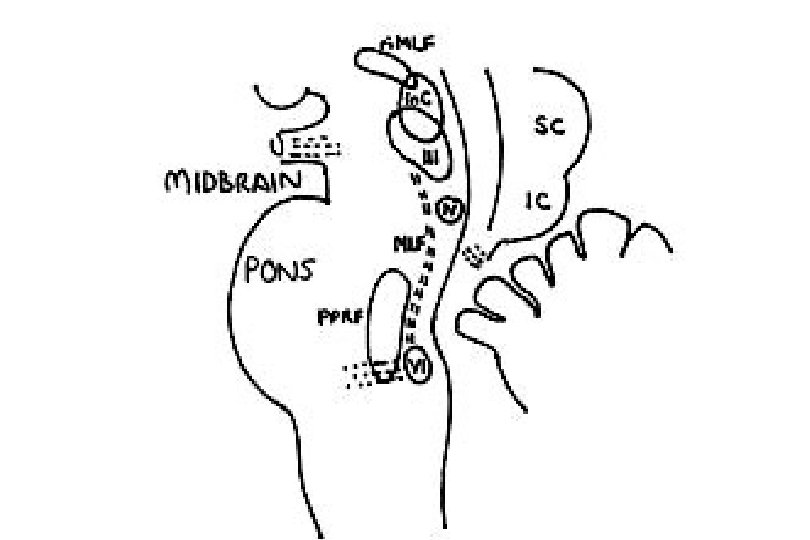
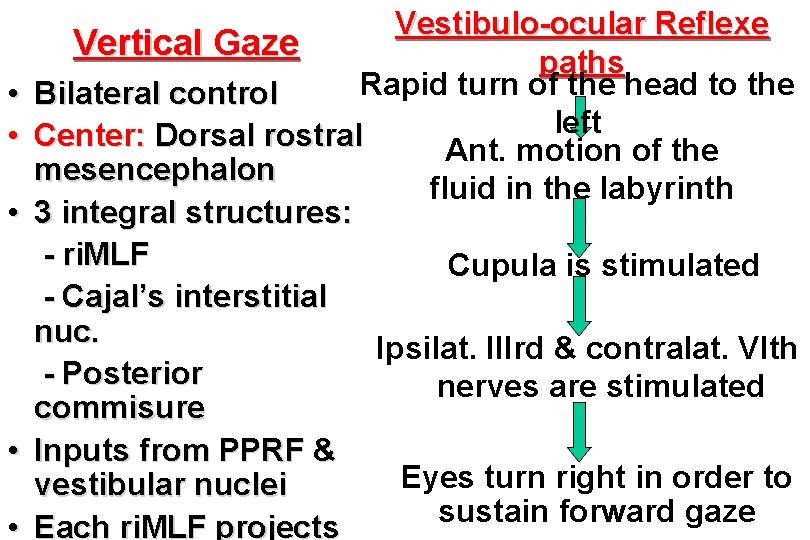
• • • Vestibulo-ocular Reflexe Vertical Gaze paths Rapid turn of the head to the Bilateral control left Center: Dorsal rostral Ant. motion of the mesencephalon fluid in the labyrinth 3 integral structures: - ri. MLF Cupula is stimulated - Cajal’s interstitial nuc. Ipsilat. IIIrd & contralat. VIth - Posterior nerves are stimulated commisure Inputs from PPRF & Eyes turn right in order to vestibular nuclei sustain forward gaze Each ri. MLF projects
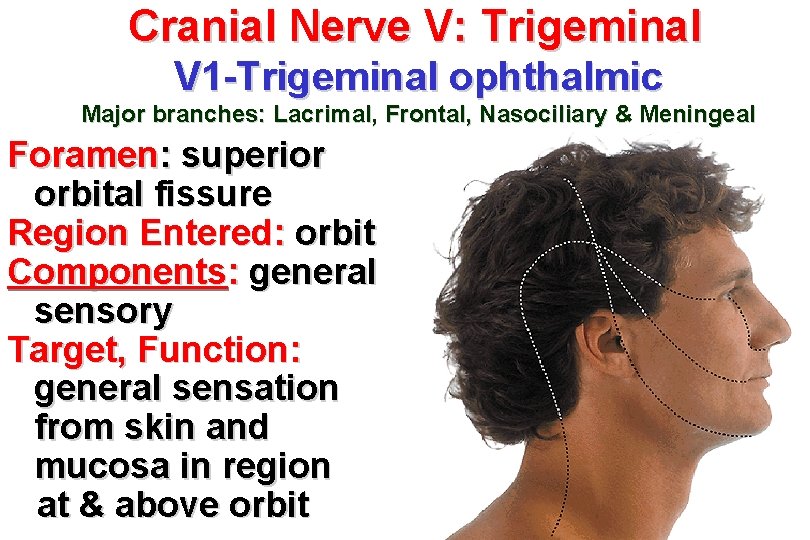
Cranial Nerve V: Trigeminal V 1 -Trigeminal ophthalmic Major branches: Lacrimal, Frontal, Nasociliary & Meningeal Foramen: superior orbital fissure Region Entered: orbit Components: general sensory Target, Function: general sensation from skin and mucosa in region at & above orbit
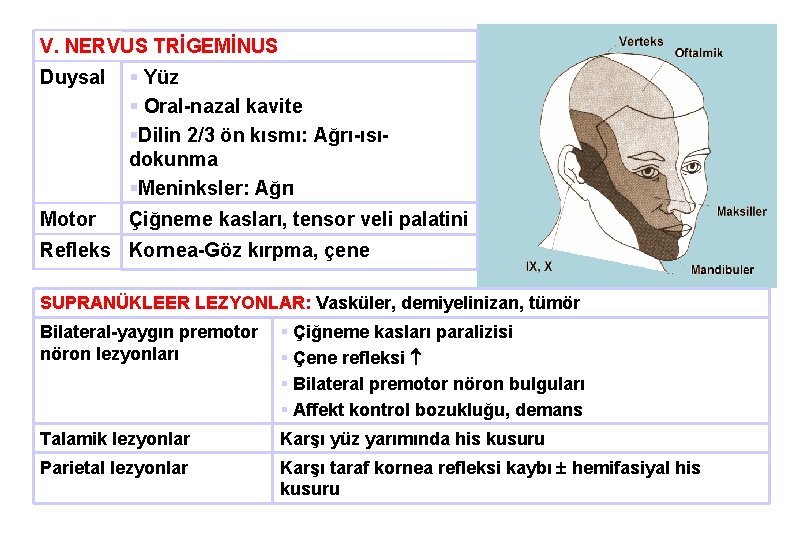
V. NERVUS TRİGEMİNUS Duysal § Yüz § Oral-nazal kavite §Dilin 2/3 ön kısmı: Ağrı-ısıdokunma §Meninksler: Ağrı Motor Çiğneme kasları, tensor veli palatini Refleks Kornea-Göz kırpma, çene SUPRANÜKLEER LEZYONLAR: Vasküler, demiyelinizan, tümör Bilateral-yaygın premotor nöron lezyonları § Çiğneme kasları paralizisi § Çene refleksi § Bilateral premotor nöron bulguları § Affekt kontrol bozukluğu, demans Talamik lezyonlar Karşı yüz yarımında his kusuru Parietal lezyonlar Karşı taraf kornea refleksi kaybı hemifasiyal his kusuru
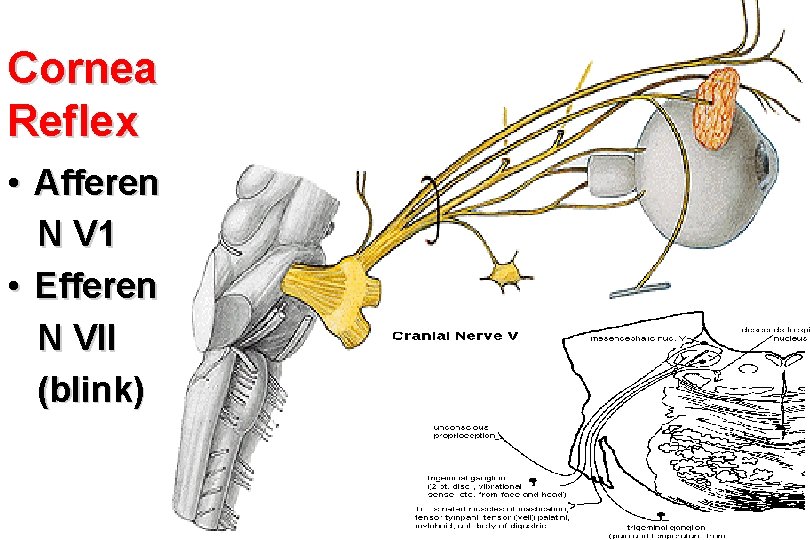
Cornea Reflex • Afferent: N V 1 • Efferent: N VII (blink) Ciliary ganglion
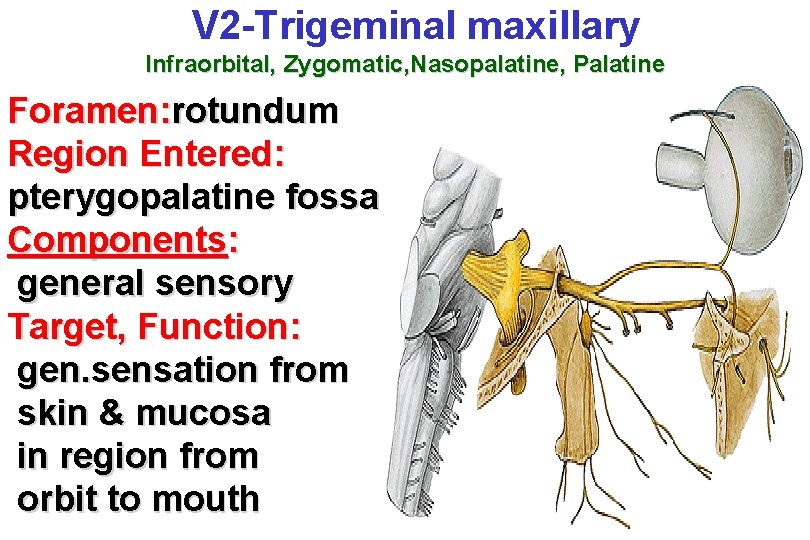
V 2 -Trigeminal maxillary Infraorbital, Zygomatic, Nasopalatine, Palatine Foramen: rotundum Region Entered: pterygopalatine fossa Components: general sensory Target, Function: gen. sensation from skin & mucosa in region from orbit to mouth
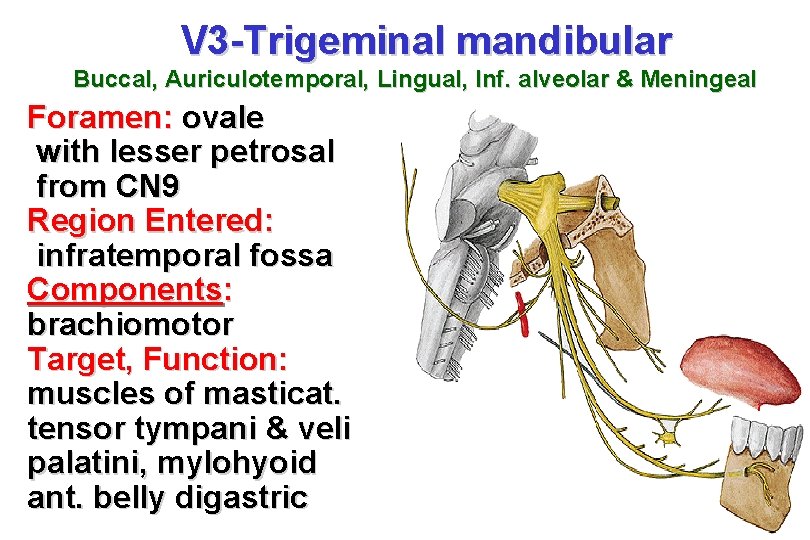
V 3 -Trigeminal mandibular Buccal, Auriculotemporal, Lingual, Inf. alveolar & Meningeal Foramen: ovale with lesser petrosal from CN 9 Region Entered: infratemporal fossa Components: brachiomotor Target, Function: muscles of masticat. tensor tympani & veli palatini, mylohyoid ant. belly digastric
§ Lesion of spinal tract V IPSILATERAL deficits in pain & temperature from the face etc. (the pain information never gets to the caudal spinal nucleus) § Interruption of the trigeminothalamic tract deficits in pain & temperature on the contralateral side of the face
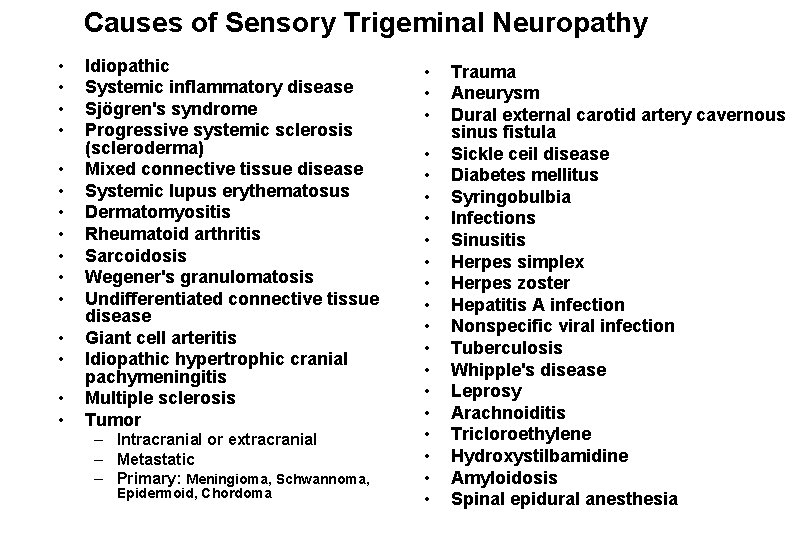
Causes of Sensory Trigeminal Neuropathy • • • • Idiopathic Systemic inflammatory disease Sjögren's syndrome Progressive systemic sclerosis (scleroderma) Mixed connective tissue disease Systemic lupus erythematosus Dermatomyositis Rheumatoid arthritis Sarcoidosis Wegener's granulomatosis Undifferentiated connective tissue disease Giant cell arteritis Idiopathic hypertrophic cranial pachymeningitis Multiple sclerosis Tumor – Intracranial or extracranial – Metastatic – Primary: Meningioma, Schwannoma, Epidermoid, Chordoma • • • • • Trauma Aneurysm Dural external carotid artery cavernous sinus fistula Sickle ceil disease Diabetes mellitus Syringobulbia Infections Sinusitis Herpes simplex Herpes zoster Hepatitis A infection Nonspecific viral infection Tuberculosis Whipple's disease Leprosy Arachnoiditis Tricloroethylene Hydroxystilbamidine Amyloidosis Spinal epidural anesthesia
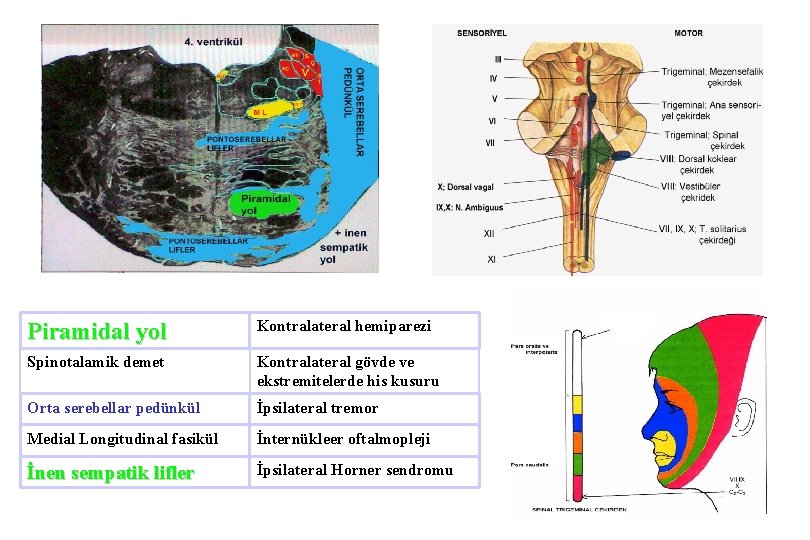
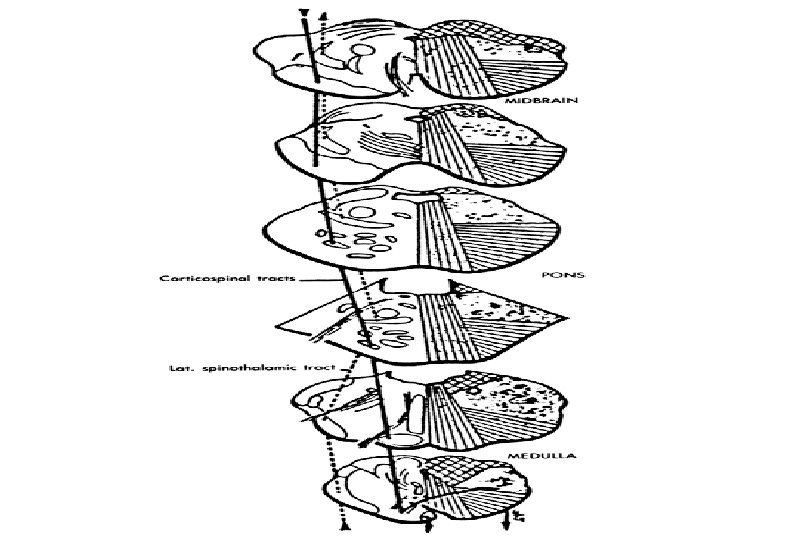
Piramidal yol Kontralateral hemiparezi Spinotalamik demet Kontralateral gövde ve ekstremitelerde his kusuru Orta serebellar pedünkül İpsilateral tremor Medial Longitudinal fasikül İnternükleer oftalmopleji İnen sempatik lifler İpsilateral Horner sendromu
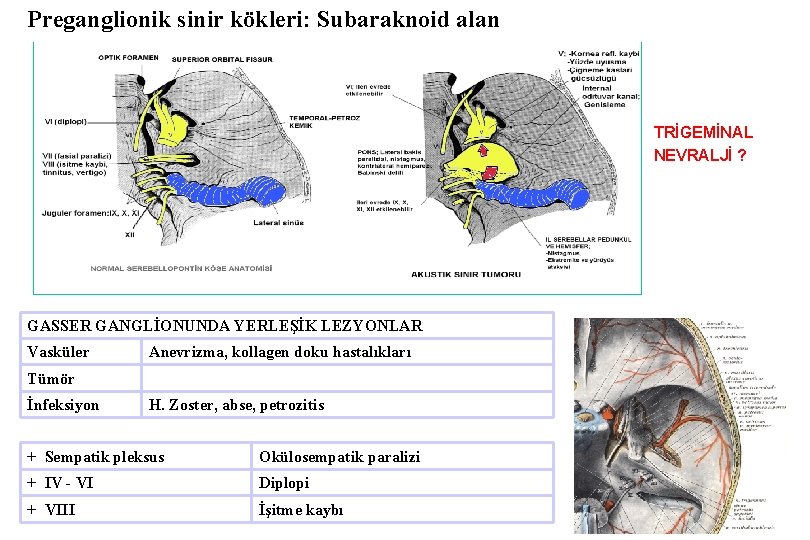
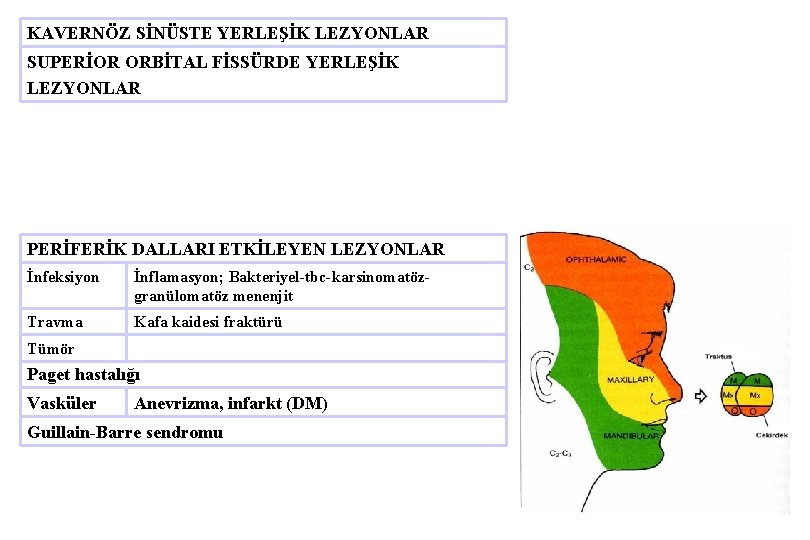
Preganglionik sinir kökleri: Subaraknoid alan TRİGEMİNAL NEVRALJİ ? GASSER GANGLİONUNDA YERLEŞİK LEZYONLAR Vasküler Anevrizma, kollagen doku hastalıkları Tümör İnfeksiyon H. Zoster, abse, petrozitis + Sempatik pleksus Okülosempatik paralizi + IV - VI Diplopi + VIII İşitme kaybı
KAVERNÖZ SİNÜSTE YERLEŞİK LEZYONLAR SUPERİOR ORBİTAL FİSSÜRDE YERLEŞİK LEZYONLAR PERİFERİK DALLARI ETKİLEYEN LEZYONLAR İnfeksiyon İnflamasyon; Bakteriyel-tbc-karsinomatözgranülomatöz menenjit Travma Kafa kaidesi fraktürü Tümör Paget hastalığı Vasküler Anevrizma, infarkt (DM) Guillain-Barre sendromu
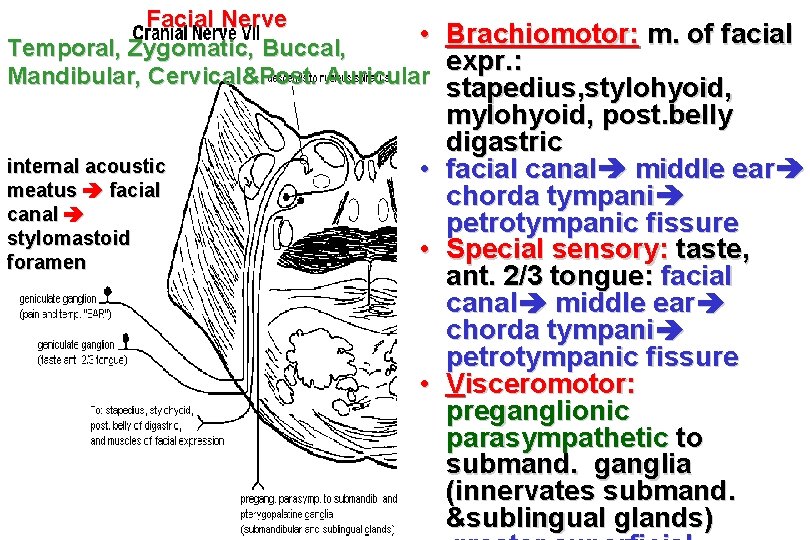
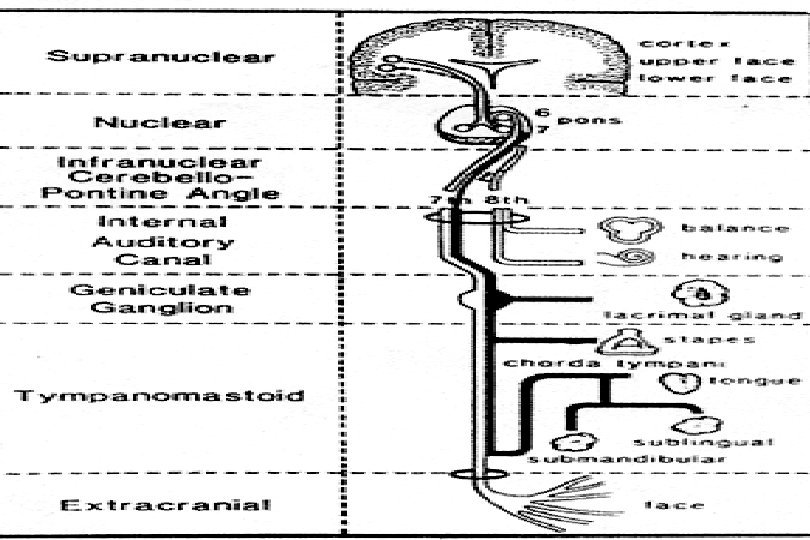
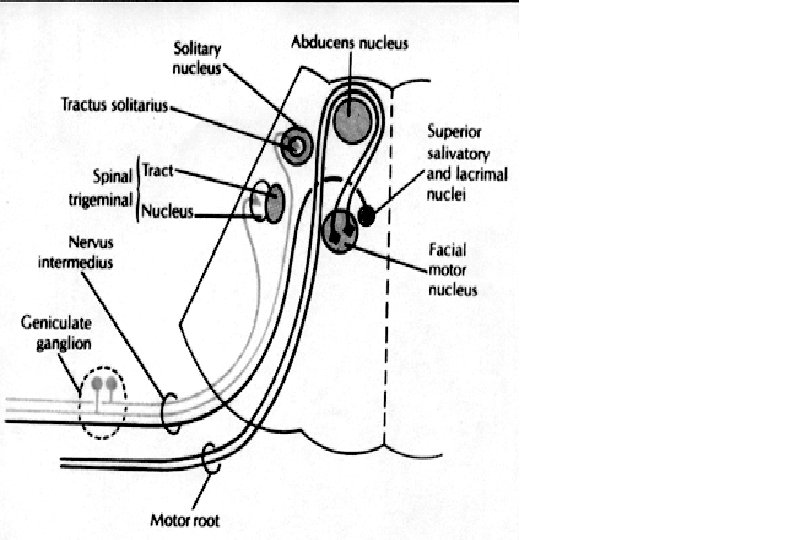
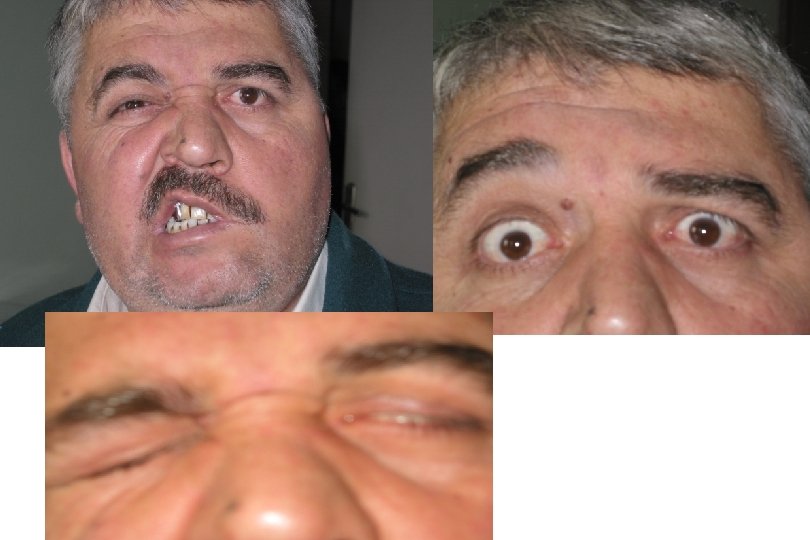
Facial Nerve • Temporal, Zygomatic, Buccal, Mandibular, Cervical&Post. Auricular internal acoustic meatus facial canal stylomastoid foramen Brachiomotor: m. of facial expr. : stapedius, stylohyoid, mylohyoid, post. belly digastric • facial canal middle ear chorda tympani petrotympanic fissure • Special sensory: taste, ant. 2/3 tongue: facial canal middle ear chorda tympani petrotympanic fissure • Visceromotor: preganglionic parasympathetic to submand. ganglia (innervates submand. &sublingual glands)
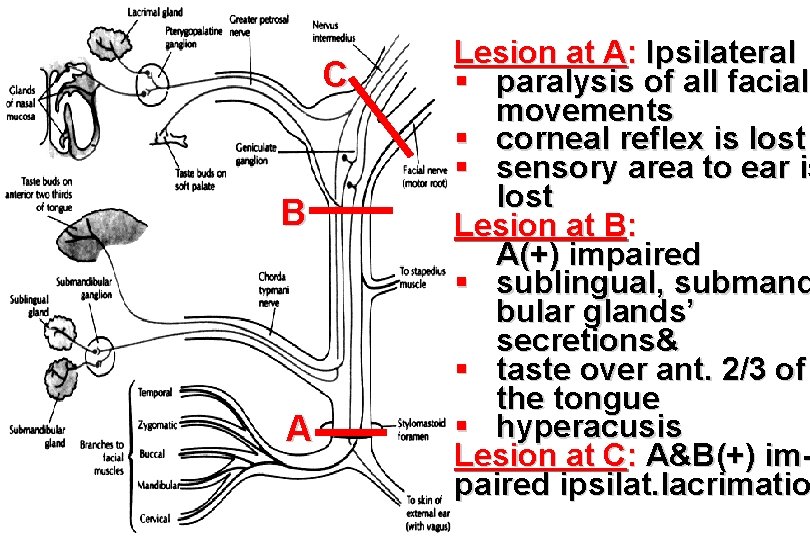
C B A Lesion at A: Ipsilateral § paralysis of all facial movements § corneal reflex is lost § sensory area to ear is lost Lesion at B: A(+) impaired § sublingual, submand bular glands’ secretions& § taste over ant. 2/3 of the tongue § hyperacusis Lesion at C: A&B(+) impaired ipsilat. lacrimatio
Causes of Peripheral Facial Nerve Palsy • • • Idiopathic (Bell's palsy) Infectious: – – – – Herpes simplex Herpes zoster Otitis media Borrelia burgdorferi Human immunodeficiency virus Syphilis Infectious mononucleosis Mastoiditis Poliomyelitis Meningitis Malaria Leprosy Rubella Mumps Osteomyelitis Cat scratch disease • • • Inflammatory – – – Guillain-Barré syndrome Sarcoidosis Multiple sclerosis Arteritis Melkersson-Rosenthal syndrome Behçet syndrome Wegener's granulomatosis Lymphomatoid granulomatosis Kawasaki disease Angioedema Pseudotumor (Tolosa-Hunt syndrome) – Amyloidosis – Idiopathic hypertrophic cranial pachymeningitis Neoplastic – – – – Schwannoma Neurofibroma Meningioma Cholesteatoma Parotid gland tumor Metastasis Carcinomatous meningitis Leukemia Metabolic – – Diabetes mellitus Hypothyroidism Uremia Porphyria Trauma: Surgical trauma to nerve Congenital, Familial Miscellaneous – – – Pregnancy Paget's disease Osteopetrosis Hypertension Diphtheria-pertussis-tetanus vaccination Pontine infarction Myasthenia gravis Traumatic external carotid artery aneurysm Lumbar extradural blood patch Vascular malformation Pseudotumor cerebri Ethylene glycol poisoning
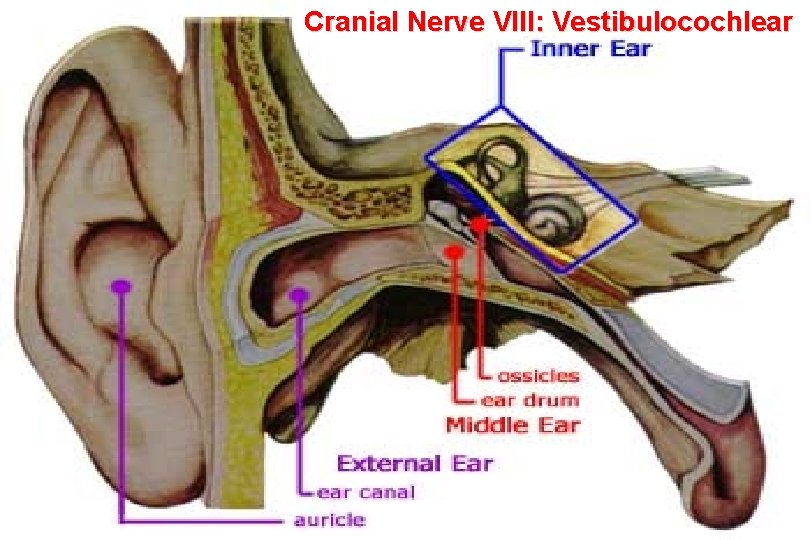
Cranial Nerve VIII: Vestibulocochlear
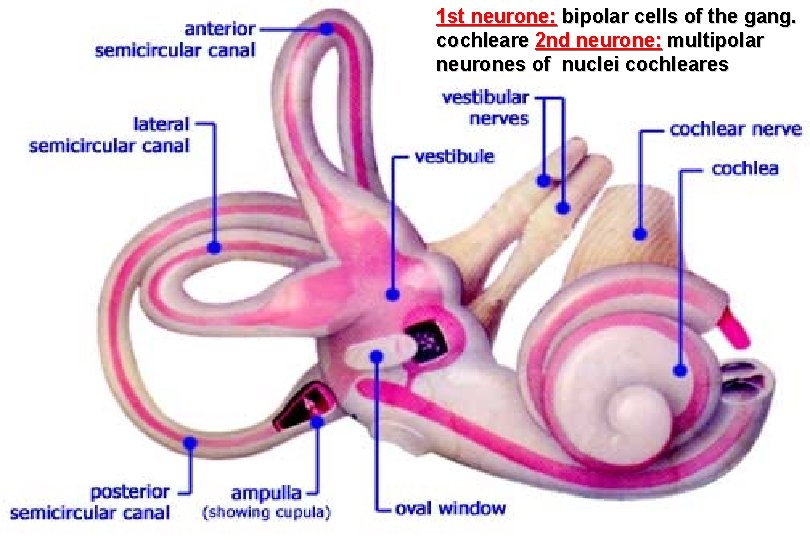
1 st neurone: bipolar cells of the gang. cochleare 2 nd neurone: multipolar neurones of nuclei cochleares
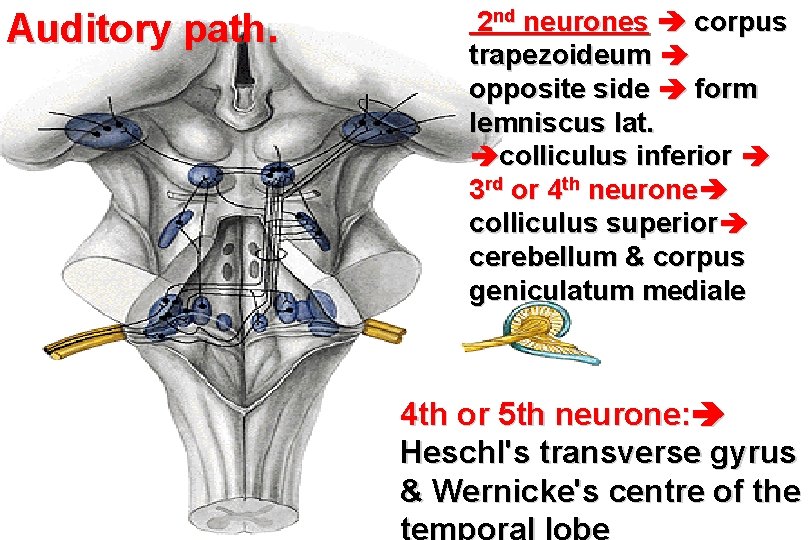
Auditory path. 2 nd neurones corpus trapezoideum opposite side form lemniscus lat. colliculus inferior 3 rd or 4 th neurone colliculus superior cerebellum & corpus geniculatum mediale 4 th or 5 th neurone: Heschl's transverse gyrus & Wernicke's centre of the temporal lobe
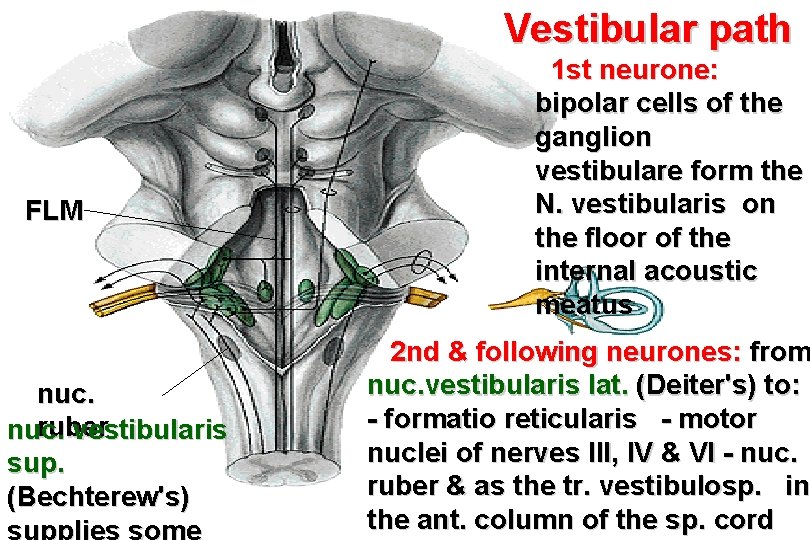
Vestibular path FLM nuc. ruber nuc. vestibularis sup. (Bechterew's) supplies some 1 st neurone: bipolar cells of the ganglion vestibulare form the N. vestibularis on the floor of the internal acoustic meatus 2 nd & following neurones: from nuc. vestibularis lat. (Deiter's) to: - formatio reticularis - motor nuclei of nerves III, IV & VI - nuc. ruber & as the tr. vestibulosp. in the ant. column of the sp. cord
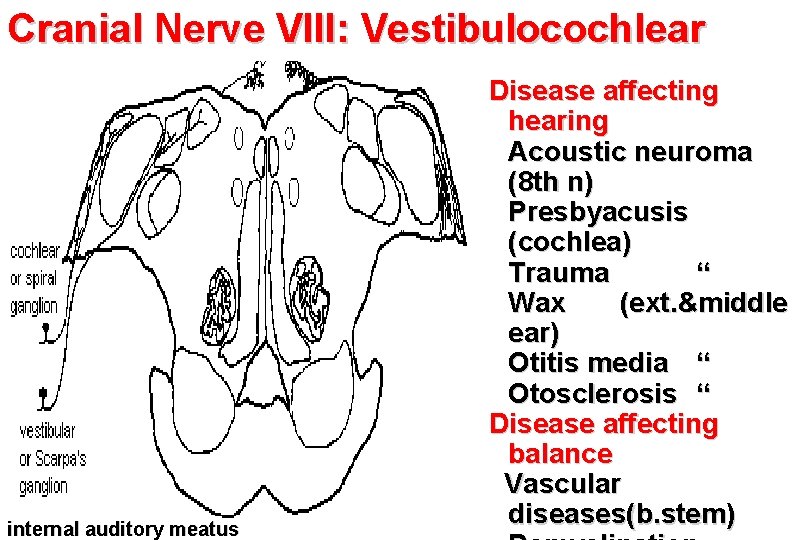
Cranial Nerve VIII: Vestibulocochlear internal auditory meatus Disease affecting hearing Acoustic neuroma (8 th n) Presbyacusis (cochlea) Trauma “ Wax (ext. &middle ear) Otitis media “ Otosclerosis “ Disease affecting balance Vascular diseases(b. stem)
Cochleo-vestibular Disease Main Symptoms Main Signs • • Deafness Tinnitus Vertigo Loss of balance • Deafness • Nystagmus • Ataxia • Positional nystagmus
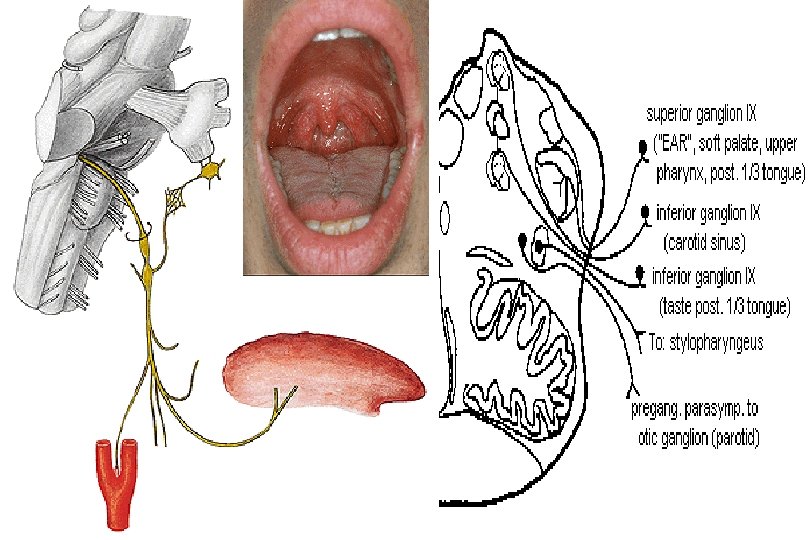
Cranial Nerve IX: • Foramen: jugular • Special visceromotor: Function: elevates pharynx nucleus ambiguus stylopharyngeus • Gen. Sensory Components Function: general sensation of external, middle ear & auditory tube geniculate ganglion spinal trigeminal nucleus • Special Viscerosensory Component: • Function: taste, posterior 1/3 tongue=> inferior petrosal ganglion rostral tractus solitarius • Region Entered: infratemporal fossa • Gen. Viscerosensory: Sensory receptors of ant. surface epiglottis, root of tongue, border of soft palate, uvula, tonsil, pharynx, eustachian tube, carotid sinus & body caudal tractus solitarius • Gen. Visceromotor comp. : İnf. salivary nuc. tympani n. lesser petrosal n otic ganglion auriculotemporal n. • Function: parotid gland secretion
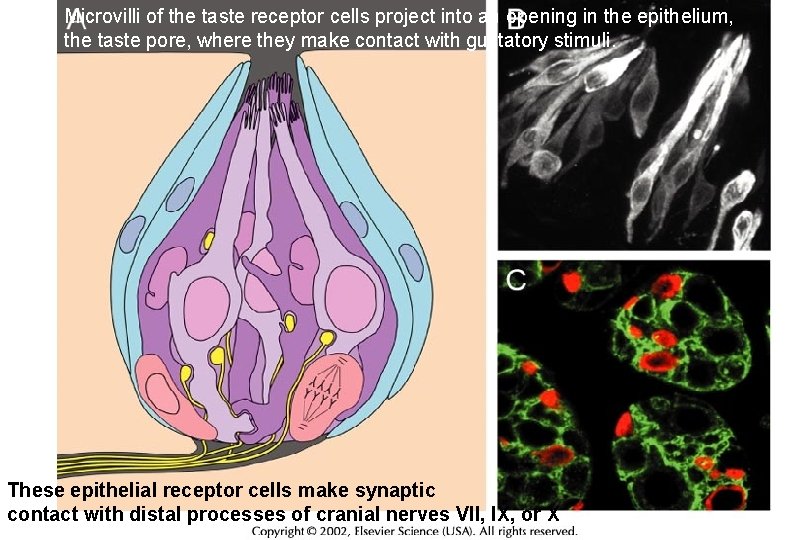
Microvilli of the taste receptor cells project into an opening in the epithelium, the taste pore, where they make contact with gustatory stimuli. These epithelial receptor cells make synaptic contact with distal processes of cranial nerves VII, IX, or X
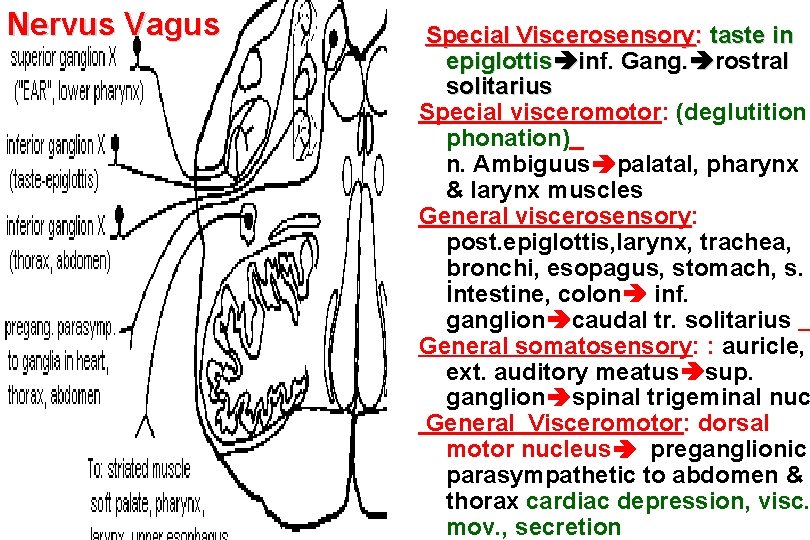
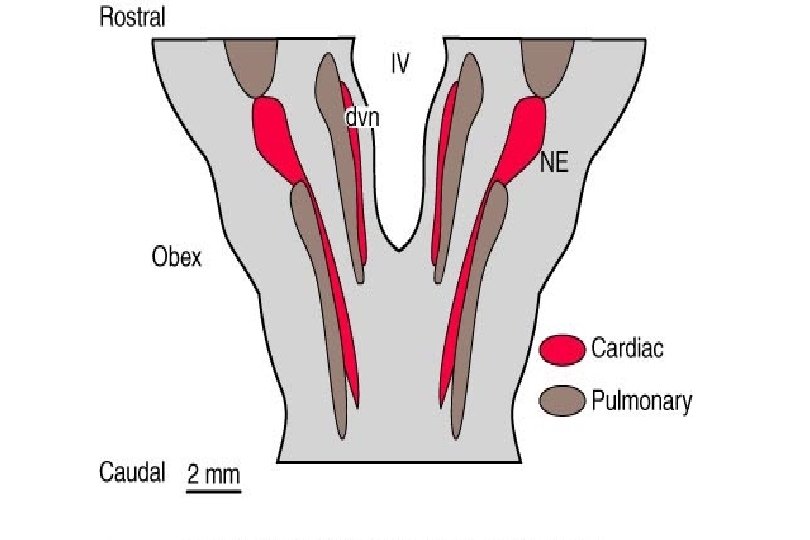
Nervus Vagus Special Viscerosensory: taste in epiglottis inf. Gang. rostral solitarius Special visceromotor: (deglutition phonation) n. Ambiguus palatal, pharynx & larynx muscles General viscerosensory: post. epiglottis, larynx, trachea, bronchi, esopagus, stomach, s. İntestine, colon inf. ganglion caudal tr. solitarius General somatosensory: : auricle, ext. auditory meatus sup. ganglion spinal trigeminal nuc General Visceromotor: dorsal motor nucleus preganglionic parasympathetic to abdomen & thorax cardiac depression, visc. mov. , secretion
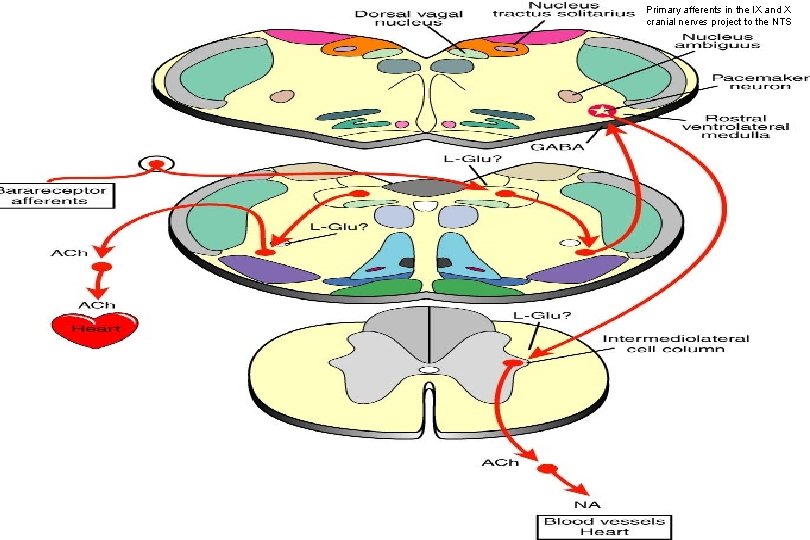
Primary afferents in the IX and X cranial nerves project to the NTS
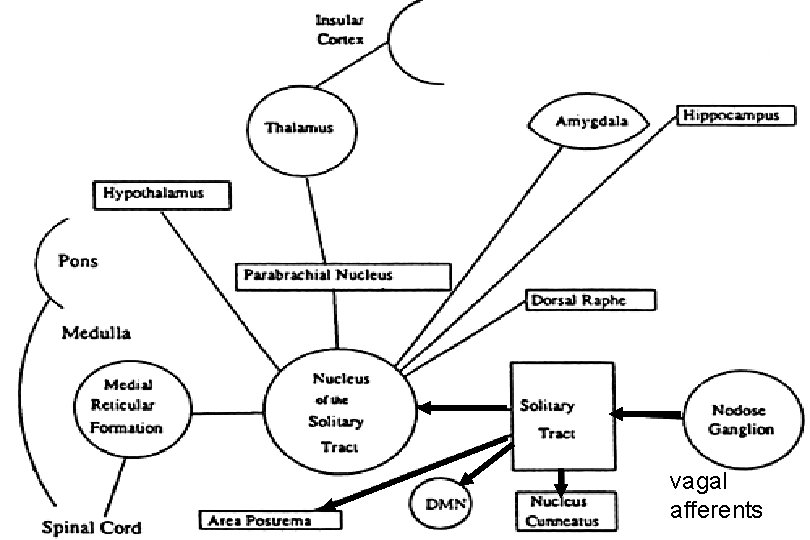
vagal afferents
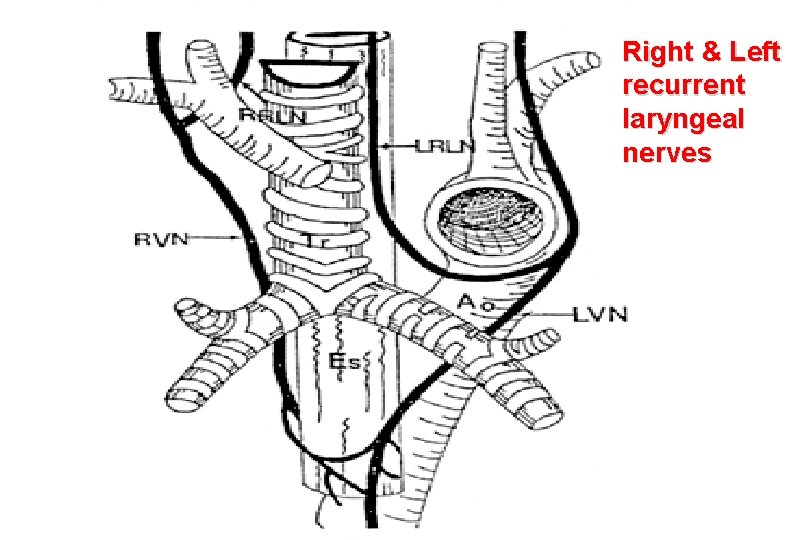
Right & Left recurrent laryngeal nerves
Selected Causes of Vagus Nerve Dysfunction • • • • Lateral medullary syndrome Hyperextension injury of upper cervical spine Chronic lead poisoning Radiation therapy to head and neck Glomus vagale tumor Neuroma Schwannoma presenting as cerebellopontine angle mass Nasopharyngeal diphtheria Viral or postviral mononeuritis Herpes simplex Cytomegalovirus Herpes zoster Multiple system atrophy Superior laryngeal neuralgia
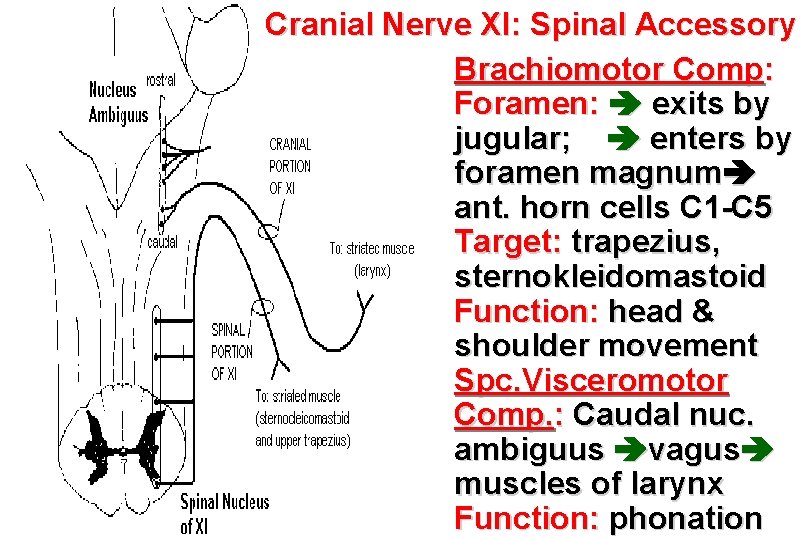
Cranial Nerve XI: Spinal Accessory • Brachiomotor Comp: Foramen: exits by jugular; enters by foramen magnum ant. horn cells C 1 -C 5 Target: trapezius, sternokleidomastoid Function: head & shoulder movement • Spc. Visceromotor Comp. : Caudal nuc. ambiguus vagus muscles of larynx Function: phonation
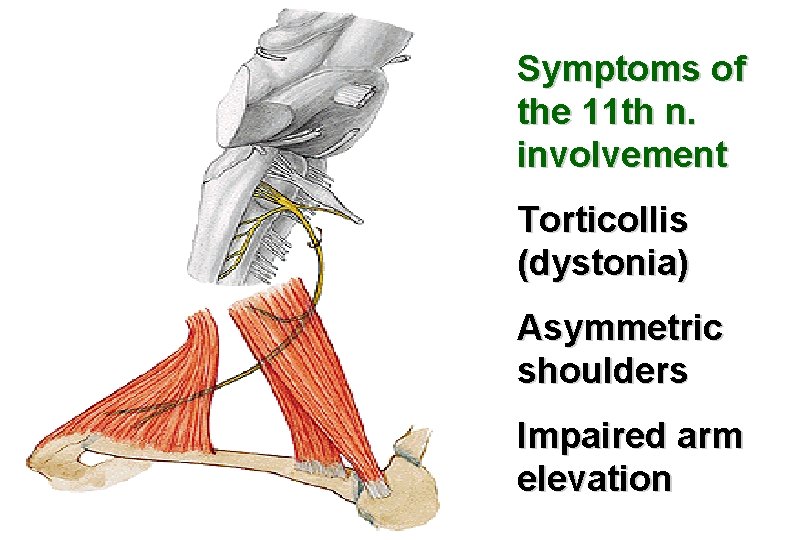
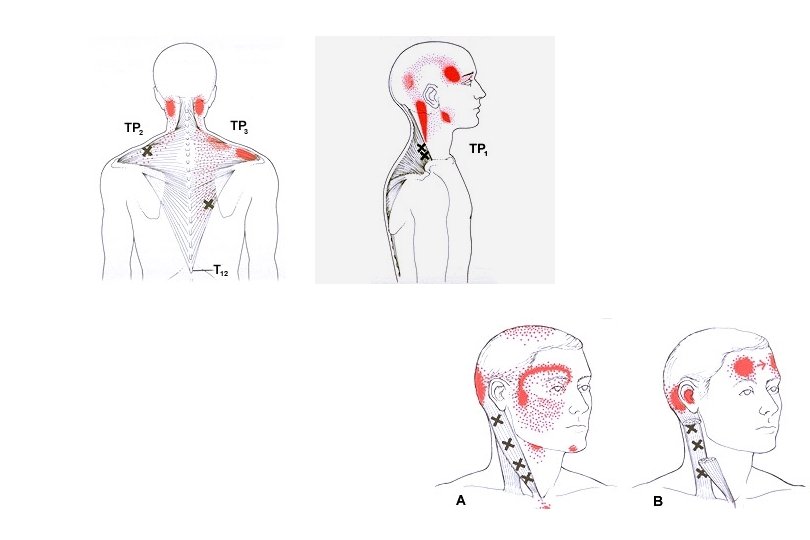
Symptoms of the 11 th n. involvement Torticollis (dystonia) Asymmetric shoulders Impaired arm elevation
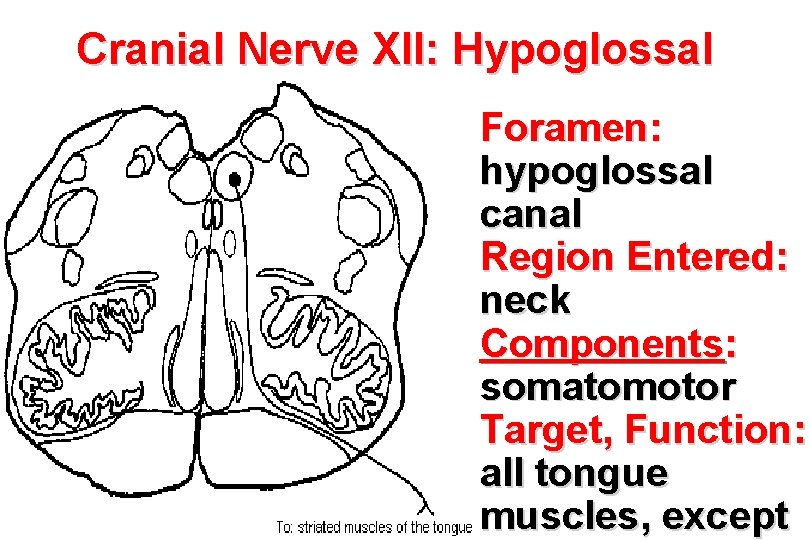
Cranial Nerve XII: Hypoglossal • Foramen: hypoglossal canal • Region Entered: neck • Components: somatomotor • Target, Function: all tongue muscles, except
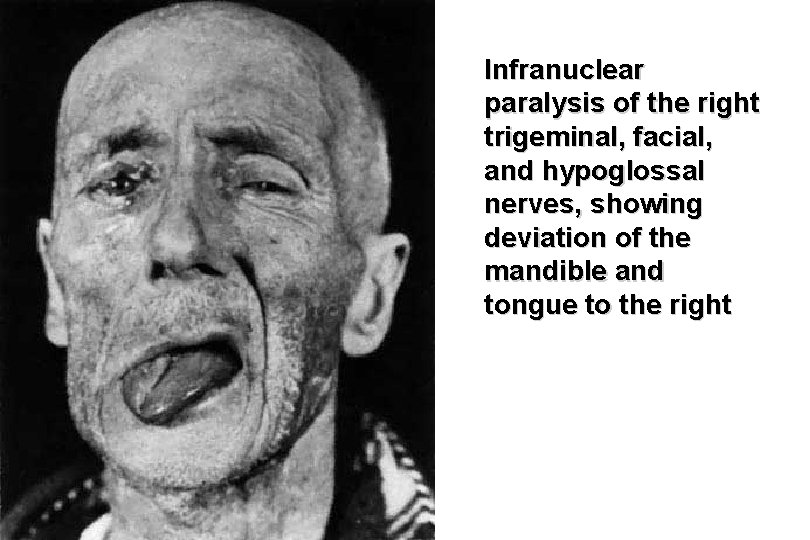
Infranuclear paralysis of the right trigeminal, facial, and hypoglossal nerves, showing deviation of the mandible and tongue to the right
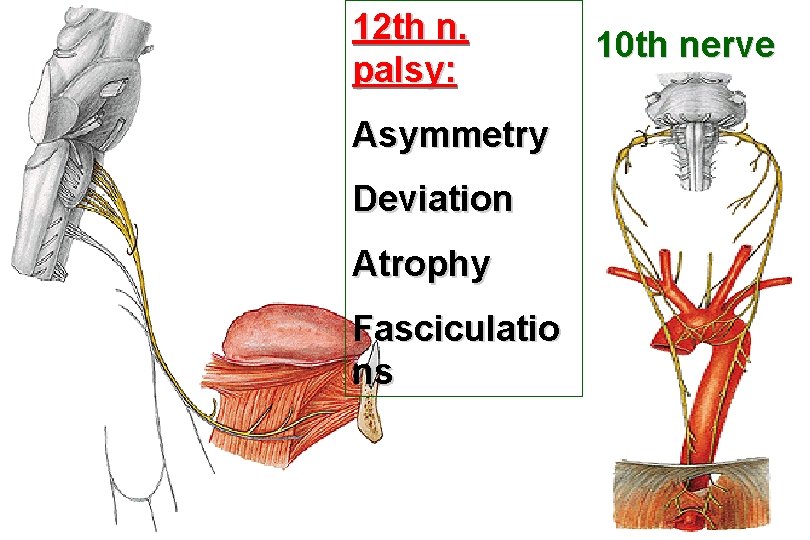
12 th n. palsy: Asymmetry Deviation Atrophy Fasciculatio ns 10 th nerve
Common Condition Affecting 9 th, 10 th & 12 th Nerve Function Bulbar § Motor neuron disease palsy § Cerebrovascular disease • Dysartria § Syringobulbia § Erosive tm of the skull base • Dysphagi a § Guillain-Barré syndrome § Recurrent laryngeal nerve • Dysphoni palsy a § Myastenia gravis • Aspiratio