Periodontal DiseaseInfection and Cardiovascular Disease Maurizio Trevisan MD
























- Slides: 61
Periodontal Disease/Infection and Cardiovascular Disease Maurizio Trevisan, MD MS
The size of the potential problem Ø Periodontitis l Leading cause of tooth loss • 49, 000 Americans have some form of “gum disease” Ø Cardiovascular Disease l Leading cause of death and disability • 13, 000 Americans have CHD • 5, 500, 000 Strokes
Is there a link ?
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
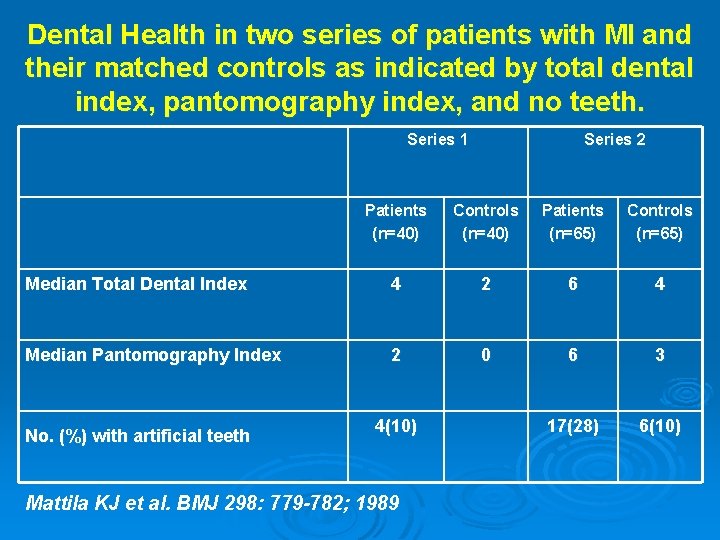
Dental Health in two series of patients with MI and their matched controls as indicated by total dental index, pantomography index, and no teeth. Series 1 Series 2 Patients (n=40) Controls (n=40) Patients (n=65) Controls (n=65) Median Total Dental Index 4 2 6 4 Median Pantomography Index 2 0 6 3 17(28) 6(10) No. (%) with artificial teeth 4(10) Mattila KJ et al. BMJ 298: 779 -782; 1989
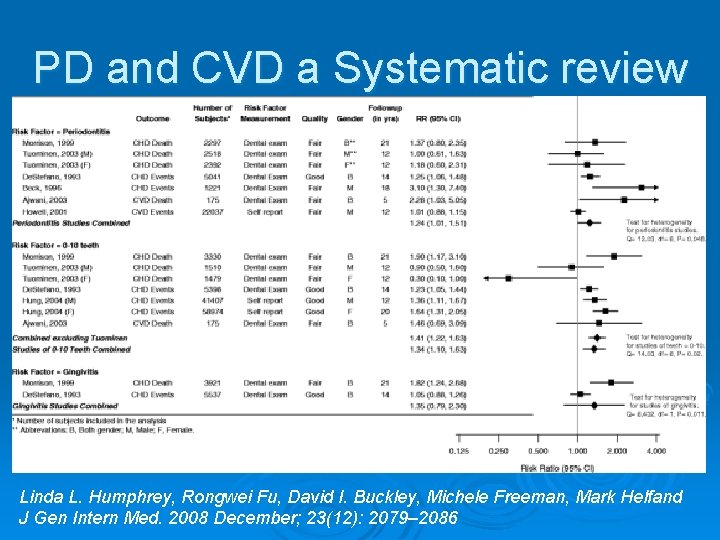
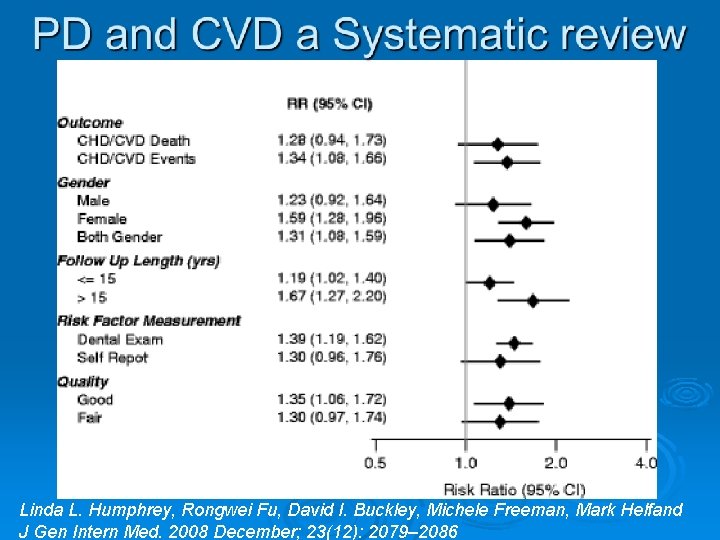
PD and CVD a Systematic review Linda L. Humphrey, Rongwei Fu, David I. Buckley, Michele Freeman, Mark Helfand J Gen Intern Med. 2008 December; 23(12): 2079– 2086
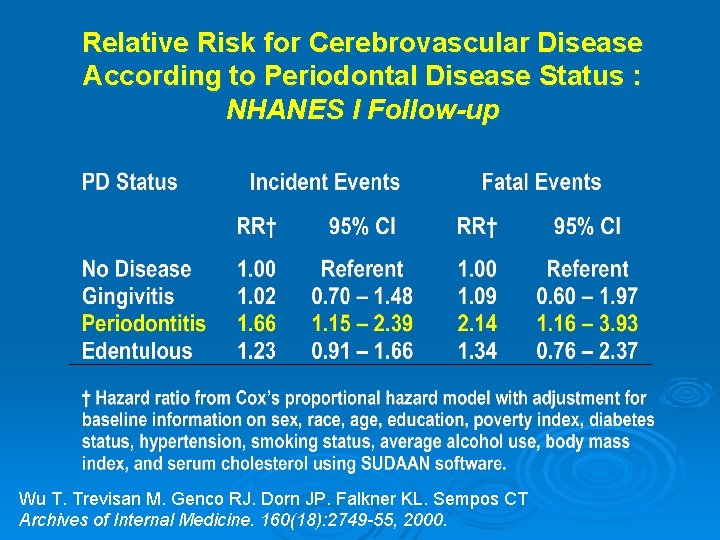
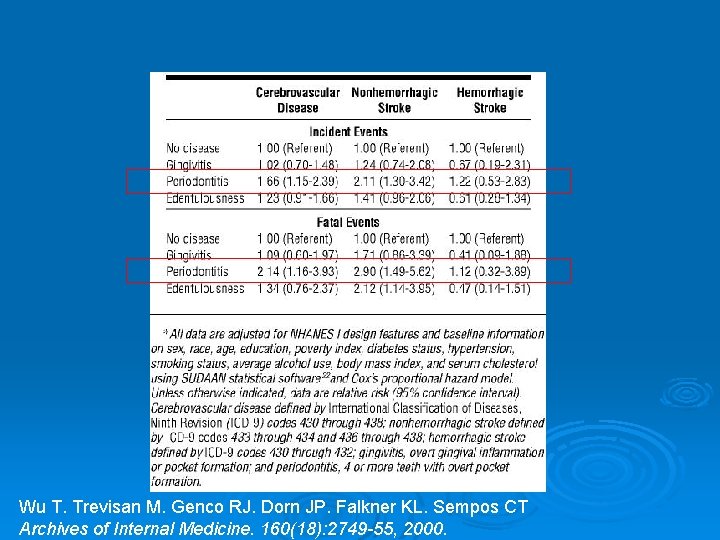
Relative Risk for Cerebrovascular Disease According to Periodontal Disease Status : NHANES I Follow-up Wu T. Trevisan M. Genco RJ. Dorn JP. Falkner KL. Sempos CT Archives of Internal Medicine. 160(18): 2749 -55, 2000.
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
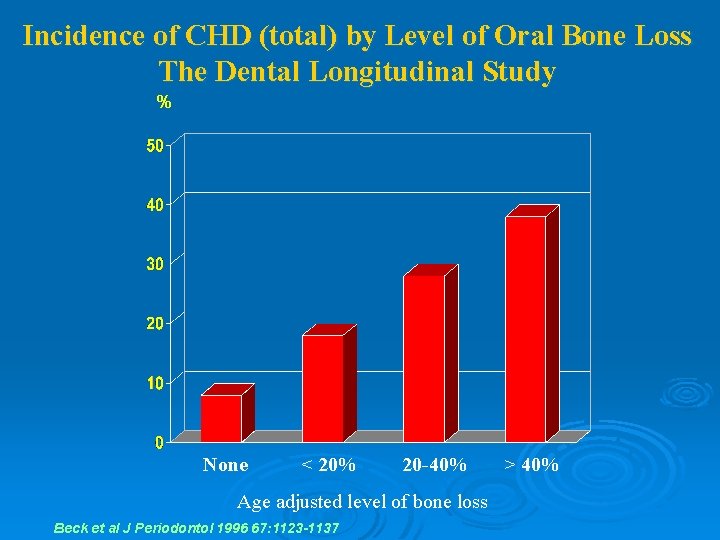
Incidence of CHD (total) by Level of Oral Bone Loss The Dental Longitudinal Study % None < 20% 20 -40% Age adjusted level of bone loss Beck et al J Periodontol 1996 67: 1123 -1137 > 40%
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
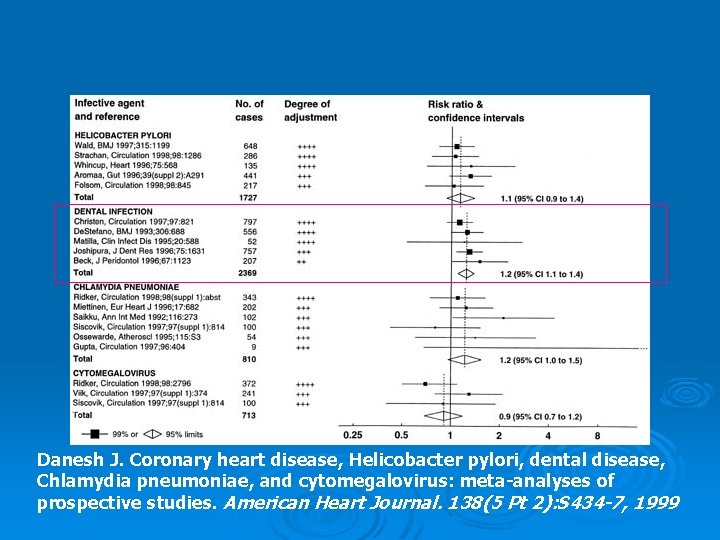
Danesh J. Coronary heart disease, Helicobacter pylori, dental disease, Chlamydia pneumoniae, and cytomegalovirus: meta-analyses of prospective studies. American Heart Journal. 138(5 Pt 2): S 434 -7, 1999
Periodontal Disease and CVD The role of gender
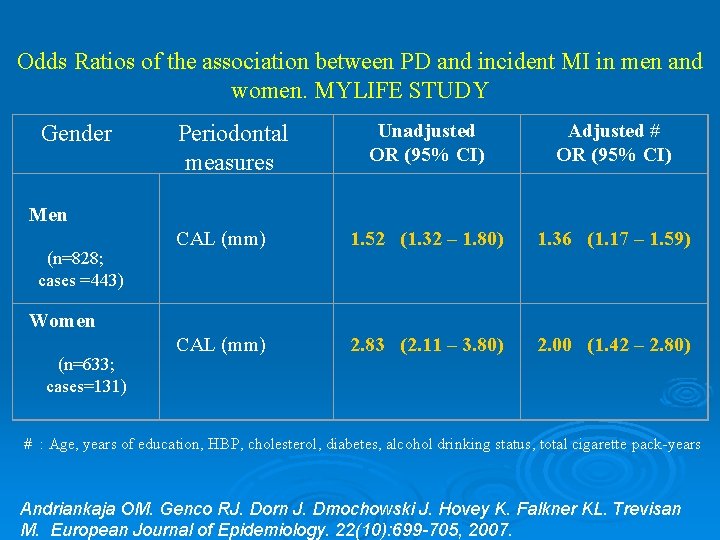
Odds Ratios of the association between PD and incident MI in men and women. MYLIFE STUDY Gender Periodontal measures Unadjusted OR (95% CI) Adjusted # OR (95% CI) 1. 36 (1. 17 – 1. 59) Men (n=828; cases =443) CAL (mm) 1. 52 (1. 32 – 1. 80) CAL (mm) 2. 83 (2. 11 – 3. 80) Women (n=633; cases=131) 2. 00 (1. 42 – 2. 80) # : Age, years of education, HBP, cholesterol, diabetes, alcohol drinking status, total cigarette pack-years Andriankaja OM. Genco RJ. Dorn J. Dmochowski J. Hovey K. Falkner KL. Trevisan M. European Journal of Epidemiology. 22(10): 699 -705, 2007.
Periodontal Disease and CVD The role of smoking
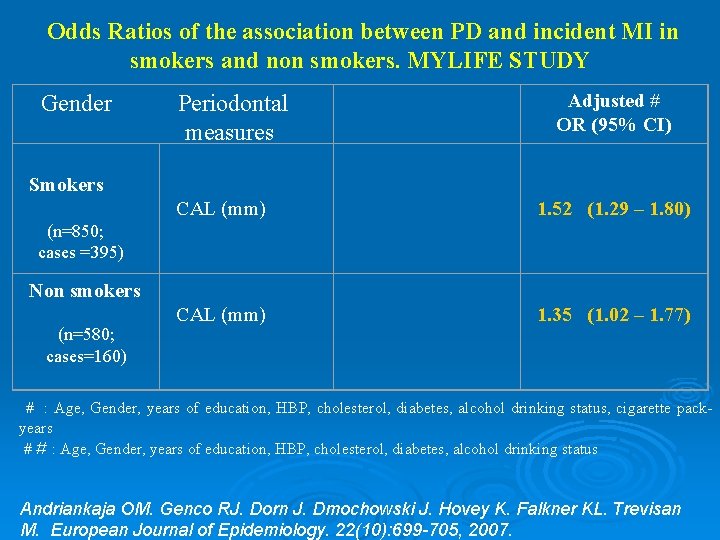
Odds Ratios of the association between PD and incident MI in smokers and non smokers. MYLIFE STUDY Adjusted # OR (95% CI) Gender Periodontal measures Smokers CAL (mm) (n=850; cases =395) 1. 52 (1. 29 – 1. 80) Non smokers (n=580; cases=160) CAL (mm) 1. 35 (1. 02 – 1. 77) # : Age, Gender, years of education, HBP, cholesterol, diabetes, alcohol drinking status, cigarette packyears # # : Age, Gender, years of education, HBP, cholesterol, diabetes, alcohol drinking status Andriankaja OM. Genco RJ. Dorn J. Dmochowski J. Hovey K. Falkner KL. Trevisan M. European Journal of Epidemiology. 22(10): 699 -705, 2007.
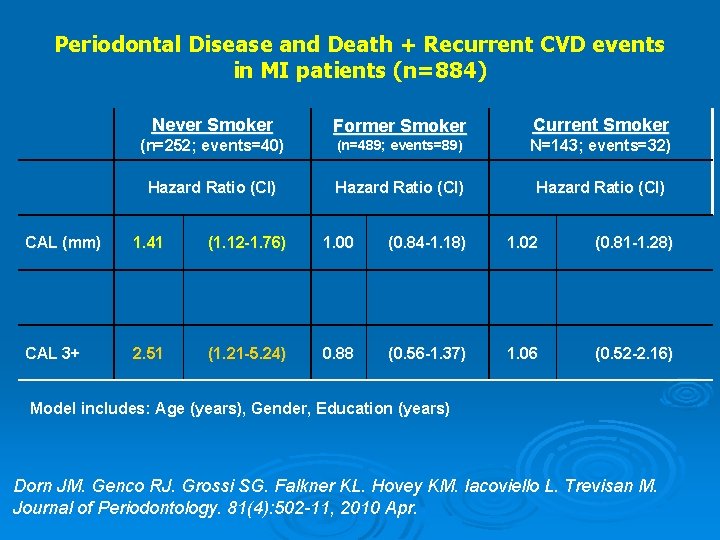
Periodontal Disease and Death + Recurrent CVD events in MI patients (n=884) Never Smoker (n=252; events=40) Hazard Ratio (CI) Former Smoker Current Smoker (n=489; events=89) N=143; events=32) Hazard Ratio (CI) CAL (mm) 1. 41 (1. 12 -1. 76) 1. 00 (0. 84 -1. 18) 1. 02 (0. 81 -1. 28) CAL 3+ 2. 51 (1. 21 -5. 24) 0. 88 (0. 56 -1. 37) 1. 06 (0. 52 -2. 16) Model includes: Age (years), Gender, Education (years) Dorn JM. Genco RJ. Grossi SG. Falkner KL. Hovey KM. Iacoviello L. Trevisan M. Journal of Periodontology. 81(4): 502 -11, 2010 Apr.
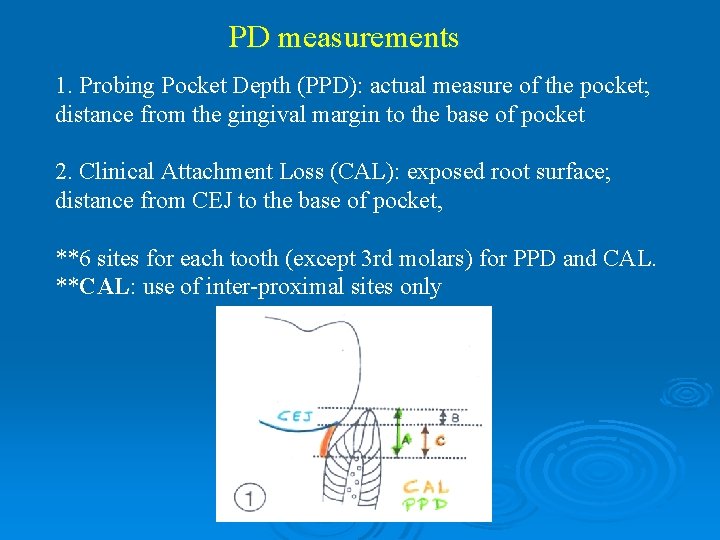
PD measurements 1. Probing Pocket Depth (PPD): actual measure of the pocket; distance from the gingival margin to the base of pocket 2. Clinical Attachment Loss (CAL): exposed root surface; distance from CEJ to the base of pocket, **6 sites for each tooth (except 3 rd molars) for PPD and CAL. **CAL: use of inter-proximal sites only
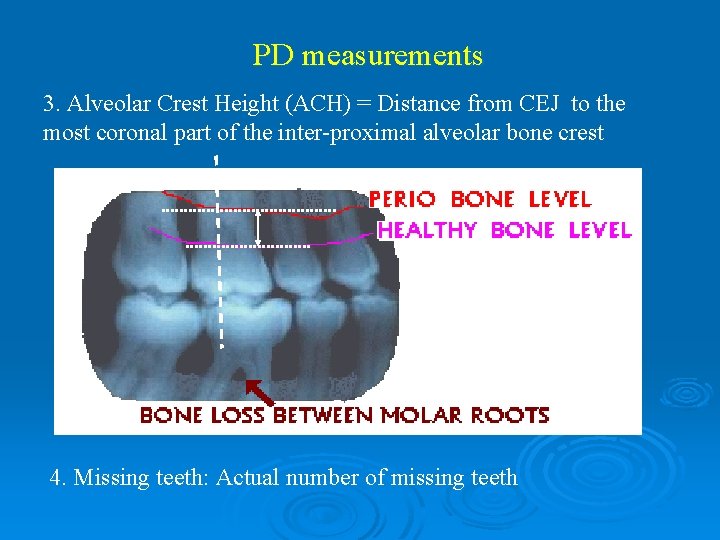
PD measurements 3. Alveolar Crest Height (ACH) = Distance from CEJ to the most coronal part of the inter-proximal alveolar bone crest 4. Missing teeth: Actual number of missing teeth
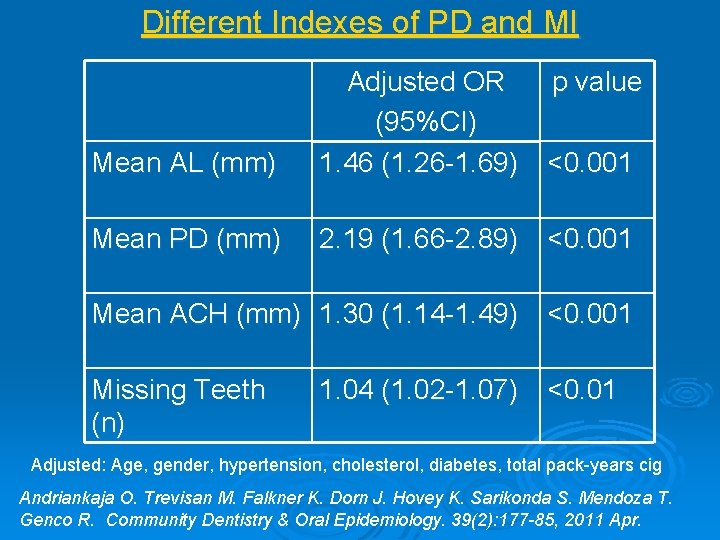
Different Indexes of PD and MI Mean AL (mm) Adjusted OR p value (95%CI) 1. 46 (1. 26 -1. 69) <0. 001 Mean PD (mm) 2. 19 (1. 66 -2. 89) <0. 001 Mean ACH (mm) 1. 30 (1. 14 -1. 49) <0. 001 Missing Teeth (n) 1. 04 (1. 02 -1. 07) <0. 01 Adjusted: Age, gender, hypertension, cholesterol, diabetes, total pack-years cig Andriankaja O. Trevisan M. Falkner K. Dorn J. Hovey K. Sarikonda S. Mendoza T. Genco R. Community Dentistry & Oral Epidemiology. 39(2): 177 -85, 2011 Apr.
Linda L. Humphrey, Rongwei Fu, David I. Buckley, Michele Freeman, Mark Helfand J Gen Intern Med. 2008 December; 23(12): 2079– 2086
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
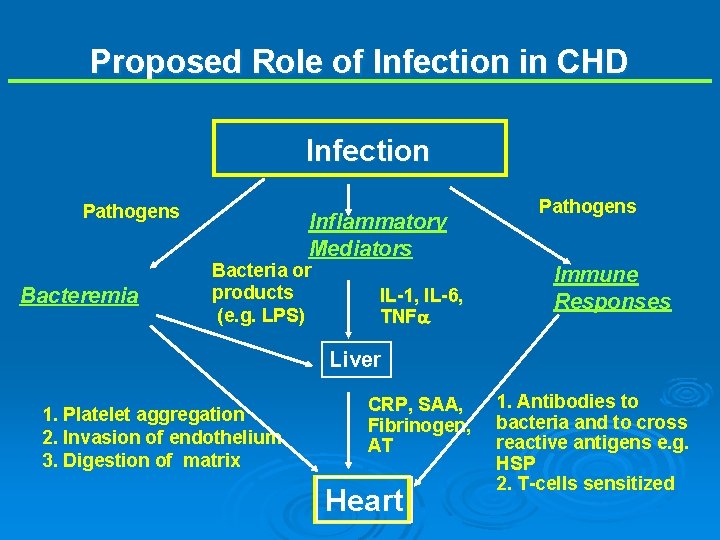
Proposed Role of Infection in CHD Infection Pathogens Bacteremia Inflammatory Mediators Bacteria or products (e. g. LPS) IL-1, IL-6, TNF Pathogens Immune Responses Liver 1. Platelet aggregation 2. Invasion of endothelium 3. Digestion of matrix CRP, SAA, Fibrinogen, AT Heart 1. Antibodies to bacteria and to cross reactive antigens e. g. HSP 2. T-cells sensitized
Periodontal Infection and CVD Ø Specific mechanisms linked to specific agent Ø General mechanisms ?
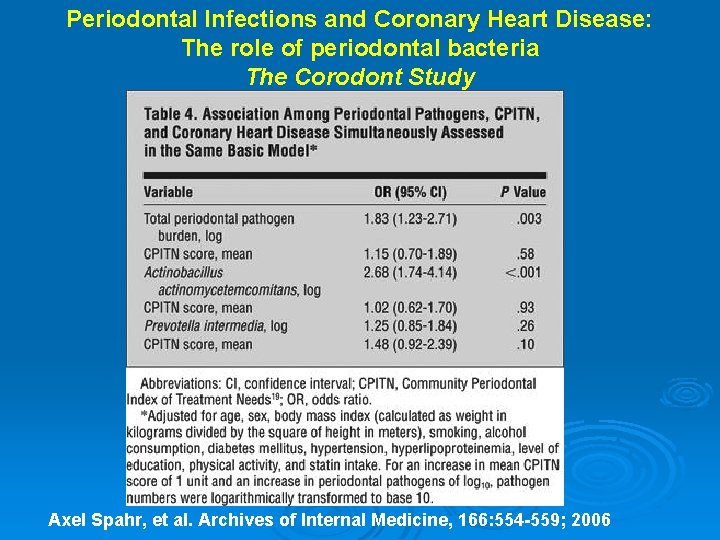
Periodontal Infections and Coronary Heart Disease: The role of periodontal bacteria The Corodont Study Axel Spahr, et al. Archives of Internal Medicine, 166: 554 -559; 2006
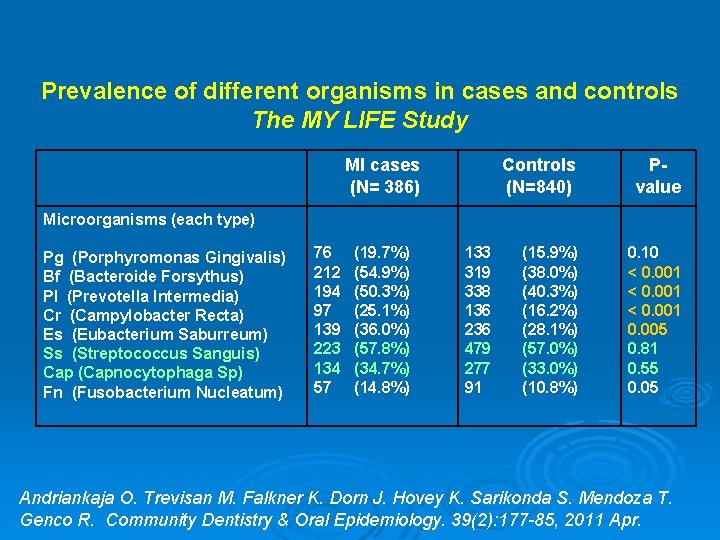
Prevalence of different organisms in cases and controls The MY LIFE Study MI cases (N= 386) Controls (N=840) Pvalue (15. 9%) (38. 0%) (40. 3%) (16. 2%) (28. 1%) (57. 0%) (33. 0%) (10. 8%) 0. 10 < 0. 001 0. 005 0. 81 0. 55 0. 05 Microorganisms (each type) Pg (Porphyromonas Gingivalis) Bf (Bacteroide Forsythus) PI (Prevotella Intermedia) Cr (Campylobacter Recta) Es (Eubacterium Saburreum) Ss (Streptococcus Sanguis) Cap (Capnocytophaga Sp) Fn (Fusobacterium Nucleatum) 76 212 194 97 139 223 134 57 (19. 7%) (54. 9%) (50. 3%) (25. 1%) (36. 0%) (57. 8%) (34. 7%) (14. 8%) 133 319 338 136 236 479 277 91 Andriankaja O. Trevisan M. Falkner K. Dorn J. Hovey K. Sarikonda S. Mendoza T. Genco R. Community Dentistry & Oral Epidemiology. 39(2): 177 -85, 2011 Apr.
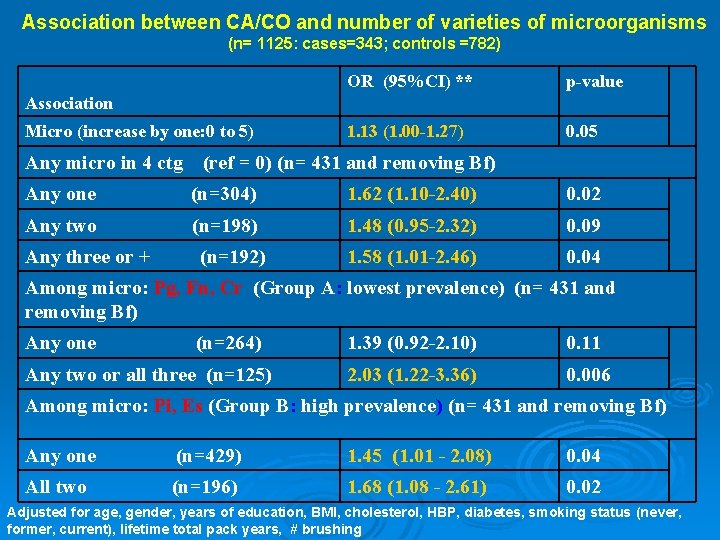
Association between CA/CO and number of varieties of microorganisms (n= 1125: cases=343; controls =782) OR (95%CI) ** p-value 1. 13 (1. 00 -1. 27) 0. 05 Association Micro (increase by one: 0 to 5) Any micro in 4 ctg (ref = 0) (n= 431 and removing Bf) Any one (n=304) 1. 62 (1. 10 -2. 40) 0. 02 Any two (n=198) 1. 48 (0. 95 -2. 32) 0. 09 Any three or + (n=192) 1. 58 (1. 01 -2. 46) 0. 04 Among micro: Pg, Fn, Cr (Group A: lowest prevalence) (n= 431 and removing Bf) Any one (n=264) 1. 39 (0. 92 -2. 10) 0. 11 Any two or all three (n=125) 2. 03 (1. 22 -3. 36) 0. 006 Among micro: Pi, Es (Group B: high prevalence) (n= 431 and removing Bf) Any one (n=429) 1. 45 (1. 01 - 2. 08) 0. 04 All two (n=196) 1. 68 (1. 08 - 2. 61) 0. 02 Adjusted for age, gender, years of education, BMI, cholesterol, HBP, diabetes, smoking status (never, former, current), lifetime total pack years, # brushing
Periodontal Infection and CVD Ø Inflammation Pathway l C Reactive Protein
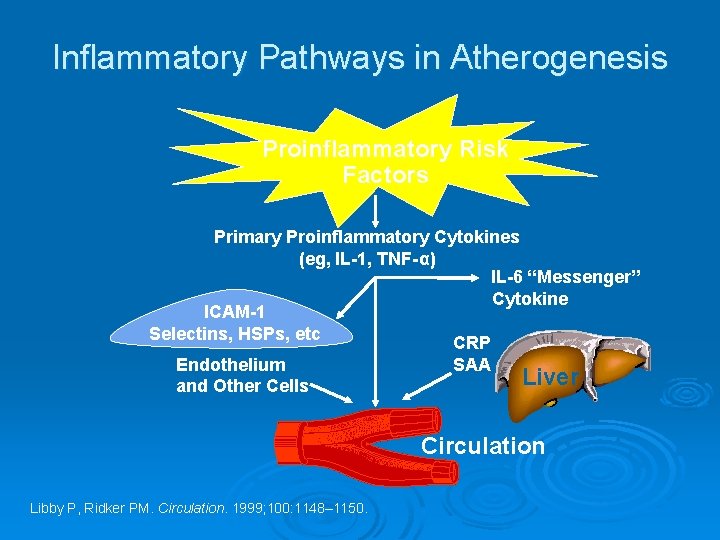
Inflammatory Pathways in Atherogenesis Proinflammatory Risk Factors Primary Proinflammatory Cytokines (eg, IL-1, TNF-α) IL-6 “Messenger” Cytokine ICAM-1 Selectins, HSPs, etc CRP SAA Endothelium Liver and Other Cells Circulation Libby P, Ridker PM. Circulation. 1999; 100: 1148– 1150.
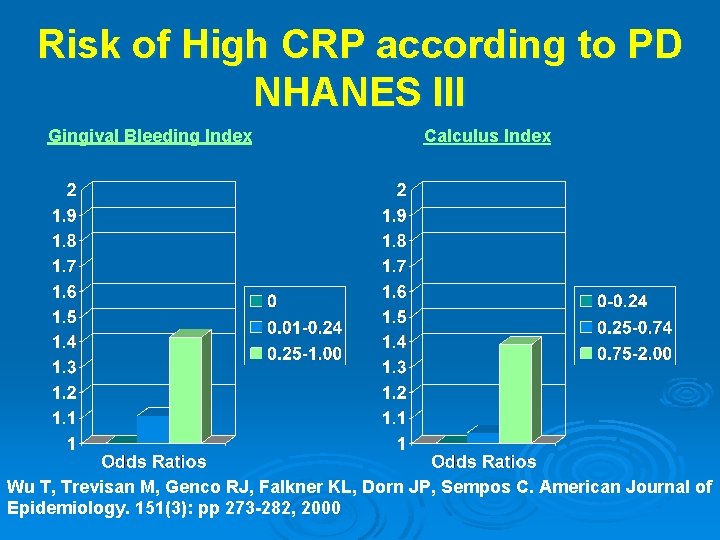
Risk of High CRP according to PD NHANES III Gingival Bleeding Index Calculus Index Wu T, Trevisan M, Genco RJ, Falkner KL, Dorn JP, Sempos C. American Journal of Epidemiology. 151(3): pp 273 -282, 2000
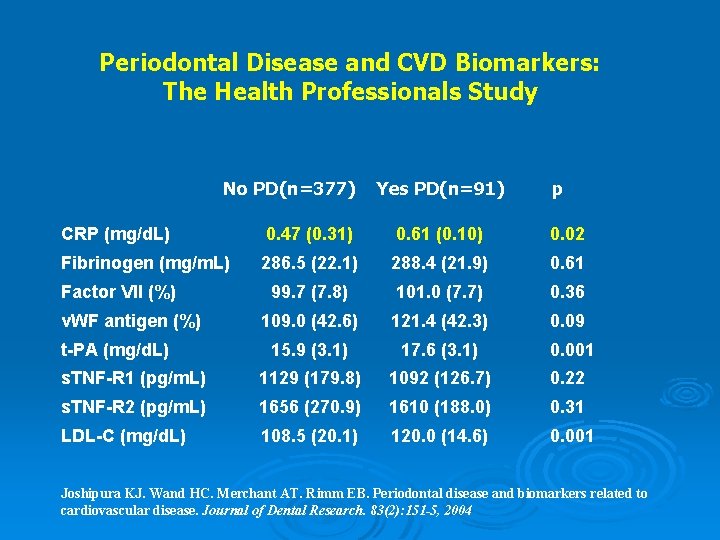
Periodontal Disease and CVD Biomarkers: The Health Professionals Study No PD(n=377) Yes PD(n=91) p CRP (mg/d. L) 0. 47 (0. 31) 0. 61 (0. 10) 0. 02 Fibrinogen (mg/m. L) 286. 5 (22. 1) 288. 4 (21. 9) 0. 61 99. 7 (7. 8) 101. 0 (7. 7) 0. 36 109. 0 (42. 6) 121. 4 (42. 3) 0. 09 15. 9 (3. 1) 17. 6 (3. 1) 0. 001 s. TNF-R 1 (pg/m. L) 1129 (179. 8) 1092 (126. 7) 0. 22 s. TNF-R 2 (pg/m. L) 1656 (270. 9) 1610 (188. 0) 0. 31 LDL-C (mg/d. L) 108. 5 (20. 1) 120. 0 (14. 6) 0. 001 Factor VII (%) v. WF antigen (%) t-PA (mg/d. L) Joshipura KJ. Wand HC. Merchant AT. Rimm EB. Periodontal disease and biomarkers related to cardiovascular disease. Journal of Dental Research. 83(2): 151 -5, 2004
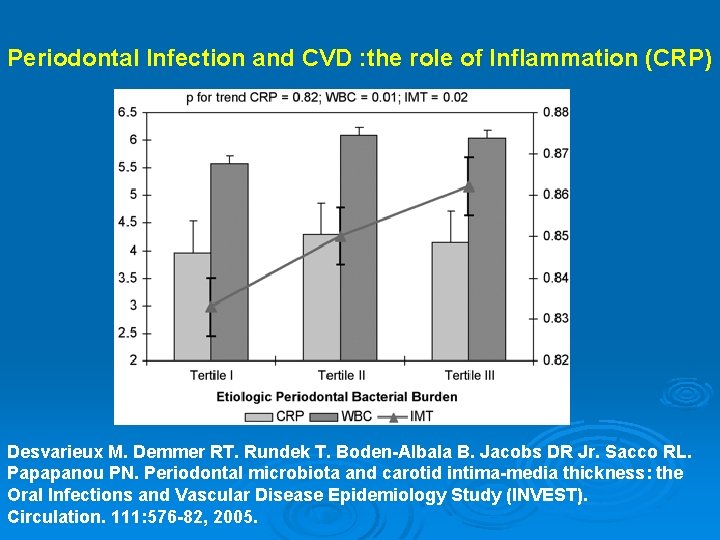
Periodontal Infection and CVD : the role of Inflammation (CRP) Desvarieux M. Demmer RT. Rundek T. Boden-Albala B. Jacobs DR Jr. Sacco RL. Papapanou PN. Periodontal microbiota and carotid intima-media thickness: the Oral Infections and Vascular Disease Epidemiology Study (INVEST). Circulation. 111: 576 -82, 2005.
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
Wu T. Trevisan M. Genco RJ. Dorn JP. Falkner KL. Sempos CT Archives of Internal Medicine. 160(18): 2749 -55, 2000.
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence 9: Analogy
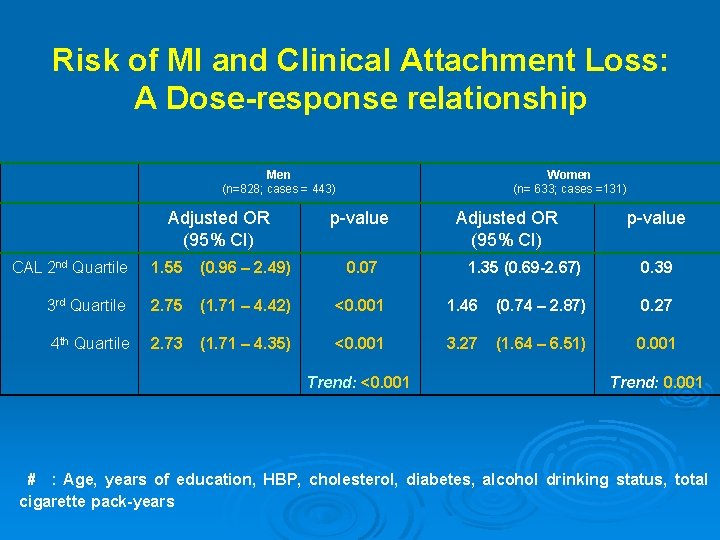
Risk of MI and Clinical Attachment Loss: A Dose-response relationship Men (n=828; cases = 443) Adjusted OR (95% CI) Women (n= 633; cases =131) p-value Adjusted OR (95% CI) CAL 2 nd Quartile 1. 55 (0. 96 – 2. 49) 0. 07 3 rd Quartile 2. 75 (1. 71 – 4. 42) <0. 001 1. 46 (0. 74 – 2. 87) 0. 27 4 th Quartile 2. 73 (1. 71 – 4. 35) <0. 001 3. 27 (1. 64 – 6. 51) 0. 001 Trend: <0. 001 1. 35 (0. 69 -2. 67) p-value 0. 39 Trend: 0. 001 # : Age, years of education, HBP, cholesterol, diabetes, alcohol drinking status, total cigarette pack-years
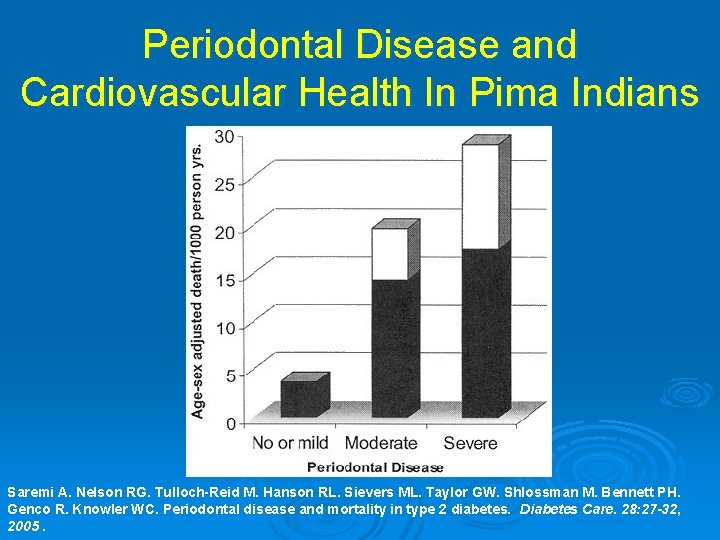
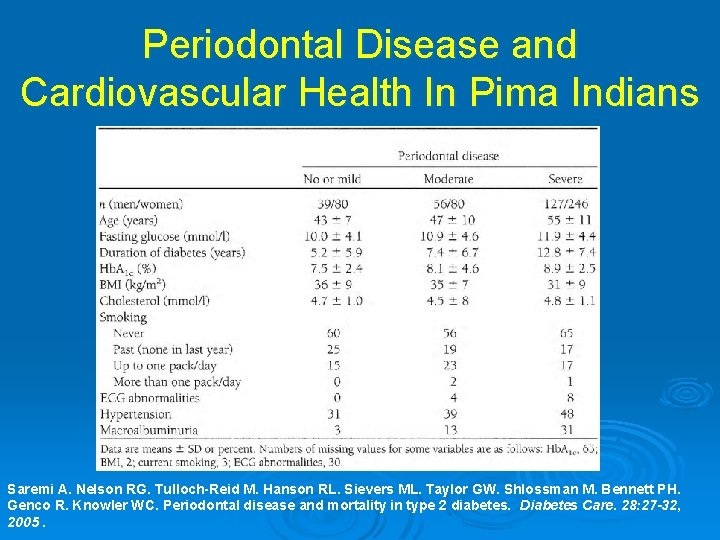
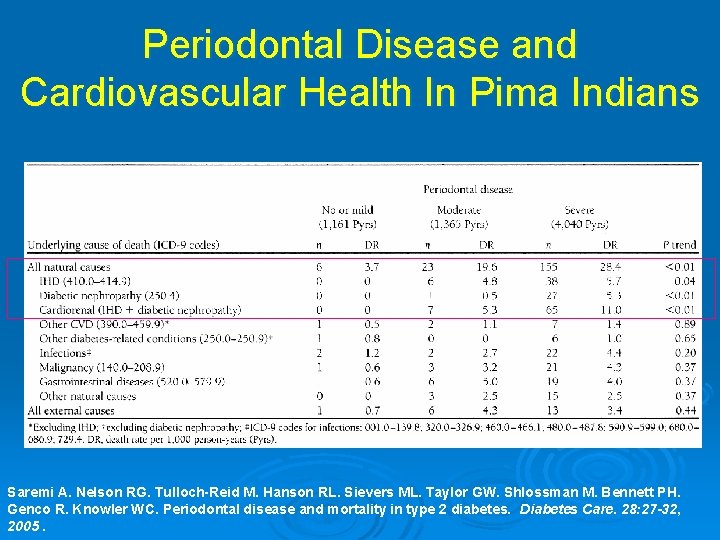
Periodontal Disease and Cardiovascular Health In Pima Indians Saremi A. Nelson RG. Tulloch-Reid M. Hanson RL. Sievers ML. Taylor GW. Shlossman M. Bennett PH. Genco R. Knowler WC. Periodontal disease and mortality in type 2 diabetes. Diabetes Care. 28: 27 -32, 2005.
Is there a link? The Bradford Hill Criteria 1: Strength of Association 2: Temporality 3: Consistency 4: Theoretical Plausibility 5: Coherence 6: Specificity in the causes 7: Dose Response Relationship 8: Experimental Evidence
Periodontal Infection and CVD Ø Periodontal Intervention Ø Antimicrobial Periodontal Treatment Ø Tooth extraction (full mouth) Prevent Cardiovascular Events ? ? Improve CVD surrogate endpoints ? ?
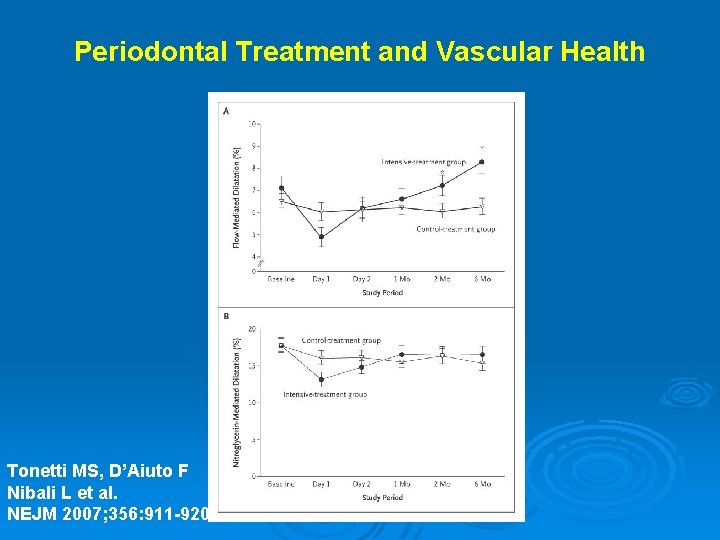
Periodontal Treatment and Vascular Health Tonetti MS, D’Aiuto F Nibali L et al. NEJM 2007; 356: 911 -920
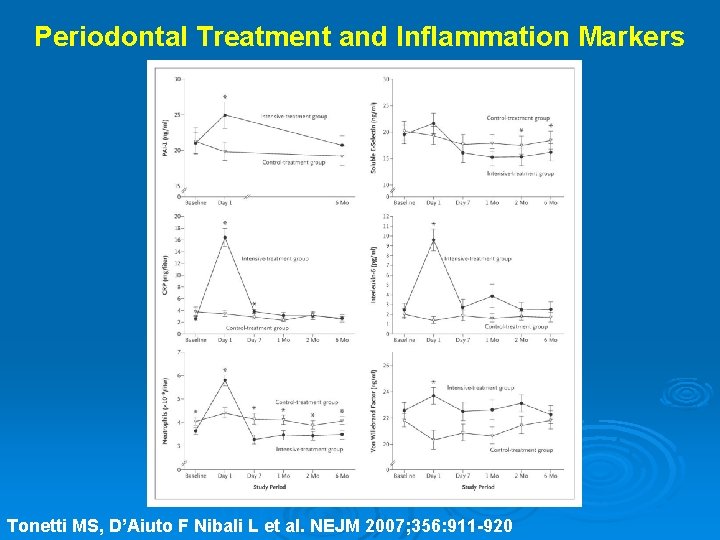
Periodontal Treatment and Inflammation Markers Tonetti MS, D’Aiuto F Nibali L et al. NEJM 2007; 356: 911 -920
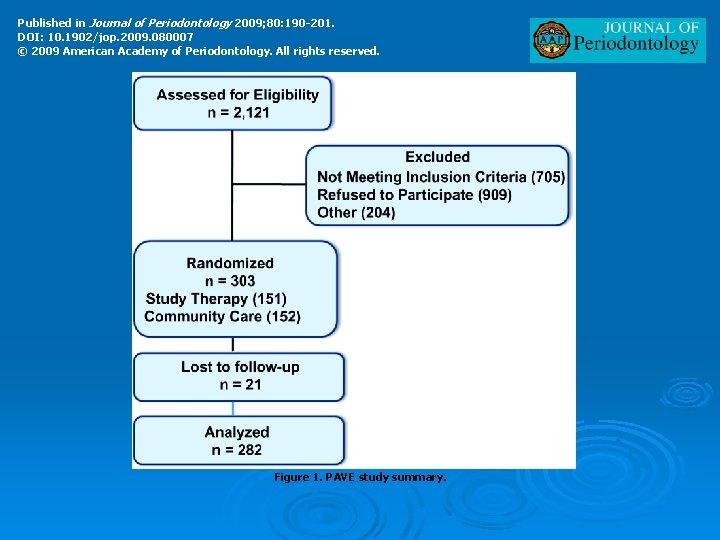
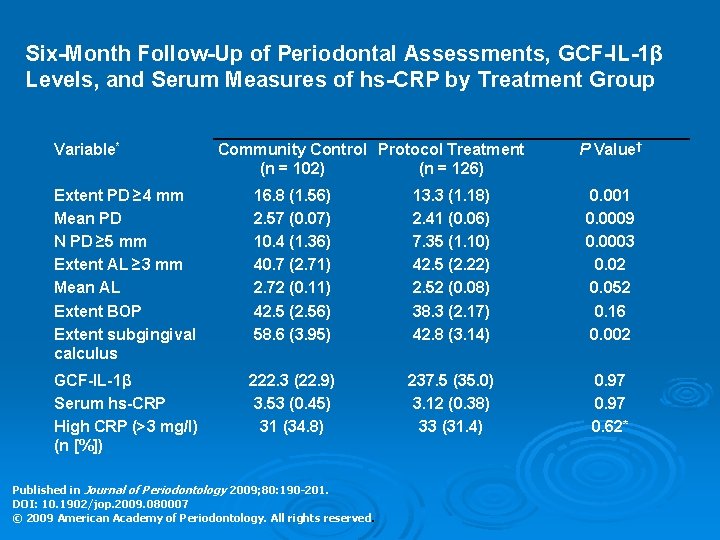
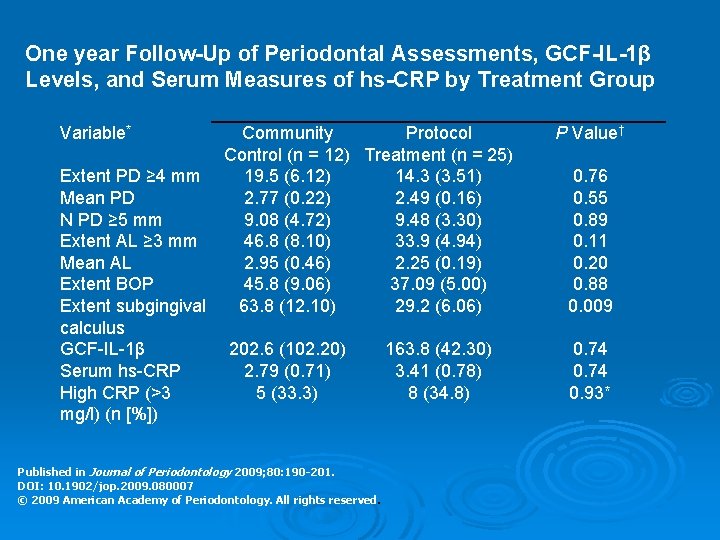
PAVE Study The Periodontitis and Vascular Events (PAVE) pilot study was conducted to investigate the feasibility of a randomized secondary prevention trial to test whether treatment of periodontal disease reduces the risk for cardiovascular disease.
PAVE Study Five clinical centers recruited participants with documented coronary heart disease and met study criteria for periodontal disease. Eligible participants were randomized to receive periodontal therapy provided by the study or community dental care. Follow-up telephone calls and clinic visits were planned to alternate at 3 -month intervals after randomization, with all participants followed until at least the 6 -month clinic visit. Participants were followed for adverse events and periodontal and cardiovascular outcomes.
Published in Journal of Periodontology 2009; 80: 190 -201. DOI: 10. 1902/jop. 2009. 080007 © 2009 American Academy of Periodontology. All rights reserved. Figure 1. PAVE study summary.
Six-Month Follow-Up of Periodontal Assessments, GCF-IL-1β Levels, and Serum Measures of hs-CRP by Treatment Group Variable* Community Control Protocol Treatment (n = 102) (n = 126) P Value† Extent PD ≥ 4 mm Mean PD N PD ≥ 5 mm Extent AL ≥ 3 mm Mean AL Extent BOP Extent subgingival calculus 16. 8 (1. 56) 2. 57 (0. 07) 10. 4 (1. 36) 40. 7 (2. 71) 2. 72 (0. 11) 42. 5 (2. 56) 58. 6 (3. 95) 13. 3 (1. 18) 2. 41 (0. 06) 7. 35 (1. 10) 42. 5 (2. 22) 2. 52 (0. 08) 38. 3 (2. 17) 42. 8 (3. 14) 0. 001 0. 0009 0. 0003 0. 02 0. 052 0. 16 0. 002 GCF-IL-1β Serum hs-CRP High CRP (>3 mg/l) (n [%]) 222. 3 (22. 9) 3. 53 (0. 45) 31 (34. 8) 237. 5 (35. 0) 3. 12 (0. 38) 33 (31. 4) 0. 97 0. 62* Published in Journal of Periodontology 2009; 80: 190 -201. DOI: 10. 1902/jop. 2009. 080007 © 2009 American Academy of Periodontology. All rights reserved.
One year Follow-Up of Periodontal Assessments, GCF-IL-1β Levels, and Serum Measures of hs-CRP by Treatment Group Variable* Extent PD ≥ 4 mm Mean PD N PD ≥ 5 mm Extent AL ≥ 3 mm Mean AL Extent BOP Extent subgingival calculus GCF-IL-1β Serum hs-CRP High CRP (>3 mg/l) (n [%]) Community Protocol Control (n = 12) Treatment (n = 25) 19. 5 (6. 12) 14. 3 (3. 51) 2. 77 (0. 22) 2. 49 (0. 16) 9. 08 (4. 72) 9. 48 (3. 30) 46. 8 (8. 10) 33. 9 (4. 94) 2. 95 (0. 46) 2. 25 (0. 19) 45. 8 (9. 06) 37. 09 (5. 00) 63. 8 (12. 10) 29. 2 (6. 06) 202. 6 (102. 20) 2. 79 (0. 71) 5 (33. 3) Published in Journal of Periodontology 2009; 80: 190 -201. DOI: 10. 1902/jop. 2009. 080007 © 2009 American Academy of Periodontology. All rights reserved. 163. 8 (42. 30) 3. 41 (0. 78) 8 (34. 8) P Value† 0. 76 0. 55 0. 89 0. 11 0. 20 0. 88 0. 009 0. 74 0. 93*
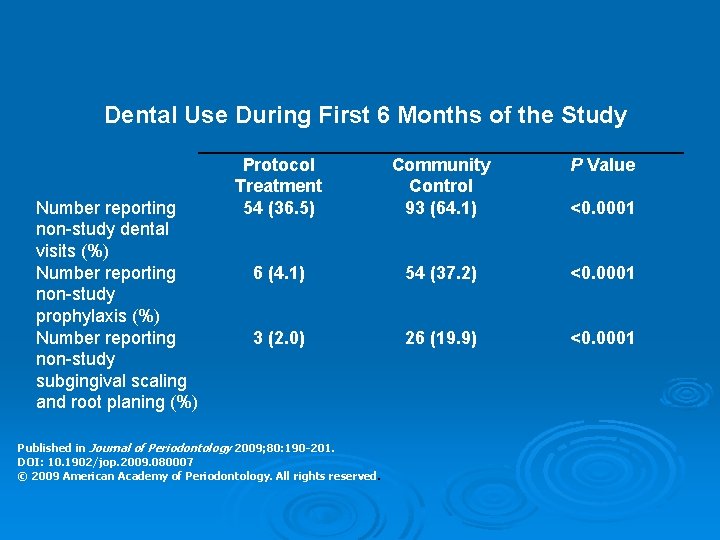
Dental Use During First 6 Months of the Study Number reporting non-study dental visits (%) Number reporting non-study prophylaxis (%) Number reporting non-study subgingival scaling and root planing (%) Protocol Treatment 54 (36. 5) Community Control 93 (64. 1) <0. 0001 6 (4. 1) 54 (37. 2) <0. 0001 3 (2. 0) 26 (19. 9) <0. 0001 Published in Journal of Periodontology 2009; 80: 190 -201. DOI: 10. 1902/jop. 2009. 080007 © 2009 American Academy of Periodontology. All rights reserved. P Value
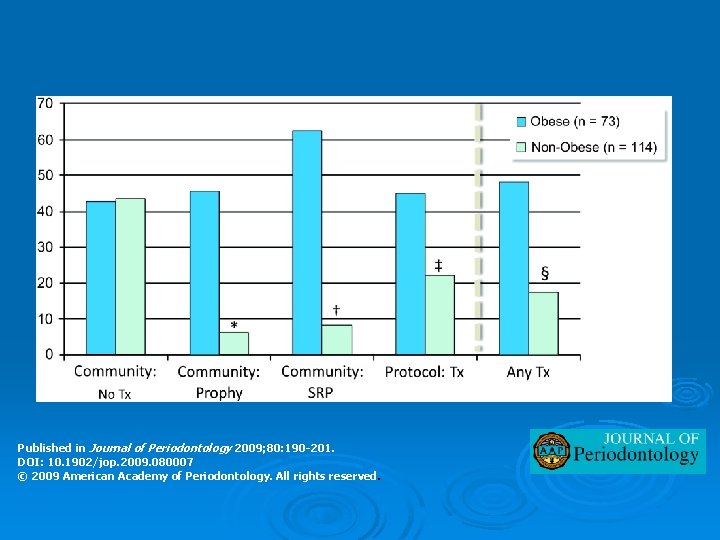
Published in Journal of Periodontology 2009; 80: 190 -201. DOI: 10. 1902/jop. 2009. 080007 © 2009 American Academy of Periodontology. All rights reserved.
Periodontal Infection and CVD Ø CRP (and possibly inflammation) is not the whole story Ø There is need to better understand the mechanisms linking PD to CVD
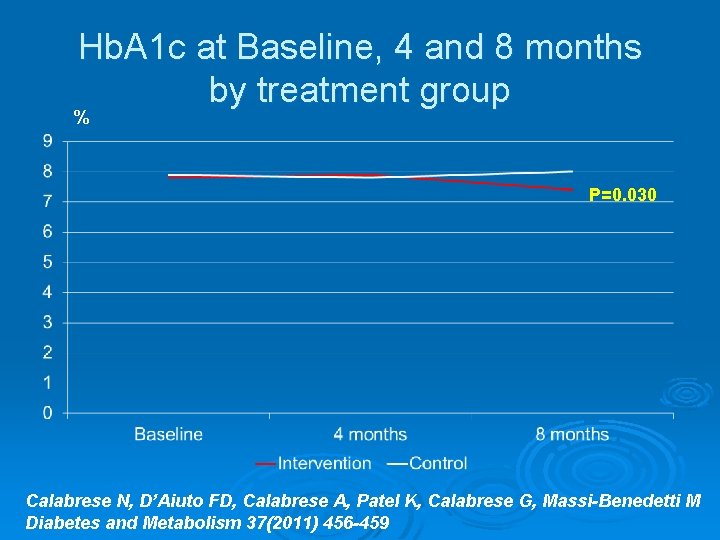
Hb. A 1 c at Baseline, 4 and 8 months by treatment group % P=0. 030 Calabrese N, D’Aiuto FD, Calabrese A, Patel K, Calabrese G, Massi-Benedetti M Diabetes and Metabolism 37(2011) 456 -459
Investigate the role of Genes and Environment in the link between Periodontal Disease (PD) and Myocardial infarction (MI). 1381 Ø In healthy controls we will evaluate the association between genetic and biochemical markers of pathophysiological pathways (inflammation and inflammation-mediated hemostasis/thrombosis) involved in the etiology of both PD and MI. Ø In the case-control study ( 953 cases of MI and 1381 healthy controls) we will evaluate the potential role of genetic markers and environmental exposures (smoking and alcohol use) of these pathways in modulating the observed association between PD and MI. Ø We will extend the follow-up of the 953 MI cases to evaluate whether these genetic markers and the environmental exposures can modulate the longitudinal association between periodontal disease and secondary cardiovascular events.
The final complex questions we want to answer by combining biological, epidemiological and computational approaches are: o o o Is the association between periodontal disease and myocardial infarction mediated by the genetic control of metabolic pathways involved in the pathogenesis of both diseases? Are there haplotype patterns that can predict the development of myocardial infarction in subjects with periodontal disease? Is it possible to develop a model of haplotype prediction that takes into consideration environmental factors and quantitative phenotypes in addition to genetic characteristics?
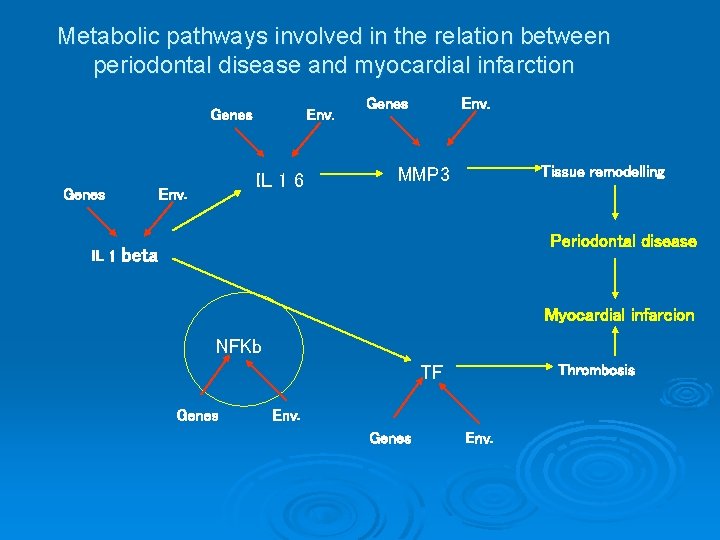
Metabolic pathways involved in the relation between periodontal disease and myocardial infarction Genes IL 1 Env. IL 1 6 Env. Genes Env. Tissue remodelling MMP 3 Periodontal disease beta Myocardial infarcion NFKb Thrombosis TF Genes Env.
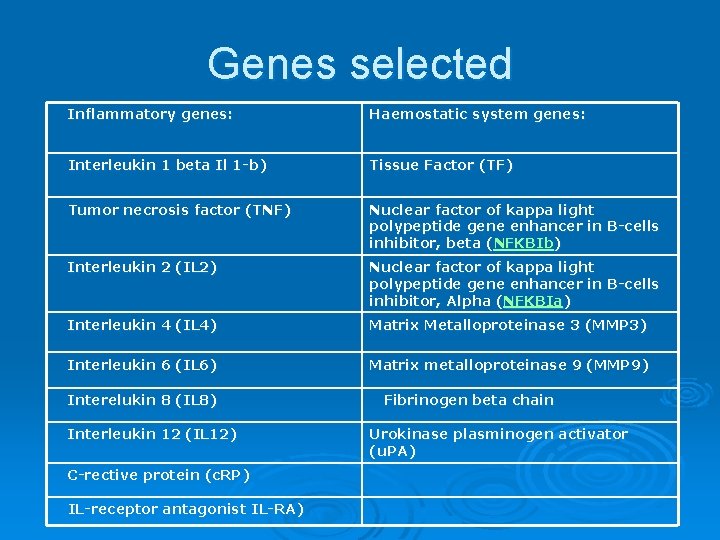
Genes selected Inflammatory genes: Haemostatic system genes: Interleukin 1 beta Il 1 -b) Tissue Factor (TF) Tumor necrosis factor (TNF) Nuclear factor of kappa light polypeptide gene enhancer in B-cells inhibitor, beta (NFKBIb) Interleukin 2 (IL 2) Nuclear factor of kappa light polypeptide gene enhancer in B-cells inhibitor, Alpha (NFKBIa) Interleukin 4 (IL 4) Matrix Metalloproteinase 3 (MMP 3) Interleukin 6 (IL 6) Matrix metalloproteinase 9 (MMP 9) Interelukin 8 (IL 8) Interleukin 12 (IL 12) C-rective protein (c. RP) IL-receptor antagonist IL-RA) Fibrinogen beta chain Urokinase plasminogen activator (u. PA)
Periodontal Disease and CVD Ø The association has important potential Public Health implications Ø The observed association satisfies many of the Bradford Hill criteria for causality Ø Missing definite experimental evidence Ø Need to better evaluate the potential mechanisms linking PD to CVD
9294914
Periodontal Disease and Cardiovascular Health In Pima Indians Saremi A. Nelson RG. Tulloch-Reid M. Hanson RL. Sievers ML. Taylor GW. Shlossman M. Bennett PH. Genco R. Knowler WC. Periodontal disease and mortality in type 2 diabetes. Diabetes Care. 28: 27 -32, 2005.
Periodontal Disease and Cardiovascular Health In Pima Indians Saremi A. Nelson RG. Tulloch-Reid M. Hanson RL. Sievers ML. Taylor GW. Shlossman M. Bennett PH. Genco R. Knowler WC. Periodontal disease and mortality in type 2 diabetes. Diabetes Care. 28: 27 -32, 2005.
Smoking history ü 3 categories: * Non-smokers - never smoked in the entire life - smoked < 100 cig. (~5 packs) in the entire life * Former smokers: smoked cig ≥ 100 and quit smoking * Current smokers : smoked cig ≥ 100 and still smoking at the time of interview ü 2 categories [non-smokers; smokers (former and current)] ü Duration and intensity of exposure: * Total pack-years of cigarette smoking * Number of years since Pts had quit smoking