Ascites Associate Professor Dr Meltem Ergun Yeditepe University











- Slides: 51
Ascites Associate Professor Dr Meltem Ergun Yeditepe University Department of Gastroenterology
Points of this lecture What is ascites? Etiologies of ascites Clinical presentations Pyhsical examination findings Laboratory tests Prognosis Spontaneous bacterial peritonitis
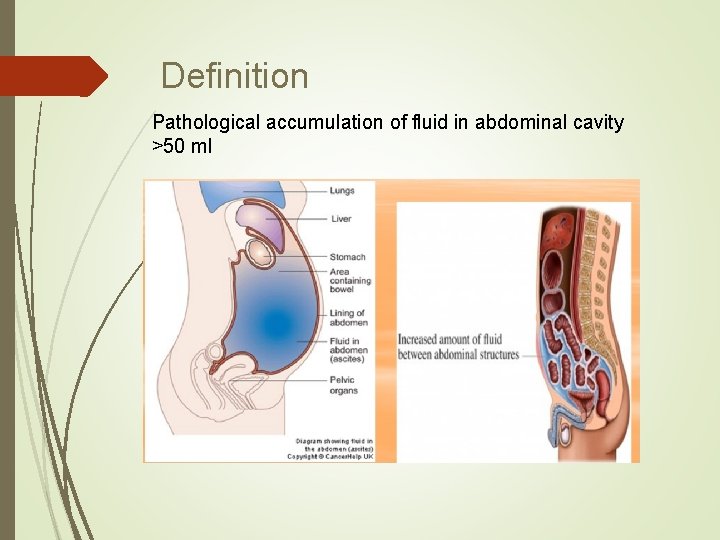
Definition Pathological accumulation of fluid in abdominal cavity >50 ml
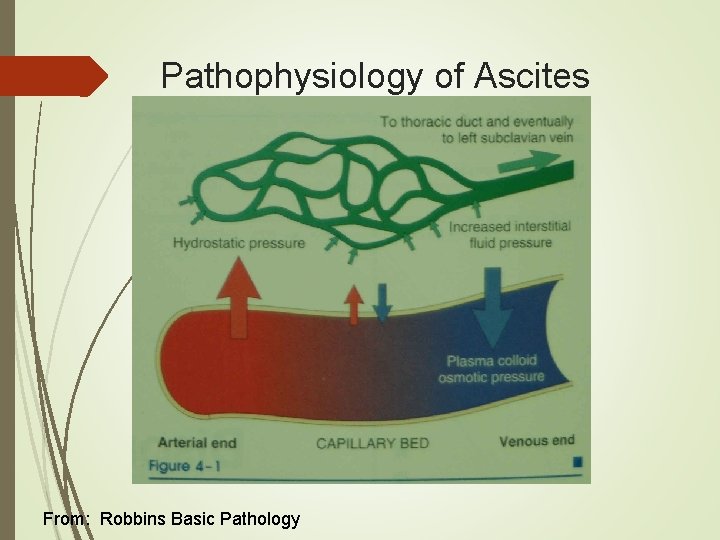
Pathophysiology of Ascites From: Robbins Basic Pathology
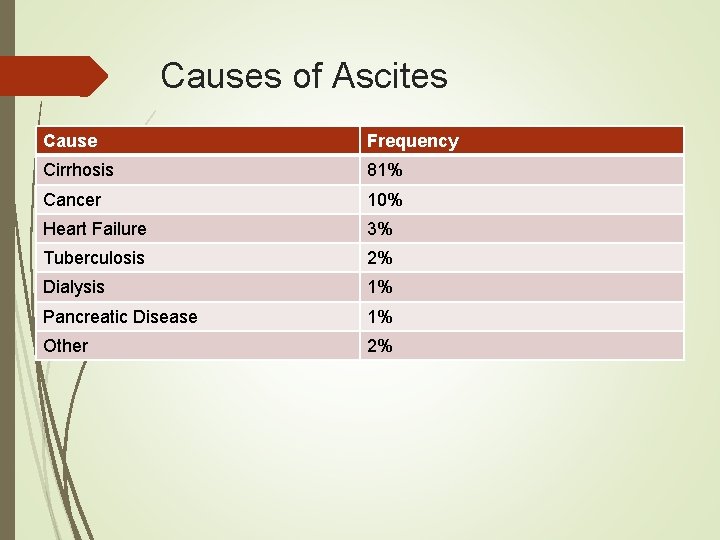
Causes of Ascites Cause Frequency Cirrhosis 81% Cancer 10% Heart Failure 3% Tuberculosis 2% Dialysis 1% Pancreatic Disease 1% Other 2%
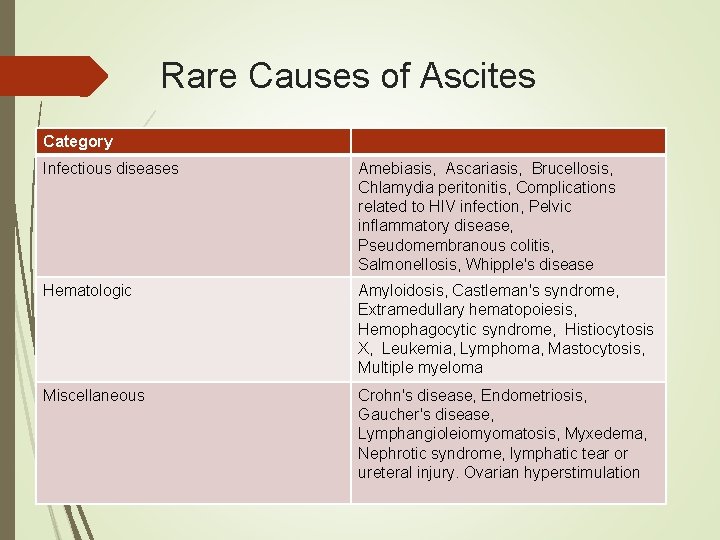
Rare Causes of Ascites Category Infectious diseases Amebiasis, Ascariasis, Brucellosis, Chlamydia peritonitis, Complications related to HIV infection, Pelvic inflammatory disease, Pseudomembranous colitis, Salmonellosis, Whipple's disease Hematologic Amyloidosis, Castleman's syndrome, Extramedullary hematopoiesis, Hemophagocytic syndrome, Histiocytosis X, Leukemia, Lymphoma, Mastocytosis, Multiple myeloma Miscellaneous Crohn's disease, Endometriosis, Gaucher's disease, Lymphangioleiomyomatosis, Myxedema, Nephrotic syndrome, lymphatic tear or ureteral injury. Ovarian hyperstimulation
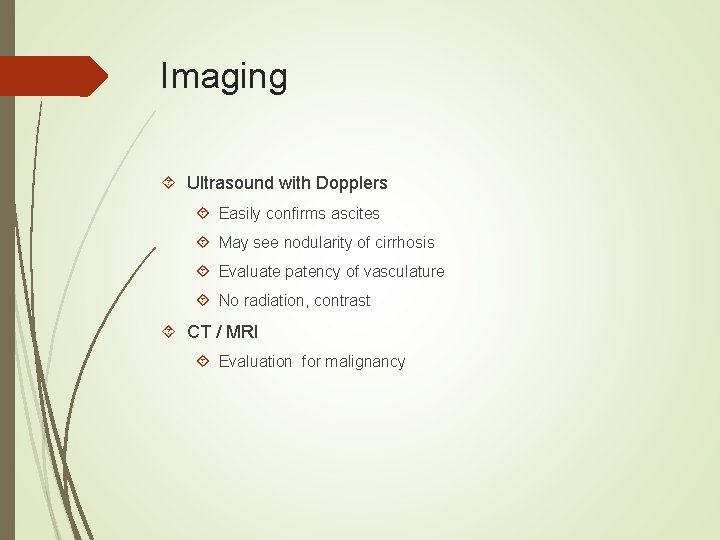
Imaging Ultrasound with Dopplers Easily confirms ascites May see nodularity of cirrhosis Evaluate patency of vasculature No radiation, contrast CT / MRI Evaluation for malignancy
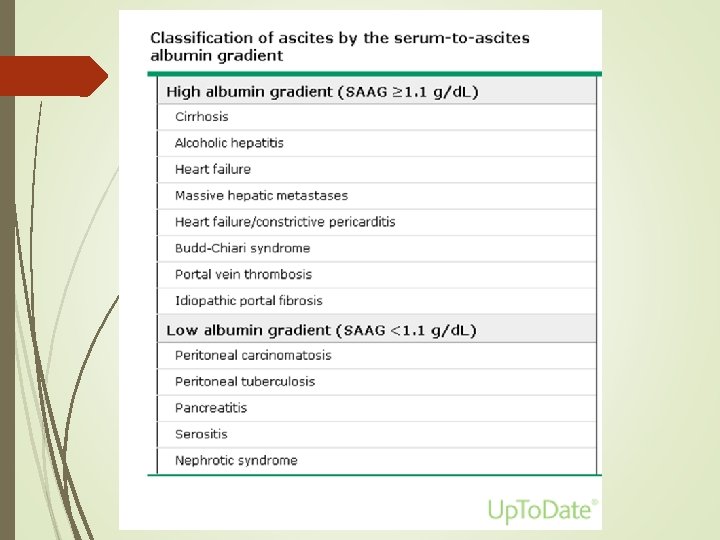
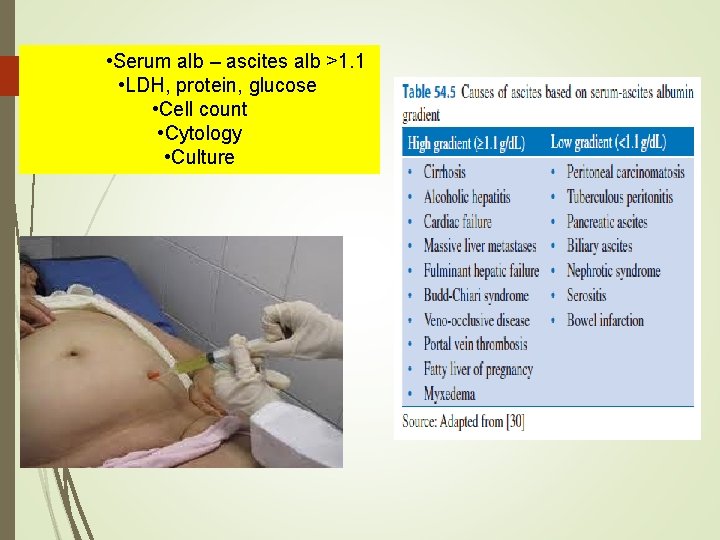
Serum to Ascites Albumin Gradient Is portal hypertension present? 97% accurate SAAG > 1. 1 g/d. L Portal HTN SAAG < 1. 1 g/d. L Other causes The serum-ascites albumin gradient is superior to the exudate-transudate concept in the differential diagnosis of ascites. Runyon BA; Montano AA; Akriviadis EA; Antillon MR; Irving MA; Mc. Hutchison Ann Intern Med 1992 Aug 1; 117(3): 215 -20.
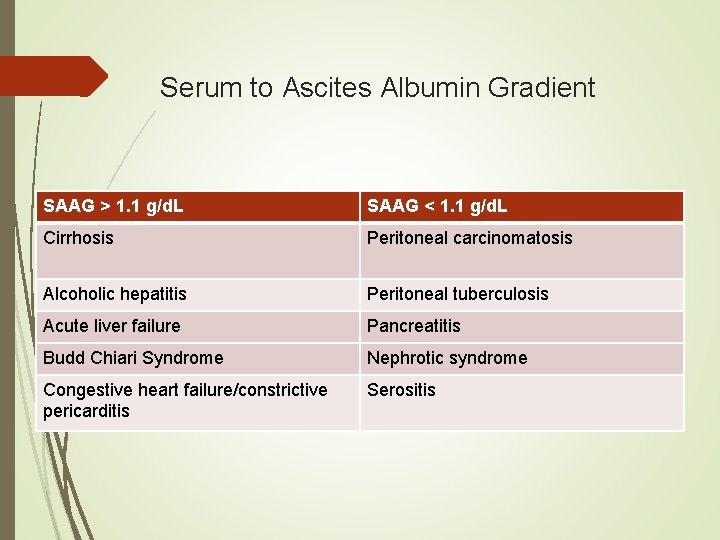
Serum to Ascites Albumin Gradient SAAG > 1. 1 g/d. L SAAG < 1. 1 g/d. L Cirrhosis Peritoneal carcinomatosis Alcoholic hepatitis Peritoneal tuberculosis Acute liver failure Pancreatitis Budd Chiari Syndrome Nephrotic syndrome Congestive heart failure/constrictive pericarditis Serositis
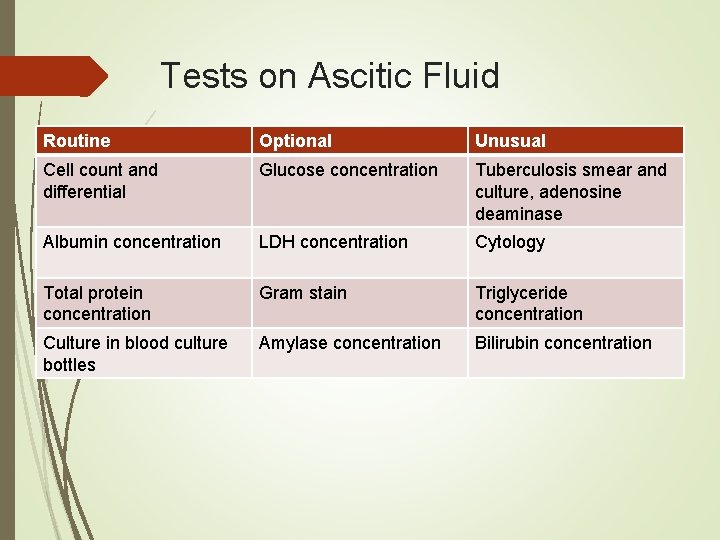
Tests on Ascitic Fluid Routine Optional Unusual Cell count and differential Glucose concentration Tuberculosis smear and culture, adenosine deaminase Albumin concentration LDH concentration Cytology Total protein concentration Gram stain Triglyceride concentration Culture in blood culture bottles Amylase concentration Bilirubin concentration
Cell Count, differential and culture Is ascites infected? Greater than 250 PMN = SBP If ascites is bloody ( > 50, 000 RBC/mm 3), correct by subtracting 1 PMN / 250 RBC Is ascites bloody? 5% of pts w/ cirrhosis - spontaneous or s/p traumatic tap. Non-traumatic associated with malignancy 20% of malignant ascites 10% of peritoneal carcinomatosis
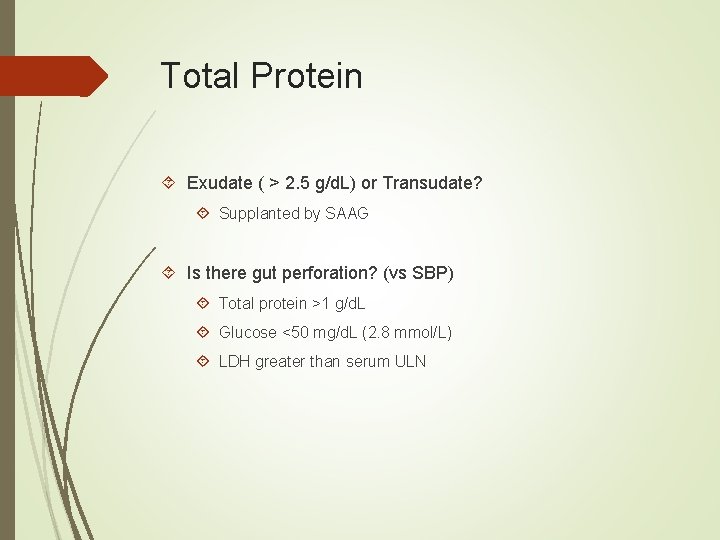
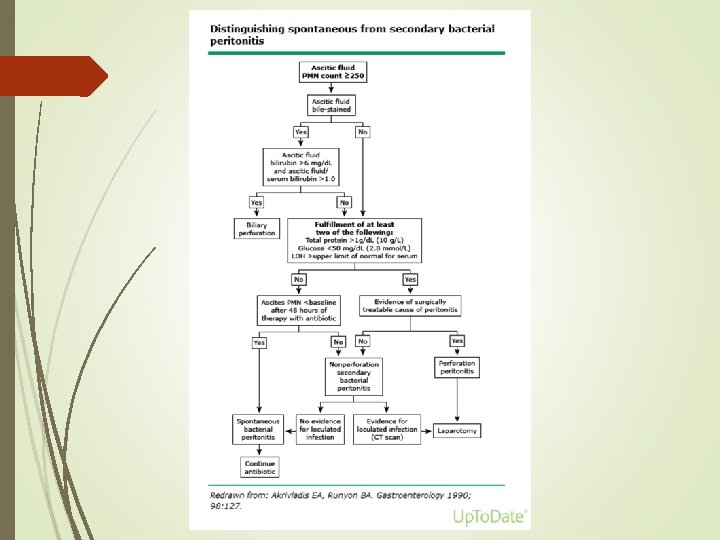
Total Protein Exudate ( > 2. 5 g/d. L) or Transudate? Supplanted by SAAG Is there gut perforation? (vs SBP) Total protein >1 g/d. L Glucose <50 mg/d. L (2. 8 mmol/L) LDH greater than serum ULN
Glucose and LDH Consistent with infection or malignancy? Infection and cancer consume glucose low LDH is a larger molecule than glucose, enters ascitic fluid with difficulty. Ascitis/Serum LDH ratio ~ 0. 4 in cirrhotic ascites Approaches 1. 0 in SBP >1. 0, usually infection or tumor
Other tests Amylase Uncomplicated cirrhotic ascites About 40 IU/L. The AF/S ratio is about 0. 4 Pancreatic ascites About 2000 IU/L. The AF/S ratio is about 6 Triglycerides — run on milky fluid. Chylous ascites - TG > 200 mg/d. L, usually 1000 mg/d. L Bilirubin — run on brown ascites. Biliary perforation – AF Bili > serum Bili
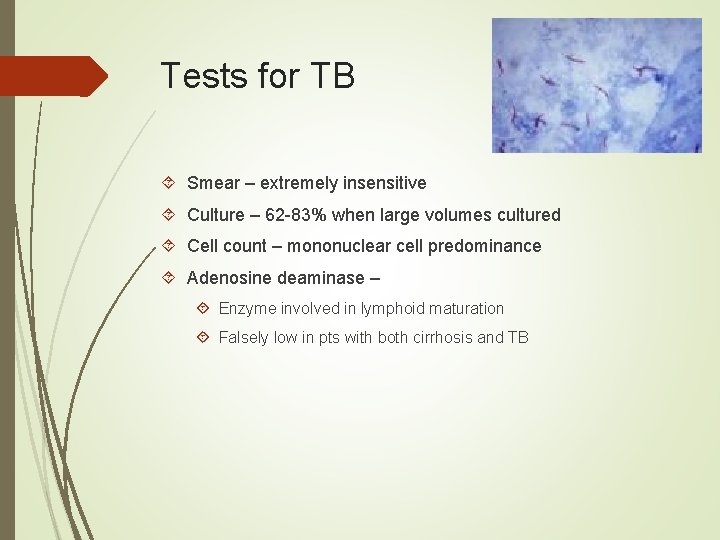
Tests for TB Smear – extremely insensitive Culture – 62 -83% when large volumes cultured Cell count – mononuclear cell predominance Adenosine deaminase – Enzyme involved in lymphoid maturation Falsely low in pts with both cirrhosis and TB
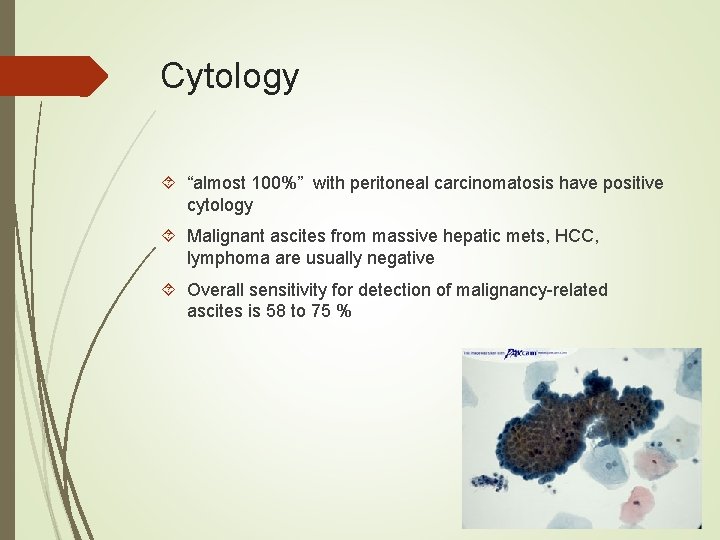
Cytology “almost 100%” with peritoneal carcinomatosis have positive cytology Malignant ascites from massive hepatic mets, HCC, lymphoma are usually negative Overall sensitivity for detection of malignancy-related ascites is 58 to 75 %
Not helpful “Some tests of ascitic fluid appear to be useless. These include p. H, lactate, and ‘humoral tests of malignancy’ such as fibronectin, cholesterol, and many others”
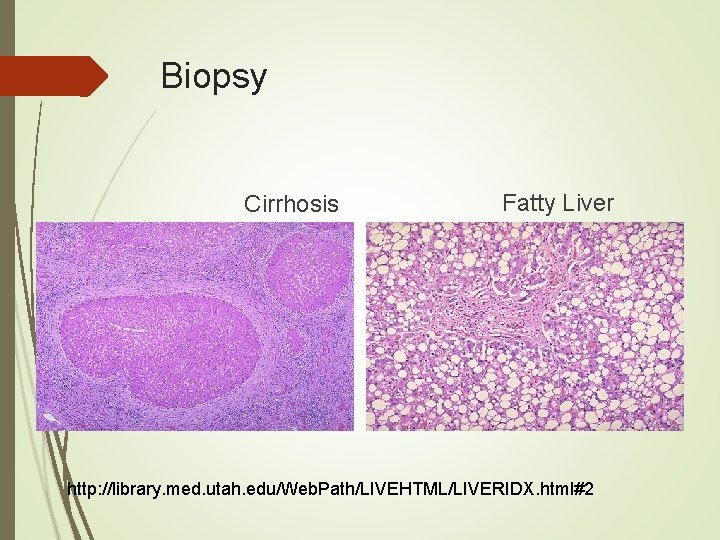
Biopsy Cirrhosis Fatty Liver http: //library. med. utah. edu/Web. Path/LIVEHTML/LIVERIDX. html#2
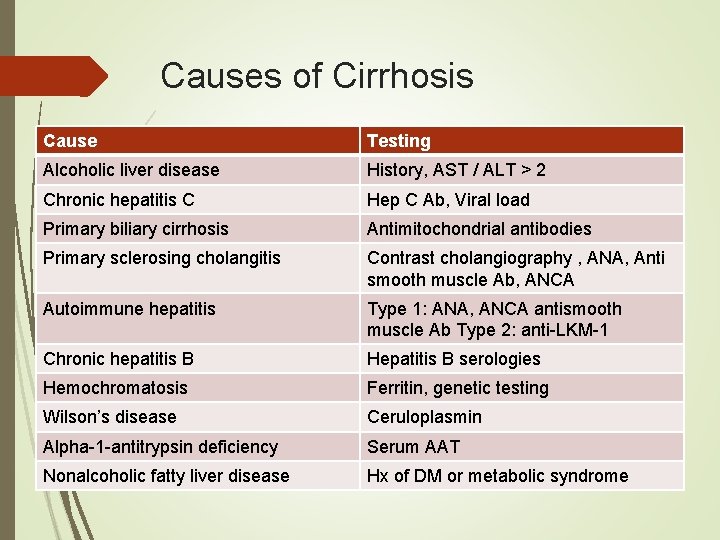
Causes of Cirrhosis Cause Testing Alcoholic liver disease History, AST / ALT > 2 Chronic hepatitis C Hep C Ab, Viral load Primary biliary cirrhosis Antimitochondrial antibodies Primary sclerosing cholangitis Contrast cholangiography , ANA, Anti smooth muscle Ab, ANCA Autoimmune hepatitis Type 1: ANA, ANCA antismooth muscle Ab Type 2: anti-LKM-1 Chronic hepatitis B Hepatitis B serologies Hemochromatosis Ferritin, genetic testing Wilson’s disease Ceruloplasmin Alpha-1 -antitrypsin deficiency Serum AAT Nonalcoholic fatty liver disease Hx of DM or metabolic syndrome
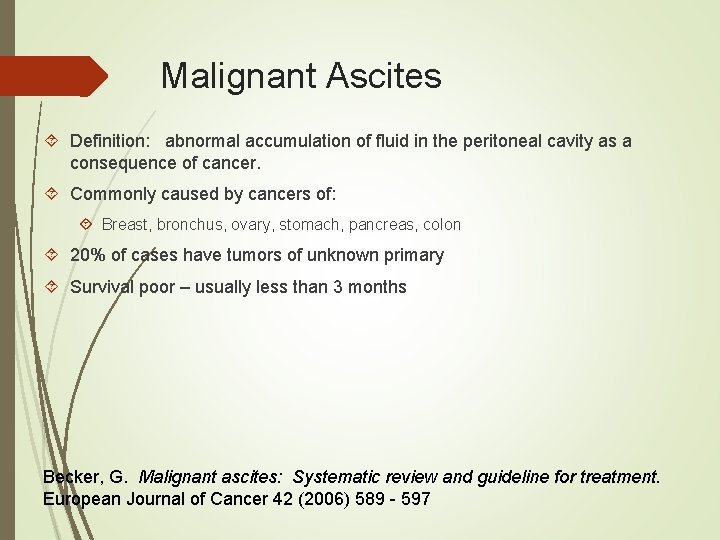
Malignant Ascites Definition: abnormal accumulation of fluid in the peritoneal cavity as a consequence of cancer. Commonly caused by cancers of: Breast, bronchus, ovary, stomach, pancreas, colon 20% of cases have tumors of unknown primary Survival poor – usually less than 3 months Becker, G. Malignant ascites: Systematic review and guideline for treatment. European Journal of Cancer 42 (2006) 589 - 597
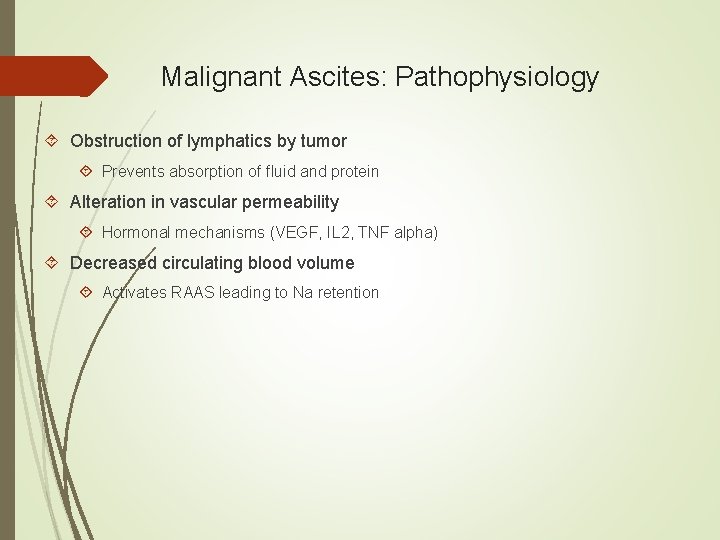
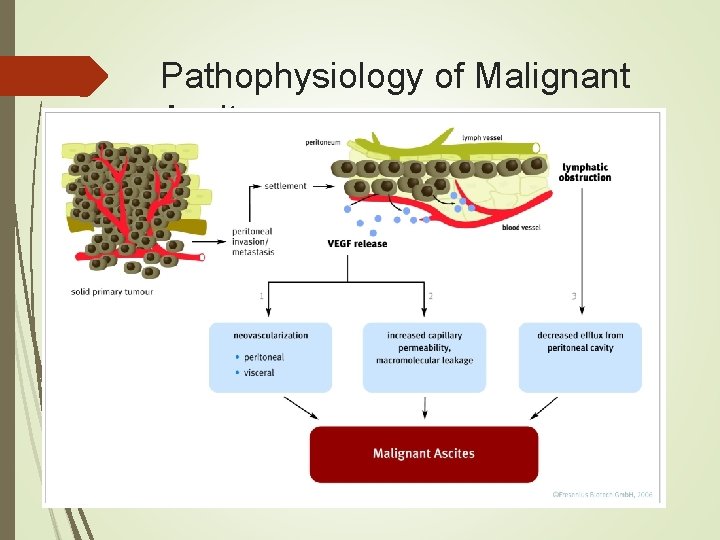
Malignant Ascites: Pathophysiology Obstruction of lymphatics by tumor Prevents absorption of fluid and protein Alteration in vascular permeability Hormonal mechanisms (VEGF, IL 2, TNF alpha) Decreased circulating blood volume Activates RAAS leading to Na retention
Pathophysiology of Malignant Ascites
Management of Malignant Ascites Therapeutic paracentesis Removing up to 5 L appears safe No good data on role of volume expanders Diuretics Equivocal evidence of efficacy May be helpful for portal HTN Less/minimally useful when no portal HTN Drainage Catheters Peritoneovenous shunts
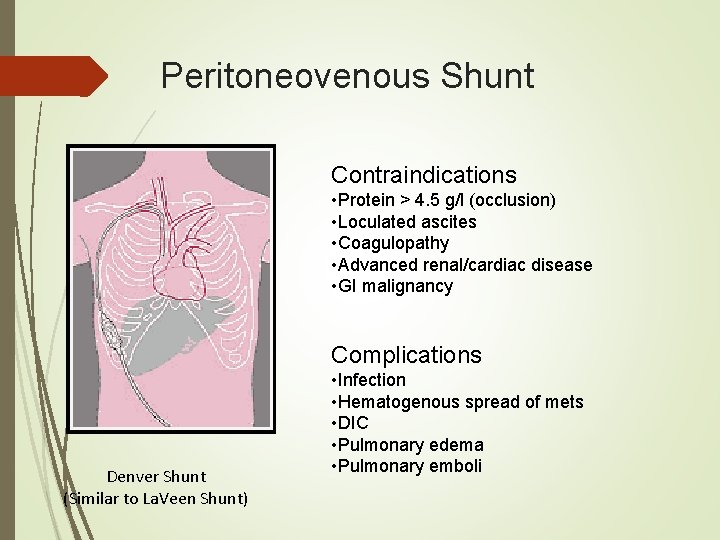
Peritoneovenous Shunt Contraindications • Protein > 4. 5 g/l (occlusion) • Loculated ascites • Coagulopathy • Advanced renal/cardiac disease • GI malignancy Complications Denver Shunt (Similar to La. Veen Shunt) • Infection • Hematogenous spread of mets • DIC • Pulmonary edema • Pulmonary emboli
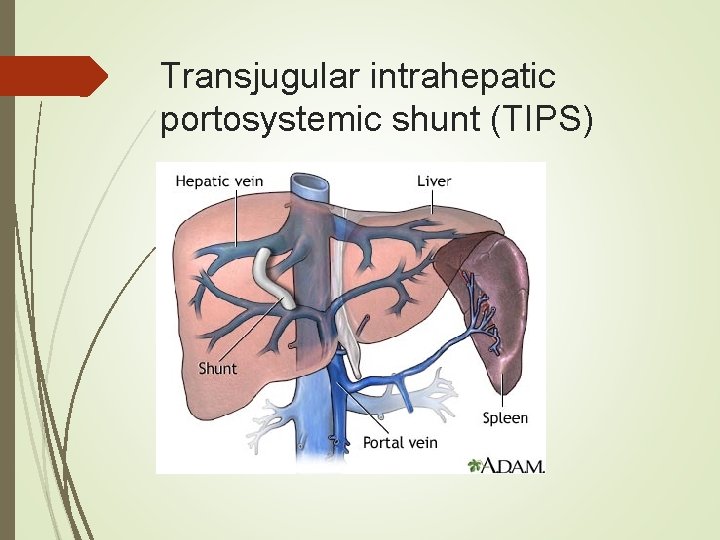
Transjugular intrahepatic portosystemic shunt (TIPS)
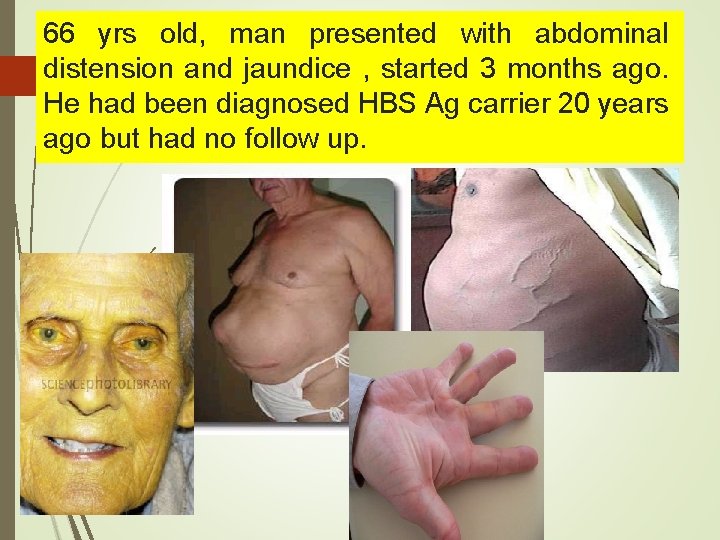
66 yrs old, man presented with abdominal distension and jaundice , started 3 months ago. He had been diagnosed HBS Ag carrier 20 years ago but had no follow up.
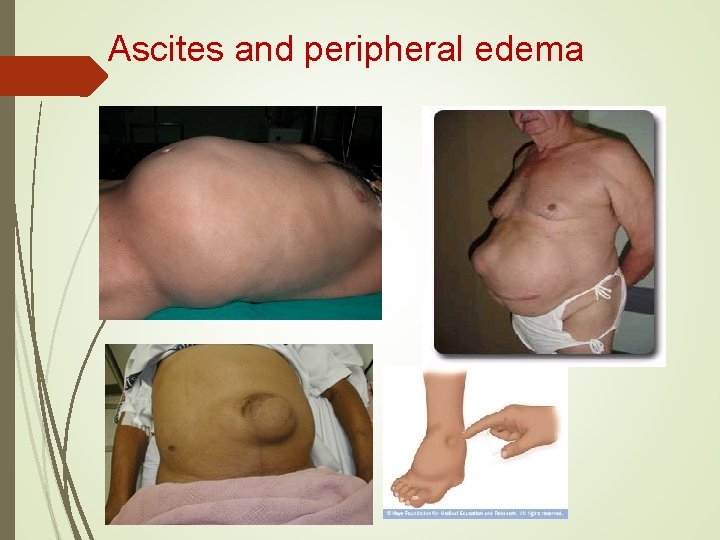
Ascites and peripheral edema
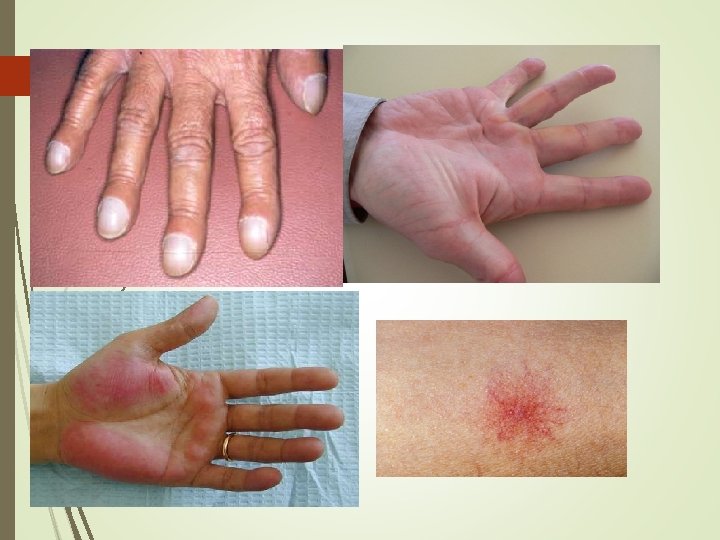
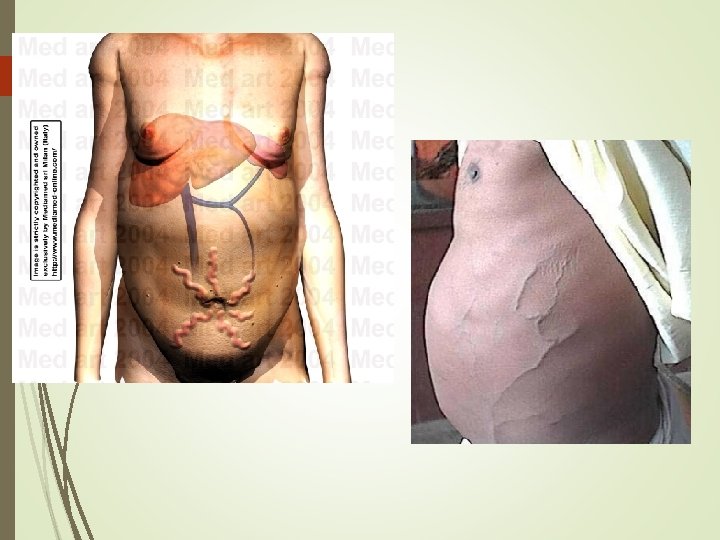
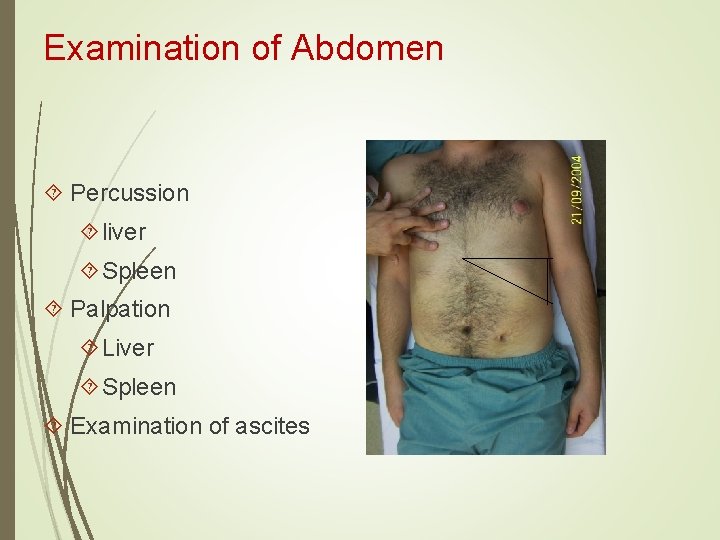
Examination of Abdomen Percussion liver Spleen Palpation Liver Spleen Examination of ascites
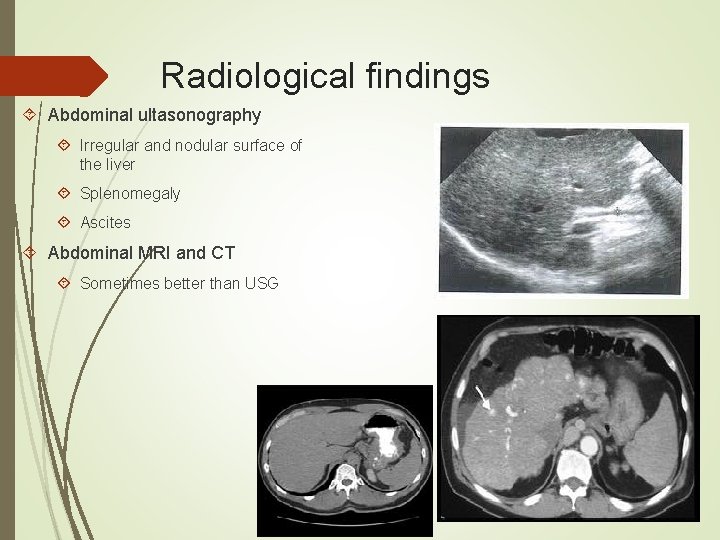
Radiological findings Abdominal ultasonography Irregular and nodular surface of the liver Splenomegaly Ascites Abdominal MRI and CT Sometimes better than USG
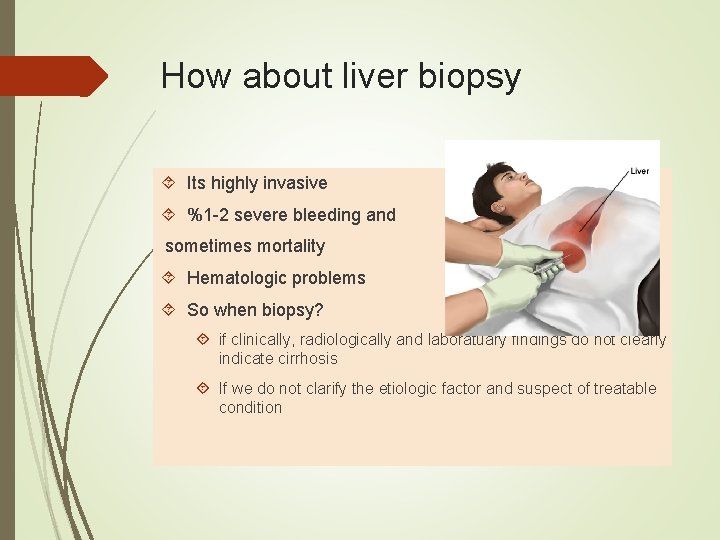
How about liver biopsy Its highly invasive %1 -2 severe bleeding and sometimes mortality Hematologic problems So when biopsy? if clinically, radiologically and laboratuary findings do not clearly indicate cirrhosis If we do not clarify the etiologic factor and suspect of treatable condition
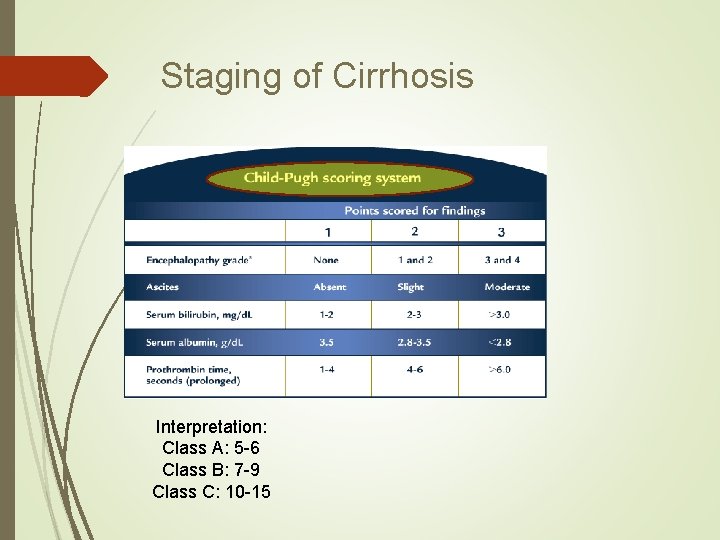
Staging of Cirrhosis Interpretation: Class A: 5 -6 Class B: 7 -9 Class C: 10 -15
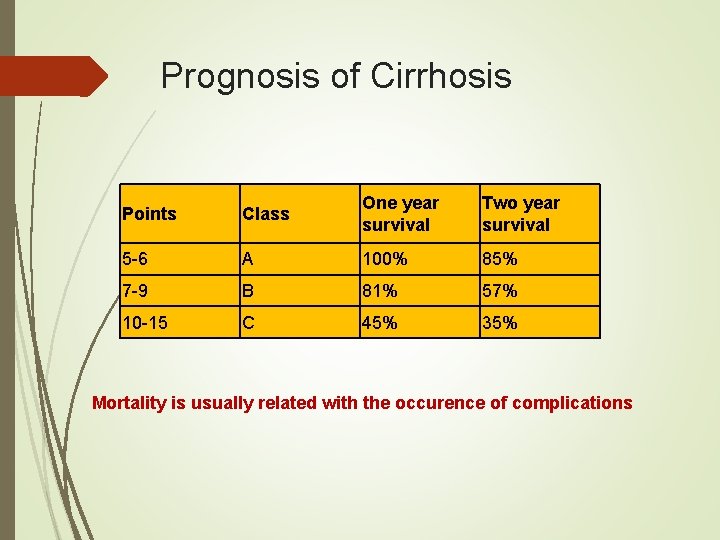
Prognosis of Cirrhosis Points Class One year survival Two year survival 5 -6 A 100% 85% 7 -9 B 81% 57% 10 -15 C 45% 35% Mortality is usually related with the occurence of complications
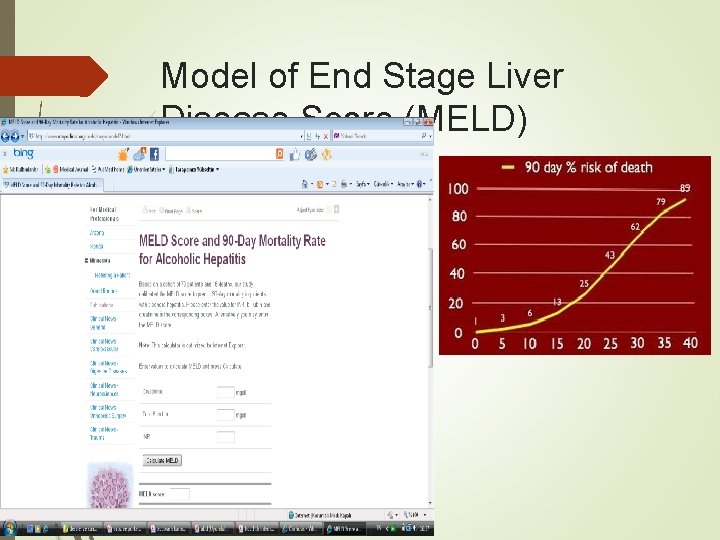
Model of End Stage Liver Disease Score (MELD)
Treatment At Early Stage Early treatment may affect prognosis Stop alcohol drinking Eradication of viruses Treatment of the cause – Autoimmune – Wilson – Hemachromatosis – Sclerozing Cholangitis Very good followup Prevention of complications Low Na Diet
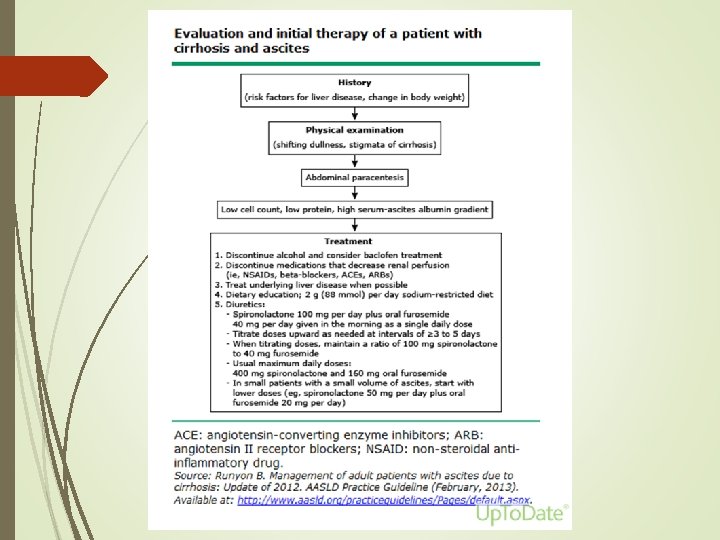
Treatment for Ascites Diuretics (Spironolactone, furosemide) Low sodium diet Therapeutic parasentesis Transplantation
Ascites; usually the first complication !! Sometimes no symptom Abdominal distension Feeling abdominal tenderness Treatment Na restriction Dıuretics Terapeutic parasentesis
• Serum alb – ascites alb >1. 1 • LDH, protein, glucose • Cell count • Cytology • Culture
Spontaneous bacterial peritonitis Spontaneous infection of ascites Any cirrhotic patient with Fever Abdominal pain Abdominal tenderness Detoriation of clinical situation Parasentesis Neutrophil count>250/ml Ascites culture: mostly E. coli Treatment i. v antibiotics: 3 th generation cephalosporins (cefotaxim) first choise, quinalons or penicilins
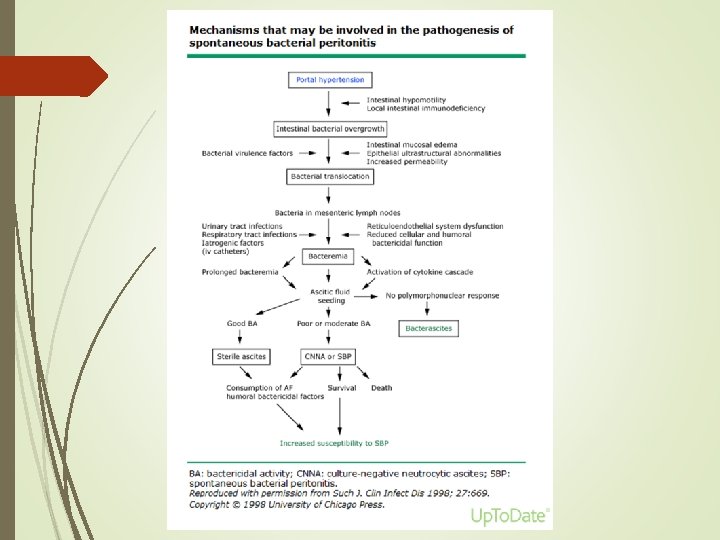
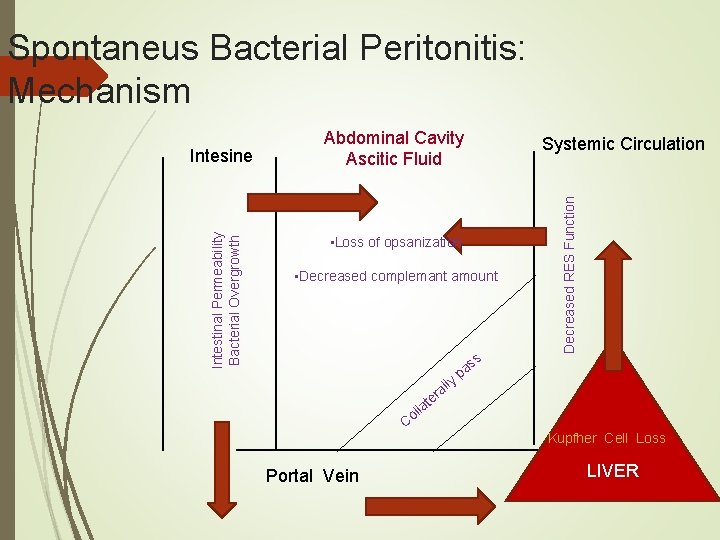
Spontaneus Bacterial Peritonitis: Mechanism • Loss of opsanization • Decreased complemant amount lly ss a p Systemic Circulation Decreased RES Function Intestinal Permeability Bacterial Overgrowth Intesine Abdominal Cavity Ascitic Fluid a er t lla Co Portal Vein Kupfher Cell Loss LIVER
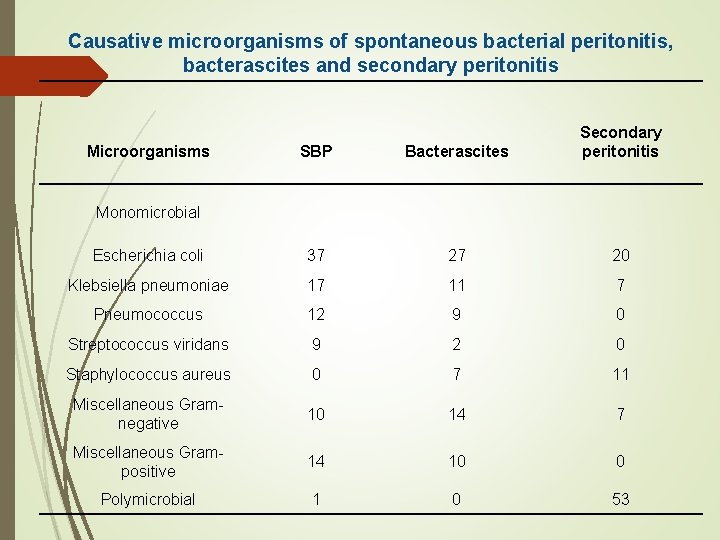
Causative microorganisms of spontaneous bacterial peritonitis, bacterascites and secondary peritonitis SBP Bacterascites Secondary peritonitis Escherichia coli 37 27 20 Klebsiella pneumoniae 17 11 7 Pneumococcus 12 9 0 Streptococcus viridans 9 2 0 Staphylococcus aureus 0 7 11 Miscellaneous Gramnegative 10 14 7 Miscellaneous Grampositive 14 10 0 Polymicrobial 1 0 53 Microorganisms Monomicrobial
Liver Transplantation Each patient who has the complications must be listed for transplantation Child Score > 9 MELD Score > 10 Urgent Tx Acute fulminant liver failure Acute on chronic liver failure
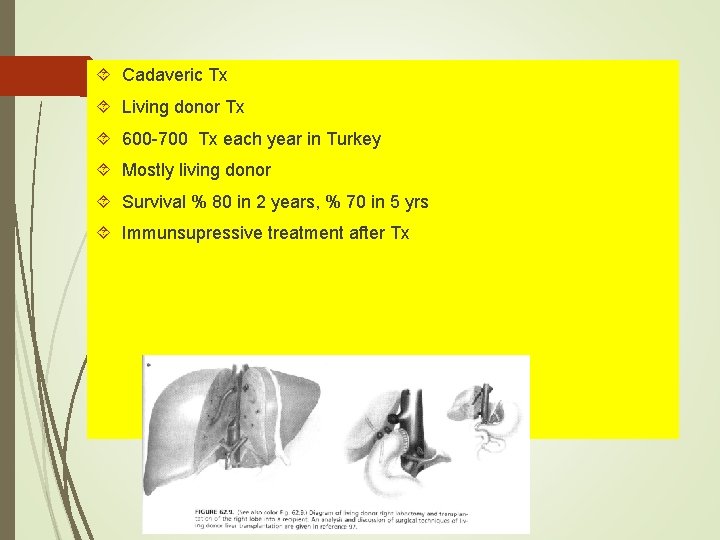
Cadaveric Tx Living donor Tx 600 -700 Tx each year in Turkey Mostly living donor Survival % 80 in 2 years, % 70 in 5 yrs Immunsupressive treatment after Tx
You are free now !!!