
HEPATOLOGY Hepatology Phase 2 a Revision Session Rye












- Slides: 38
HEPATOLOGY
Hepatology Phase 2 a Revision Session Rye Yap & May Phoon 20. 03. 2017 The Peer Teaching Society is not liable for false or misleading information…
Learning Objectives 1. Jaundice 2. Biliary tract disease 3. Cirrhosis: causes & complications – Metabolic causes – Autoimmune causes – Alcoholic liver disease – Viral hepatitis 4. Liver failure 5. Liver tumours The Peer Teaching Society is not liable for false or misleading information…
Jaundice • Raised plasma bilirubin → yellow • Types of bilirubin: – Conjugated – Unconjugated • Classification: – Prehepatic – Intrahepatic – Posthepatic The Peer Teaching Society is not liable for false or misleading information…
Biliary Tract Diseases 1. Biliary colic 1. Cholecystitis 1. Ascending cholangitis The Peer Teaching Society is not liable for false or misleading information…
Biliary Colic Pain due to temporary obstruction of the cystic or common bile duct by a stone Symptoms • Recurrent epigastric/RUQ region abdominal pain lasting <24 hr – Radiate → R shoulder/subscapular – Pain → vomit – Associated with fatty food Investigations • Bloods → LFT (only ↑bilirubin or ALP during an attack) • Imaging → Abdo US (gallstones + distended gallbladder/dilated ducts) Management • Analgesia • Elective cholecystectomy The Peer Teaching Society is not liable for false or misleading information…
Cholecystitis Impaction neck of GB/cystic duct → static bile → inflammation Signs Acute Chronic • • Symptoms ● Murphy’s sign ● Local peritonism ● Palpable mass ● Abdominal pain - RUQ/epigastric +/radiation ● N&V ● Fever ● Abdominal distension ● Flatulence ● Fat intolerance Investigations: – Blood tests – Imaging: Abdo US Management: – Cholecystectomy [1 st line] – Surgery prep: NBM, IVI, ABx The Peer Teaching Society is not liable for false or misleading information… LFTs affected ● Bilirubin ● ALP ● GGT
Ascending Cholangitis Infection of the biliary tree most commonly due to common bile duct obstruction by gallstones. Symptoms Signs ● Fever ● Jaundice ● Right upper quadrant pain ● Epigastric/RUQ tenderness + guarding ● Rigors ● Hypotension ● Pruritus ● Confusion ● Dark urine & pale stool Investigations • Bloods: FBC, CRP, LFT • Imaging: USS, ERCP, MRCP Management: • IV fluid + antibiotics (e. g. cefotaxime + metronidazole) • Analgesia • Relieve obstruction - ERCP stone removal/stenting • Cholecystectomy The Peer Teaching Society is not liable for false or misleading information…
Cirrhosis Cell necrosis → fibrosis → nodule formation IRREVERSIBLE! General signs: • Investigations: – Bloods – Imaging – Special tests ● Hepatomegal y ● Jaundice ● Ascites The Peer Teaching Society is not liable for false or misleading information… Signs that med school loves: ● ● ● ● ● Spider naevi Clubbing Leuconychia Terry’s nail Palmar erythema Dupuytren’s contracture Xantelasma Gynaecomastia Loss of body hair Atrophic testes
Cirrhosis Management: 1. Find out cause & treat (p. s. more than likely caused by alcohol) 2. Symptomatic treatment 3. Lifestyle changes 4. Monitor 5. Consider liver transplant BEWARE THE COMPLICATIONS! The Peer Teaching Society is not liable for false or misleading information…
Metabolic Causes of Liver Disease Hereditary haemochromatosis Jack Joint (arthralgia) Lost Liver (hepatomegaly) His Heart (cardiomyopathy) Point & Shoo t Pancreas (diabetes) & pituitary (hypogonadism) Erectile dysfunction Skin (bronze pigmentation) Investigation: ● Bloods: ↑ferritin, transferrin saturation >45% ● Liver biopsy: Perl’s stain blue Management: ● Venesect ● Low iron diet The Peer Teaching Society is not liable for false or misleading information…
Metabolic Causes of Liver Disease Alpha 1 -antitrypsin deficiency Lung → emphysema • • Liver → cirrhosis and hepatocellular cancer Chromosome 14 (AR) Alpha 1 -antitrypsin is inactivated by smoking Investigations: • Serum alpha 1 -antitrypsin • Liver biopsy → Periodic acid schiff Management: • Smoking cessation The Peer Teaching Society is not liable for false or misleading information…
Metabolic Causes of Liver Disease Wilson’s disease • • Chromosome 13 (AR) Abnormal copper transporting ATPase → ↓ copper incorporation into caeruloplasmin and ↓ biliary copper excretion → copper accumulate in the liver. Hepatitis, cirrhosis, fulminant liver failure Liver CNS Basal ganglia (most commonly affected) ● Tremor, dysarthria, dysphagia, dyskinesias, dystonias, parkinsonism, etc. Mood ● Depression, personality change, labile emotions, mania Cognition ● ↓Memory, ↓IQ Others Eye: Kayser-Fleischer rings (slit lamp examination) Skin: Grey skin Joints: Arthritis, hypermobility Nails: Blue lanulae Blood: Haemolysis The Peer Teaching Society is not liable for false or misleading information…
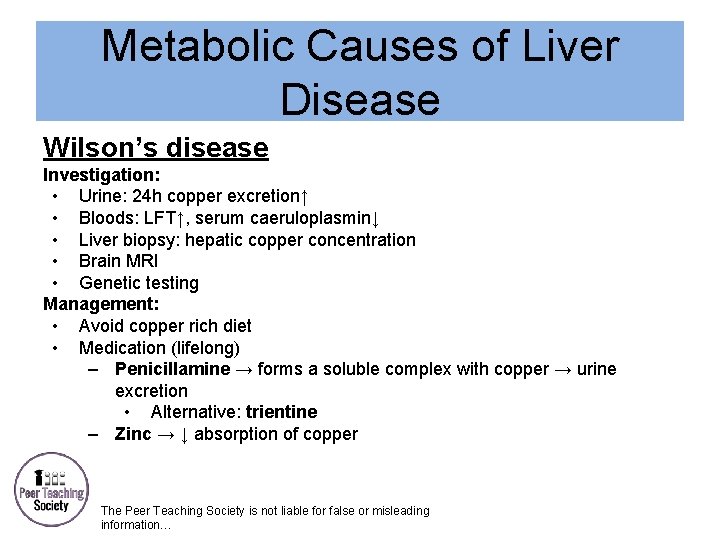
Metabolic Causes of Liver Disease Wilson’s disease Investigation: • Urine: 24 h copper excretion↑ • Bloods: LFT↑, serum caeruloplasmin↓ • Liver biopsy: hepatic copper concentration • Brain MRI • Genetic testing Management: • Avoid copper rich diet • Medication (lifelong) – Penicillamine → forms a soluble complex with copper → urine excretion • Alternative: trientine – Zinc → ↓ absorption of copper The Peer Teaching Society is not liable for false or misleading information…
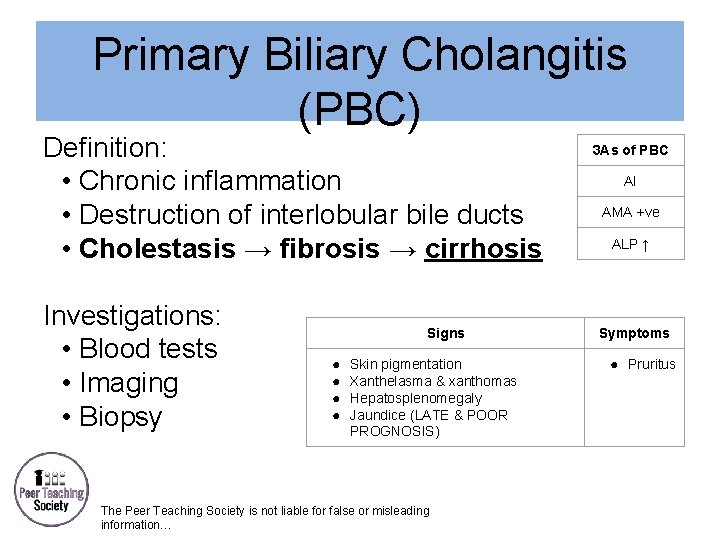
Primary Biliary Cholangitis (PBC) Definition: • Chronic inflammation • Destruction of interlobular bile ducts • Cholestasis → fibrosis → cirrhosis Investigations: • Blood tests • Imaging • Biopsy Signs ● ● Skin pigmentation Xanthelasma & xanthomas Hepatosplenomegaly Jaundice (LATE & POOR PROGNOSIS) The Peer Teaching Society is not liable for false or misleading information… 3 As of PBC AI AMA +ve ALP ↑ Symptoms ● Pruritus
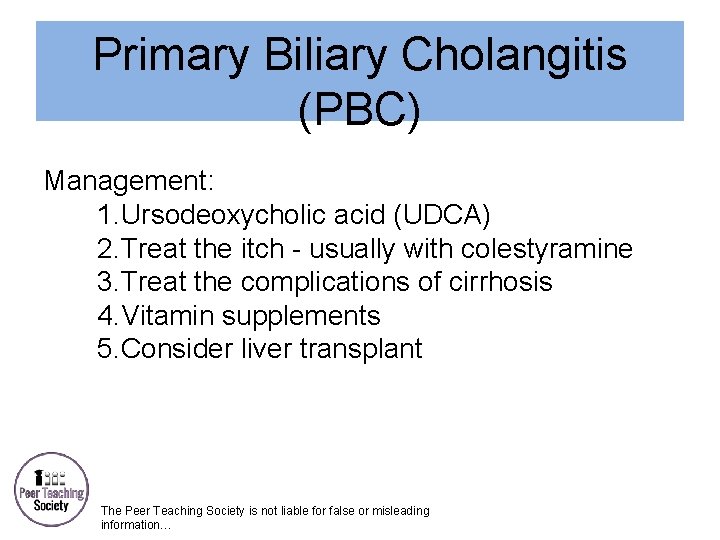
Primary Biliary Cholangitis (PBC) Management: 1. Ursodeoxycholic acid (UDCA) 2. Treat the itch - usually with colestyramine 3. Treat the complications of cirrhosis 4. Vitamin supplements 5. Consider liver transplant The Peer Teaching Society is not liable for false or misleading information…
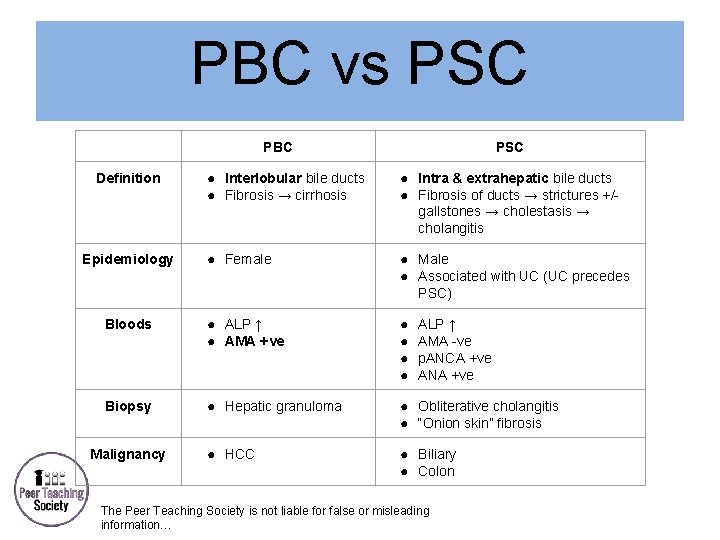
PBC vs PSC PBC PSC ● Interlobular bile ducts ● Fibrosis → cirrhosis ● Intra & extrahepatic bile ducts ● Fibrosis of ducts → strictures +/gallstones → cholestasis → cholangitis ● Female ● Male ● Associated with UC (UC precedes PSC) Bloods ● ALP ↑ ● AMA +ve ● ● Biopsy ● Hepatic granuloma ● Obliterative cholangitis ● “Onion skin” fibrosis ● HCC ● Biliary ● Colon Definition Epidemiology Malignancy ALP ↑ AMA -ve p. ANCA +ve ANA +ve The Peer Teaching Society is not liable for false or misleading information…
Alcoholic Liver Disease (ALD) Excessive alcohol intake → damage → impaired function [MAIN CAUSE OF LIVER DEATH IN UK!] Stages: 1. Fatty liver – Metabolism of alcohol → net increase hepatic fatty acid – Accumulation → steatosis 2. Hepatitis – Too much fat → necrosis → inflammation – Look out for Mallory bodies & giant mitochondria 3. Cirrhosis The Peer Teaching Society is not liable for false or misleading information…
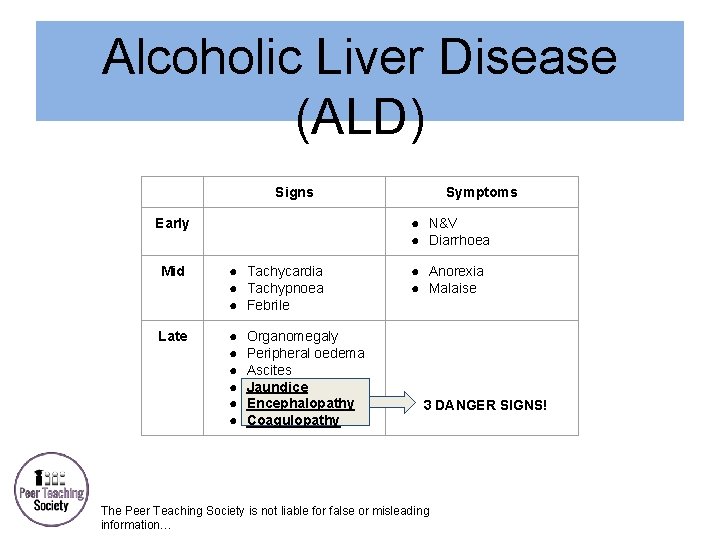
Alcoholic Liver Disease (ALD) Signs Symptoms ● N&V ● Diarrhoea Early Mid ● Tachycardia ● Tachypnoea ● Febrile Late ● ● ● Organomegaly Peripheral oedema Ascites Jaundice Encephalopathy Coagulopathy ● Anorexia ● Malaise 3 DANGER SIGNS! The Peer Teaching Society is not liable for false or misleading information…
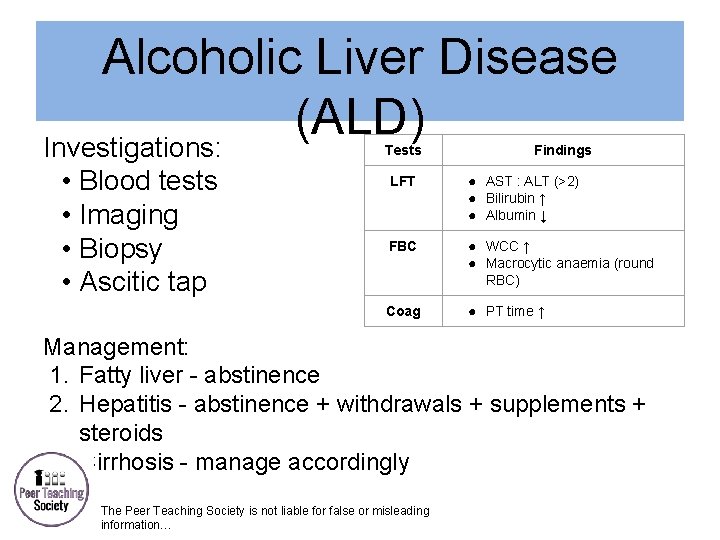
Alcoholic Liver Disease (ALD) Investigations: Tests • Blood tests • Imaging • Biopsy • Ascitic tap Findings LFT ● AST : ALT (>2) ● Bilirubin ↑ ● Albumin ↓ FBC ● WCC ↑ ● Macrocytic anaemia (round RBC) Coag ● PT time ↑ Management: 1. Fatty liver - abstinence 2. Hepatitis - abstinence + withdrawals + supplements + steroids 3. Cirrhosis - manage accordingly The Peer Teaching Society is not liable for false or misleading information…
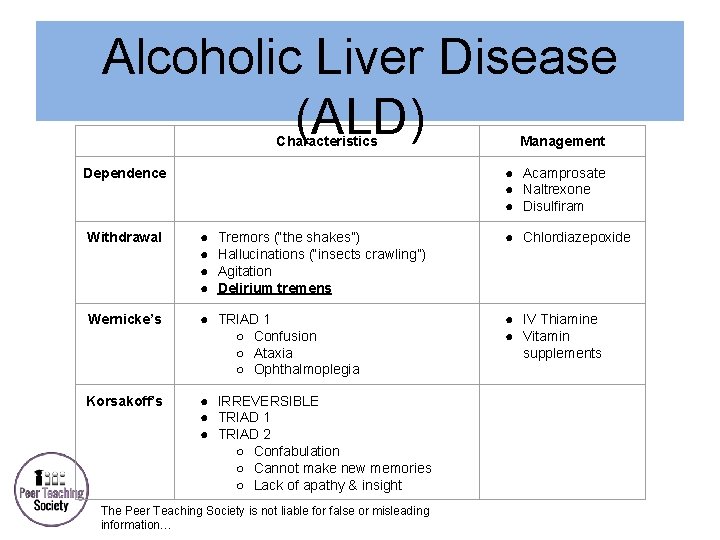
Alcoholic Liver Disease (ALD) Characteristics Management ● Acamprosate ● Naltrexone ● Disulfiram Dependence Withdrawal ● ● Wernicke’s ● TRIAD 1 ○ Confusion ○ Ataxia ○ Ophthalmoplegia Korsakoff’s ● IRREVERSIBLE ● TRIAD 1 ● TRIAD 2 ○ Confabulation ○ Cannot make new memories ○ Lack of apathy & insight Tremors (“the shakes”) Hallucinations (“insects crawling”) Agitation Delirium tremens The Peer Teaching Society is not liable for false or misleading information… ● Chlordiazepoxide ● IV Thiamine ● Vitamin supplements
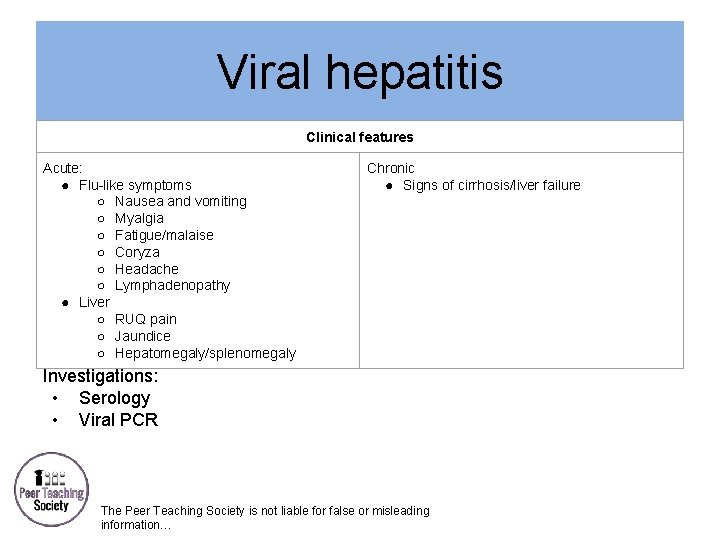
Viral hepatitis Clinical features Acute: ● Flu-like symptoms ○ Nausea and vomiting ○ Myalgia ○ Fatigue/malaise ○ Coryza ○ Headache ○ Lymphadenopathy ● Liver ○ RUQ pain ○ Jaundice ○ Hepatomegaly/splenomegaly Chronic ● Signs of cirrhosis/liver failure Investigations: • Serology • Viral PCR The Peer Teaching Society is not liable for false or misleading information…
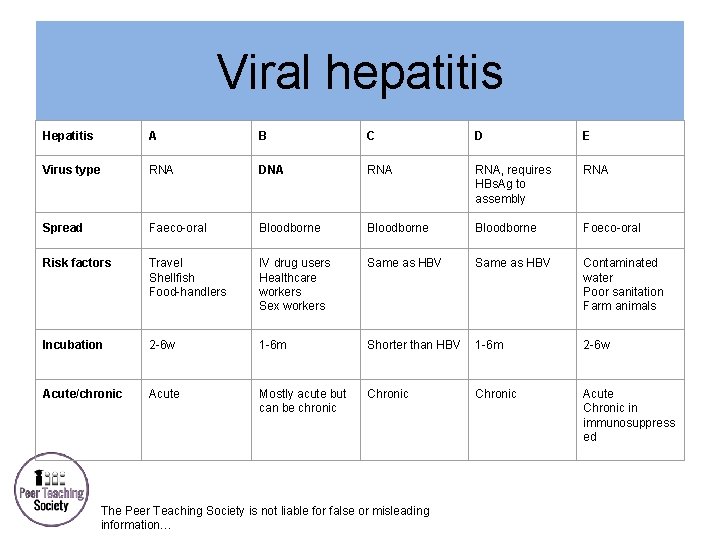
Viral hepatitis Hepatitis A B C D E Virus type RNA DNA RNA, requires HBs. Ag to assembly RNA Spread Faeco-oral Bloodborne Foeco-oral Risk factors Travel Shellfish Food-handlers IV drug users Healthcare workers Sex workers Same as HBV Contaminated water Poor sanitation Farm animals Incubation 2 -6 w 1 -6 m Shorter than HBV 1 -6 m 2 -6 w Acute/chronic Acute Mostly acute but can be chronic Chronic Acute Chronic in immunosuppress ed The Peer Teaching Society is not liable for false or misleading information…
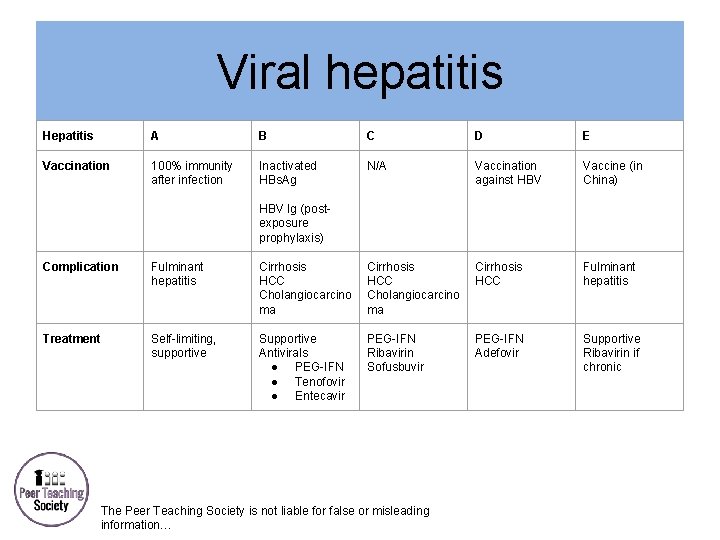
Viral hepatitis Hepatitis A B C D E Vaccination 100% immunity after infection Inactivated HBs. Ag N/A Vaccination against HBV Vaccine (in China) HBV Ig (postexposure prophylaxis) Complication Fulminant hepatitis Cirrhosis HCC Cholangiocarcino ma Cirrhosis HCC Fulminant hepatitis Treatment Self-limiting, supportive Supportive Antivirals ● PEG-IFN ● Tenofovir ● Entecavir PEG-IFN Ribavirin Sofusbuvir PEG-IFN Adefovir Supportive Ribavirin if chronic The Peer Teaching Society is not liable for false or misleading information…
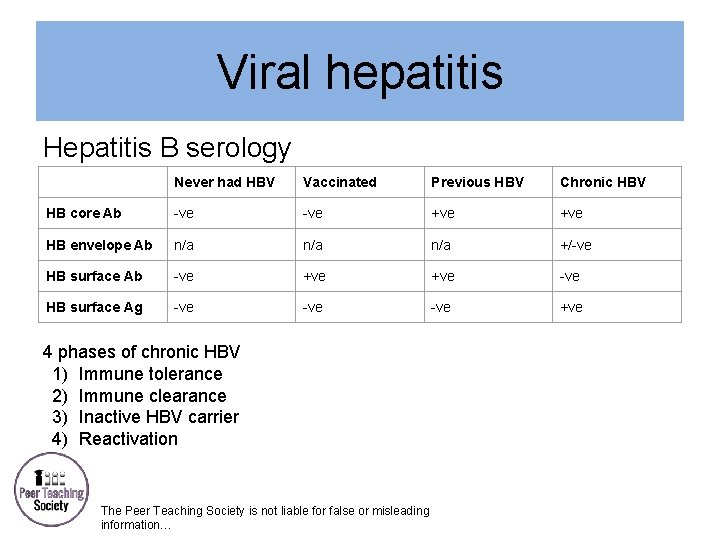
Viral hepatitis Hepatitis B serology Never had HBV Vaccinated Previous HBV Chronic HBV HB core Ab -ve +ve HB envelope Ab n/a n/a +/-ve HB surface Ab -ve +ve -ve HB surface Ag -ve -ve +ve 4 phases of chronic HBV 1) Immune tolerance 2) Immune clearance 3) Inactive HBV carrier 4) Reactivation The Peer Teaching Society is not liable for false or misleading information…
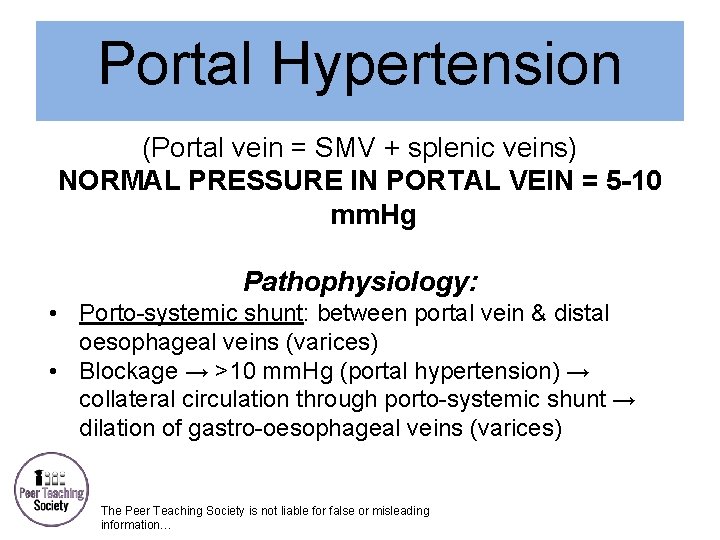
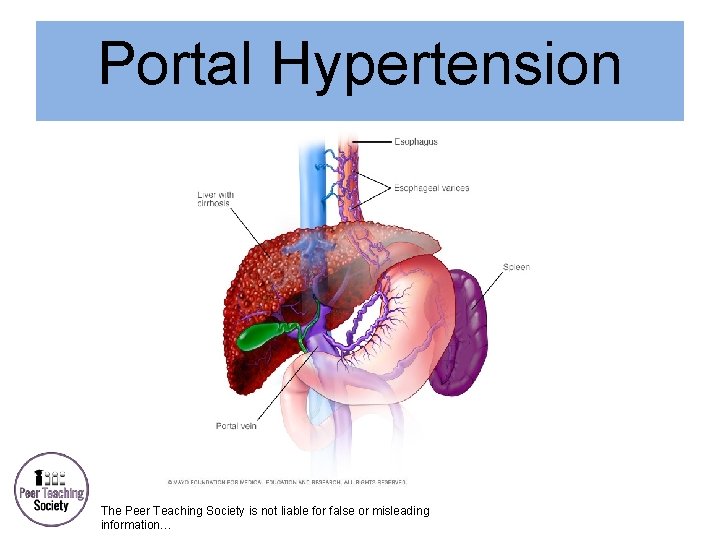
Portal Hypertension (Portal vein = SMV + splenic veins) NORMAL PRESSURE IN PORTAL VEIN = 5 -10 mm. Hg Pathophysiology: • Porto-systemic shunt: between portal vein & distal oesophageal veins (varices) • Blockage → >10 mm. Hg (portal hypertension) → collateral circulation through porto-systemic shunt → dilation of gastro-oesophageal veins (varices) The Peer Teaching Society is not liable for false or misleading information…
Portal Hypertension The Peer Teaching Society is not liable for false or misleading information…
Oesophago-gastric Varices Dilated veins at the gastro-oesophageal junction due to increased blood flow through the porto -systemic shunt Symptoms ● Haematemesis/melaena ● Abdominal pain ● Dysphagia/odynophagia Signs ● Anaemia ● Signs of liver disease Investigations • Endoscopy • Bloods: FBC, U&E, LFT • CXR: for aspiration or chest infection • Check for portal hypertension Treatment • Blood transfusion if severe blood loss • Correct clotting abnormalities - vit K, fresh frozen plasma, platelet transfusion • IV terlipressin • Therapeutic endoscopy - variceal ligation/banding/sclerotherapy The Peer Teaching Society is not liable for false or misleading information…
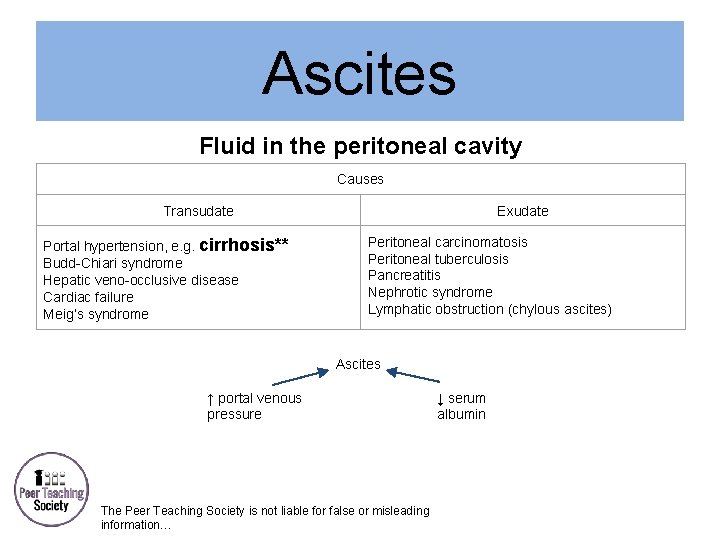
Ascites Fluid in the peritoneal cavity Causes Transudate Portal hypertension, e. g. cirrhosis** Budd-Chiari syndrome Hepatic veno-occlusive disease Cardiac failure Meig’s syndrome Exudate Peritoneal carcinomatosis Peritoneal tuberculosis Pancreatitis Nephrotic syndrome Lymphatic obstruction (chylous ascites) Ascites ↑ portal venous pressure The Peer Teaching Society is not liable for false or misleading information… ↓ serum albumin
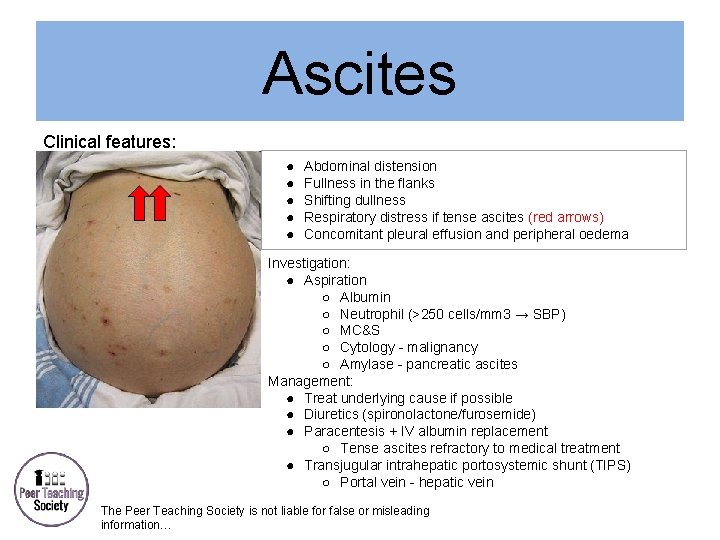
Ascites Clinical features: ● ● ● Abdominal distension Fullness in the flanks Shifting dullness Respiratory distress if tense ascites (red arrows) Concomitant pleural effusion and peripheral oedema Investigation: ● Aspiration ○ Albumin ○ Neutrophil (>250 cells/mm 3 → SBP) ○ MC&S ○ Cytology - malignancy ○ Amylase - pancreatic ascites Management: ● Treat underlying cause if possible ● Diuretics (spironolactone/furosemide) ● Paracentesis + IV albumin replacement ○ Tense ascites refractory to medical treatment ● Transjugular intrahepatic portosystemic shunt (TIPS) ○ Portal vein - hepatic vein The Peer Teaching Society is not liable for false or misleading information…
Spontaneous Bacterial Peritonitis (SBP) Most commonly: E. coli Ascitic patient who deteriorates suddenly → ? SBP • Mortality rate 10 -15% Ascitic neutrophil (>250 cells/mm 3 → SBP) Management: • 3 rd cephalosporin (IV cefotaxime) or tazocin +/- metronidazole • Prophylaxis: – PO norfloxacin The Peer Teaching Society is not liable for false or misleading information…
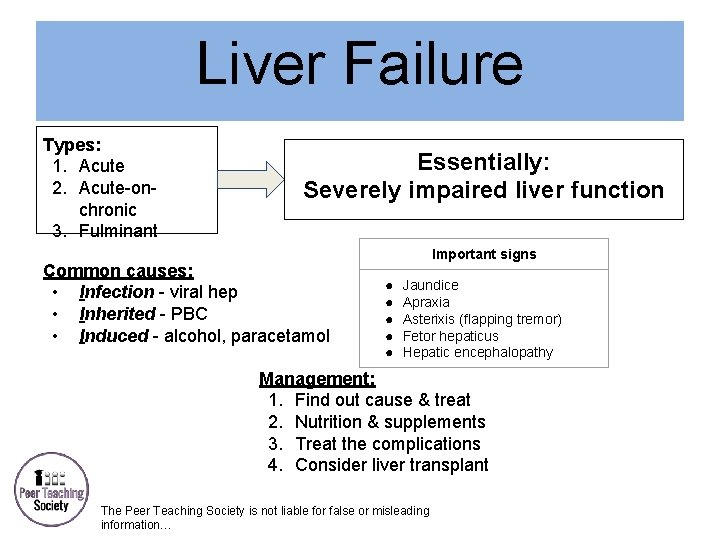
Liver Failure Types: 1. Acute 2. Acute-onchronic 3. Fulminant Essentially: Severely impaired liver function Common causes: • Infection - viral hep • Inherited - PBC • Induced - alcohol, paracetamol Important signs ● ● ● Jaundice Apraxia Asterixis (flapping tremor) Fetor hepaticus Hepatic encephalopathy Management: 1. Find out cause & treat 2. Nutrition & supplements 3. Treat the complications 4. Consider liver transplant The Peer Teaching Society is not liable for false or misleading information…
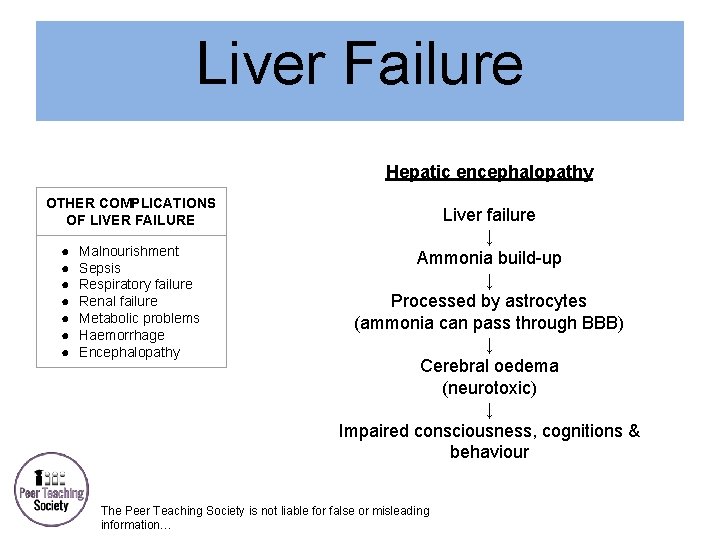
Liver Failure Hepatic encephalopathy OTHER COMPLICATIONS OF LIVER FAILURE ● ● ● ● Malnourishment Sepsis Respiratory failure Renal failure Metabolic problems Haemorrhage Encephalopathy Liver failure ↓ Ammonia build-up ↓ Processed by astrocytes (ammonia can pass through BBB) ↓ Cerebral oedema (neurotoxic) ↓ Impaired consciousness, cognitions & behaviour The Peer Teaching Society is not liable for false or misleading information…
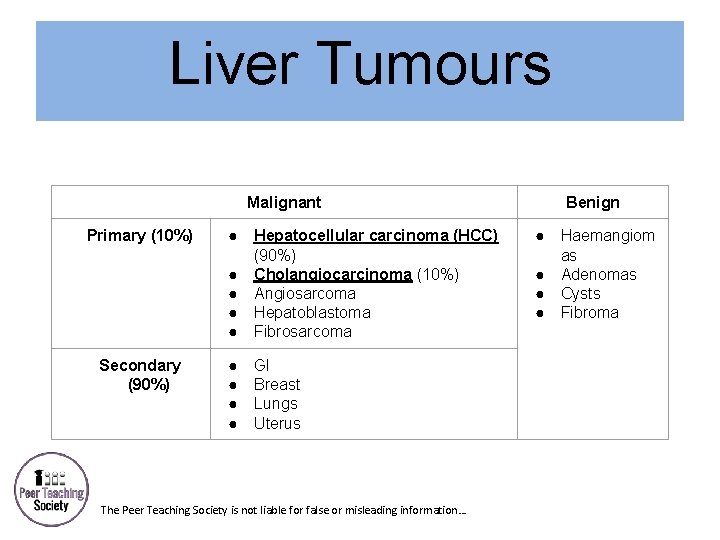
Liver Tumours Malignant Primary (10%) Secondary (90%) ● Hepatocellular carcinoma (HCC) (90%) ● Cholangiocarcinoma (10%) ● Angiosarcoma ● Hepatoblastoma ● Fibrosarcoma ● ● GI Breast Lungs Uterus The Peer Teaching Society is not liable for false or misleading information… Benign ● Haemangiom as ● Adenomas ● Cysts ● Fibroma
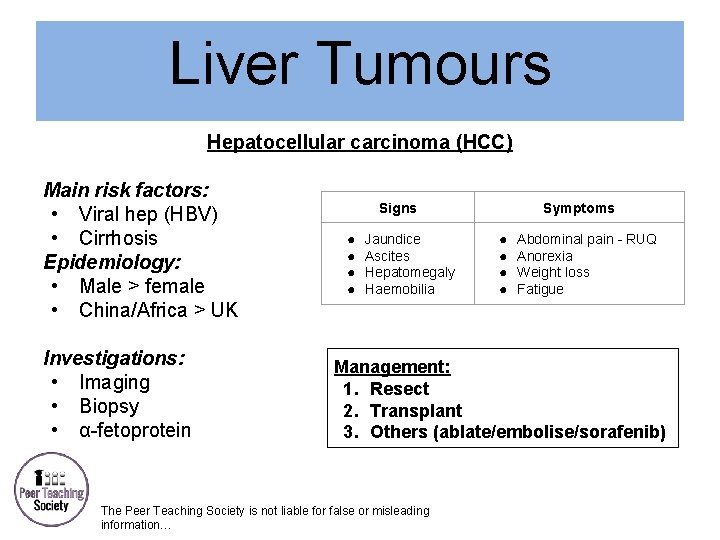
Liver Tumours Hepatocellular carcinoma (HCC) Main risk factors: • Viral hep (HBV) • Cirrhosis Epidemiology: • Male > female • China/Africa > UK Investigations: • Imaging • Biopsy • α-fetoprotein Signs ● ● Jaundice Ascites Hepatomegaly Haemobilia Symptoms ● ● Abdominal pain - RUQ Anorexia Weight loss Fatigue Management: 1. Resect 2. Transplant 3. Others (ablate/embolise/sorafenib) The Peer Teaching Society is not liable for false or misleading information…
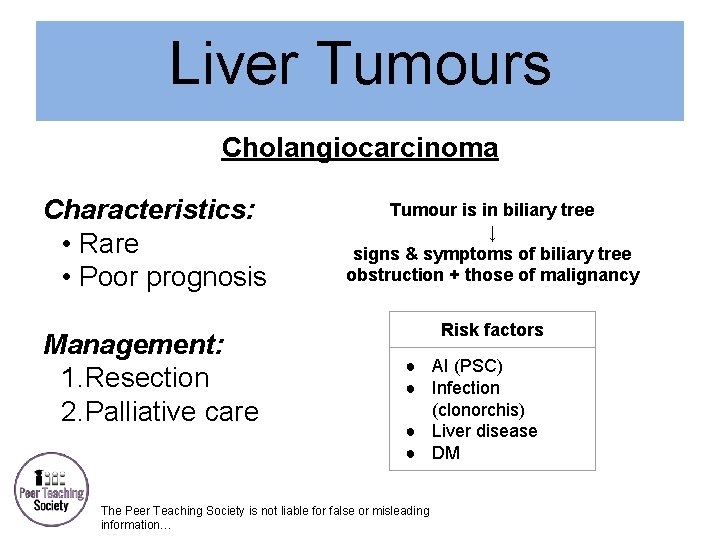
Liver Tumours Cholangiocarcinoma Characteristics: • Rare • Poor prognosis Tumour is in biliary tree ↓ signs & symptoms of biliary tree obstruction + those of malignancy Management: 1. Resection 2. Palliative care Risk factors ● AI (PSC) ● Infection (clonorchis) ● Liver disease ● DM The Peer Teaching Society is not liable for false or misleading information…
One Last Point Q: What tests would you do to assess the function of the liver? A: Albumin and INR! NOT LFT. The Peer Teaching Society is not liable for false or misleading information…