The Role of POLST in Advance Care Planning






































- Slides: 50
The Role of POLST in Advance Care Planning Richard W. Cohen MD
Financial Disclosure This presenter has no financial interests or relationships to disclose 2
Dying in America: Improving Quality and Honoring Individual Preferences Near the End of Life “The IOM committee believes a person-centered, familyoriented approach that honors individual preferences and promotes quality of life through the end of life should be a national priority. ” http: //www. iom. edu/Reports/2014/Dying-In-America. Improving-Quality-and. Honoring-Individual-Preferences-Near-the-End-of. Life. aspx SEPTEMBER 2014 3
END-OF-LIFE DEMOGRAPHICS IN THE U. S. • The majority of deaths occur in elderly adults • Seriously ill patients spend most of their final months at home, but most deaths occur in the hospital or nursing home • Location of death varies regionally: • Portland: 35% in hospitals • New York City: >70% in hospitals 4
QUALITY OF END-OF-LIFE IN THE U. S. Typical deaths are: • slow, associated with chronic disease and in persons with multiple problems • marked by dependency and care needs 5
QUALITY OF END-OF-LIFE IN THE U. S. Quality of life during the dying process is often poor because of: • inadequate treatment of distress • fragmented care • strains on family, support system Difficult decisions about use of life-prolonging treatments are commonly necessary 6
One conversation can make all the difference • 70% of people say they prefer to die at home yet 70% die in a hospital, nursing home, or long-termcare facility (Centers for Disease Control, 2005) • 82% of people say it’s important to put their wishes in writing ; 23% have actually done it (Survey of Californians by the California Health. Care Foundation, 2012) • 80% of people say that if seriously ill, they would want to talk to their doctor about end-of-life care; 7% report having had an end-of-life conversation with their doctor (Survey of Californians by the California Health. Care Foundation, 2012) 7
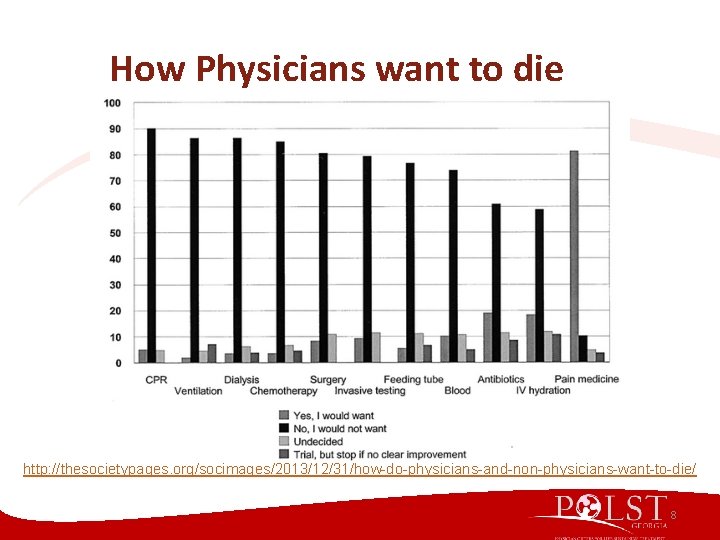
How Physicians want to die http: //thesocietypages. org/socimages/2013/12/31/how-do-physicians-and-non-physicians-want-to-die/ 8
End-of-Life Principles End-Of-Life Care Is About: • Compassion at the bedside • Providing comfort • Honoring patients’ preferences
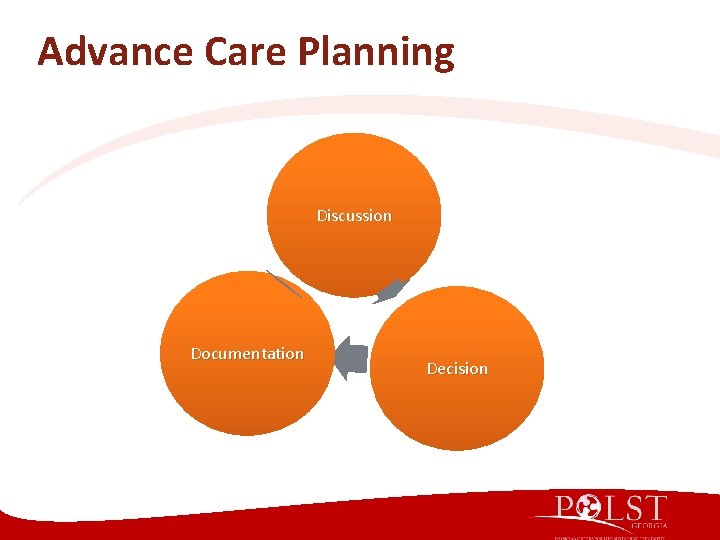
Advance Care Planning "Advance Care Planning Is Not An Event, It's A Process. " - Susan Tolle, Director of the Center for Ethics in Health Care at Oregon Health & Science University 10 10
Advance Care Planning Discussion Documentation Decision
When Should Advance Care Planning Happen? While individuals are still actively able to participate in the conversation prior to a crisis “Planning is important! It wasn’t raining when Noah started the ark. ” ~ Richard Cushing
Advance Care Planning Talk with the patient Have the surrogate (proxy) there Try to discern: • If the patient understands his/her situation • What is most important to him/her now • If the patient understands his/her choices • Discussion of trade-offs and goals of care • Use “compassionate honesty”
Gold Standard Discussing and following a patient’s preferences for end-of-life care should be as routine as asking about and responding to a patient’s allergies to medicines
Right to Refuse Medical Treatments § In Georgia, a competent adult has the right to refuse any unwanted medical treatment for any reason § Right to refuse medical treatments includes life support and other lifesustaining treatments § The right to refuse or terminate treatments may be exercised by family members or loved ones
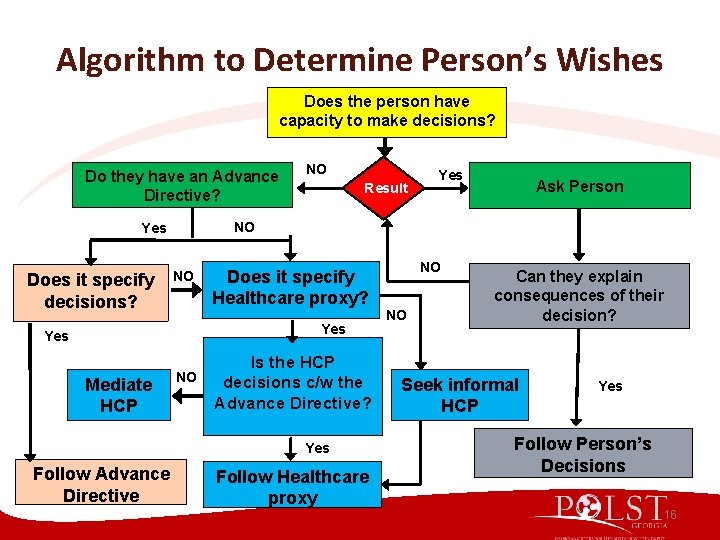
Algorithm to Determine Person’s Wishes Does the person have capacity to make decisions? Do they have an Advance Directive? Result NO Does it specify Healthcare proxy? Yes Mediate HCP NO Is the HCP decisions c/w the Advance Directive? Yes Follow Advance Directive Yes Ask Person NO Yes Does it specify decisions? NO Follow Healthcare proxy NO NO Can they explain consequences of their decision? Seek informal HCP Yes Follow Person’s Decisions 16
History • It is a National movement • Advance Directive • POLST • The Conversation • It is a State movement • Georgia Health Decision • Georgia POLST Collaborative
Tools For Advance Care Planning These are now all part of the Ga. 2007 AD law Living Will § Specifies what kind of treatment should be given if you cannot speak for yourself § Only effective when you cannot make decisions Durable Power of Attorney for Health Care § Allows an agent to be appointed to carry out health care decisions when you cannot Guardianship § Allows you to nominate someone to be appointed as Guardian if a court rules that a guardian is necessary
Georgia Advance Directive for Health Care In 2007, Georgia Law combined all three advance care planning tools into one document: § Naming a health care agent § Stating treatment preferences § Nominating a guardian (if a court rules that a guardian is necessary) Also includes: § Authorizing organ donation, autopsy, burial Legal with: § Patient signature & 2 witnesses http: //ngoc. com/wp-content/uploads/ELAP-GEORGIA-ADVANCE-DIRECTIVE-2012. pdf
POLST Physician Orders for Life Sustaining Treatment • Medical order completed by a health care provider – Requires signatures by the patient or patient’s authorized representative AND a physician • Activates a patient’s Advance directive • Mechanism to communicate a patient’s wishes for their care at the end of their life • Designed to travel with patient from one care setting to another • Must be honored by all health care professionals
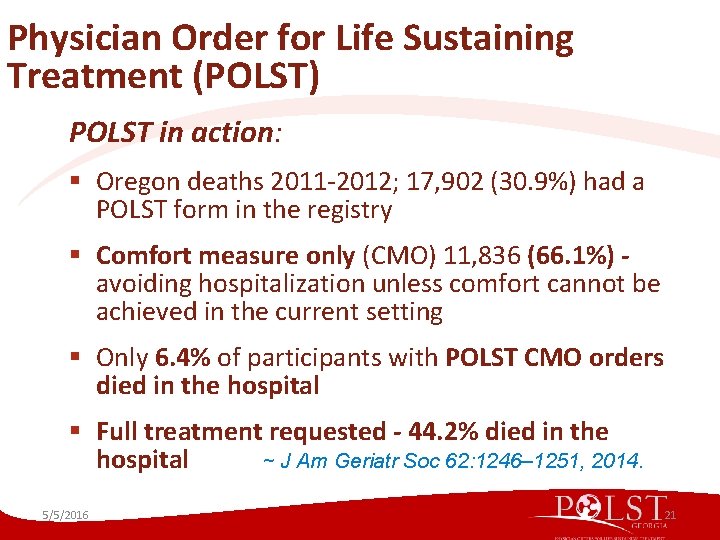
Physician Order for Life Sustaining Treatment (POLST) POLST in action: § Oregon deaths 2011 -2012; 17, 902 (30. 9%) had a POLST form in the registry § Comfort measure only (CMO) 11, 836 (66. 1%) avoiding hospitalization unless comfort cannot be achieved in the current setting § Only 6. 4% of participants with POLST CMO orders died in the hospital § Full treatment requested - 44. 2% died in the hospital ~ J Am Geriatr Soc 62: 1246– 1251, 2014. 5/5/2016 21
Who Should Have a POLST? § Anyone who wants their end-of-life decisions honored § Anyone choosing “Allow Natural Death” or DNR § Anyone choosing to limit or not limit medical interventions § Anyone residing in a long term care facility § Anyone who might die or lose decisionmaking capacity within the next year
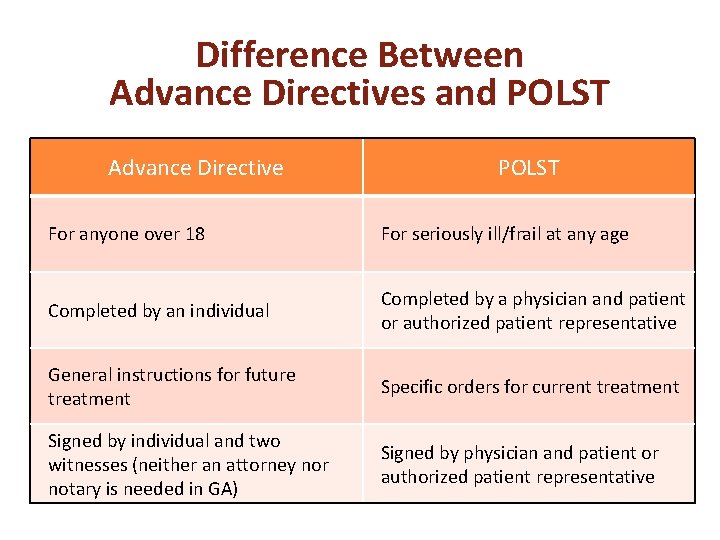
Difference Between Advance Directives and POLST Advance Directive POLST For anyone over 18 For seriously ill/frail at any age Completed by an individual Completed by a physician and patient or authorized patient representative General instructions for future treatment Specific orders for current treatment Signed by individual and two witnesses (neither an attorney nor notary is needed in GA) Signed by physician and patient or authorized patient representative
Georgia Legal Foundations § GA Advance Directive § Ga. AD Law - 2007 HB 24 § Ga. Dept. Of Human Resources (2007 HB 24 Rules And Regulations) § Ga. Code 31 -39 DNR/AND & Cardiopulmonary Resuscitation Laws § GA Physician Order For Life Sustaining Treatment (POLST) • Ga. DPH, POLST Form, 2012 • SB 109 2015
SB 109 • A Legally Sufficient Order In • All Settings • Valid Consent • Unless Revoked • From Another State • If substantially similar & with the same signatures • A Copy
SB 109 • Portable Across Care Settings • Review of form recommended as care transitions • Immunity For All, including guardian actions • Protections for treating pain • Except if violates Code Section 16 -5 -5 • Assisted Suicide
SB 109 • Equates Terms DNR=AND etc. • All conflicting laws or parts are repealed • Most recent document is the valid one
Georgia POLST Form § Developed by the Georgia Department of Public Health in 2012 pursuant to Official Code of Georgia Section 29 -418(l) § Available at www. gapolst. org § Use and compliance with POLST form provides immunity to any “person” acting in good faith (2015)
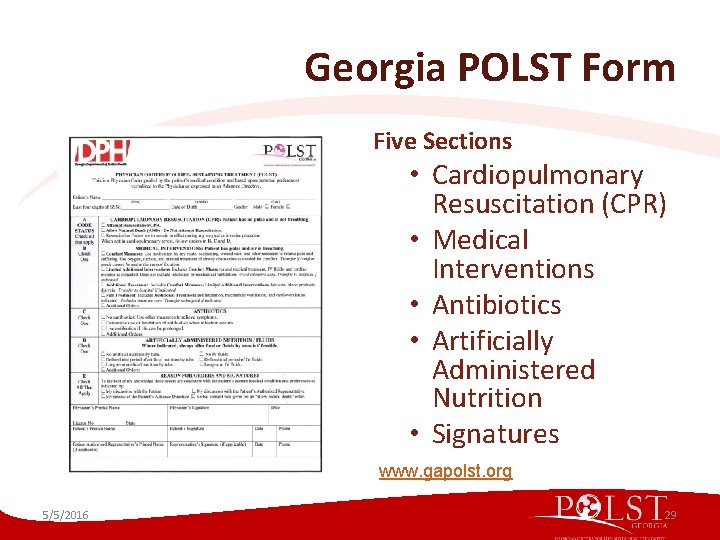
Georgia POLST Form Five Sections • Cardiopulmonary Resuscitation (CPR) • Medical Interventions • Antibiotics • Artificially Administered Nutrition • Signatures www. gapolst. org 5/5/2016 29
Signatures • Two Required • Patient & Physician OR • Authorized Person / Healthcare Advocate & Physician OR • Two physicians • Remember • Physician must be on the staff of the institution honoring the POLST
POLST Conversation • POLST is not just a check-box form • The POLST conversation provides context for patients/families to: ⁻ Make informed decisions ⁻ Identify goals of treatment • A patient or their Health Care Agent can request alternative treatment or revoke a POLST at any time
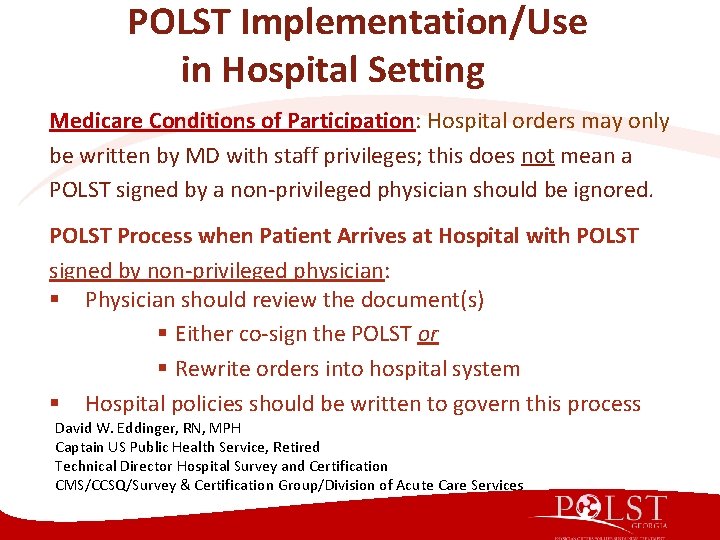
POLST Implementation/Use in Hospital Setting Medicare Conditions of Participation: Hospital orders may only be written by MD with staff privileges; this does not mean a POLST signed by a non-privileged physician should be ignored. POLST Process when Patient Arrives at Hospital with POLST signed by non-privileged physician: § Physician should review the document(s) § Either co-sign the POLST or § Rewrite orders into hospital system § Hospital policies should be written to govern this process David W. Eddinger, RN, MPH Captain US Public Health Service, Retired Technical Director Hospital Survey and Certification CMS/CCSQ/Survey & Certification Group/Division of Acute Care Services
Admission to Long-Term Care (LTC) Facility Identify or determine: Health Care Advocate’s name • Patient’s medical state • Code status based on: • — Patient’s wishes and/or — When, in the judgment of a physician, Either: — A patient is in a terminal condition — A patient is in a permanent state of unconsciousness — In medical judgment CPR would be medically inappropriate O. C. G. A. 31 -39 -4 (2010)
Health Care Team Responsibilities in ALL Healthcare Settings §To follow the patient’s known preferences §To honor the patient’s Advance Directive and POLST without regard to personal views §If unable to honor preferences, facilitate the transfer of patient’s care 5/5/2016 34
Healthcare Agent / Authorized Person Must be named in either • Advance Directive • POA Responsibilities: • To follow the patient’s known preferences • To honor the patient’s Advance Directive and POLST • To act in the best interest of the patient 35
My Vision 5/5/2016 36
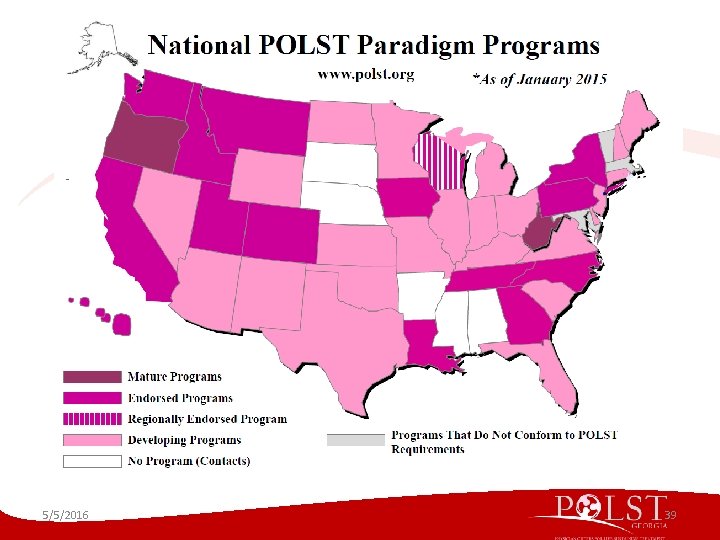
Georgia POLST Collaborative § 40+ Statewide Organizations § Part of a national movement to promote POLST § Endorsed by the National POLST Paradigm Taskforce § Vision: All Georgians will have their health care preferences known and honored
5/5/2016 39
Georgia POLST Collaborative (cont’d) § Mission: To improve health care at the end-of-life through ─ Promoting the utilization of the Physician Orders for Life Sustaining Treatment form by health care professionals and institutions across the state ─ Educating Georgians about advance care planning and the role of POLST in having their wishes honored
‘Getting it Right’ § Honor all patients wishes § Encourage all patients to have an Advance Care Plan § Utilize POLST when patient condition applies § Apply reasonable medical judgment
Additional Resources
Critical Conditions Guide http: //georgiahealthdeci sions. org/store. html
Prepare For Your Care Step 1: Choose a Medical Decision Maker Step 2: Decide What Matters Most in Life Step 3: Choose Flexibility for Your Decision Maker Step 4: Tell Others About Your Wishes Step 5: Ask Doctors the Right Questions http: //prepareforyourcare. org/
Conversation Project § Veteran Boston journalist Ellen Goodman § Launched in August 2012 § Backing from the Institute for Healthcare Improvement www. theconversationproject. org
“Conversation Project” Goodman, who launched her project after a difficult experience caring for her own dying mother, says, "What we really need is to change the cultural norm from not talking about it to talking about it. "
“Let’s Have Dinner and Talk About Death” • Michael Hebb • TED Talk • “Death Over Dinner. org • Three Question • What do we want our final days to look like? • Who do we want to be nears us? • How can we support the E-O-L wishes of those closest to us?
POLST Websites • Critical Conditions Planning Guide • www. critical-conditions. org • www. gapolst. org • www. dph. ga. gov/POLST • www. polst. org • www. capolst. org/documents/POLSTFAQ
References CDC (2005). NCHS, National Vital Statistics System, Mortality. Accessed on Nov. 26, 2014 at: http: //www. cdc. gov/nchs/data/dvs/Mortfinal 2005_worktable_309. pdf Survey of Californians by the California Health. Care Foundation. (2012). Accessed on Nov. 26, 2014 at: http: //www. chcf. org/~/media/MEDIA%20 LIBRARY%20 Files/PDF/F/PDF%20 Final. Chapter. Death. Dying. pdf Hale, J. (2013). “Making Choices: Honoring Wishes. ” Well. Star Ethics Department. Louisiana Physician Orders for Scope of Treatment. n. d. Guide to Advance Care Planning. http: //www. polst. org/wp-content/uploads/2012/12/La. POST-Guide-to-Advance-Care-Planning. pdf GA Department of Human Resources. (2007). Georgia Advance Directive for Health Care. http: //aging. dhr. georgia. gov/sites/aging. dhs. georgia. gov/files/imported/DHRDAS/GEORGIA%20 ADVANC E%20 DIRECTIVE%20 FOR%20 HEALTH%20 CARE-07. pdf West Virginia Center for End-of-Life Care. (2012). Using the POST Form: Guidance for Healthcare Professionals. http: //www. polst. org/wp-content/uploads/2013/01/POST-Manual-2012 -complete. pdf Heerema, E. (2013). Antibiotic Use in Advanced Dementia. About. com Alzheimer’s/Dementia. http: //alzheimers. about. com/od/latestagealzheimers/a/Antibiotic-Use-In-Advanced-Dementia. htm Coalition for Compassionate Care of California. (2011). Introducing the POLST. http: //www. youtube. com/watch? feature=player_embedded&v=Fj. Ur. I 1 Ns. M-M American Geriatric Society Geriatric Review Syllabus Teaching Slide-set
50