Mr Kim Son Lett Consultant Ophthalmologist VitreoRetinal Surgeon









- Slides: 48
Mr. Kim Son Lett Consultant Ophthalmologist & Vitreo-Retinal Surgeon Birmingham & Midland Eye Centre & BMI The Priory
Pre-Triage System § Red Need to be seen within a few hrs, further triaging. § Amber Need to be seen within 72 hrs, diverted to UCC slots. § Green No need for urgent assessment, referred to GP, optometrist or to OPD (via GP). v
Red – Very Urgent § § § Penetrating eye injury Acute post-op endophthalmitis Severe chemical injury Orbital cellulitis GCA with visual symptoms Sudden loss of vision <6 hrs v
Red - Urgent § § § Painful red eye with visual loss Retinal detachment with good VA Corneal ulcer, esp. with CL wear Blunt trauma with hyphaema & ↑ IOP Corneal graft rejection Painful diplopia v
Amber § § § Flashes & floaters, no loss of vision Red eye without pain or visual loss Retinal vein occlusions (OPD 4 -6/52) Diabetic retinopathy with vitreous haemorrhage Wet AMD (preferably refer to Fast Track Macular Clinic) v
Green – GP / Optometrist Mx § § § Bacterial & viral conjunctivitis Allergic conjunctivitis Blepharitis Dry eyes Lid lumps and bumps v
Green – OPD Referral § § § § Cataract Chronic / gradual visual loss (months) Open angle glaucoma, ocular hypertension Watery eyes Ectropion, entropion Lid lumps & bumps v Non-acute diplopia
Trauma § Burns § Acid, alkali, thermal, arc eye § Abrasions & lacerations § Lid, corneal and conjunctival, Penetrating Eye Injuries § Foreign bodies § Corneal, conjunctival, sub-tarsal, intra-ocular § Blunt trauma v § Sub-conjunctival haemorrhage, hyphaema, choroidal rupture § Orbital Blowout Fracture, Traumatic Optic Neuropathy
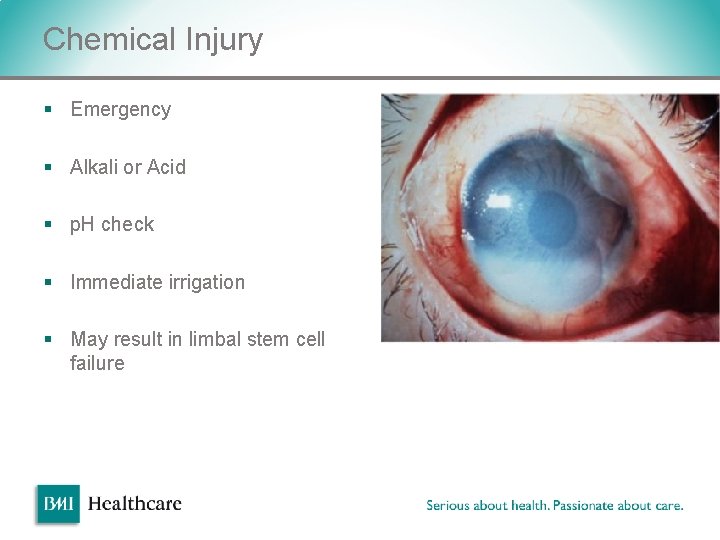
Chemical Injury § Emergency § Alkali or Acid § p. H check § Immediate irrigation v § May result in limbal stem cell failure
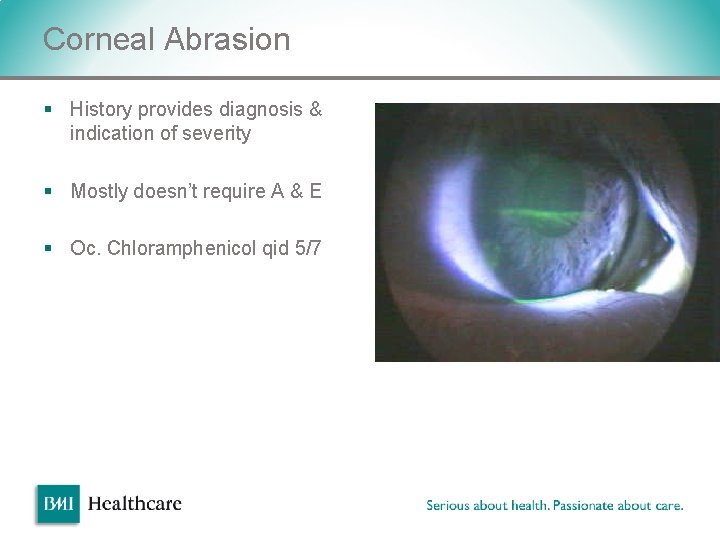
Corneal Abrasion § History provides diagnosis & indication of severity § Mostly doesn’t require A & E § Oc. Chloramphenicol qid 5/7 v
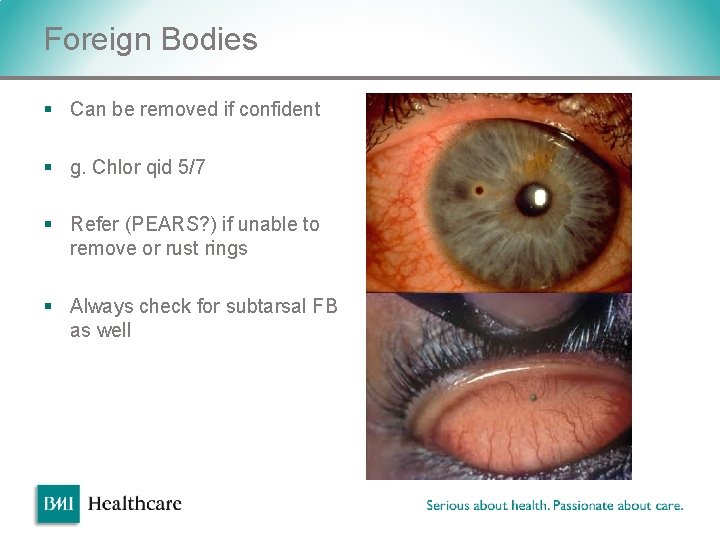
Foreign Bodies § Can be removed if confident § g. Chlor qid 5/7 § Refer (PEARS? ) if unable to remove or rust rings § Always check for subtarsal FB v as well
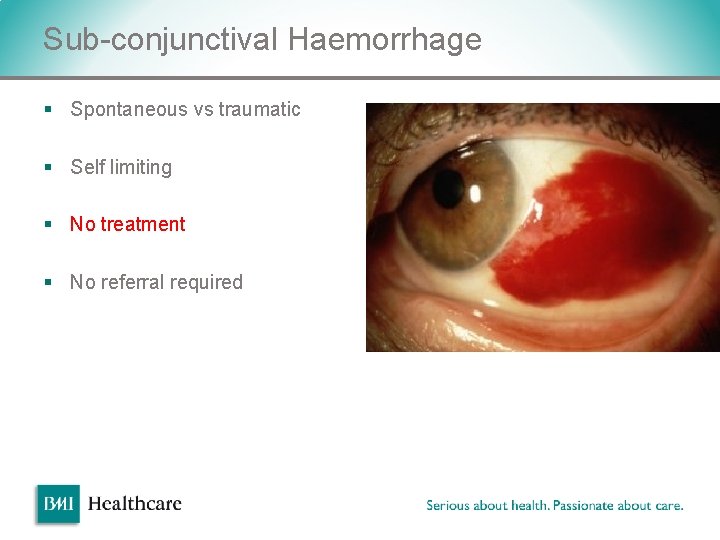
Sub-conjunctival Haemorrhage § Spontaneous vs traumatic § Self limiting § No treatment § No referral required v
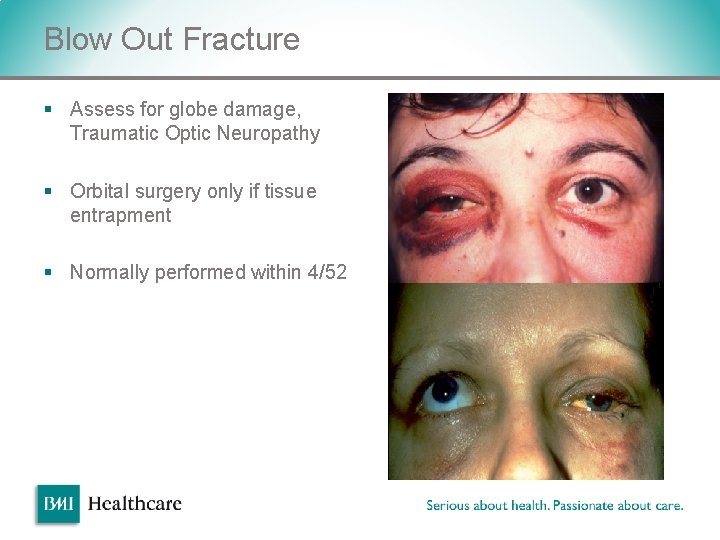
Blow Out Fracture § Assess for globe damage, Traumatic Optic Neuropathy § Orbital surgery only if tissue entrapment § Normally performed within 4/52 v
Cornea § Dry eye § Recurrent erosion syndrome § Ulcers § CL related § Acanthamoeba § Dendritic § Shingles v
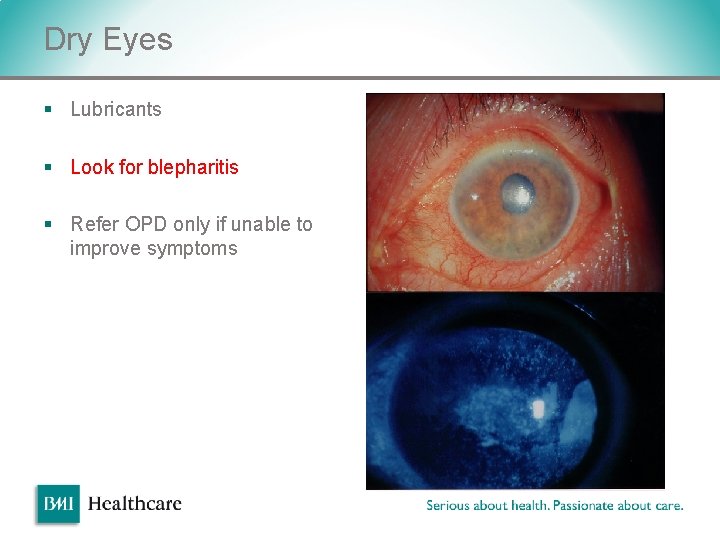
Dry Eyes § Lubricants § Look for blepharitis § Refer OPD only if unable to improve symptoms v
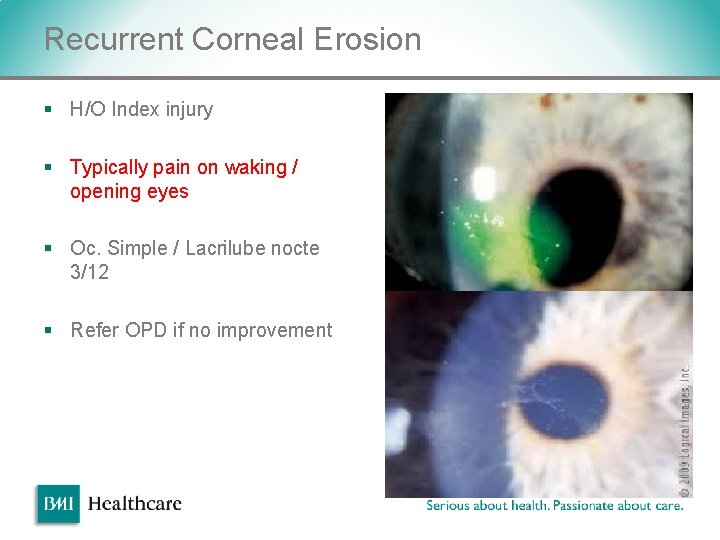
Recurrent Corneal Erosion § H/O Index injury § Typically pain on waking / opening eyes § Oc. Simple / Lacrilube nocte 3/12 § Refer OPD if no improvement v
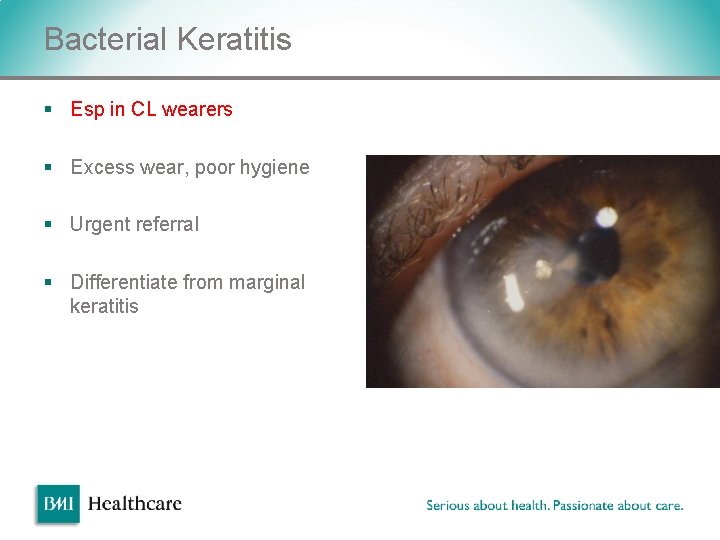
Bacterial Keratitis § Esp in CL wearers § Excess wear, poor hygiene § Urgent referral § Differentiate from marginal keratitis v
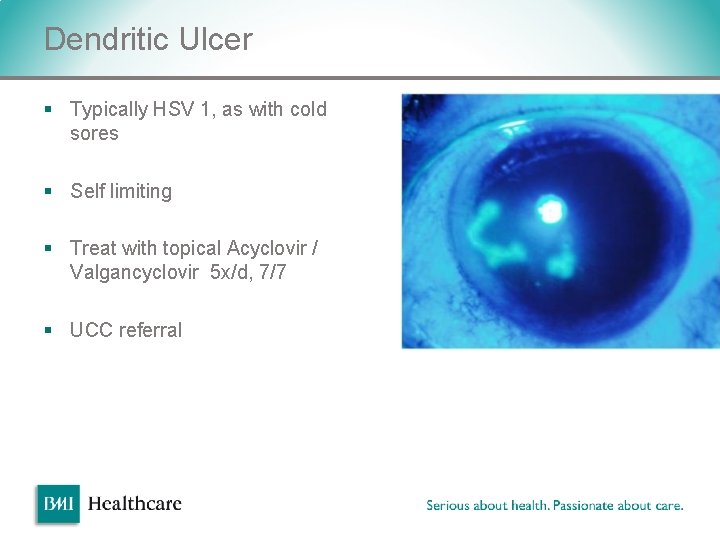
Dendritic Ulcer § Typically HSV 1, as with cold sores § Self limiting § Treat with topical Acyclovir / Valgancyclovir 5 x/d, 7/7 § UCC referral v
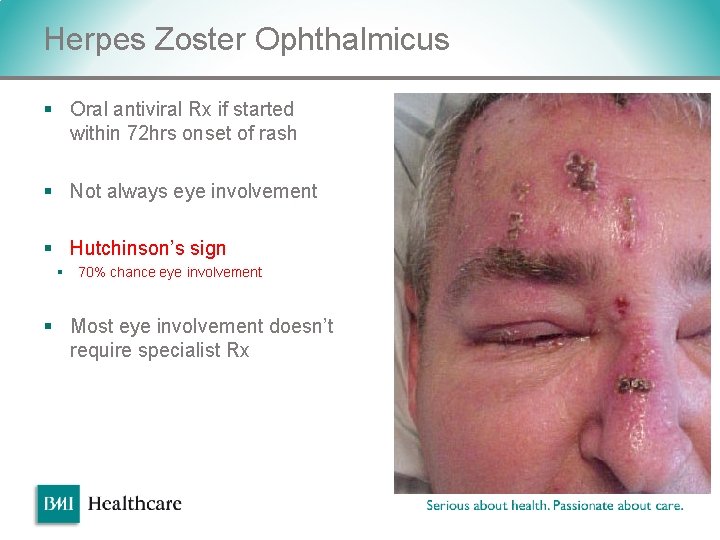
Herpes Zoster Ophthalmicus § Oral antiviral Rx if started within 72 hrs onset of rash § Not always eye involvement § Hutchinson’s sign § 70% chance eye involvement § Most eye involvement doesn’t require specialist Rx v
Conjunctiva § Conjunctivitis § Bacterial, viral, allergic § Episcleritis § Scleritis v
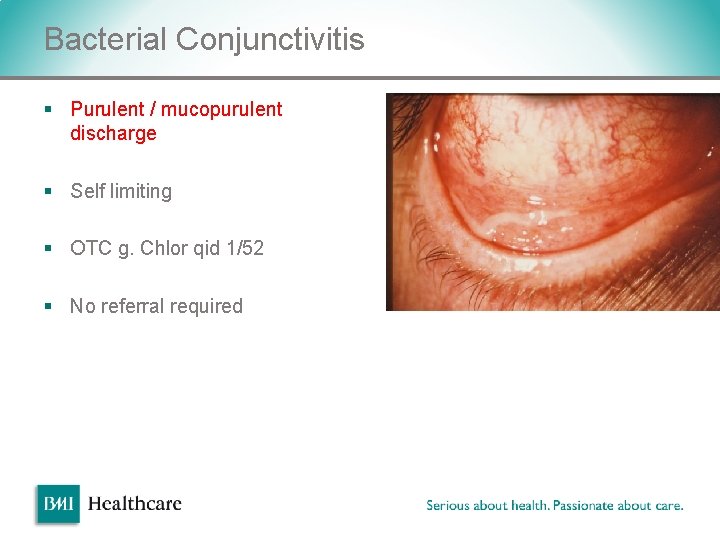
Bacterial Conjunctivitis § Purulent / mucopurulent discharge § Self limiting § OTC g. Chlor qid 1/52 § No referral required v
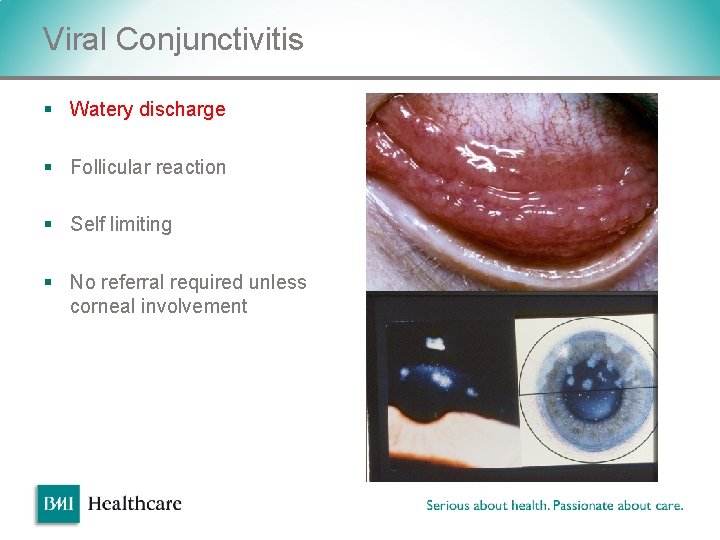
Viral Conjunctivitis § Watery discharge § Follicular reaction § Self limiting § No referral required unless corneal involvement v
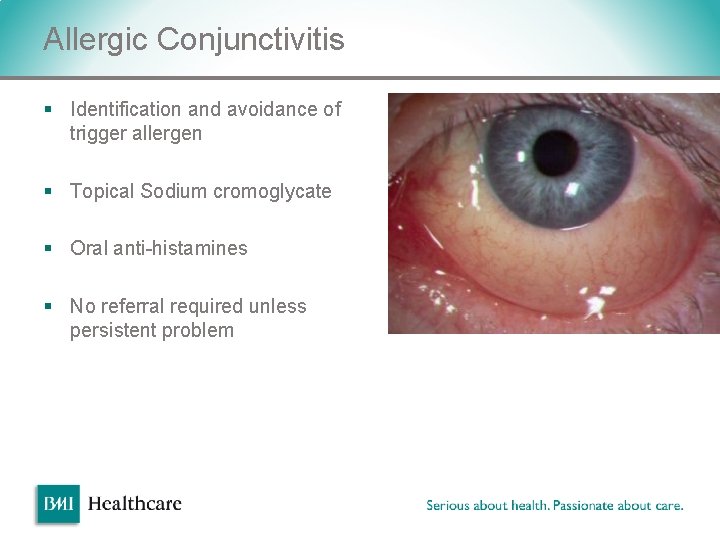
Allergic Conjunctivitis § Identification and avoidance of trigger allergen § Topical Sodium cromoglycate § Oral anti-histamines § No referral required unless persistent problem v
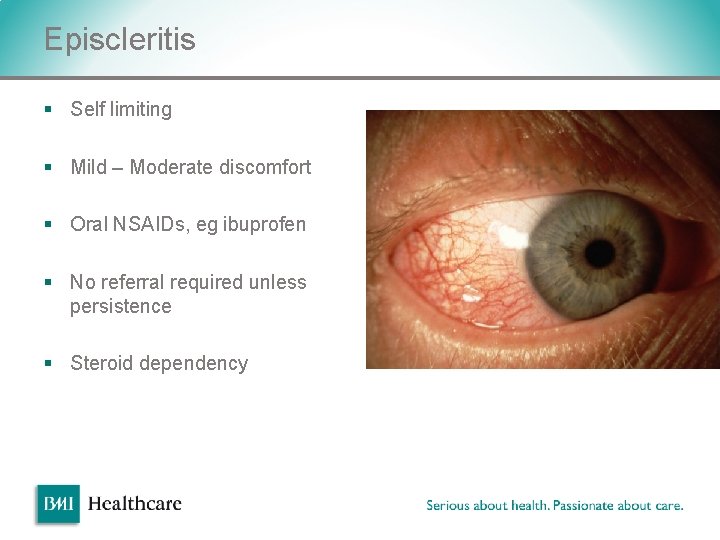
Episcleritis § Self limiting § Mild – Moderate discomfort § Oral NSAIDs, eg ibuprofen § No referral required unless persistence § Steroid dependency v
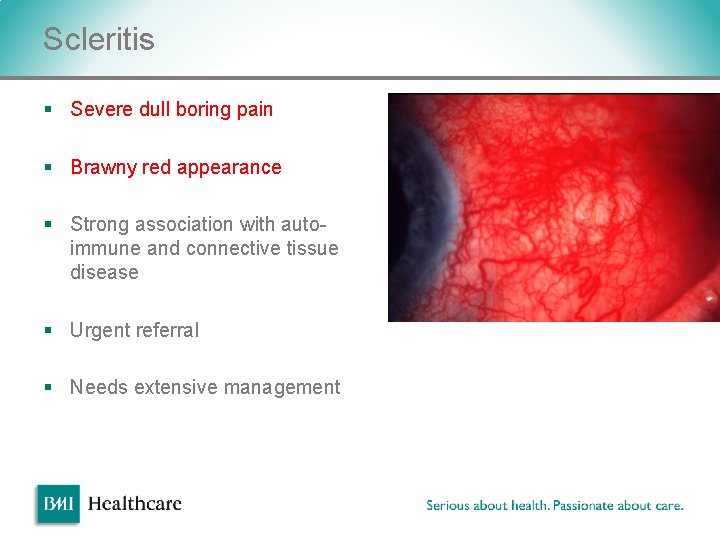
Scleritis § Severe dull boring pain § Brawny red appearance § Strong association with autoimmune and connective tissue disease § Urgent referral § Needs extensive management v
Lids § Blepharitis § Anterior, posterior § Chalazion, stye § Ectropion, entropion § Pre-septal cellulitis v
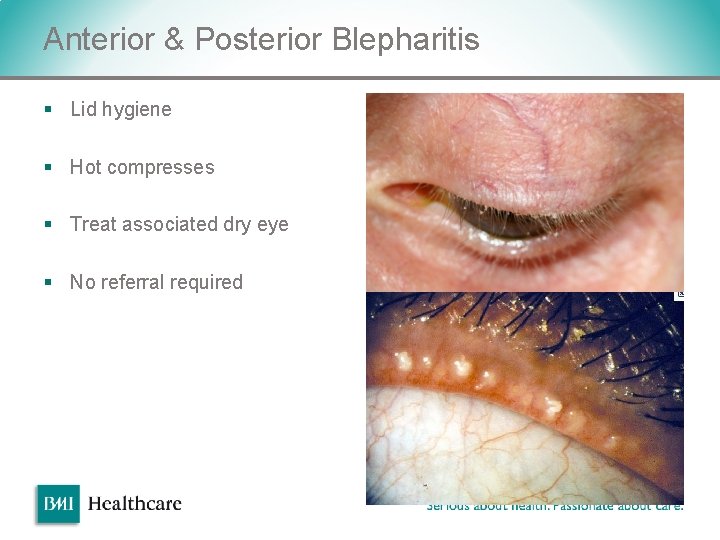
Anterior & Posterior Blepharitis § Lid hygiene § Hot compresses § Treat associated dry eye § No referral required v
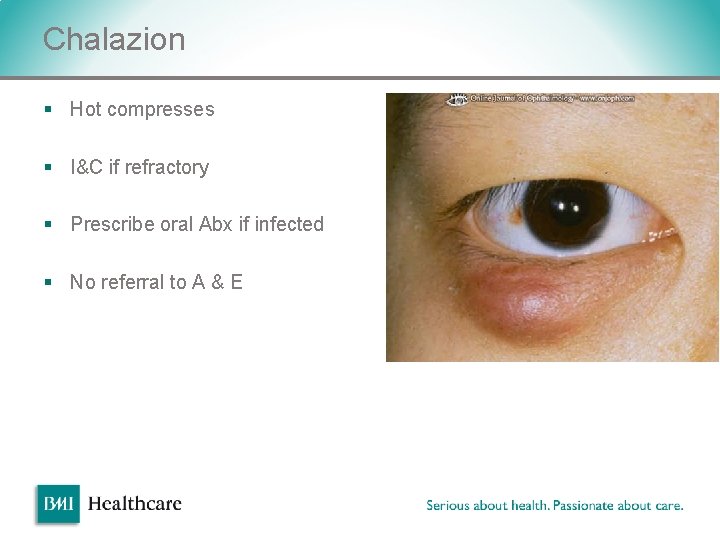
Chalazion § Hot compresses § I&C if refractory § Prescribe oral Abx if infected § No referral to A & E v
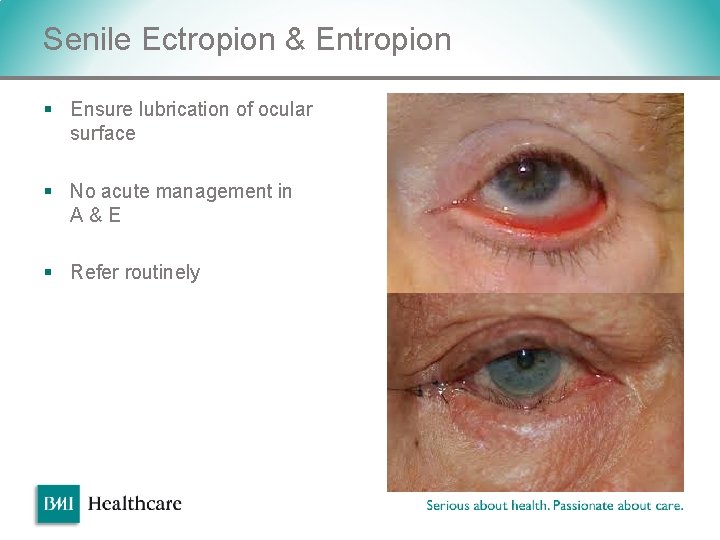
Senile Ectropion & Entropion § Ensure lubrication of ocular surface § No acute management in A&E § Refer routinely v
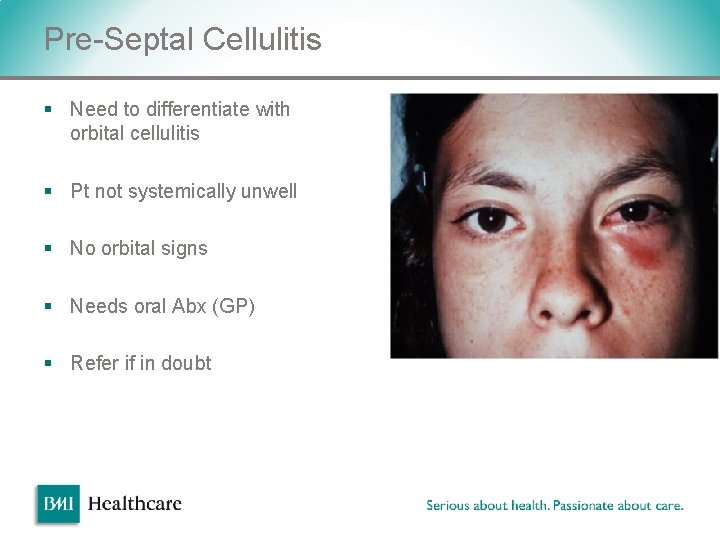
Pre-Septal Cellulitis § Need to differentiate with orbital cellulitis § Pt not systemically unwell § No orbital signs § Needs oral Abx (GP) § Refer if in doubt v
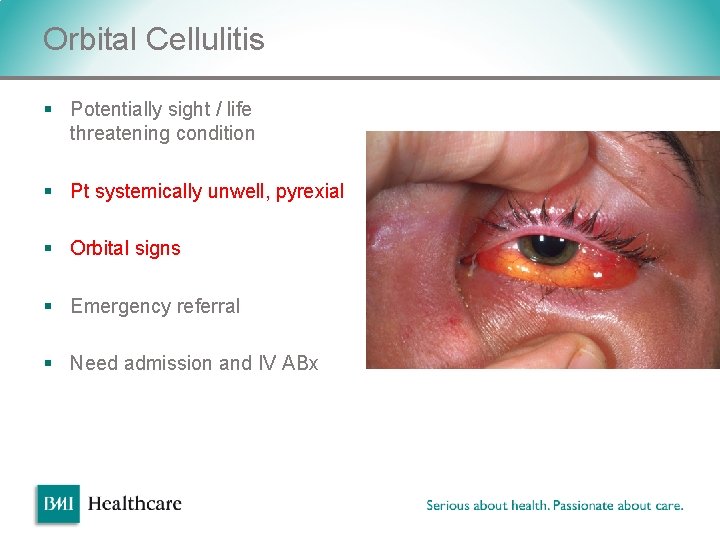
Orbital Cellulitis § Potentially sight / life threatening condition § Pt systemically unwell, pyrexial § Orbital signs § Emergency referral § Need admission and IV ABx v
Neuro-ophthalmology § § IIIrd, IVth, VIth nerve palsies Optic neuritis Papilloedema Giant cell arteritis v
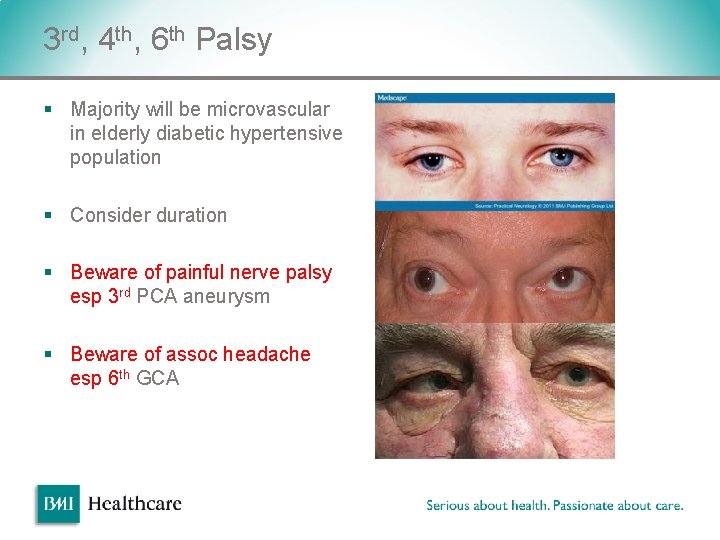
3 rd, 4 th, 6 th Palsy § Majority will be microvascular in elderly diabetic hypertensive population § Consider duration § Beware of painful nerve palsy esp 3 rd PCA aneurysm § Beware of assoc headache esp 6 th GCA v
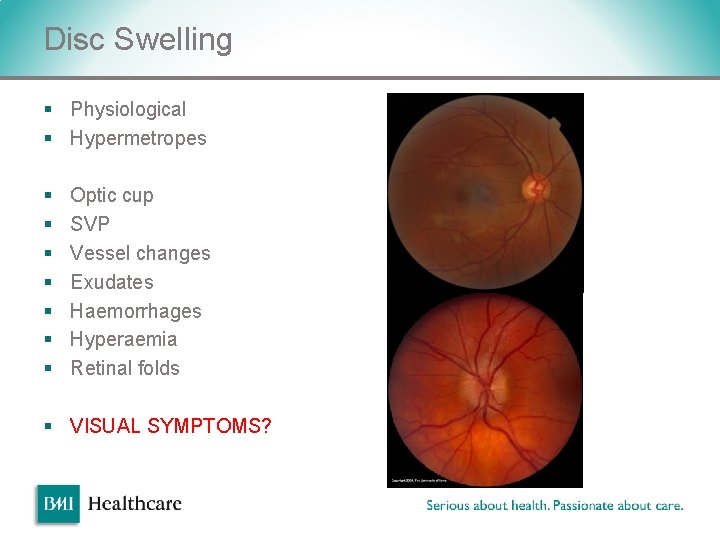
Disc Swelling § Physiological § Hypermetropes § § § § Optic cup SVP Vessel changes Exudates Haemorrhages Hyperaemia Retinal folds § VISUAL SYMPTOMS? v
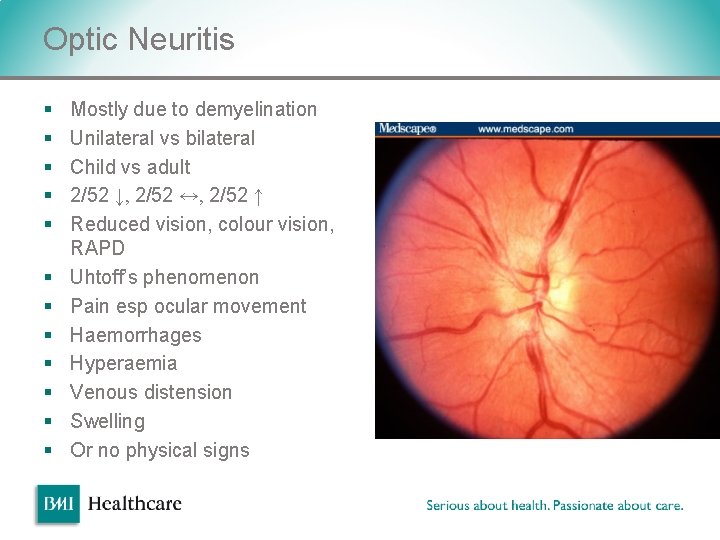
Optic Neuritis § § § Mostly due to demyelination Unilateral vs bilateral Child vs adult 2/52 ↓, 2/52 ↔, 2/52 ↑ Reduced vision, colour vision, RAPD Uhtoff’s phenomenon Pain esp ocular movement Haemorrhages Hyperaemia Venous distension Swelling Or no physical signs v
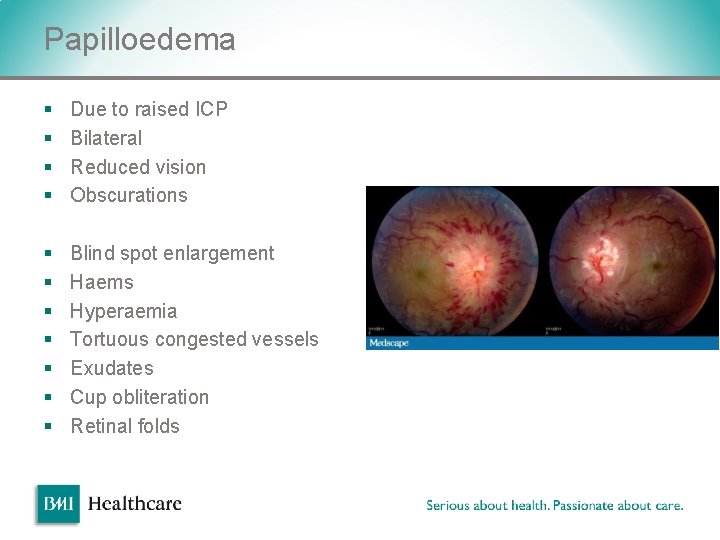
Papilloedema § § Due to raised ICP Bilateral Reduced vision Obscurations § § § § Blind spot enlargement Haems Hyperaemia Tortuous congested vessels Exudates Cup obliteration Retinal folds v
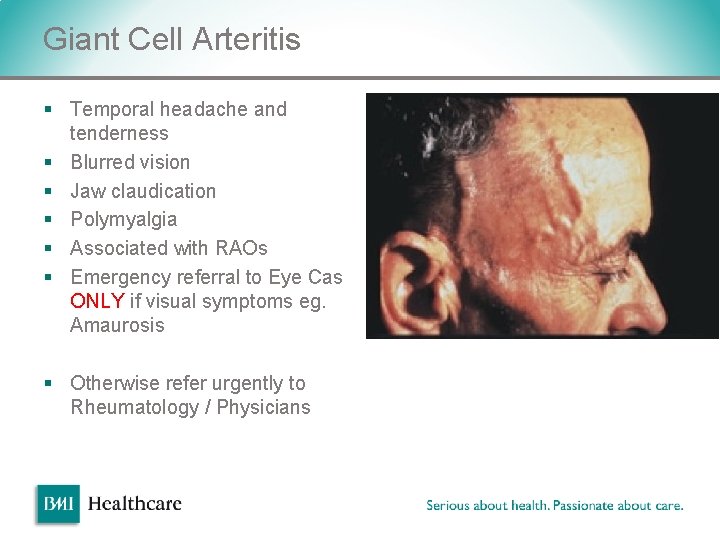
Giant Cell Arteritis § Temporal headache and tenderness § Blurred vision § Jaw claudication § Polymyalgia § Associated with RAOs § Emergency referral to Eye Cas ONLY if visual symptoms eg. v Amaurosis § Otherwise refer urgently to Rheumatology / Physicians
Glaucoma § § Open vs Closed angle 1 vs 2 Neovascular What IOP is urgent? § <30 mm. Hg refer to outpatients § >30 mm. Hg D/W on call team v
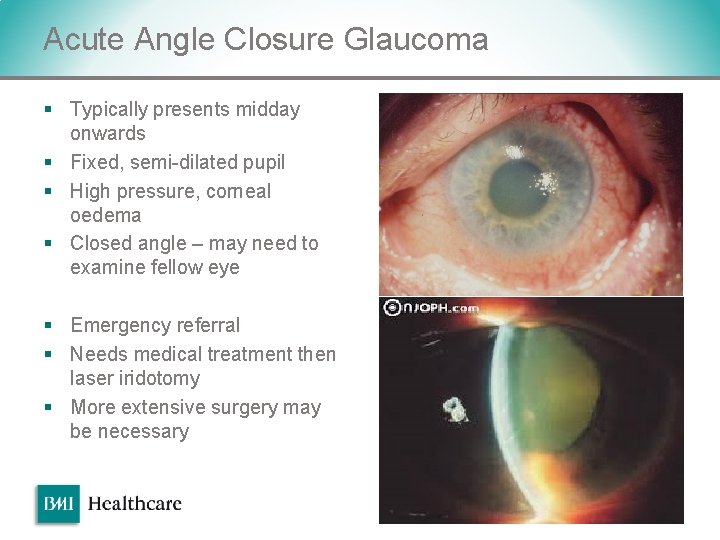
Acute Angle Closure Glaucoma § Typically presents midday onwards § Fixed, semi-dilated pupil § High pressure, corneal oedema § Closed angle – may need to examine fellow eye § Emergency referral § Needs medical treatment then laser iridotomy § More extensive surgery may be necessary v
Vitreo & Medical Retina § § § § Posterior Vitreous Detachment Vitreous haemorrhage Retinal tears and holes Retinal detachment Wet AMD Vascular occlusions v Proliferative diabetic retinopathy
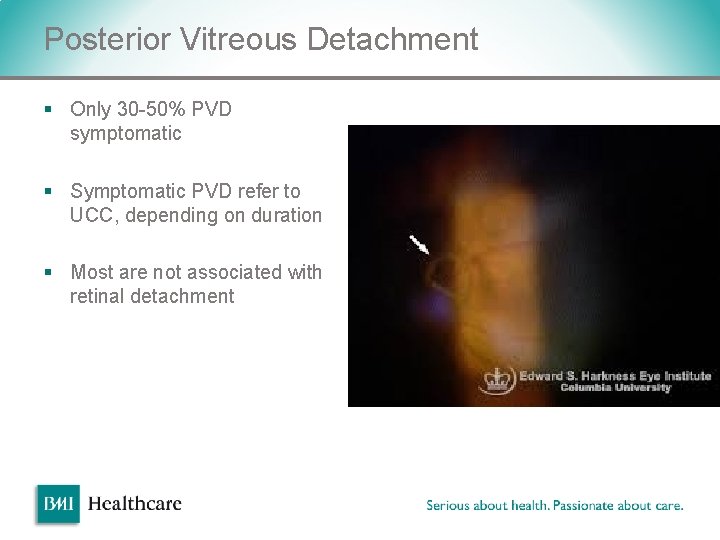
Posterior Vitreous Detachment § Only 30 -50% PVD symptomatic § Symptomatic PVD refer to UCC, depending on duration § Most are not associated with retinal detachment v
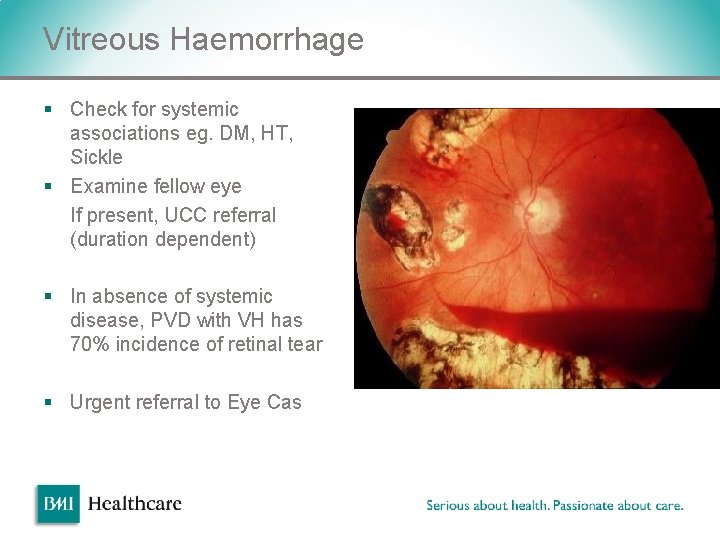
Vitreous Haemorrhage § Check for systemic associations eg. DM, HT, Sickle § Examine fellow eye If present, UCC referral (duration dependent) § In absence of systemic disease, PVD with VH has 70% incidence of retinal tear § Urgent referral to Eye Cas v
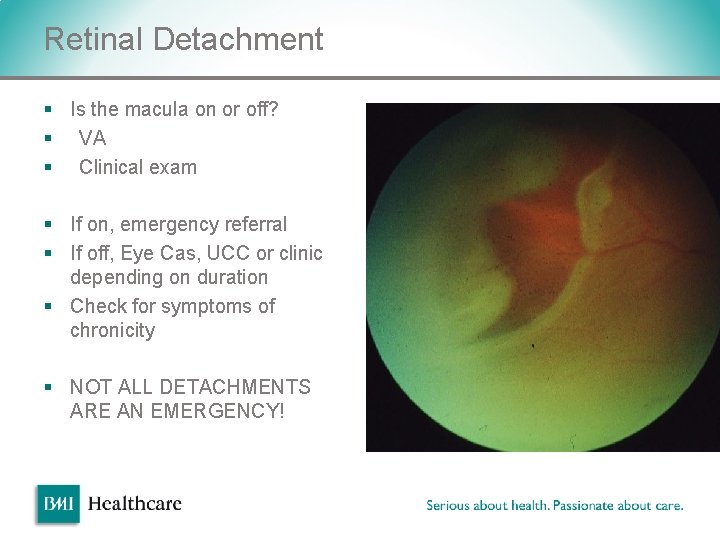
Retinal Detachment § Is the macula on or off? § VA § Clinical exam § If on, emergency referral § If off, Eye Cas, UCC or clinic depending on duration § Check for symptoms of chronicity § NOT ALL DETACHMENTS ARE AN EMERGENCY! v
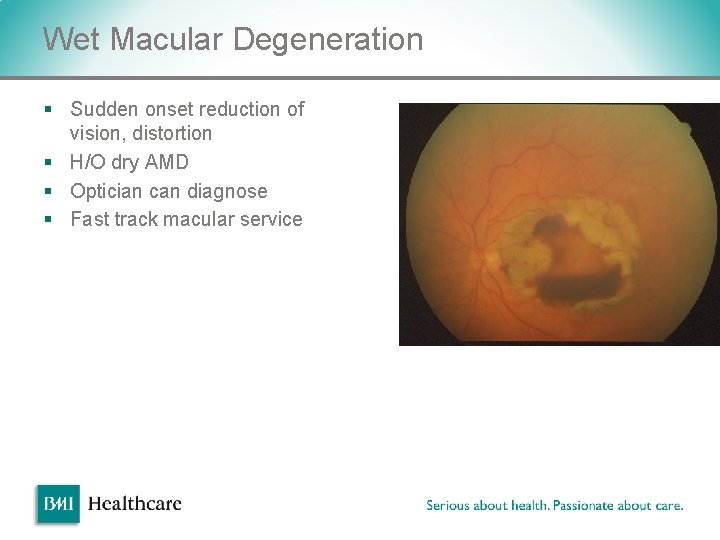
Wet Macular Degeneration § Sudden onset reduction of vision, distortion § H/O dry AMD § Optician can diagnose § Fast track macular service v
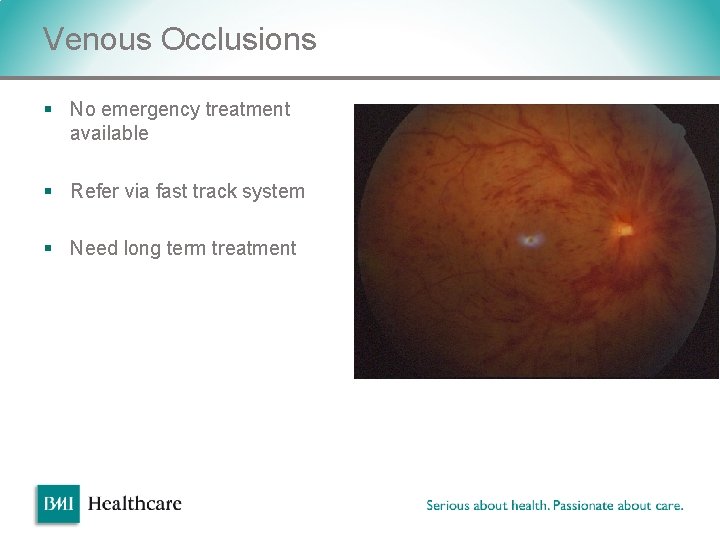
Venous Occlusions § No emergency treatment available § Refer via fast track system § Need long term treatment v
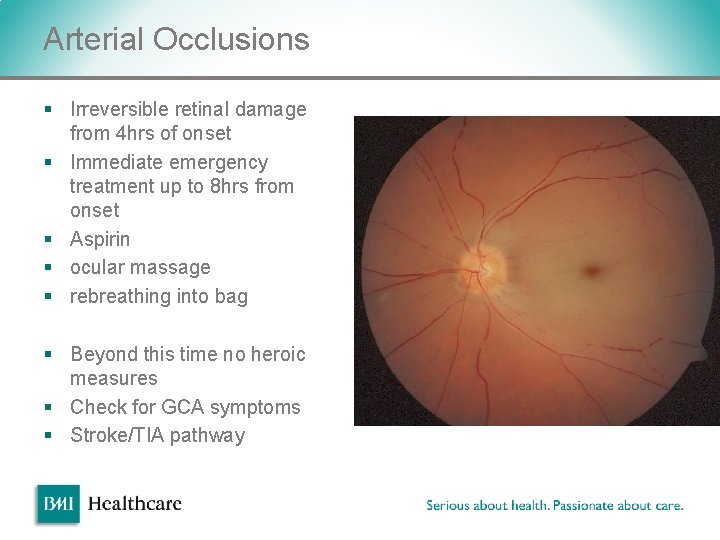
Arterial Occlusions § Irreversible retinal damage from 4 hrs of onset § Immediate emergency treatment up to 8 hrs from onset § Aspirin § ocular massage § rebreathing into bag § Beyond this time no heroic measures § Check for GCA symptoms § Stroke/TIA pathway v
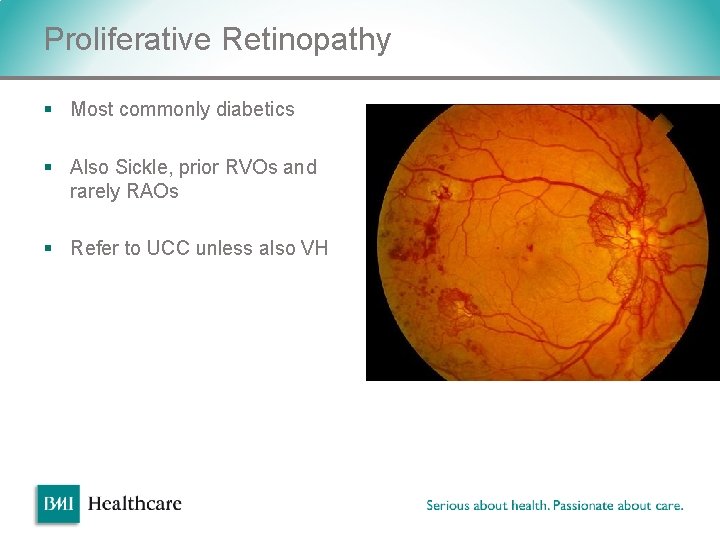
Proliferative Retinopathy § Most commonly diabetics § Also Sickle, prior RVOs and rarely RAOs § Refer to UCC unless also VH v
The Future § § § 6 -9% annual increase in demand <30% of attenders are genuine 4 hr cases PEARS / MECS Rapid access clinics Allied professionals in house § Nurses § Optometrists § Orthoptists v § GP surgeries open all hours!