
Prof Amgad Fouad Gastroenterology center Mansoura University Achalasia






























- Slides: 53
Prof. Amgad Fouad Gastroenterology center Mansoura University
Achalasia of the esophagus, different line for therapy
Achalasia – Greek word – Failure to relax – Willis (1672)
Ø Zenker & Vonziemssen (1877): Diminished contractile power of the esophageal musculature. Ø Meltzer & Miklicz (1888): Spasmodic contraction of the cardiac sphincter. Ø Einhorn (1888): Failure of relaxation of the cardia on swallowing. Ø Horst (1929): Established the term achalasia (failure to relax).
Achalasia: – The most recognised motor disorder of the esophagus. – Cardinal features: • Poorly relaxing LES • Prolonged esophageal transit • Defective esophageal body peristalsis.
• 1 -2 / 200. 000 • ♂ =♀. • Any age. • Onset 3 rd – 5 th decade. • Duration of symptoms at presentation 2 years average. (Mayberry & Atkinson, 1985)
Presentation • • • Dysphagia (almost 100%) Regurgitation (60 -90%) Chest pain (30 – 50%) Wt loss (Advanced disease). Pulmonary symptoms. – Bronchopneumonia – Lung abscess – Ht burn (rare presentation )
Diagnosis – Compatible clinical history. – Radiography. – Endoscopy. – Manometry.
Radiographic studies Plain X ray : q Widened mediastinum. q Air fluid level q Absence of gastric air bubble q Evidence of pulmonary complications
Radiographic studies (continue) Barium swallow q Screening test q Esophageal body dilated q Lower end esophagus → tapered point. (birds Beak ) q Nitrite test → Diagnostic.
Radiographic staging q Stage I : Slight dilatation of the body not >3. 5 cm. q Stage II : Moderate dilatation 3. 5 -6 cm. q Stage III : Marked dilatation >6 cm. q Stage IV : Marked dilatation elongation and tortiousity of the esophagus (sigmoid esophagus).
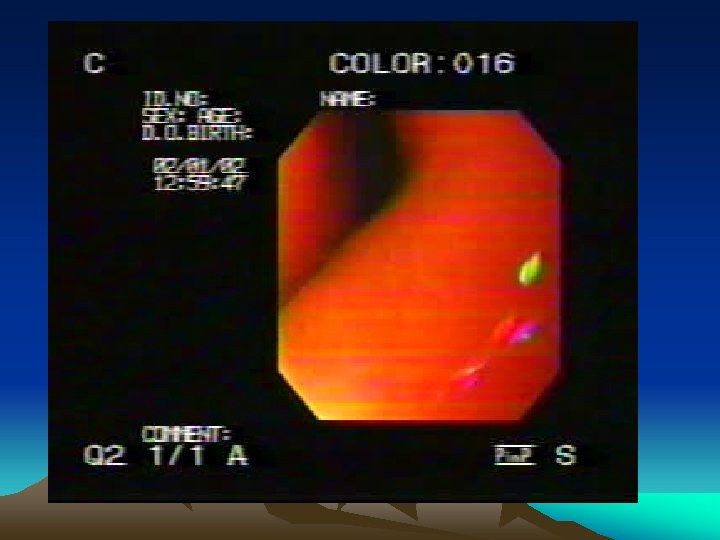
Endoscopy Important diagnostic tool • Rule out several diseases that mimic achalasia. • Evaluate esophageal mucasa before therapeutic manipulation. Typical finding • Dilated esophgeal body • Puckered closed LES • No organic stricture
Mamometry • Confirms & establishes the diagnosis • Features: Essential features v Absence of esophgeal body peristalsis (1 ry peristaltic waves) v ↑ intraesophageal resting pressure. v Abnormal LES relaxation. Supportive Features v Hypertensive LES pressure v Low amplitude esophageal contractions (Castell, 1996)
☺Treatment of Achalasia
Medical Treatment Nitrates. Ca ++ channel blockers Anticholinergic drugs ØAll have been shown to reduce the force of contraction of esophageal body smooth muscles. ØMay be of value in reducing chest pain & improving dysphagia (Gelfond et al. , 1982)
Botulinum toxin Ø Neurotoxin produced by clostridium botulinum. Ø Only serotype A+B have been approved for clinical use. Ø Two preparations of BTX (A) available: q. Dysport (UK) q. Botox (USA)
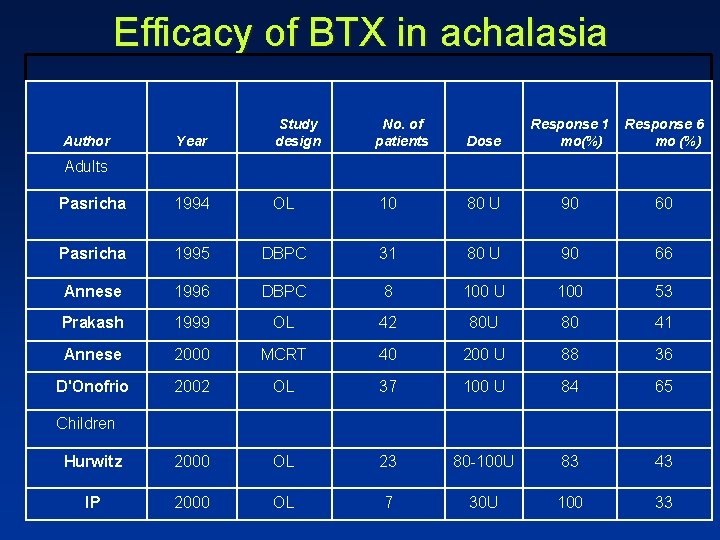
Efficacy of BTX in achalasia Year Study design Pasricha 1994 OL 10 80 U 90 60 Pasricha 1995 DBPC 31 80 U 90 66 Annese 1996 DBPC 8 100 U 100 53 Prakash 1999 OL 42 80 U 80 41 Annese 2000 MCRT 40 200 U 88 36 D'Onofrio 2002 OL 37 100 U 84 65 Hurwitz 2000 OL 23 80 -100 U 83 43 IP 2000 OL 7 30 U 100 33 Author No. of patients Dose Response 1 mo(%) Response 6 mo (%) Adults Children
Pneumatic dilatation Ø The most effective non-surgical treatment option. Ø Forceful dilatation using air or water pressure can be applied to the lower esophageal segment and controlled to secure further stretching to the point of rupture of the circular ms fibers.
Recommended technique for pneumatic balloon dilatation 1 Fasting for at least 12 h before procedure. 2 Esophageal lavage with a large-bore tube )if needed). 3 Sedation and endoscopy in Rt lateral position. 4 Guidewire positioned in stomach and balloon passed over the guidewire. 5 6 7 8 Initial dilatation with 3 -cm diameter balloon; subsequent progression to 3. 5 -cm and 4 cm balloons may be required at separate sessions. Accurate placement of balloon across gastroesophageal junction fluoroscopically. Balloon distention to obliterate the waist, which usually requires 7 -10 psi )this is the key to a successful dilatation) Gastrograffin study followed by barium swallow to exclude esophageal perforation. 9 Observation for 4 h for chest pain and fever. 10 Discharge with follow-up in 1 mo. *Before proceeding with pneumatic dilatation, it is important to ensure that a cardiothoracic surgeon is available in case of an esophageal perforation. (Voizi et al, 1994)
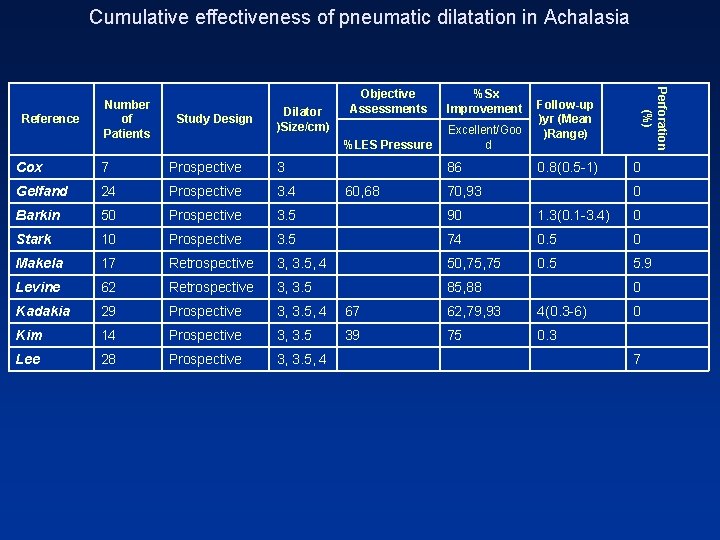
Cumulative effectiveness of pneumatic dilatation in Achalasia Study Design Dilator )Size/cm) Objective Assessments %Sx Improvement %LES Pressure Excellent/Goo d 86 Perforation (%) Reference Number of Patients Follow-up )yr (Mean )Range) Cox 7 Prospective 3 Gelfand 24 Prospective 3. 4 Barkin 50 Prospective 3. 5 90 1. 3(0. 1 -3. 4) 0 Stark 10 Prospective 3. 5 74 0. 5 0 Makela 17 Retrospective 3, 3. 5, 4 50, 75 0. 5 5. 9 Levine 62 Retrospective 3, 3. 5 85, 88 Kadakia 29 Prospective 3, 3. 5, 4 67 62, 79, 93 4(0. 3 -6) Kim 14 Prospective 3, 3. 5 39 75 0. 3 Lee 28 Prospective 3, 3. 5, 4 60, 68 0. 8(0. 5 -1) 70, 93 0 0 7
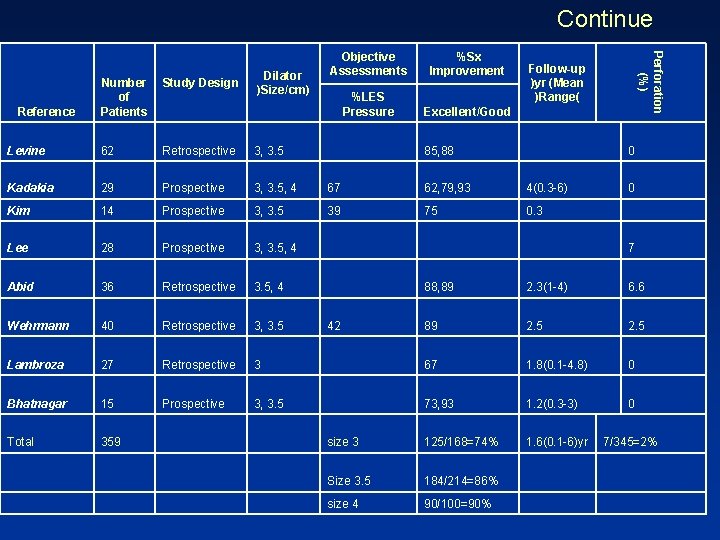
Continue %Sx Improvement %LES Pressure Excellent/Good Follow-up )yr (Mean )Range( Number of Patients Study Design Levine 62 Retrospective 3, 3. 5 Kadakia 29 Prospective 3, 3. 5, 4 67 62, 79, 93 4(0. 3 -6) Kim 14 Prospective 3, 3. 5 39 75 0. 3 Lee 28 Prospective 3, 3. 5, 4 Abid 36 Retrospective 3. 5, 4 Wehrmann 40 Retrospective 3, 3. 5 Lambroza 27 Retrospective Bhatnagar 15 Prospective Total 359 Reference Perforation (%) Dilator )Size/cm) Objective Assessments 85, 88 0 0 7 88, 89 2. 3(1 -4) 6. 6 89 2. 5 3 67 1. 8(0. 1 -4. 8) 0 3, 3. 5 73, 93 1. 2(0. 3 -3) 0 size 3 125/168=74% 1. 6(0. 1 -6)yr Size 3. 5 184/214=86% size 4 90/100=90% 42 7/345=2%
Surgical management of Achalasia • Rationale of surgery is to weaken the lower esophageal sphincteric pressure but in controlled Faison avoiding subsequent reflux (Earlam, 1976)
Heller (1913) v First performed extra mucosal cardiorytomy. v Two 8 cm incisions one ant & one post. v Incisions extending 2 cm into the dilated part cranially & into the fundus of the stomach caudally.
Modified Heller’s myotomy (Zaaijer, 1985) • Most widely used technique. • Single anterior myotomy. • Transabdominal. However Two problems →poor results 1. Incomplete myotomy 2. Reflux esophagitis.
Anti – Reflux
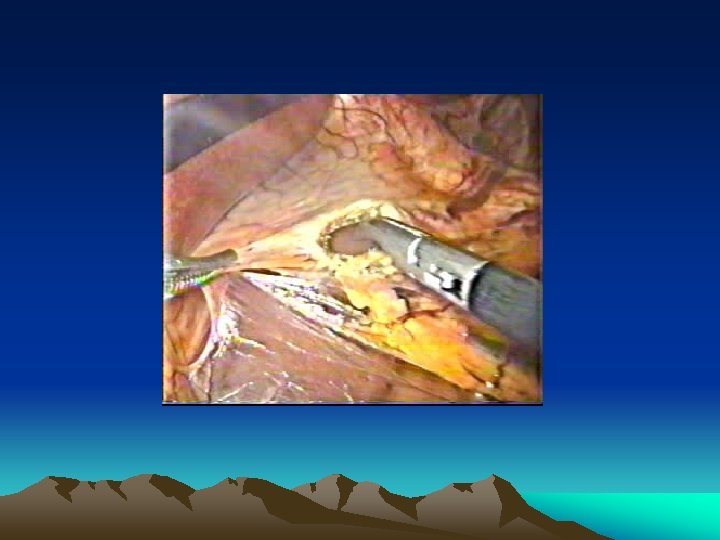
Laparoscopic Heller’s Ø Most preferred by gastrointestinal laparoscopic surgeon. Ø Easy access. Ø Good result Ø Anti – reflux +
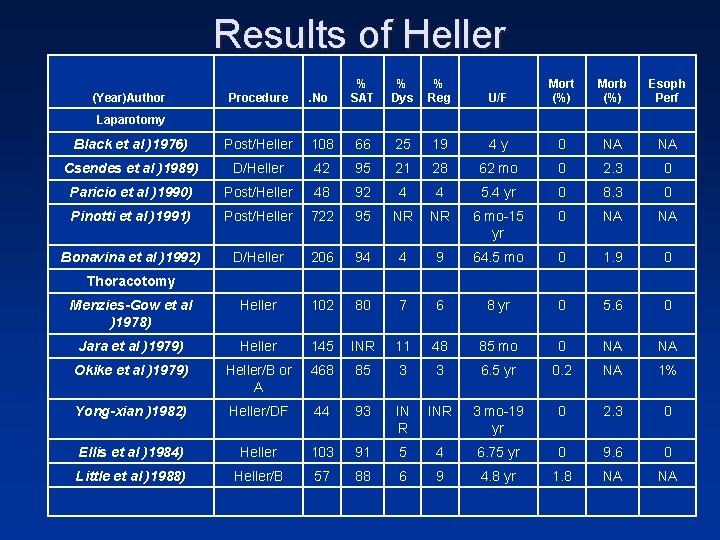
Results of Heller Procedure . No % SAT Black et al )1976) Post/Heller 108 66 25 19 4 y 0 NA NA Csendes et al )1989) D/Heller 42 95 21 28 62 mo 0 2. 3 0 Paricio et al )1990) Post/Heller 48 92 4 4 5. 4 yr 0 8. 3 0 Pinotti et al )1991) Post/Heller 722 95 NR NR 6 mo-15 yr 0 NA NA Bonavina et al )1992) D/Heller 206 94 4 9 64. 5 mo 0 1. 9 0 Menzies-Gow et al )1978) Heller 102 80 7 6 8 yr 0 5. 6 0 Jara et al )1979) Heller 145 INR 11 48 85 mo 0 NA NA Okike et al )1979) Heller/B or A 468 85 3 3 6. 5 yr 0. 2 NA 1% Yong-xian )1982) Heller/DF 44 93 IN R INR 3 mo-19 yr 0 2. 3 0 Ellis et al )1984) Heller 103 91 5 4 6. 75 yr 0 9. 6 0 Little et al )1988) Heller/B 57 88 6 9 4. 8 yr 1. 8 NA NA (Year)Author % Dys % Reg U/F Mort (%) Morb (%) Esoph Perf Laparotomy Thoracotomy
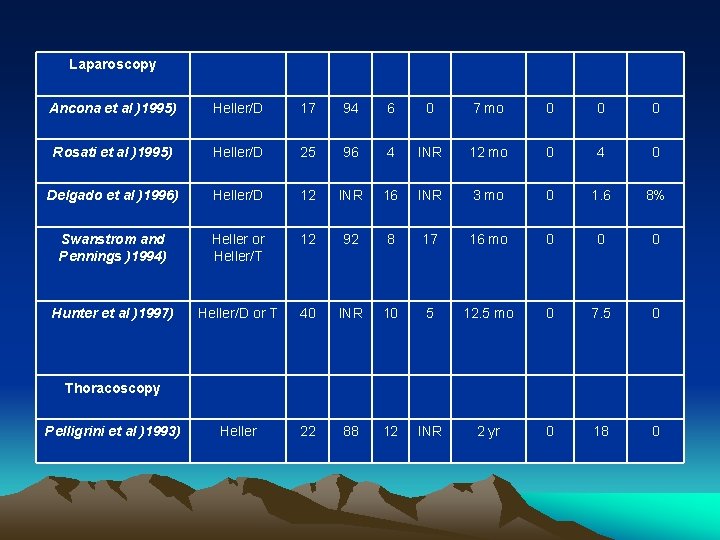
Laparoscopy Ancona et al )1995) Heller/D 17 94 6 0 7 mo 0 0 0 Rosati et al )1995) Heller/D 25 96 4 INR 12 mo 0 4 0 Delgado et al )1996) Heller/D 12 INR 16 INR 3 mo 0 1. 6 8% Swanstrom and Pennings )1994) Heller or Heller/T 12 92 8 17 16 mo 0 0 0 Hunter et al )1997) Heller/D or T 40 INR 10 5 12. 5 mo 0 7. 5 0 Heller 22 88 12 INR 2 yr 0 18 0 Thoracoscopy Pelligrini et al )1993)
Aim of work § The aim of this work was to evaluate Heller’s myotomy and preumatic balloon dilatation as two alternative lines of therapy for patients with achalasia of the esophagus.
Patients and Methods
o Our study is a retrospective non- randomised study conducted at GEC during the period between October 1979 - November 2002. o The study included 310 cases with achalasia. o 169 ♂ & 141♀ o According to the line of management the study included two groups: § Group A: 150 patients treated with myotomy + fundoplication. § Group B: 160 patient treated by pneumatic balloon dilatation.
Preoperative work up • Thorough history and clinical examination. • Patients were divided into 4 groups according to Demeester's grading for dysphagia. (Cuschieri et al. , 2002) • No dysphasia • Mild : occasional episodes. • Moderate: requires fluids to clear. • Severe : episodes of solid food impaction & require medical treatment.
Preoperative work up • • Radiological examination According to Olsen scoring system, patients were divided into 4 groups (Olsen et al. , 1983) • • (continue ) Endoscopic evaluation Manometric study
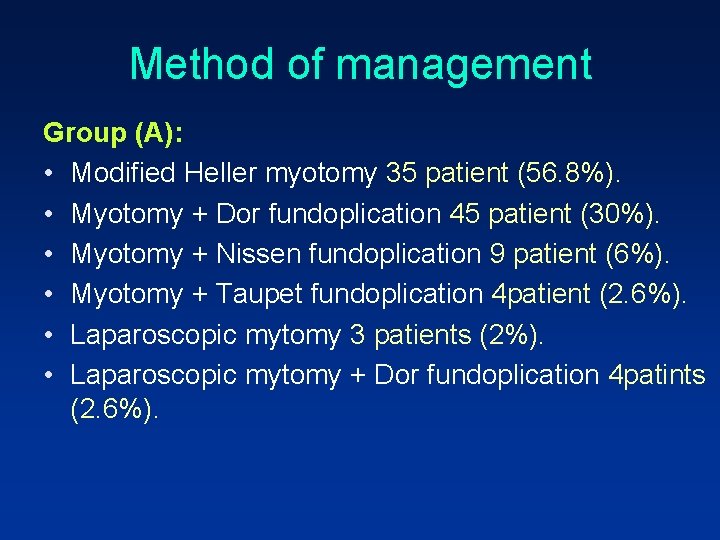
Method of management Group (A): • Modified Heller myotomy 35 patient (56. 8%). • Myotomy + Dor fundoplication 45 patient (30%). • Myotomy + Nissen fundoplication 9 patient (6%). • Myotomy + Taupet fundoplication 4 patient (2. 6%). • Laparoscopic mytomy 3 patients (2%). • Laparoscopic mytomy + Dor fundoplication 4 patints (2. 6%).
Method of management Continue Group (B): • • Pneumatic balloon dilatation (1. 8+ 1 set) One session in 79 patients (60. 5%). Two sessions in 48 patients (30%). Three or more sessions in only 15 patients (9. 5%).
Results
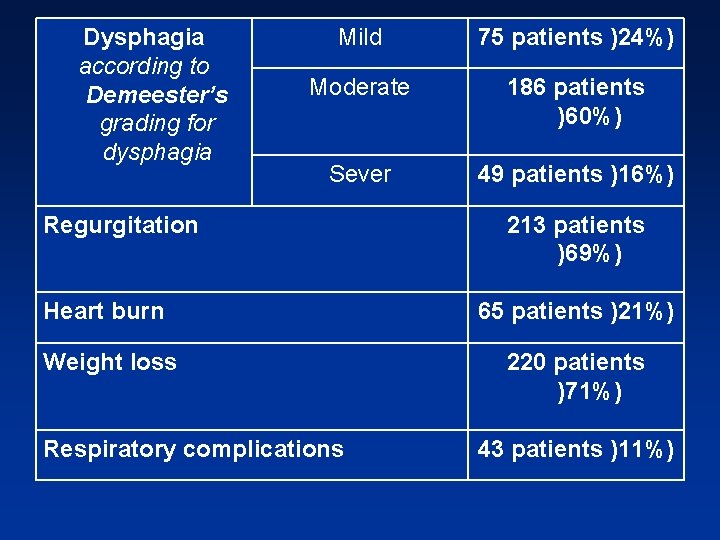
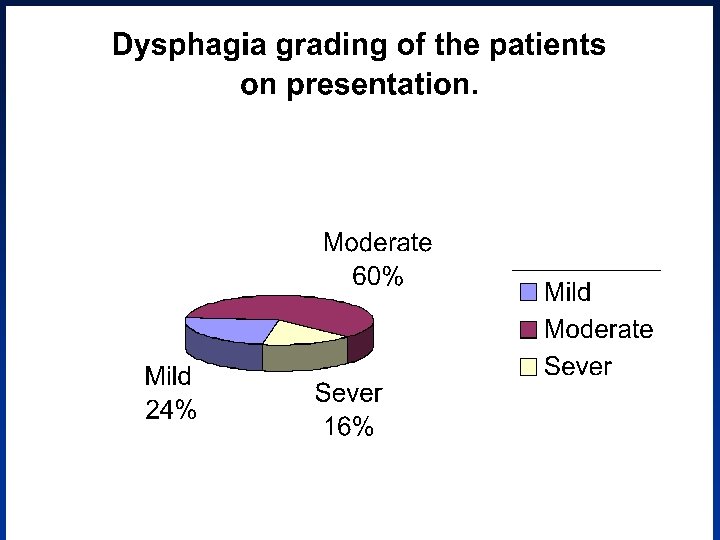
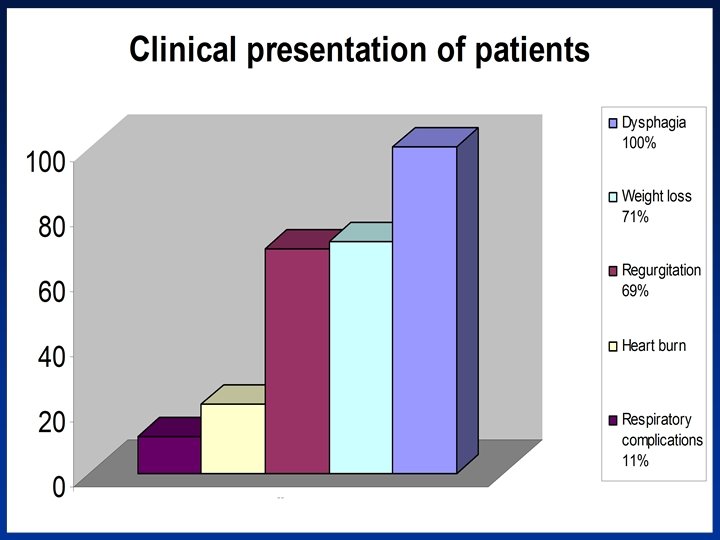
Dysphagia according to Demeester’s grading for dysphagia Mild 75 patients )24%) Moderate 186 patients )60%) Sever 49 patients )16%) Regurgitation 213 patients )69%) Heart burn 65 patients )21%) Weight loss 220 patients )71%) Respiratory complications 43 patients )11%)
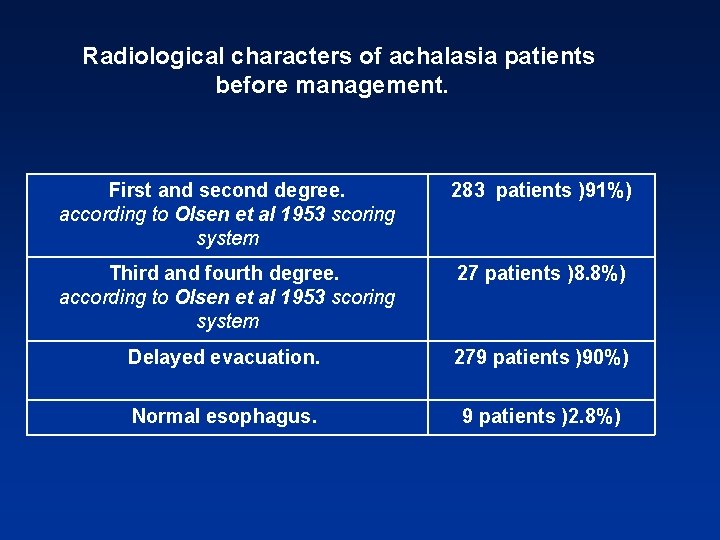
Radiological characters of achalasia patients before management. First and second degree. according to Olsen et al 1953 scoring system 283 patients )91%) Third and fourth degree. according to Olsen et al 1953 scoring system 27 patients )8. 8%) Delayed evacuation. 279 patients )90%) Normal esophagus. 9 patients )2. 8%)
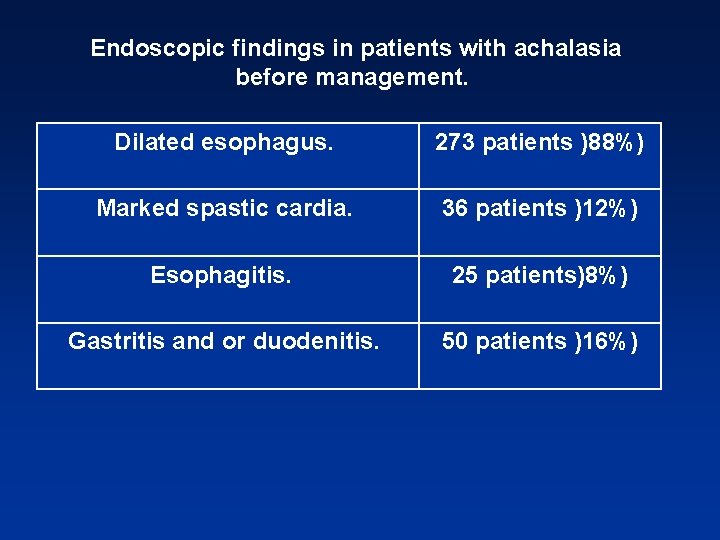
Endoscopic findings in patients with achalasia before management. Dilated esophagus. 273 patients )88%) Marked spastic cardia. 36 patients )12%) Esophagitis. 25 patients)8%) Gastritis and or duodenitis. 50 patients )16%)
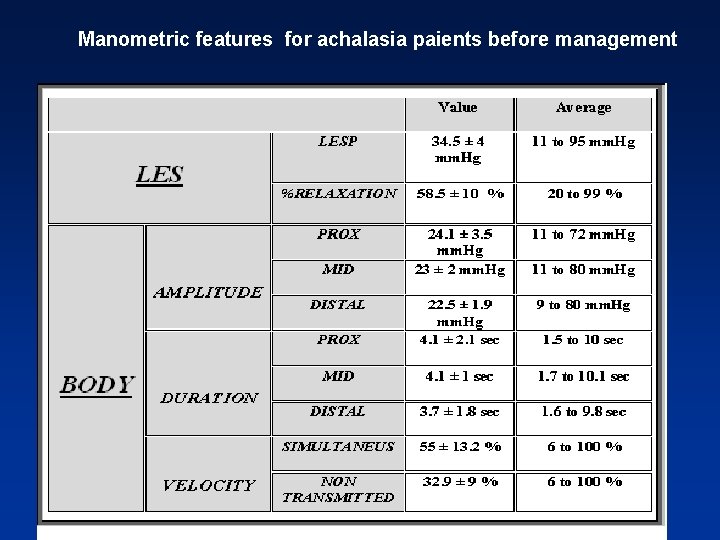
Manometric features for achalasia paients before management
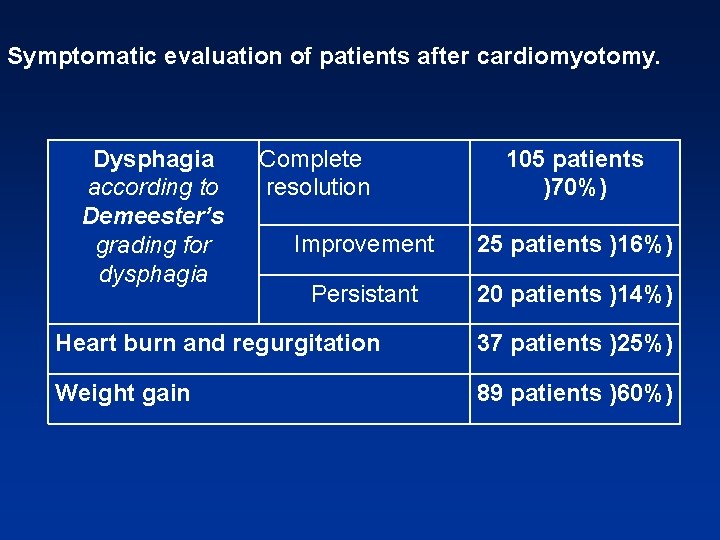
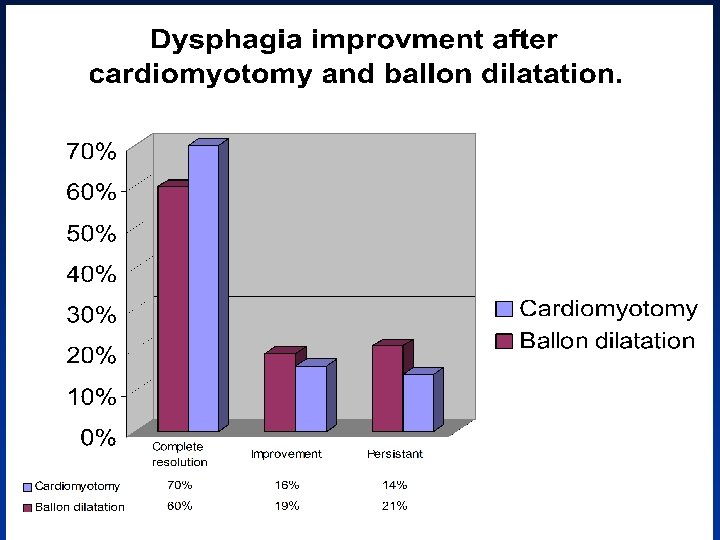
Symptomatic evaluation of patients after cardiomyotomy. Dysphagia according to Demeester’s grading for dysphagia Complete resolution 105 patients )70%) Improvement 25 patients )16%) Persistant 20 patients )14%) Heart burn and regurgitation 37 patients )25%) Weight gain 89 patients )60%)
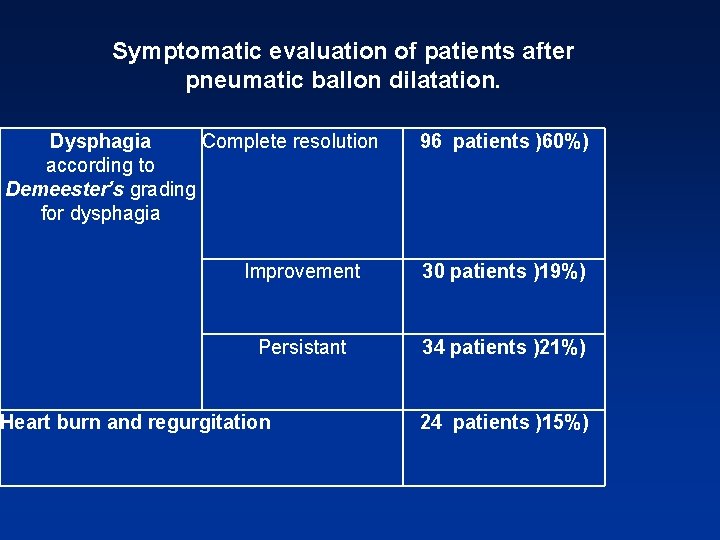
Symptomatic evaluation of patients after pneumatic ballon dilatation. Dysphagia Complete resolution according to Demeester’s grading for dysphagia 96 patients )60%) Improvement 30 patients )19%) Persistant 34 patients )21%) Heart burn and regurgitation 24 patients )15%)
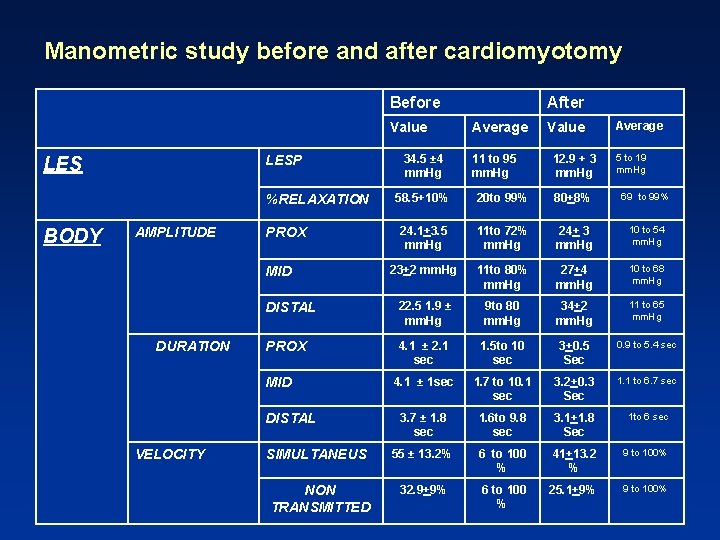
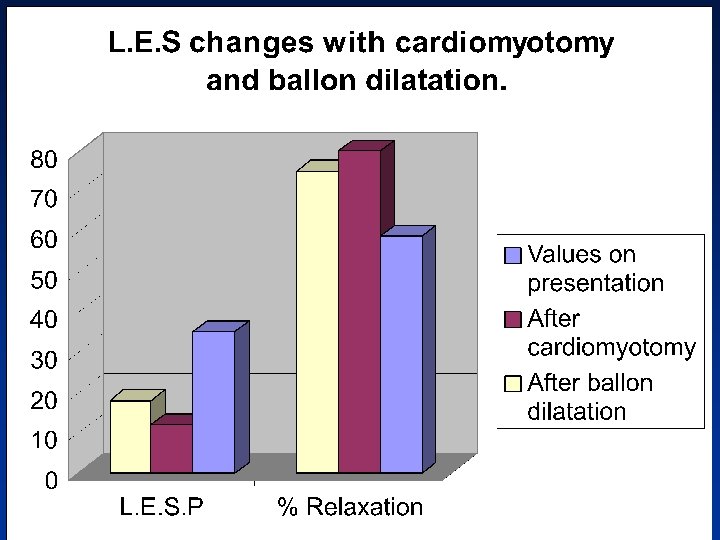
Manometric study before and after cardiomyotomy Before Value LESP LES AMPLITUDE 12. 9 + 3 mm. Hg Average 5 to 19 mm. Hg 80+8% 69 to 99% 24. 1+3. 5 mm. Hg 11 to 72% mm. Hg 24+ 3 mm. Hg 10 to 54 mm. Hg 23+2 mm. Hg 11 to 80% mm. Hg 27+4 mm. Hg 10 to 68 mm. Hg DISTAL 22. 5 1. 9 ± mm. Hg 9 to 80 mm. Hg 34+2 mm. Hg 11 to 65 mm. Hg PROX 4. 1 ± 2. 1 sec 1. 5 to 10 sec 3+0. 5 Sec 0. 9 to 5. 4 sec 4. 1 ± 1 sec 1. 7 to 10. 1 sec 3. 2+0. 3 Sec 1. 1 to 6. 7 sec 3. 7 ± 1. 8 sec 1. 6 to 9. 8 sec 3. 1+1. 8 Sec 1 to 6 sec 55 ± 13. 2% 6 to 100 % 41+13. 2 % 9 to 100% 32. 9+9% 6 to 100 % 25. 1+9% 9 to 100% PROX MID DISTAL VELOCITY 11 to 95 mm. Hg Value 20 to 99% MID DURATION Average 58. 5+10% %RELAXATION BODY 34. 5 ± 4 mm. Hg After SIMULTANEUS NON TRANSMITTED
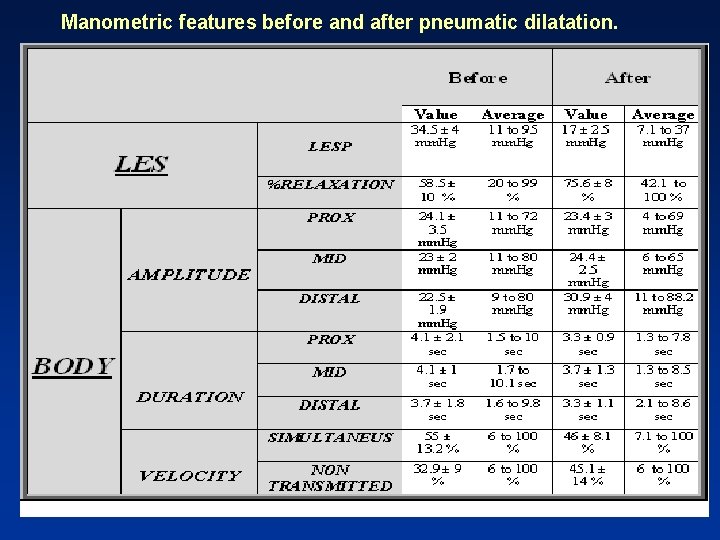
Manometric features before and after pneumatic dilatation.
Summary and conclusion
We agree that life long palliation of dysphagia is not guaranteed but It is obvious that Heller cardiomyotomy in our study gives good to excellent results as regard the improvement of dysphagia. As in the largest series puplished about the management of achalasia. Pneumatic ballon dilatation is also a good method of management of patients with achalasia, but it doesn’t give the same longterm response as surgical cardiomyotomy besides that some cases may have early recurrence or persistant dysphagia after dilatation.





















































