Primary glomerulonephritides GN Miroslav Merta Klinika nefrologie 1



















- Slides: 41
Primary glomerulonephritides (GN) Miroslav Merta Klinika nefrologie 1. LF a VFN
Definition of GN, definition of primary GN In GN (generally) we find: • an immunological process • an inflammatory character of glomerular affection In primary GN we find: • an isolated affection of kidneys Some GN can manifest as well as primary or as secondary GN (MGN, MPGN…)
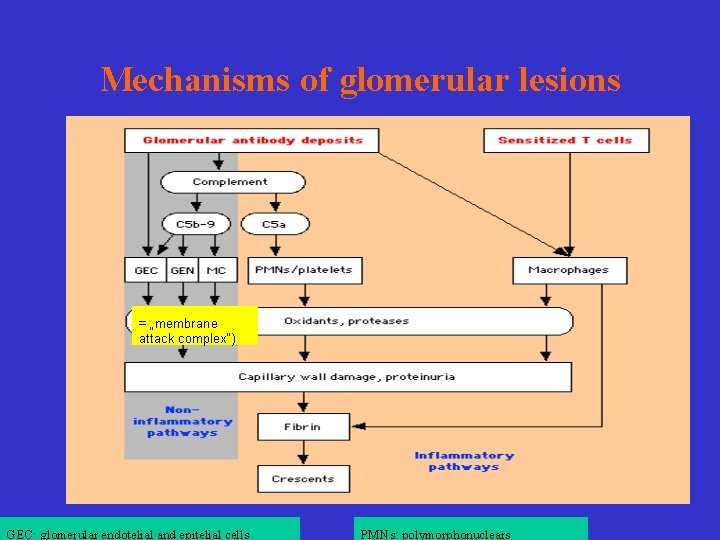
Mechanisms of glomerular lesions = „membrane attack complex“) GEC: glomerular endotelial and epitelial cells PMNs: polymorphonuclears
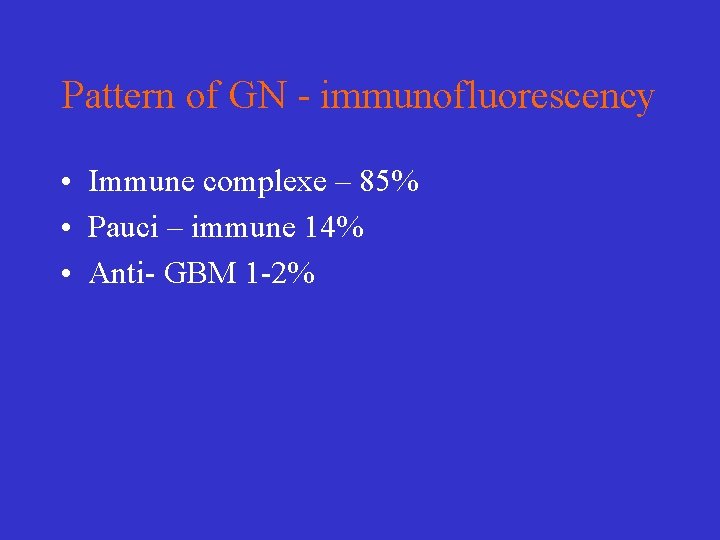
Pattern of GN - immunofluorescency • Immune complexe – 85% • Pauci – immune 14% • Anti- GBM 1 -2%
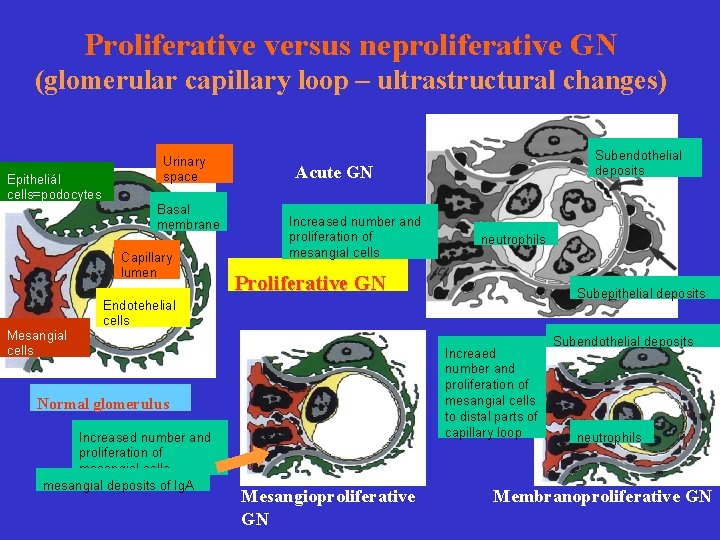
Inflammatory affection of glomeruli is characterized by: • Exsudation of neutrophils/macrophages • Proliferation of mesangial/endothelial cells
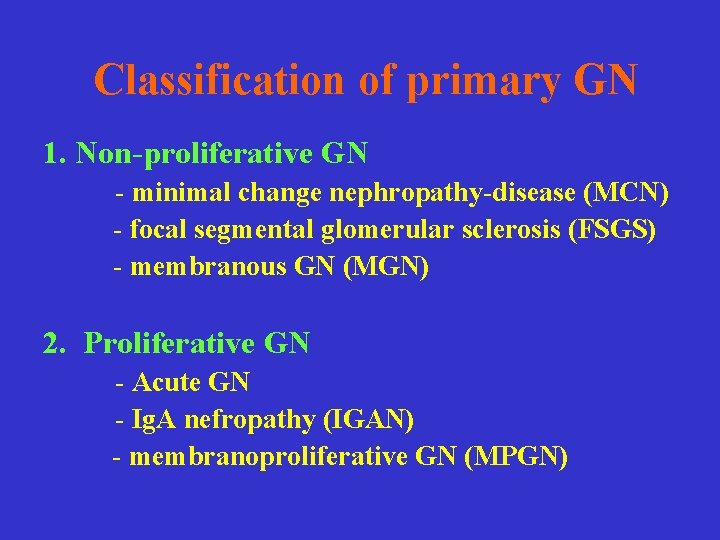
Classification of primary GN 1. Non-proliferative GN - minimal change nephropathy-disease (MCN) - focal segmental glomerular sclerosis (FSGS) - membranous GN (MGN) 2. Proliferative GN - Acute GN - Ig. A nefropathy (IGAN) - membranoproliferative GN (MPGN)
Role of renal biopsy in glomerular disease 1. Diagnosis of GN 2. Assessment of activity of the disease – important for the decision to treat (intention to treat) 3. Assessment of chronicity – important for the prognosis of the disease
Treatment of primary GN 1. Treatment and treatment tactics with well defined indications, good clinical experience • corticosteroids • • cytotoxic agents (CPA, chlorambucil) azathioprine cyklosporine symptomatic treatment: – ACEI či AT 2 receptors blockers, – Hypolipidemics (statins)
Treatment of primary GN 2. Drugs with limited clinical experience • mycophenolate tacrolimus rapamycine intravenous immunoglobulins monoclonal antibodies • • – – • • anti-TNF =infliximab, adalimumab anti-CD 20=rituximab solubile cytokine receptors (TNF rec. =etanercept) plasmaexchange
Treatment of primary GN conclusions 1. Patients with primary GN are threatened with: a. complications of NS b. progression of the disease to ESRF 2. Urinary findings important, however renal biopsy essential for dg. , treatment and prognosis. 3. Primary GN are treatable diseases. Patients should be treated according to available clinical evidence.
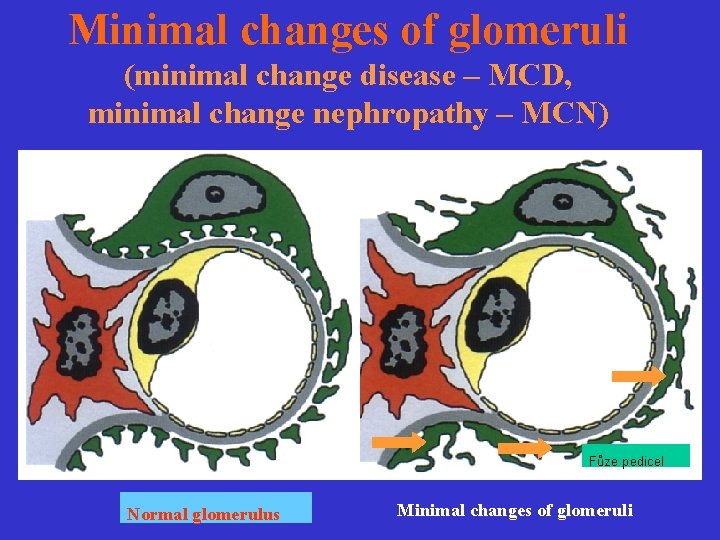
Proliferative versus nonproliferative GN (glomerular capillary wall – ultrastructural changes) Epitelial cells=podocytes Urinary space Basement membrane Capllary lumen Mesangial cells Fusion of pedicels Subepithelial deposits Minimal chenge nephropathy (MCN) Endothelial cells Nonproliferative GN Membranous GN (MGN) Normal glomerulus FSGS Sclerotisation of the loops (here in perihilar region)
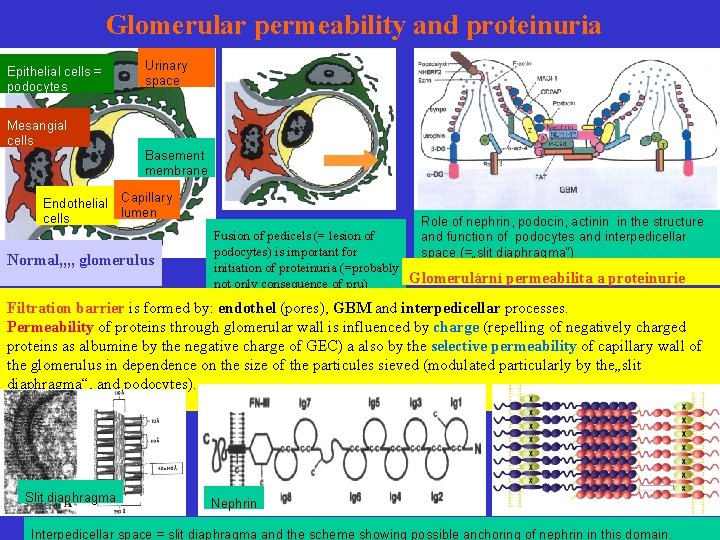
Glomerular permeability and proteinuria Epithelial cells = podocytes Mesangial cells Urinary space Basement membrane Endothelial Capillary lumen cells Normal, , glomerulus Role of nephrin, podocin, actinin in the structure and function of podocytes and interpedicellar space (=„slit diaphragma“) Fusion of pedicels (= lesion of podocytes) is important for initiation of proteinuria (=probably Glomerulární permeabilita a proteinurie not only consequence of pru) Filtration barrier is formed by: endothel (pores), GBM and interpedicellar processes. Permeability of proteins through glomerular wall is influenced by charge (repelling of negatively charged proteins as albumine by the negative charge of GEC) a also by the selective permeability of capillary wall of the glomerulus in dependence on the size of the particules sieved (modulated particularly by the„slit diaphragma“, and podocytes). Slit diaphragma Nephrin Interpedicellar space = slit diaphragma and the scheme showing possible anchoring of nephrin in this domain.
Nonproliferative GN - selectivity of proteinuria Impairment of glomerular capillary wall leads to: 1. Selective proteinuria – nefrotic range – minimal change nephropathy (MCN) 2. Non-selective proteinuria (associated event. with microscopic hematuria) - FSGS - idiopatic membranous GN
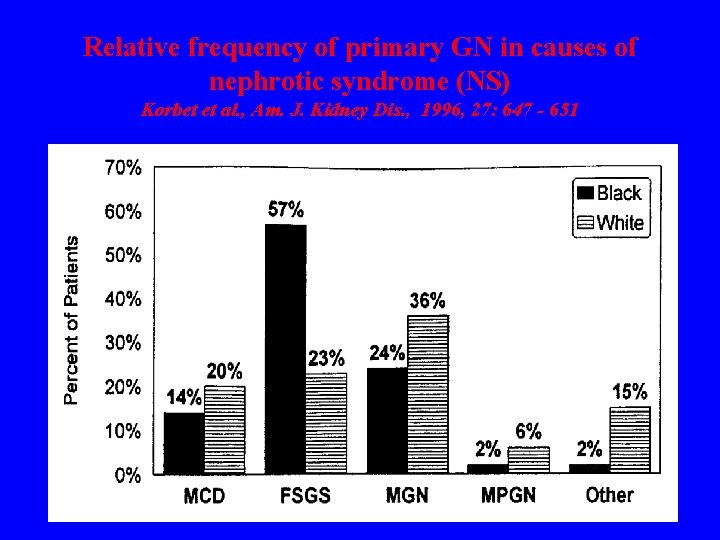
Relative frequency of primary GN in causes of nephrotic syndrome (NS) Korbet et al. , Am. J. Kidney Dis. , 1996, 27: 647 - 651
Minimal changes of glomeruli (minimal change disease – MCD, minimal change nephropathy – MCN) Fůze pedicel Normal glomerulus Minimal changes of glomeruli
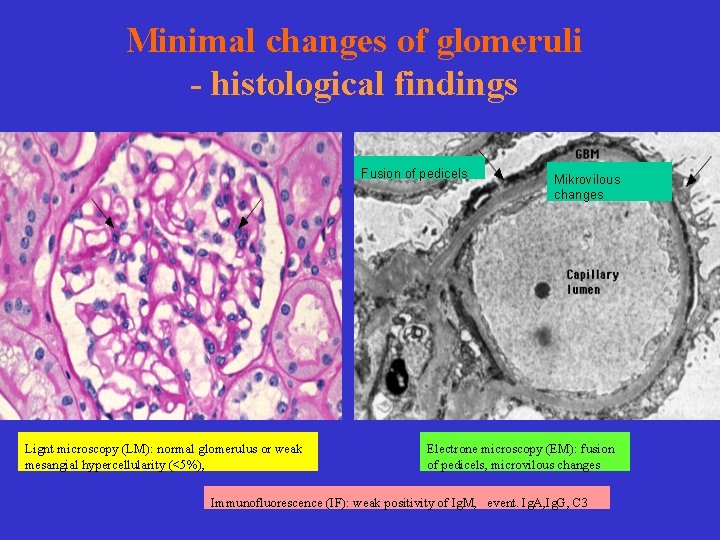
Minimal changes of glomeruli - histological findings Fusion of pedicels Lignt microscopy (LM): normal glomerulus or weak mesangial hypercellularity (<5%), Mikrovilous changes Electrone microscopy (EM): fusion of pedicels, microvilous changes Immunofluorescence (IF): weak positivity of Ig. M, event. Ig. A, Ig. G, C 3
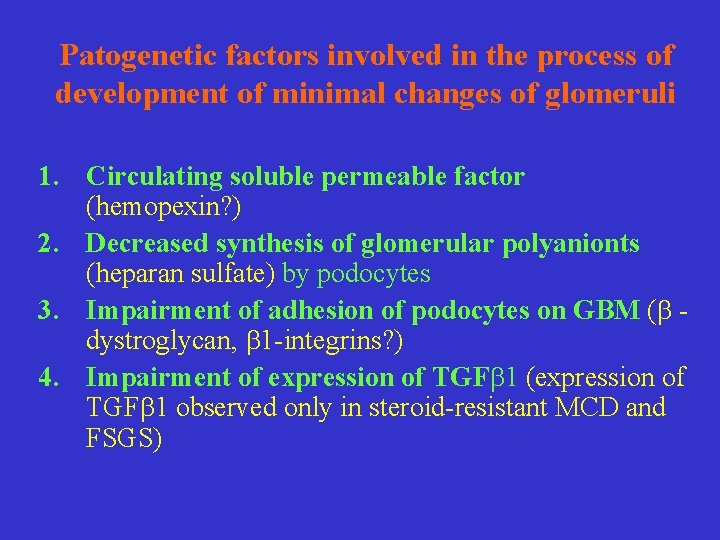
Patogenetic factors involved in the process of development of minimal changes of glomeruli 1. Circulating soluble permeable factor (hemopexin? ) 2. Decreased synthesis of glomerular polyanionts (heparan sulfate) by podocytes 3. Impairment of adhesion of podocytes on GBM ( dystroglycan, 1 -integrins? ) 4. Impairment of expression of TGF 1 (expression of TGF 1 observed only in steroid-resistant MCD and FSGS)
Minimal changes of glomeruli – basic characteristics 1. Full blown nephrotic syndrome with selective proteinuria 2. Rarely presence of hematuria, hypertension a decrease of kidney function 3. Absence of glomerular abnormits in the histological (LM, IF) picture. 4. Typical picture of damage of epithelial cells (fusion of pedicels) in EM
Minimal changes of glomeruli - prevalence in patients with NS (dependence on age) Children - 85 – 95% Adults < 40 y - 50% Adults > 40 y - 20 – 25%
Classification of patients with MCN in dependance on the answer to the treatment with corticosteroids (KS) – cortico-sensitivity 1. Cortico-sensitive patients do develop full remission of proteinuria during 8 – 12 weeks of treatment (in adults within 16 weeks) 2. Cortico (steroid) dependant patients do develop relapse during the period of tapering the dosis of CS or shortly (2 weeks) after termination of CS treatment 3. Cortico (steroid) resistant do not respond to the treatment with CS
Therapy of MCD in adults 1. Initial treatment with prednisone 1 mg/kg for a period of 8 -16 weeks or at least 1 week after achievement of remission, thereafter several weeks (4) a treatment with dosis of 1 mg/kg in alterning interval, thereafter slow withdravel of CS („tapering“) during a period of several months. 2. Relapses should be treated in the same regime 3. In patients suffering from frequent relapses or corticosteroid-dependent patients to give the treatment: Cyclophosphamide 2 mg/kg/day for a period of 8 weeks or Cy. A 5 mg/kg/day for a period of 6 -12 months Treatment of CS-resistant patients is not usually successful
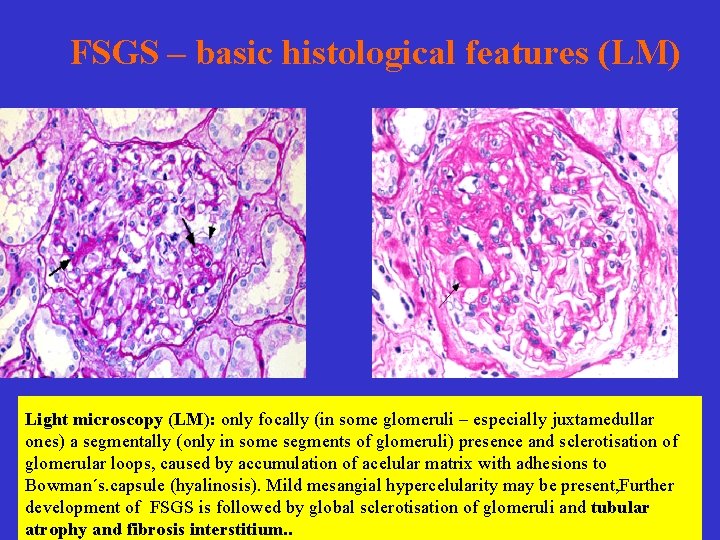
FSGS – basic histological features (LM) Light microscopy (LM): only focally (in some glomeruli – especially juxtamedullar ones) a segmentally (only in some segments of glomeruli) presence and sclerotisation of glomerular loops, caused by accumulation of acelular matrix with adhesions to Bowman´s. capsule (hyalinosis). Mild mesangial hypercelularity may be present, Further development of FSGS is followed by global sclerotisation of glomeruli and tubular atrophy and fibrosis interstitium. .
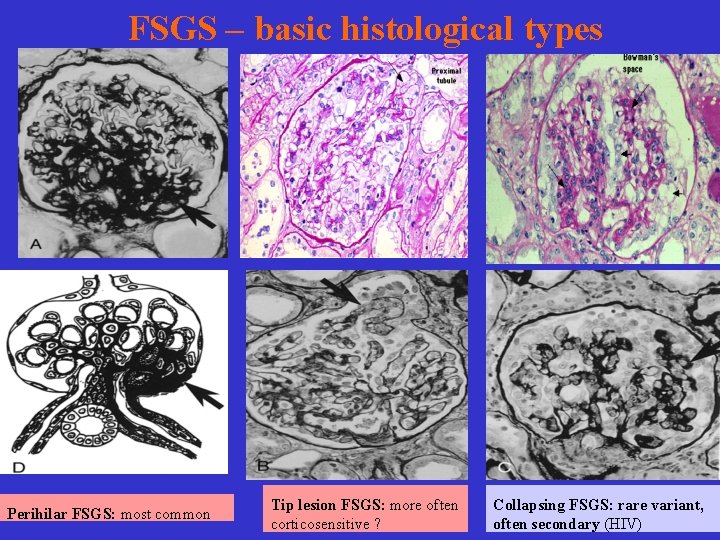
FSGS – basic histological types Perihilar FSGS: most common Tip lesion FSGS: more often corticosensitive ? Collapsing FSGS: rare variant, often secondary (HIV)
Etiology of FSGS 1. Primary FSGS a. perihilar variant b. „tip“lesion 2. Secondary FSGS a. foci of healing b. hyperfiltration in residual nephrones - agenesis of kieny - vesico-ureteral reflux - morbid obesity c. injury of epithelial cells - HIV nephropathy („collapsing FSGS“) - heroin nephropathy
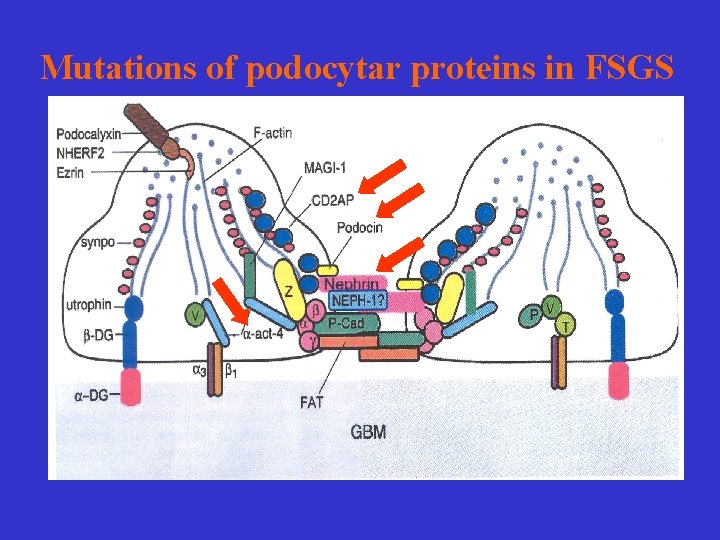
Patogenesis of primary FSGS 1. Late manifestation of inborn FSGS impairment of morphrology/function podocytar proteins (podocin, -actinin, CD 2 AP, and other) 2. Circulating permeabile factor/s a. immunoglobulin, or Ig-like molecule b. protein with MW of 30 -50 k. Da c. faktor inhibating NO inducible synthasis in mesangial cells (hemopexin) 3. Deficit of inhibitors of permeabile factors by loss into urine apolipoproteins of HDL complexe (e. g. apo J, apo E 2 and apo E 4)
Mutations of podocytar proteins in FSGS
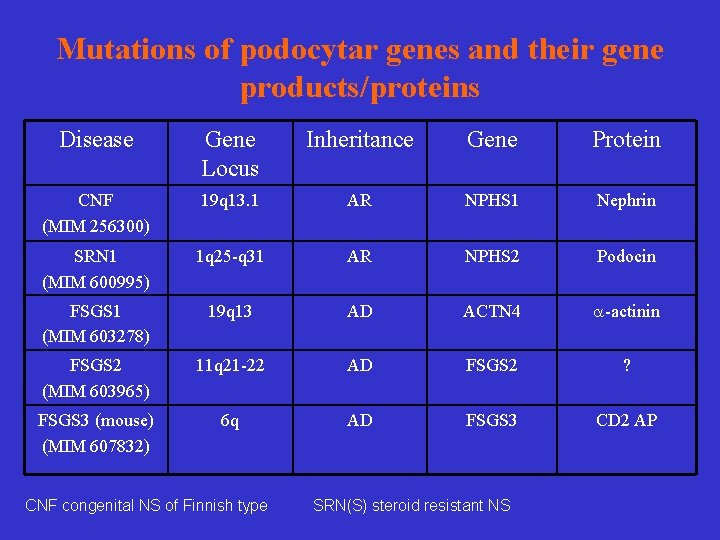
Mutations of podocytar genes and their gene products/proteins Disease Gene Locus Inheritance Gene Protein CNF (MIM 256300) 19 q 13. 1 AR NPHS 1 Nephrin SRN 1 (MIM 600995) 1 q 25 -q 31 AR NPHS 2 Podocin FSGS 1 (MIM 603278) 19 q 13 AD ACTN 4 -actinin FSGS 2 (MIM 603965) 11 q 21 -22 AD FSGS 2 ? FSGS 3 (mouse) (MIM 607832) 6 q AD FSGS 3 CD 2 AP CNF congenital NS of Finnish type SRN(S) steroid resistant NS
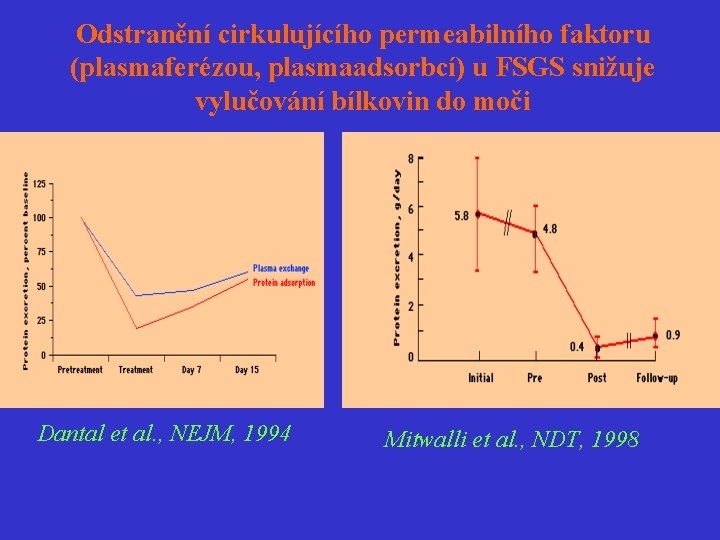
Odstranění cirkulujícího permeabilního faktoru (plasmaferézou, plasmaadsorbcí) u FSGS snižuje vylučování bílkovin do moči Dantal et al. , NEJM, 1994 Mitwalli et al. , NDT, 1998
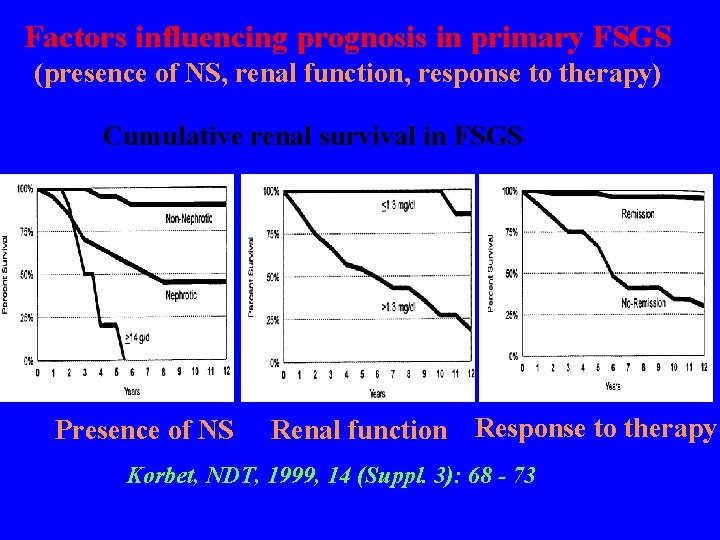
Focal segmental glomerulosclerosis - basic characteristics 1. Asymptomatic proteinuria or full blown nephrotic syndrome 2. Commonly presence of hematuria, hypertension and decrease of renal functions 3. Slow decrease of renal functions - 10 y renal survival in 50% 4. Typical histological finding is focal and segmental sclerosis of glomerular tuft
Factors influencing prognosis in primary FSGS (presence of NS, renal function, response to therapy) Cumulative renal survival in FSGS Presence of NS Renal function Response to therapy Korbet, NDT, 1999, 14 (Suppl. 3): 68 - 73
Therapy of FSGS 1. Response to CS may increase from 10 -30% to 60% by prolongation of therapy by higher doses (60 mg/m 2) for a period minimum of 3 months, patients should be considered steroid – resistant after 6 mo. 2. Cyclosporine may cause a decrease of proteinuria and decrease the risk of progression to ESRD even in steroid-rezistant patients, therapy should be prolonged (at least 6 mo), relapses after withdravel of Cy. A are frequent 3. Cytotoxic agents are drugs of 2 nd line, evidence of their efficacy are not convincing
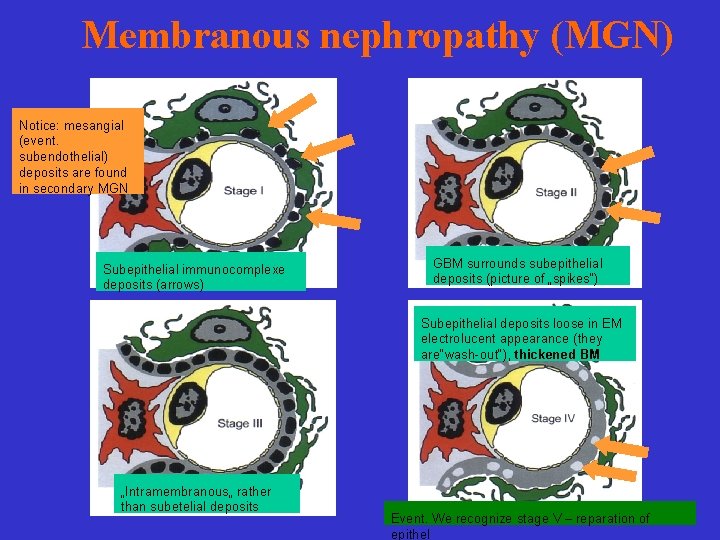
Membranous nephropathy (MGN) Notice: mesangial (event. subendothelial) deposits are found in secondary MGN Subepithelial immunocomplexe deposits (arrows) GBM surrounds subepithelial deposits (picture of „spikes“) Subepithelial deposits loose in EM electrolucent appearance (they are“wash-out“), thickened BM „Intramembranous„ rather than subetelial deposits Event. We recognize stage V – reparation of epithel
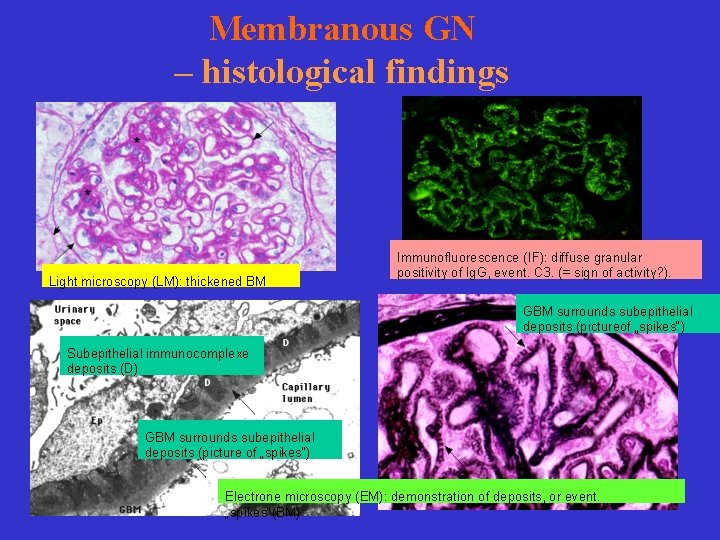
Membranous GN – histological findings Light microscopy (LM): thickened BM Immunofluorescence (IF): diffuse granular positivity of Ig. G, event. C 3. (= sign of activity? ). GBM surrounds subepithelial deposits (pictureof „spikes“) Subepithelial immunocomplexe deposits (D) GBM surrounds subepithelial deposits (picture of „spikes“) Electrone microscopy (EM): demonstration of deposits, or event. „spikes“(BM)
Etiology of membranous GN 1. Idiopathic MGN 2. Secondary MGN (therapy different from therapy of idiopthic MGN) - infection (hepatitis B, syphilis, malaria) - drugs (organic gold, penicillamine, NSAID) - tumors (carcinomas, for ex. Ca of coli, lung Ca, or gastric Ca, also lymphomas) - systemic lupus erythematosus
Idiopathic membranous GN - basic characteristics 1. Membranous GN accounts for 15 -25% cases of NS in adults 2. Proteinuria of nephrotic range is present approxiomately in 80% of patients, in the remaining subgroup the proteinuria is less pronounced 3. Microscopic hematuria is frequent 4. Hypertension and ESRD are not initial symptoms, but may develop during the further course of the disease. 5. Histology – subepithelial deposit leading to thickening of GBM
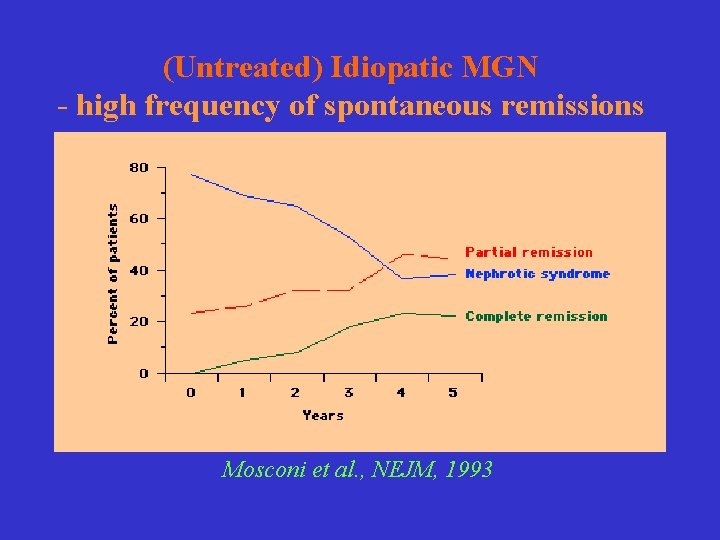
(Untreated) Idiopatic MGN - high frequency of spontaneous remissions Mosconi et al. , NEJM, 1993
Idiopatic membranous GN - natural course of the disease 1. Spontaneous remission develops approximately in 1/3 of patients 2. Nephrotic syndrome outlasts in other 1/3 of patients 3. Approximately 20 -30% of patients do progress to ESRD during 20 -30 y of follow-up
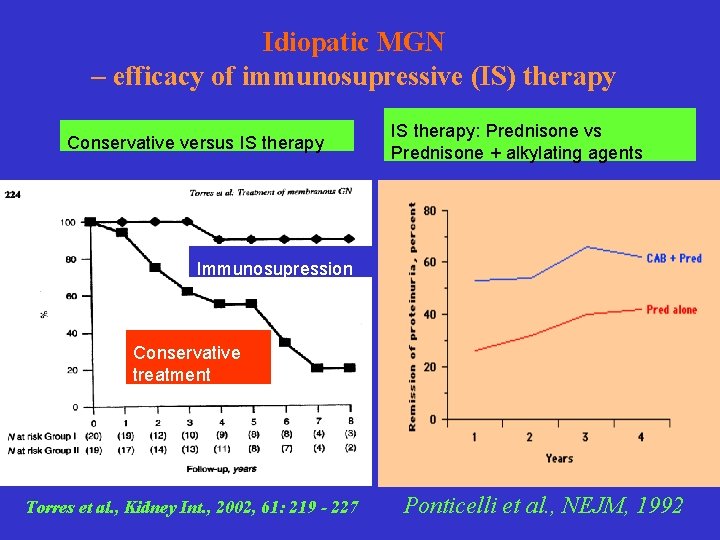
Idiopatic MGN – efficacy of immunosupressive (IS) therapy Conservative versus IS therapy: Prednisone vs Prednisone + alkylating agents Immunosupression Conservative treatment Torres et al. , Kidney Int. , 2002, 61: 219 - 227 Ponticelli et al. , NEJM, 1992
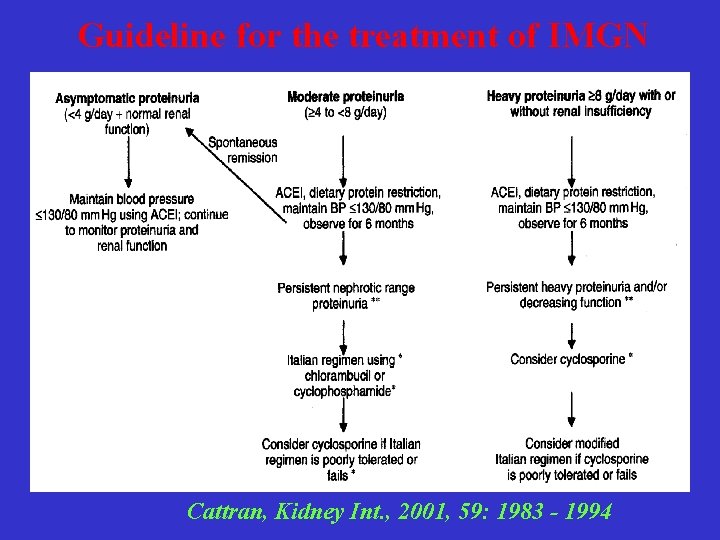
Treatment of idiopatic MGN 1. Before starting IS therapy do consider its necessity, do exploit the profit of conzervative treatment (ACEi, ABR) 2. Cortikosteroids only partially efficient in monotherapy 3. Cytotoxic agents (cyclophosphamide, leukerane) bring about long-term remission of NS and ameliorate renal survival. With regard to serious side-effects these agents should be reserved to patients with serious involvement/resp. with progressing form of MGN 4. Cyklosporine seems to be satisfactory alternative to cytotoxic therapy. The impact on proteinuria is clear, however the effect on stabilisation of disease is questionable. There is concern about relapse after withdraval.
Guideline for the treatment of IMGN Cattran, Kidney Int. , 2001, 59: 1983 - 1994
Proliferative versus neproliferative GN (glomerular capillary loop – ultrastructural changes) Epitheliál cells=podocytes Urinary space Basal membrane Capillary lumen Mesangial cells Subendothelial deposits Acute GN Increased number and proliferation of mesangial cells neutrophils Proliferative GN Subepithelial deposits Endotehelial cells Increaed number and proliferation of mesangial cells to distal parts of capillary loop Normal glomerulus Increased number and proliferation of mesangial cells mesangial deposits of Ig. A Mesangioproliferative GN Subendothelial deposits neutrophils Membranoproliferative GN