Gastrointestinal Disorders and Immunotherapy for POTS MCAS EDS




























- Slides: 55
Gastrointestinal Disorders and Immunotherapy for POTS, MCAS, & EDS Leonard Weinstock, MD, FACG Specialists in Gastroenterology
Disclosures • Speakers bureau: Salix Syndromes don’t get no respect
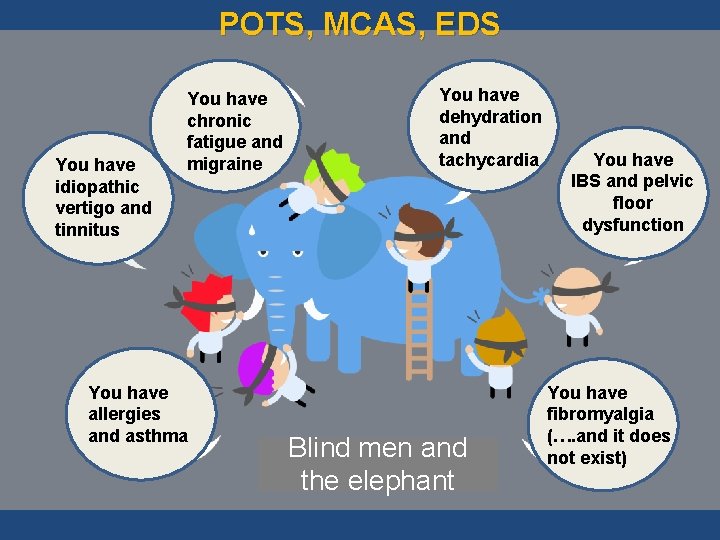
POTS, MCAS, EDS You have idiopathic vertigo and tinnitus You have chronic fatigue and migraine You have allergies and asthma You have dehydration and tachycardia Blind men and the elephant You have IBS and pelvic floor dysfunction You have fibromyalgia (…. and it does not exist)
19 MD’s Sick for 25 yrs
Age 18 – Trigger-induced flushing, rash, nausea Age 20 - Bloating, constipation, bad gas Ages 23 -43 - Weak, painful dependent edema, ortho. lightheaded & tachy, syncope, body pain, stopped sweating Ages 37 -43 - 45 Sx: above + fatigue, brain fog, HA, vertigo, tinnitus, dry mouth, vision prob. , nocturia, pressure-induced urticaria, cyanosis, early satiety, pelvic floor dysfx, … No sleep/rest, liquid diet, syncope with straining, unable to tolerate warmth Mayo… Dx. . but failed 12 POTS & MCAS meds, thyroid Rx, salt, and stockings
Thinking Inside Our Own GI Box For this case - tempting to think separate sx = separate diseases • • • Nausea Abdominal pain Constipation Bloating Flatulence Anal outlet disorder … remarkable ROS…Dx
My Own Blindness • 34 y. o. WF w 17 yrs abd pain, GERD, diarrhea, >250 ER visits; 5 universities • W/U and Rx – every known test, +LBT & SOD: failed CCK, 9 ERCPs, and all IBS and GERD Rx • Tachycardia w/u: + tilt table • New Medical Therapy – no GI Sx for 14 mo…
POTS: Systemic Syndrome • • • Esophagus – GERD, dysphagia Stomach – slow or rapid gastric emptying Intestinal and sphincter dysmotility CNS – migraines/HA, brain fog, anxiety, depres. Urinary tract - inability to empty the bladder Ocular – inability to accommodate Salivary glands – dry mouth Skin – flushing, rashes, swelling Extremities – pain, swelling, vasospasm Benarroch. Mayo Clin Proc 2012
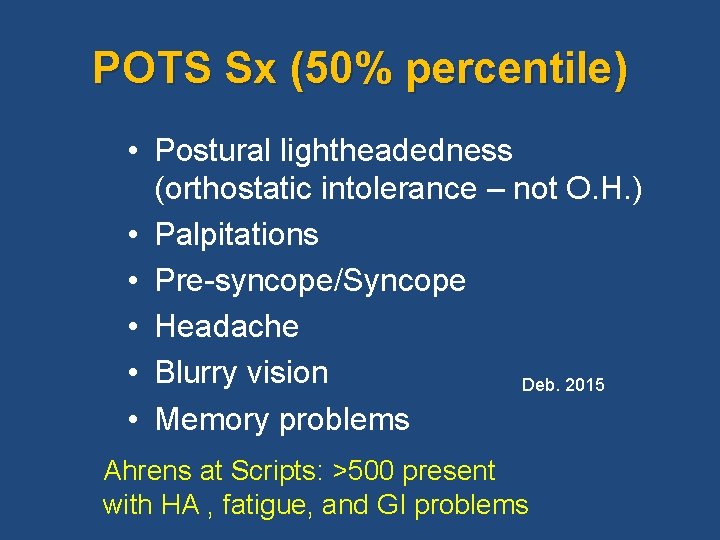
POTS Sx (50% percentile) • Postural lightheadedness (orthostatic intolerance – not O. H. ) • Palpitations • Pre-syncope/Syncope • Headache • Blurry vision Deb. 2015 • Memory problems Ahrens at Scripts: >500 present with HA , fatigue, and GI problems
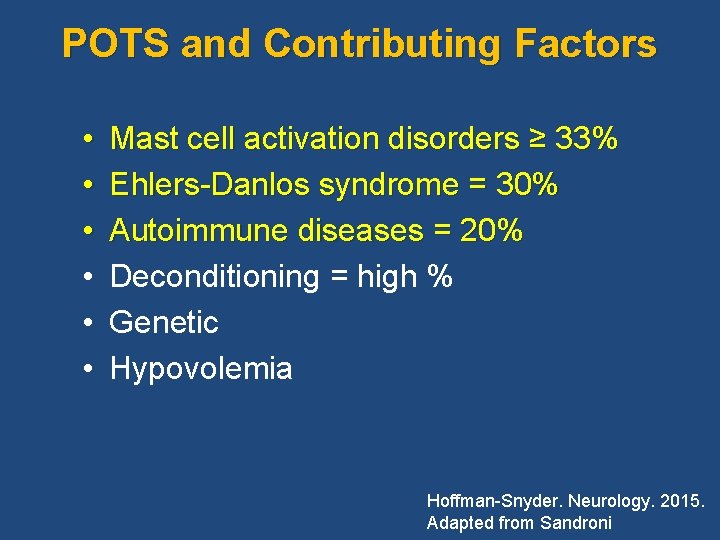
POTS and Contributing Factors • • • Mast cell activation disorders ≥ 33% Ehlers-Danlos syndrome = 30% Autoimmune diseases = 20% Deconditioning = high % Genetic Hypovolemia Hoffman-Snyder. Neurology. 2015. Adapted from Sandroni
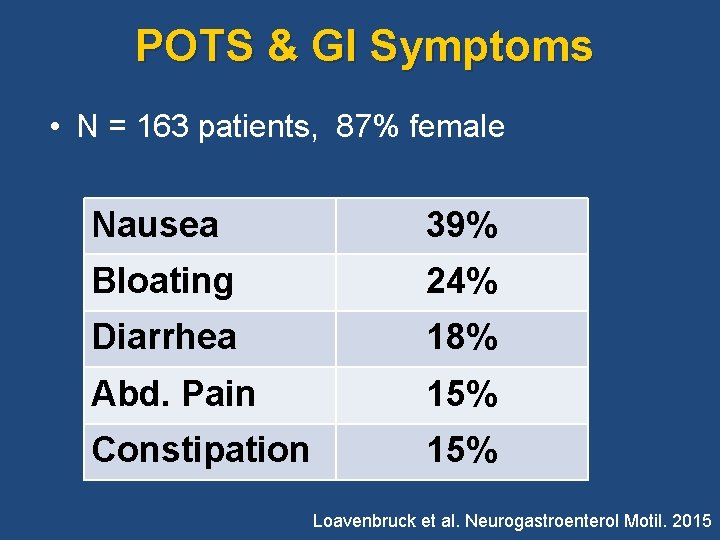
POTS & GI Symptoms • N = 163 patients, 87% female Nausea 39% Bloating 24% Diarrhea 18% Abd. Pain 15% Constipation 15% Loavenbruck et al. Neurogastroenterol Motil. 2015
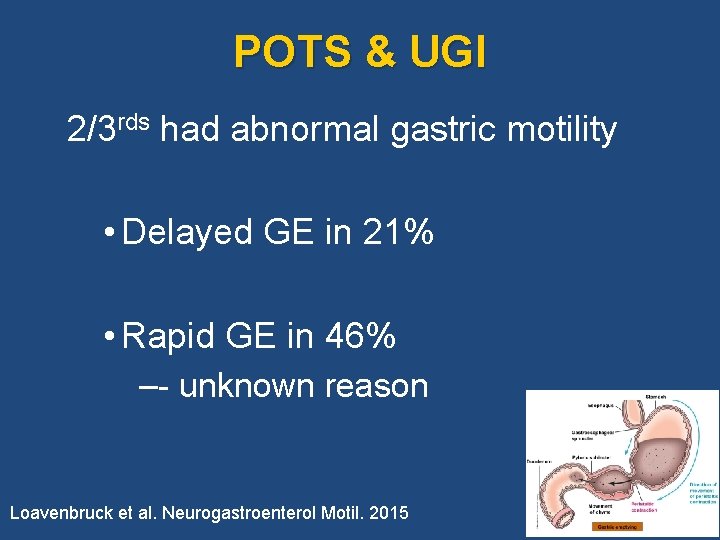
POTS & UGI 2/3 rds had abnormal gastric motility • Delayed GE in 21% • Rapid GE in 46% –- unknown reason Loavenbruck et al. Neurogastroenterol Motil. 2015
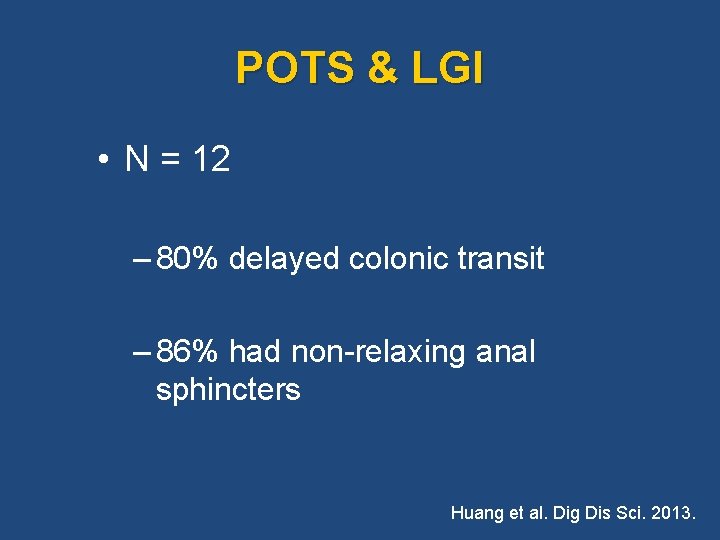
POTS & LGI • N = 12 – 80% delayed colonic transit – 86% had non-relaxing anal sphincters Huang et al. Dig Dis Sci. 2013.
POTS & “IBS” • In review articles IBS stated to be common • Visceral sensitivity is mediated by sensory afferent nerves - not autonomic • Consider SIBO & MC disease
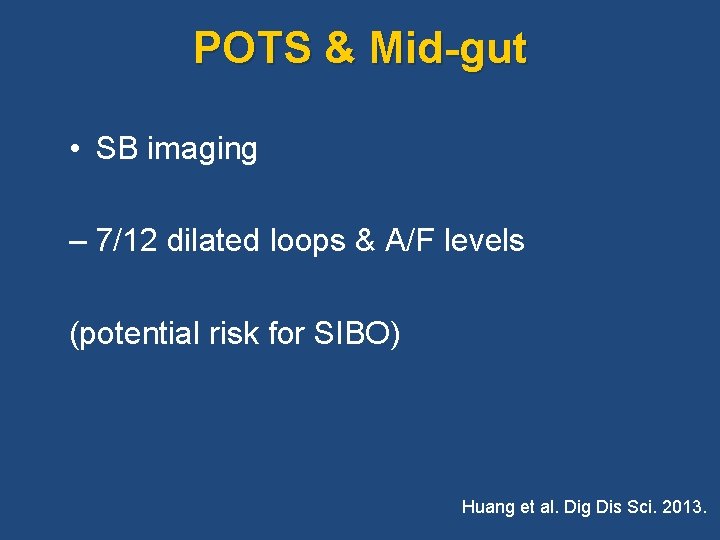
POTS & Mid-gut • SB imaging – 7/12 dilated loops & A/F levels (potential risk for SIBO) Huang et al. Dig Dis Sci. 2013.
Ehlers-Danlos Syndrome Point each for: Palms to floor - 1 Thumbs to wrist - 2 Pinky back 90 o - 2 Elbows hyperextend - 2 Knees hyperextend - 2 Positive if ≥ 4
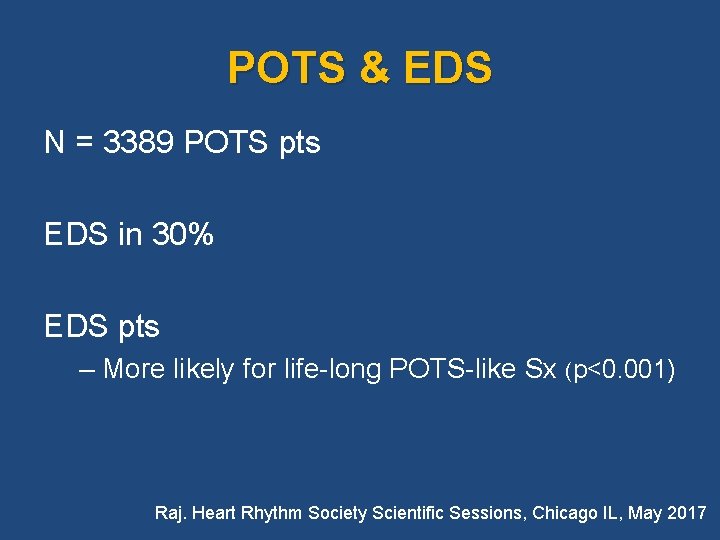
POTS & EDS N = 3389 POTS pts EDS in 30% EDS pts – More likely for life-long POTS-like Sx (p<0. 001) Raj. Heart Rhythm Society Scientific Sessions, Chicago IL, May 2017
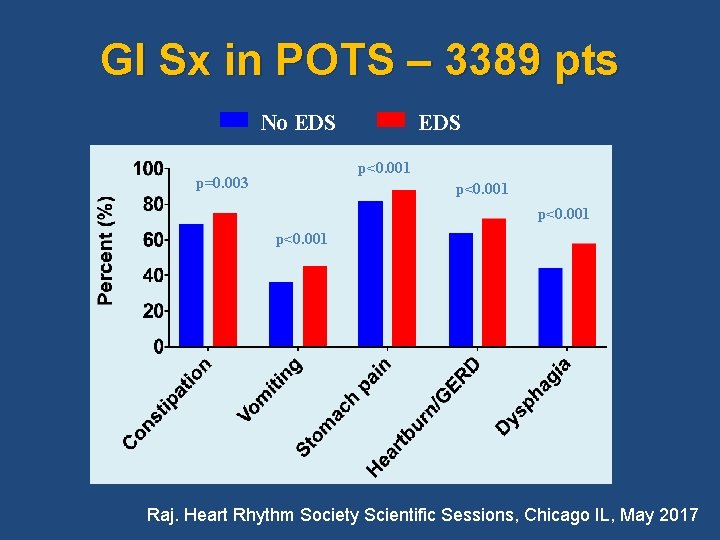
GI Sx in POTS – 3389 pts No EDS p<0. 001 p=0. 003 p<0. 001 Raj. Heart Rhythm Society Scientific Sessions, Chicago IL, May 2017
Ehlers-Danlos Syndrome and MCAS EDS pts: increased frequency of MCAS Immunohistochemistry analysis: increased MC in uninvolved skin Luzgina. 2011. Sevenviratne. 2017.
Normal Mast Cells Biology: • Produced in marrow • Circulates in immature form • Goes to sites of inflamm. & T-cell activity • Lives in mucosa and by vessels/nerves Functions: • Wound healing • Angiogenesis • Immune tolerance • Defense against pathogens • Blood–brain barrier function
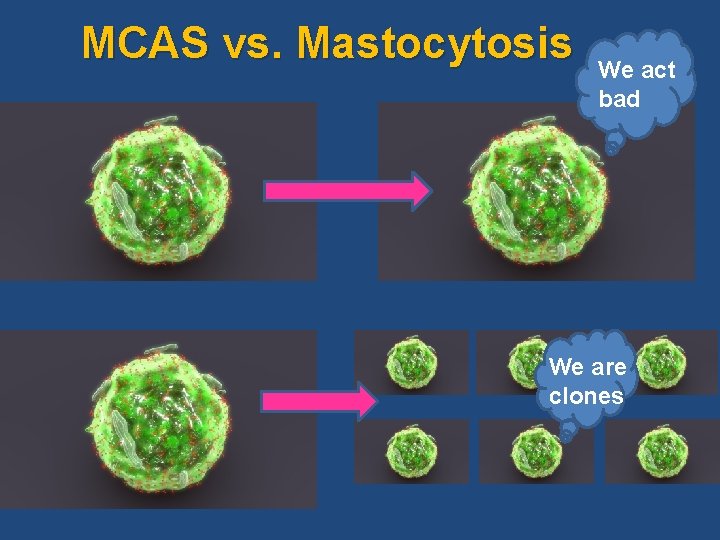
MCAS vs. Mastocytosis We act bad We are clones
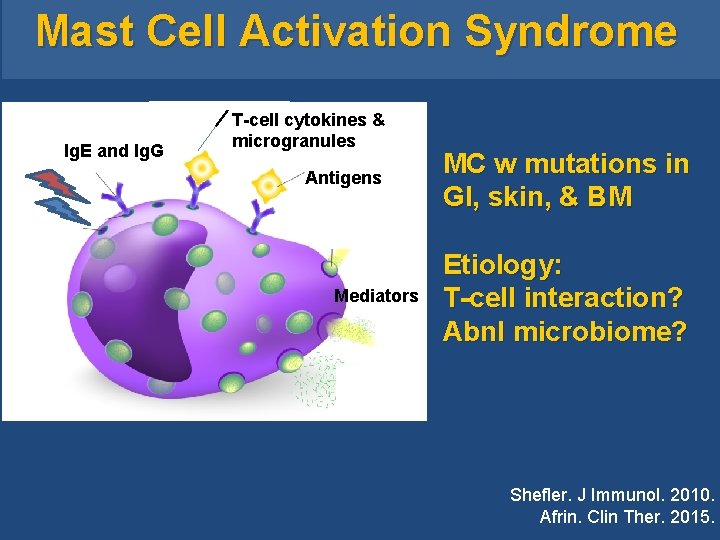
Mast Cell Activation Syndrome Ig. E and Ig. G T-cell cytokines & microgranules Antigens Mediators MC w mutations in GI, skin, & BM Etiology: T-cell interaction? Abnl microbiome? Shefler. J Immunol. 2010. Afrin. Clin Ther. 2015.
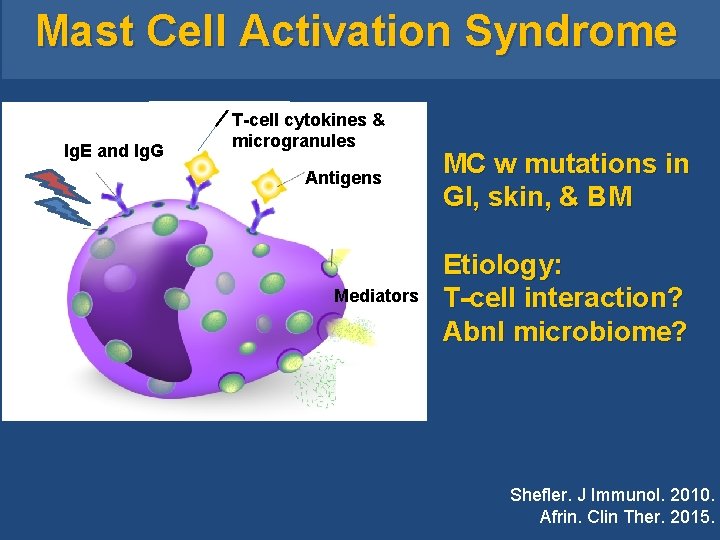
Mast Cell Activation Syndrome Ig. E and Ig. G T-cell cytokines & microgranules Antigens Mediators MC w mutations in GI, skin, & BM Etiology: T-cell interaction? Abnl microbiome? Shefler. J Immunol. 2010. Afrin. Clin Ther. 2015.
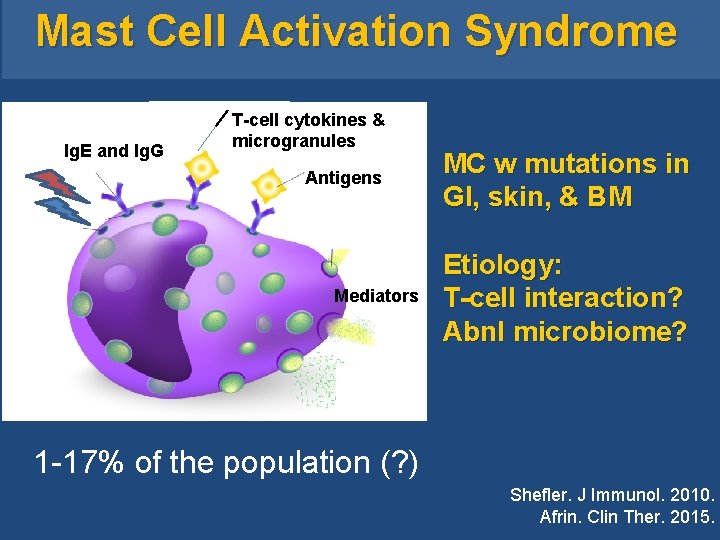
Mast Cell Activation Syndrome Ig. E and Ig. G T-cell cytokines & microgranules Antigens Mediators MC w mutations in GI, skin, & BM Etiology: T-cell interaction? Abnl microbiome? 1 -17% of the population (? ) Shefler. J Immunol. 2010. Afrin. Clin Ther. 2015.
MCAS: Mediators • 200 mediators • • Histamine Heparin Typtase Pro-inflammatory cytokines (TNF-α…) Proteases Vascular permeability/dilators Leukotrienes Platelet aggregation factor … www. Cells-Talk. com
MCAS: Systemic Syndrome • • • Esophagus – GERD, dysphagia Stomach – gastritis, dyspepsia Colon – diarrhea, constipation Liver – abnormal liver chemistries CNS – migraines/HA, brain fog, panic attacks, anxiety, depression CVS - tachycardia Urinary tract – interstitial cystitis Ocular – conjunctivitis Salivary glands – swelling Skin – flushing, rashes, swelling Extremities – pain, swelling, vasospasm Constitutional – fatigue, fever, wt. loss/gain Afrin. 2017
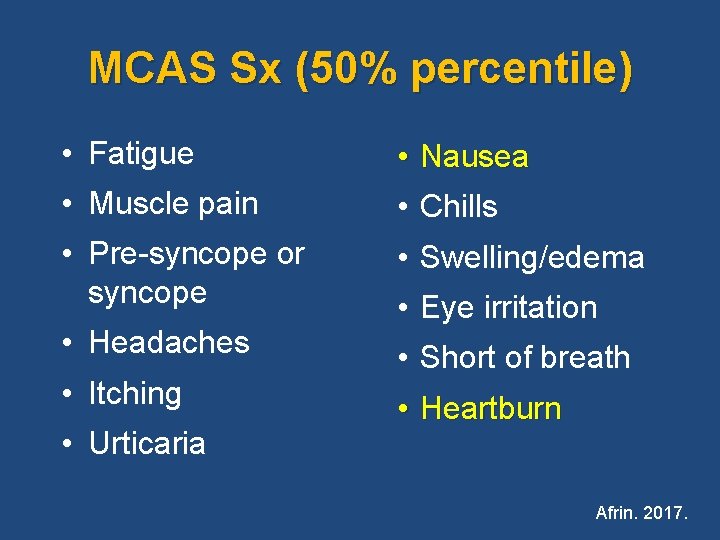
MCAS Sx (50% percentile) • Fatigue • Nausea • Muscle pain • Chills • Pre-syncope or syncope • Swelling/edema • Headaches • Short of breath • Itching • Urticaria • Eye irritation • Heartburn Afrin. 2017.
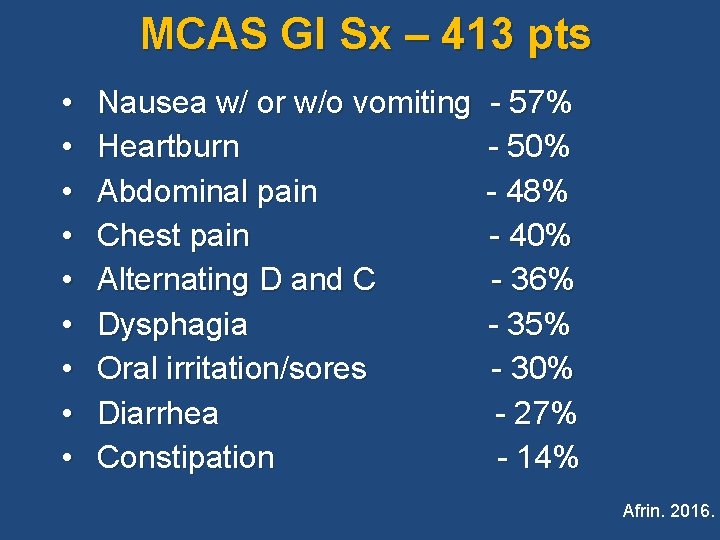
MCAS GI Sx – 413 pts • • • Nausea w/ or w/o vomiting - 57% Heartburn - 50% Abdominal pain - 48% Chest pain - 40% Alternating D and C - 36% Dysphagia - 35% Oral irritation/sores - 30% Diarrhea - 27% Constipation - 14% Afrin. 2016.
MC & UGI Esophagus • Pain and dysphagia: 2 recent case reports – C/P & increased distal pressure – MC seen – C/P & dysphagia - MC seen - responded to MC Rx • Heartburn – Histamine-induced hyperacidity – LES changes by different mediators? Lee. Gut Liver. 2016. Parks. Dis Esophagus. 2015. Benedicte. BBA. 2012.
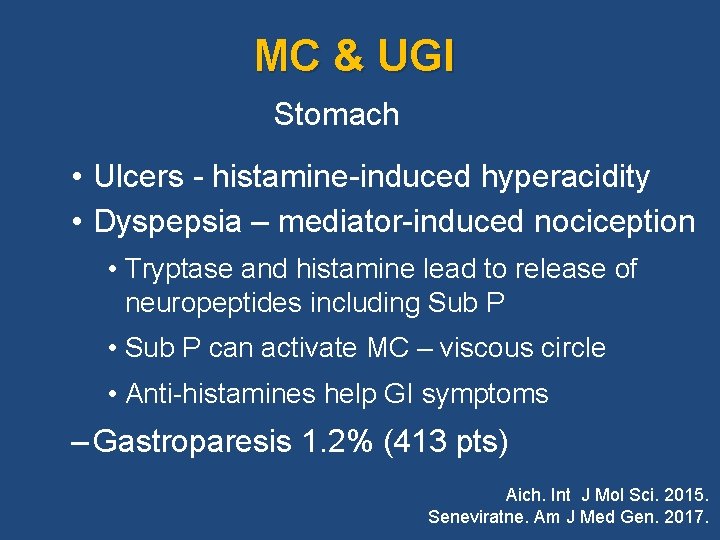
MC & UGI Stomach • Ulcers - histamine-induced hyperacidity • Dyspepsia – mediator-induced nociception • Tryptase and histamine lead to release of neuropeptides including Sub P • Sub P can activate MC – viscous circle • Anti-histamines help GI symptoms – Gastroparesis 1. 2% (413 pts) Aich. Int J Mol Sci. 2015. Seneviratne. Am J Med Gen. 2017.
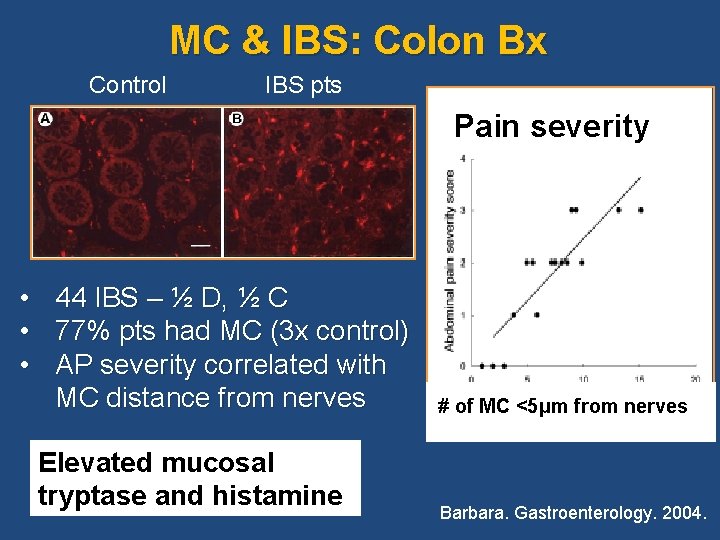
MC & IBS: Colon Bx Control IBS pts Pain severity • 44 IBS – ½ D, ½ C • 77% pts had MC (3 x control) • AP severity correlated with MC distance from nerves # of MC <5μm from nerves Elevated mucosal tryptase and histamine Barbara. Gastroenterology. 2004.
MC & LGI: Pain – Proximity to nerves (2 human studies) – Incr. intraluminal tryptase (2 human studies) – Incr. visceral hypersensitivity - IBS pts mucosal mediators increased rat mesenteric nerve firing & Ca++ in dorsal root ganglia neurons – Incr. proteases - IBS pt mucosal mediators led to incr. somatic and visceral pain in mice – Incr. visceral hypersensitivity assoc. w fungal dysbiosis (animal study) Guilarte. Gut. 2007. Cenec. J Clin Invest. 2007. Benedicte. BBA. 2012. Barbara. Gastroenterology. 2004 and 2007.
MC in Refractory IBS-D • N=20 refractory IBS-D – Sx of MCAS in 19 pts – Coag. & fibrinolysis factors detected in 11/12 tested • N = 3 refractory IBS-D – Omalizumab (Xolair) - reduces Ig. E-induced MC activity led to complete remission • MC stabilizer Rx: – Cromolyn (67% of 200 pts improved) – Ketotifen (RTC 60 pts) less visceral hypersensitivity Frieling. Z Gastro 2011, Stefanini. Scand J Gastro 1995, Magen W J Gastro 2016, Klooker. Gut 2010.
MC & Constipation Full-thickness Bx w surgery for slow transit constipation (n=29) vs. controls • Constipated pts - significantly higher # MC • Degranulated MC close to enteric glial cells and filaments in pts Bassotti. Aliment Pharmacol Ther. 2017.
MCAS & Liver • AST, ALT, AP inc – 40% in 413 pt • High chol in 75% & LFT inc in 40% of 40 pts – Down-regulated chitotriosidase expression in MC Afrin. Am J Med Sci. 2017. Alfter. Liver Int. 2009.
MC Detection and Activation • Basic stains do not see them • Request CD 117 stain (>20 MC/HPF) • Labs may not reflect local activation
Usual POTS Rx Cardiovascular Rx and anal PT Bennoch 2012
Usual EDS Rx - Orthopedic procedures - Joint stabilizers - Collagen injections - Physical therapy - Pain medicines
Usual MCAS Rx Mediator effectors & MC receptor blockers: H 1/H 2 blockers, vit C, montelukast, zileuton, ASA Mast cell stabilizers: quercetin, cromolyn, ketotifen Advanced Rx: amalizumab, etoricoxib, hydroxyurea, tamoxifen, steroids, mercaptopurine, methotrexate, cyclosporine, initinib, sunitinib Afrin 2016.
MCAS Rx: additional Rx Avoid triggers: food, scents, temperature Gluten, yeast, cow milk protein free Low histamine diet – MC has H-1, 2, 3, 4, 5 receptors Natural: Vit B - 6, 9, 12, omega-3, α lipoic acid, N-acetylcysteine, SAMe, DAO, Bifidobacter, L. rhamnosus FODMAP-free – theoretically could help (decreases histamine and improves microbiome) Molderings. Naum S Arch Pharm. 2016. Theoharides. Ann All Asth Immunol. 2004.
Immune therapy for GI disorders, POTS, MCAS, and EDS
Immunotherapy for Autoimmune GI Dysmotility • Slow transit – gastric 11, SB 12, colon 11 • Rx 6 – 12 wks: IVIG 0. 4 gm/kg (16), methylprednisolone 1000 mg/d/3 then weekly (5) or both (2) • 74% improved Sx and testing, 21% Sx only, and 17% testing only Flanagan. Neurogastroenterol Motil. 2014.
Immunotherapy for Autoimmune Gastroparesis • Pts with autoimmune dysautonomia and drug/pacer resistant GP • 11 F, pos GAD-65, Rx 8 -12 wks: 1) IVIg, 2) mycophenolate mofetil (MM) + IV steroid, or 3) MM • Max improvement w IVIg (67%): 6 pts (55%) improved V and 5 pts (45%) improved N, AP, & Bloat Soota. Results Immunol. 2016.
IVIg for Autonomic Neuropathy • 2017 – 1 st case of a POTS pt - remission • Approved in other autonomic and autoimmune neurologic diseases • Online interviews: 9/13 improved: ranged from no help/terrible SE to miraculous, got my life back, life changing, sensational, huge improvement, magic, amazing • Not FDA-approved for POTS Goodman. Am J Ther. 2017. Zivkovic. Acta Neurol Scan. 2015. Brooks, Weinstock. Manuscript under review. 2017.
Low Dose Naltrexone • Short acting opioid antagonist • Increases endorphins which regulate T -cell and B-cell activity and cell growth • Reduces inflammation (cytokine) and autoantibody production • Decreases pain
Endorphins • Endorphins activate Mu-receptor – endogenous opioid effect for analgesia • Regulate T-cells – Reduce cytokines and subsequent sensory pain – Reduce cytokines and subsequent mast cell activity
LDN Directly Reduces Pain • Microglia – nerve cells – Multiple disorders have activated microglia causing neuroexitability and enhanced pain via Toll-like receptor 4 pathway • LDN blocks this receptor Li. Med Hypotheses 2012; 79: 754 -6. Hutchinson et al. Brain Behav Immun 2010; 24: 83 -95.
Personal Experience with Pain Disorders and LDN Rx • • Irritable bowel syndrome Restless legs syndrome Fibromyalgia Sarcoidosis Ehlers-Danlos syndrome Complex regional pain syndrome POTS MCAS
EDS and LDN Rx • Ehlers-Danlos syndrome: joint pain d/t: – Entrapment of nerves owing to subluxations of joints or thoracic outlet obstruction – Increased glial activity in brain which irritates brain or spinal column sensory nerves – CRPS – Mast cells in tissues or next to nerves Scheper. Arthritis Care Res. 2017. Weinstock. A A reports. 2016. Seneviratne. Am J Med Genet C Semin Med Genet. 2017
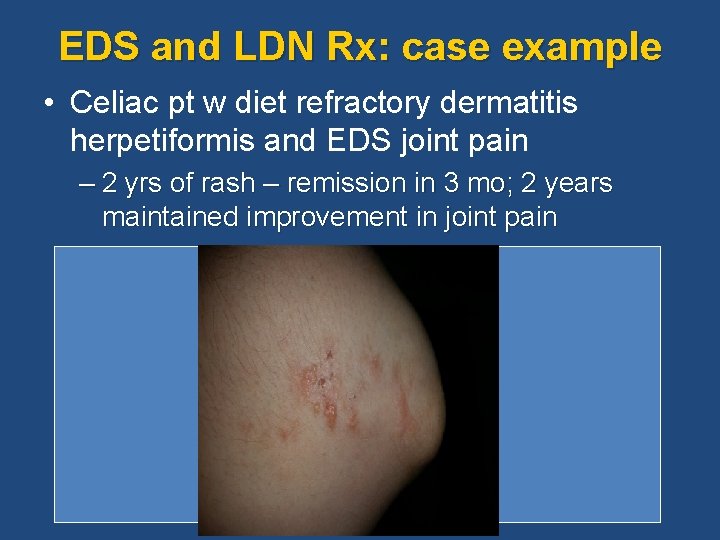
EDS and LDN Rx: case example • Celiac pt w diet refractory dermatitis herpetiformis and EDS joint pain – 2 yrs of rash – remission in 3 mo; 2 years maintained improvement in joint pain
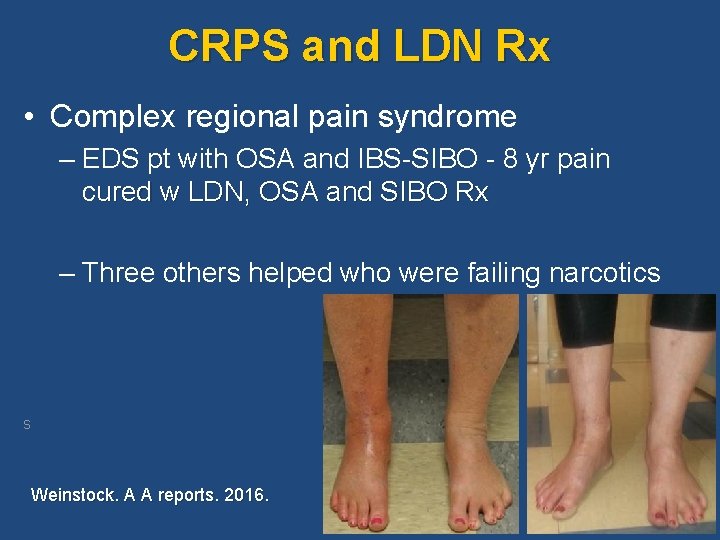
CRPS and LDN Rx • Complex regional pain syndrome – EDS pt with OSA and IBS-SIBO - 8 yr pain cured w LDN, OSA and SIBO Rx – Three others helped who were failing narcotics s Weinstock. A A reports. 2016.
Novel Rx for MCAS and POTS
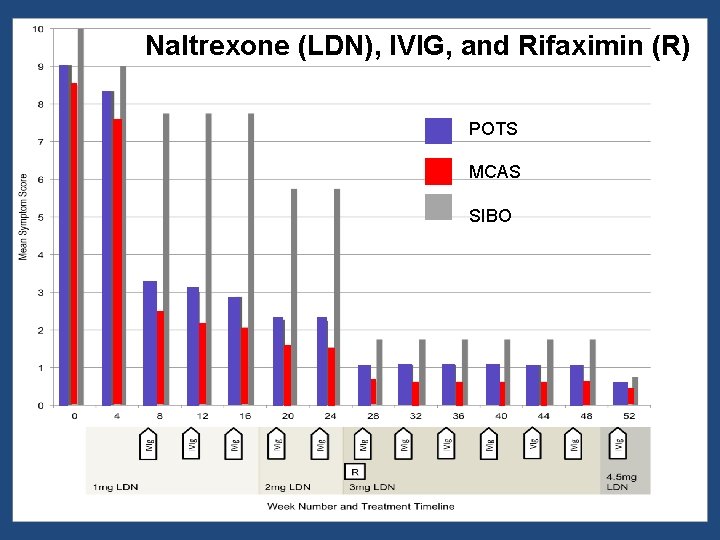
Naltrexone (LDN), IVIG, and Rifaximin (R) POTS MCAS SIBO
POTS & SIBO N = 27 (26 F, 27% MCAS, 42% EDS) LBT abnl in 19/27 (69%) Antibiotics helped: GI Sx in 10/15 POTS Sx in 4/15 LDN helped: GI Sx in 7/11 POTS/MCAS Sx in 5/11 (1 POTS, 2 both, 2 MCAS)
Summary • GI problems are common in POTS, EDS, & MCAS • Systemic problem not “somatic” • New therapeutic options