Contraception Update 2018 Dr Caroline Marfleet Consultant in






































- Slides: 60
Contraception Update 2018 Dr Caroline Marfleet Consultant in Sexual and Reproductive Healthcare
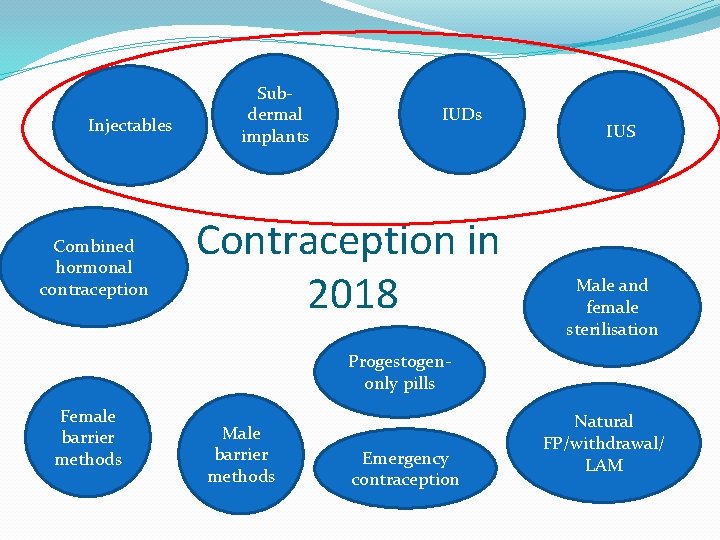
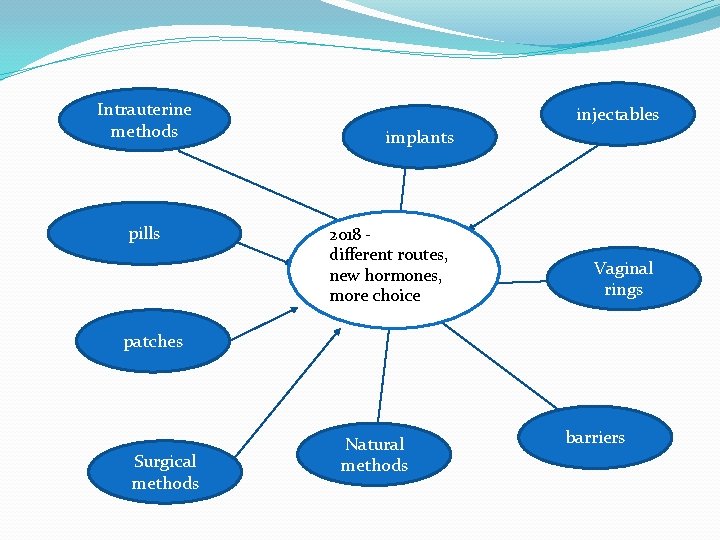
Injectables Combined hormonal contraception Subdermal implants IUDs Contraception in 2018 IUS Male and female sterilisation Progestogenonly pills Female barrier methods Male barrier methods Emergency contraception Natural FP/withdrawal/ LAM
Women are all different! No one method will suit all women
Choosing a method of contraception Safe Effective Reliable Easy to use Few side effects Easy to remember What’s important to women when deciding on a method of contraception? Easy access No effect on future fertility Minimal effect on periods Minimal medical interference
At the initial visit: ● A full sexual, reproductive and medical history need to be taken including: ✓Present and past use of contraception ✓History of migraine & risk factors for cardiovascular disease eg smoking; previous VTE; hyperlipidaemia ✓Any personal medical history ✓Drug use (prescription, non-prescription & herbal) ✓Family history – VTE; stroke; arterial disease; breast cancer; diabetes; other ● BP should be documented ● Height, weight & BMI should be documented
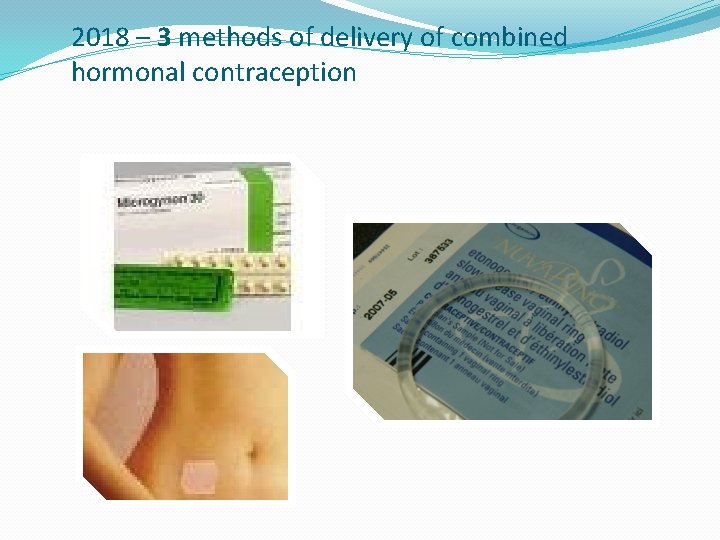
2018 – 3 methods of delivery of combined hormonal contraception
WHICH CHC? • Types of OCPs – combined and progestogen-only • Ethinyl oestradiol and progestogens • Oestradiol valerate /hemihydrate(body-identical oestrogen) and progestogen • Routes of administration -pill. patch, ring • Risks and benefits to individuals • Side effects relating to oestrogens/progestogens • Which pill and managing side effects
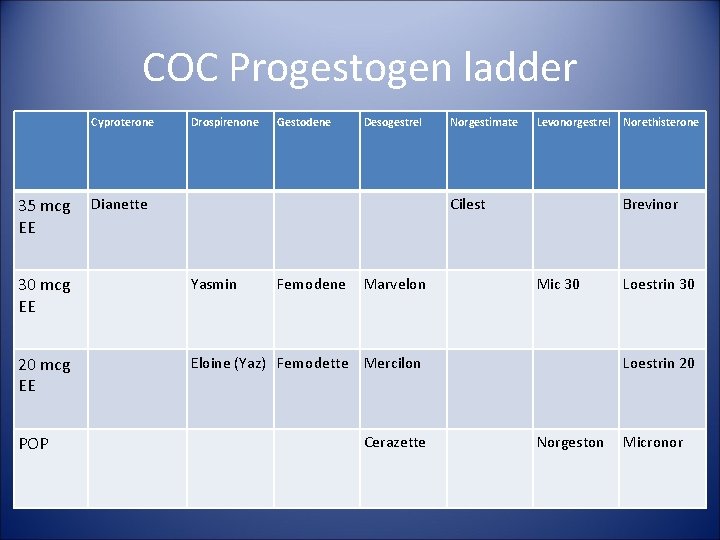
COC Progestogen ladder Cyproterone 35 mcg EE Drospirenone Gestodene Desogestrel Dianette Levonorgestrel Cilest 30 mcg EE Yasmin 20 mcg EE Eloine (Yaz) Femodette Mercilon POP Norgestimate Femodene Marvelon Cerazette Norethisterone Brevinor Mic 30 Loestrin 20 Norgeston Micronor
Androgenicity series Norethisterone Levonorgestrel Gestodene Desogestrel Drospirenone Cyproterone acetate
Choice of COCP by progestogen More oestrogen dominant • Drospirenone • Norgestimate • Gestodene • Desogestrel Less oestrogen dominant • Levonorgestrel group • Norethisterone group
Which COC? Oestrogen dominant COCs • Cilest • Marvelon • Femodene • Dianette • Yasmin Progestogen dominant COCs • Microgynon 30 • Loestrin 30
Side effects Oestrogenic Progestogenic • Nausea • Bloating • Weight gain (water retention) • Vaginal discharge (no infection) • Breast enlargement/tenderness • Some headaches • Chloasma • Photosensitivity • • Acne Greasy hair Hirsutism Weight gain (increased appetite) • Depression • Loss of libido • Vaginal dryness
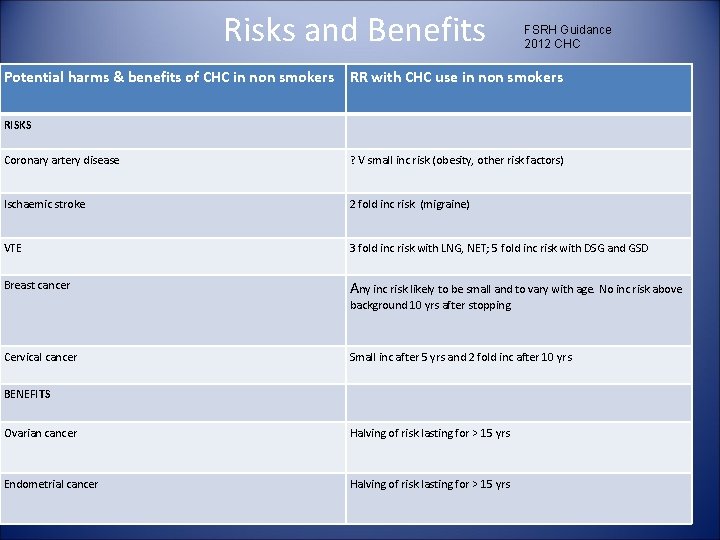
Risks and Benefits FSRH Guidance 2012 CHC Potential harms & benefits of CHC in non smokers RR with CHC use in non smokers RISKS Coronary artery disease ? V small inc risk (obesity, other risk factors) Ischaemic stroke 2 fold inc risk (migraine) VTE 3 fold inc risk with LNG, NET; 5 fold inc risk with DSG and GSD Breast cancer Any inc risk likely to be small and to vary with age. No inc risk above background 10 yrs after stopping Cervical cancer Small inc after 5 yrs and 2 fold inc after 10 yrs BENEFITS Ovarian cancer Halving of risk lasting for > 15 yrs Endometrial cancer Halving of risk lasting for > 15 yrs
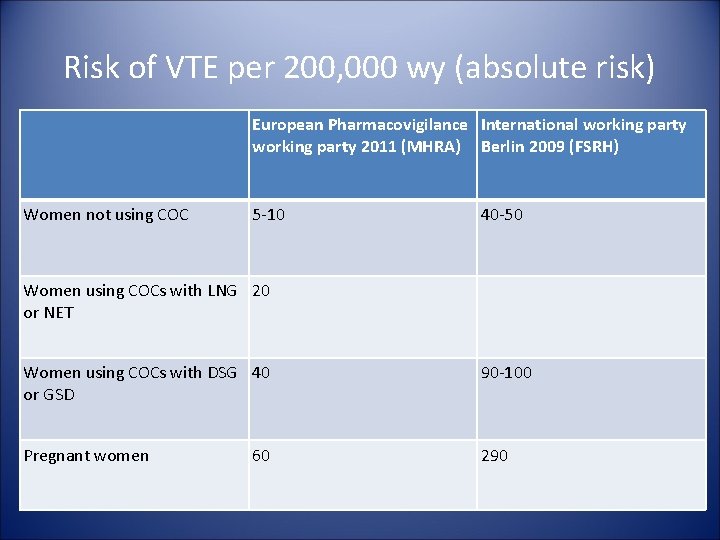
Risk of VTE per 200, 000 wy (absolute risk) European Pharmacovigilance International working party 2011 (MHRA) Berlin 2009 (FSRH) Women not using COC 5 -10 40 -50 Women using COCs with LNG 20 or NET Women using COCs with DSG 40 or GSD 90 -100 Pregnant women 290 60
COCs and risk of VTE • • BMI and smoking are significant risk factors Smoking doubles the risk BMI 30 -35 doubles the risk BMI > 35 has a 4 -6 fold increased risk BMI 30 -34= UKMEC 2 BMI > 35 = UKMEC 3 Smoking age < 25 yrs UKMEC 2 Smoking age > 35 yrs UKMEC 3 (<15/day) or UKMEC 4 (> 15 day)
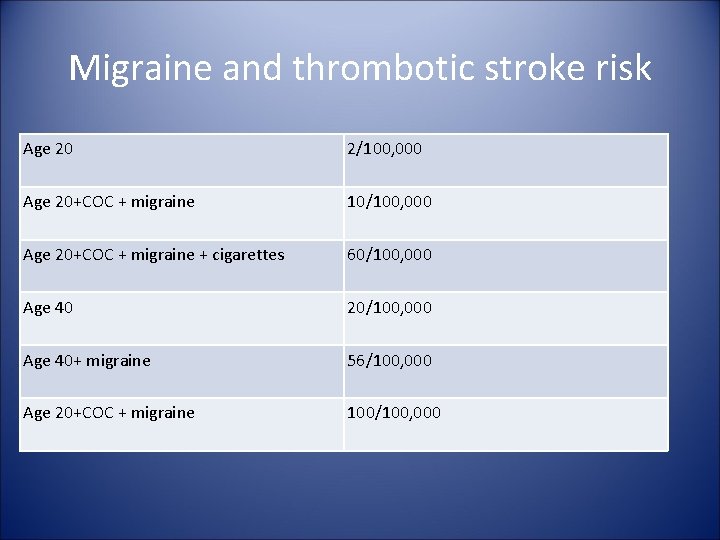
Migraine and thrombotic stroke risk Age 20 2/100, 000 Age 20+COC + migraine 10/100, 000 Age 20+COC + migraine + cigarettes 60/100, 000 Age 40 20/100, 000 Age 40+ migraine 56/100, 000 Age 20+COC + migraine 100/100, 000
Non contraceptive health benefits of oral contraceptives Endometriosis; dysmenorrhoea and ovulatory pain Menorrhagia; Fe deficiency anaemia; fibroids Endometrial and ovarian cancer; colon cancer Acne; hirsutism; symptoms of PCOS Functional ovarian cysts; PID; benign breast disease; rheumatoid arthritis • PMS • RCGP study - women in the UK who have ever used the oral contraceptive pill are less likely to die from any cause, including all cancers and heart disease, compared with never users • • • FSRH Guidance 2012 CHC
Reasons to stop immediately • Serious neurological effects (prolonged headache, getting worse) • Partial or complete loss of vision • Sudden disturbance of hearing or other perceptual disorders • Dysphasia • 1 st epileptic seizure or weakness, motor disturbance or numbness affecting one side or part of body Sudden chest pain Sudden breathlessness Haemoptysis Severe pain in one calf Hepatitis, jaundice, enlarged liver • Severe depression • BP > 100/160 • Detection of a risk factor (UKMEC) • • • FSRH Guidance 2012 CHC
Yasmin ● Monophasic COC with 30 mcg EE + Drospirenone 3 mg ● It acts as an anti-androgen & is therefore an alternative to Dianette for women with moderate acne or PCOS ● It has diuretic properties due to antimineralocortocoid activity ● It offers a useful oestrogen dominant pill for control of minor side effects such as bloating and cyclical breast enlargement ● EURAS and Ingenix studies – no difference in VTE risk compared with 2 nd generation OCs
Yasmin GPRD (UK) + Pharmetrics (US) Both showed a 2 -3 fold increase of VTE BUT – GPRD – low numbers, data missing (obesity), case mix not reflecting clinical practice ● Pharmetrics – incomplete data on obesity, unrelaible data on duration of exposure to Ocs ● ● ● Evidence for increased risk is inconclusive and absolute risk of VTE when using low dose OCs is small
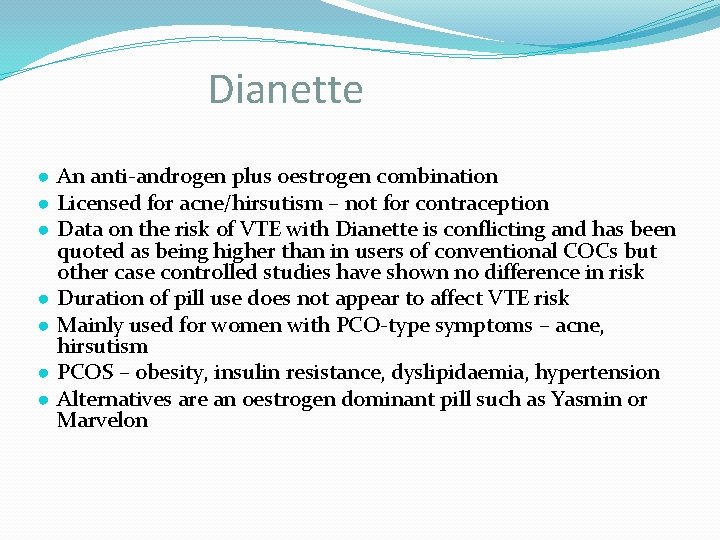
Dianette ● An anti-androgen plus oestrogen combination ● Licensed for acne/hirsutism – not for contraception ● Data on the risk of VTE with Dianette is conflicting and has been quoted as being higher than in users of conventional COCs but other case controlled studies have shown no difference in risk ● Duration of pill use does not appear to affect VTE risk ● Mainly used for women with PCO-type symptoms – acne, hirsutism ● PCOS – obesity, insulin resistance, dyslipidaemia, hypertension ● Alternatives are an oestrogen dominant pill such as Yasmin or Marvelon
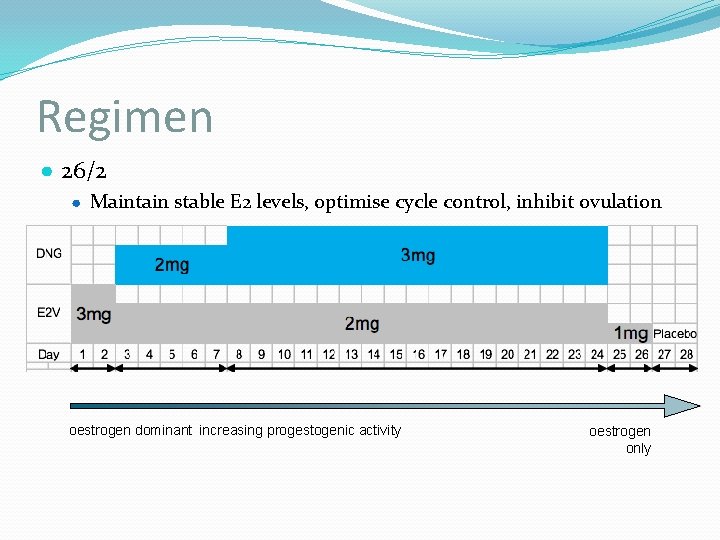
Qlaira ● COC containing estradiol valerate (E 2 V) and dienogest (DNG) ● E 2 V Estradiol (E 2 = natural oestrogen) ● DNG offers good suppression of endometrial proliferation ● The first and only COC to deliver E 2 ● The first product in the UK to contain DNG
Regimen ● 26/2 ● Maintain stable E 2 levels, optimise cycle control, inhibit ovulation oestrogen dominant increasing progestogenic activity oestrogen only
Summary - Qlaira ● Clinical studies of E 2 V/DNG demonstrate ● Relatively stable oestrogen levels throughout the menstrual cycle ● Effective inhibition of ovulation ● Effective contraception ● Good bleeding profile – shorter, lighter bleeding and fewer bleeding/spotting days compared with monophasic EE/LNG ● An absence of all bleeding or spotting occurred in 15. 4% of cycles ● No discontinuations due to bleeding disorders
Zoely • 24 active pills/ 4 placebo pills – no PFI • 1. 5 mg estradiol (as hemi hydrate) + Nomegestrol acetate 2. 5 mg (NOMAC) • NOMAC has a strong affinity for progesterone receptor, strong antigonadotrophic activity, mild antiandrogenic activity • Shorter/lighter WTB, higher incidence of absent WTB • Acne improvement • Efficacy comparable to COC (Yasmin ethinylestradiol, drospirenone) Faculty of SRH Statement from CEU May 2013
Nuvaring – vaginal ring ● A flexible transparent ring of ethylene vinyl acetate with an outer diameter of 54 mm and cross-sectional diameter of 4 mm ● One size for all! ● Combined hormonal contraceptive vaginal ring containing 2. 7 mg ethinylestradiol and 11. 7 mg etonorgestrel FSRH Guidance 2012 CHC It has the lowest oestrogen content of any combined hormonal contraceptive
Ingredients - Nuvaring ● Each Nuvaring is used for one monthly cycle ● It stay in the vagina for 3 weeks and is then removed for a 1 week ring ● The hormones are absorbed -free interval into the rich supply of blood vessels within the vagina and ● The 7 days without enter the general circulation, Nuvaring allows for a avoiding the first-pass withdrawal bleed metabolism by the liver ● Every 24 hours the device releases: ● 15 mcg EE ● 120 mcg ENG
Nuvaring ● Low dose ● Good cycle control ● No daily pill to remember ● No daily fluctuations in hormone levels ● Easy to use ● No interference with SI ● Useful if GI absorption problems
Evra - contraceptive patch ● ● ● ● Daily dose 20 mcg EE + 150 mcg Norelgestromin (similar to Cilest) Levels sufficient to inhibit ovulation for at least 7 days Contraindications similar to COCs Efficacy similar to triphasic COC (overall PI 1. 24) BUT – 60% more Probable reduced efficacy in women > 90 Kg exposure to BTB more common in 1 st 2 cycles than COC oestrogen Additional contraception advised for women on enzyme inducers Suitable for women with absorption problems, who are forgetful or have difficulty swallowing pills
Checklist for BTB with CHC ● Disease ● Disorders of pregnancy ● Default ● Drugs ● Diarrhoea and vomiting ● Disturbances of absorption ● Diet ● Duration of use ● Dose
CEU 2017 Drug interactions and hormonal contraception ● Additional precautions NO longer required when using nonenzyme inducing antibiotics with CHC ● All women on enzyme inducing drugs should be advised to use methods unaffected by those drugs – Cu-IUD; IUS; Injectables ● CHC not recommended in women on Lamotrigine monotherapy (inc risk of seizures) ● UPA not recommended while using enzyme inducers or within 28 days
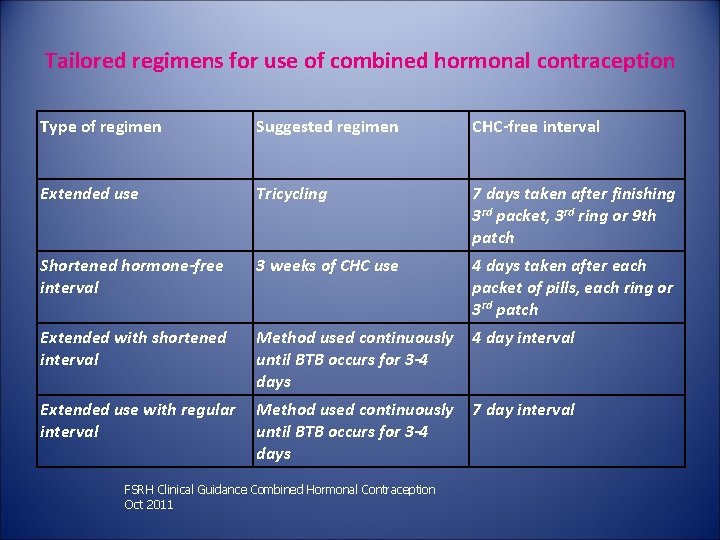
Tailored regimens for use of combined hormonal contraception Type of regimen Suggested regimen CHC-free interval Extended use Tricycling 7 days taken after finishing 3 rd packet, 3 rd ring or 9 th patch Shortened hormone-free interval 3 weeks of CHC use 4 days taken after each packet of pills, each ring or 3 rd patch Extended with shortened interval Method used continuously until BTB occurs for 3 -4 days 4 day interval Extended use with regular interval Method used continuously until BTB occurs for 3 -4 days 7 day interval FSRH Clinical Guidance Combined Hormonal Contraception Oct 2011
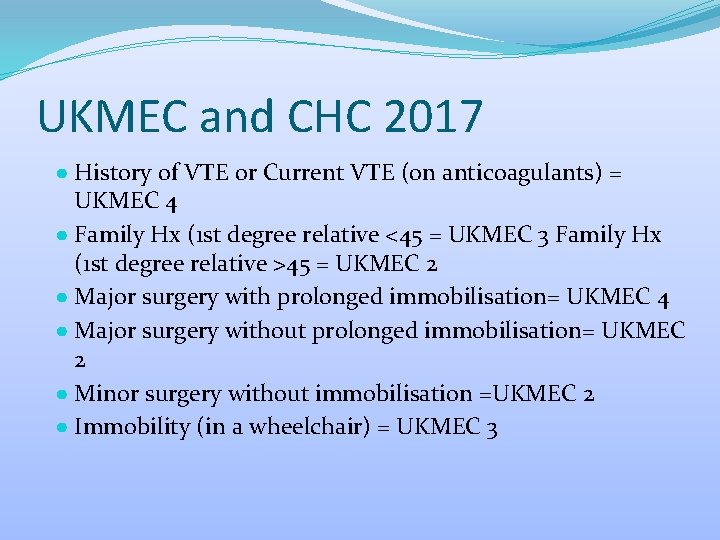
UKMEC and CHC 2017 ● History of VTE or Current VTE (on anticoagulants) = UKMEC 4 ● Family Hx (1 st degree relative <45 = UKMEC 3 Family Hx (1 st degree relative >45 = UKMEC 2 ● Major surgery with prolonged immobilisation= UKMEC 4 ● Major surgery without prolonged immobilisation= UKMEC 2 ● Minor surgery without immobilisation =UKMEC 2 ● Immobility (in a wheelchair) = UKMEC 3
UKMEC and CHC 2017 ● Varicose veins = UKMEC 1 ● Superficial venous thrombosis = UKMEC 2 ● Known thrombotic mutations = UKMEC 4
Breastfeeding and CHC 2017 ● No differentiation between full and partial breastfeeding ● <6 weeks postnatal CHC is still UKMEC 4 ● 6 weeks to 6 months postnatal CHC is UKMEC 2 whether full or partial feeding ● No evidence of effect on breastfeeding Code: UKWHG 07160046 Date of prep: August 2016
Long Acting Reversible Contraception (LARC)
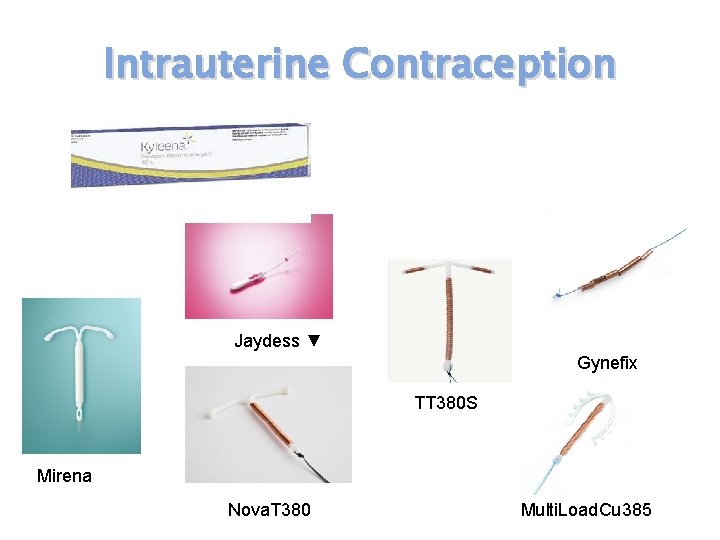
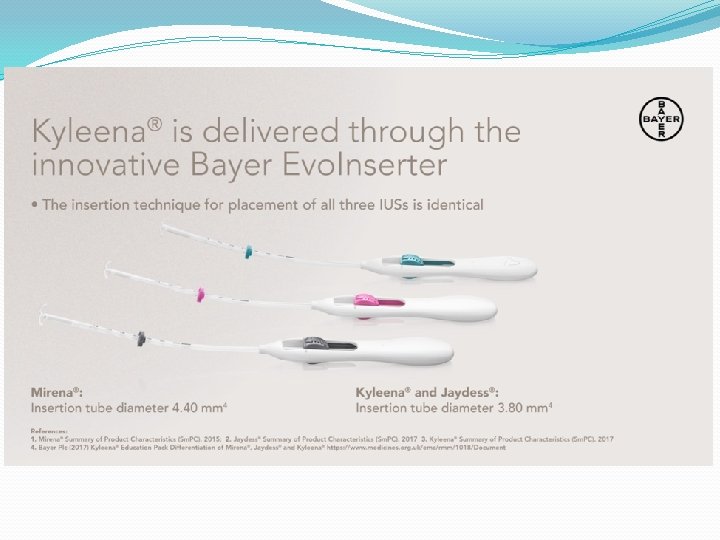
Intrauterine Contraception Jaydess ▼ Gynefix TT 380 S Mirena Nova. T 380 Multi. Load. Cu 385
Copper IUDs ● Use IUDs with >300 sqmm Copper ● Effective: failure rate < 2 in 100 women over 5 years ● Reversible and no effect on future fertility ● No systemic effects ● Reduces risk of ectopic pregnancy ● Can be fitted in nulliparous women (consider local anaesthesia) ● Failure rate < 1% when used for post coital contraception ● TT 380 licensed and effective for 10 years ● Cu IUDs fitted > age 40 may be left until after menopause ● Is least costly LARC method
Nexplanon ● Single rod releasing 30 -40 mcg etonorgestrel per day ● Contains 3% barium sulphate ● >99% inhibition of ovulation ● Most effective LARC method ● Lasts 3 years ( no need to change early if high BMI) ● Not recommended for women on enzyme inducers ● Does not affect bone density ● 20% amenorrhoea (but 47% will get bleeding by 2 years) ● 50% infrequent, frequent or prolonged bleeding ● Not associated with weight change, mood, libido or headaches ● May be associated with acne FSRH Guidance 2014 P-O Iimplants
Management of women taking anticoagulants or anti platelet medications who request IUC or SDI ● Insertion of IUC and SDI in women using Warfarin is unlikely to be associated with a risk of significant bleeding ● From clinical experience, DOAC use with these procedures carries a low bleeding risk FSRH CEU Guidance March 2017
Assessment of women with bleeding risks ● What anticoagulant is she taking and why? ● Is she highly anticoagulated? ● Expected duration of therapy? ● Previous bleeding problems with procedures? (e. g. dental work) ● Other medical conditions or medications that may increase the risk of bleeding further (e. g. dual anti platelet therapy, liver disease) ● Result and date of most recent INR if on Warfarin ● Is she postnatal/breastfeeding? Increased risk of perforation in 1 st 36 weeks postnatal and if breast feeding ● Previous difficult/failed IUC insertions FSRH CEU Guidance March 2017
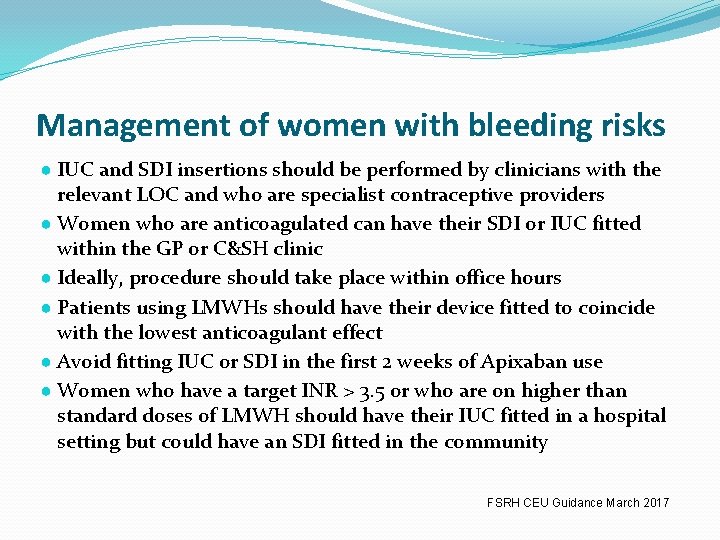
Management of women with bleeding risks ● IUC and SDI insertions should be performed by clinicians with the relevant LOC and who are specialist contraceptive providers ● Women who are anticoagulated can have their SDI or IUC fitted within the GP or C&SH clinic ● Ideally, procedure should take place within office hours ● Patients using LMWHs should have their device fitted to coincide with the lowest anticoagulant effect ● Avoid fitting IUC or SDI in the first 2 weeks of Apixaban use ● Women who have a target INR > 3. 5 or who are on higher than standard doses of LMWH should have their IUC fitted in a hospital setting but could have an SDI fitted in the community FSRH CEU Guidance March 2017
Injectables Depoprovera ● Medroxyprogesterone acetate ● 150 mg/ml every 13 weeks by deep i. m. injection ● If necessary, can be given from 10 weeks ● CEU guidance states it can be given up to 7 days late without need for additional precautions ● Cost: £ 6. 01 ● Annual cost: £ 26. 11 Sayana-Press ● Medroxyprogesterone acetate ● 104 mg in 0. 65 ml suspension every 13 weeks s. c. into upper thigh or lower abdomen ● Can be given up to 7 days early or late without need for additional precautions ● Cost: £ 6. 90 ● Annual cost: £ 27. 68 FSRH CEU New Product Review 2013 FSRH Clinical Guidance Progestogen-only Injectables March 2015
UKMEC Injectables • • • History of VTE = UKMEC 2 Current VTE (on anticoagulants) = UKMEC 2 Family Hx of VTE (any age) = UKMEC 1 Major surgery with prolonged immobilisation = UKMEC 2 Major surgery without prolonged immobilisation or immobility = UKMEC 1 • Known thrombotic mutations = UKMEC 2
4 unique aspects! ● Cannot be speedily reversed ● Can cause delayed return of (but no loss of) fertility ● Can truly cause weight gain (mean of 3 kg in 2 years) ● Excellent choice for women on EIDs so no change in usual injection frequency during EID use FSRH CEU Guidance Progestogenonly Injectables Nov 2008
MHRA Guidance 2004 ● Women < 18 yrs – DMPA may be used as 1 st line contraception after all options have been discussed and are considered unsuitable or unacceptable ● A re-evaluation of the risks and benefits of treatment should be carried out every 2 years in those who wish to continue use ● Women with considerable life style and/or medical risk factors for osteoporosis should consider other methods of contraception
Quick starting contraception!!! Criteria for excluding pregnancy: ● No SI since last menses ● Is correctly and consistently using a reliable method ● Is within 7 days of onset of menses ● Is within 4 weeks postpartum and not breast feeding ● Is fully or nearly fully breast feeding, amenorrhoeic and < 6 months postpartum
What drug interactions are relevant to e. c. use? ● Women using EIDs should be advised that the efficacy of UPA-ec and LNG-ec could be reduced ● Women using EIDs should be offered a Cu-IUD ● Women using EIDs can be offered 3 mg LNG-ec but the efficacy is not known. A double dose of UPA-ec is not recommended ● The efficacy of UPA-ec could be reduced if progestogens are taken in 5 days after UPA-ec ● The efficacy of UPA-ec could be reduced if progestogens in 7 days prior to UPA-ec
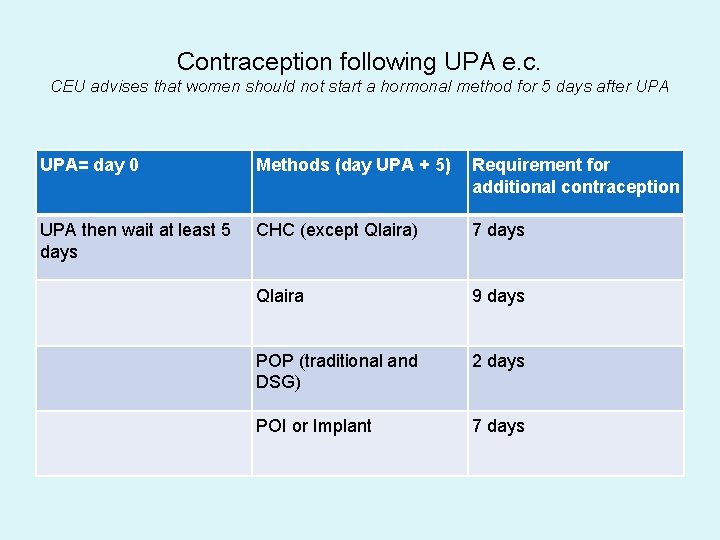
Contraception following UPA e. c. CEU advises that women should not start a hormonal method for 5 days after UPA= day 0 Methods (day UPA + 5) Requirement for additional contraception UPA then wait at least 5 days CHC (except Qlaira) 7 days Qlaira 9 days POP (traditional and DSG) 2 days POI or Implant 7 days
Intrauterine methods pills injectables implants 2018 different routes, new hormones, more choice Vaginal rings patches Surgical methods Natural methods barriers