HIV Update Ardis Moe M D amoemednet ucla
































- Slides: 48
HIV Update Ardis Moe, M. D. amoe@mednet. ucla. edu UCLA CARE clinic/NEVHC Van Nuys 21 June 2014
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com § I do not have any financial arrangements or affiliations with commercial sponsors which have direct interest in the subject matter
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Goals: § Discuss PREP and PEP options § DHHS treatment options § New HIV meds
PREP and PEP update
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Audience Response Questions § 1)I have prescribed PREP for at least one patient § 2)I have never prescribed PREP
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com PREP § Truvada (tenofovir/emtricitabine) 1 pill a day § FDA approved to prevent HIV infections in MSM/transgender women § Needs baseline HIV, hep B testing and testing every 3 months while on truvada § $8 a pill. Risk of kidney, bone damage.
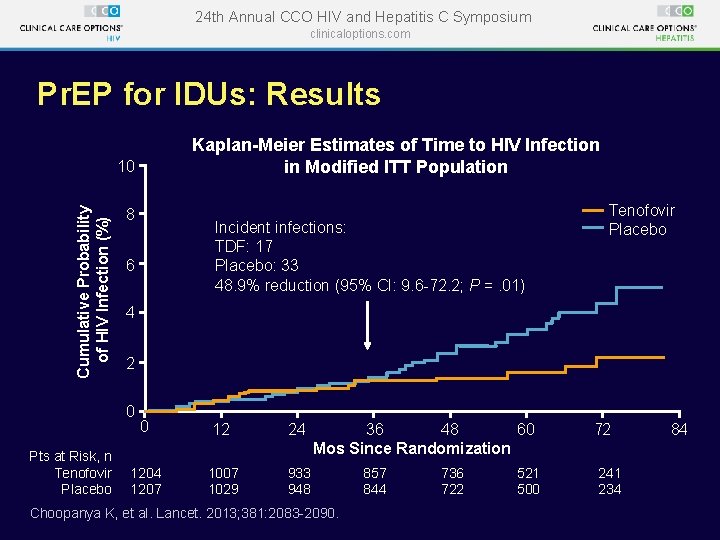
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com ART Prophylaxis for HIV Infection in Injection Drug Users in Bangkok, Thailand § Randomized, double-blind, placebo-controlled, phase 3 clinical trial of tenofovir vs placebo to prevent HIV § DOT option based on investigator discretion § N = 2413 – Median age, 31 yrs – 80% men – < 10% injected daily; 18% shared needles Choopanya K, et al. 2013; 381: 2083 -2090.
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Pr. EP for IDUs: Results Kaplan-Meier Estimates of Time to HIV Infection in Modified ITT Population Cumulative Probability of HIV Infection (%) 10 8 6 4 2 0 Pts at Risk, n Tenofovir Placebo Incident infections: TDF: 17 Placebo: 33 48. 9% reduction (95% CI: 9. 6 -72. 2; P =. 01) Tenofovir Placebo 0 12 24 1207 1007 1029 933 948 48 36 60 Mos Since Randomization Choopanya K, et al. Lancet. 2013; 381: 2083 -2090. 857 844 736 722 521 500 72 241 234 84
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Update to Interim Guidance for Pr. EP for Prevention of HIV Infection: Pr. EP for IDUs § Recommendations – Consider for those at “very high risk”: – Sharing of equipment – Injecting daily – Using cocaine or crystal meth – Critical to exclude HIV first – Use TDF/FTC (truvada --not tenofovir) MMWR. 2013; 62: 463 -465.
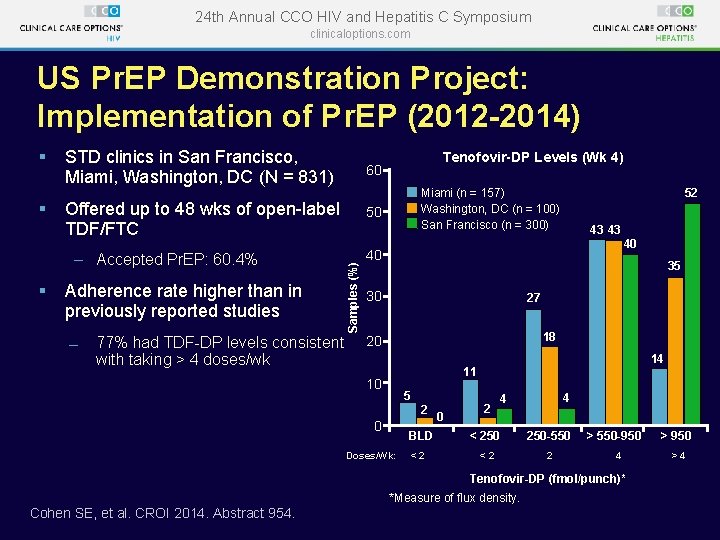
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com US Pr. EP Demonstration Project: Implementation of Pr. EP (2012 -2014) § STD clinics in San Francisco, Miami, Washington, DC (N = 831) 60 Offered up to 48 wks of open-label TDF/FTC 50 – Accepted Pr. EP: 60. 4% § Adherence rate higher than in previously reported studies 77% had TDF-DP levels consistent with taking > 4 doses/wk Samples (%) § Tenofovir-DP Levels (Wk 4) Miami (n = 157) Washington, DC (n = 100) San Francisco (n = 300) 52 43 43 40 40 35 30 27 18 20 14 11 10 5 2 0 BLD Doses/Wk: <2 0 2 4 4 < 250 -550 <2 2 > 550 -950 4 Tenofovir-DP (fmol/punch)* *Measure of flux density. Cohen SE, et al. CROI 2014. Abstract 954. > 950 >4
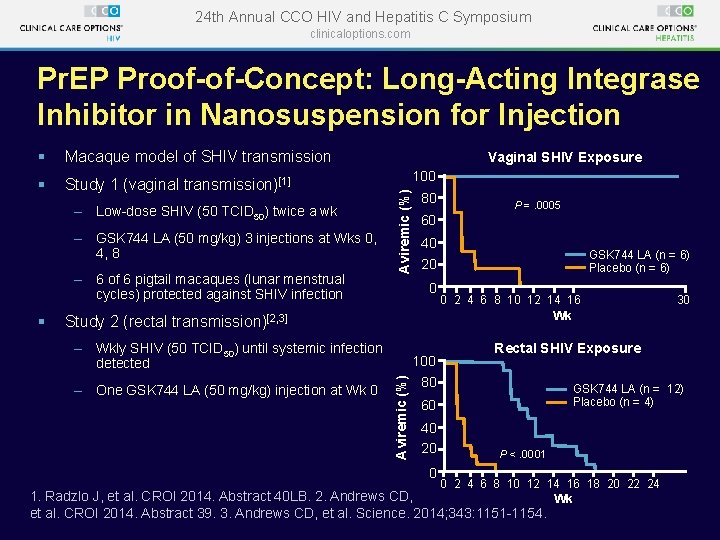
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com § PREP. § Any alternatives to taking pills?
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Pr. EP Proof-of-Concept: Long-Acting Integrase Inhibitor in Nanosuspension for Injection Macaque model of SHIV transmission § Study 1 (vaginal transmission)[1] – Low-dose SHIV (50 TCID 50) twice a wk – GSK 744 LA (50 mg/kg) 3 injections at Wks 0, 4, 8 – 6 of 6 pigtail macaques (lunar menstrual cycles) protected against SHIV infection § Vaginal SHIV Exposure 100 Aviremic (%) § 80 60 40 20 0 Study 2 (rectal transmission)[2, 3] – Wkly SHIV (50 TCID 50) until systemic infection detected 100 Aviremic (%) – One GSK 744 LA (50 mg/kg) injection at Wk 0 P =. 0005 GSK 744 LA (n = 6) Placebo (n = 6) 0 2 4 6 8 10 12 14 16 Wk Rectal SHIV Exposure 80 GSK 744 LA (n = 12) Placebo (n = 4) 60 40 20 0 30 P <. 0001 0 2 4 6 8 10 12 14 16 18 20 22 24 1. Radzlo J, et al. CROI 2014. Abstract 40 LB. 2. Andrews CD, Wk et al. CROI 2014. Abstract 39. 3. Andrews CD, et al. Science. 2014; 343: 1151 -1154.
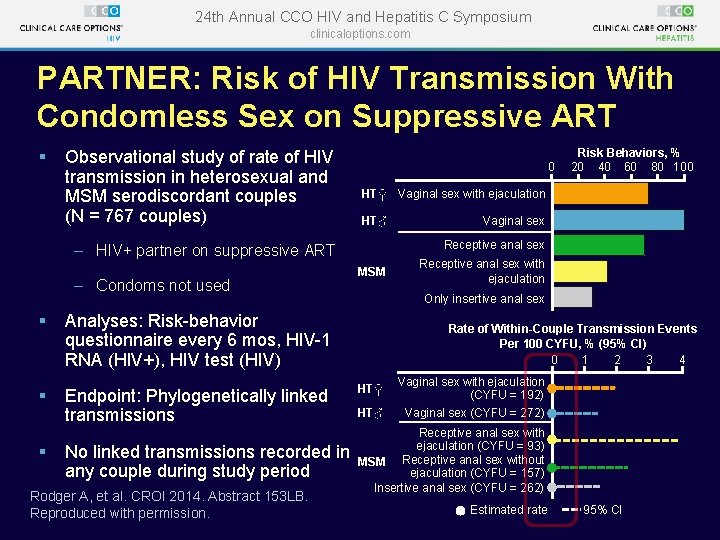
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Treatment as Prevention § PARTNER study § 1 st study to show that treatment of MSM also prevents transmission to HIV neg partner § 40% MSM couples in this study § Average 2 years of observation
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com PARTNER: Risk of HIV Transmission With Condomless Sex on Suppressive ART § Observational study of rate of HIV transmission in heterosexual and MSM serodiscordant couples (N = 767 couples) 0 HT♀ Vaginal sex with ejaculation HT♂ § § § MSM No linked transmissions recorded in any couple during study period Rodger A, et al. CROI 2014. Abstract 153 LB. Reproduced with permission. Receptive anal sex with ejaculation Only insertive anal sex Analyses: Risk-behavior questionnaire every 6 mos, HIV-1 RNA (HIV+), HIV test (HIV) Endpoint: Phylogenetically linked transmissions Vaginal sex Receptive anal sex – HIV+ partner on suppressive ART – Condoms not used Risk Behaviors, % 20 40 60 80 100 Rate of Within-Couple Transmission Events Per 100 CYFU, % (95% CI) 4 0 1 2 3 HT♀ HT♂ Vaginal sex with ejaculation (CYFU = 192) Vaginal sex (CYFU = 272) Receptive anal sex with ejaculation (CYFU = 93) MSM Receptive anal sex without ejaculation (CYFU = 157) Insertive anal sex (CYFU = 262) Estimated rate 95% CI
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Study will continue for 3 more years
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Management of Occupational Exposure to HIV and Recommendations for PEP § First choice: TDF/FTC + raltegravir (isentress and truvada)x 28 days[1] § ID consult recommended for complex cases (eg, source patient on isentress and truvada) § Follow-up shortened to 4 mos if 4 th-generation Ag/Ab combination test used § Baseline HIV testing, 6 weeks, 3 months, 6 months. 1. Kuhar DT, et al. Inf Cont Hosp Epi. 2013. 2. NYS Dept Health. HIV prophylaxis following occupational exposure. October 2012.
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com § For pregnant HCW: Lopinavir/ritonavir + zidovudine/lamivudine (Kaletra+Combivir) still first choice for PEP
Initial Therapy – Established Drugs
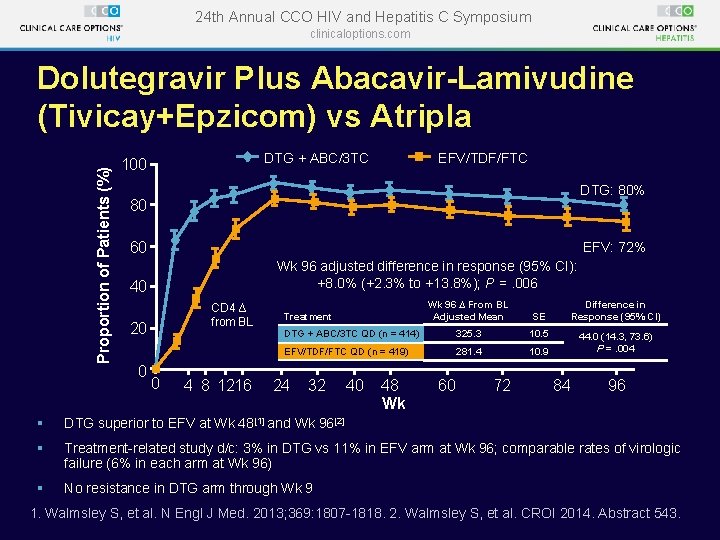
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Proportion of Patients (%) Dolutegravir Plus Abacavir-Lamivudine (Tivicay+Epzicom) vs Atripla DTG + ABC/3 TC 100 EFV/TDF/FTC DTG: 80% 80 60 EFV: 72% Wk 96 adjusted difference in response (95% CI): +8. 0% (+2. 3% to +13. 8%); P =. 006 40 CD 4 ∆ from BL 20 0 0 4 8 1216 Wk 96 ∆ From BL Adjusted Mean SE DTG + ABC/3 TC QD (n = 414) 325. 3 10. 5 EFV/TDF/FTC QD (n = 419) 281. 4 10. 9 Treatment 24 32 40 48 Wk 60 72 Difference in Response (95% CI) 44. 0 (14. 3, 73. 6) P =. 004 84 96 § DTG superior to EFV at Wk 48[1] and Wk 96[2] § Treatment-related study d/c: 3% in DTG vs 11% in EFV arm at Wk 96; comparable rates of virologic failure (6% in each arm at Wk 96) § No resistance in DTG arm through Wk 9 1. Walmsley S, et al. N Engl J Med. 2013; 369: 1807 -1818. 2. Walmsley S, et al. CROI 2014. Abstract 543.
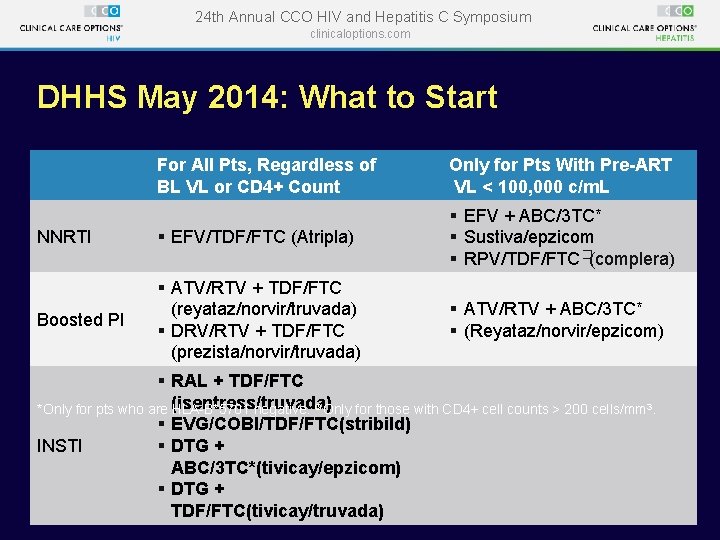
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com DHHS May 2014: What to Start For All Pts, Regardless of BL VL or CD 4+ Count Only for Pts With Pre-ART VL < 100, 000 c/m. L NNRTI § EFV/TDF/FTC (Atripla) § EFV + ABC/3 TC* § Sustiva/epzicom § RPV/TDF/FTC�(complera) Boosted PI § ATV/RTV + TDF/FTC (reyataz/norvir/truvada) § DRV/RTV + TDF/FTC (prezista/norvir/truvada) § ATV/RTV + ABC/3 TC* § (Reyataz/norvir/epzicom) § RAL + TDF/FTC *Only for pts who are (isentress/truvada) HLA-B*5701 negative. Only for those with CD 4+ cell counts > 200 cells/mm 3. § EVG/COBI/TDF/FTC(stribild) INSTI § DTG + ABC/3 TC*(tivicay/epzicom) § DTG + DHHS guidelines. May TDF/FTC(tivicay/truvada) 2014.
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com § Ok, so what cocktail works best for what sort of patient? § Plan A, B, C, D system—Dr. Moe’s quick and dirty plan of action
Plan A: A pill a day for Type A Personalities
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Plan A drugs § Complera (only for those with <100, 000 viral load and no GERD) § Atripla (risk of depression, vivid dreams, panic attacks) § Stribild (risk of diarrhea) § Tivcay/epzicom (risk of diarrhea; needs HLAB 5701 blood test to be negative before starting) § All with low barriers to resistance; need for near perfect adherence
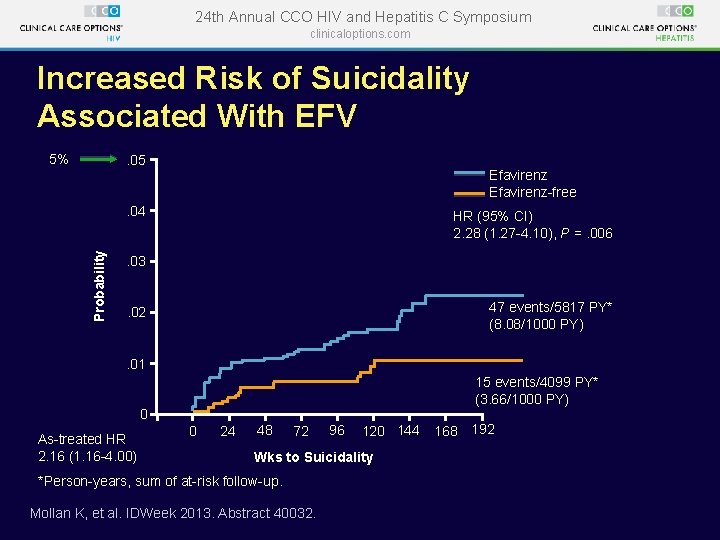
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Increased Risk of Suicidality Associated With EFV 5% . 05 Efavirenz-free Probability . 04 HR (95% CI) 2. 28 (1. 27 -4. 10), P =. 006 . 03 47 events/5817 PY* (8. 08/1000 PY) . 02 . 01 15 events/4099 PY* (3. 66/1000 PY) 0 As-treated HR 2. 16 (1. 16 -4. 00) 0 24 48 72 96 120 144 Wks to Suicidality *Person-years, sum of at-risk follow-up. Mollan K, et al. IDWeek 2013. Abstract 40032. 168 192
Plan B: Boosted protease inhibitors for batty buddies on the brink:
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Plan B: poor adherence risk factors § Mentally ill § Meth/cocaine/alcoholic § In and out of jail § Homeless § Chaotic home life § Or: on the brink: CD 4 count <200, AIDS OI or cancer
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Plan B drugs § Reytataz/norvir/truvada § Prezista/norvir/truvada
Plan C: Curses I forgot the contraception
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Plan C § Combivir and Kaletra § Still has the most extensive and best data on safety in pregnancy. – Reyataz, norvir, truvada – Complera – Truvada and isentress are also options – AVOID Sustiva (efavirenz, atripla) : neural tube defects on one study in France
Plan D: Darn I stuck myself or Drug-Drug interactions
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Plan D § Isentress and truvada – Fewest drug interactions (warfarin, dilantin) – Need to double dose of isentress when taken with rifampin – Preferred PEP med for needlestick injuries
Novel Strategies for Treatment
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com HIV Cure: The Score So Far § Still without HIV relapse – 1 patient (“Berlin”) post–stem cell transplant from CCR 5 delta 32 negative donor – 1 baby (“Mississippi”) treated at birth[1] § No consistently detectable virus in reservoir (important: still on ART) – Another baby treated at birth (“Long Beach”)[1] 1. Persaud D, et al. CROI 2014. Abstract 75 LB. 2. Hatano H, et al. CROI 2014. Abstract 397 LB. 3. Heinrich TH, et al. CROI 2014. Abstract 144 LB.
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com § What if my Plan B patient (or patient on Atripla) wants to switch to Stribild?
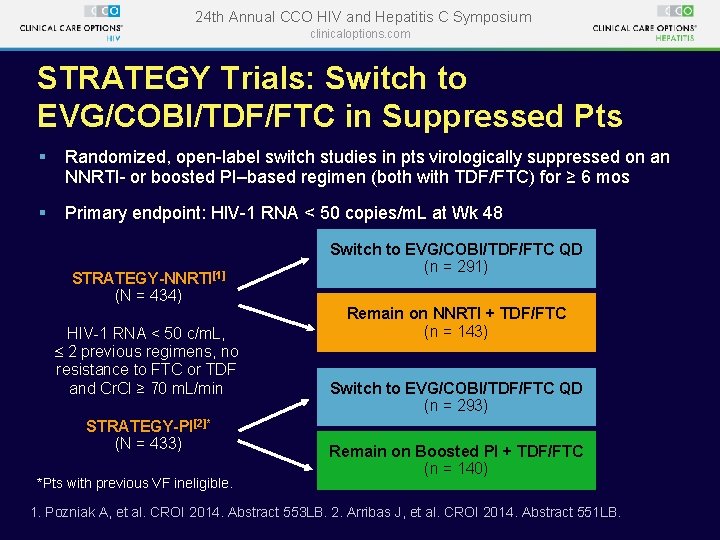
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com STRATEGY Trials: Switch to EVG/COBI/TDF/FTC in Suppressed Pts § Randomized, open-label switch studies in pts virologically suppressed on an NNRTI- or boosted PI–based regimen (both with TDF/FTC) for ≥ 6 mos § Primary endpoint: HIV-1 RNA < 50 copies/m. L at Wk 48 STRATEGY-NNRTI[1] (N = 434) HIV-1 RNA < 50 c/m. L, 2 previous regimens, no resistance to FTC or TDF and Cr. Cl ≥ 70 m. L/min STRATEGY-PI[2]* (N = 433) *Pts with previous VF ineligible. Switch to EVG/COBI/TDF/FTC QD (n = 291) Remain on NNRTI + TDF/FTC (n = 143) Switch to EVG/COBI/TDF/FTC QD (n = 293) Remain on Boosted PI + TDF/FTC (n = 140) 1. Pozniak A, et al. CROI 2014. Abstract 553 LB. 2. Arribas J, et al. CROI 2014. Abstract 551 LB.
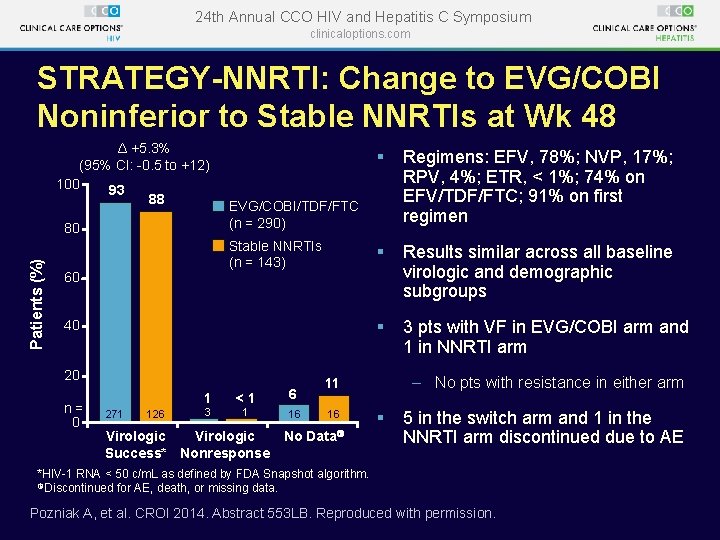
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com STRATEGY-NNRTI: Change to EVG/COBI Noninferior to Stable NNRTIs at Wk 48 Δ +5. 3% (95% CI: -0. 5 to +12) 100 93 88 Patients (%) 80 40 20 n= 0 271 126 Regimens: EFV, 78%; NVP, 17%; RPV, 4%; ETR, < 1%; 74% on EFV/TDF/FTC; 91% on first regimen § Results similar across all baseline virologic and demographic subgroups § 3 pts with VF in EVG/COBI arm and 1 in NNRTI arm EVG/COBI/TDF/FTC (n = 290) Stable NNRTIs (n = 143) 60 § 1 <1 6 3 1 16 Virologic Success* Nonresponse – No pts with resistance in either arm 11 16 No Data § 5 in the switch arm and 1 in the NNRTI arm discontinued due to AE *HIV-1 RNA < 50 c/m. L as defined by FDA Snapshot algorithm. Discontinued for AE, death, or missing data. Pozniak A, et al. CROI 2014. Abstract 553 LB. Reproduced with permission.
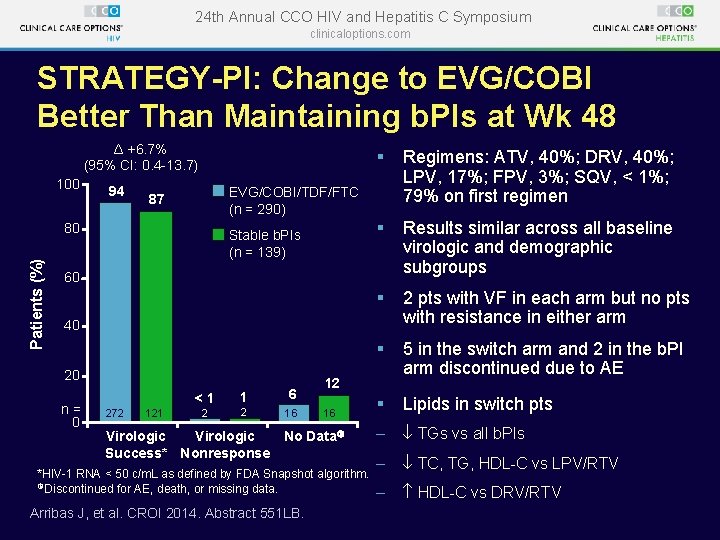
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com STRATEGY-PI: Change to EVG/COBI Better Than Maintaining b. PIs at Wk 48 Δ +6. 7% (95% CI: 0. 4 -13. 7) 100 94 Regimens: ATV, 40%; DRV, 40%; LPV, 17%; FPV, 3%; SQV, < 1%; 79% on first regimen § Results similar across all baseline virologic and demographic subgroups § 2 pts with VF in each arm but no pts with resistance in either arm § 5 in the switch arm and 2 in the b. PI arm discontinued due to AE § Lipids in switch pts – TGs vs all b. PIs – TC, TG, HDL-C vs LPV/RTV – HDL-C vs DRV/RTV EVG/COBI/TDF/FTC (n = 290) 87 80 Patients (%) § Stable b. PIs (n = 139) 60 40 20 n= 0 <1 272 121 2 1 6 2 16 12 16 Virologic No Data Success* Nonresponse *HIV-1 RNA < 50 c/m. L as defined by FDA Snapshot algorithm. Discontinued for AE, death, or missing data. Arribas J, et al. CROI 2014. Abstract 551 LB.
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Audience Response: Which is TRUE § 1)there have been 10 cases of cure of HI so far § 2)the best drug cocktail for pregnant women is atripla § 3)the best drug cocktail for a homeless, mentally ill man is atripla § 4)if my patient has an undetectable viral load and is on reyataz/norvir/truvada and wants to switch to stribild, this is safe to d
Investigational Drugs
TAF: Son of viread
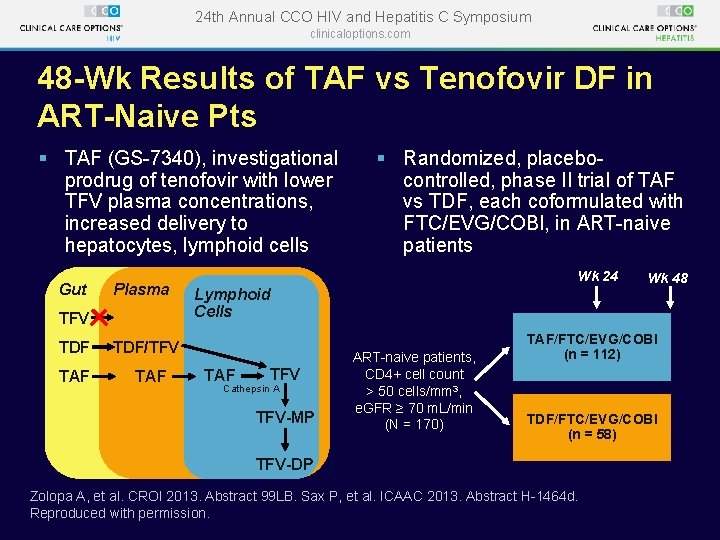
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com 48 -Wk Results of TAF vs Tenofovir DF in ART-Naive Pts § TAF (GS-7340), investigational prodrug of tenofovir with lower TFV plasma concentrations, increased delivery to hepatocytes, lymphoid cells Gut Plasma TFV TDF TAF Wk 24 Lymphoid Cells TDF/TFV TAF § Randomized, placebocontrolled, phase II trial of TAF vs TDF, each coformulated with FTC/EVG/COBI, in ART-naive patients TAF TFV Cathepsin A TFV-MP ART-naive patients, CD 4+ cell count > 50 cells/mm 3, e. GFR ≥ 70 m. L/min (N = 170) Wk 48 TAF/FTC/EVG/COBI (n = 112) TDF/FTC/EVG/COBI (n = 58) TFV-DP Zolopa A, et al. CROI 2013. Abstract 99 LB. Sax P, et al. ICAAC 2013. Abstract H-1464 d. Reproduced with permission.
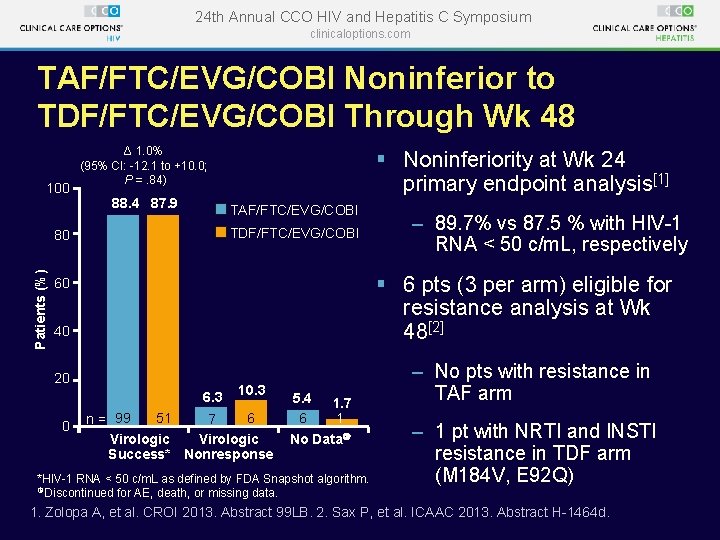
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com TAF/FTC/EVG/COBI Noninferior to TDF/FTC/EVG/COBI Through Wk 48 100 Δ 1. 0% (95% CI: -12. 1 to +10. 0; P =. 84) 88. 4 87. 9 TAF/FTC/EVG/COBI TDF/FTC/EVG/COBI 80 Patients (%) § Noninferiority at Wk 24 primary endpoint analysis[1] § 6 pts (3 per arm) eligible for resistance analysis at Wk 48[2] 60 40 20 6. 3 0 – 89. 7% vs 87. 5 % with HIV-1 RNA < 50 c/m. L, respectively 10. 3 51 6 7 n = 99 Virologic Success* Nonresponse 5. 4 1. 7 6 1 No Data *HIV-1 RNA < 50 c/m. L as defined by FDA Snapshot algorithm. Discontinued for AE, death, or missing data. – No pts with resistance in TAF arm – 1 pt with NRTI and INSTI resistance in TDF arm (M 184 V, E 92 Q) 1. Zolopa A, et al. CROI 2013. Abstract 99 LB. 2. Sax P, et al. ICAAC 2013. Abstract H-1464 d.
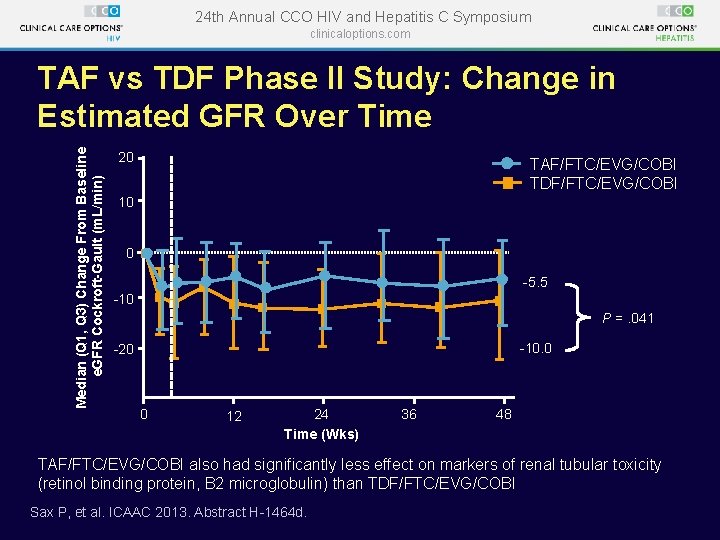
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Median (Q 1, Q 3) Change From Baseline e. GFR Cockroft-Gault (m. L/min) TAF vs TDF Phase II Study: Change in Estimated GFR Over Time 20 TAF/FTC/EVG/COBI TDF/FTC/EVG/COBI 10 0 -5. 5 -10 P =. 041 -10. 0 -20 0 12 24 Time (Wks) 36 48 TAF/FTC/EVG/COBI also had significantly less effect on markers of renal tubular toxicity (retinol binding protein, B 2 microglobulin) than TDF/FTC/EVG/COBI Sax P, et al. ICAAC 2013. Abstract H-1464 d.
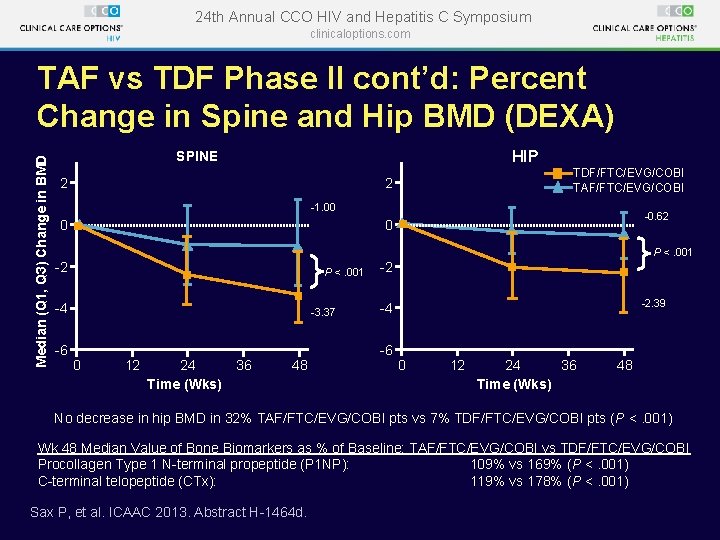
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Median (Q 1, Q 3) Change in BMD TAF vs TDF Phase II cont’d: Percent Change in Spine and Hip BMD (DEXA) HIP SPINE TDF/FTC/EVG/COBI TAF/FTC/EVG/COBI 2 2 -1. 00 0 0 -2 -2 -0. 62 P <. 001 -4 -6 -3. 37 0 12 24 Time (Wks) 36 48 -2. 39 -4 -6 0 12 24 36 Time (Wks) 48 No decrease in hip BMD in 32% TAF/FTC/EVG/COBI pts vs 7% TDF/FTC/EVG/COBI pts (P <. 001) Wk 48 Median Value of Bone Biomarkers as % of Baseline: TAF/FTC/EVG/COBI vs TDF/FTC/EVG/COBI Procollagen Type 1 N-terminal propeptide (P 1 NP): 109% vs 169% (P <. 001) C-terminal telopeptide (CTx): 119% vs 178% (P <. 001) Sax P, et al. ICAAC 2013. Abstract H-1464 d.
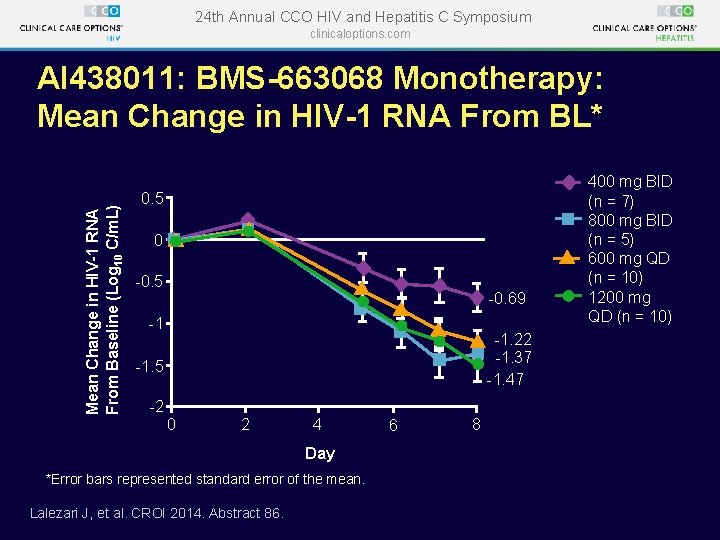
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Drugs With Novel Mechanisms for Pan-Resistant HIV in Phase II or Later § BMS-663068 (attachment inhibitor) § … that’s it! It is therefore critical that patients with highly resistant virus preserve virologic suppression through excellent adherence! Lalezari J, et al. CROI 2014. Abstract 86. Discontinuation notice for virco. TYPE, November 2013
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Mean Change in HIV-1 RNA From Baseline (Log 10 C/m. L) AI 438011: BMS-663068 Monotherapy: Mean Change in HIV-1 RNA From BL* 0. 5 0 -0. 5 -0. 69 -1 -1. 22 -1. 37 -1. 47 -1. 5 -2 0 2 4 Day *Error bars represented standard error of the mean. Lalezari J, et al. CROI 2014. Abstract 86. 6 8 400 mg BID (n = 7) 800 mg BID (n = 5) 600 mg QD (n = 10) 1200 mg QD (n = 10)
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com In next few months expect… § Coformulated cobisistat with prezista, reyataz. § New one pill regimen: tivicay/epzicom § Son of viread: TAF
24 th Annual CCO HIV and Hepatitis C Symposium clinicaloptions. com Summary § Truvada works for IDU as well as MSM and transgender women. § Injectable once monthly PREP meds in future § Ok to switch to stribild if HIV viral load undetectable on boosted PI or atripla § Plan A, B, C, D cocktails § Truvada and isentress first choice for PEP § Son of viread coming