
Department of Genitourinary Medicine Burden of problem Challenges

* Department of Genitourinary Medicine

*Burden of problem *Challenges *Risk assessment *HIV testing in primary care *Indicator conditions *HIV treatment and prognosis *HIV prevention *Future direction *
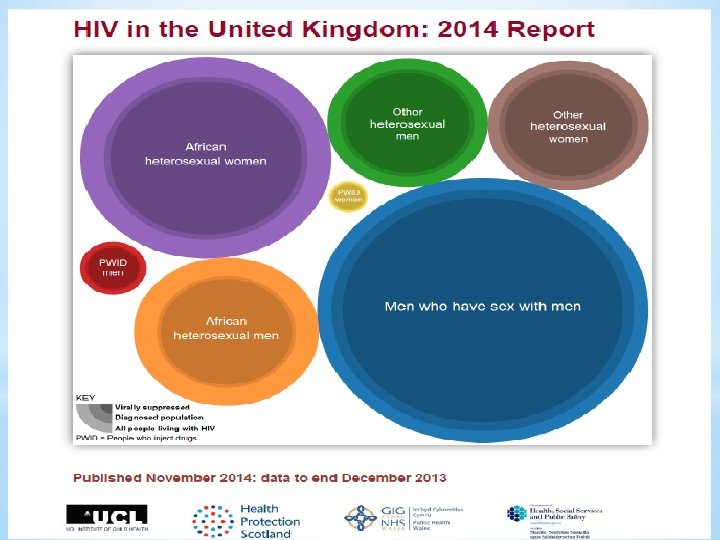

*~ 200 registered patients *Boston, Lincoln, Grantham, Skegness *male>female *Mostly UK (NB Boston) *Many undisclosed MSM *Women diagnosed late *Most on antiretroviral therapy *Most good adherence *

*Undiagnosed (≈ 17% in UK - 2014) *Late diagnosis (≈ 55% among heterosexuals in UK – 2014) *Stepping up treatment * HIV care continuum target – ‘ 90 -90 -90’ in 2020 (UNAIDS) *HIV prevention *HIV stigma reduction *

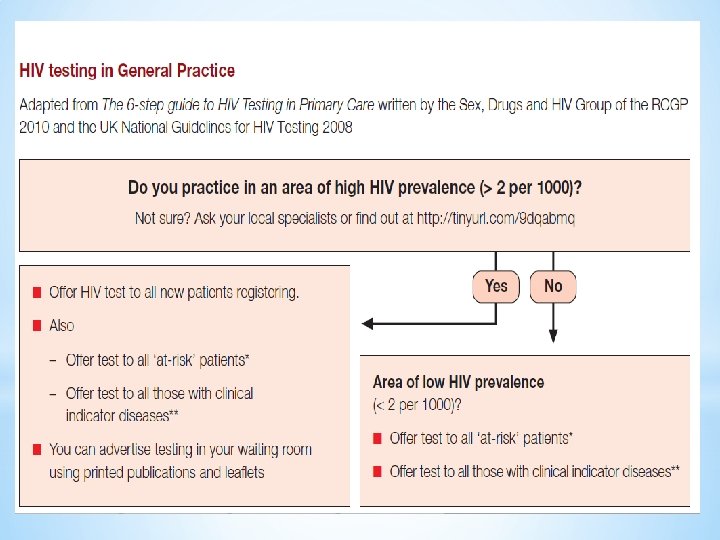
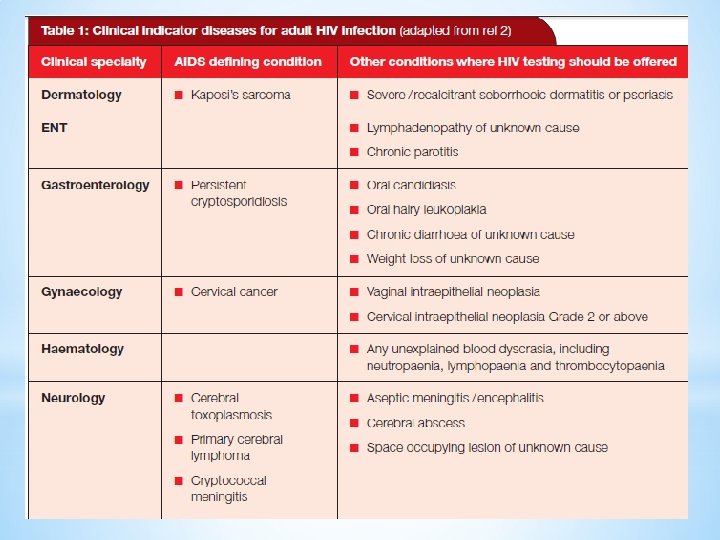
* HIV TESTING

�The benefits of early diagnosis of HIV are well recognized – not offering HIV testing represents a missed opportunity Earlier treatment Earlier institution of preventative measures Improved QOL Cost-effectiveness and economical gain in the longer term ▪ Reduced AIDS and non-AIDS morbidities and mortalities ▪ Reduced HIV transmission ▪ Public health benefits *Why HIV testing?
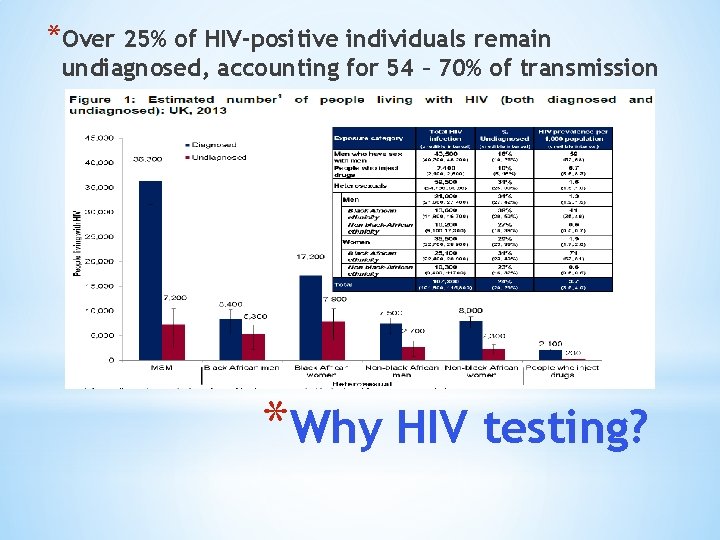
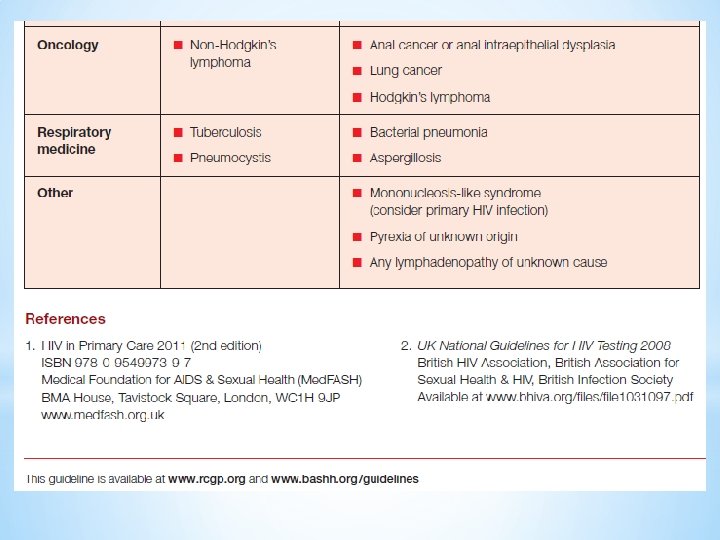
*Over 25% of HIV-positive individuals remain undiagnosed, accounting for 54 – 70% of transmission *Why HIV testing?
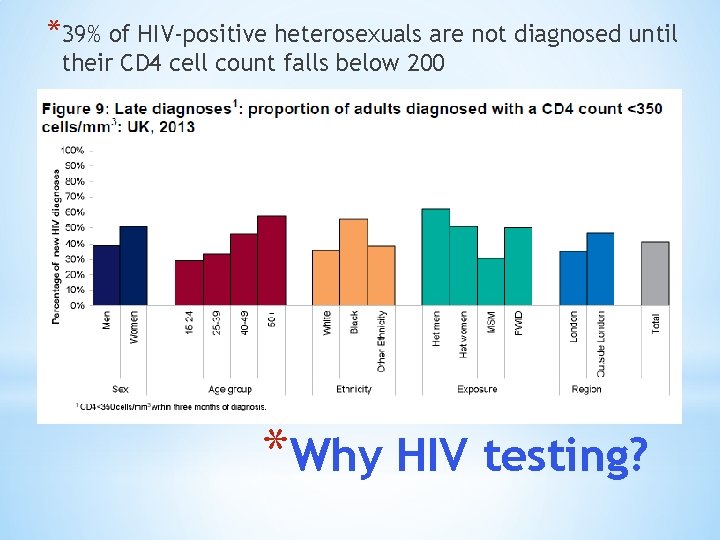
*39% of HIV-positive heterosexuals are not diagnosed until their CD 4 cell count falls below 200 *Why HIV testing?

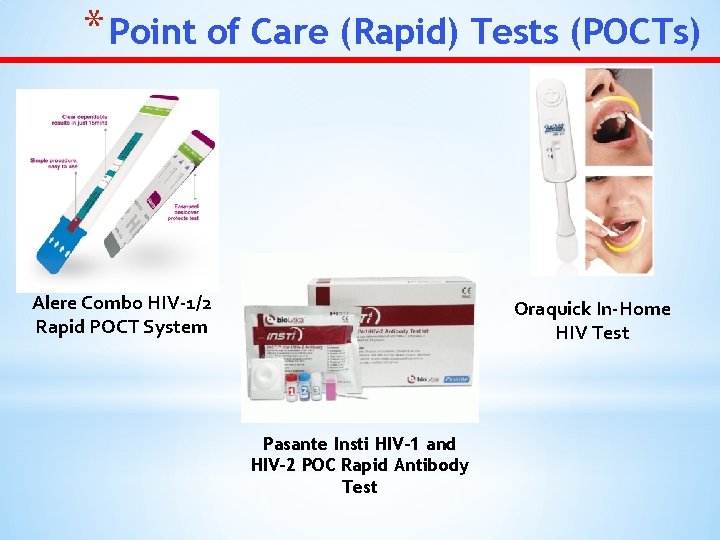
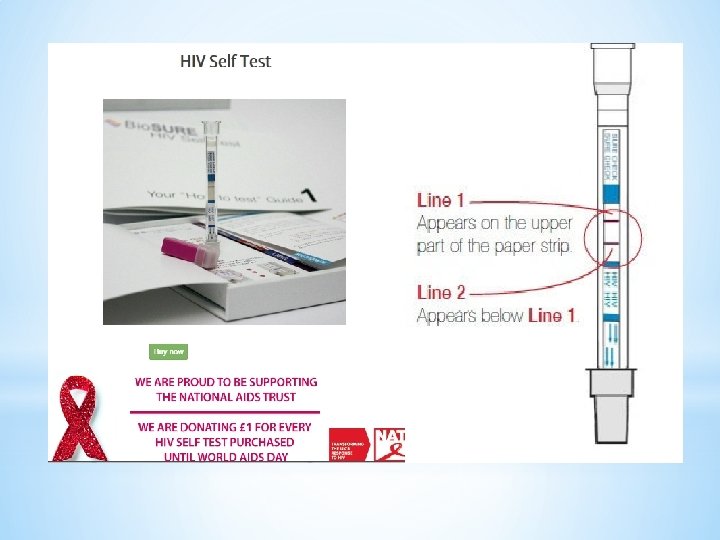
* Point of Care (Rapid) Tests (POCTs) Alere Combo HIV-1/2 Rapid POCT System Oraquick In-Home HIV Test Pasante Insti HIV-1 and HIV-2 POC Rapid Antibody Test




*Antiretroviral therapy (ART) has transformed treatment of HIV infection Atripla Stribild Eviplera Triumeq *Why HIV testing?
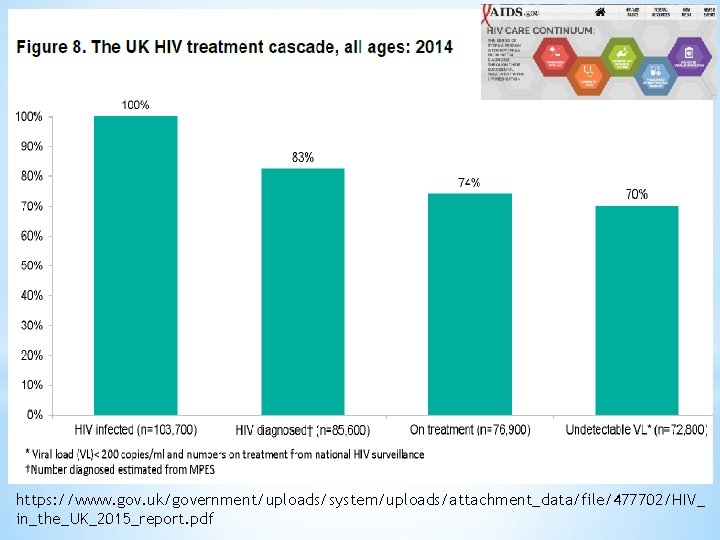
https: //www. gov. uk/government/uploads/system/uploads/attachment_data/file/477702/HIV_ in_the_UK_2015_report. pdf
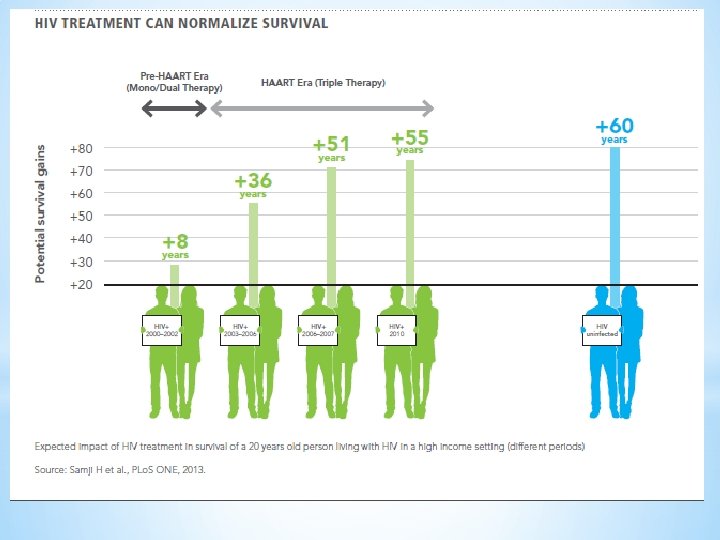

* The clinical goal * Extend life expectancy and QOL in HIV-positive individuals * The virological goal * Reduce HIV viral load to the lowest level possible for as long as possible to prevent disease progression, as well as limiting resistance to ARV drugs * The immunological goal * Restore and preserve immunological function, by maintaining CD 4 cell counts and resisting infection by opportunistic pathogens * The epidemiological goal * To reduce transmission of HIV to others *Goal of anti-retroviral therapy
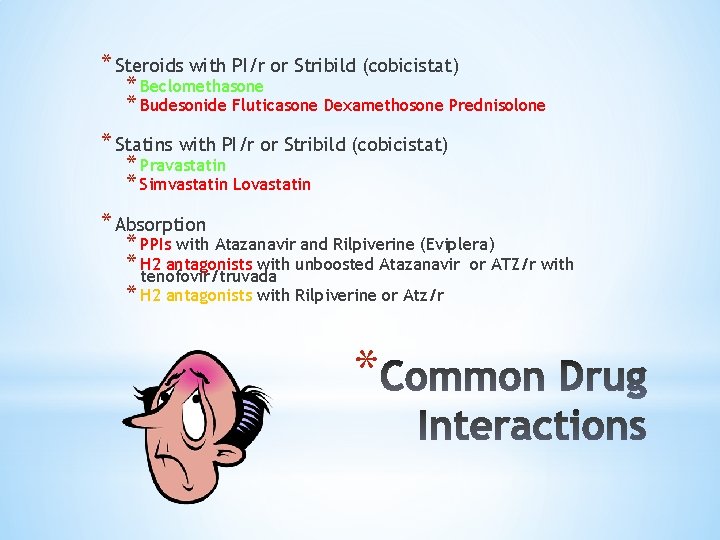
* Steroids with PI/r or Stribild (cobicistat) * Beclomethasone * Budesonide Fluticasone Dexamethosone Prednisolone * Statins with PI/r or Stribild (cobicistat) * Pravastatin * Simvastatin Lovastatin * Absorption * PPIs with Atazanavir and Rilpiverine (Eviplera) * H 2 antagonists with unboosted Atazanavir or ATZ/r with tenofovir/truvada * H 2 antagonists with Rilpiverine or Atz/r *
● ● Antidepressants – Citalopram, Fluoxetine levels increased with ritonavir – Quetiapine Olanzapine PI/r Contraception – ● Methadone – ● COCP POP Implant levels are decreased with HAART Methadone reduction in levels so dose increase Anticoagulation/blood thinning – Warfarin levels may be affected by HAART therefore monitor – Clopidogrel reduces effect with PI/r *

*If in doubt * www. hiv-druginteractions. org * University of Liverpool *Or contact sexual health services for advice
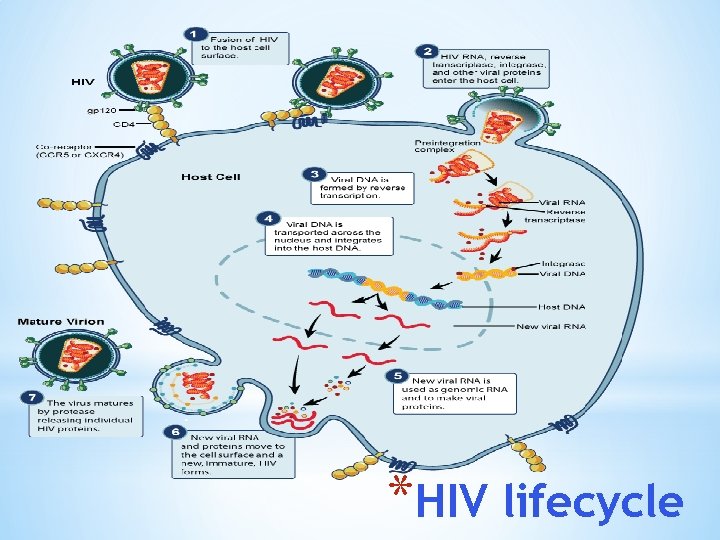
*HIV lifecycle

* Nucleoside Reverse Transcriptase Inhibitors (NRTI) * Tenofovir, Abacavir, Zidovudine, Lamivudine, Emtricitabine * Non-nucleoside Reverse Transcriptase Inhibitors (NNRTI) * Efavirenz, Nevirapine, Etravirine * Protease Inhibitors (PI) * Darunavir, Atazanavir, Lopinavir, Ritonavir * Integrase Inhibitors (INSTI) * Raltegravir, Elvitegravir, Dolutegravir * Entry Inhibitors * Maraviroc (CCR 5 antagonist) * Enfuvirtide (Fusion inhibitor) *Anti-retroviral drug classes

* Risk reduction measures * Condoms provision * needle and syringe provision * Male circumcision * STI diagnosis and treatment * ART as prevention * Early diagnosis and treatment of HIV * Tas. P (Treatment as Prevention) * * HPTN 052 – 93% reduction in HIV transmission with early ART Partner study – no transmission with undetectable viral load (gay or heterosexual) * PEP (Post-exposure Prophylaxis) * Pr. EP (Pre-exposure Prophylaxis) * PROUD (UK) and IPERGAY (France) – 86% reduction in HIV acquisition with Truvada *

*Asses risk *Needs to be accessed within 72 hours from GUM clinics, or A&E departments at night and weekends *28 days of ARV therapy * Raltegravir/Truvada *Google “BHIVA guidelines PEPSE” * BHIVA 2011 PEPSE guidelines

*HIV cure research * Berlin patient!!/Mississippi child? ? * Stem cell transplantation * Gene therapies *Combination approaches * HIV managed in primary care!!! *

*Be aware of the undiagnosed *Multidisciplinary approach to HIV testing and prevention * Primary care * Secondary care * Community/outreach *Stepping up HIV treatment * UNAIDS targets to end HIV epidemic *HIV stigma and discrimination * shared responsibility * Crucial intervention to achieve AIDS-free generation *

* www. bashh. org * www. bhiva. org * https: //www. gov. uk/government/organisations/pu blic-health-england * www. medfash. org. uk * www. clinicaloptions. com * www. aidsmap. com * www. hivinsite. com * www. stif. org. uk *Useful Websites
- Slides: 33