INTRODUCTION TO RHEUMATOLOGY KATHRYN DAO MD Arthritis Consultation





















- Slides: 58
INTRODUCTION TO RHEUMATOLOGY KATHRYN DAO, MD Arthritis Consultation Center July 21, 2005
What am I? I am the size of a rabbit with fur as smooth as an otter. I have a spongy beak covered with sensitive skin. I am a monotreme. I protect myself with poisonous spurs from my hind legs My name means "flat feet. "
Why even care? 3500 rheumatologists • • • 2002 CDC reported arthritis as the leading cause of disability in the US. 55. 4 million have chronic joint symptoms lasting for more than 3 months 21. 5 million have not seen a physician 2 million have activity limitations 25% will be unable to work within 7 years of disease onset Direct and indirect costs are estimated at 1% of the US gross domestic product = $86. 2 billion Center for Disease Control and Prevention. MMWR 2004; 53: 383 -6.
Musculoskeletal Complaint Joint Pain Joint Swelling Diffuse/Systemic Sxs Initial Rheumatic History and Physical Exam to Determine: 1. 2. 3. 4. 5. Is it articular Is it acute or chronic? Is inflammation present? How many/which joints are involved? Are there RED FLAGS?
Goals of Assessment • Identify “Red Flag” conditions ~ Conditions with sufficient morbidity/mortality to warrant an expedited diagnosis • Make a timely diagnosis Common conditions occur commonly • Many Sk. M conditions are self-limiting • Some conditions require serial evaluation over time to make a Dx Provide relief, reassurance and plan for evaluation and treatment • •
RED FLAG CONDITIONS • FRACTURE • INFECTION • ORGAN INVOLVEMENT
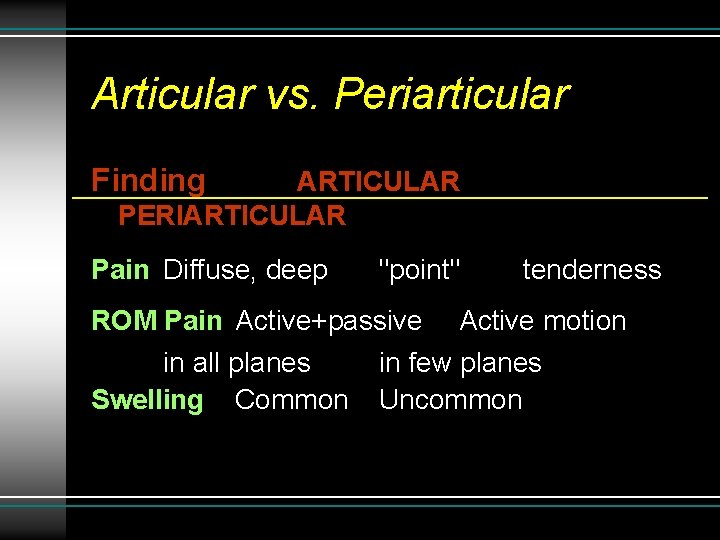
Articular vs. Periarticular Finding ARTICULAR PERIARTICULAR Pain Diffuse, deep "point" tenderness ROM Pain Active+passive Active motion in all planes in few planes Swelling Common Uncommon
Peri-/Non-articular Pain • • • Fibromyalgia Fracture Bursitis, Tendinitis, Enthesitis, Periostitis Carpal tunnel syndrome Polymyalgia rheumatica Sickle Cell Crisis Raynaud’s phenomenon Reflex sympathetic dystrophy Myxedema
Inflammatory vs Noninflammatory
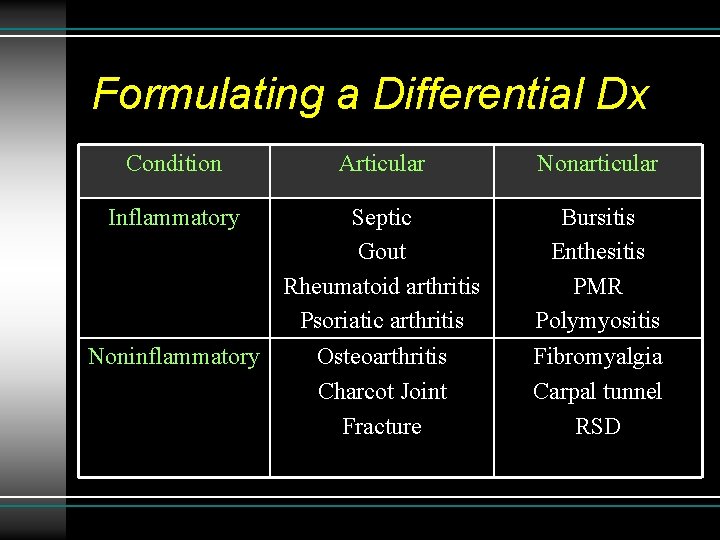
Formulating a Differential Dx Condition Articular Nonarticular Inflammatory Septic Gout Rheumatoid arthritis Psoriatic arthritis Bursitis Enthesitis PMR Polymyositis Noninflammatory Osteoarthritis Charcot Joint Fracture Fibromyalgia Carpal tunnel RSD
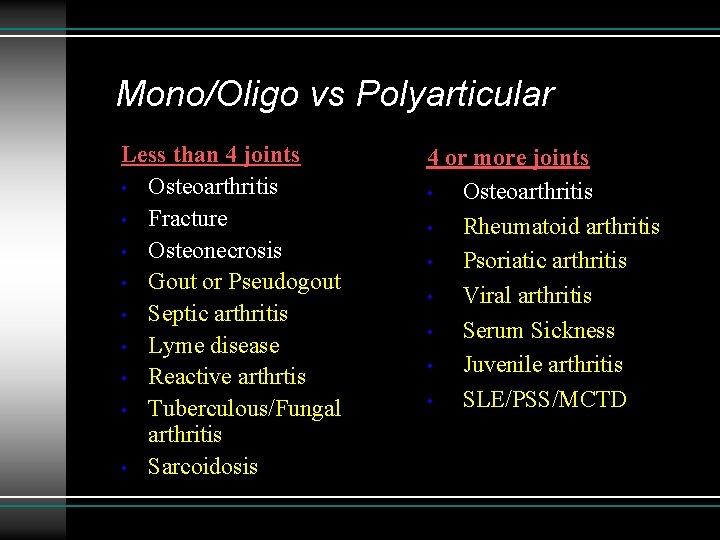
Mono/Oligo vs Polyarticular Less than 4 joints • Osteoarthritis • Fracture • Osteonecrosis • Gout or Pseudogout • Septic arthritis • Lyme disease • Reactive arthrtis • Tuberculous/Fungal arthritis • Sarcoidosis 4 or more joints • Osteoarthritis • Rheumatoid arthritis • Psoriatic arthritis • Viral arthritis • Serum Sickness • Juvenile arthritis • SLE/PSS/MCTD
History: Clues to Diagnosis • • • Age • Young: JRA, SLE, Reiter's, GC arthritis • Middle: Fibromyalgia, tendinitis, bursitis, LBP RA • Elderly: OA, crystals, PMR, septic, osteoporosis Sex • Males: Gout, AS, Reiter's syndrome • Females: Fibrositis, RA, SLE, osteoarthritis Race • White: PMR, GCA and Wegener's • Black: SLE, sarcoidosis • Asian: RA, SLE, Takayasu's arteritis, Behcet's
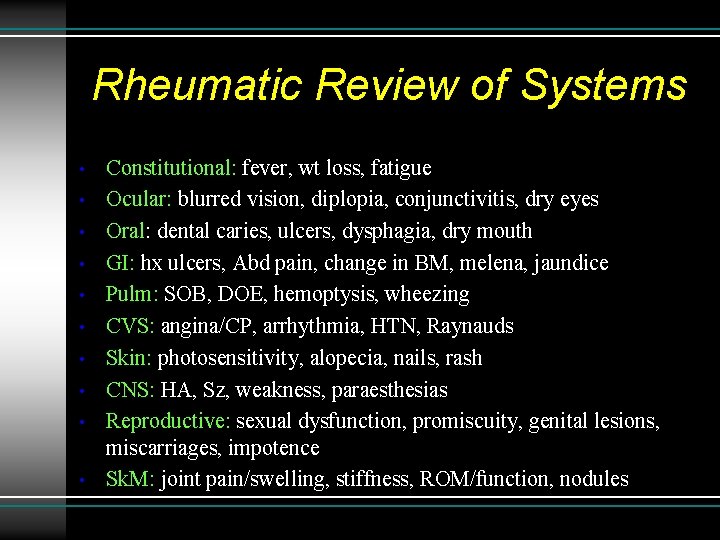
Rheumatic Review of Systems • • • Constitutional: fever, wt loss, fatigue Ocular: blurred vision, diplopia, conjunctivitis, dry eyes Oral: dental caries, ulcers, dysphagia, dry mouth GI: hx ulcers, Abd pain, change in BM, melena, jaundice Pulm: SOB, DOE, hemoptysis, wheezing CVS: angina/CP, arrhythmia, HTN, Raynauds Skin: photosensitivity, alopecia, nails, rash CNS: HA, Sz, weakness, paraesthesias Reproductive: sexual dysfunction, promiscuity, genital lesions, miscarriages, impotence Sk. M: joint pain/swelling, stiffness, ROM/function, nodules
Rheumatic Review of Systems • • • Fever/Constitutional: septic arthritis, vasculitis, Still’s disease Ocular: Reiters, Behcets, Sjogrens, Cataracts (steroids) Oral: Sjogrens, Lupus, GC, myositis, drugs GI: Reactive arthritis, IBD, hepatitis, Polyarteritis, Scleroderma Pulm: SLE, RA lung, Churg-Strauss, Wegeners, Scleroderma CVS: Vasculitis, PSS, Raynauds, antiphospholipid syndrome Skin: SLE, psoriatic, vasculitis, Kawasaki syndrome CNS: lupus carpal tunnel, antiphospholipid, vasculitis GYN/GU: antiphospholipid, SLE, Reiters, Behcets, CTX Musculoskeletal: Gout, RA, OA, fibromyalgia, fracture
Onset & Chronology • Acute: Fracture, septic arthritis, gout, rheumatic fever, Reiter's syndrome • Chronic: OA, RA, SLE, psoriatic arthritis, fibromyalgia • Intermittent: gout, pseudogout, Lyme, palindromic rheumatism, Behcet's, Familial Mediterranean Fever • Additive: OA, Reiter's syndrome, psoriatic • Migratory: Viral arthritis (hepatitis B), rheumatic fever, GC arthritis, SLE
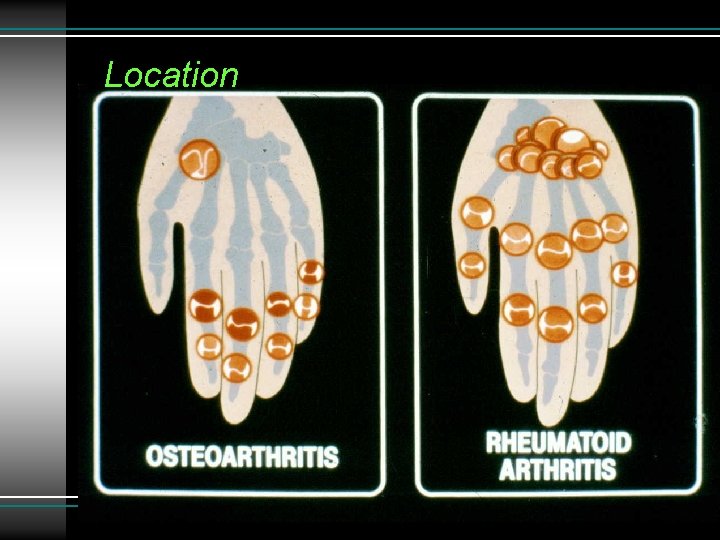
Location
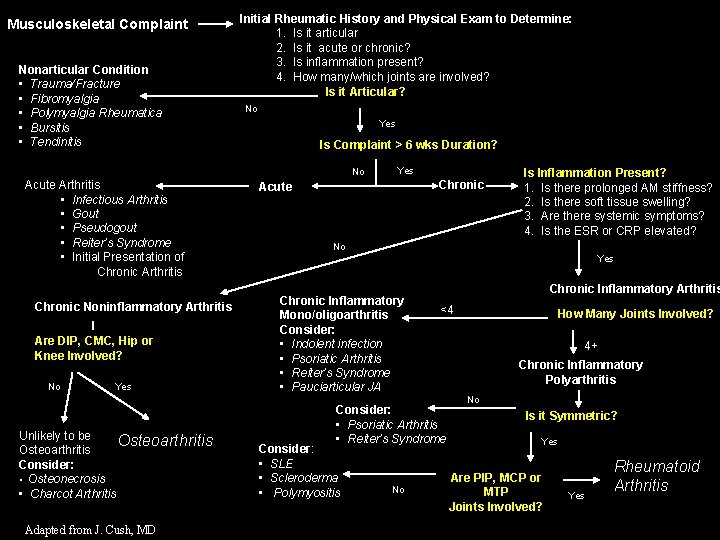
Musculoskeletal Complaint Nonarticular Condition • Trauma/Fracture • Fibromyalgia • Polymyalgia Rheumatica • Bursitis • Tendinitis Initial Rheumatic History and Physical Exam to Determine: 1. Is it articular 2. Is it acute or chronic? 3. Is inflammation present? 4. How many/which joints are involved? Is it Articular? No Yes Is Complaint > 6 wks Duration? No Acute Arthritis • Infectious Arthritis • Gout • Pseudogout • Reiter’s Syndrome • Initial Presentation of Chronic Arthritis Chronic Noninflammatory Arthritis Are DIP, CMC, Hip or Knee Involved? No Yes Unlikely to be Osteoarthritis Consider: • Osteonecrosis • Charcot Arthritis Adapted from J. Cush, MD Yes Chronic Acute Is Inflammation Present? 1. Is there prolonged AM stiffness? 2. Is there soft tissue swelling? 3. Are there systemic symptoms? 4. Is the ESR or CRP elevated? No Yes Chronic Inflammatory Mono/oligoarthritis Consider: • Indolent infection • Psoriatic Arthritis • Reiter’s Syndrome • Pauciarticular JA Chronic Inflammatory Arthritis <4 Consider: • Psoriatic Arthritis • Reiter’s Syndrome Consider: • SLE • Scleroderma • Polymyositis No How Many Joints Involved? 4+ Chronic Inflammatory Polyarthritis No Is it Symmetric? Yes Are PIP, MCP or MTP Joints Involved? Yes Rheumatoid Arthritis
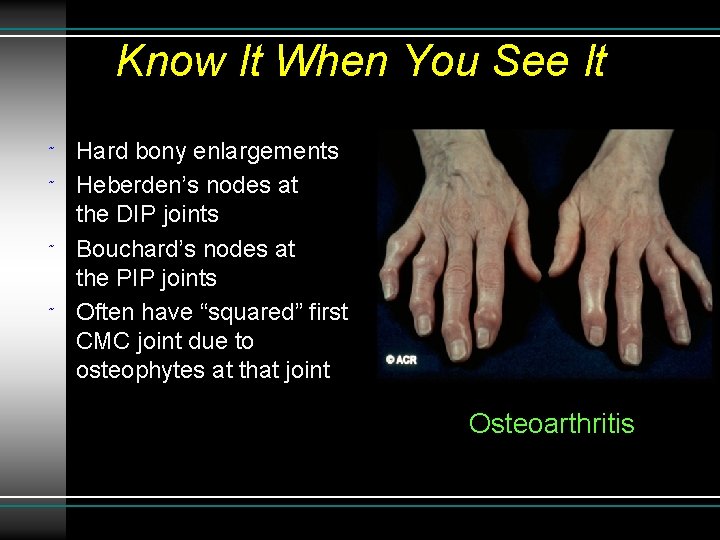
Know It When You See It ˜ ˜ Hard bony enlargements Heberden’s nodes at the DIP joints Bouchard’s nodes at the PIP joints Often have “squared” first CMC joint due to osteophytes at that joint Osteoarthritis
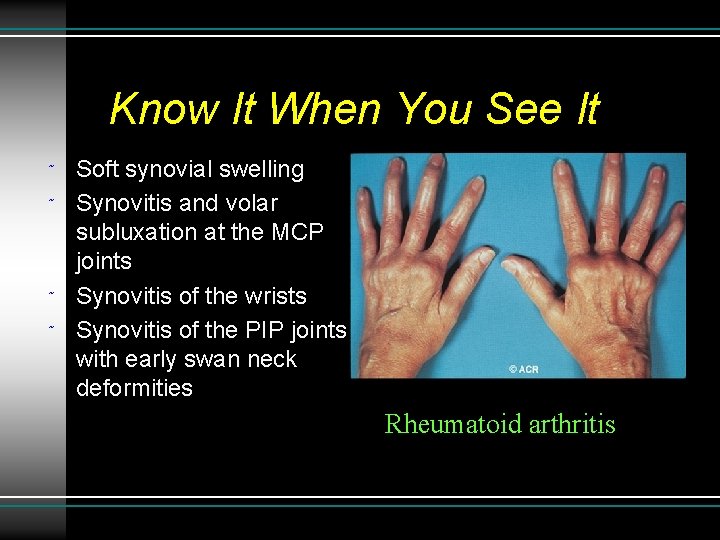
Know It When You See It ˜ ˜ Soft synovial swelling Synovitis and volar subluxation at the MCP joints Synovitis of the wrists Synovitis of the PIP joints with early swan neck deformities Rheumatoid arthritis
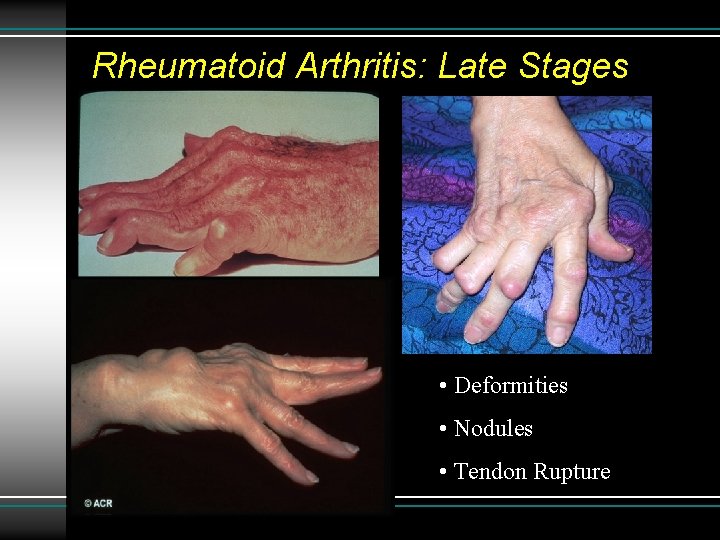
Rheumatoid Arthritis: Late Stages • Deformities • Nodules • Tendon Rupture
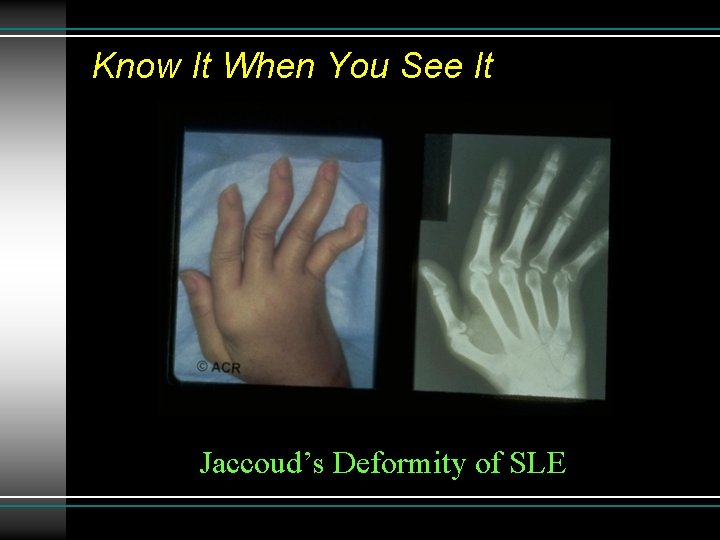
Know It When You See It Jaccoud’s Deformity of SLE
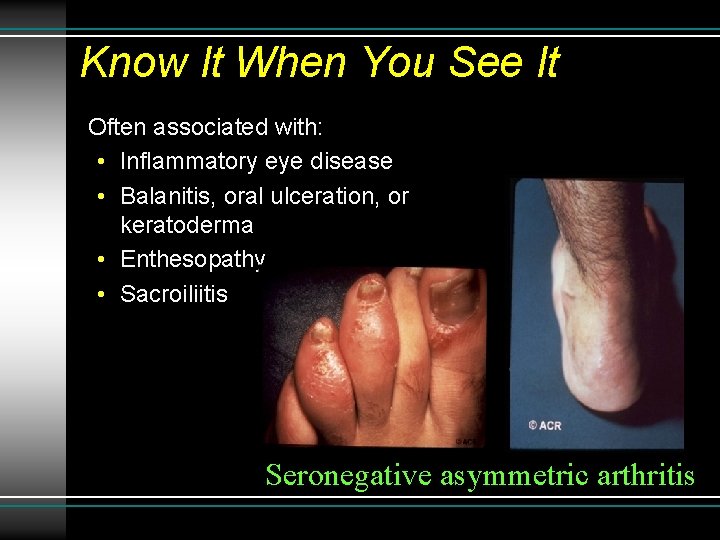
Know It When You See It Often associated with: • Inflammatory eye disease • Balanitis, oral ulceration, or keratoderma • Enthesopathy • Sacroiliitis Seronegative asymmetric arthritis
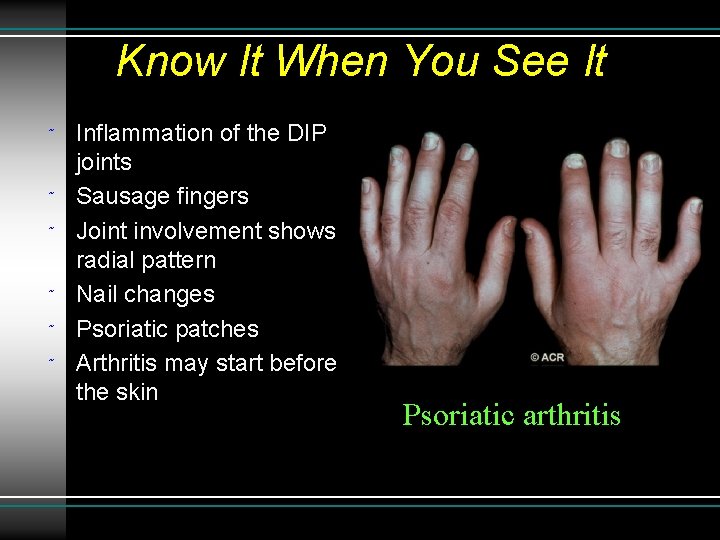
Know It When You See It ˜ ˜ ˜ Inflammation of the DIP joints Sausage fingers Joint involvement shows radial pattern Nail changes Psoriatic patches Arthritis may start before the skin Psoriatic arthritis
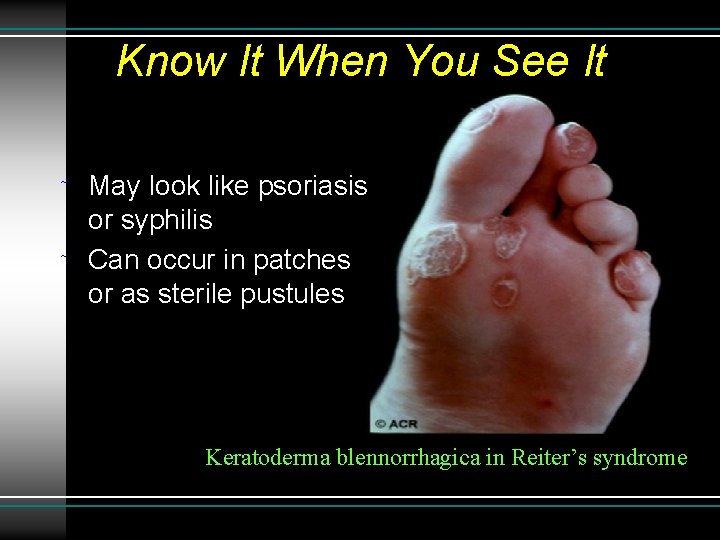
Know It When You See It ˜ ˜ May look like psoriasis or syphilis Can occur in patches or as sterile pustules Keratoderma blennorrhagica in Reiter’s syndrome
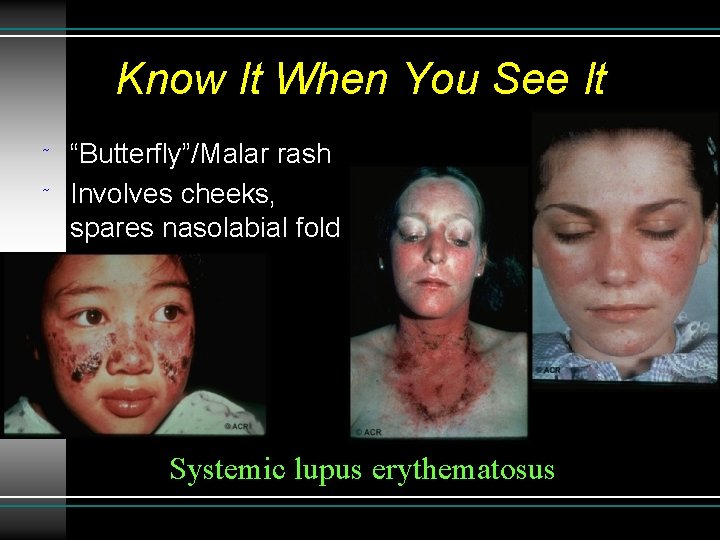
Know It When You See It ˜ ˜ “Butterfly”/Malar rash Involves cheeks, spares nasolabial fold Systemic lupus erythematosus
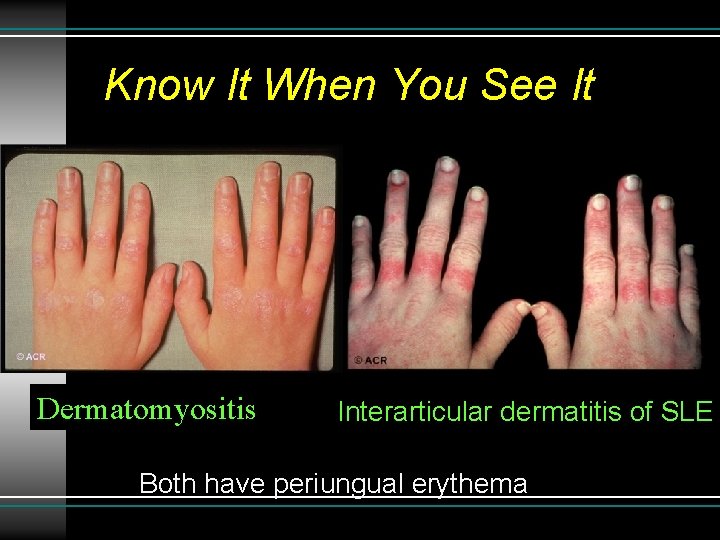
Know It When You See It Dermatomyositis Interarticular dermatitis of SLE Both have periungual erythema
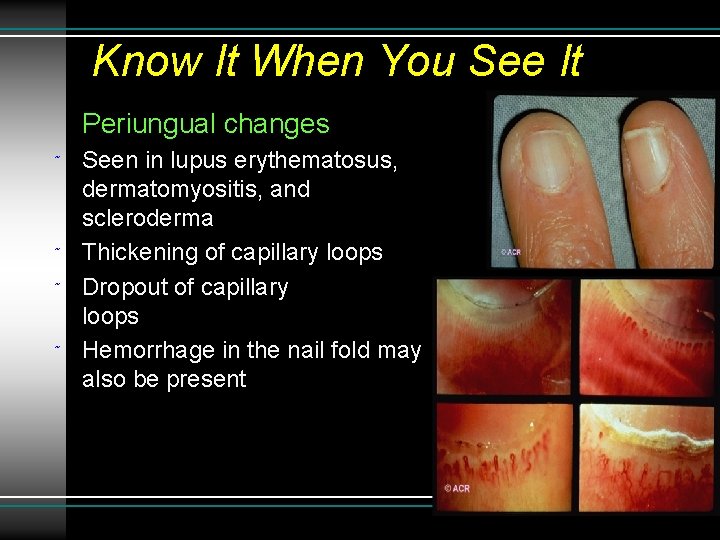
Know It When You See It Periungual changes ˜ ˜ Seen in lupus erythematosus, dermatomyositis, and scleroderma Thickening of capillary loops Dropout of capillary loops Hemorrhage in the nail fold may also be present
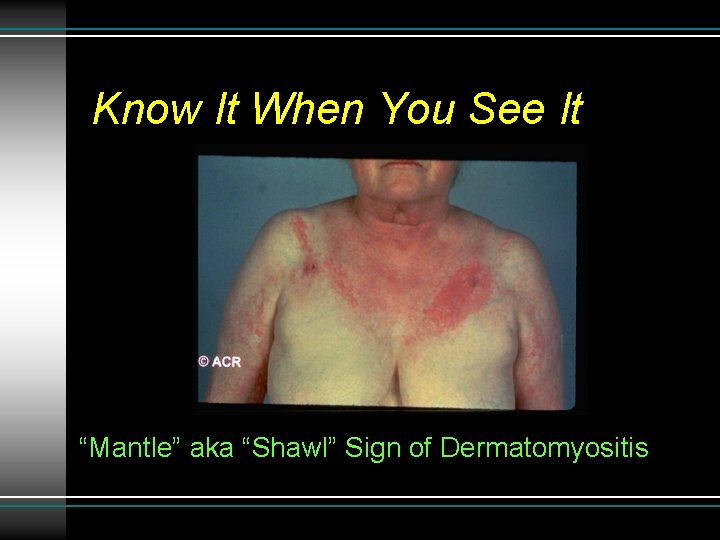
Know It When You See It “Mantle” aka “Shawl” Sign of Dermatomyositis
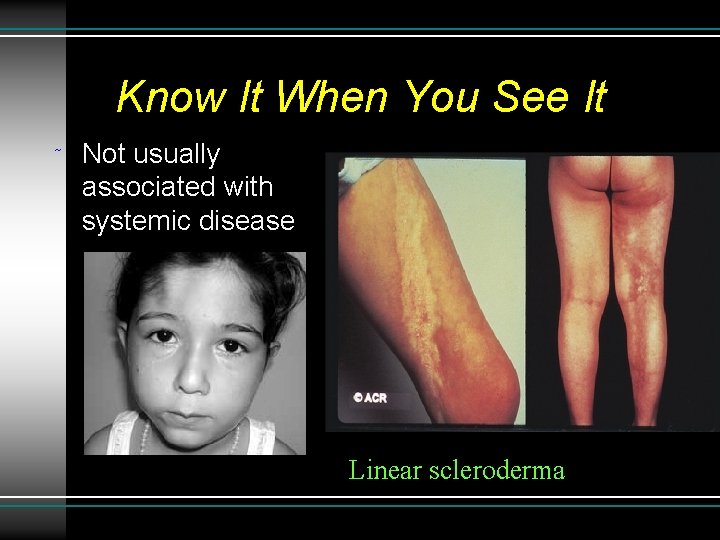
Know It When You See It ˜ Not usually associated with systemic disease Linear scleroderma
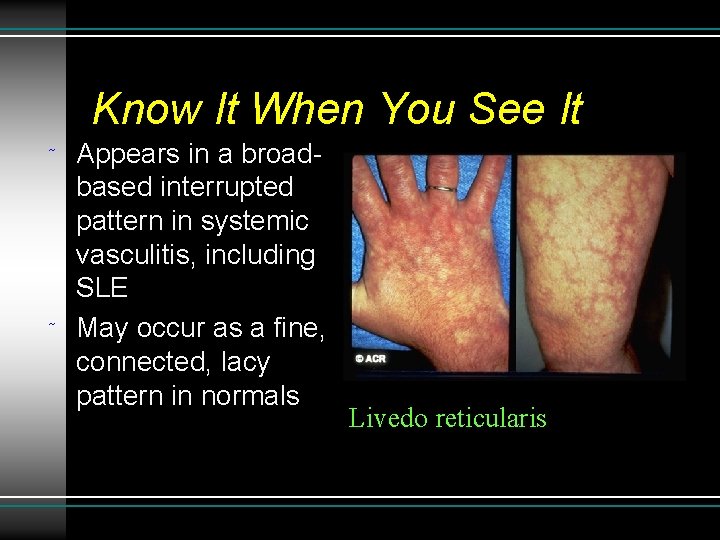
Know It When You See It ˜ ˜ Appears in a broadbased interrupted pattern in systemic vasculitis, including SLE May occur as a fine, connected, lacy pattern in normals Livedo reticularis
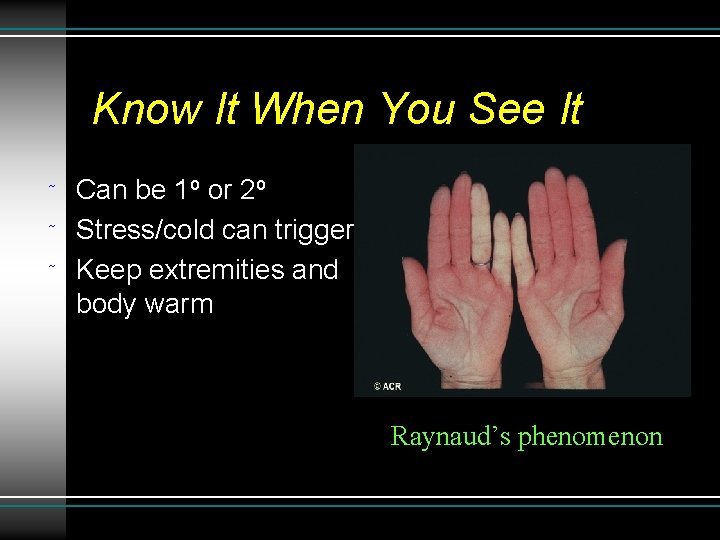
Know It When You See It ˜ ˜ ˜ Can be 1 o or 2 o Stress/cold can trigger Keep extremities and body warm Raynaud’s phenomenon
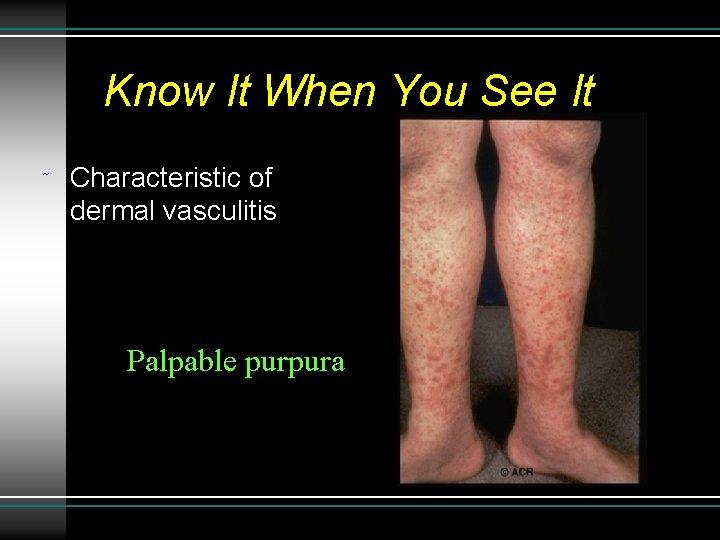
Know It When You See It ˜ Characteristic of dermal vasculitis Palpable purpura
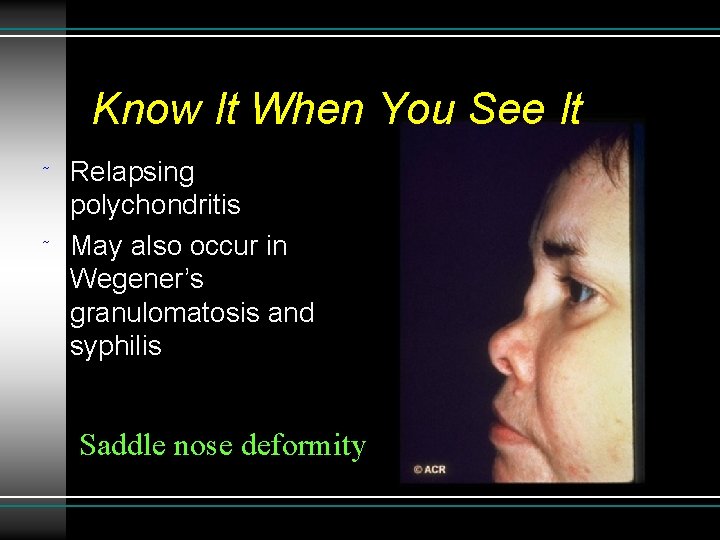
Know It When You See It ˜ ˜ Relapsing polychondritis May also occur in Wegener’s granulomatosis and syphilis Saddle nose deformity
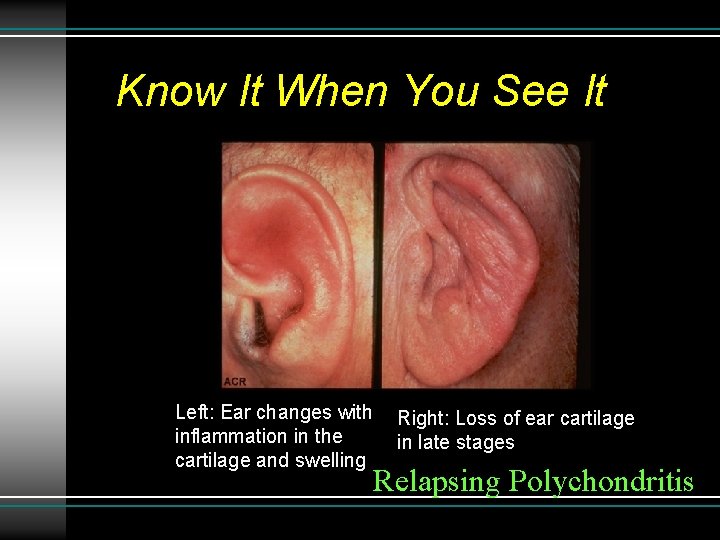
Know It When You See It Relapsing polychondritis Left: Ear changes with inflammation in the cartilage and swelling Right: Loss of ear cartilage in late stages Relapsing Polychondritis
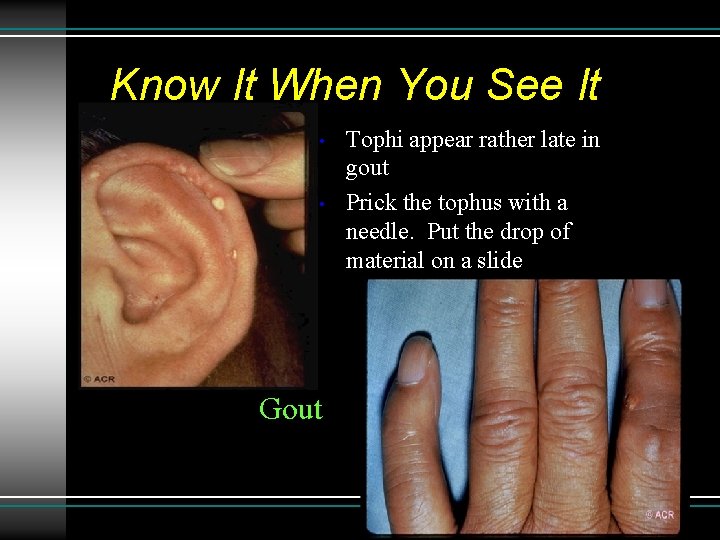
Know It When You See It • • Gout Tophi appear rather late in gout Prick the tophus with a needle. Put the drop of material on a slide
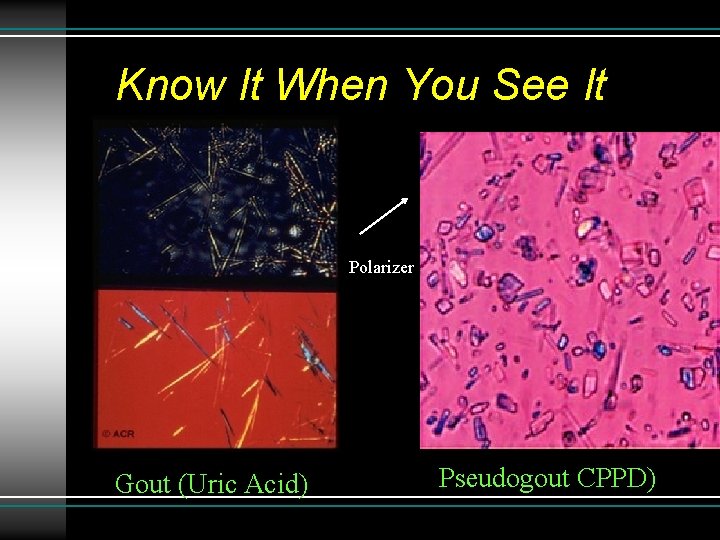
Know It When You See It Polarizer Gout (Uric Acid) Pseudogout CPPD)
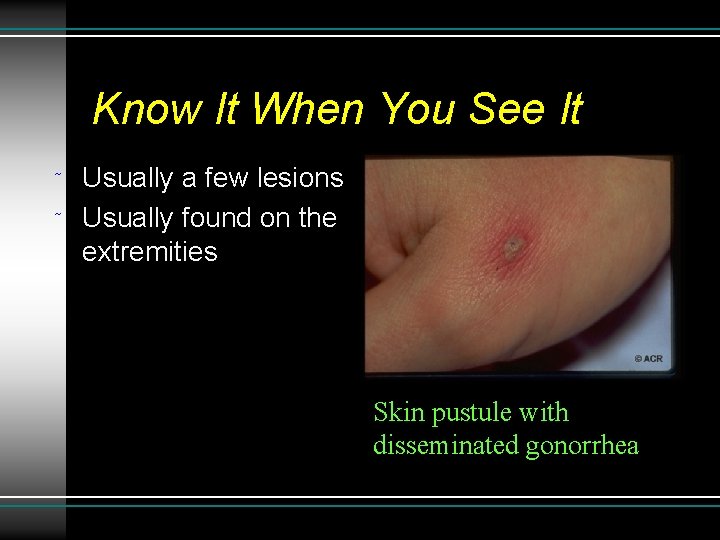
Know It When You See It ˜ ˜ Usually a few lesions Usually found on the extremities Skin pustule with disseminated gonorrhea
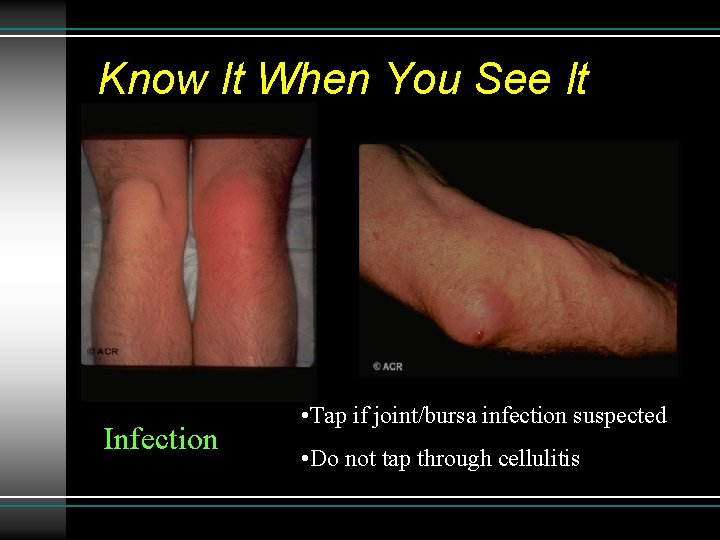
Know It When You See It Infection • Tap if joint/bursa infection suspected • Do not tap through cellulitis
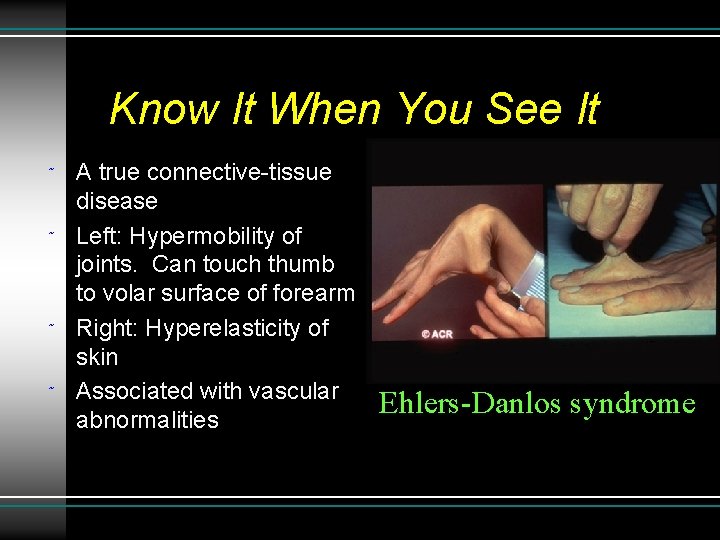
Know It When You See It ˜ ˜ A true connective-tissue disease Left: Hypermobility of joints. Can touch thumb to volar surface of forearm Right: Hyperelasticity of skin Associated with vascular abnormalities Ehlers-Danlos syndrome
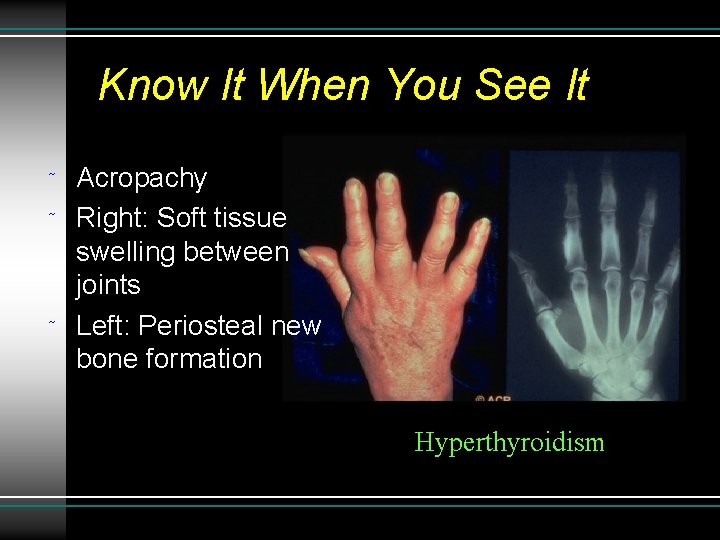
Know It When You See It ˜ ˜ ˜ Acropachy Right: Soft tissue swelling between joints Left: Periosteal new bone formation Hyperthyroidism
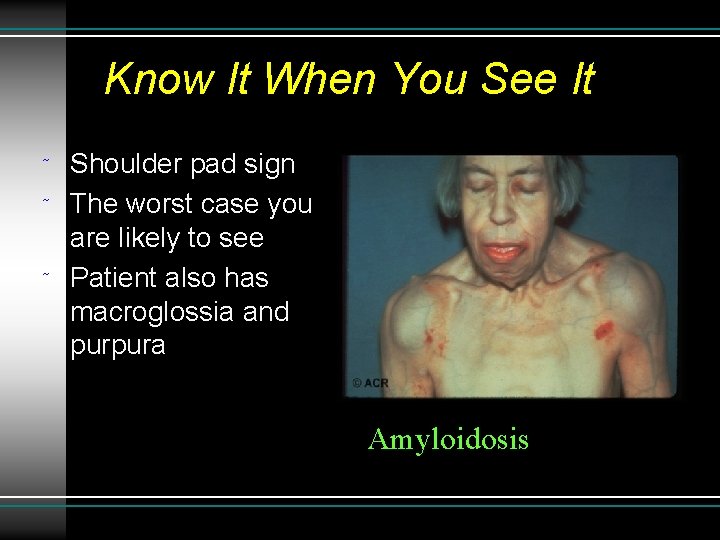
Know It When You See It ˜ ˜ ˜ Shoulder pad sign The worst case you are likely to see Patient also has macroglossia and purpura Amyloidosis
Rheumatologic Assessments • • LABS DO NOT MAKE A DIAGNOSIS; H&P DOES! How can labs lead you astray? ESR/CRP: Origins and associations Serologies (RF, ANA, CCP, APL, ANCA): when to do & in what OTHER diseases are they positive? • Arthrocentesis for diagnosis
RHEUMATOSCREEN PLUS n CBC & differential n Ig. M- RF n Chem-20 n ANA n Uric acid n Urinalysis n ESR n ENA (SSA, SSB, n n C-reactive protein n n RPR n n CPK n n Aldolase n n ASO titer n n Immune complexes n n TFT’s w/ TSH n n EBV titers n RNP, Sm) ds. DNA-Crithidia Scl-70, Jo-1 Histone Abs Ribosomal P Ab Coombs C 3, C 4 CH 50 Cryoglobulins West Nile Ab n Lupus anticoag. n Cardiolipin Ab n c-ANCA n anti-PR 3, -MPO n anti-GBM n SPEP n Lyme titer n HIV n Chlamydia Ab. n Parvovirus B 19 n HBV, HCV, HAV n HLA typing n CCP Ab CUSHY LABS INC. “YOUR INDECISION IS OUR BREAD AND BUTTER”
Presbyterian Hosp. Cheapo. Screen CBC & diff Chem-20 Urinalysis ESR or CRP Uric acid $35. 00 $108. 00 $30. 00 $25. 30 $40. 00 ANA + RF $ 238. 30 CUSHY LABS INC. “YOUR INDECISION IS OUR BREAD AND BUTTER”
Further Investigations • • Many conditions are self-limiting Consider when: • • • Systemic manifestations (fever, wt. loss, rash, etc) Trauma (do exam or imaging for Fracture, ligament tear) Neurologic manifestations Lack of response to observation & symptomatic Rx (<6 wks) Chronicity ( > 6 weeks)
Acute Phase Reactants • • • Erythrocyte Sedimentation Rate (nonspecific) C-Reactive Protein (CRP) Fibrinogen Serum Amyloid A (SAA) Ceruloplasmin Complement (C 3, C 4) Haptoglobin Ferritin Other indicators: leukocytosis, thrombocytosis, hypoalbuminemia, anemia of chronic disease
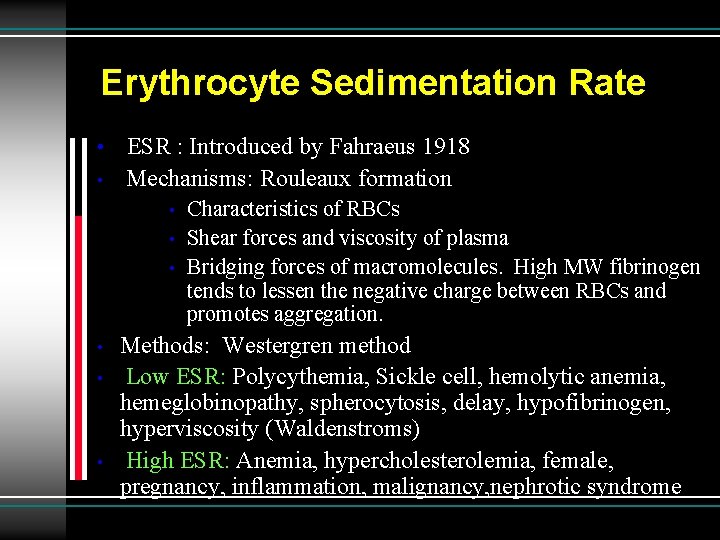
Erythrocyte Sedimentation Rate • • ESR : Introduced by Fahraeus 1918 Mechanisms: Rouleaux formation • • • Characteristics of RBCs Shear forces and viscosity of plasma Bridging forces of macromolecules. High MW fibrinogen tends to lessen the negative charge between RBCs and promotes aggregation. Methods: Westergren method Low ESR: Polycythemia, Sickle cell, hemolytic anemia, hemeglobinopathy, spherocytosis, delay, hypofibrinogen, hyperviscosity (Waldenstroms) High ESR: Anemia, hypercholesterolemia, female, pregnancy, inflammation, malignancy, nephrotic syndrome
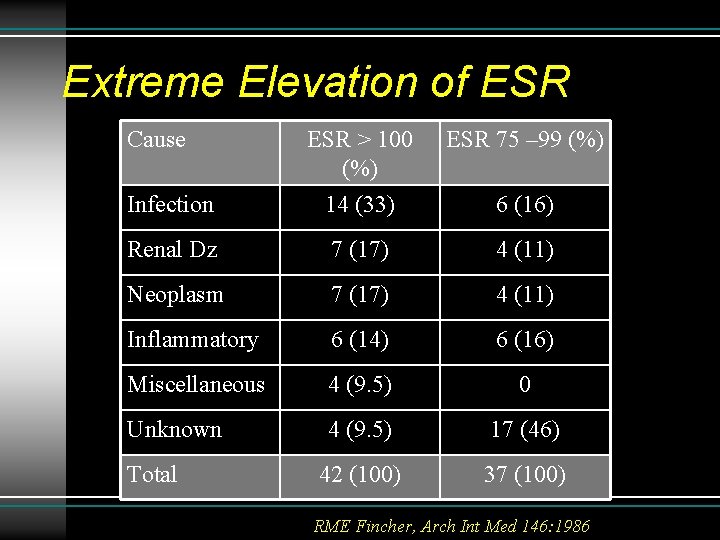
Extreme Elevation of ESR Cause ESR 75 – 99 (%) Infection ESR > 100 (%) 14 (33) Renal Dz 7 (17) 4 (11) Neoplasm 7 (17) 4 (11) Inflammatory 6 (14) 6 (16) Miscellaneous 4 (9. 5) 0 Unknown 4 (9. 5) 17 (46) 42 (100) 37 (100) Total 6 (16) RME Fincher, Arch Int Med 146: 1986
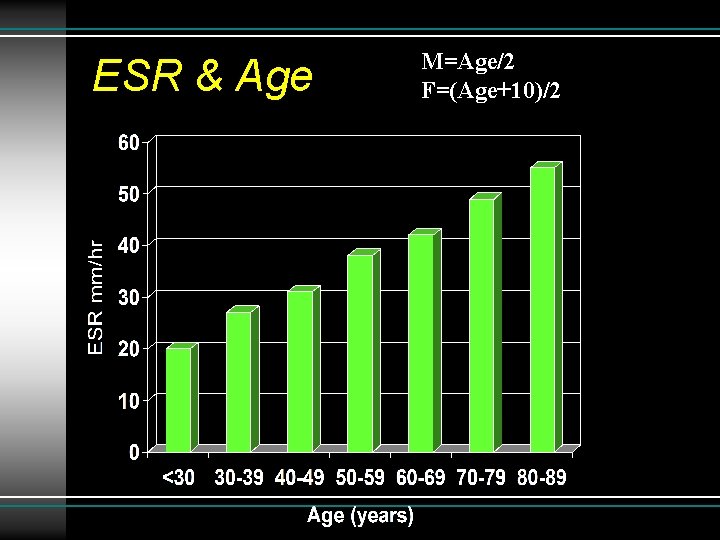
ESR & Age M=Age/2 F=(Age+10)/2
ACP Recommendations for Diagnostic Use of Erythrocyte Sedimentation Rate • The ESR should not be used to screen asymptomatic persons for disease • The ESR should be used selectively and interpreted with caution. . Extreme elevation of the ESR seldom occurs in patients with no evidence of serious disease • If there is no immediate explanation for an increased ESR, the physician should repeat the test in several months rather than search for occult disease • The ESR is indicated for the diagnosis and monitoring of temporal arteritis and polymyalgia rheumatica • In diagnosing and monitoring patients with rheumatoid arthritis, the ESR should be used prinicipally to resolve conflicting clinical evidence • The ESR may be helpful in monitoring patients with treated Hodgkin’s disease
Case • • 28 yr. old WF presents with sudden onset of knee swelling and pain 7 days ago. Two days later, knee resolved but both wrists began to swell. On day 7, the wrists improved but all PIPs were swollen and tender. By day 10 She visits her PCP who examines her and orders “Rheumatoscreen Plus” and XRAYs. He sends her home on OTC ibuprofen, tylenol and Vicks Vapo-Rub. she complained of arthritis in PIPs, wrists, knees and ankles. + Tenosynovitis L wrist. AM stiffness was 4 hours.
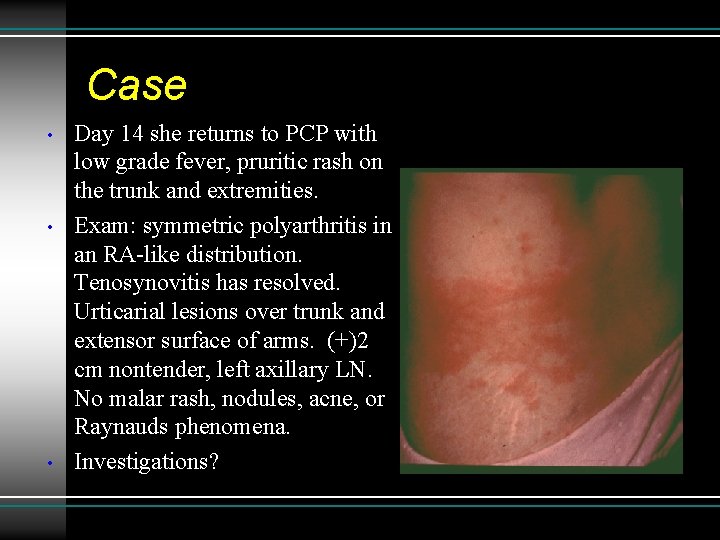
Case • • • Day 14 she returns to PCP with low grade fever, pruritic rash on the trunk and extremities. Exam: symmetric polyarthritis in an RA-like distribution. Tenosynovitis has resolved. Urticarial lesions over trunk and extensor surface of arms. (+)2 cm nontender, left axillary LN. No malar rash, nodules, acne, or Raynauds phenomena. Investigations?
Case • • • WBC = 11. 2 H/H = 13. 7 / 38. 9 MCV = 89 ESR = 123 mm/hr SMA-12 WNL, except albumin = 3. 3, AST-67, ALT 77 ANA negative RF 57 IU/ml (nl < 30 IU/ ml) C 3 173, C 4 28, ASO = 151 Todd units Uric Acid = 6. 6, CCP Ab neg Normal SPEP, UPEP, TFT’s, TSH, Ferritin Others?
Case • • • She returns after 1 wk for LN Bx results (negative) Pt. states her rash and arthritis have nearly resolved. Exam confirms only mild swelling in knees However, her sclera are definitely icteric. Next?
Case • • • WBC = 11. 2 H/H = 13. 7 / 38. 9 MCV = 89 ESR = 123 mm/hr SMA-12 WNL, except albumin = 3. 3 ANA negative RF 31 IU/ml (nl < 30 IU/ ml) C 3 173, C 4 28, ASO = 151 Todd units Uric Acid = 6. 6 Normal SPEP, UPEP, TFT’s, TSH, Ferritin HBs. Ag (+), Neg. for HCV, HAV, HIV
DDx of Migratory Arthritis • Viral arthritis (hepatitis B) • Rheumatic fever • Gonococcal arthritis • SLE • Behcets
Hepatitis B Associated Arthritis • • • Arthritis and urticaria part of the “prodrome” • Manifestations due to immune complex deposition • Before the Jaundice • Usually while LFTs elevated Acute onset Additive (RA like) or migratory (ARF like) arthritis Often with tenosynovitis Synovial fluid: inflammatory Arthritis disappears with onset of Jaundice
What am I?