Dr Shehram Moghul Consultant in OPMH Liaison Psychiatry























- Slides: 39
Dr. Shehram Moghul Consultant in OPMH Liaison Psychiatry Southampton General Hospital Nuffield Wessex Hospital, Chandler’s Ford
� Consultant in Hampshire since 2003 � GMC examiner � Medical member for Ministry of Justice � Board of Royal College of Examiners � Private Consultant for memory problems at Wessex Nuffield Hospital and Priory Hospital � www. moghulmedical. co. uk � (private sec. 02380 877524)
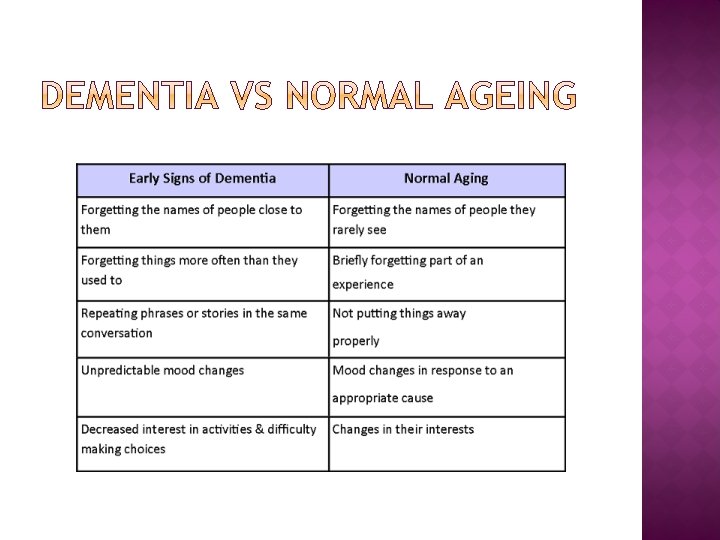
� Dementia vs old age (‘normal ageing’) � Different types � How it ideally should be diagnosed � How it can be helped � Some tips � Time for questions
� Dementia vs old age (‘normal ageing’) � Different types � How it should* be diagnosed � How it can be helped � Some tips � Time for questions *Increasingly difficult due to NHS pressures
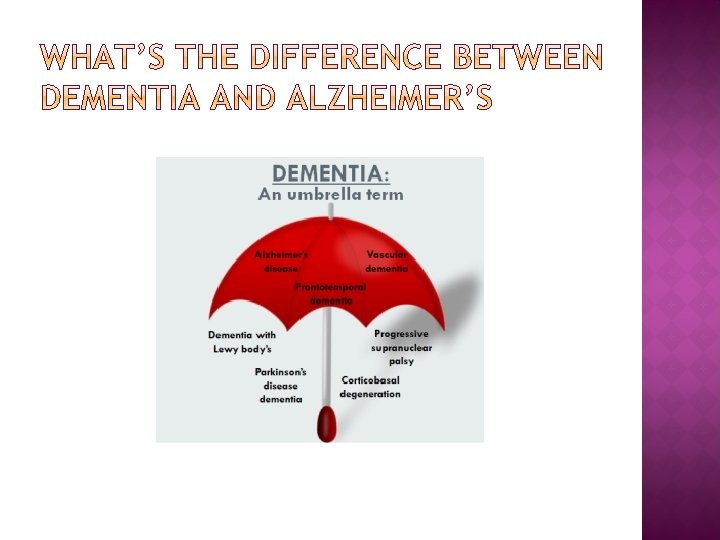
� Dementia vs old age (‘normal ageing’) � Different types (dementia vs Alzheimer’s) � How it ideally should be diagnosed � How it can be helped � Some tips � Time for questions
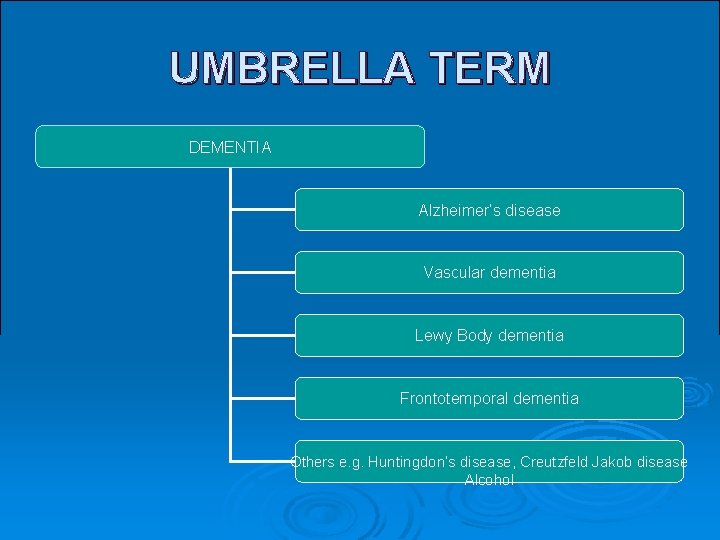
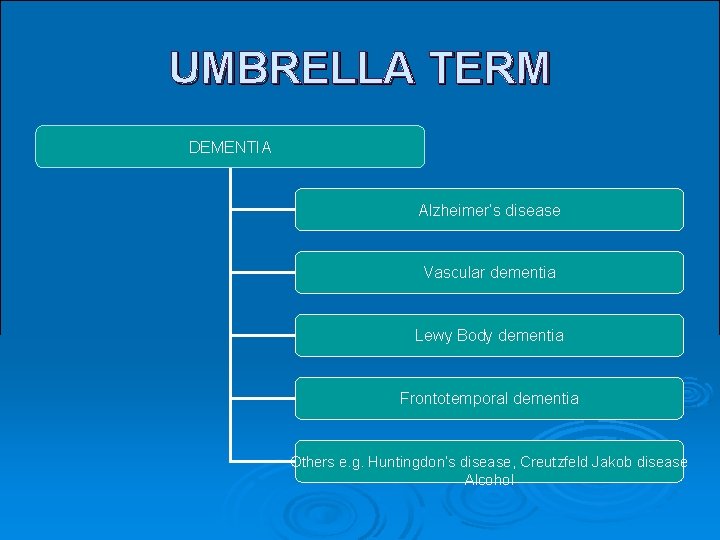
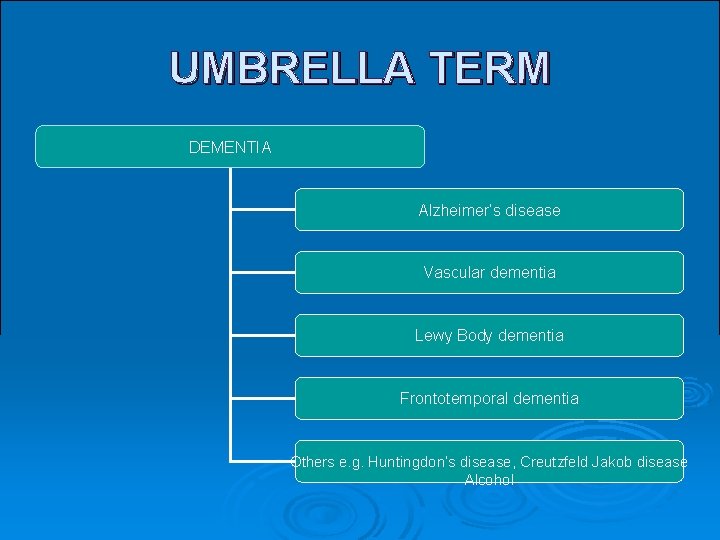
UMBRELLA TERM DEMENTIA Alzheimer’s disease Vascular dementia Lewy Body dementia Frontotemporal dementia Others e. g. Huntingdon’s disease, Creutzfeld Jakob disease Alcohol
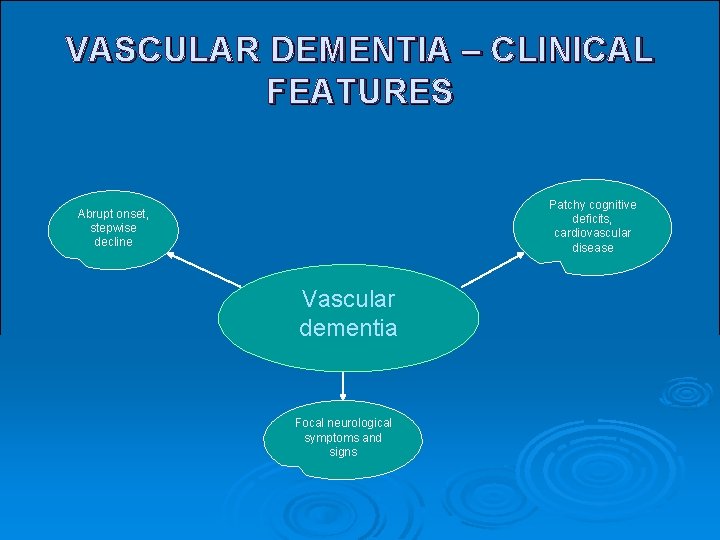
VASCULAR DEMENTIA – CLINICAL FEATURES Patchy cognitive deficits, cardiovascular disease Abrupt onset, stepwise decline Vascular dementia Focal neurological symptoms and signs
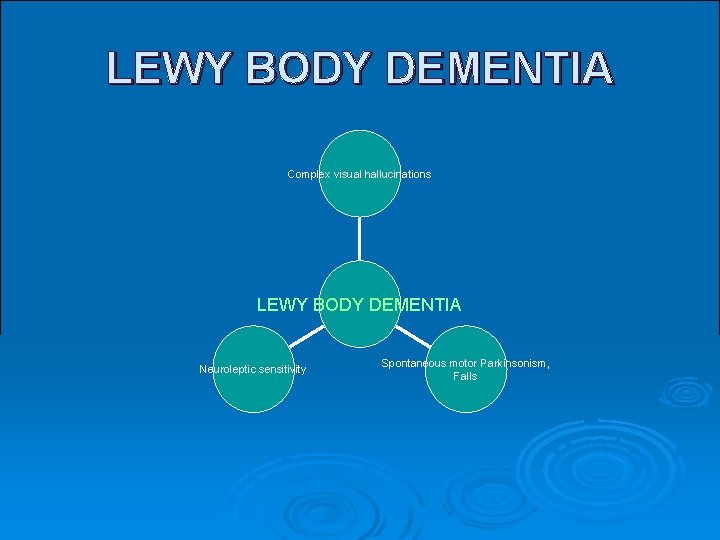
LEWY BODY DEMENTIA Complex visual hallucinations LEWY BODY DEMENTIA Neuroleptic sensitivity Spontaneous motor Parkinsonism, Falls
UMBRELLA TERM DEMENTIA Alzheimer’s disease Vascular dementia Lewy Body dementia Frontotemporal dementia Others e. g. Huntingdon’s disease, Creutzfeld Jakob disease Alcohol
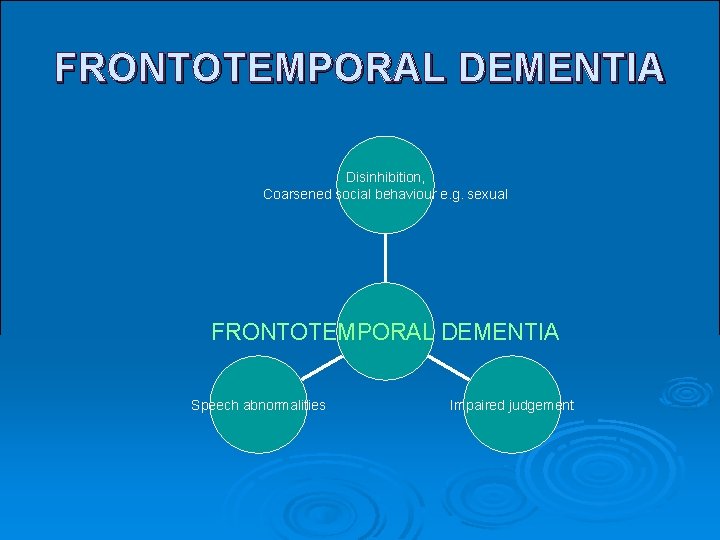
FRONTOTEMPORAL DEMENTIA Disinhibition, Coarsened social behaviour e. g. sexual FRONTOTEMPORAL DEMENTIA Speech abnormalities Impaired judgement
UMBRELLA TERM DEMENTIA Alzheimer’s disease Vascular dementia Lewy Body dementia Frontotemporal dementia Others e. g. Huntingdon’s disease, Creutzfeld Jakob disease Alcohol
� Dementia vs old age (‘normal ageing’) � Different types � How it ideally should* be diagnosed � How it can be helped � Some tips � Time for questions *Recognise can be difficult due to NHS pressures
� History (duration, pattern of symptoms) � Examination (physical, neuro, cognitive) � MMSE – 25/30 � Blood screen (thyroid, alcohol, kidney, B 12) � Maybe a brain scan
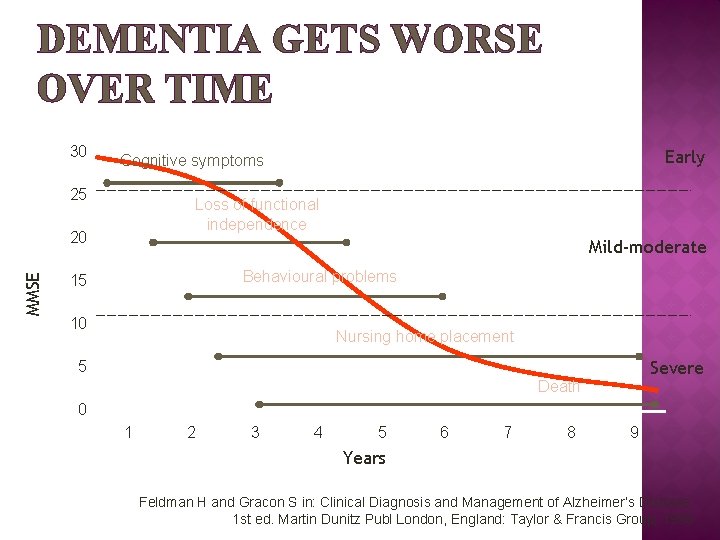
DEMENTIA GETS WORSE OVER TIME 30 25 Loss of functional independence 20 MMSE Early Cognitive symptoms Mild-moderate Behavioural problems 15 10 Nursing home placement Severe 5 Death 0 1 2 3 4 5 6 7 8 9 Years Feldman H and Gracon S in: Clinical Diagnosis and Management of Alzheimer’s Disease. 1 st ed. Martin Dunitz Publ London, England: Taylor & Francis Group; 1998
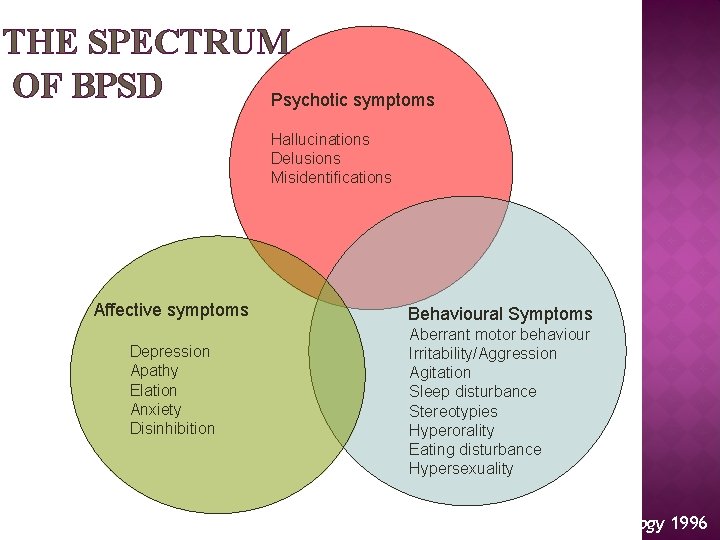
THE SPECTRUM OF BPSD Psychotic symptoms Hallucinations Delusions Misidentifications Affective symptoms Depression Apathy Elation Anxiety Disinhibition Behavioural Symptoms Aberrant motor behaviour Irritability/Aggression Agitation Sleep disturbance Stereotypies Hyperorality Eating disturbance Hypersexuality Mega et al. Neurology 1996
� Dementia vs old age (‘normal ageing’) � Different types � How it should be diagnosed � How it can be helped � Some tips � Time for questions
� There is a cure for dementia? � True or false?
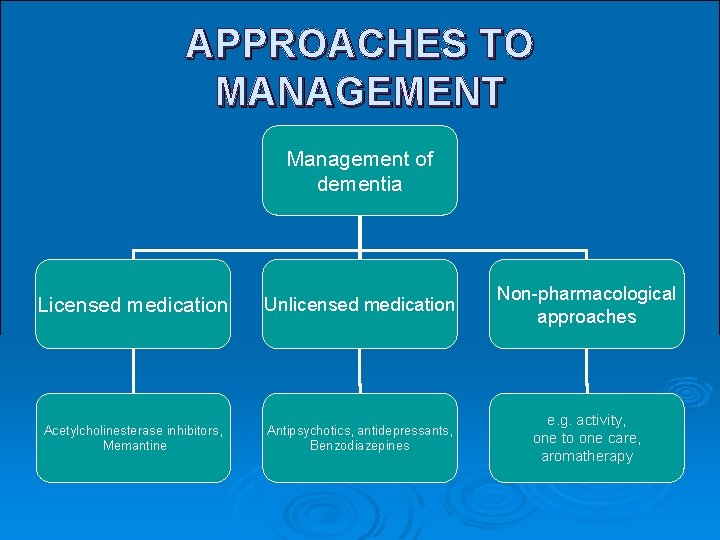
APPROACHES TO MANAGEMENT Management of dementia Licensed medication Unlicensed medication Non-pharmacological approaches Acetylcholinesterase inhibitors, Memantine Antipsychotics, antidepressants, Benzodiazepines e. g. activity, one to one care, aromatherapy
MEMANTINE MECHANISM OF ACTION
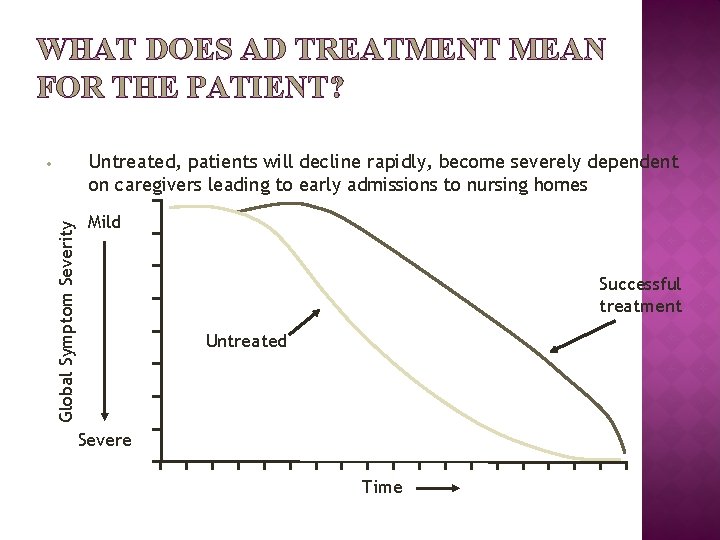
WHAT DOES AD TREATMENT MEAN FOR THE PATIENT? Untreated, patients will decline rapidly, become severely dependent on caregivers leading to early admissions to nursing homes Global Symptom Severity • Mild Successful treatment Untreated Severe Time
� Dementia vs old age (‘normal ageing’) � Different types � How it should be diagnosed � How it can be helped � Some tips � Time for questions
� Peripheral vision � 180 degrees reduced to 35…equivalent to glaucoma � Be within field of vision � Don’t speak until you are within field! � Colour perception drops (rods and cones)– ignore good taste and glam up! � Bright plates, presentation darling � Food dye (Westacre RH)
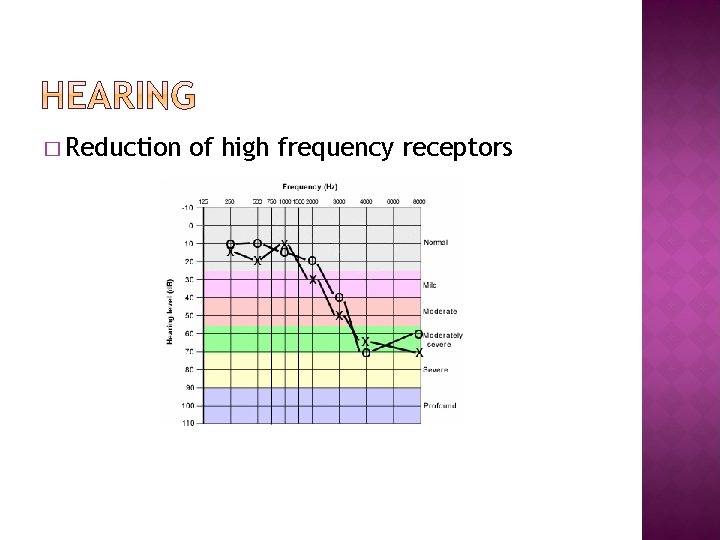
� Reduction of high frequency receptors
� Natural loss worsened in dementia
�LOWER THE TONE OF YOUR VOICE! � Low, familiar tones, spoken slowly…
� Bitter and sweet are the last receptors to deteriorate � Therefore reconsider foods if appetite seems poor � Sherbert lemons, humbugs, don’t worry about diet
� Dementia vs old age (‘normal ageing’) � Different types � How it should* be diagnosed � How it can be helped � Some tips � Time for questions *Increasingly difficult due to NHS pressures
� It’s � not genetic!* *Ahem, actually it is sometimes…
� Consultant in Hampshire since 2003 � GMC examiner � Medical member for Ministry of Justice � Board of Royal College of Examiners � Private Consultant for memory problems at Wessex Nuffield Hospital and Priory Hospital � www. moghulmedical. co. uk � (private sec. 02380 877524)
Dr. Shehram Moghul Consultant in OPMH Liaison Psychiatry Southampton General Hospital