Rh Isoimmunization Professor Hassan A Nasrat Chairman of




















































- Slides: 80
Rh Isoimmunization Professor Hassan A Nasrat Chairman of the Department of Obstetrics and Gynecology Faculty of Medicine King Abdul-Aziz University
ISO: is a prefix means similar, equal or uniform. Isoimmunization: is the process of immunizing a species with antigen derived from the same subject.
Alloimmune Hemolytic Disease Of The Fetus / Newborn: Definition: The Red Cells Of The Fetus Or Newborn Are Destroyed By Maternally Derived Alloantibodies The Antibodies Arise In The Mother As The Direct Result Of A Blood Group Incompatibility Between The Mother And Fetus e. g. When An Rh. D Negative Mother Carries An Rh. D Positive Fetus. In The Fetus: Erythroblastosis Fetalis In The Newborn: HDN.
Antibodies That May Be Detected During Pregnancy: q Innocuous Antibodies: Most Of These Antibody Are Ig. M Therefore Cannot Cross The Placental Barrier E. G. Those Directed Against Such Specificities As A, P(1), Le(a), M, I, IH And Sd(a). q Antibodies Capable Of Causing Significant Hemolytic Transfusion Reactions: Ig. G antibodies, Their Corresponding Antigens Are Not Well Developed At Birth E. g. Lu (b), Yt (a), And VEL — q Antibodies That Are Responsible For HDN : Anti-c, Anti-d, Anti-e, And Anti-k (Kell)
The RH Antigen – Biochemical and Genetic Aspects Mechanism of Development of Maternal Rh Isoimmunization Natural History of Maternal isoimmunization /HD of the Newborn Diagnosis of Rh isoimmunization
The Rh Antigen- Biochemical Aspects: § The Rh Antigen Is A Complex Lipoprotein. § It Has A Molecular Weight Of Approximately 30, 000. § It Is Distributed Throughout The Erythrocyte Membrane In A Nonrandom Fashion. § The Surface Antigens Can Not Be Seen By Routine Microscopy, But Can Be Identified By Specific Antisera Function of the Rh antigen: Its Precise Function Is Unknown. Rh Null Erythrocytes Have Increased Osmotic Fragility And Abnormal Shapes.
The RH Antigen- Genetic Aspect Ø The Rh gene complex is located on the distal end of the short arm of chromosome one. Ø A given Rh antigen complex is determined by a specific gene sequence inherited in a Mendelian fashion from the parents. one haploid from the mother and one from the father. Ø Three genetic loci, determine the Rh antigen (i. e. Rh blood group). Ø Each chromosome will be either D positive or D negative (there is no "d" antigen), C or c positive, and E or e positive.
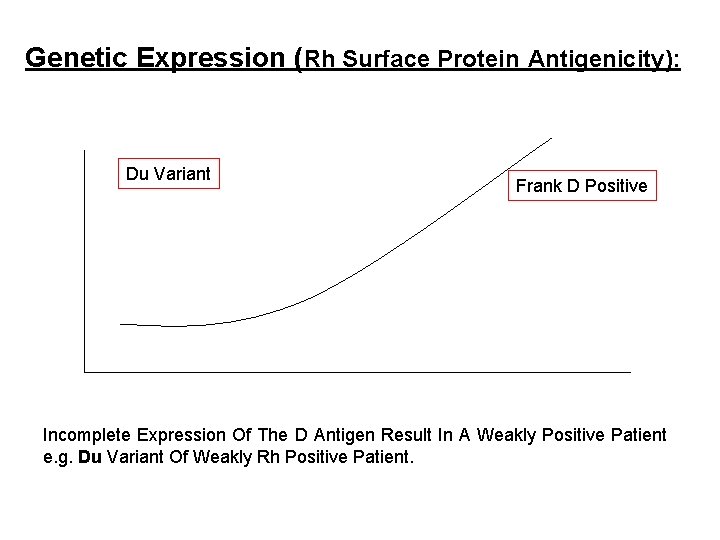
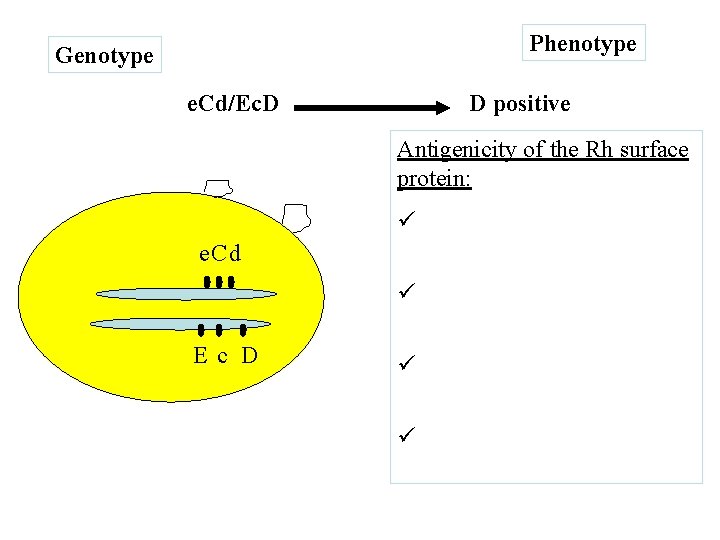
Genetic Expression (Rh Surface Protein Antigenicity): Grades Of “Positively” Due To Variation In The Degree Genetic Expression Of The D Antigen. Incomplete Expression May Result In A Weakly Positive Patient e. g. Du Variant Of Weakly Rh Positive Patient (They May Even Be Determined As Rh Negative). A Mother With Du Rh Blood Group (Although Genetically Positive) May Become Sensitized From A D-positive Fetus Or The Other Way Around May Take Place.
Genetic Expression (Rh Surface Protein Antigenicity): Du Variant Frank D Positive Incomplete Expression Of The D Antigen Result In A Weakly Positive Patient e. g. Du Variant Of Weakly Rh Positive Patient.
Factors Affect The Expression Of The Rh Antigen q The Number Of Specific Rh-antigen Sites: - The Gene Dose, - The Relative Position Of The Alleles, - The Presence Or Absence Of Regulator Genes. q Interaction Of Other Components Of The Rh Blood Group. Erythrocytes Of Individuals Of Genotype Cde/cde Express Less D Antigen Than Do The Erythrocytes Of Individuals Of Genotype c. DE/cde. q The Exposure Of The D Antigen On The Surface Of The Red Cell Membrane.
Phenotype Genotype e. Cd/Ec. D D positive Antigenicity of the Rh surface protein: e. Cd ügenetic expression of the D allele. üNumber of specific Rh antigen sites. Ec D üInteraction of components of the Rh gene complex. üExposure of the D antigen on the surface of the red cell
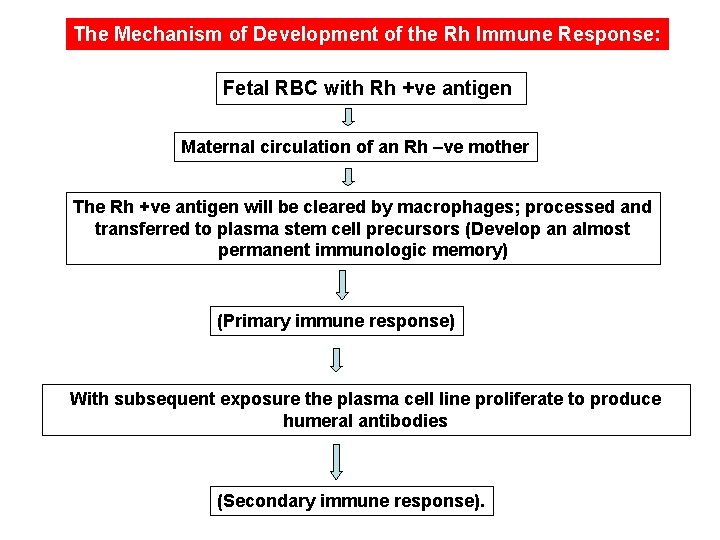
The Mechanism of Development of the Rh Immune Response: Fetal RBC with Rh +ve antigen Maternal circulation of an Rh –ve mother The Rh +ve antigen will be cleared by macrophages; processed and transferred to plasma stem cell precursors (Develop an almost permanent immunologic memory) (Primary immune response) With subsequent exposure the plasma cell line proliferate to produce humeral antibodies (Secondary immune response).
The Primary Response: ØIs a slow response (6 weeks to 6 months). ØIg. M antibodies Øa molecular weight of 900, 000 that does not cross the placenta. The Secondary Response: ØIs a Rapid response ØIg. G antibodies Øa molecular weight of 160, 000 that cross the placenta.
Exposure to maternal antigen in utero “the grandmother theory”: This theory explains the development of fetal isoimmunization in a primigravida, who has no history of exposure to incompatible Rh blood. If a fetus is Rh negative and the mother is Rh positive, the may be exposed to the maternal Rh antigen through maternal-fetal transplacental bleed. In such cases the fetus immune system develop a permanent template (memory) for the Rh-positive antigen. When the fetus becomes a mother herself and exposed to a new load of D antigen from her fetus (hence the grandmother connection) the immune memory is recalled and a secondary immune response occur.
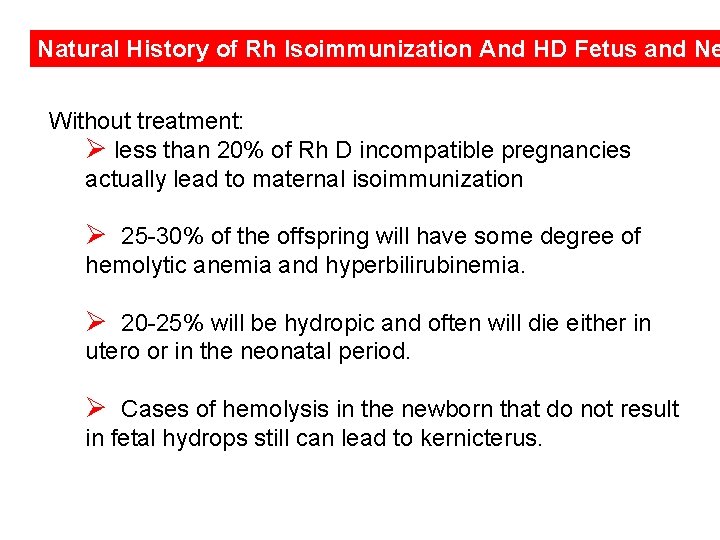
Natural History of Rh Isoimmunization And HD Fetus and Ne Without treatment: Ø less than 20% of Rh D incompatible pregnancies actually lead to maternal isoimmunization Ø 25 -30% of the offspring will have some degree of hemolytic anemia and hyperbilirubinemia. Ø 20 -25% will be hydropic and often will die either in utero or in the neonatal period. Ø Cases of hemolysis in the newborn that do not result in fetal hydrops still can lead to kernicterus.
The Risk of development of Fetal Rh-disease is affected by: Less than 20% of Rh D incompatible pregnancies actually lead to maternal alloimmunization Ø The Husband Phenotype And Genotype (40 % Of Rh Positive Men Are Homozygous And 60% Are Heterozygous). Ø The Antigen Load And Frequency Of Exposure. Ø ABO Incompatibility
Ø Why Not All the Fetuses of Isoimmunized Women Develop the Same Degree of Disease? Ø The Amount Of Fetal Cells In Maternal Blood Ø The Non-responders: Ø ABO Incompatibility: Ø Antigenic Expression Of The Rh Antigen: Ø Classes Of Ig. G Family
Diagnosis of Rh isoimmunization The diagnose is Based on the presence of anti-Rh (D) antibody in maternal serum. q Methods of Detecting Anti D Antibodies in Maternal Serum: Ø The Enzymatic Method Ø The Antibody Titer In Saline, In Albumin Ø The Indirect Coombs Tests.
Diagnosis Maternal Isoimmunization Antibody Titre in Saline: Rh. D-positive cells suspended in saline solution are agglutinated by Ig. M anti-Rh. D antibody, but not Ig. G anti-Rh. D antibody. Thus, this test measure Ig. M, or recent antibody production. Antibody Titre in Albumin: Reflects the presence of any anti. Rh. D Ig. M or Ig. G antibody in the maternal serum. The Indirect Coombs Test: o First Step: Rh. D-positive RBCs are incubated with maternal serum Any anti-Rh. D antibody present will adhere to the RBCs. o Second Step: The RBCs are then washed and suspended in serum containing antihuman globulin (Coombs serum). Red cells coated with maternal anti-Rh. D will be agglutinated by the antihuman globulin (positive indirect Coombs test).
The Direct Coombs Test Is Done After Birth To Detect The Presence Of Maternal Antibody On The Neonate's RBCs. The Infant's RBCs Are Placed In Coombs Serum. If The Cells Are Agglutinated This Indicate The Presence Of Maternal Antibody
Interpretation of Maternal Anti-D Titer q Antibody Titer Is A Screening Test. A Positive Anti-d Titer Means That The Fetus Is At Risk For Hemolytic Disease, Not That It Has Occurred Or Will Develop. q Variation In Titer Results Between Laboratories And Intra Laboratory Is Common. q A Truly Stable Titer Should Not Vary By More Than One Dilution When Repeated In A Given Laboratory.
Pathogenesis of The HD of the Fetus and Newborn
Fetal Rhesus Determination Ø RHD Type And Zygosity (If RHD-positive) Of The Father Ø Amniocentesis To Determine The Fetal Blood Type Using The Polymerase Chain Reaction (PCR) Ø Detection Of Free Fetal RHD DNA (FDNA) Sequences In Maternal Plasma Or Serum Using PCR Ø Flow Cytometry Of Maternal Blood For Fetal Cells
Pathogenesis of Fetal Hemolytic Disease
Methods of Diagnosis and Evaluation of Fetal Rh Isoimmunization Ø Measurements Of Antibodies in Maternal Serum Ø Determination of Fetal Rh Blood Group Ø Ultrasonography Ø Amniocentesis Ø Fetal Blood Sampling
Ultrasonography: Ø To Establish The Correct Gestational Age. Ø In Guiding Invasive Procedures And Monitoring Fetal Growth And Well-being. Ø Ultrasonographic Parameters To Determine Fetal Anemia: o Placental Thickness. o Umbilical Vein Diameter o Hepatic Size. o Splenic Size. o Polyhydramnios. o Fetal Hydrops (e. g. Ascites, Pleural Effusions, Skin Edema).
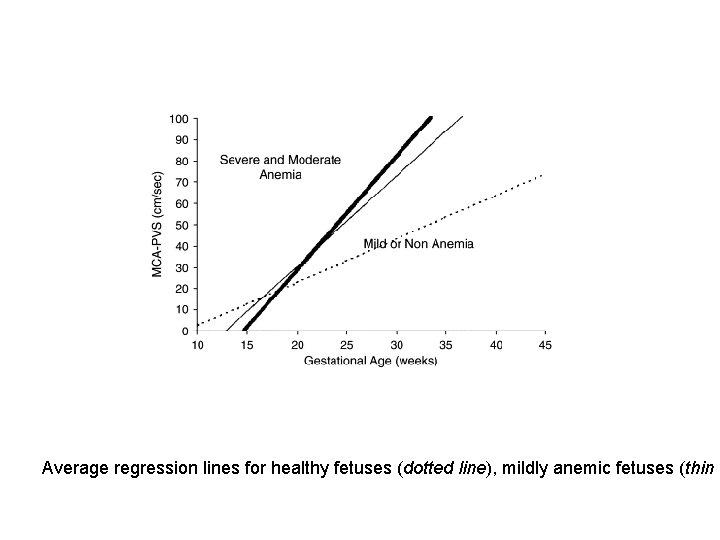
Doppler Velocimetry Of The Fetal Middle Cerebral Artery (MCA) Anemic Fetus Preserves Oxygen Delivery To The Brain By Increasing Cerebral Flow Of Its Already Low Viscosity Blood. Ø For Predicting Fetal Anemia Ø To Predict The Timing Of A Second Intrauterine Fetal Transfusion.
Invasive Techniques ( Amniocentesis and Fetal Blood Sampling): Indications: Ø A Critical Anti-D Titer: I. E. A Titer Associated With A Significant Risk For Fetal Hydrops. Anti-D Titer Value Between 8 And 32 Ø Previous Seriously Affected Fetus Or Infant (e. g. Intrauterine Fetal Transfusion, Early Delivery, Fetal Hydrops, Neonatal Exchange Transfusion).
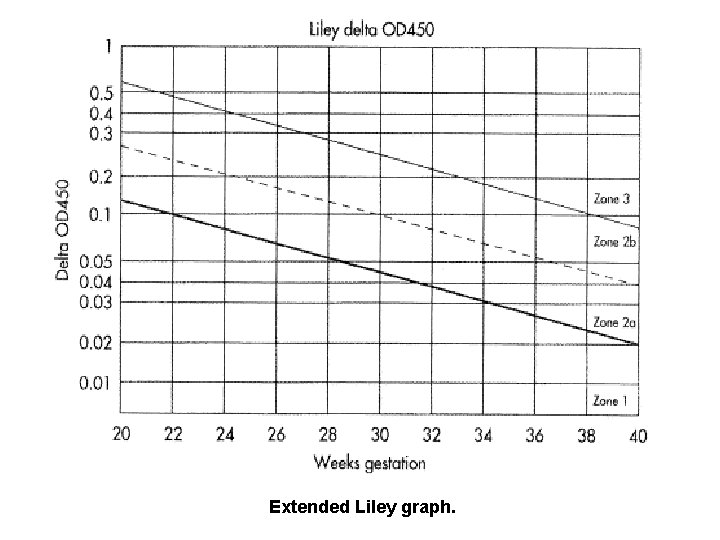
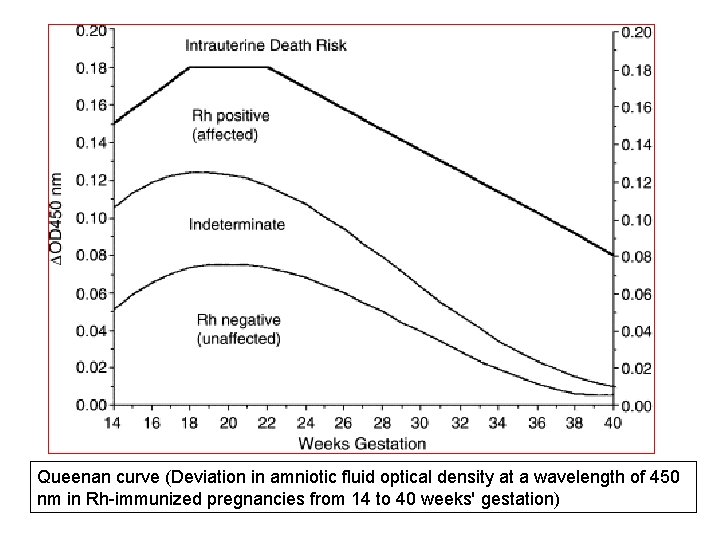
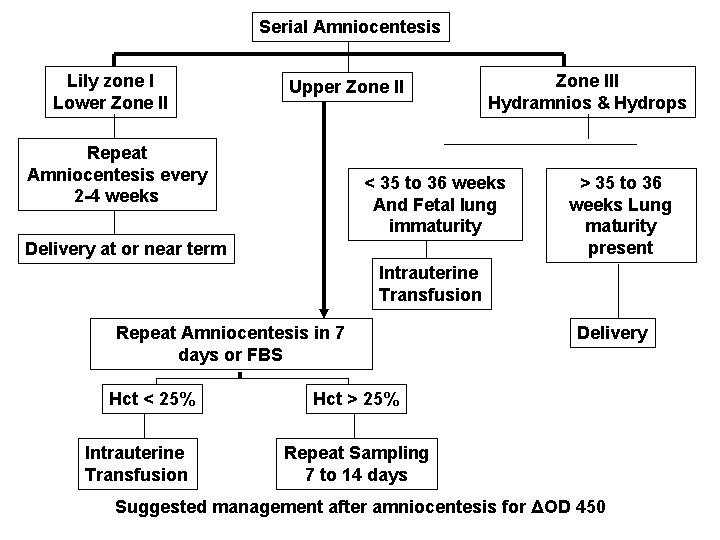
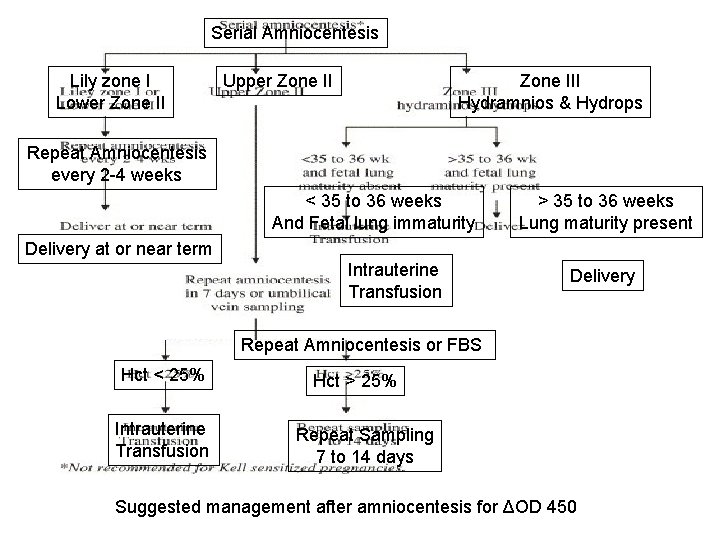
Amniocentesis ü Normally Bilirubin In Amniotic Fluid Decreases With Advanced Gestation. ü It Derives From Fetal Pulmonary And Tracheal Effluents. ü Its Level Rises in Correlation With Fetal Hemolysis. Determination Of Amniotic Fluid Bilirubin: By The Analysis Of The Change In Optical Density Of Amniotic Fluid At 450 nm On The Spectral Absorption Curve (delta OD 450) Procedures Are Undertaken At 10 -15 Days Intervals Until Delivery Data Are Plotted On A Normative Curve Based Upon Gestational Age.
Extended Liley graph.
Queenan curve (Deviation in amniotic fluid optical density at a wavelength of 450 nm in Rh-immunized pregnancies from 14 to 40 weeks' gestation)
Interpretation Of Amniotic Fluid Bilirubin: Ø A Falling Curve: Is Reassuring: i. e. An Unaffected Or Rh. D-negative Fetus. Ø A Plateauing Or Rising Curve: Suggests Active Hemolysis (Require Close Monitoring And May Require Fetal Blood Sampling And/Or Early Delivery). Ø A Curve That Reaches To Or Beyond The 80 th Percentile Of Zone II On The Liley Graph Or Enters The “ Intrauterine Transfusion" Zone Of The Queenan Curve: Necessitates Investigation By Fetal Blood Sampling
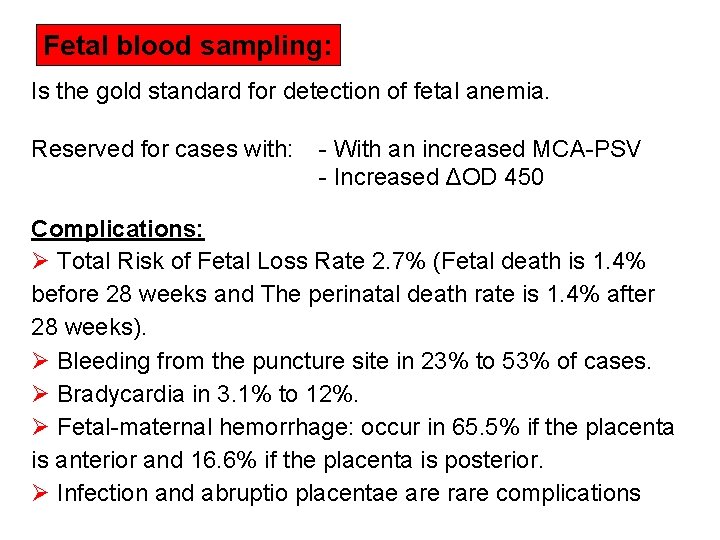
Fetal blood sampling: Is the gold standard for detection of fetal anemia. Reserved for cases with: - With an increased MCA-PSV - Increased ΔOD 450 Complications: Ø Total Risk of Fetal Loss Rate 2. 7% (Fetal death is 1. 4% before 28 weeks and The perinatal death rate is 1. 4% after 28 weeks). Ø Bleeding from the puncture site in 23% to 53% of cases. Ø Bradycardia in 3. 1% to 12%. Ø Fetal-maternal hemorrhage: occur in 65. 5% if the placenta is anterior and 16. 6% if the placenta is posterior. Ø Infection and abruptio placentae are rare complications
MONOCLONAL ANTI-D Most polyclonal Rh. Ig comes from male volunteers who are intentionally exposed to Rh. D-positive red blood cells. Potential Problems: infectious risk solve supply problems. ethical issues anti-D monoclonal antibody: Although monoclonal anti-D is promising, it cannot be recommended at this time as a replacement for polyclonal Rh. Ig.
Complications of Fetal-Neonatal Anemia: Ø Fetal Hydrops And Stillbirth Ø Hepatosplenomegaly Ø Neonatal Jaundice Ø Compilations Of Neonatal Kernicterus (Lethargy, Hypertonicity, Hearing Loss, Cerebral Palsy And Learning Disability) Ø Neonatal Anemia
Causes Of Fetal Neonatal Anemia: Blood Loss: o Abnormal Placental Separation (Abruptio Placentae) Or Placenta Previa o Traumatic Tear Of The Umbilical Cord o Occult Blood Loss In Utero As A Result Of Fetomaternal Hemorrhage. o A Chronic Twin-to-twin Transfusion In Identical Twins Alloimmune Hemolytic Disease Of The Newborn (HDN): Anemia Due To Congenital Spherocytosis Nonspherocytic Hemolytic Anemias Infections: Hemoglobinopathies:
The RH Antigen
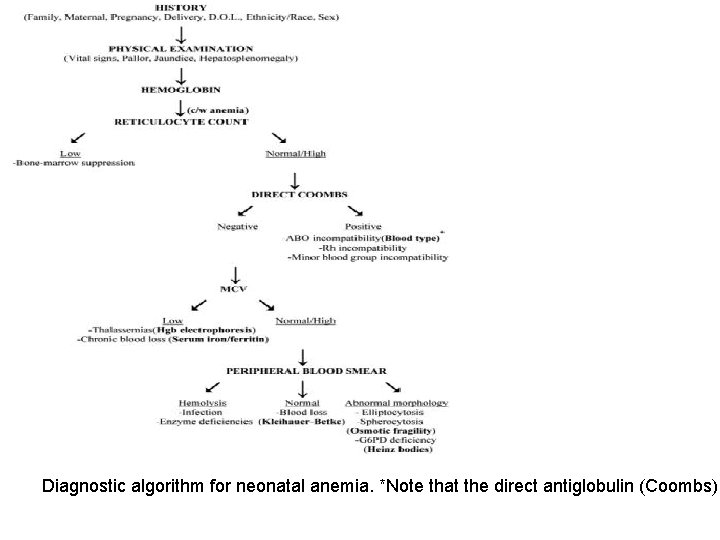
Diagnostic algorithm for neonatal anemia. *Note that the direct antiglobulin (Coombs)
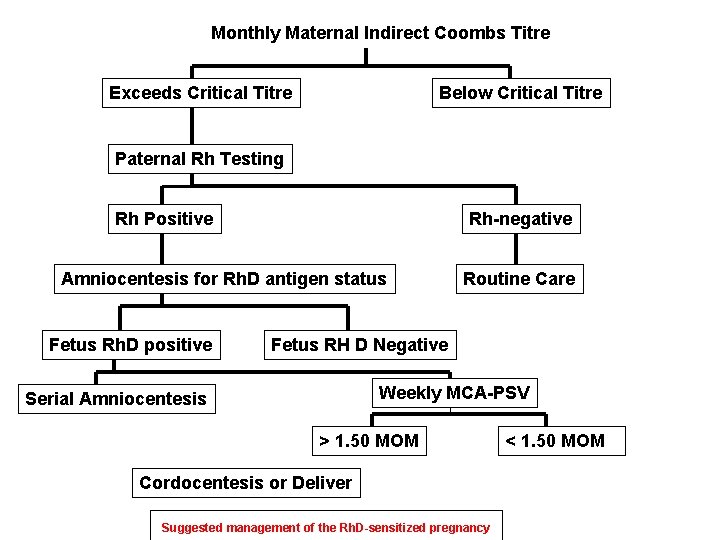
Monthly Maternal Indirect Coombs Titre Exceeds Critical Titre Below Critical Titre Paternal Rh Testing Rh Positive Rh-negative Amniocentesis for Rh. D antigen status Fetus Rh. D positive Routine Care Fetus RH D Negative Weekly MCA-PSV Serial Amniocentesis > 1. 50 MOM Cordocentesis or Deliver Suggested management of the Rh. D-sensitized pregnancy < 1. 50 MOM
Monthly Maternal Indirect Coombs Titre Exceeds Critical Titre Below Critical Titre Paternal Rh Testing Rh-negative Rh Positive Amniocentesis for Rh. D antigen status Fetus Rh. D positive Serial Amniocentesis Routine Care Fetus RH D Negative Weeklyl MCA-PSV < 1. 50 MOM >1. 5 MOM Cordocentesis or De Suggested management of the Rh. D-sensitized pregnancy
Serial Amniocentesis Lily zone I Lower Zone II Upper Zone II Repeat Amniocentesis every 2 -4 weeks Zone III Hydramnios & Hydrops < 35 to 36 weeks And Fetal lung immaturity Delivery at or near term > 35 to 36 weeks Lung maturity present Intrauterine Transfusion Repeat Amniocentesis in 7 days or FBS Hct < 25% Intrauterine Transfusion Delivery Hct > 25% Repeat Sampling 7 to 14 days Suggested management after amniocentesis for ΔOD 450
Serial Amniocentesis Lily zone I Lower Zone II Upper Zone III Hydramnios & Hydrops Repeat Amniocentesis every 2 -4 weeks < 35 to 36 weeks And Fetal lung immaturity > 35 to 36 weeks Lung maturity present Delivery at or near term Intrauterine Transfusion Delivery Repeat Amniocentesis or FBS Hct < 25% Intrauterine Transfusion Hct > 25% Repeat Sampling 7 to 14 days Suggested management after amniocentesis for ΔOD 450
Average regression lines for healthy fetuses (dotted line), mildly anemic fetuses (thin l
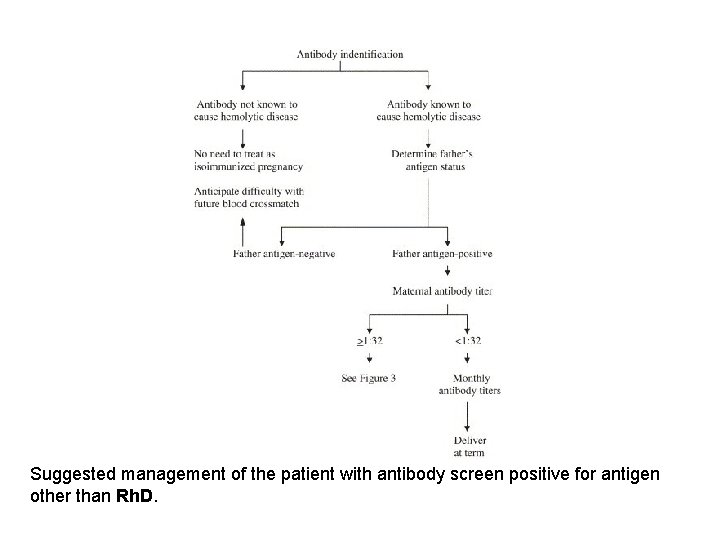
Suggested management of the patient with antibody screen positive for antigen other than Rh. D.
Incidence Of Maternal Alloimmunization The overall incidence of maternal alloimmunization to clinically significant RBC antigens has been estimated to be 25 per 10, 000 live births
Rh. D D negativity primarily occurs among Caucasians; the average incidence is 15 percent in this group. Examples of the blood group distribution in various populations are illustrated below: Basques — 30 to 35 percent Finland — 10 to 12 percent American blacks — 8 percent Indo-Eurasians — 2 percent Native Americans and Inuit Eskimos — 1 to 2 percent.
Changes since introduction of Anti-D
PATHOGENESIS • Chronic transplacental hemorrhage. • Failure to administer Rh immune globulin when indicated. • or non-detection of a large fetal bleed at delivery
As an example, in a study of 110 pregnant mothers with 111 at-risk fetuses, and maternal serum titers of 1: 16 or greater, antibodies to D, K, E, and c were present in 84, 18, 8, and 3 fetuses, respectively
The nature of the Rh antigen complex is determined by a specific gene sequence inherited in a Mendelian fashion from the parents, one haploid from the mother and one from the father. In 1974 the location of the Rh gene complex was pinpointed on the distal end of the short arm of chromosome one. Three genetic loci, each with two possible alleles determined the Rh antigen (i. e. Rh blood group).
The amount of fetal cells in maternal blood: the Kleihauer-Braun-Betke test
The severity of fetal anemia is influenced: Primarily by antibody concentration, Additional factors that are not fully understood. These include the subclass and glycosylation of maternal antibodies. The structure, site density, maturational development and tissue distribution of blood group antigens. The efficiency of transplacental Ig. G transport. The functional maturity of the fetal spleen. Polymorphisms which affect Fc receptor function; and the presence of HLArelated inhibitory antibodies [13].
DIAGNOSIS Blood and Rh(D) typing and an antibody screen should always be performed at the firs
Below the critical titer there is a risk of mild to moderate, but not severe, fetal or neonatal hemolytic anemia. Fetal assessment with invasive techniques (eg, amniocentesis, fetal blood sampling) is required when a critical titer is present or if the patient has had a prior significantly affected pregnancy (eg, intrauterine fetal transfusion, early delivery, fetal hydrops, neonatal exchange transfusion). The purpose of these invasive tests is to determine whether severe fetal anemia is present.
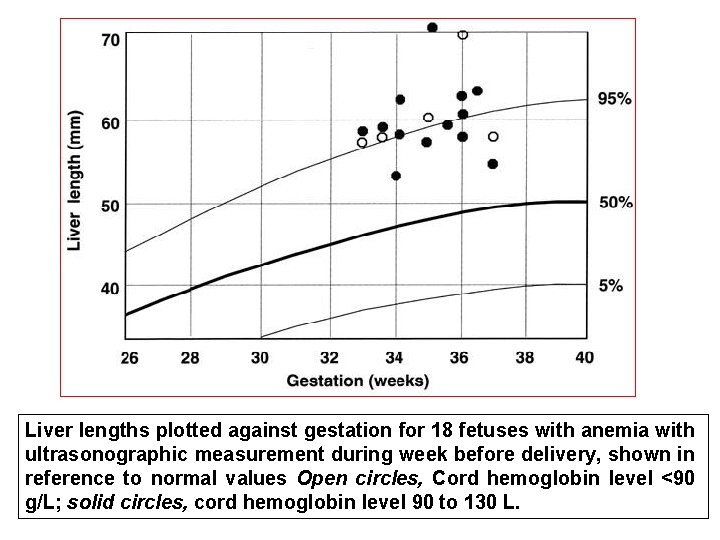
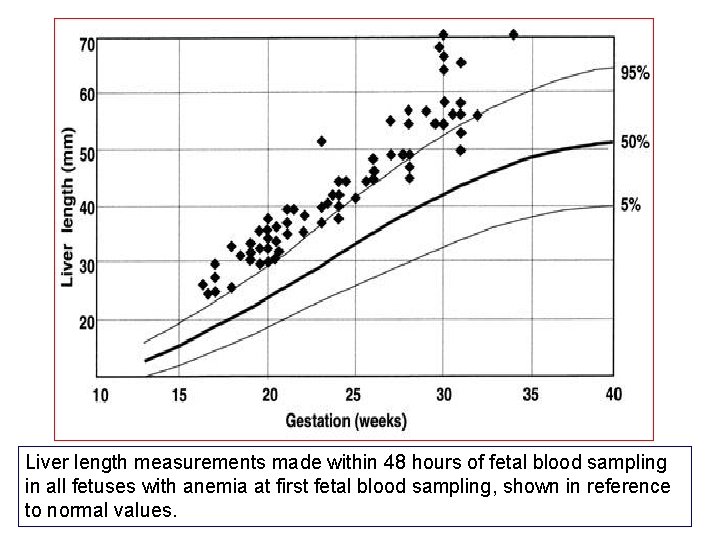
Ultrasonography A variety of ultrasonographic parameters have been used to determine whether fetal anemia is present. These parameters include: placental thickness; umbilical vein diameter; hepatic size; splenic size; and polyhydramnios
Liver lengths plotted against gestation for 18 fetuses with anemia with ultrasonographic measurement during week before delivery, shown in reference to normal values Open circles, Cord hemoglobin level <90 g/L; solid circles, cord hemoglobin level 90 to 130 L.
Liver length measurements made within 48 hours of fetal blood sampling in all fetuses with anemia at first fetal blood sampling, shown in reference to normal values.
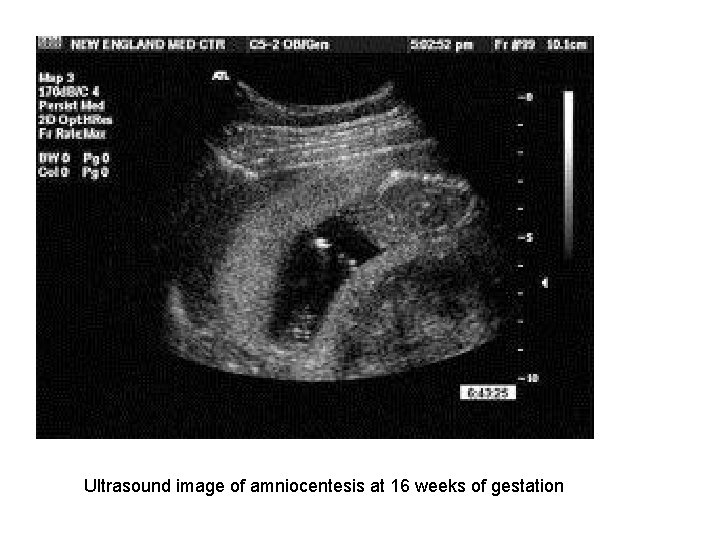
Ultrasound image of amniocentesis at 16 weeks of gestation
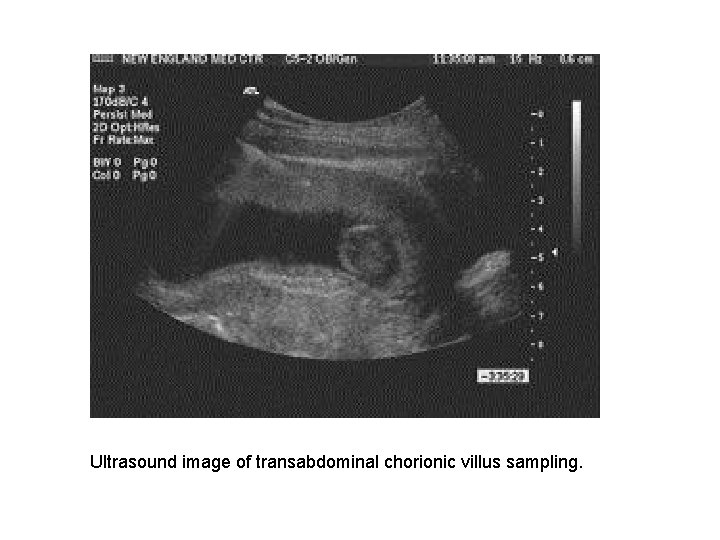
Ultrasound image of transabdominal chorionic villus sampling.
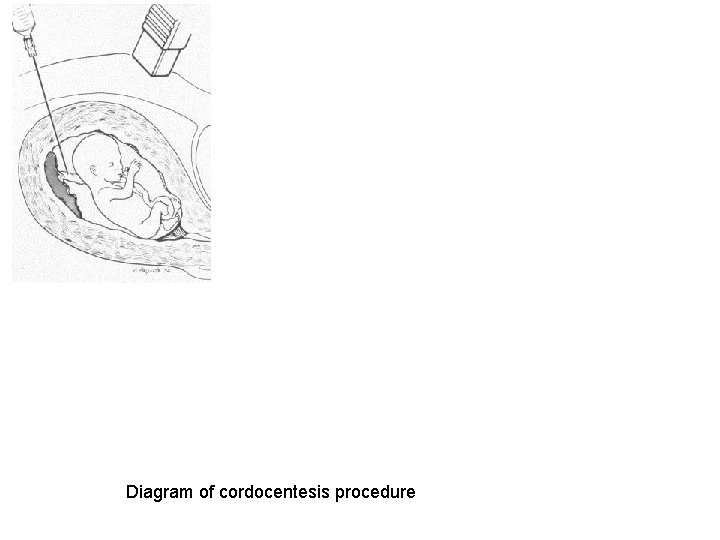
Diagram of cordocentesis procedure
Doppler velocimetry — Doppler assessment of the fetal middle cerebral artery (MCA)
Amniocentesis — Amniocentesis is performed when the critical titer is reached or if there has been a previous seriously affected fetus or infant.
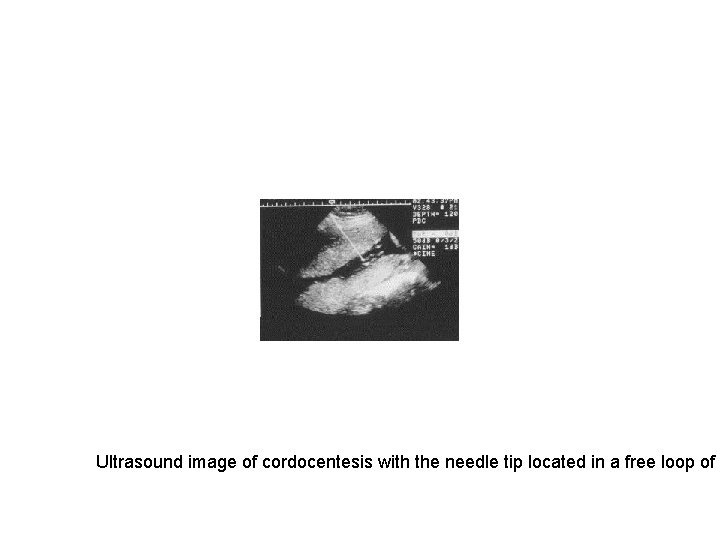
Fetal blood sampling — Ultrasound-directed fetal blood sampling (ie, percutaneous umbilical blood sampling, cordocentesis, funipuncture) allows direct access to the fetal circulation to obtain important laboratory values such as hematocrit, direct Coombs, fetal blood type, reticulocyte count, and total bilirubin
Multiple antibodies Some women develop antibodies to more than one red blood cell antigen.
Ultrasound image of cordocentesis with the needle tip located in a free loop of c
Ultrasound-guided transabdominal fetocentesis
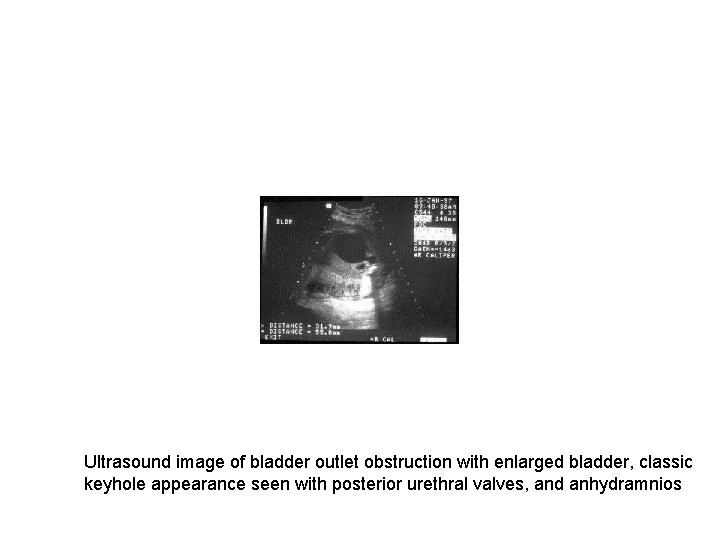
Ultrasound image of bladder outlet obstruction with enlarged bladder, classic keyhole appearance seen with posterior urethral valves, and anhydramnios
Double pig-tailed Rocket catheter and trocar used for vesicoamniotic shunting.