Primary Care Aspects of HIV Ellis Frazier MD
























- Slides: 44
Primary Care Aspects of HIV Ellis Frazier, MD Portsmouth Health Department Portsmouth, OH
Primary Care Aspects of HIV Research suggests that primary care physicians do not routinely perform risk assessments for HIV infection, often missing clinically important risk behaviors and failing to include HIV infection in the differential diagnosis.
Primary Care Aspects of HIV Educate yourself, your staff and the patient HIV is transmitted via sexual contact, blood, and sharing needles HIV is a treatable, chronic disease Know when to call for help
We as Primary care providers should at least Provide universal HIV screening Counsel patients on prevention of HIV transmission Counsel on risk reduction measures Provide basic monitoring of labs and routine healthcare services including health screening, immunizations, and prophylaxis along with other primary care support services that all patients should be entitled to based on age appropriate guidelines of care.
Primary Care Aspects of HIV Stigma fear and ignorance behavior that led to HIV Cultural Background minorities Confidentiality risk of job loss, insurance loss Rapidly changing field – easier to refer/transfer
Remember and promote this ONE message The CDC has called for routine, voluntary HIV screening of all patients aged 13 -64 in all health care settings. The agency issued: “Revised Recommendations for HIV Testing of Adults, Adolescents and Pregnant Women in Health Care Settings" in the Sept. 22, 2006 issue of Morbidity and Mortality Weekly Report.
Do you know how your providers communicate? Do your providers even know each other? Do your providers send letters to each other or fax notes from office visits? Do they send copies of laboratory studies to each other? Do they even know that you are seeing another specialist? Whose responsibility is it to coordinate this? ? Case manager? Patient? Primary Care Provider? Husband? Wife? Significant other?
Conspiracy Beliefs about HIV/AIDS Telephone survey of 400 African-Americans Bogart LM and Thorburn S. JAIDS. 2005; 38(2): 213 -218.
What is the estimated life expectancy of a male diagnosed with HIV in 2009? A) 10 years B) 17 years C) 22 years D) 30 years
Life Expectancy for persons with HIV
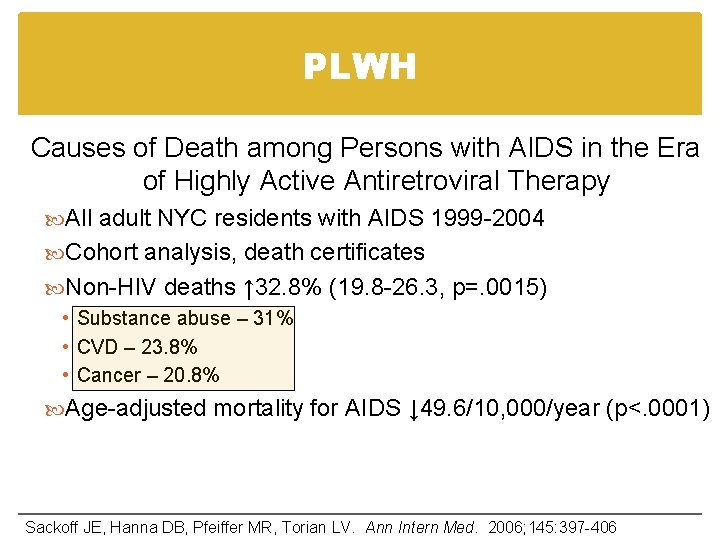
PLWH Causes of Death among Persons with AIDS in the Era of Highly Active Antiretroviral Therapy All adult NYC residents with AIDS 1999 -2004 Cohort analysis, death certificates Non-HIV deaths ↑ 32. 8% (19. 8 -26. 3, p=. 0015) • Substance abuse – 31% • CVD – 23. 8% • Cancer – 20. 8% Age-adjusted mortality for AIDS ↓ 49. 6/10, 000/year (p<. 0001) Sackoff JE, Hanna DB, Pfeiffer MR, Torian LV. Ann Intern Med. 2006; 145: 397 -406
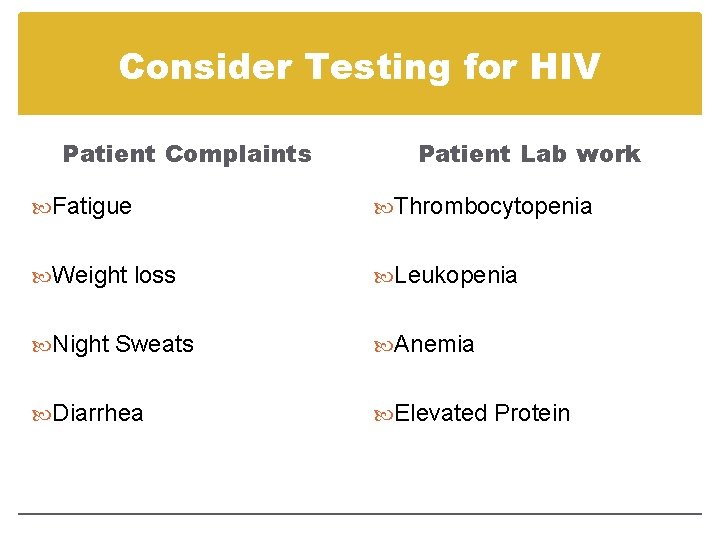
Consider Testing for HIV Patient Complaints Patient Lab work Fatigue Thrombocytopenia Weight loss Leukopenia Night Sweats Anemia Diarrhea Elevated Protein
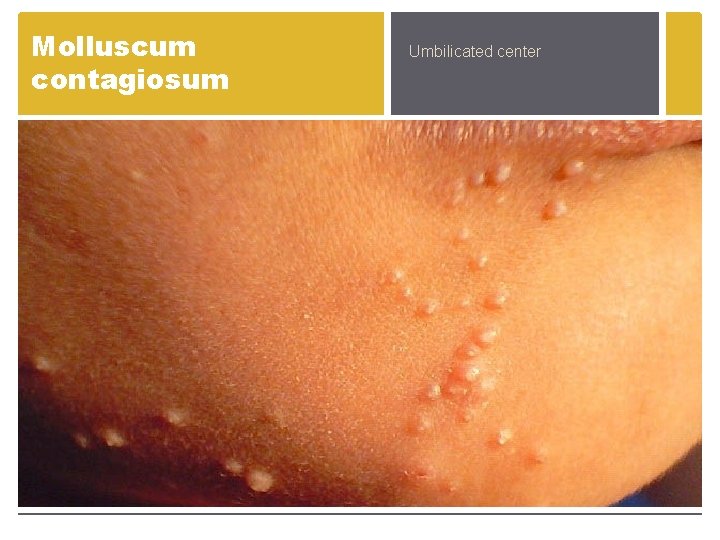
Molluscum contagiosum Umbilicated center
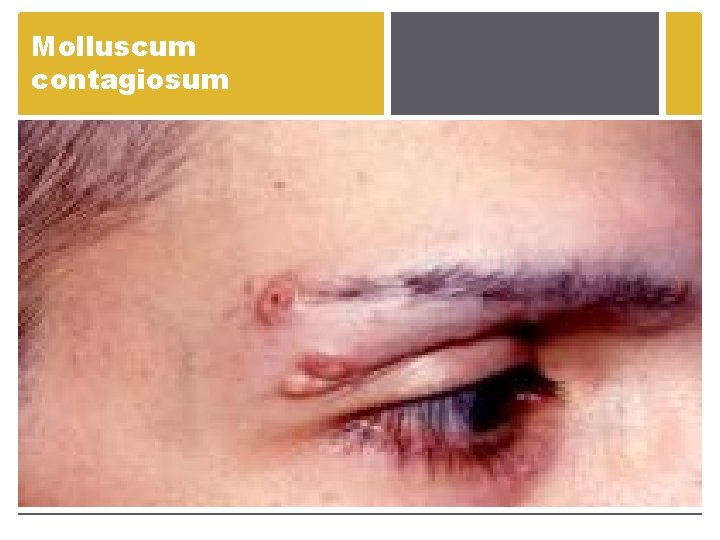
Molluscum contagiosum
Seborrheic Dermatitis
Seborrheic dermatitis
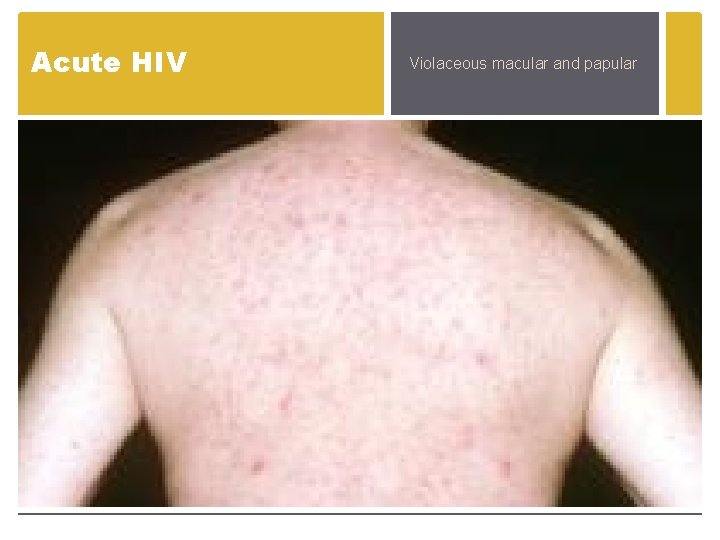
Acute HIV Violaceous macular and papular
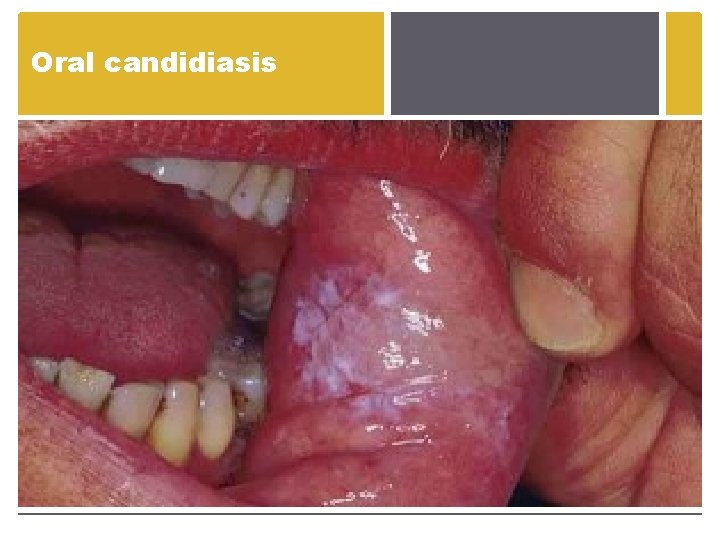
Oral candidiasis
Severe psoriasis
Primary Care Aspects of HIV RPR Testosterone Bone Density? CBC- increased leukopenia, anemia and thrombocytopenia Glucose – increased prevalence UA and calculated Cr. Cl (most studies use CG) TB screen (5 mm or close contact with active case)
Primary Care Aspects of HIV Lipids ( HIV meds and HIV itself assoc. with) Hepatitis Serology – and vaccinate if indicated Pap – q 6 months X 2 then annual (anal pap? ) Renal (kidney function abnl in up to 30%) Cardiac Osteoporosis Cancers Drug drug interactions
Counseling Safer sex practices Substance Use Tobacco use Reproductive Health Psychosocial Assessment Insurance, Contacts, Legal Issues Diet and Exercise HIV Guidelines: New York State Department of Health AIDS Institute, 2009. http: //www. hivguidelines. org/Content. aspx
Other Issues to Follow HIVAN HIV associated nephropathy STD Testing Depression The great mimicker
PLWH and Dyslipidemia Untreated HIV: ↑TG and ↓HDL HAART: ↑TC and ↑TG (♂ > ♀) HDL may increase with NNRTIs Other PI Atazanavir did not change endothelial dysfunction despite improved lipid profile FLP before and 3 -6 months after HAART AHRQ National Guideline Clearinghouse. Infectious Disease Society of America. Mod 5/23/2005. Flammer AJ, Vo NT, et al. Heart. 2009; 95(5): 385 -90.
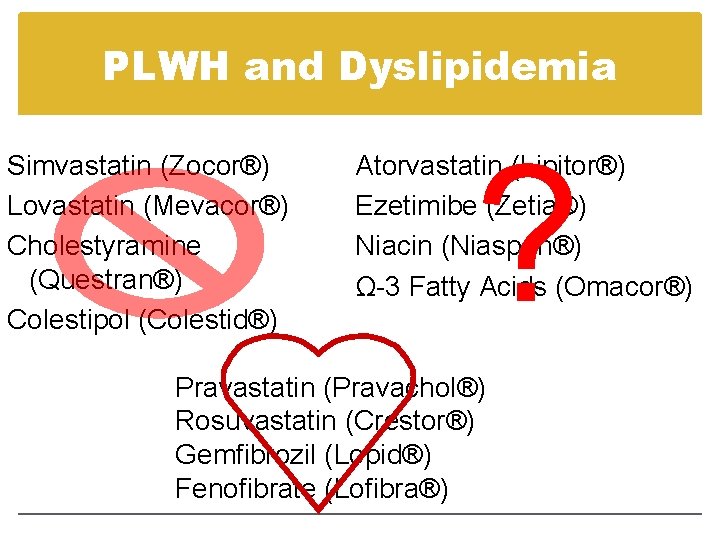
PLWH and Dyslipidemia Other recommendations: Δ PI to nevirapine or abacavir (C-III) ‘Statin for LDL and TG 200 -500 (B-I) Fibrates less optimal (C-I TC/LDL, B-I TG) Avoid niacin and bile-sequestering resins (C-III) Niacin increases risk of glucose intolerance Fish oils may be tried (C-III) Can combine with fibrates if necessary Aberg JA. Lipid Management in Patients who have HIV and are Receiving HIV Therapy. Endocrinol Metab Clin N Am. 2009; 38: 207 -222.
PLWH and Dyslipidemia Simvastatin (Zocor®) Lovastatin (Mevacor®) Cholestyramine (Questran®) Colestipol (Colestid®) ? Atorvastatin (Lipitor®) Ezetimibe (Zetia®) Niacin (Niaspan®) Ω-3 Fatty Acids (Omacor®) Pravastatin (Pravachol®) Rosuvastatin (Crestor®) Gemfibrozil (Lopid®) Fenofibrate (Lofibra®)
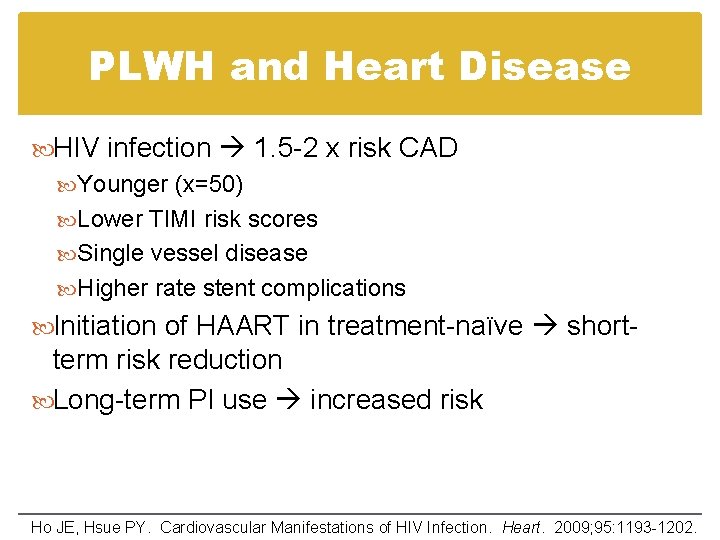
PLWH and Heart Disease HIV infection 1. 5 -2 x risk CAD Younger (x=50) Lower TIMI risk scores Single vessel disease Higher rate stent complications Initiation of HAART in treatment-naïve short- term risk reduction Long-term PI use increased risk Ho JE, Hsue PY. Cardiovascular Manifestations of HIV Infection. Heart. 2009; 95: 1193 -1202.
Cardiovascular Disease “Cigarette smoking is the most important modifiable cardiovascular risk factor among HIV-infected patients. ”
Primary Care for Patients with HIV/AIDS Cardiovascular Disease All PLWH should be evaluated for CAD risk Traditional risk factors • tobacco, HTN, Dyslipidemia, family history Emerging risk factors • weight, HAART (PIs) Treatment Lifestyle modification • smoking cessation Treat diabetes, HTN, Dyslipidemia Low CV-risk HAART
Lipids Total Cholesterol Level Category Less than 200 mg/d. L Desirable level that puts you at lower risk for coronary heart disease. A cholesterol level of 200 mg/d. L or higher raises your risk. 200 to 239 mg/d. L Borderline high 240 mg/d. L and above High blood cholesterol. A person with this level has more than twice the risk of coronary heart disease as someone whose cholesterol is below 200 mg/d HDL Cholesterol Level Category Less than 40 mg/d. L (for men) Less than 50 mg/d. L (for women) Low HDL cholesterol. A major risk factor for heart disease. 60 mg/d. L and above High HDL cholesterol. An HDL of 60 mg/d. L and above is considered protective against heart disease. LDL Cholesterol Level Category Less than 100 mg/d. L Optimal 100 to 129 mg/d. L Near or above optimal 130 to 159 mg/d. L Borderline high 160 to 189 mg/d. L High 190 mg/d. L and above Very high
HIV and Cardiovascular Risk
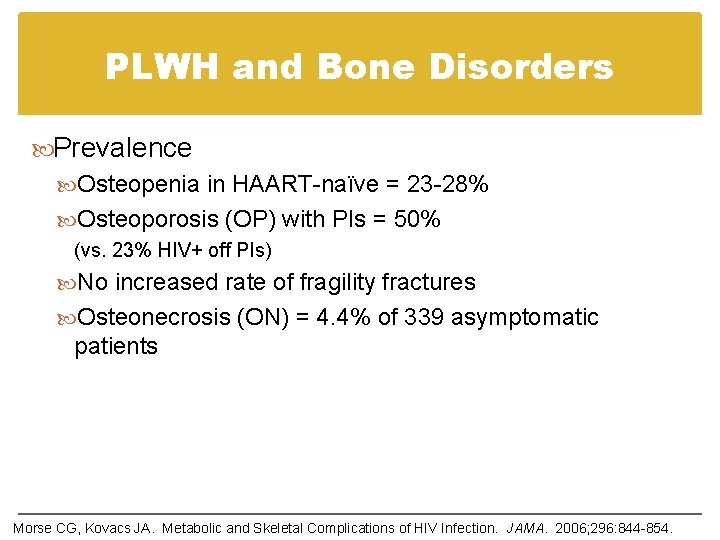
PLWH and Bone Disorders Prevalence Osteopenia in HAART-naïve = 23 -28% Osteoporosis (OP) with PIs = 50% (vs. 23% HIV+ off PIs) No increased rate of fragility fractures Osteonecrosis (ON) = 4. 4% of 339 asymptomatic patients Morse CG, Kovacs JA. Metabolic and Skeletal Complications of HIV Infection. JAMA. 2006; 296: 844 -854.
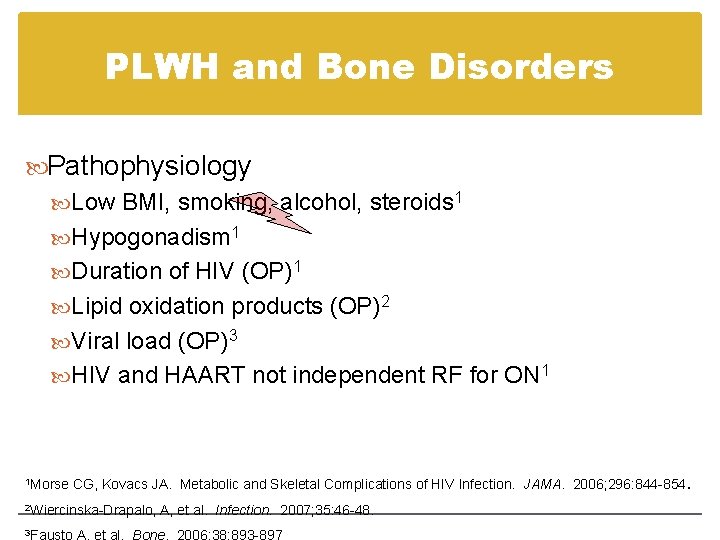
PLWH and Bone Disorders Pathophysiology Low BMI, smoking, alcohol, steroids 1 Hypogonadism 1 Duration of HIV (OP)1 Lipid oxidation products (OP)2 Viral load (OP)3 HIV and HAART not independent RF for ON 1 1 Morse CG, Kovacs JA. Metabolic and Skeletal Complications of HIV Infection. JAMA. 2006; 296: 844 -854. 2 Wiercinska-Drapalo, 3 A, et al. Infection. 2007; 35: 46 -48.
PLWH and Diabetes Insulin resistance and impaired glucose tolerance in up to 50% of PLWH on PIs 1 Men – >4 x risk compared to seronegative men 2 Diagnosis Fasting glucose >126, random >200 Insulin levels and GTT* not currently recommended 1. Grinspoon S, Carr A. Cardiovascular Risk and Body-Fat Abnormalities in HIV-Infected Adults. NEJM. 2005; 352; 48 -62. 2. Brown TT, Cole SR, et al. Antiretroviral Therapy and Prevalence and Incidence of Diabetes Mellitus in the Multicenter AIDS Cohort Study. Arch Intern Med. 2005; 165: 1179 -84.
Blood Sugar Recommendations The American Diabetes Association normal blood sugar for healthy people who do not have diabetes: fasting/before eating < 100 mg/dl bedtime 120 mg/dl A 1 c blood sugar test (3 month blood sugar indicator) <6% The American Diabetes Association recommends the following blood sugar goals for those with diabetes: before eating (pre-prandial plasma glucose) 90 -130 mg/dl 1 -2 hours after the beginning of eating (peak postprandial plasma glucose) <180 mg/dl A 1 c blood sugar test (3 month blood sugar indicator) <7% What do other organizations recommend for blood sugar goals? The American Association of Clinical Endocrinologists (endocrinologists are medical doctors specializing in disorders including diabetes) recommends the following blood sugar goals for those with diabetes: before eating (pre-prandial) 110 mg/dl 2 hours after eating (post-prandial) 140 mg/dl A 1 c blood sugar test (3 month blood sugar indicator) <6. 5%
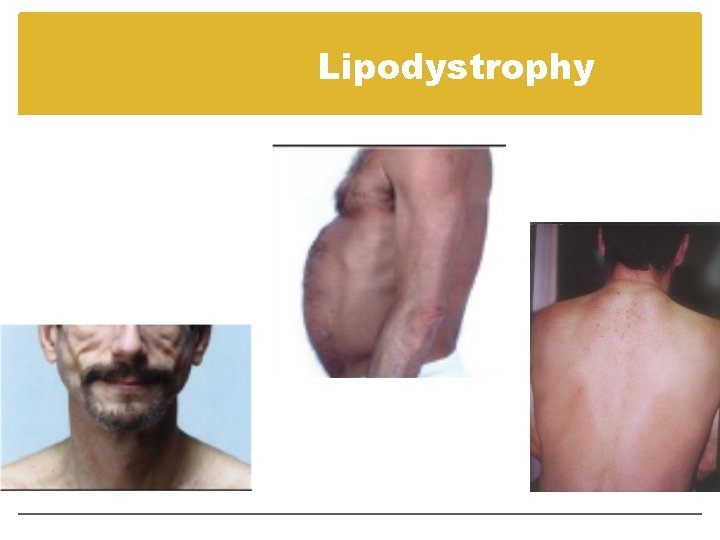
PLWH and Lipodystrophy Subcutaneous lipoatrophy (♂ > ♀) • Face • Extremities • Buttocks Accumulation of central fat (♀ > ♂) • Visceral fat • Dorsocervical fat pad, breasts, lipomatosis Lipodystrophy Syndrome with insulin resistance and Dyslipidemia Morse CG, Kovacs JA. Metabolic and Skeletal Complications of HIV Infection. JAMA. 2006; 296: 844 -854.
Lipodystrophy
PLWH and Lipodystrophy Prevalence 20 -84% 20 -50% will develop at least 1 sign of lipodystrophy within 2 years of HAART Pathophysiology Mitochondrial toxicity impaired ATP NRTIs (stavudine > AZT >> ABC/TDF) PIs (except Atazanavir) Morse CG, Kovacs JA. Metabolic and Skeletal Complications of HIV Infection. JAMA. 2006; 296: 844 -854.
Resources www. aahiv. org www. aidsinfonet. org www. aidsinfo. nih. gov www. iasociety. org www. nrharural. org www. aids-ed. org www. aids. gov www. aidsetc. org www. aidsmeds. com www. thebody. com
The Reality of the HIV Epidemic With 40, 000 (More recently the number is up to 56, 000) people becoming infected each year and with HIV+ patients living longer, there is definitely a need for more physicians to assume the primary care and specialty care of these patients. About One half of the HIV sub specialists in the US have been trained in family or internal medicine. HIV/AIDS is now considered “A chronic, manageable disease”, perhaps not unlike diabetes, hypertension, or hyperlipidemia. Jeffery Kirschner, D. O. Medical director of the Comprehensive Care Clinic at Lancaster General Hospital, Lancaster, Pennsylvania—Editorial “Who should care for Patients with HIV/AIDS
We as Primary care providers should at least Provide universal HIV screening Counsel patients on prevention of HIV transmission Counsel on risk reduction measures Provide basic monitoring of labs and routine healthcare services including health screening, immunizations, and prophylaxis along with other primary care support services that all patients should be entitled to based on age appropriate guidelines of care.
As Primary Care Physicians we know how to be efficient!!!!