Colorectal Cancer Screening 2016 Update Howard Zhang MD






























- Slides: 52
Colorectal Cancer Screening – 2016 Update Howard Zhang, MD Chief of Gastroenterology and Hepatology Summa Health System
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
Why CRC Screening l Colorectal CA (CRC) impact in U. S. n n l 2 nd leading cause of death from cancer 3 rd most common cancer diagnosed Most preventable cancers n n Adenomatous colon polyp removal prevents CRC (National Polyp Study) Colonoscopy reduces CRC incidence and mortality by 61%* *Pan, J et al, Am J Gastroenterol 2016; 111: 355– 365;
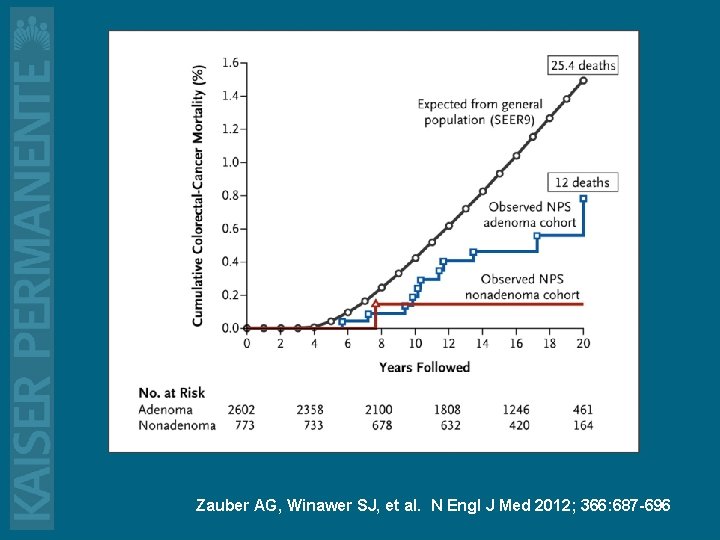
Why CRC Screening l Colonoscopic removal of adenoma prevents death from colorectal cancer n n 2602 pts from NPS: had adenomatous polyps removed; followed 15. 8 yrs 12 died of CRC 25. 4 expected CRC death (SEER) 53% reduction in CRC mortality after adenomatous polypectomy Zauber AG, Winawer SJ, et al. N Engl J Med 2012; 366: 687 -696
Zauber AG, Winawer SJ, et al. N Engl J Med 2012; 366: 687 -696
Colonoscopy Screening: Evidence, Recommendations, and Public Support l l l <1992: no controlled studies support any CRC screening 1992: sigmoidoscopy: case-control study (Selby, NEJM) 1993 -6: FOBT: 3 RCTs (Minnesota, NEJM; UK, Den. , Lancet) 1996: USPSTF recommends CRC screening, though colonoscopy is not an option 1997: GI Consortium recommends any of several tests, and colonoscopy is ‘an option’ (Gastroenterology 1997) 2000: ‘Colon cancer awareness month’ (March), celebrity endorsement, NEJM editorial (‘Going the distance. . ’)
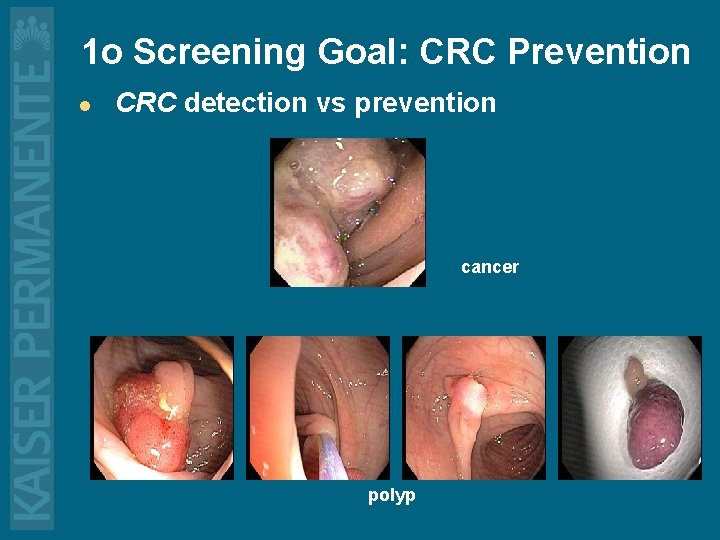
1 o Screening Goal: CRC Prevention l CRC detection vs prevention cancer polyp
1 o Screening Goal: CRC Prevention l American Cancer Society, US Multi. Society Task Force on CRC, and American College of Radiology n n Endorse CRC prevention as 1 o screening goal but, clinician should offer screening choice effective u u either at both early cancer detection and prevention through detection and removal of polyps or primarily at early cancer detection. Levin B, et al. CA cancer J Clin 2008; 58: 130 -160
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
Levin B, et al. CA cancer J Clin 2008; 58: 130 -160
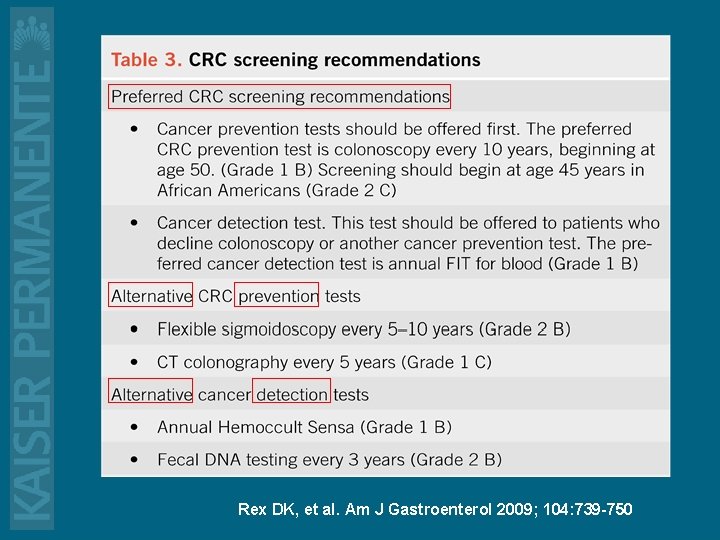
Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
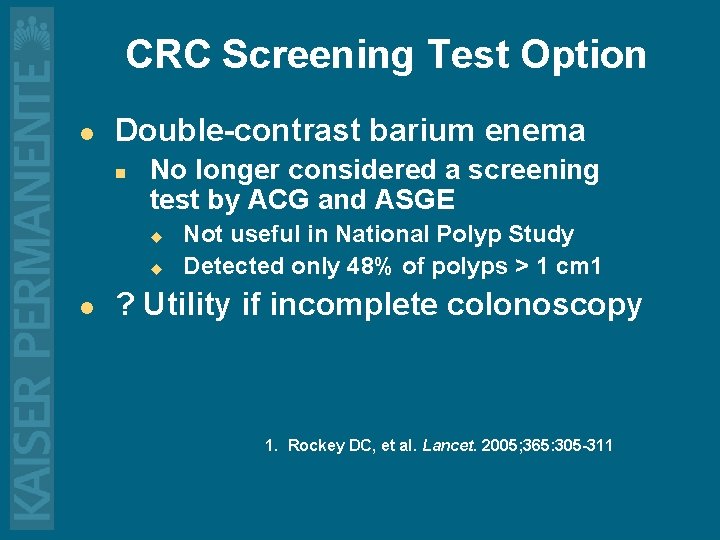
CRC Screening Test Option l Double-contrast barium enema n No longer considered a screening test by ACG and ASGE u u l Not useful in National Polyp Study Detected only 48% of polyps > 1 cm 1 ? Utility if incomplete colonoscopy 1. Rockey DC, et al. Lancet. 2005; 365: 305 -311
Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
ACG CRC Screening Recommendations 2009 l l Colonoscopy - preferred CRC prevention test If pt declines colonoscopy or other prevention test – annual FIT If pt declines colonoscopy, consider alternative prevention tests n Flex sig n CT colonography Other alternative detection tests include n Fecal DNA n Hemoccult Sensa
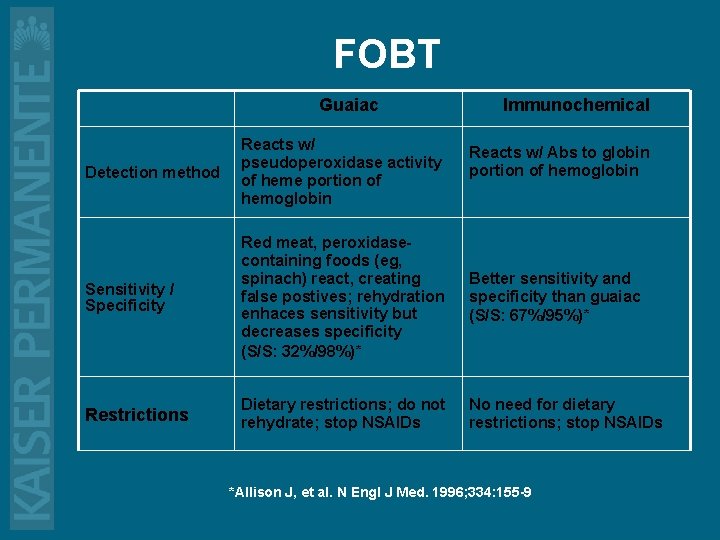
FOBT Guaiac Immunochemical Detection method Reacts w/ pseudoperoxidase activity of heme portion of hemoglobin Sensitivity / Specificity Red meat, peroxidasecontaining foods (eg, spinach) react, creating false postives; rehydration enhaces sensitivity but decreases specificity (S/S: 32%/98%)* Better sensitivity and specificity than guaiac (S/S: 67%/95%)* Restrictions Dietary restrictions; do not rehydrate; stop NSAIDs No need for dietary restrictions; stop NSAIDs Reacts w/ Abs to globin portion of hemoglobin *Allison J, et al. N Engl J Med. 1996; 334: 155 -9
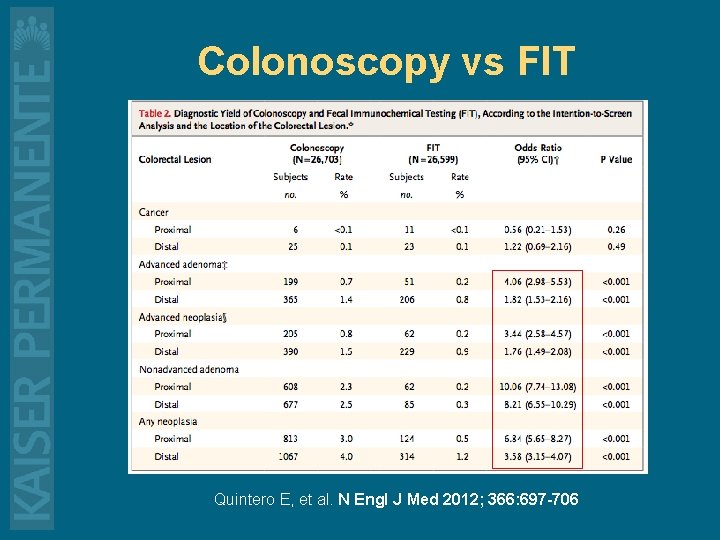
Colonoscopy vs FIT Quintero E, et al. N Engl J Med 2012; 366: 697 -706
Colonoscopy vs FIT l Conclusions n n Pt more likely to participate in FIT screening than colonoscopy CRC detection similar in two groups More adenomas identified by colonoscopy FIT seems to detect mainly left-sided lesions FIT - CRC detection, not prevention test Quintero E, et al. N Engl J Med 2012; 366: 697 -706
Flex Sigmoidoscopy l l Associated w/ decrease in CRC incidence in both distal (21%) and proximal colon (14%); and 50% mortality (distal colon only)1 Associated w/ 40% decrease in CRC incidence in distal 2, not proximal colon l Women - more right-sided colon cancer? 3 l Sigmoidoscopy q 5 y + yrly FOBT increased detection rates of CRC from 70% to 76% (case-control trial)1 n 1. 2. 3. 4. Schoen R. E. , Pinsky P. F. , et al. N Engl J Med 2012; 366: 2345 -2357 Nishihara R. , Wu K. , Lochhead P. , et al. N Engl J Med 2013; 369: 1095 -1105 Schoenfeld P, et al. N Engl J Med 2005; 352: 2061 -8 Lieberman DA, et al. N Engl J Med. 2000; 343: 162 -8
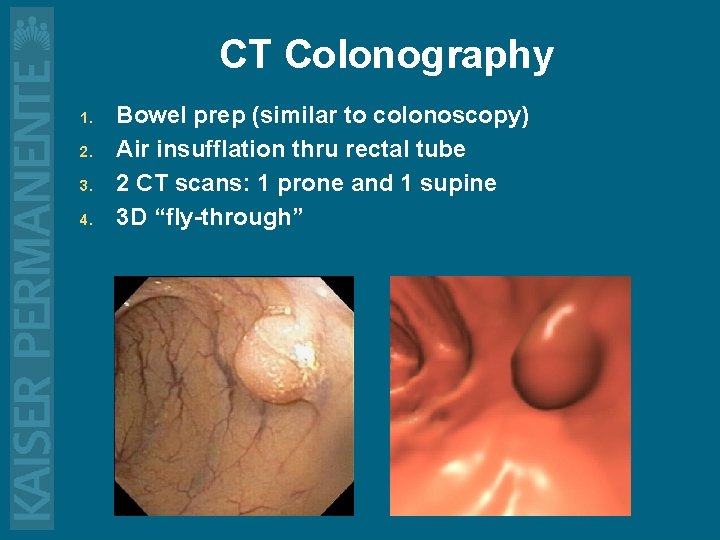
CT Colonography 1. 2. 3. 4. Bowel prep (similar to colonoscopy) Air insufflation thru rectal tube 2 CT scans: 1 prone and 1 supine 3 D “fly-through”
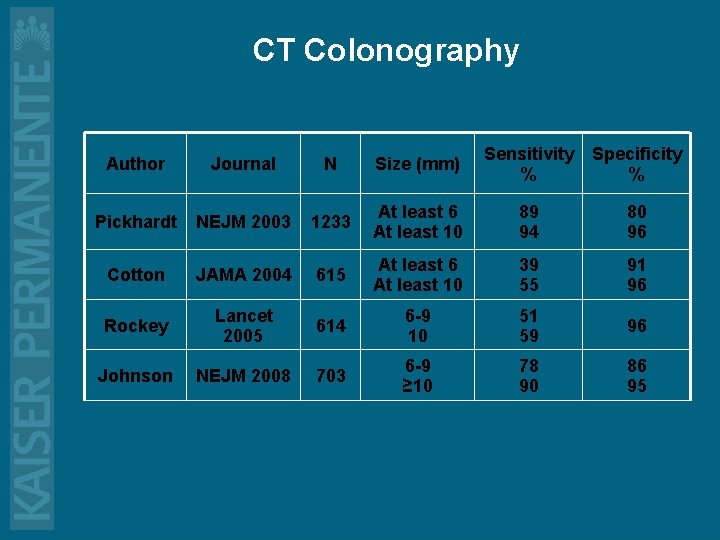
CT Colonography Author Journal N Pickhardt NEJM 2003 1233 Cotton JAMA 2004 615 Rockey Johnson Lancet 2005 NEJM 2008 614 703 Sensitivity Specificity % % 89 80 94 96 least 6 At least 10 39 91 55 96 6 -9 51 10 59 6 -9 78 86 ≥ 10 95 Size (mm) At least 6 At least 10 At 96
CT Colonography l CT colonography limitations n n n n Unable to remove detected polyp Polyps ≤ 6 mm & flat polyps not detected Bowel prep Inter-observer variability Radiation dosage 7 - 13 m. Sv, equivalent of 8 CXR Perforation risk 0. 05 -0. 06% Cost associated with incidental findings Q 5 yr cumulative radiation dosage
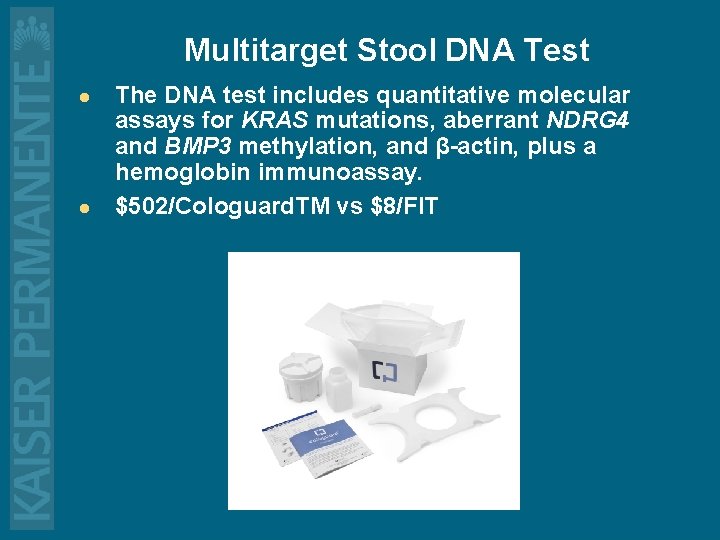
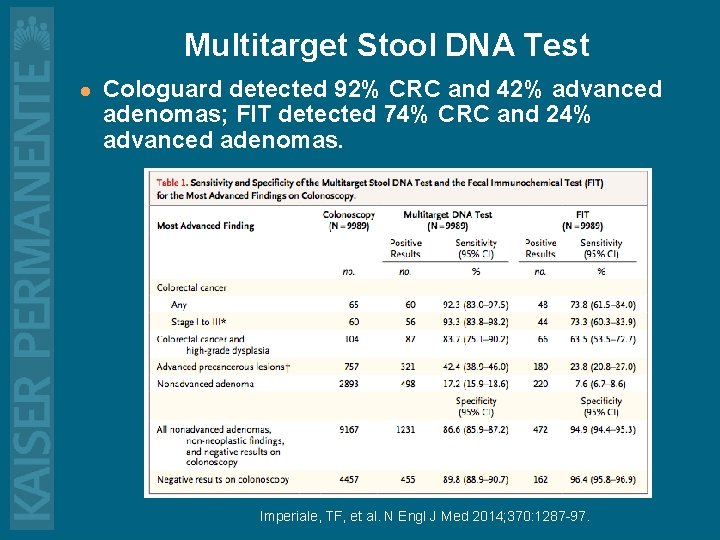
Multitarget Stool DNA Test l l The DNA test includes quantitative molecular assays for KRAS mutations, aberrant NDRG 4 and BMP 3 methylation, and β-actin, plus a hemoglobin immunoassay. $502/Cologuard. TM vs $8/FIT
Multitarget Stool DNA Test l Cologuard detected 92% CRC and 42% advanced adenomas; FIT detected 74% CRC and 24% advanced adenomas. Imperiale, TF, et al. N Engl J Med 2014; 370: 1287 -97.
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
ACG CRC Screening Recommendations 2009 l African American starts screening at age 45 n n l Higher incidence and death rate for CRC Higher proportion of CRCs under age 50 compared with Caucasians (10. 6% vs 5. 5%) More right-sided lesions Unclear cause: genetic, dietary, lifestyle, socioeconomic, or preventive issues ? Insurance coverage for early screening Agrawal S, et al. Am J Gastroenterol 2005; 100 (3): 515 -523
ACG CRC Screening Recommendations 2009 Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
ACG CRC Screening Recommendations 2009 l Other high risk groups: FAP, AFAP, HNPCC, MAP (MUTYH-associated polyposis) etc n n Reference below Call GI or Oncology Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
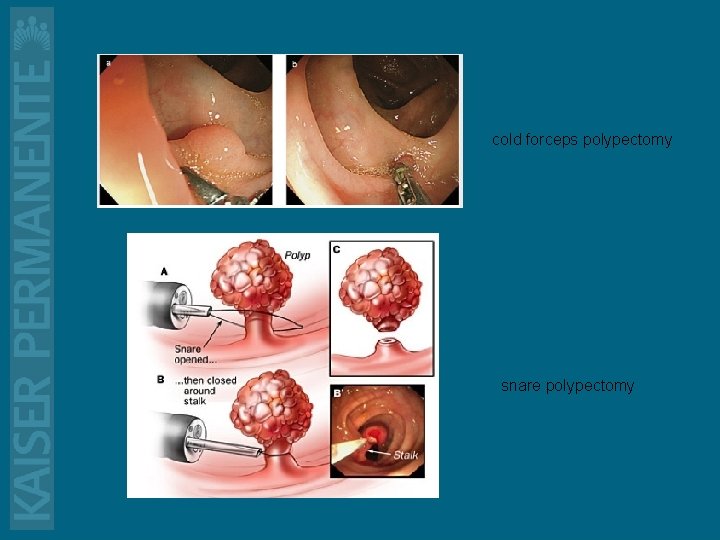
cold forceps polypectomy snare polypectomy
Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
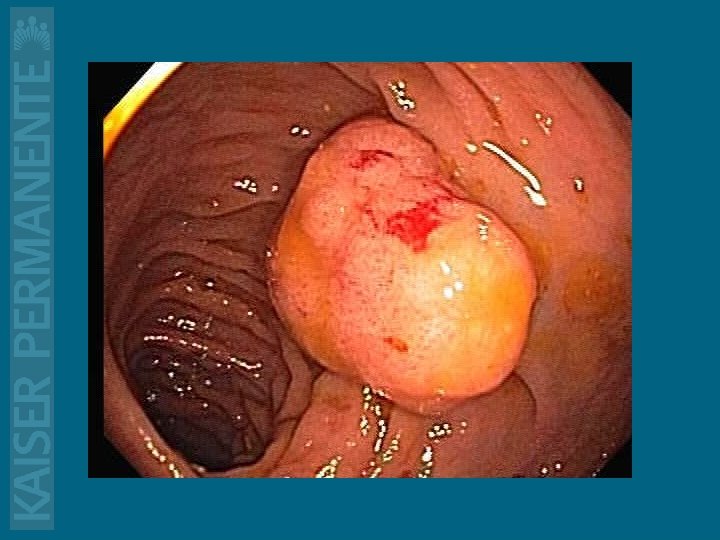
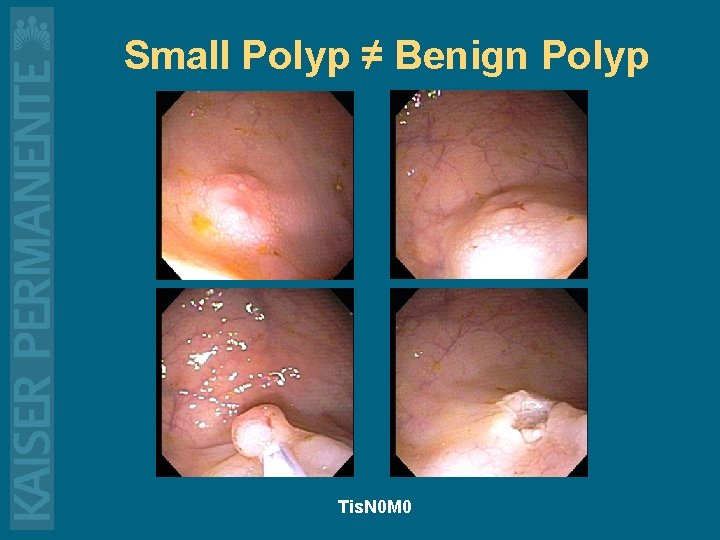
Small Polyp ≠ Benign Polyp Tis. N 0 M 0
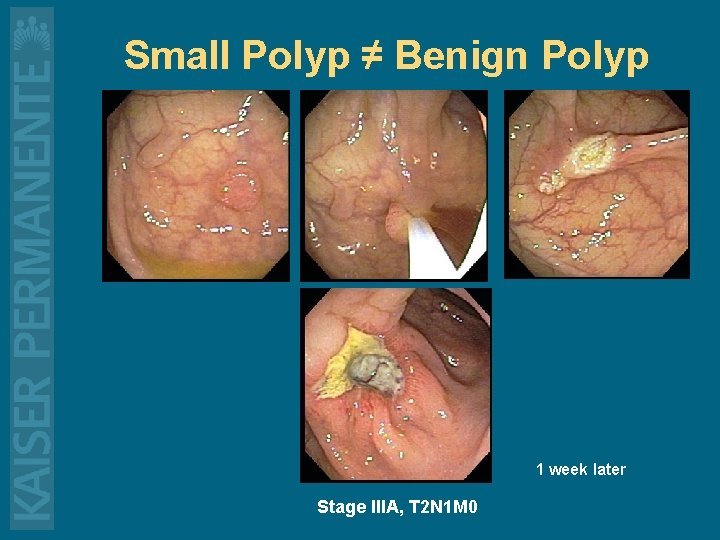
Small Polyp ≠ Benign Polyp 1 week later Stage IIIA, T 2 N 1 M 0
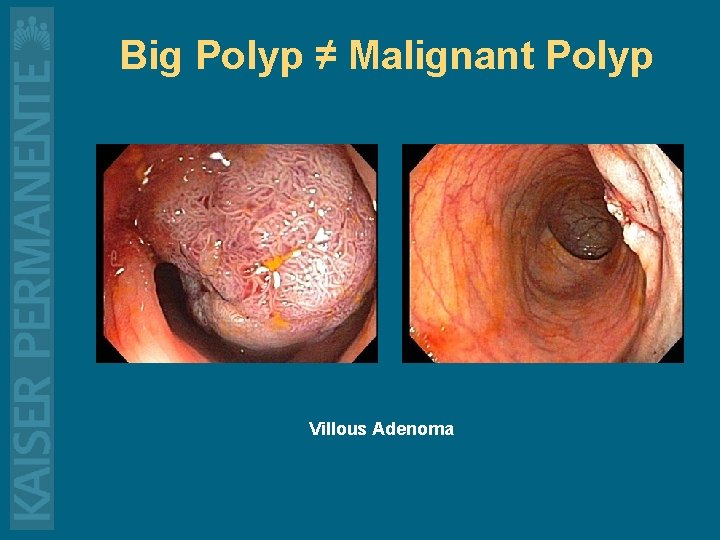
Big Polyp ≠ Malignant Polyp Villous Adenoma
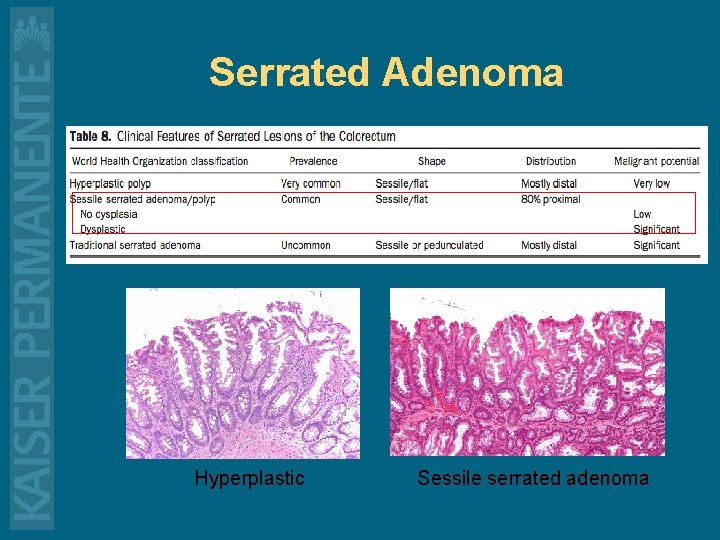
Common Colonic Polyp Type l Adenomatous - CRC precursor n n n l l l Tubular; Villous; High grade dysplasia (HGD/Ca-in-situ) LRA: 1 -2 adenomas < 10 mm HRA: 3 more adenomas, tubular ≥ 10 mm, villous adenoma, or HGD Hyperplastic - benign (mostly) Inflammatory - benign Serrated adenoma
Serrated Adenoma Hyperplastic Sessile serrated adenoma
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
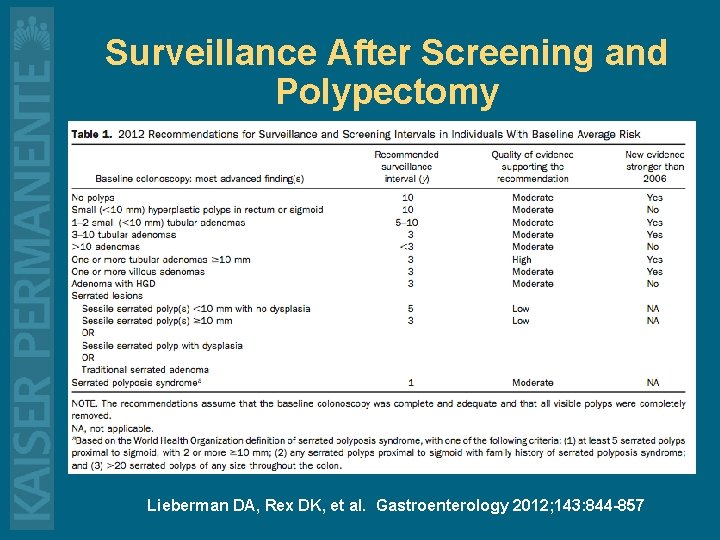
Surveillance After Screening and Polypectomy Lieberman DA, Rex DK, et al. Gastroenterology 2012; 143: 844 -857
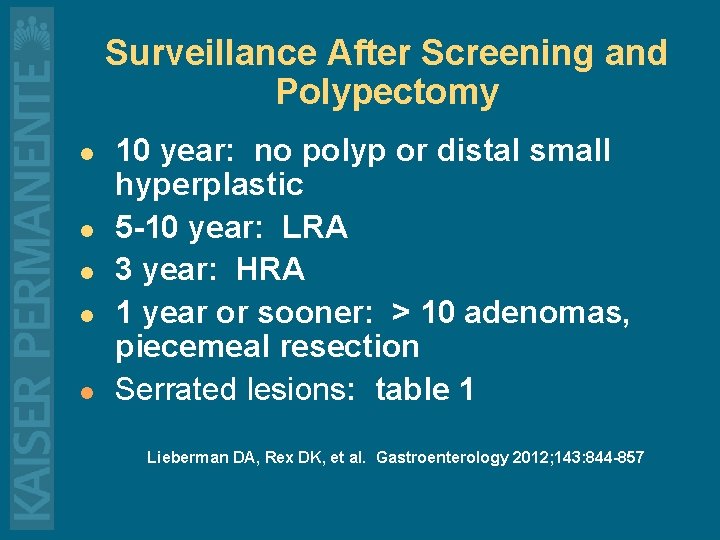
Surveillance After Screening and Polypectomy l l l 10 year: no polyp or distal small hyperplastic 5 -10 year: LRA 3 year: HRA 1 year or sooner: > 10 adenomas, piecemeal resection Serrated lesions: table 1 Lieberman DA, Rex DK, et al. Gastroenterology 2012; 143: 844 -857
Usefulness of FIT in Postpolypectomy Surveillance? l Interval positive FIT before scheduled surveillance colonoscopy identified advanced lesions earlier. n n l CRC dx’ed 25 mo earlier Advanced adenoma dx’ed 24 mo earlier. Editorial critique – n n failure to evaluate baseline findings or examination quality hard to establish relationship of interval CRC Lane JM, Chow E. et al. Gastroenterology 2010; 139: 1918 -1926
Usefulness of FIT in Postpolypectomy Surveillance? l USMSTF: Interval FIT NOT recommended within the first 5 years after colonoscopy. Lieberman DA, Rex DK, et al. Gastroenterology 2012; 143: 844 -857
Posttreatment Surveillance for Resected CRC Colonoscopy in 1 yr, then 3 yr, then 5 yr
Outline l l l CRC screening saves lives Choosing a test Getting screened earlier for some Getting a colonoscopy Looking forward to next colonoscopy Gray area in real world practice
Dilemma in Clinical Practice l How reliable is patient history? n n l FHx of colon cancer? Personal history of colon polyps? Why did outside GI recommend sooner repeat colonoscopy? – esp when records are not available n n n Polyp type & number? Prep quality? Incomplete exam or polypectomy? …
Dilemma in Clinical Practice l Should environmental factors be factored in CRC screening? n Risks for CRC development u u u u n Tobacco Red meat and high fat diet Alcohol High BMI Lack of physical activity DM Menopause Aspirin 81 mg qd reduces 20% new adenomatous polyps in pt w/ prior adenomas 1, 2 1. 2. Chan, et al. JAMA 2009; 302: 649 -659 Liao, et al. N Engl J Med 2012; 367: 1596 -1606
Dilemma in Clinical Practice l When to stop screening or surveillance? n 80 yo healthy WF with 2 small LRA removed 5 years ago a. b. Colonoscopy now No need to repeat colonoscopy
When to Stop Screening or Surveillance? l USPSTF recommends n n l individualized decision making from age 75 -85 no further screening after age 85 ACS recommends n 10 year life expectancy needed to benefit from screening
When to Stop Screening or Surveillance? l American Geriatric Society recommends n n n individualized decision making for older adults; pt input emphasized pt w/ short life expectancy should focus on conditions whose Tx has more immediate benefit burden associated w/ screening in the older person should be considered * American Geriatric Society Ethics Committee. Health screening decisions for older adults: AGS position paper. J Am Geriatr Soc. 2003 Feb; 51(2): 270 -1
Summary l CRC screening saves lives n n l Choosing a test n n l Adenoma removal led to 50 -60% CRC mortality reduction 1 o CRC screening goal – CA prevention Gold standard – colonoscopy FIT crucial in getting more screened Getting screened earlier for some n Update on risk stratification Rex DK, et al. Am J Gastroenterol 2009; 104: 739 -750
Summary l Getting a colonoscopy n l Good result depending on good bowel prep and thorough test Looking forward to next colonoscopy n Update on surveillance guideline Lieberman DA, Rex DK, et al. Gastroenterology 2012; 143: 844 -857 l Gray area in real world practice n Clinical judgment tops guideline