ANTEPARTUM HEMORRHAGE RAGHAD ALFARAJAT DEFINITION ANTEPARTUM HEMORRHAGE TYPICALLY




















- Slides: 26
ANTEPARTUM HEMORRHAGE RAGHAD ALFARAJAT
DEFINITION ANTEPARTUM HEMORRHAGE TYPICALLY REFERS TO VAGINAL BLEEDING AFTER 20 WEEKS OF GESTATION THAT IS UNRELATED TO LABOR AND DELIVERY. IT IS ASSOCIATED WITH SIGNIFICANT MATERNAL AND FETAL MORBIDITY AND MORTALITY.
• Common • Placenta previa (20 percent) • Abruptio placentae (30 percent) CAUSES OF ANTEPARTUM BLEEDING • Uncommon • Uterine rupture • Fetal (chorionic) vessel rupture • Cervical or vaginal lacerations • Cervical or vaginal lesions, including cancer • Congenital bleeding disorder • Unknown (by exclusion of the above)
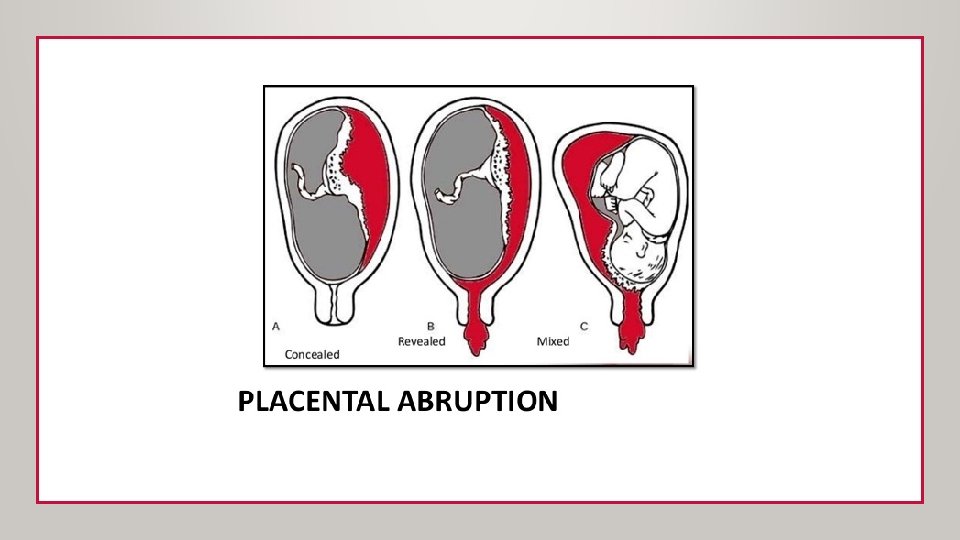
PLACENTA ABRUPTION • The partial or complete separation of the placenta from the uterus prior to delivery. Subsequent hemorrhage occurs from both maternal and fetal vessels. • Epidemiology • Incidence: ∼ 0. 2– 1% of pregnancies. • Occurs most often in the third trimester. • The recurrence rate in subsequent pregnancies is 3– 15%.
Etiology • Predisposing factors • Vascular changes • Hypertension (most common cause) • Preeclampsia/eclampsia • (Abdominal) trauma (up to 10% of cases): car accidents, falls, iatrogenic (e. g. , post-amniocentesis) • Sudden decrease in intrauterine pressure (After delivery of the first child in multiple pregnancy or in premature rupture of the membrane) • Previous abruption, chorioamnionitis, prolonged rupture of membranes, short umbilical cord • Maternal age: < 20 years and > 35 years • Alcohol and cigarette consumption, cocaine use • Clinical picture • Continuous, dark, vaginal bleeding (revealed abruptio placentae) • In ∼ 20% of cases, the hemorrhage is mainly retroplacental; vaginal bleeding does not occur (concealed abruptio placentae) • Abdominal pain or back pain • , uterine tenderness • Hypertonic contractions (rigid uterus), premature labor • Fetal distress (60% of cases) • Possible diminished or absent fetal movement • Decelerations seen on fetal heart monitor • Vaginal exam contraindicated: may worsen bleeding
• * RAPID DIAGNOSIS AND IMMEDIATE TREATMENT ARE VITAL FOR THE SURVIVAL OF BOTH MOTHER AND CHILD! • • Diagnostics • Placental abruption is a clinical diagnosis. Ultrasound (transabdominal, transvaginal): only 25% sensitivity! • Presentation of the placental position and a possible retroplacental hematoma • Monitoring vital signs of the fetus (heartbeat, fetal movement) • To rule out placenta previa in unclear cases Fetal heart rate monitoring Laboratory tests: CBC, coagulation factors • Treatment • General approach • Hemodynamic control: monitor vital signs, maintain airways, volume resuscitation, type and crossmatch blood • Correct coagulopathy if necessary • Rh. D prophylaxis in Rh. D negative mothers. •
Specific approach according to severity • Normal fetal findings and a hemodynamically stable mother • Observation, bed rest, regular control • Up to the 34 th week of pregnancy • Fetal lung maturity induction with corticosteroids (e. g. , betamethasone) • If necessary, tocolysis (e. g. , nifedipine, β 2 -adrenergic agonist) • Aim for a normal delivery • 34 th to 36 th week • Active uterine contractions present: vaginal delivery • No contractions + no signs of fetal distress + bleeding has stopped: expectant management and observation • All pregnancies are delivered if acute abruption occurs after 36 th weeks. • In acute symptoms and a live fetus • Emergency cesarean section independent of gestational age unless vaginal delivery is impending • In acute symptoms and intrauterine fetal death • Induction of vaginal delivery through pharmacologic uterine contraction inducers and opening of the amniotic sac • An emergency cesarean section must be performed if there is a maternal risk due to severe bleeding or slow progression of the birthing process, even in cases of intrauterine fetal death.
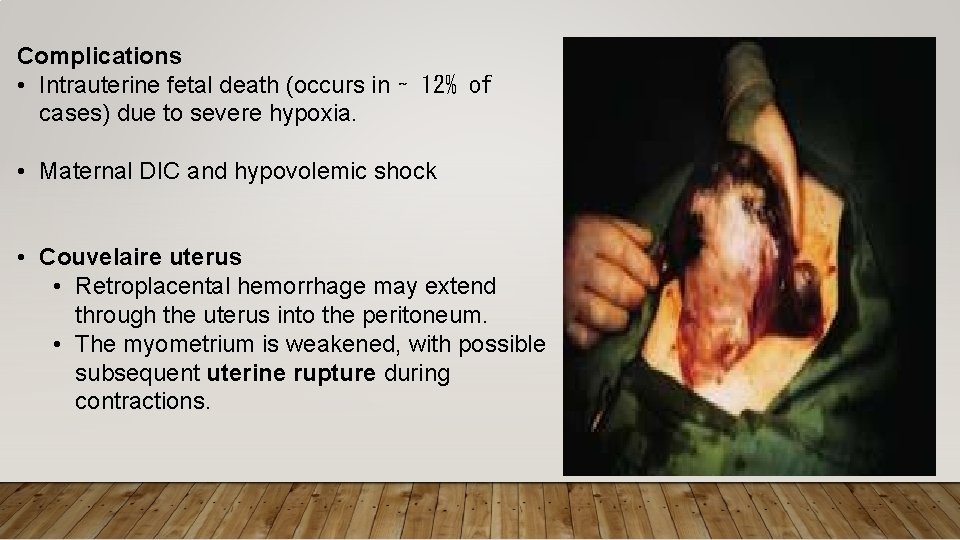
Complications • Intrauterine fetal death (occurs in ∼ 12% of cases) due to severe hypoxia. • Maternal DIC and hypovolemic shock • Couvelaire uterus • Retroplacental hemorrhage may extend through the uterus into the peritoneum. • The myometrium is weakened, with possible subsequent uterine rupture during contractions.
• Definition PLACENTA PREVIA • Presence of the placenta in lower uterine segment, which might lead to partial or full obstruction of the neck of the uterus with high risk of hemorrhage (rupture of placental vessels) and birth complications. • Epidemiology • ∼ 0. 3– 0. 5% of all pregnancies
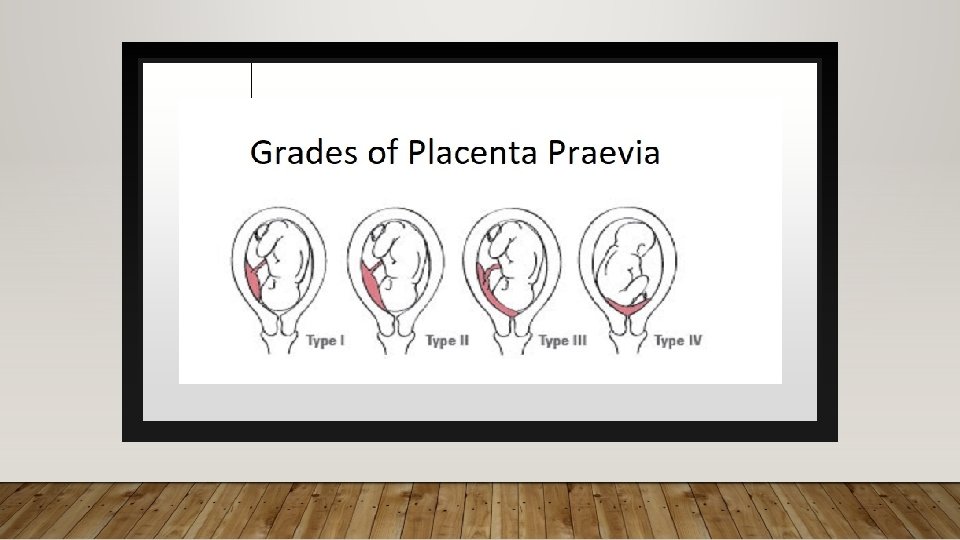
• Etiology • Risk factors • Maternal age > 35 years, multiparity, short intervals between pregnancies • Previous curettage or cesarean section PLACENTA PREVIA • Previous placenta previa, previous/recurrent abortion • Classification • Placenta previa is classified based on how much of the cervical orifice is covered by the placenta. • Low-lying placenta: lower edge of the placenta lies less than 2 cm from the internal cervical os • Marginal previa: placenta reaches the internal cervical os • Partial previa: placenta partially covers the internal cervical os • Complete previa (total previa): placenta completely covers the internal cervical os.
PLACENTA PREVIA • Clinical features • Sudden, painless, bright red vaginal bleeding • Usually occurs during the 3 rd trimester (before rupture of the membranes), stops spontaneously after 1– 2 hours, and recurs during birth • Often causes preterm delivery (∼ 45% of cases) • Soft, nontender uterus • Usually no fetal distress • Diagnostics • Transvaginal ultrasound to assess the position of the placenta (Transvaginal ultrasound is the most sensitive imaging modality. Transabdominal ultrasound can be performed in conjunction with transvaginal ultrasound. ) • Digital vaginal examinations are contraindicated in cases of hemorrhage of unknown cause!
• Treatment • Approach • Gestational age < 37 weeks PLACENTA PREVIA V • No active bleeding AND no evidence of fetal distress: expectant management • Severe, active bleeding OR evidence of fetal distress: stabilization and emergency cesarian section • Gestational age > 37 weeks: immediate delivery
• Expectant management • Hospitalization and observation for 48 hours • If gestational age is < 34 weeks: fetal lung maturity induction with corticosteroids (e. g. , betamethasone) • If gestational age is between 34 and 37 weeks and delivery is likely within 7 days: fetal lung maturity induction with corticosteroids PLACENTA PREVIA • If mild uterine contractions are present: tocolysis with magnesium sulfate may be performed (especially if the fetus is extremely premature) • Route of delivery • Lower segment cesarean section is almost always preferred; ideally scheduled at 36– 37 weeks gestation • Induction of labor and/or vaginal delivery may be performed in the operating room if the mother is hemodynamically stable, fetal cardiac status is reassuring, and the placenta lies > 2 cm away from the internal os on ultrasonography
VAGINAL DELIVERY SHOULD NEVER BE ATTEMPTED OUTSIDE THE OPERATING ROOM IN A PATIENT WITH PLACENTA PREVIA
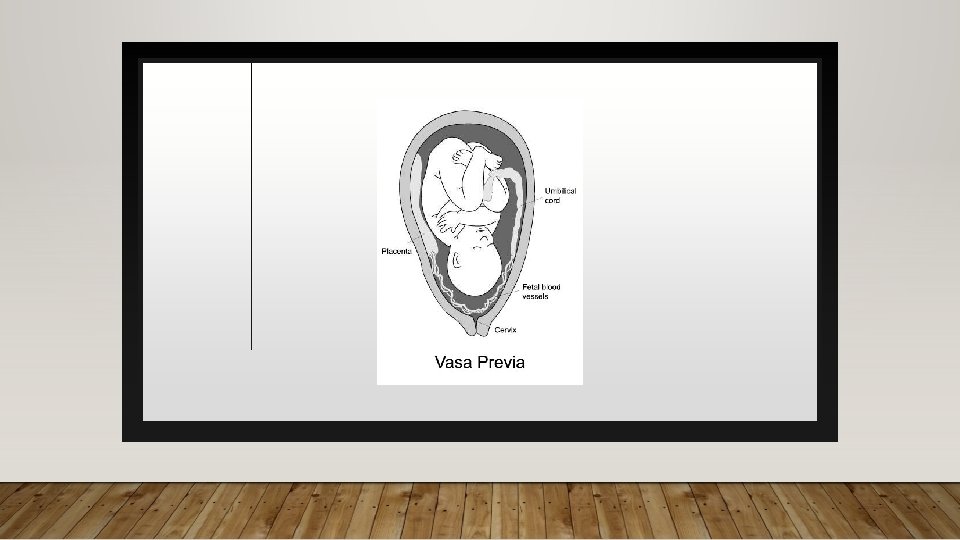
VASA PREVIA • Definition • Condition in which the fetal vessels are located in the membranes near the internal os of the cervix, putting them at risk of injury if the membranes rupture • Epidemiology • 1/2500 births • Etiology • Risk factors • Placental anomalies (e. g. , bilobate or succenturiate placenta, velamentous umbilical cord insertion) • Placenta previa • Multiparity • In-vitro fertilization
VASA PREVIA • Diagnostics • Transabdominal or transvaginal ultrasound with color Doppler shows fetal vessels overlying the internal os and decreased blood flow within fetal vessels • Treatment • Emergency cesarean if there are signs of fetal distress
UTERINE RUPTURE • Uterine rupture is a pregnancy complication that is life-threatening for the mother and the baby. It occurs in approximately one in every 4, 000 births, and in most cases, during labor. • Incidence: 1/4000 births(As a result of the rising number of C-sections and labor induction, uterine ruptures have increased in frequency)
UTERINE RUPTURE • Uterine rupture is primarily caused by uterine distention. Theoretically, this can occur at any stage of pregnancy; however, it usually takes place during active labor because of the massive force exerted during contractions. • Uterine distention • Delay in labor progression because of fetal malpresentation • Fetal macrosomia and multiple gestations • Overdose of oxytocin • Uterine scar/prior uterine surgery (e. g. , C-section or myomectomy) • Traumatic rupture (e. g. , iatrogenic or caused by an accident)
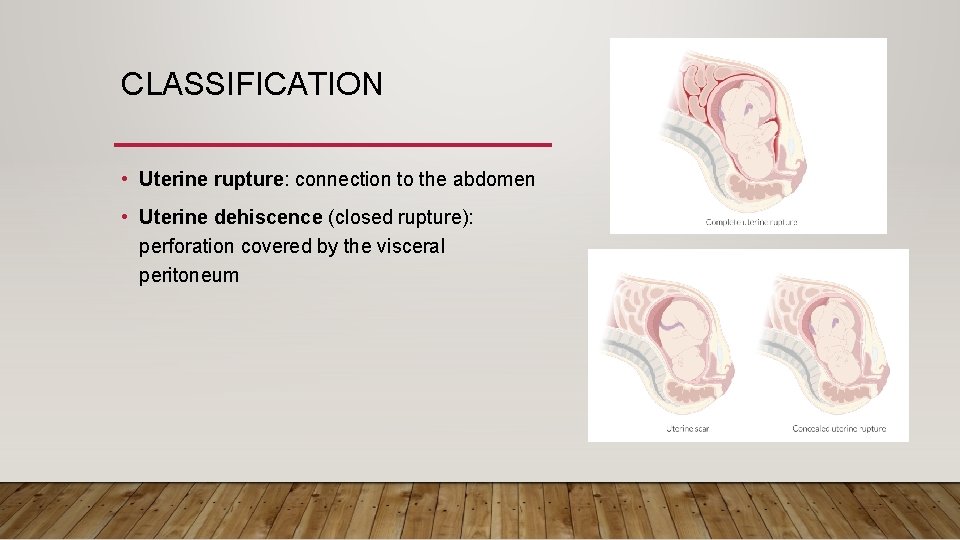
CLASSIFICATION • Uterine rupture: connection to the abdomen • Uterine dehiscence (closed rupture): perforation covered by the visceral peritoneum
CLINICAL PICTURE • Severe abdominal pain • Sudden pause in contractions • Fetal distress (e. g. , deteriorating fetal heart rate) • Vaginal bleeding • Hemodynamic instability (as a result of abdominal bleeding) • Loss of fetal station • Palpable fetal parts through the ruptur
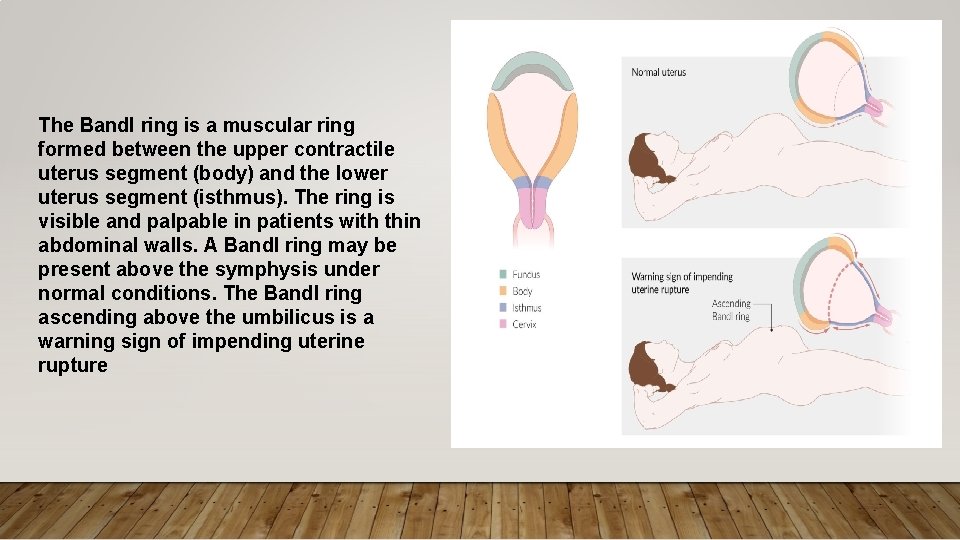
The Bandl ring is a muscular ring formed between the upper contractile uterus segment (body) and the lower uterus segment (isthmus). The ring is visible and palpable in patients with thin abdominal walls. A Bandl ring may be present above the symphysis under normal conditions. The Bandl ring ascending above the umbilicus is a warning sign of impending uterine rupture
TREATMENT • Uterine rupture: • Immediate laparotomy with emergency C‑section • Hysterectomy necessary if the bleeding does not cease • Uterine dehiscence: Cesarean delivery before labor begins is recommended to avoid a complete rupture. • prognosis • Traumatic and spontaneous ruptures increase the mortality rate of the mother and the baby. • Open ruptures lead to hypovolemia and hypoxia; as a result, the fetal mortality rate is between 50– 75%