
Emergency Department Western Health Registrar Training Pharmacy Education






















- Slides: 56
Emergency Department Western Health Registrar Training Pharmacy Education Adrian Weeks 0435 962 527 adrian. weeks@wh. org. au
Pharmacy Service MONDAY to FRIDAY 0800 – 1630 Monday & Tuesday: Sunshine ED Wednesday & Thursday: Footscray ED Friday – Admin Day (call my mobile) Call 0435962527 if you have any immediate questions Email adrian. weeks@wh. org. au if you want something followed up Footer Text 2
Medication Histories in ED Don’t rely on medication lists from GPs • Most often out of date • Often contain every single medication ever prescribed for the patient For up to date information • OPTION A: check the medication brought into ED with the patient (patients can take the medications differently from the labels) • OPTION B: call the local pharmacy and ask for a fax of the dispensed medications (most pts will be able to tell you the name/location of the local chemist) Footer Text 3
Medication Histories in ED cont. Difficult patients to be aware of 1. RDNS administer the meds: RDNS leave the histories in the patients home. Medications are often kept in locked boxes and cannot give you information over the phone 2. Psych patients in SRS/supported accom: the non medically trained carers give the psych medication, the patients often self manage their “other meds” (i. e methadone/chronic disease) 3. Methadone Footer Text 4
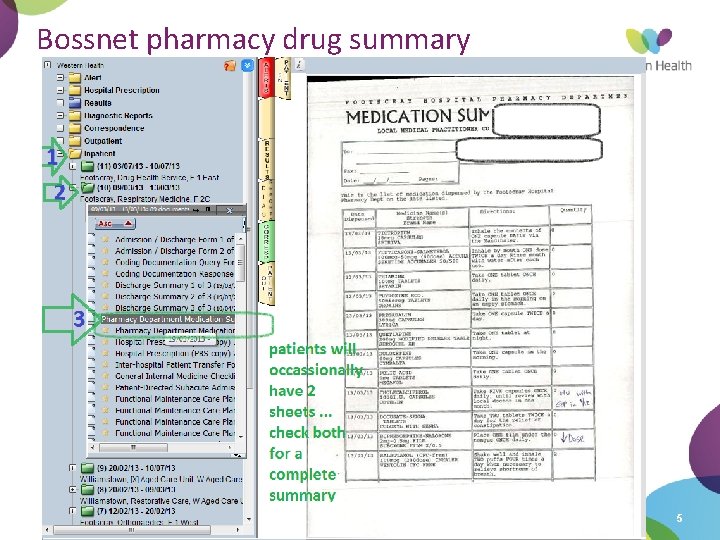
Bossnet pharmacy drug summary Footer Text 5
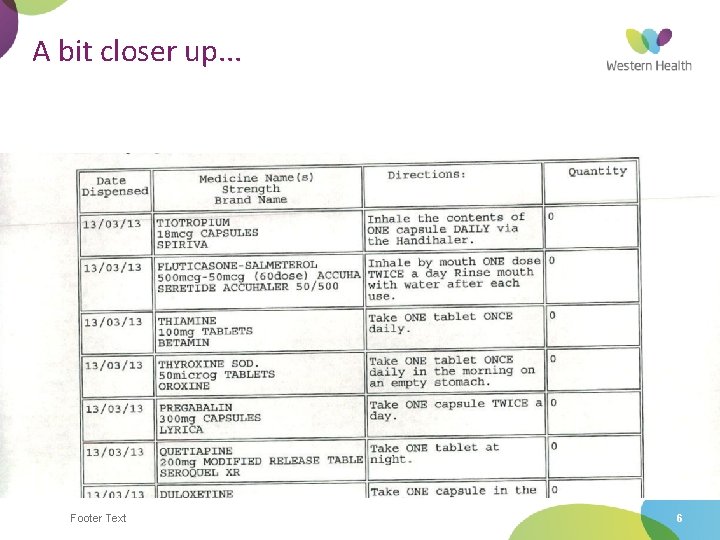
A bit closer up. . . Footer Text 6
Analgesia. . . Give it Options for guidance • NHMRC Emergency Care Acute Pain Management Manual q http: //www. nhmrc. gov. au/guidelines/publications/cp 135 • TGs q Via http: //www. health. vic. gov. au/clinicians • Oz. Emedicine q http: //www. ozemedicine. com/wiki Don’t leave patients in ED with a single dose of analgesia to just wait and see. Write adequate orders so the nurses have the scope to treat up until the patient is pain free. EOU or a cubicle. Treat pain properly Footer Text 7
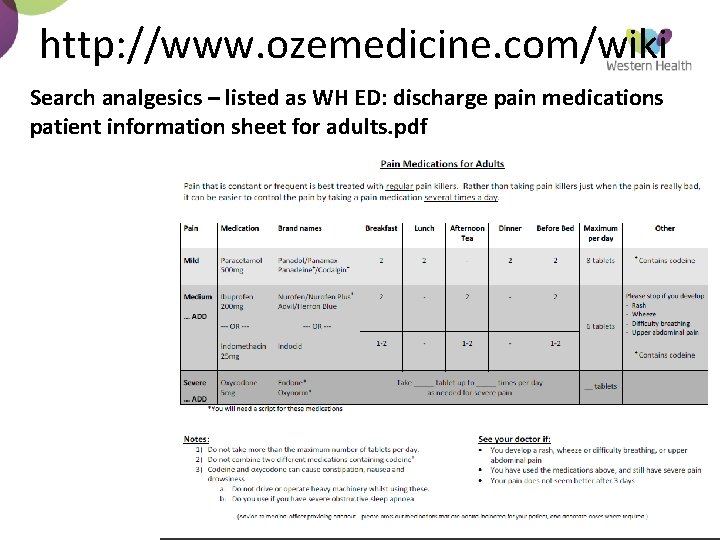
http: //www. ozemedicine. com/wiki Search analgesics – listed as WH ED: discharge pain medications patient information sheet for adults. pdf 8
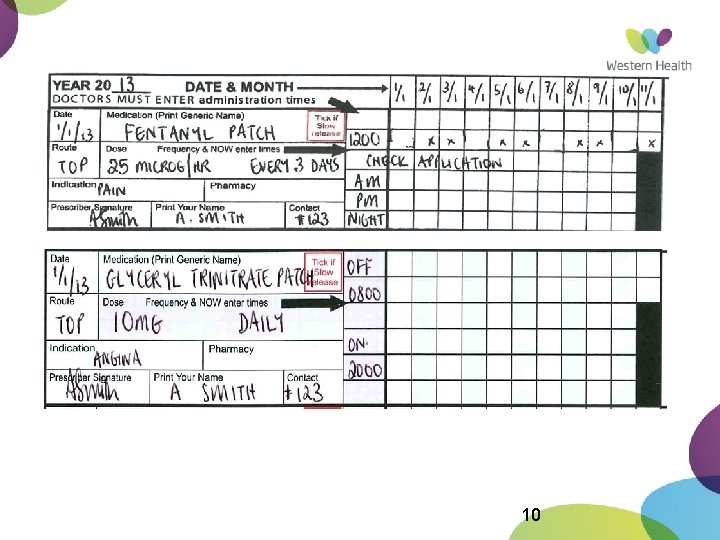
WH ‘Transdermal Medicated Patch’ Procedure *Now available on the WH Intranet* Ø Prescribing Requirements: ØASK!!!! Do you wear a patch? You know, the sticker with the medicine? ? ? Ø All medication orders (prescriptions) for patches must include: q Generic drug name (To further distinguish brand name can be included in brackets). q Dose o Opioid patch (Fentanyl and Buprenorphine): Prescribe dose as hourly rate eg 12 microg/hr o Lignocaine (Versatis®) patch: Prescribe as 5%. o All other patches: Prescribe the dose as total dose in prescription (dose per 24 hour) q Frequency of application. o Patches in situ for more than 24 hours : • Cross out the days on the administration section of the medication chart (AD 271) • Write the nursing ‘Check Application’ section for patches on > 24 hrs. Prescribers’ responsibility to complete this section. o Patches requiring drug-free period • If the patch has specific ON and OFF times (e. g. glyceryl trinitrate patches), clearly specify this on the “Administration times” section of the medication chart. Ø Prescribing Considerations: Ø Timing of application: for opioid patches, midday changeover time is preferred - allows decisions to be made on the morning round prior to re-application. Ø Be aware that more than one strength of patch is often available for the same medication. Ø Information about rate and total drug content is often on the pack & can be confusing. e. g. Fentanyl Sandoz® patches contain 2. 1 mg fentanyl, but rate for prescribing is 12 microgram/hour. Ø Consult ward pharmacist or check product information for possible drug interactions and adverse reactions.
10
NPEP Non-occupational Post Exposure Prophylaxis Change in the available medications Process for both Sunshine and Footscray ED. 1. Identify the patient risk PREPACKED STOCK • Truvada tab x 7 • (tenofovir-emtriciabine 300 mg 200 mg). • Combivir tab x 14 • (lamivudine-zidovudine 150 mg 300 mg). • Kaletra tab x 28 2. Take a thorough history 3. Phone the on call ID consultant 4. Dispense the recommended medicines from the after hours cupboard 5. Refer to ID clinic for follow-up within the week • (lopinavir-ritonavir 200 mg-50 mg). Footer Text 11
SAS FORM Fill these in 1. For unregistered medicines 2. Cat A: Lifesaving drug Cat B: not time critical 3. Without the form the hospital cannot order more stock DRUGS TO BE AWARE OF - Labetalol - Esmolol - Cyanokit Fax to pharmacy once complete. Don’t file in the medical record. Footer Text 12
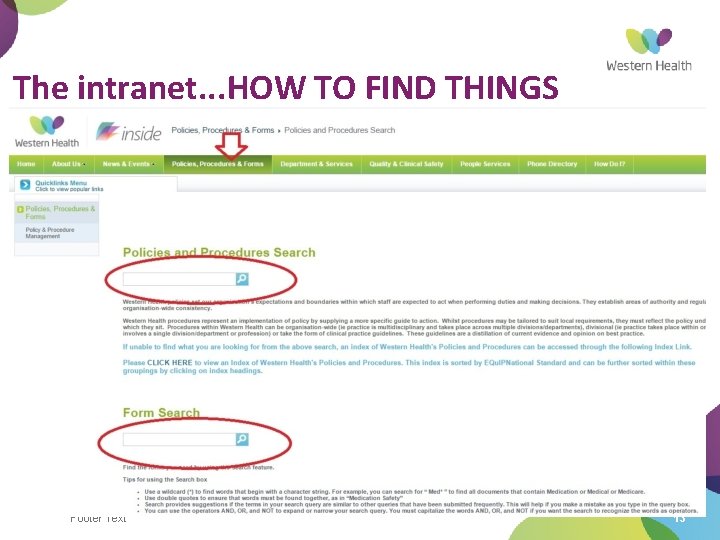
The intranet. . . HOW TO FIND THINGS Footer Text 13
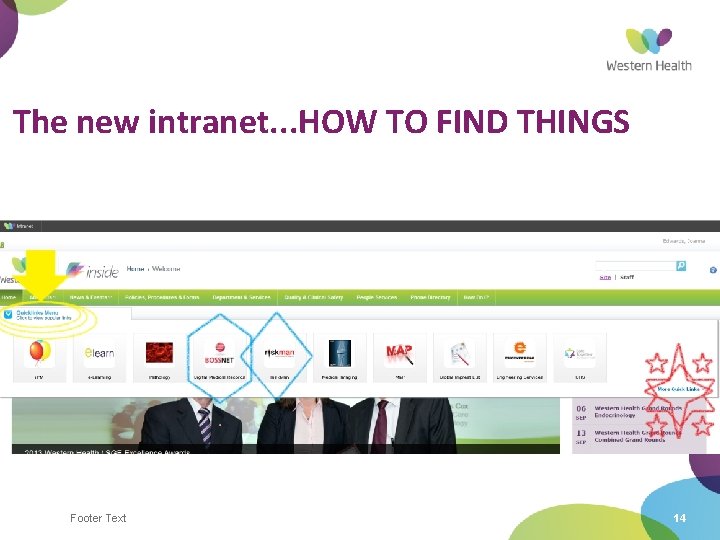
The new intranet. . . HOW TO FIND THINGS Footer Text 14
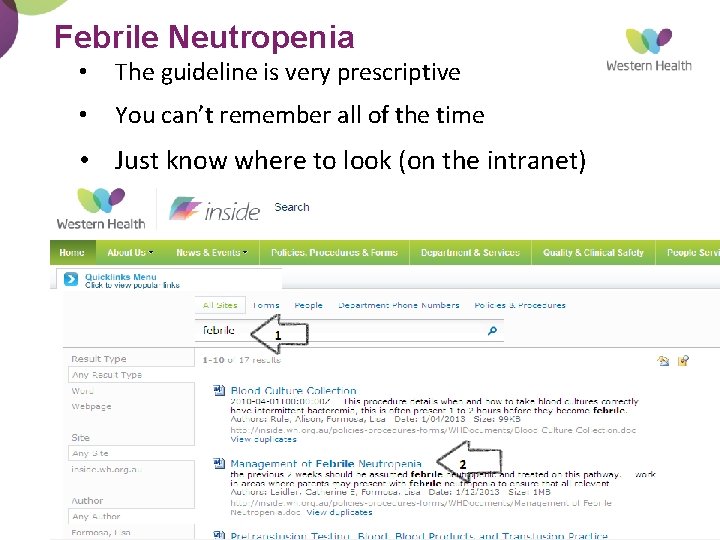
Febrile Neutropenia • The guideline is very prescriptive • You can’t remember all of the time • Just know where to look (on the intranet) Footer Text 15
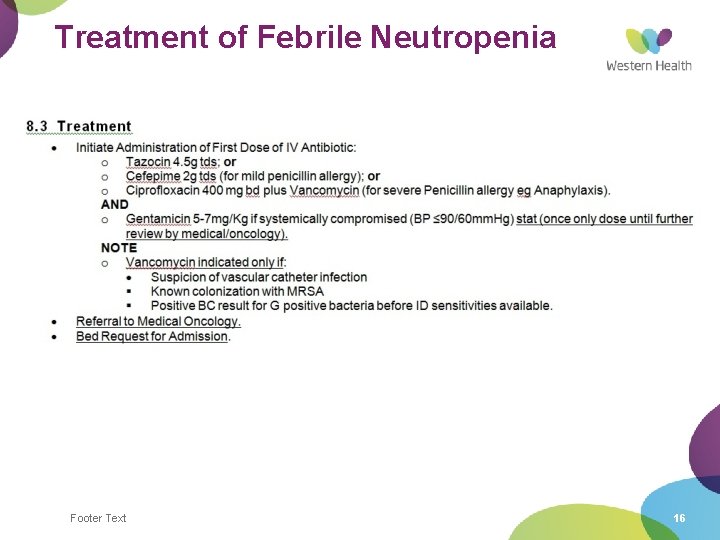
Treatment of Febrile Neutropenia Footer Text 16
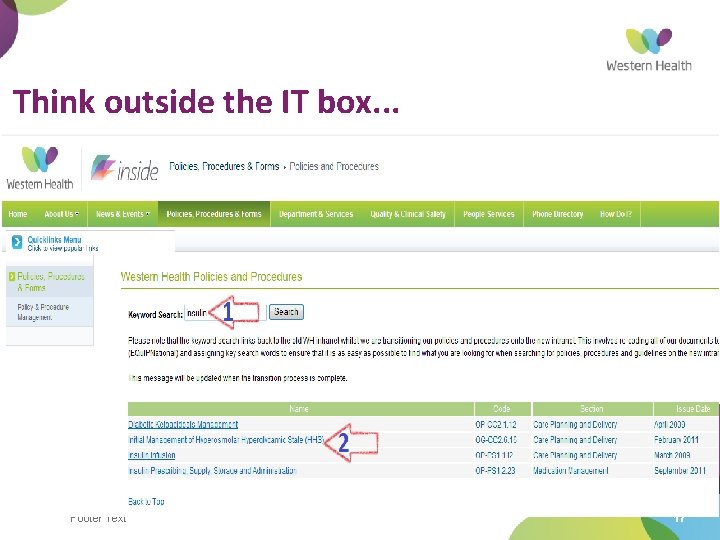
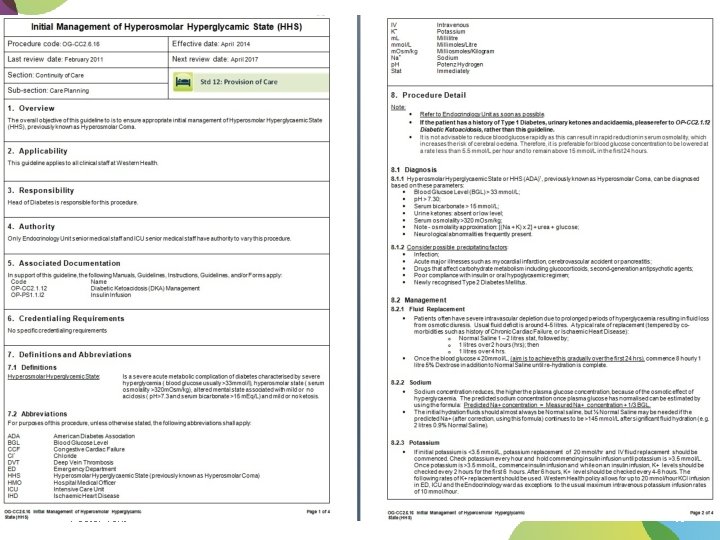
Think outside the IT box. . . Footer Text 17
Footer Text 18
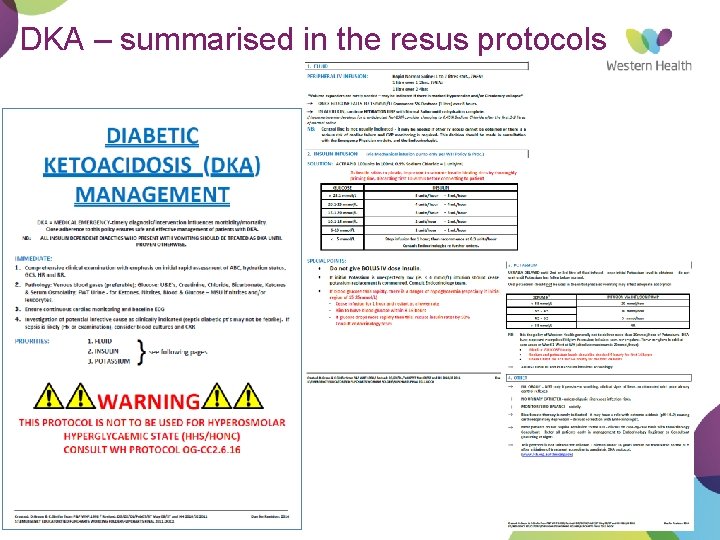
DKA – summarised in the resus protocols Footer Text 19
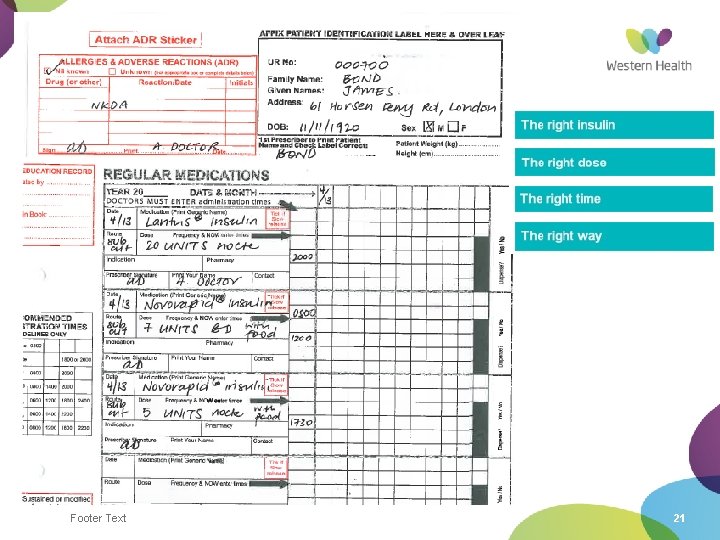
Insulin • Must be prescribed in ‘a clear and unambiguous manner’ • Dosage is to be written in full as UNITS (not U or I. U can be mistaken for 0 or 10) • Chart insulin by BRAND i. e Apidra®, Lantus®, Novomix 30® • Be clear re: the route of administration IV or subcut. SC can be mistaken for SL (subling) • Remember we feed patients at very strange times 0800, 1200 -1230, 1730. Chart short acting insulin doses accordingly. • Be clear when confirming doses ie. “ 17 – so one seven or seven zero? ? ” Footer Text 20
Footer Text 21
Insulin is tricky. . . don’t be tricked! Footer Text Ask about pumps 22
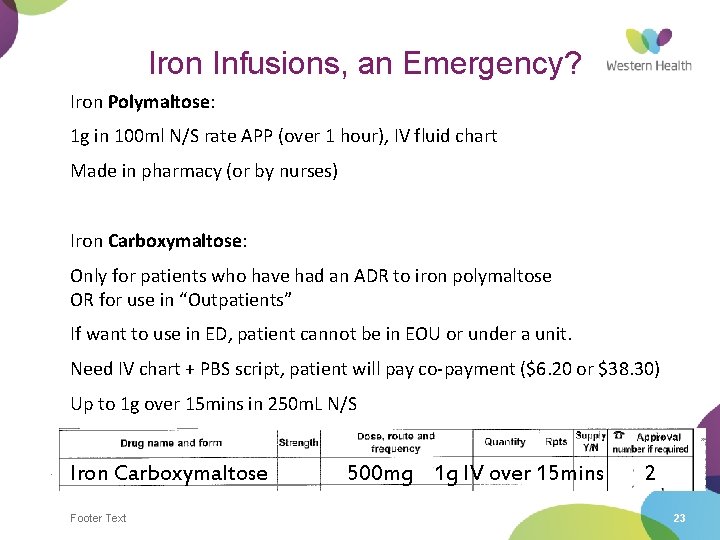
Iron Infusions, an Emergency? Iron Polymaltose: 1 g in 100 ml N/S rate APP (over 1 hour), IV fluid chart Made in pharmacy (or by nurses) Iron Carboxymaltose: Only for patients who have had an ADR to iron polymaltose OR for use in “Outpatients” If want to use in ED, patient cannot be in EOU or under a unit. Need IV chart + PBS script, patient will pay co-payment ($6. 20 or $38. 30) Up to 1 g over 15 mins in 250 m. L N/S Iron Carboxymaltose Footer Text 500 mg 1 g IV over 15 mins 2 23
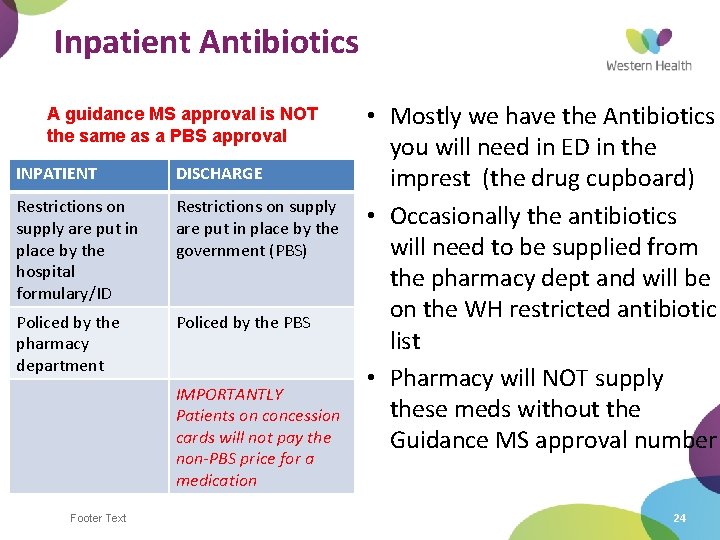
Inpatient Antibiotics A guidance MS approval is NOT the same as a PBS approval INPATIENT DISCHARGE Restrictions on supply are put in place by the hospital formulary/ID Restrictions on supply are put in place by the government (PBS) Policed by the pharmacy department Policed by the PBS IMPORTANTLY Patients on concession cards will not pay the non-PBS price for a medication Footer Text • Mostly we have the Antibiotics you will need in ED in the imprest (the drug cupboard) • Occasionally the antibiotics will need to be supplied from the pharmacy dept and will be on the WH restricted antibiotic list • Pharmacy will NOT supply these meds without the Guidance MS approval number 24
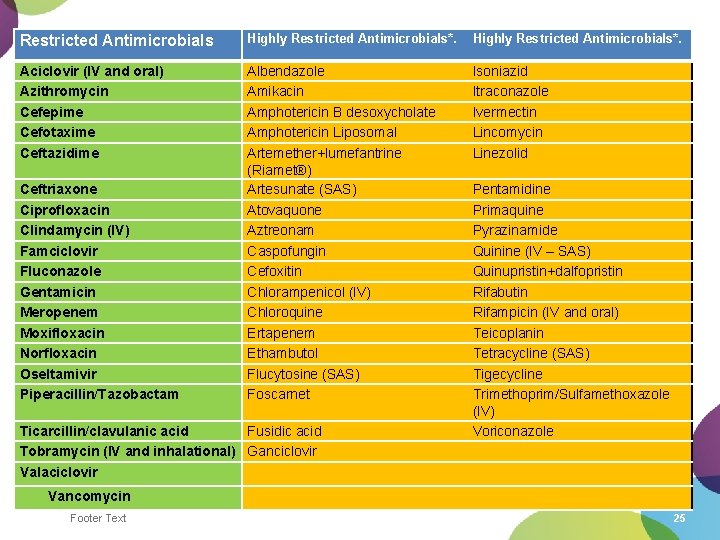
Restricted Antimicrobials Highly Restricted Antimicrobials*. Aciclovir (IV and oral) Azithromycin Cefepime Cefotaxime Ceftazidime Albendazole Amikacin Amphotericin B desoxycholate Amphotericin Liposomal Artemether+lumefantrine (Riamet®) Artesunate (SAS) Atovaquone Aztreonam Caspofungin Cefoxitin Chlorampenicol (IV) Chloroquine Ertapenem Ethambutol Flucytosine (SAS) Foscarnet Isoniazid Itraconazole Ivermectin Lincomycin Linezolid Ceftriaxone Ciprofloxacin Clindamycin (IV) Famciclovir Fluconazole Gentamicin Meropenem Moxifloxacin Norfloxacin Oseltamivir Piperacillin/Tazobactam Ticarcillin/clavulanic acid Fusidic acid Tobramycin (IV and inhalational) Ganciclovir Valaciclovir Pentamidine Primaquine Pyrazinamide Quinine (IV – SAS) Quinupristin+dalfopristin Rifabutin Rifampicin (IV and oral) Teicoplanin Tetracycline (SAS) Tigecycline Trimethoprim/Sulfamethoxazole (IV) Voriconazole Vancomycin Footer Text 25
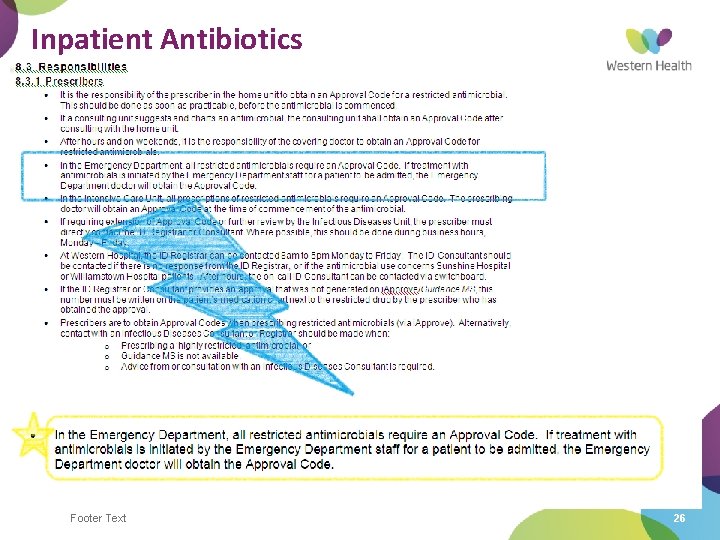
Inpatient Antibiotics Footer Text 26
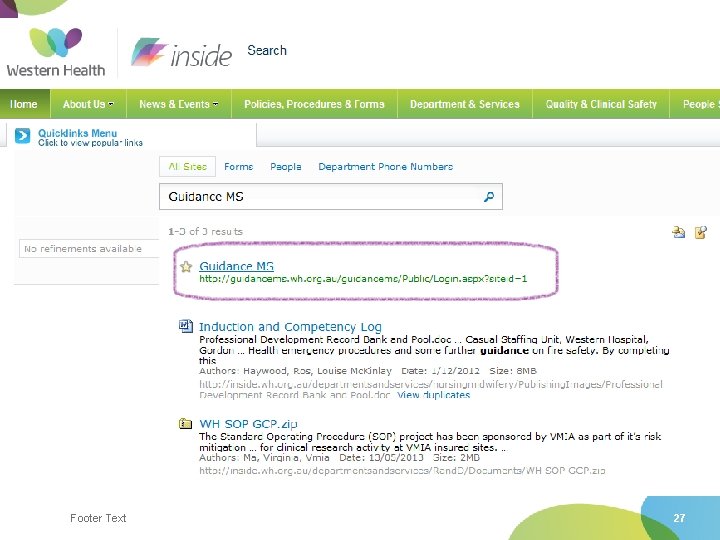
Footer Text 27
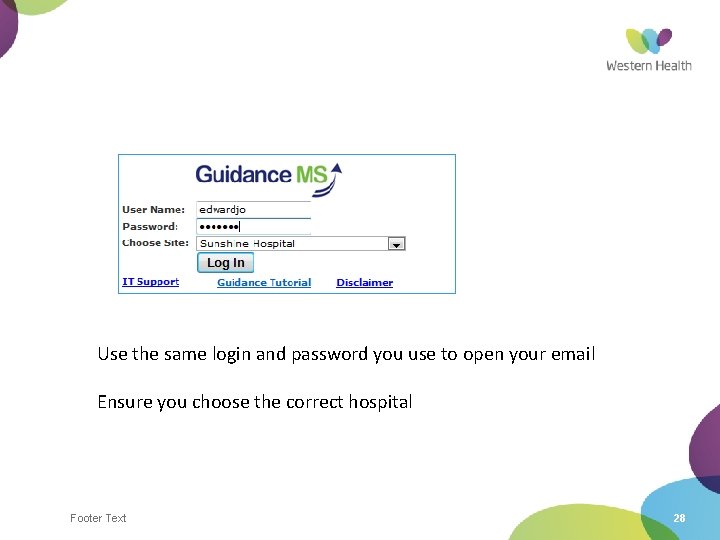
Use the same login and password you use to open your email Ensure you choose the correct hospital Footer Text 28
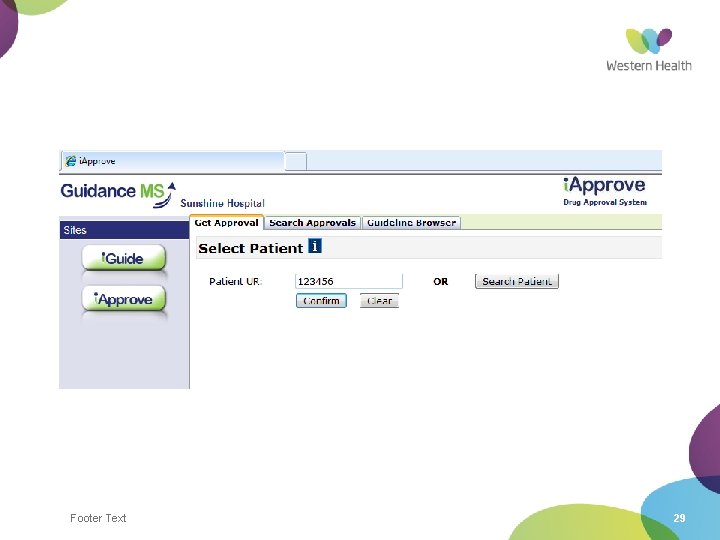
Footer Text 29
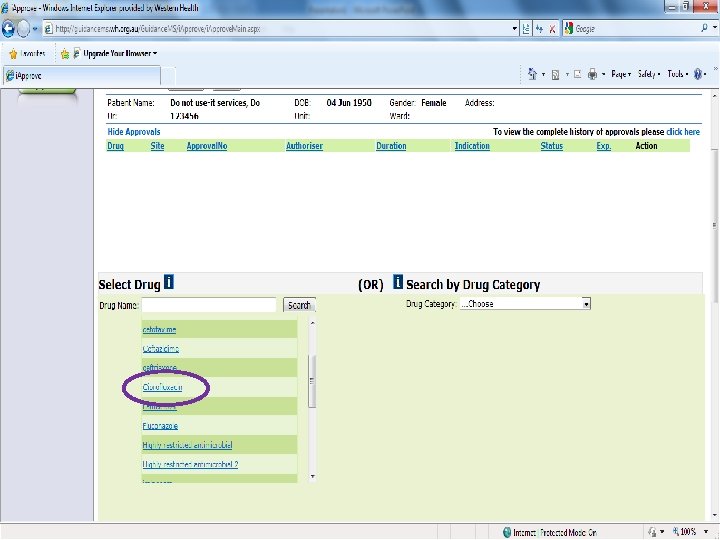
Footer Text 30
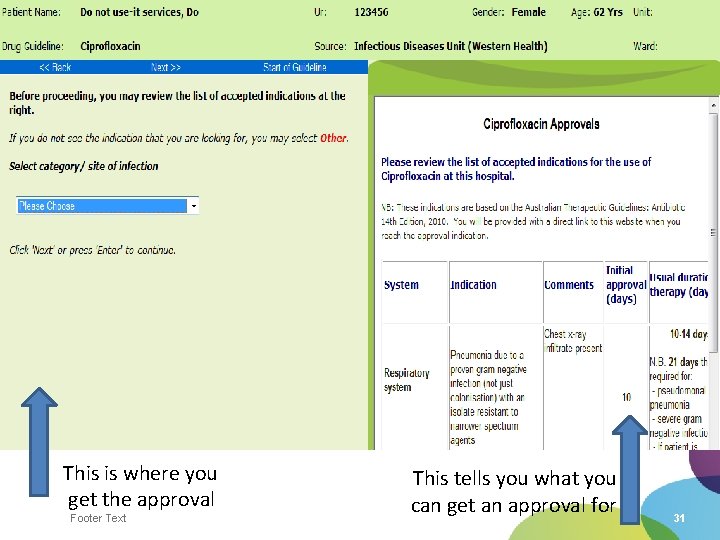
This is where you get the approval Footer Text This tells you what you can get an approval for 31
Once you have got the approval write it on the drug chart prior to faxing the chart to pharmacy 14/8/1 2 IV Ciprofloxacin 500 mg BD D. Octor Footer Text XXX-1408 Dr D Octor 5 080 0 200 0 32
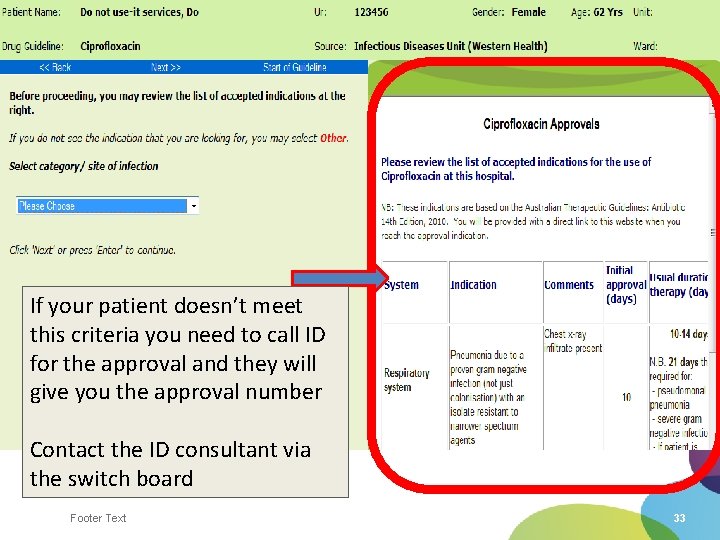
If your patient doesn’t meet this criteria you need to call ID for the approval and they will give you the approval number Contact the ID consultant via the switch board Footer Text 33
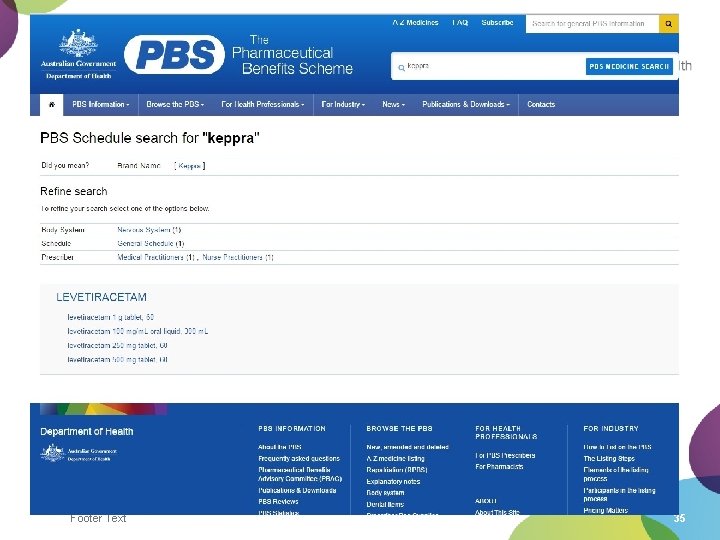
PBS APPROVALS (not just Antibiotics) www. pbs. gov. au 2 approval types for ED – Streamlined (write the approval on the script with no phone call) – Phone approval required (for restricted drugs or increased quantities, or extra repeats) Footer Text 34
Footer Text 35
Footer Text 36
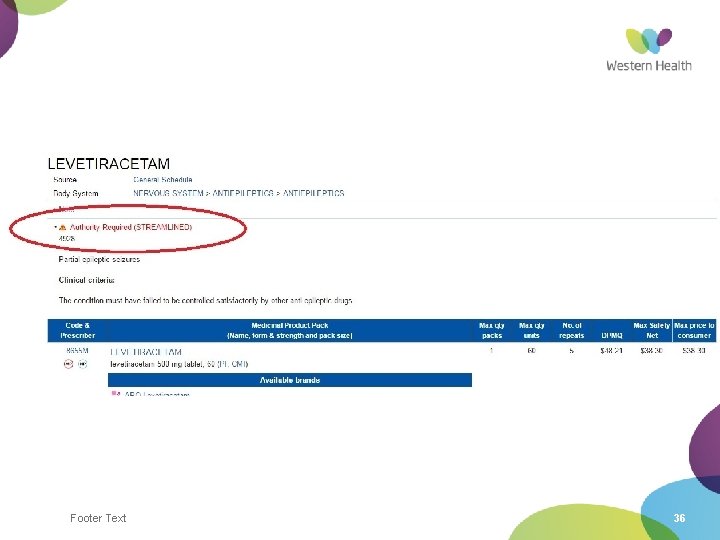
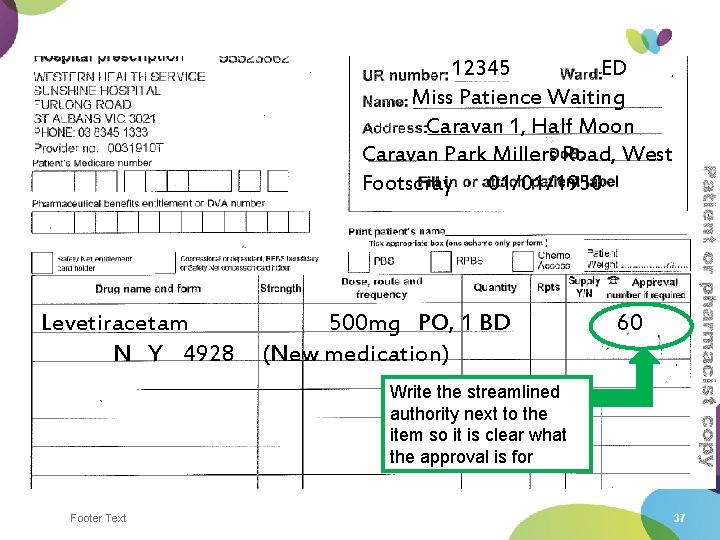
12345 ED Miss Patience Waiting Caravan 1, Half Moon Caravan Park Millers Road, West Footscray 01/01/1950 Levetiracetam N Y 4928 500 mg PO, 1 BD (New medication) 60 Write the streamlined authority next to the item so it is clear what the approval is for Footer Text 37
If the PBS website states “Authority required” you need to call the phone number on the bottom of the script and state which authority indication the patient meets Footer Text 38
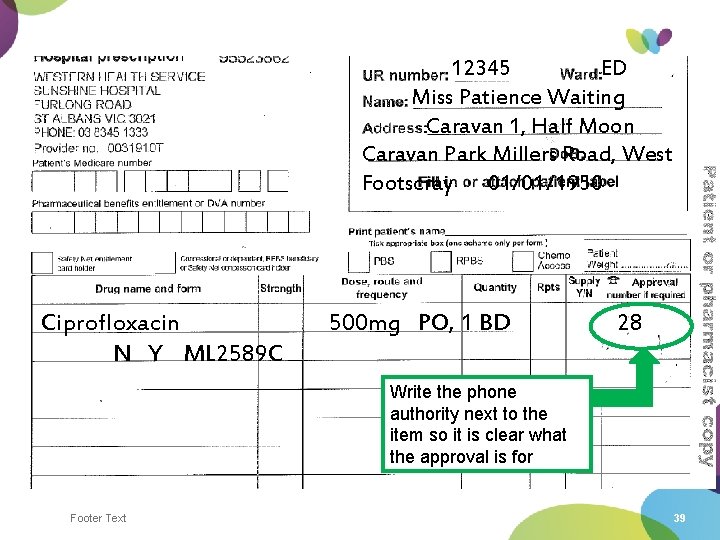
12345 ED Miss Patience Waiting Caravan 1, Half Moon Caravan Park Millers Road, West Footscray 01/01/1950 Ciprofloxacin N Y ML 2589 C 500 mg PO, 1 BD 28 Write the phone authority next to the item so it is clear what the approval is for Footer Text 39
Epipens Script needs authority – ask for 2 Demo pens in draw of nurse in charge’s desk (please return after use) www. epiclub. com. au – support program for patients Ensure family know how to use as well as patient Use: - Blue cap off - Orange end into anterolateral aspect of the thigh at 90ᵒ - Device will “click” - Hold for 10 seconds - Release Footer Text 40
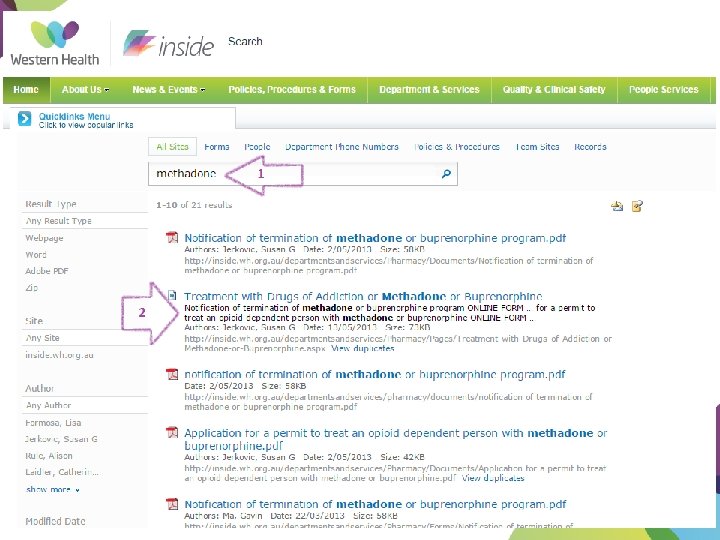
METHADONE / BUPRENORPHINE Cannot dose until you have: 1. Confirmed the dose with the dosing point (pharmacy) 2. Have confirmed that the dose hasn’t been given today 3. Faxed off the DHS paperwork or complete online Cannot dose the patient AT ALL, if the patient has missed 3 days of methadone OR 5 days of buprenorphine. If this has occurred you need to speak to Drug and Alcohol Be wary that the patient may not be on a current opioid replacement program Footer Text 41
Footer Text 42
Footer Text 43
Footer Text FAX TO: 1300 360 830 44
METHADONE / BUPRENORPHINE Cannot dose until you have: 1. 2. 3. 4. Confirmed the dose with the dosing point (pharmacy) Have confirmed that the dose hasn’t been given today Faxed off the DHS paperwork Charted the methadone in milligrams (patients will often tell you they are on m. Ls of methadone. . . meaning the milligram dose. . . but methadone syrup is 5 mg/m. L so if you chart the m. L dose as mg the patient will have a 5 times overdose) 14/2/12 Methadone syrup 5 mg/m. L PO 120 mg 14/2 0900 D. Octor Dr D Octor Methadone paperwork faxed to DHS 14/02 0830 Footer Text 45
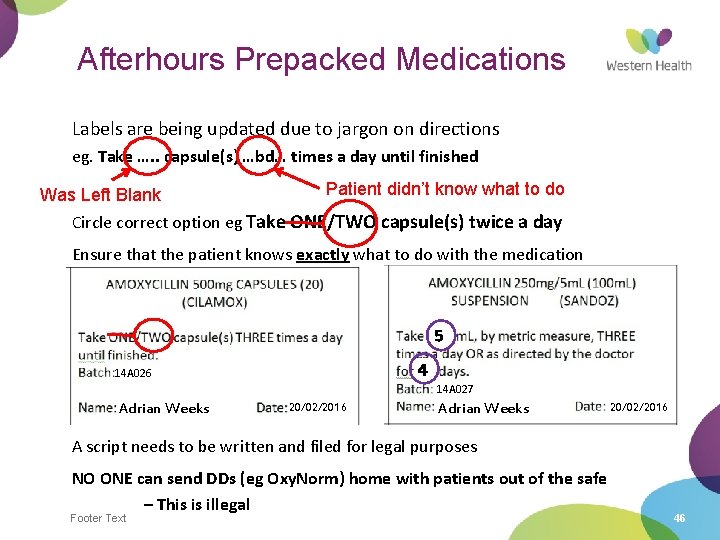
Afterhours Prepacked Medications Labels are being updated due to jargon on directions eg. Take …. . capsule(s) …bd… times a day until finished Patient didn’t know what to do Was Left Blank Circle correct option eg Take ONE/TWO capsule(s) twice a day Ensure that the patient knows exactly what to do with the medication 5 4 14 A 026 14 A 027 Adrian Weeks 20/02/2016 A script needs to be written and filed for legal purposes NO ONE can send DDs (eg Oxy. Norm) home with patients out of the safe – This is illegal Footer Text 46
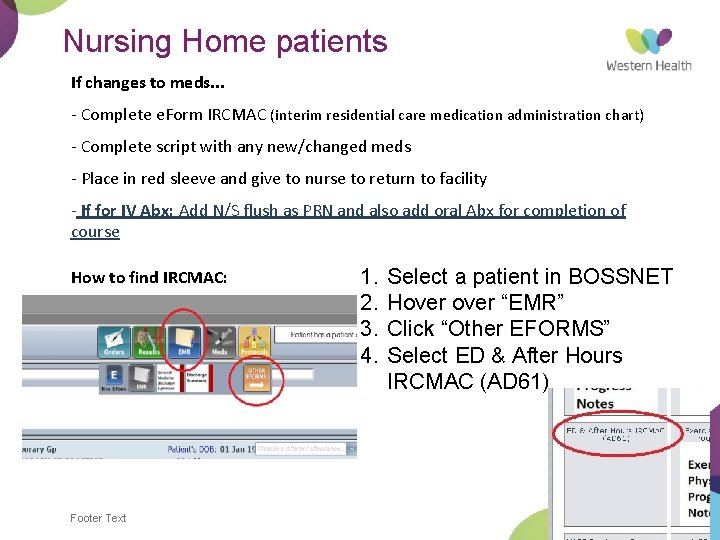
Nursing Home patients If changes to meds. . . - Complete e. Form IRCMAC (interim residential care medication administration chart) - Complete script with any new/changed meds - Place in red sleeve and give to nurse to return to facility - If for IV Abx: Add N/S flush as PRN and also add oral Abx for completion of course How to find IRCMAC: Footer Text 1. 2. 3. 4. Select a patient in BOSSNET Hover “EMR” Click “Other EFORMS” Select ED & After Hours IRCMAC (AD 61) 47
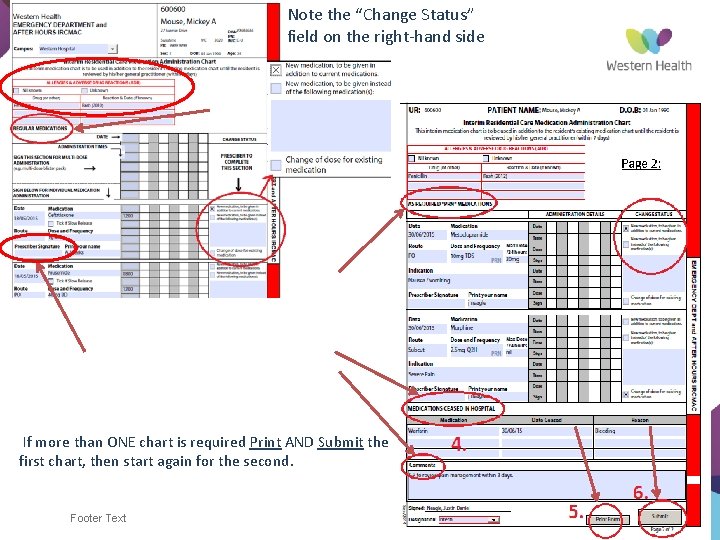
Note the “Change Status” field on the right-hand side If more than ONE chart is required Print AND Submit the first chart, then start again for the second. Footer Text 48
Footer Text 49
Footer Text 50
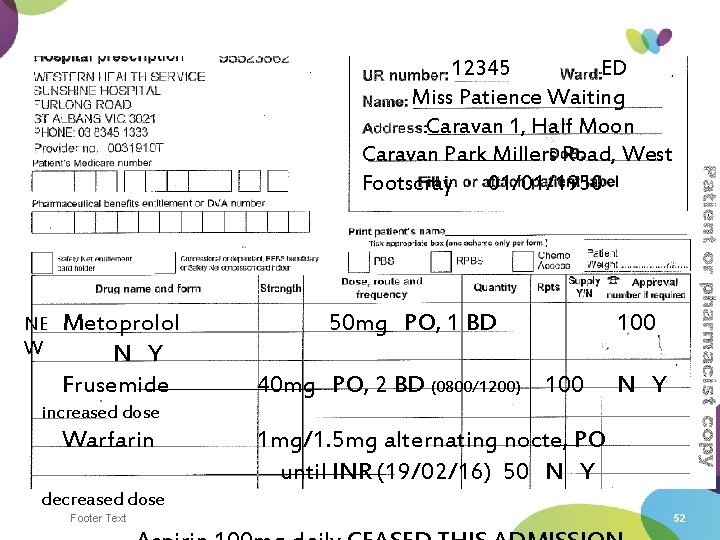
Discharge Scripts from ED SUGGESTED GUIDELINES • Only write up the new medicines • Unless, you have changed the old medications. Then indicate changes • Document CLEARLY if you have ceased any medications Footer Text 51
12345 ED Miss Patience Waiting Caravan 1, Half Moon Caravan Park Millers Road, West Footscray 01/01/1950 NE W Metoprolol N Y Frusemide 50 mg PO, 1 BD 100 40 mg PO, 2 BD (0800/1200) 100 N Y increased dose Warfarin 1 mg/1. 5 mg alternating nocte, PO until INR (19/02/16) 50 N Y decreased dose Footer Text 52
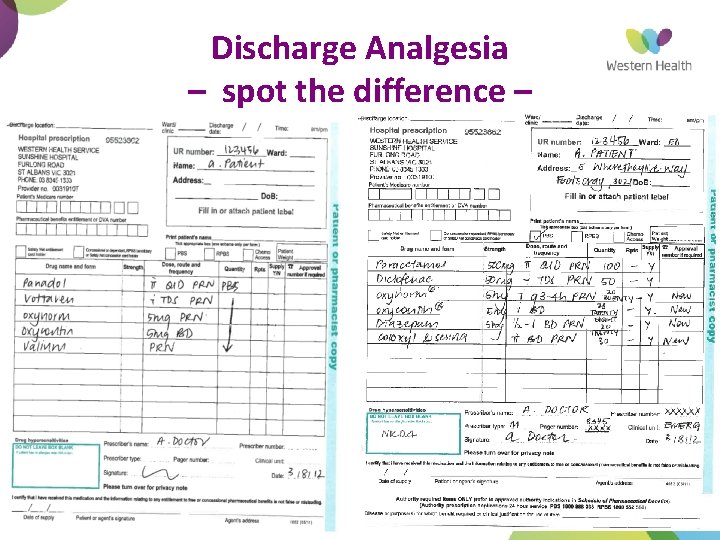
Discharge Analgesia – spot the difference –
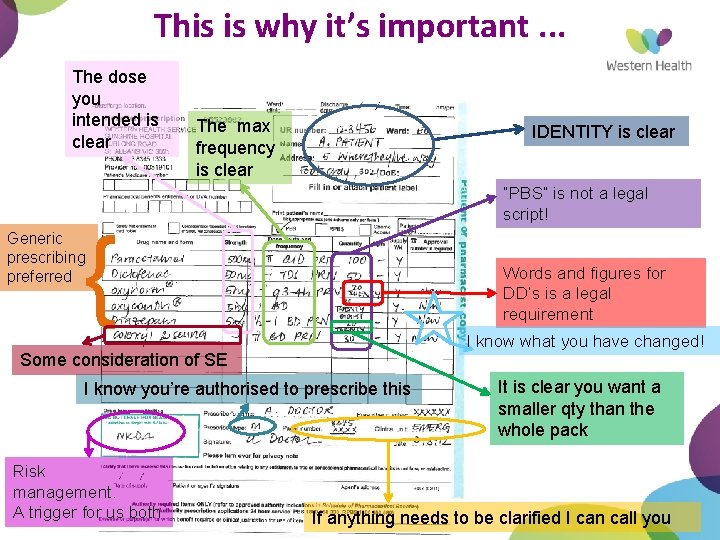
This is why it’s important. . . The dose you intended is clear The max frequency is clear IDENTITY is clear “PBS” is not a legal script! { Generic prescribing preferred Words and figures for DD’s is a legal requirement I know what you have changed! Some consideration of SE I know you’re authorised to prescribe this Risk management. A trigger for us both It is clear you want a smaller qty than the whole pack If anything needs to be clarified I can call you
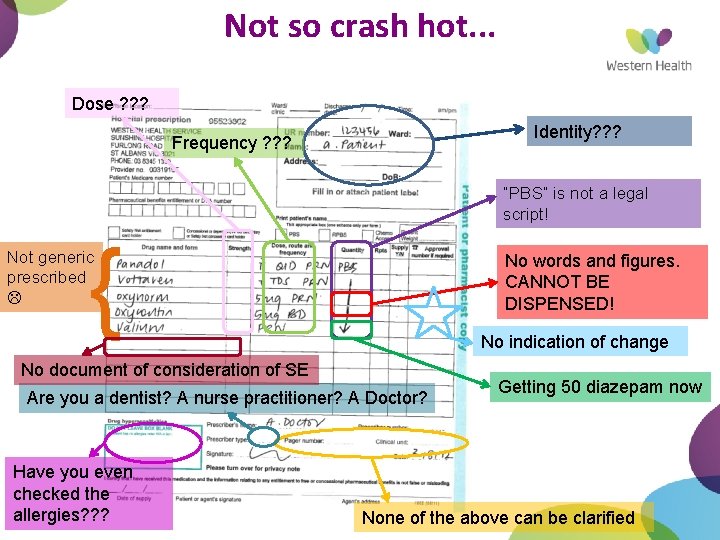
Not so crash hot. . . Dose ? ? ? Identity? ? ? Frequency ? ? ? “PBS” is not a legal script! { Not generic prescribed No words and figures. CANNOT BE DISPENSED! No indication of change No document of consideration of SE Are you a dentist? A nurse practitioner? A Doctor? Have you even checked the allergies? ? ? Getting 50 diazepam now None of the above can be clarified
Discharge Letters You must clearly state in your discharge letters, any: • Changes to medications: Up, Down and Ceased • The ACTUAL drugs you have commenced – Phone calls to the consultant asking about opioids and all the letter says is analgesia. Legalities – Represents to ED 12 hours post D/C requiring more pain relief. Bossnet not up to date. Simply says “analgesia”. Not helpful to anyone. • Plans for monitoring: INR, TDM, Electrolytes. WITH TIME FRAMES • Clearly indicated time until review by GP Footer Text 56
























































