Case Presentation Dave Choi PGY4 Emergency Medicine Edmonton

































- Slides: 39
Case Presentation Dave Choi PGY-4 Emergency Medicine Edmonton
Learning Goals § Present an interesting case § Briefly review relevant material § Be done in 25 minutes… really.
The Case § Day shift at the Foothills § Just finished resusitating a level 1 trauma patient § Feeling good about your intubation and chest tube skills, you move to the minor side to see a patient with “low back pain”
History § § Mr G. 58 y. o. male Walked into ER c/o lower back pain x 1/12 Seen by GP last week given toradol and percocet, also put on Flomax for BPH
History § § Noticed lower back pain at night initially No history of trauma Constant pain Mildly relieved by hot compresses, and pain medications § Activity doesn’t make it better or worse § Wakes him up at night sometimes
History § § Pain has been getting bit worse Worse with coughing, straining Radiating to flank/groin x 1/52 Some voiding difficulty (hard start) x 1/52 § No bowel incontinence
History § No fever, chills, night sweats § ~5 lb weight loss over last couple months
Red Flags § § § Pain not relieved by lying down Night pain Leg weakness Bowel, bladder, sexual symptoms Fever (esp. IVDU) Weight loss
History § Pm. Hx: ↑ cholesterol § Meds: Crestor 10 mg PO QD, Percocet 1 tab PO Q 4 H prn, Toradol 10 mg PO Q 6 H prn § Allergies: NKDA § FHx: father MI at 80 y. o.
History § - SHx non smoker occas. Et. OH no illegal drugs worked as senior manager for Telus, retired earlier this year, exercises 3 x/week, going on holidays soon § ANY OTHER QUESTIONS? § Ddx?
O/E § Vitals: T 36. 8, P 54, RR 15, BP 137/83, Sat 99% § Heart S 1 S 2, no EHS/murmurs/rubs § Lungs clear, AE=AE § Abd soft, normal BS, bit tender suprapubic, no peritoneal signs/guarding § No pulsating mass, no flank tenderness
MSK Exam § § § No erythema/warmth/swelling over back Pain is midline but not worse with palpation No atrophy legs Normal SLR tests (Lasegue’s) Normal ROM lower back (Schober’s) Normal gait
Neuro Exam § Motor: 5/5 power UE, Slight decreased power L hip flexor, otherwise normal § Sensation: normal UE/LE, no saddle anesthesia, normal rectal tone, mild prostate enlargement § DTR +2 bilat UE, +1 bilat LE, no Babinski
Investigations § Xray Lspine - mild degen changes § Hgb 158 WBC 5. 9 Plt 243 § Na 140 K 4. 1 Cl 105 bicarb 27 § Cr 100, Urea 5. 5 § Urine neg leuks/protein/hgb § Bladder scanned for 154 ml
Differential Dx Low Back Pain § Mechanical (>95%) - Lumbar strain (70%), degenerative process (10%), herniated disk (4%), spinal stenosis (3%), OP compression # (4%), spondylolisthesis (2%), traumatic # (<1%), congenital disease (<1%), disc disruption § Non-mechanical spinal conditions (~1%) - Neoplasia, infection, inflammatory arthritis, Paget’s § Visceral disease (~2%) - Disease of pelvic organs, renal disease, AAA, GI
PLAN § D/C home? § Any other investigations? - FAST (aorta) § Follow up?
10 days later… § Patient sent into ER from GP’s office for in/out cath and urinalysis § Lower abdominal discomfort § Cannot sleep
Physical Exam § Chest clear § Abd: bit distended, dull to percussion, suprapubic discomfort to palpation, symmetric fullness § Neuro exam unchanged from previous § Bladder scanned for 550 ml, foley drained 500 ml, foley left in
10 days later… § Urinalysis: 3+ leuks, many bacteria § Started on Septra § Discharged home with U/S pelvis booked for next day
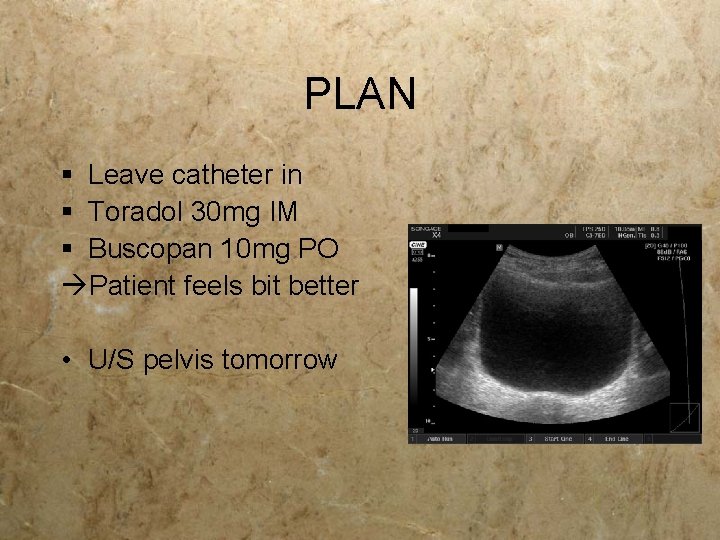
PLAN § Leave catheter in § Toradol 30 mg IM § Buscopan 10 mg PO àPatient feels bit better • U/S pelvis tomorrow
It’s tomorrow § U/S abdo/pelvis – normal GB + bile ducts, liver grossly normal, pancreas, spleen, aorta normal, multiple bilateral renal cysts, but kidneys otherwise normal § Now what? § Dx = prostate hyperplasia, UTI, and mechanical back pain
Case continued § Urology consult for cystoscopy as outpatient
28 days later § Still c/o back pain worse at night § Very tender suprapubic area § Numbness / tingling feet started 1 week ago § Meds: Flomax, Proscar, Flexeril, Percocet prn, Toradol prn
28 days later § § - O/E: AVSS Neuro Exam Motor: 4+/5 hip flexors, others 5/5 Sensation: “numb” over plantar feet bilat, touch/pinprick ok - DTR +1 LE bilat, +2 UE bilat, no Babinski - No saddle anesthesia - Rectal tone intact
Case continued § Working Dx = Urinary retention 2 o to BPH and LBP (mechanical)
Hmm… § Pt returns to ED 3 more times in the next 4 days c/o urinary retention and suprapubic discomfort § Now c/o bilateral numbness/tingling feet and lower back pain radiating to bilateral thighs
Investigations § Pt booked for outpt MRI L-spine for ? neurogenic claudication by GP § Cystoscopy – mildly enlarged prostate
2 weeks later… § Returns to ED c/o gradual bilateral leg weakness L>R § Has been unable to walk independently over last 4 days (using walker) § Foley catheter in situ x 3 weeks § Unable to cope at home
Recap of the Events § LBP, gradual onset and worsening, night pain, worse with valsalva x 4/12 § Pain radiating to bilat thighs and groin x 3/12 § Numbness/tingling bilat feet, ascending from feet to thigh x 1/12 § Urinary retention x 1/12, indwelling foley x 3/52 § Gradual bilateral leg weakness x 2/52
Neuro Exam Now § Motor: UE normal; 3/5 Hip flexors, 3+/5 Quads, 4/5 Hamstrings, 4/5 ankle dorsi/plantarflexion § Sensation: saddle anesthesia! § Reflexes: no DTRs LE, no Hoffman’s, no Babinski, normal bulbocavernosus reflex and rectal tone
Case continued § Admitted under neurosurgery § MRI – syrinx vs inflammatory or neoplastic cord disease, suggest LP by neurology to r/o viral etiology § Lumbar Puncture – WBC 103 RBC 96 Prot 4. 15 (<0. 45) Glu 2. 6 (2. 2 -4. 4) neg cultures § Diagnosis?
Case § CT chest/abd – no aortic dissection § MRA – suspicious for dural AV fistula arising from upper lumbar region causing ischemia § OR – L 2 -4 laminectomy and clipping of spinal dural AV fistula
Dural AV fistula § a. k. a. Foix-Alajouanine Syndrome § AV malformation of spinal cord vessels, usually lower thoracic or lumbosacral § Can lead to ischemic injury of the cord § Male: Female 4: 1 § Usually >50 yo § Symptoms gradual onset over months to years
Symptoms / Signs - Weakness / numbness / tingling of LE Gradual onset + worsening LE weakness Urinary / fecal incontinence lower back pain +/- radiating Abnormal gait Spastic or flaccid paraparesis +/- sensory level - DTR variable; +/- Babinski - Decreased rectal tone
Investigation / Treatment INVESTIGATION § MRI § Myelogram § angiography TREATMENT § Embolization of AVM § Laminectomy w/ obliteration of AV shunt
Case § Electrodiagnostic Study - Axonal injury to leg muscles L>R - Considerable # motor neurons still intact, prognosis for functional recovery reasonably good
Mr. G now § § Back pain significantly reduced Unable to ambulate Self in/out catheterizations BMs ok § Still hoping to go on planned holidays to Hawaii in the future
Summary § Red flags for Low back pain § Multiple ER visits with same problem, do not get blinded by the “diagnosis”