
Laura Kuiper ziekenhuisapotheker Inhalatiemedicatie op de IC 2






















- Slides: 45
Laura Kuiper, ziekenhuisapotheker Inhalatiemedicatie op de IC 2 november 2017
Inhalatiemedicatie Voorkeursbehandeling bij astma en COPD Direct lokaal effect Lagere dosering nodig Geen/weinig systemische bijwerkingen
Sympathicomimetica met vooral β 2 effect Agonisten (‘aanzetten’) van β 2 receptoren in de longen Ontspanning van longen: luchtwegverwijding
Anticholinergica/Parasympathicolytica Blokkeren muscarinereceptoren waardoor geen binding van stof acetylcholine Muscarine receptor 3 (M 3) receptor in de longen: verantwoordelijk voor samentrekking longen. Blokkeren receptor blokkeren samentrekking
Inhalatiecorticosteroïden Mechanisme niet helemaal bekend Ontstekingremmende werking Verminderen gevoeligheid voor prikkels en verminderen allergische reactie Stabiliseren celmembranen
Soorten inhalatoren Dosisaerosol Geneesmiddel is oplossing of suspensie Indrukken & langzaam inhaleren Vaak gebruik met voorzetkamer Poederinhalator Geneesmiddel in poedervorm Krachtig en diep inhaleren Verneveling In water oplosbare geneesmiddelen Passieve inhalatie middels verneveling
Inhalatoren - aërosol l Dosisaerosol (p. MDI) l Dosisaerosol + babyhaler/nebuhaler/volumatic/aerochamber l Autohaler l Soft mist inhaler (SMI)
Inhalatoren – DPI’s l Diskus l Inhalator Ingelheim l Diskhaler l Cyclohaler l Turbuhaler l Foradil poederinhalator l Handihaler l Novolizer
Vernevelaar Jet Ultrasoon Mesh
Vernevelaar Micromist Jet: Cirrus Micromist Hudson PARI Turbo Ultrasoon: Aeroneb Pro Endamed Micro 600 Pari turbo Ventstream pro
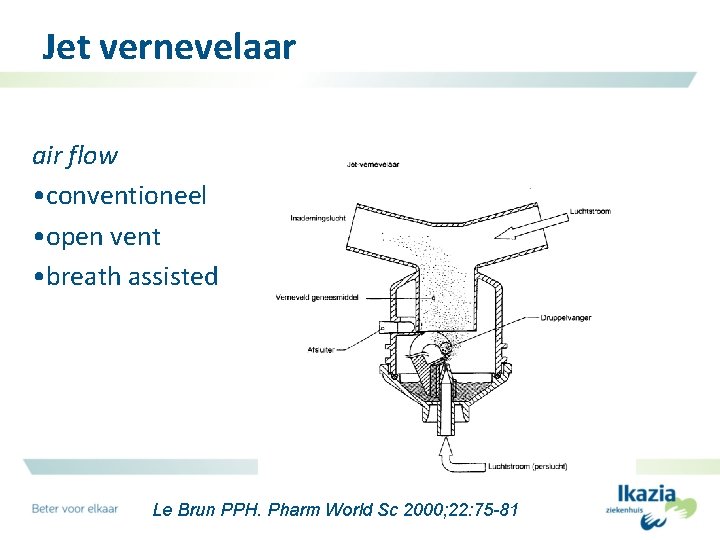
Jet vernevelaar air flow • conventioneel • open vent • breath assisted Le Brun PPH. Pharm World Sc 2000; 22: 75 -81
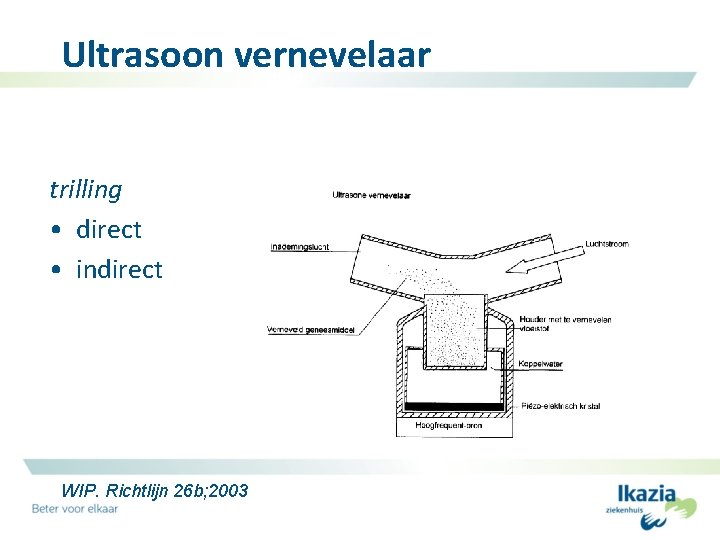
Ultrasoon vernevelaar trilling • direct • indirect WIP. Richtlijn 26 b; 2003
Mesh nebulizer Zeef Statische / vibrerende zeef
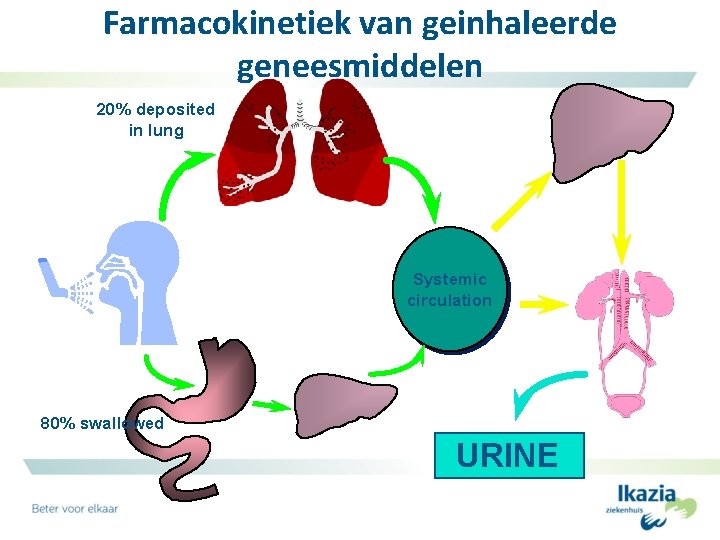
Farmacokinetiek van geinhaleerde geneesmiddelen 20% deposited in lung Systemic circulation 80% swallowed URINE
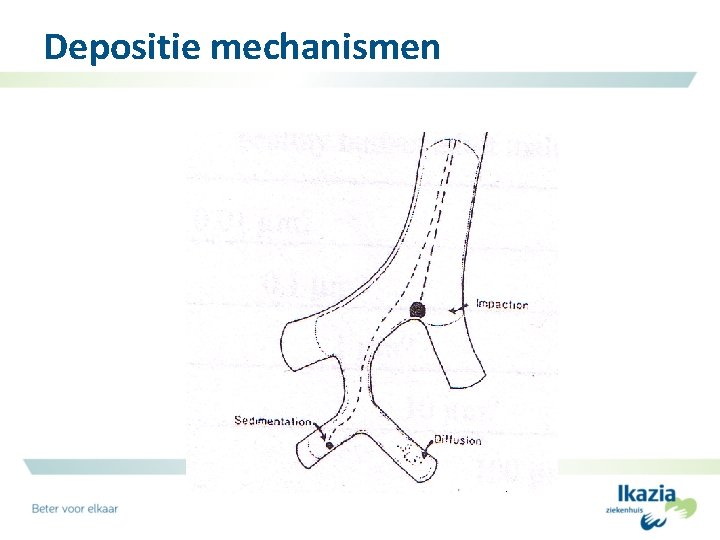
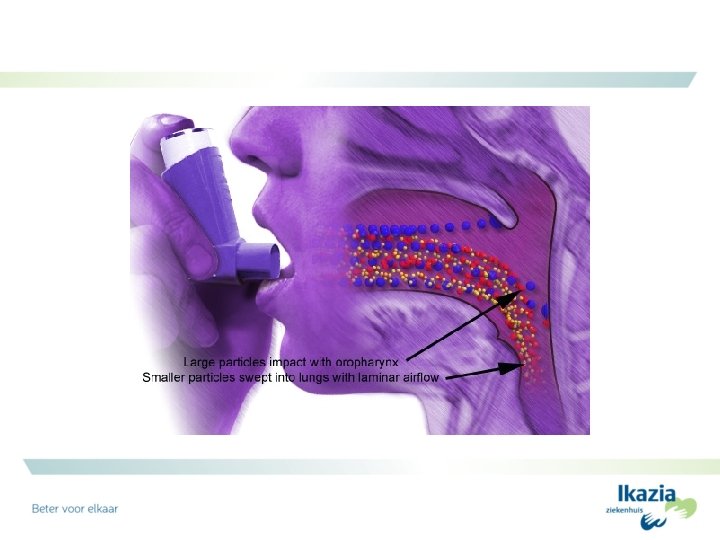
Depositie mechanismen
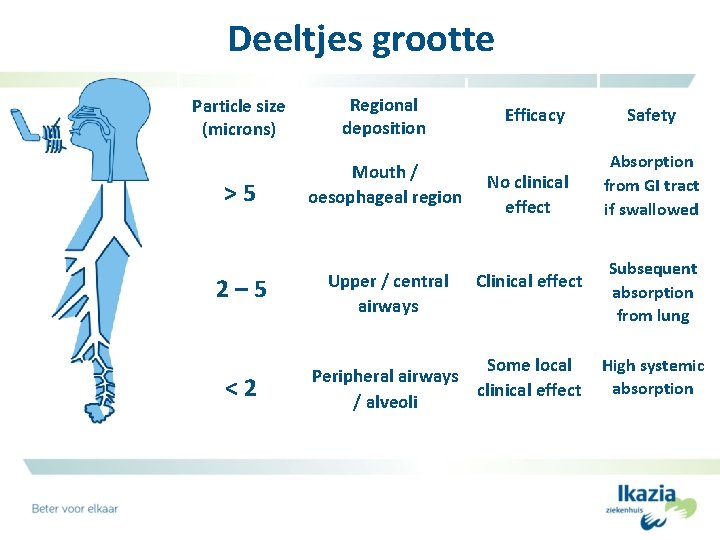
Deeltjes grootte Particle size (microns) Regional deposition >5 Mouth / oesophageal region 2– 5 Upper / central airways <2 Efficacy No clinical effect Clinical effect Some local Peripheral airways clinical effect / alveoli Safety Absorption from GI tract if swallowed Subsequent absorption from lung High systemic absorption
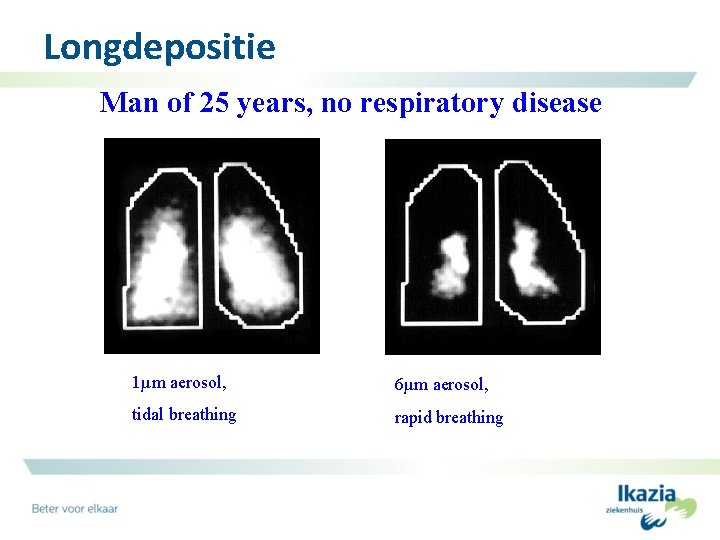
Longdepositie Man of 25 years, no respiratory disease 1µm aerosol, 6µm aerosol, tidal breathing rapid breathing
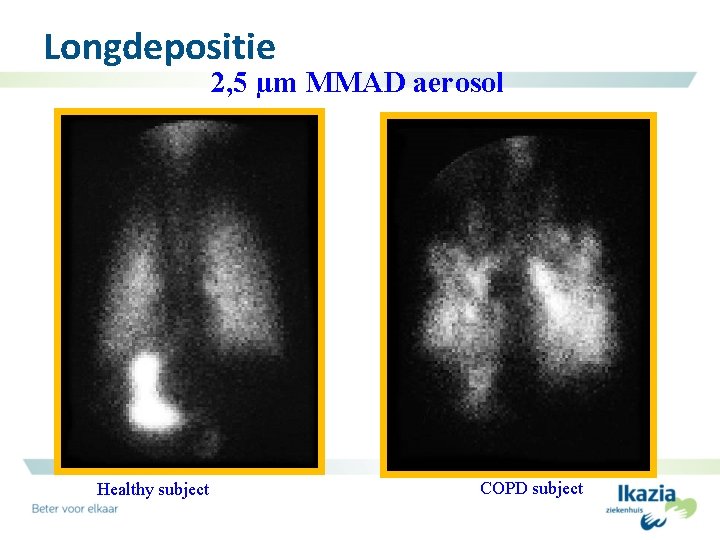
Longdepositie 2, 5 µm MMAD aerosol Healthy subject COPD subject
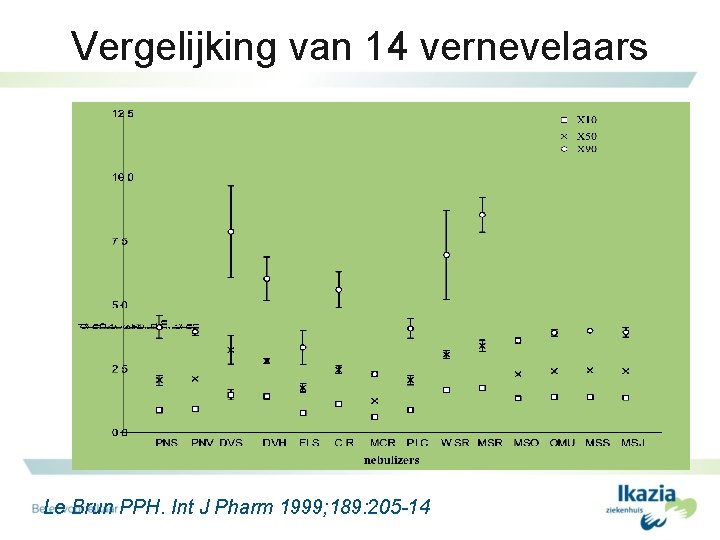
Vergelijking van 14 vernevelaars Le Brun PPH. Int J Pharm 1999; 189: 205 -14
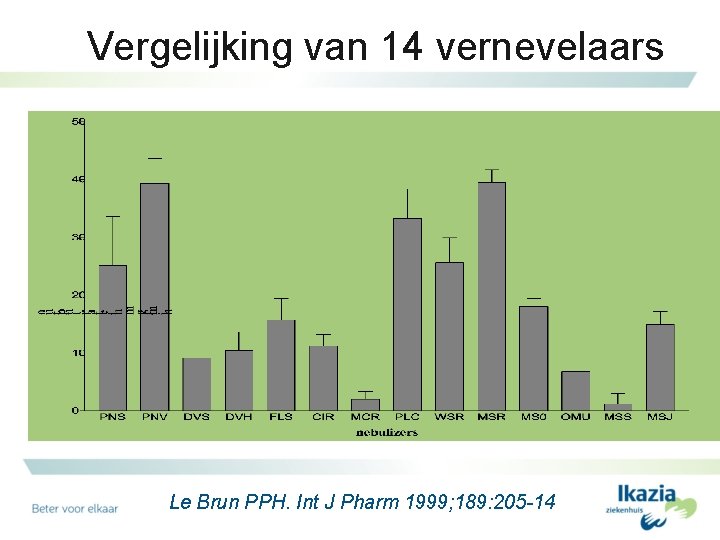
Vergelijking van 14 vernevelaars Le Brun PPH. Int J Pharm 1999; 189: 205 -14
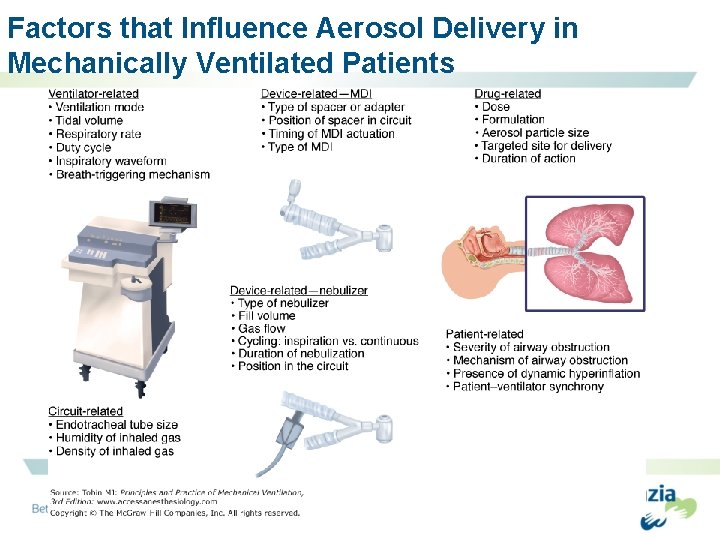
Factors that Influence Aerosol Delivery in Mechanically Ventilated Patients Dhand et al. , Respir Care 2004; 49: 611 -622
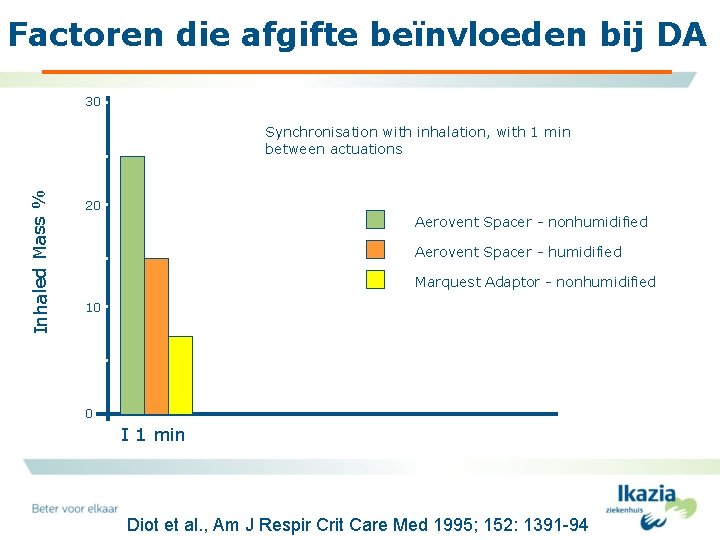
Factoren die afgifte beïnvloeden bij DA 30 Inhaled Mass % Synchronisation with inhalation, with 1 min between actuations 20 Aerovent Spacer - nonhumidified Aerovent Spacer - humidified Marquest Adaptor - nonhumidified 10 0 I 1 min Diot et al. , Am J Respir Crit Care Med 1995; 152: 1391 -94
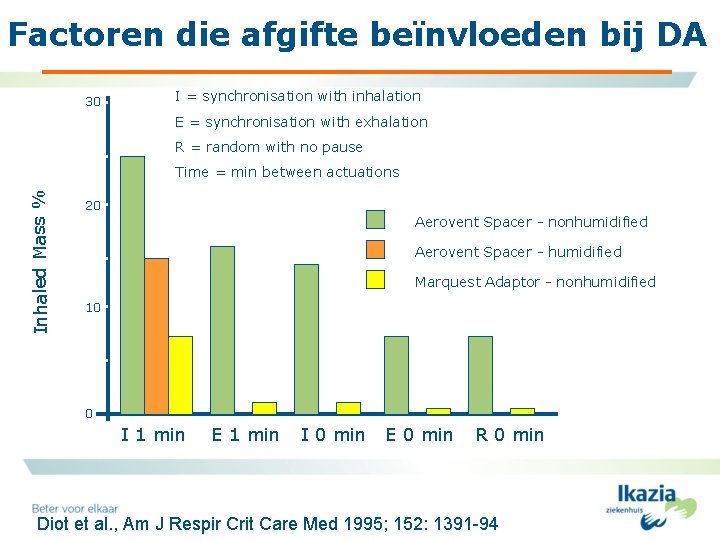
Factoren die afgifte beïnvloeden bij DA 30 I = synchronisation with inhalation E = synchronisation with exhalation R = random with no pause Inhaled Mass % Time = min between actuations 20 Aerovent Spacer - nonhumidified Aerovent Spacer - humidified Marquest Adaptor - nonhumidified 10 0 I 1 min E 1 min I 0 min E 0 min R 0 min Diot et al. , Am J Respir Crit Care Med 1995; 152: 1391 -94
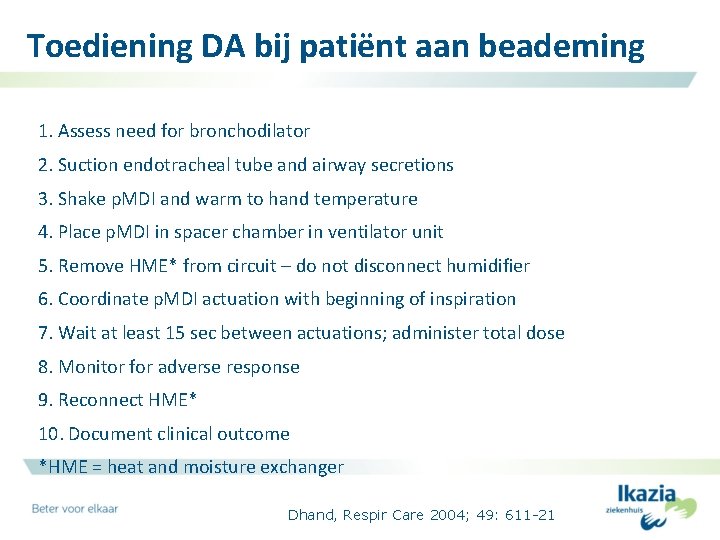
Toediening DA bij patiënt aan beademing 1. Assess need for bronchodilator 2. Suction endotracheal tube and airway secretions 3. Shake p. MDI and warm to hand temperature 4. Place p. MDI in spacer chamber in ventilator unit 5. Remove HME* from circuit – do not disconnect humidifier 6. Coordinate p. MDI actuation with beginning of inspiration 7. Wait at least 15 sec between actuations; administer total dose 8. Monitor for adverse response 9. Reconnect HME* 10. Document clinical outcome *HME = heat and moisture exchanger Dhand, Respir Care 2004; 49: 611 -21
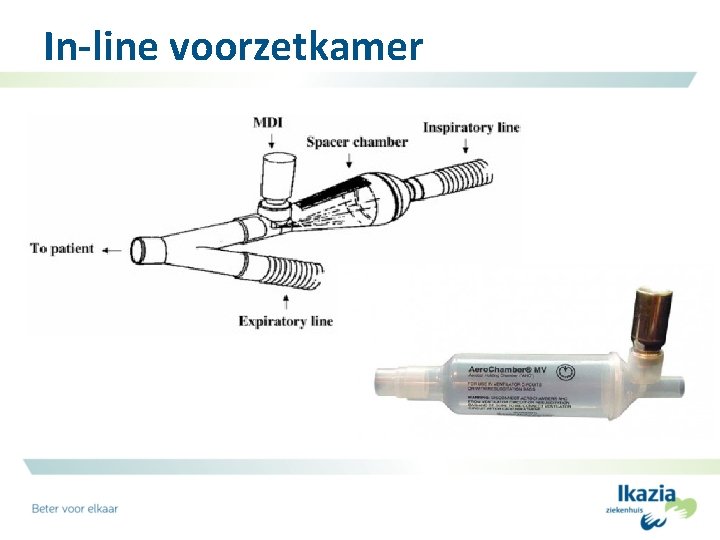
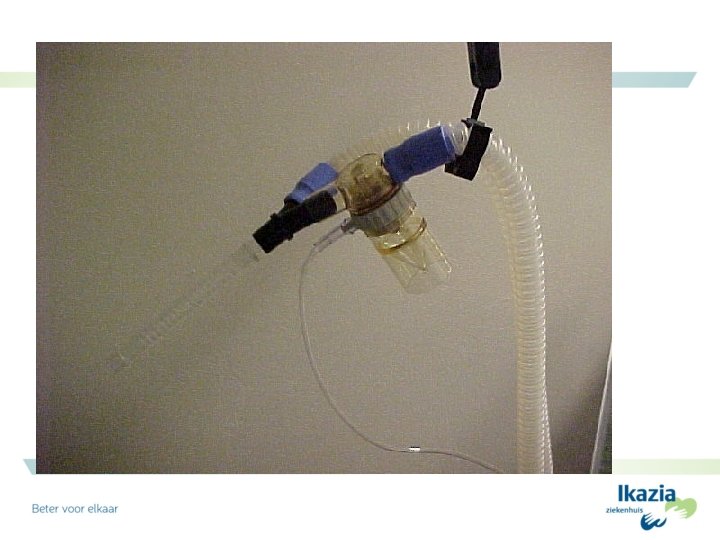
In-line voorzetkamer
Gebruik vernevelaar bij patiënt aan beademing 1. Assess need for bronchodilator 2. Suction endotracheal tube and airway secretions 3. Place drug in nebulizer to fill volume 4 -6 ml 4. Place nebulizer in the inspiratory limb (30 -40 cm from patient Y-piece) 5. Remove HME* from circuit – do not disconnect humidifier 6. Set gas flow to nebulizer at 6 -8 L/min a. use ventilator if it meets the nebulizer flow requirement and cycles on inspiration b. use continuous flow from an external source *HME = heat and moisture exchanger Dhand, Respir Care 2004; 49: 611 -21
Gebruik vernevelaar bij patiënt aan beademing 7. Adjust ventilator volume limit or pressure limit to compensate for flow added by nebulizer use a TV of > 500 ml and an flow of � 60 L/min 8. Tap nebulizer periodically until nebulizer begins to sputter 9. Remove nebulizer from circuit, rinse with sterile water, and run dry; store in safe place 10. Reconnect humidifier or HME* - return ventilator settings and alarms to previous values 11. Monitor for adverse response 12. Document clinical outcome *HME = heat and moisture exchanger Dhand, Respir Care 2004; 49: 611 -21
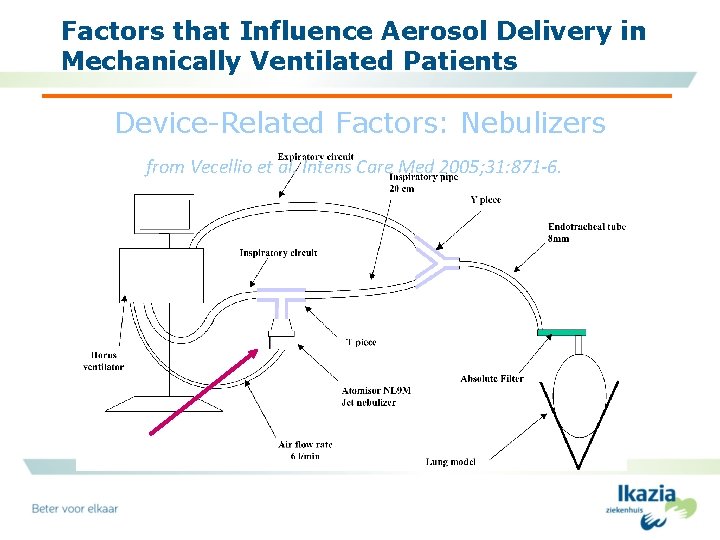
Factors that Influence Aerosol Delivery in Mechanically Ventilated Patients Device-Related Factors: Nebulizers from Vecellio et al. Intens Care Med 2005; 31: 871 -6.
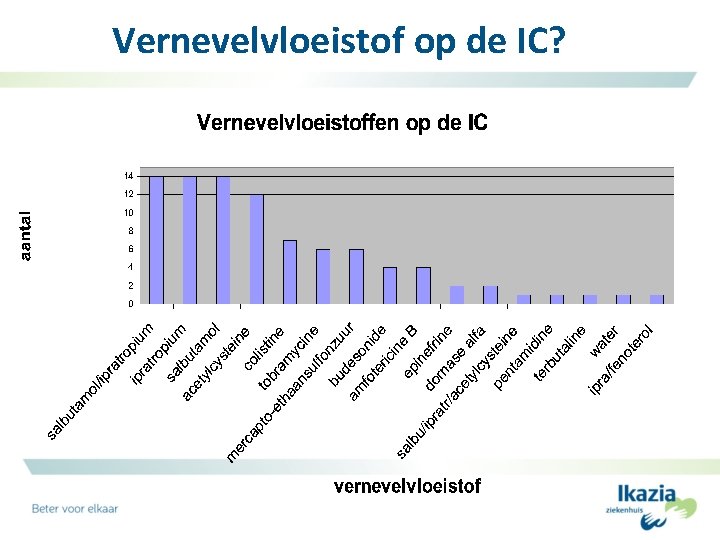
Vernevelvloeistof op de IC?
Indicaties Optimaliseren longfunctie, verdunnen/mobiliseren bronchiaal secreet; preventief of therapeutisch Astma (status astmaticus) COPD Cystic fibrosis SDD (S´P´D); P. Aeruginosa infectie (profylaxe) Pneumocystis Carinii pneumonie
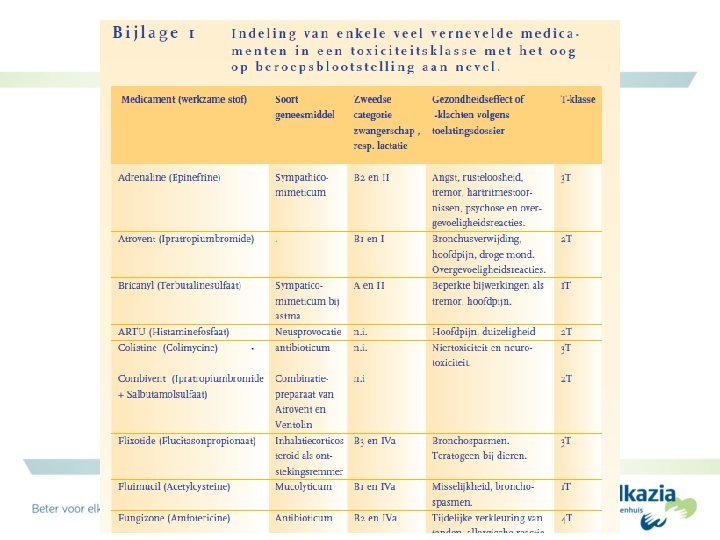
Antimicrobiele middelen per inhalatie • • Tobramycine Colistine Amfotericine Pentamidine gentamicine flucloxacilline ceftazidim
Geneesmiddelen per inhalatie Morfine / fentanyl (dyspnoe) Lidocaine Insuline (Exubera) Nicotinepuffer (electrospray)
Aspergillus fumigatus Blootstelling via sporen in de lucht Allergeen / symbiose Invasieve infectie bij immuungecomprimeerde patiënten
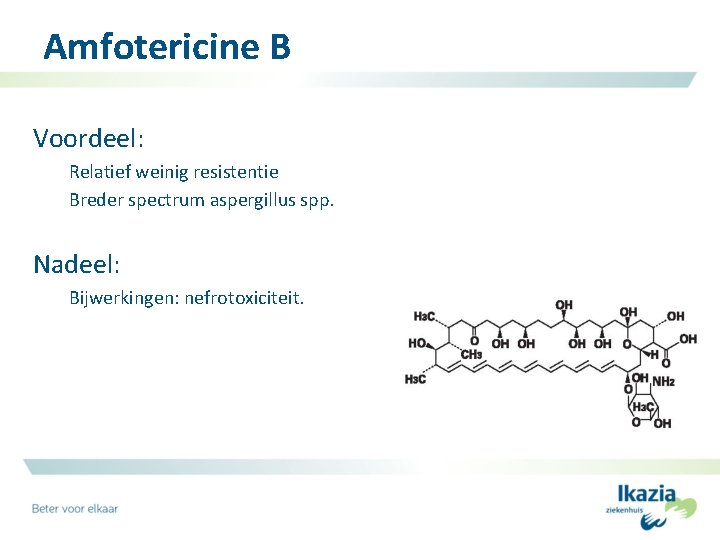
Amfotericine B Voordeel: Relatief weinig resistentie Breder spectrum aspergillus spp. Nadeel: Bijwerkingen: nefrotoxiciteit.
Reductie toxiciteit Lipide formuleringen: Am. Bisome (L-AMB) Abelcet (ABLC) Lokale toediening op plaats van werking: verneveld AMB
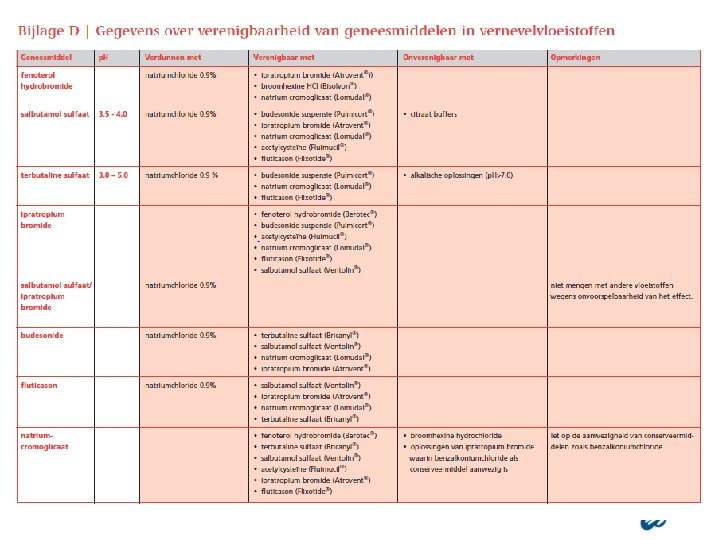
Mengen van vernevelvloeistoffen Salbutamol/ipratropiumbromide/acetylcysteine Ipratropium/fenoterol
C = compatible; N/A = not applicable; U/K = unknown; Alex Bailey, Welsh Medicines Information Centre, July 2005
Wordt er rekening gehouden met uitstoot in de omgeving? Risicoinventarisatie, protocol Uitstootfilter Mondkapje/mondmasker verpleging Gesloten systeem Ventilatie Isolatie













































