ICU Case Presentation King Faisal Specialist Hospital and

















- Slides: 42
ICU Case Presentation King Faisal Specialist Hospital and Research Center (2007 -1428) Manar Lashkar Samah Al-shehri Pharm. D candidates Supervised by: Dr. Mazen Kadri
• Hypertension affects > 65 million people in the United States and is one of the leading causes of death • One to two percent of patients with hypertension have acute elevations of BP that require urgent medical treatment 2 Manar & Samah
Hypertensive Crisis Degree of BP elevation Presence of end-organ damage 3 Manar & Samah
Outline Case Scenario Difference between hypertensive emergency and urgency Management of hypertensive crisis Special conditions of hypertensive crisis 4 Manar & Samah
24 years old single female with a history of • Systemic Lupus Erythrematosus (SLE) 8 years on steroid therapy Lupus nephritis • Multiple End Stage viral. Renal warts Disease (ESRD) As complication of lupus nephritis Leukopenia • Hemodialysis Hypertension(HD) (HTN) 3 times a week for the Not 6 compliant past months to restricted Na intake methyldopa stopped 2 months ago because of Planned for renal transplant the SLE like side effect 6 BP was controlled Manar on the medication & Samah
She was on SLE: • Prednisolone 5 mg PO OD ESRD: • Epoeitin 8000 units SC 3 times a week • Sevelamer 800 mg PO TID • One a 0. 25 mcg PO OD • Multivitamin 1 tab PO OD HTN: • Metoprolol 100 mg PO TID • Clonidine 200 mcg PO TID • Nifedipine LA 60 mg PO TID 7 Manar & Samah
Previous Investigations Ejection fraction = 55% (on 12/2007) ANA was positive 8 Manar & Samah (on 12/2007)
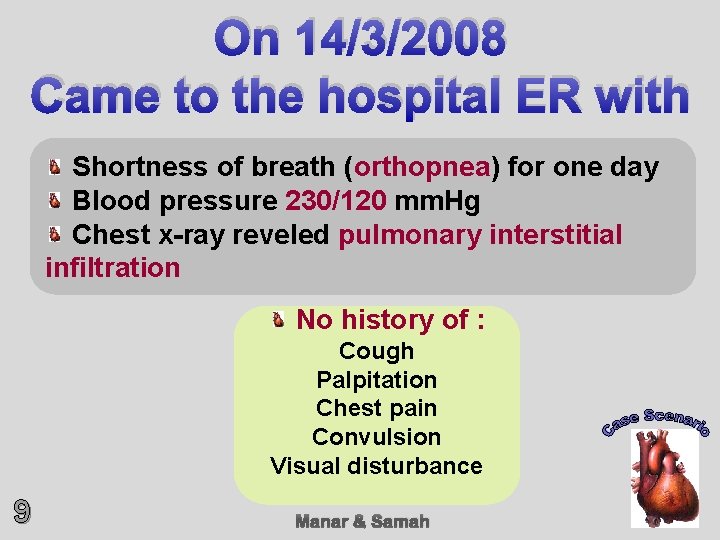
On 14/3/2008 Came to the hospital ER with Shortness of breath (orthopnea) for one day Blood pressure 230/120 mm. Hg Chest x-ray reveled pulmonary interstitial infiltration No history of : Cough Palpitation Chest pain Convulsion Visual disturbance 9 Manar & Samah
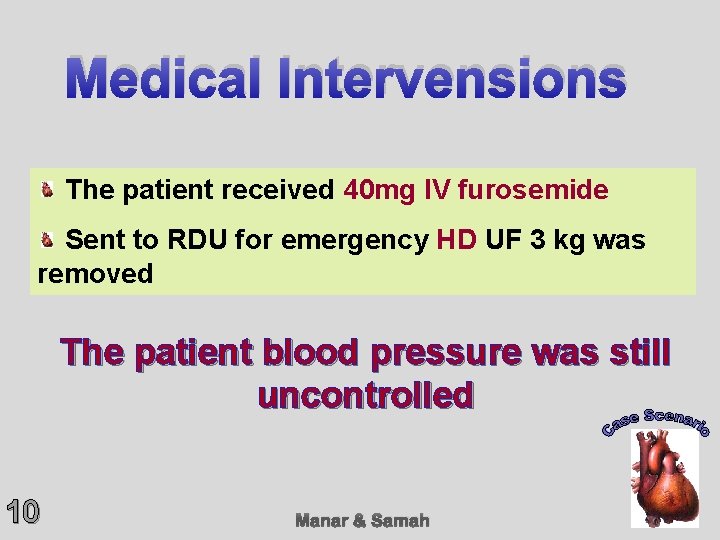
Medical Intervensions The patient received 40 mg IV furosemide Sent to RDU for emergency HD UF 3 kg was removed The patient blood pressure was still uncontrolled 10 Manar & Samah
In the ward Manar & Samah
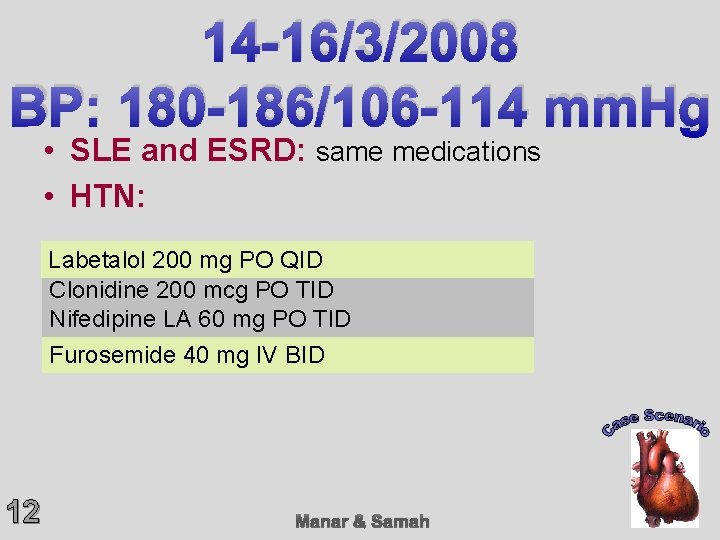
14 -16/3/2008 BP: 180 -186/106 -114 mm. Hg • SLE and ESRD: same medications • HTN: Labetalol Metoprolol 200 100 mg mg. PO POQID TID Clonidine 200 mcg PO TID Nifedipine LA 60 mg PO TID Furosemide 40 mg IV BID 12 Manar & Samah
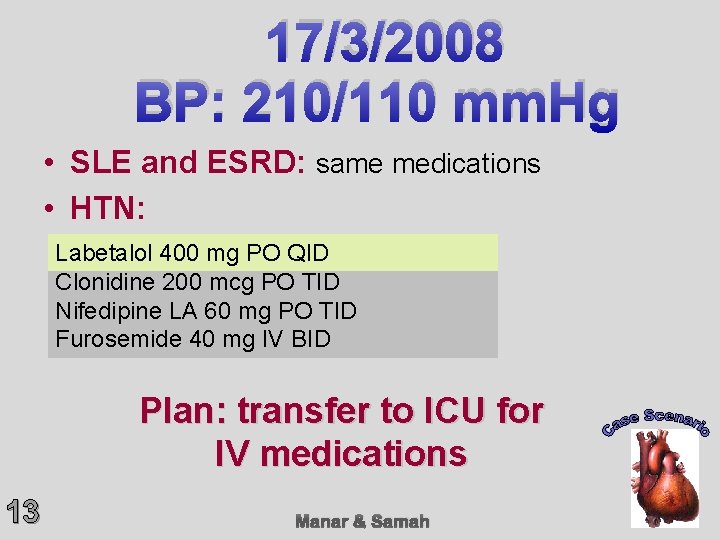
17/3/2008 BP: 210/110 mm. Hg • SLE and ESRD: same medications • HTN: Labetalol 400 200 mg PO QID Clonidine 200 mcg PO TID Nifedipine LA 60 mg PO TID Furosemide 40 mg IV BID Plan: transfer to ICU for IV medications 13 Manar & Samah
ICU Manar & Samah
ECG 15 Manar & Samah
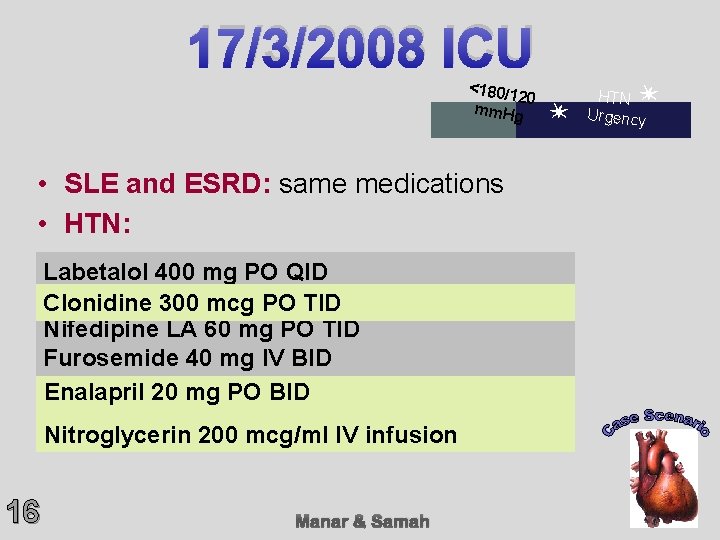
17/3/2008 ICU <180/12 mm. Hg • SLE and ESRD: same medications • HTN: Labetalol 400 mg PO QID 200 mcg PO TID Clonidine 300 Nifedipine LA 60 mg PO TID Furosemide 40 mg IV BID Enalapril 20 mg PO BID Nitroglycerin 200 mcg/ml IV infusion 16 Manar & Samah 0 HTN Urgency
18/3/2008 ICU BP: 130 -155/80 -95 mm. Hg • SLE and ESRD: same medications • HTN: Labetalol 400 mg PO QID Clonidine 300 mcg PO TID 60 mg PO TID Nifedipine LA 90 Furosemide 40 mg IV BID Enalapril 20 mg PO BID Nitroglycerin 200 mcg/ml IV infusion Plan: transfer to the floor 17 Manar & Samah
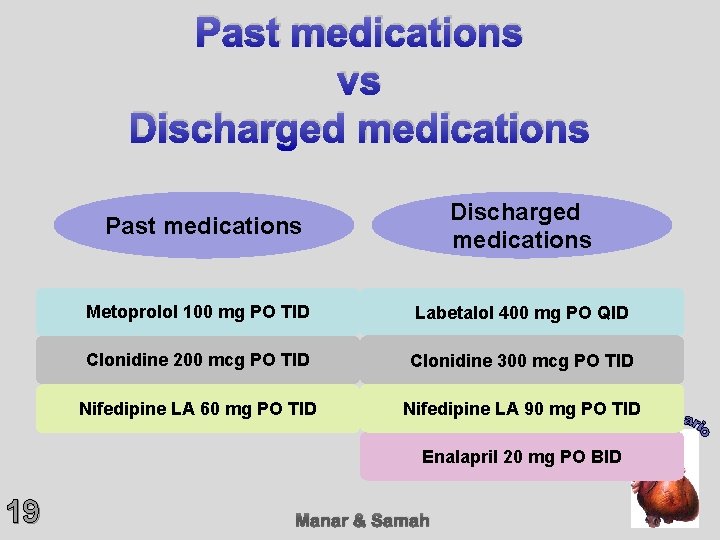
19/3/2008 BP: 134/92 mm. Hg The patient BP was controlled so the patient discharged on the same medications Labetalol 400 mg PO QID Clonidine 300 mcg PO TID Nifedipine LA 90 mg PO TID Enalapril 20 mg PO BID 18 Manar & Samah
Past medications vs Discharged medications Past medications Metoprolol 100 mg PO TID Labetalol 400 mg PO QID Clonidine 200 mcg PO TID Clonidine 300 mcg PO TID Nifedipine LA 60 mg PO TID Nifedipine LA 90 mg PO TID Enalapril 20 mg PO BID 19 Manar & Samah
Hypertensive Crisis 20 Manar & Samah
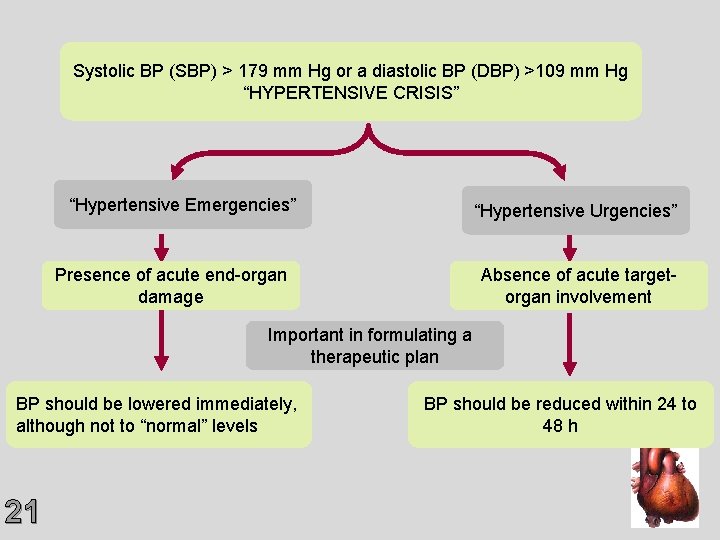
Systolic BP (SBP) > 179 mm Hg or a diastolic BP (DBP) >109 mm Hg “HYPERTENSIVE CRISIS” “Hypertensive Emergencies” “Hypertensive Urgencies” Presence of acute end-organ damage Absence of acute targetorgan involvement Important in formulating a therapeutic plan BP should be lowered immediately, although not to “normal” levels 21 BP should be reduced within 24 to 48 h
End Organ Damage • Hypertensive encephalopathy • Acute aortic dissection • Acute coronary syndrome • Pulmonary edema with respiratory failure • Severe pre-eclampsia, HELLP syndrome, eclampsia • Acute renal failure • Microangiopathic hemolytic anemia 22 Manar & Samah
Development of Hypertensive Emergency • The failure to adhere to prescribed antihypertensive regimens • Inadequate control of BP • The lack of a primary care physician 23 Manar & Samah
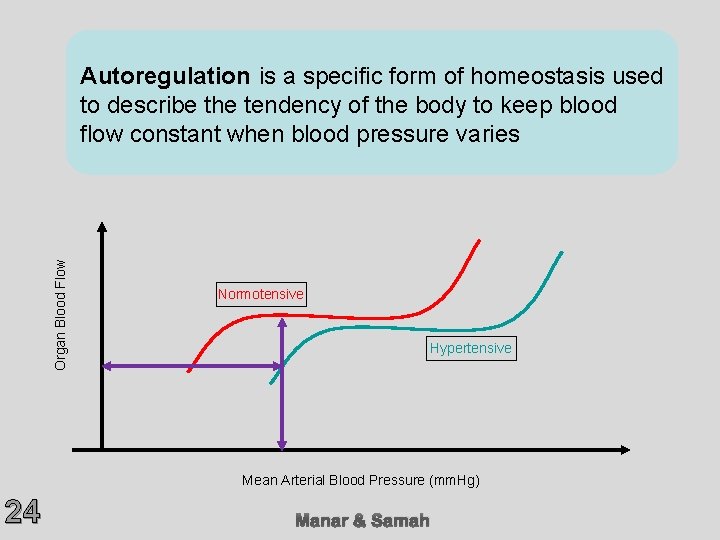
Organ Blood Flow Autoregulation is a specific form of homeostasis used to describe the tendency of the body to keep blood flow constant when blood pressure varies Normotensive Hypertensive Mean Arterial Blood Pressure (mm. Hg) 24 Manar & Samah
Managment • The preferred agents include labetalol, esmolol, nicardipine, and fenoldopam • Oral and sublingual nifedipine are potentially dangerous in patients with hypertensive emergencies and are not recommended • Clonidine and angiotensin-converting enzyme (ACE) inhibitors are long acting and poorly titratable 25 Manar & Samah
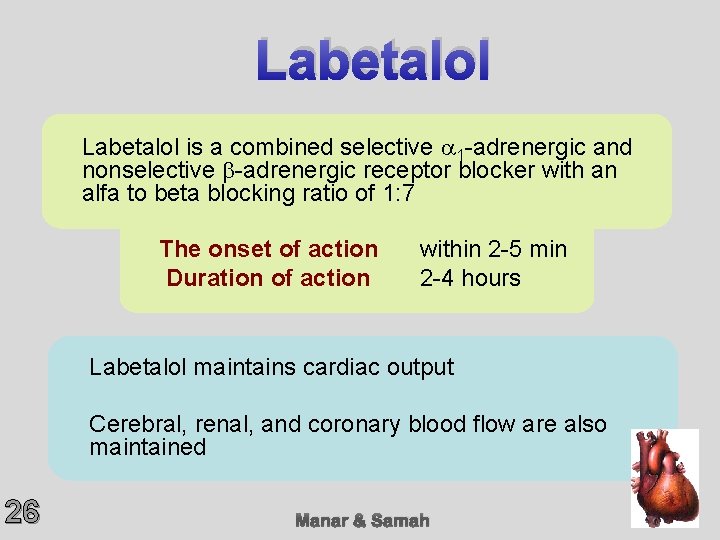
Labetalol is a combined selective a 1 -adrenergic and nonselective b-adrenergic receptor blocker with an alfa to beta blocking ratio of 1: 7 The onset of action Duration of action within 2 -5 min 2 -4 hours Labetalol maintains cardiac output Cerebral, renal, and coronary blood flow are also maintained 26 Manar & Samah
Nicardipine is a second-generation dihydropyridine derivative calcium-channel blocker with high vascular selectivity and strong cerebral and coronary vasodilatory activity The onset of action Duration of action within 5 -15 min 4 -6 hours IV nicardipine has been shown to reduce both cardiac and cerebral ischemia 27 Manar & Samah
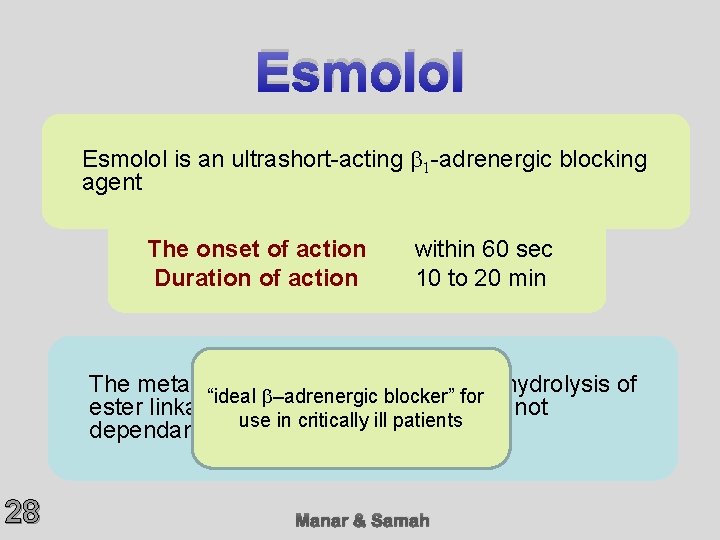
Esmolol is an ultrashort-acting b 1 -adrenergic blocking agent The onset of action Duration of action within 60 sec 10 to 20 min The metabolism of esmolol is via rapid hydrolysis of “ideal b–adrenergic blocker” for ester linkages by RBC esterases and is not in critically ill patients dependant on use renal or hepatic function 28 Manar & Samah
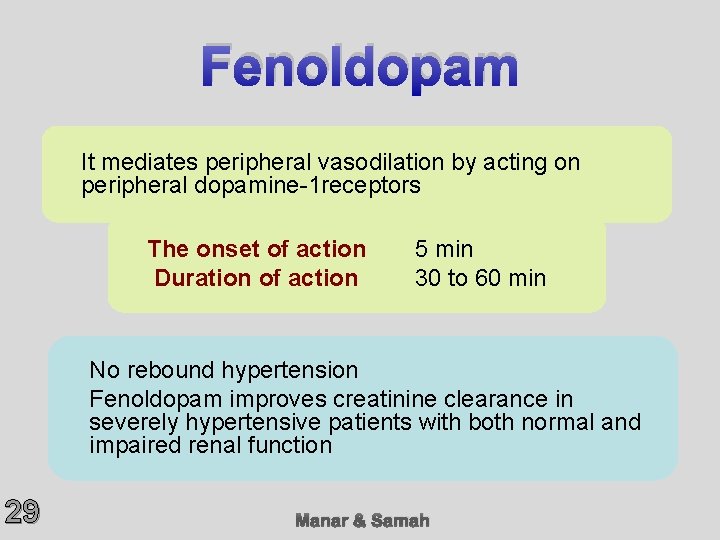
Fenoldopam It mediates peripheral vasodilation by acting on peripheral dopamine-1 receptors The onset of action Duration of action 5 min 30 to 60 min No rebound hypertension Fenoldopam improves creatinine clearance in severely hypertensive patients with both normal and impaired renal function 29 Manar & Samah
Nitroprusside It is a very potent arterial and venous vasodilator that decreases both afterload and preload The onset of action Duration of action seconds 1 to 2 min Factors limiting the use of nitroprusside: 30 • Intraarterial BP monitoring is recommended • It requires special precaution to prevent severe toxicity and adverse events • It requires special handling to prevent its degradation by light
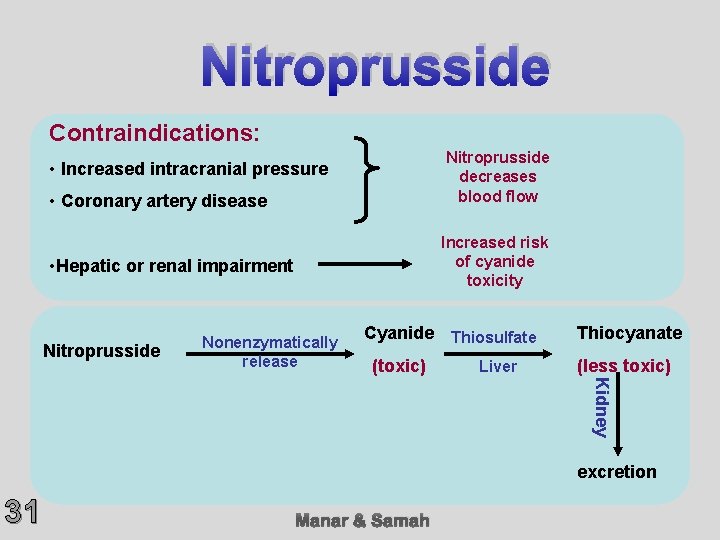
Nitroprusside Contraindications: Nitroprusside decreases blood flow • Increased intracranial pressure • Coronary artery disease Increased risk of cyanide toxicity • Hepatic or renal impairment Nitroprusside Nonenzymatically release Cyanide Thiosulfate (toxic) Liver Thiocyanate (less toxic) Kidney excretion 31 Manar & Samah
Nitroprusside Precautions: • The drug should only be used when other IV antihypertensive agents are not available and in certain circumstances and in patients with normal kidney and liver function • The duration of treatment should be as short as possible • infusion rate should not be > 2 mcg/kg/min 32 Manar & Samah
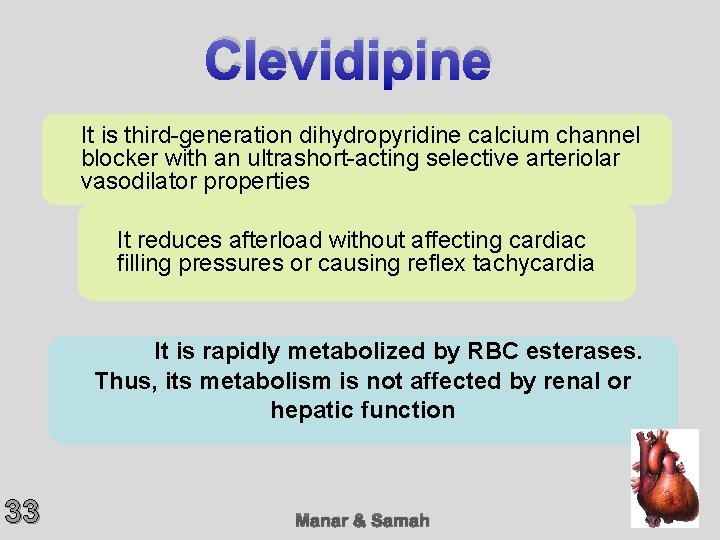
Clevidipine It is third-generation dihydropyridine calcium channel blocker with an ultrashort-acting selective arteriolar vasodilator properties It reduces afterload without affecting cardiac filling pressures or causing reflex tachycardia It is rapidly metabolized by RBC esterases. Thus, its metabolism is not affected by renal or hepatic function 33 Manar & Samah
Nifedipine It has been widely used via oral or sublingual administration in the management of hypertensive emergencies But 34 Sublingual Oral It is poorly soluble and is not absorbe through the buccal mucosa Rapidly absorbed from the GI tract after the is capsule This rout not FDA is broken or approved dissolved Manar & Samah
Nitroglycerin It is a potent venodilator and only at high doses affects arterial tone Nitroglycerin reduces BP by reducing preload and cardiac output It causes hypotension and reflex tachycardia Low-dose administration (60 mg/min) may be used as an adjunct to IV antihypertensive therapy in patients with hypertensive emergencies associated with acute coronary syndromes or acute pulmonary edema 35 Manar & Samah
Hydralazine It is a direct-acting vasodilator Following IM or IV administration, there is an initial latent period of 5 to 15 min followed by a progressive and often precipitous fall in BP that can last up to 12 h It is best avoided in the management of hypertensive crises 36 Manar & Samah
Special Conditions Manar & Samah
Acute Aortic Dissection Treatment: Vasodilator b-blocker 38 If vasodilator alone: Drug of Choice Alternative reflex tachycardia increase aortic ejection velocity Nicardipine Nitroprusside promote dissection propagation fenoldopam Esmolol Manar & Samah Metoprolol
Cerebrovascular Accidents Cerebral Ischemia withhold antihypertensive therapy for acute ischemic stroke unless • planned thrombolysis • evidence of concomitant noncerebral acute organ Cerebral Hemorrhage damage • if the BP is excessively high, a SBP 220 mm Hg or a DBP 120 mm 39 Manar & Samah
Cerebrovascular Accidents Cerebral Hemorrhage The controlled. Nicardipine lowering of BP is currently hasthe been recommended demonstratedonly to bewhen an effective agent for the in mm patients • control SBP isof>BP 200 Hg withisintracerebral • DBP > 110 mm Hg • MAPhemorrhage is > 130 mm Hg 40 Manar & Samah
Preeclampsia / Eclampsia Initial treatment for preeclampsia Magnesium sulfate for seizure prophylaxis Blood pressure control Nitroprusside and ACE inhibitors are contraindicated in pregnant patients IV labetalol or nicardipine Volume expansion 41 Manar & Samah
Summary • Hypertensive crisis is medical emergency that requires immediate treatment • Target-organ damage differentiates emergency versus urgency • Hypertensive emergency should be treated with parenteral medications of rapid onset of action and short duration • Blood pressure should not be rapidly reduced 42 Manar & Samah
Manar & Samah