ICCS Newsletter Case Study Interpretation CSI Identification of









- Slides: 35
ICCS Newsletter Case Study Interpretation (CSI) Identification of PNH Clones Andrea Illingworth, MS, H(ASCP), QCYM Dahl-Chase Diagnostic Services Bangor, ME aillingworth@dahlchase. com www. dahlchase. com
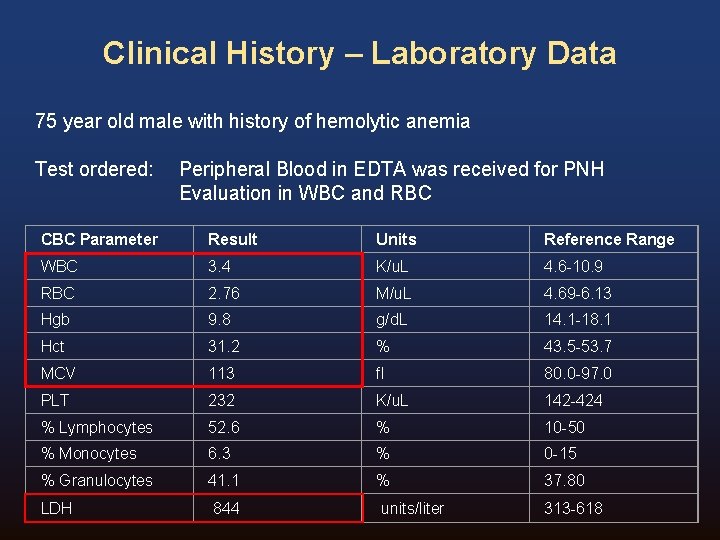
Clinical History – Laboratory Data 75 year old male with history of hemolytic anemia Test ordered: Peripheral Blood in EDTA was received for PNH Evaluation in WBC and RBC CBC Parameter Result Units Reference Range WBC 3. 4 K/u. L 4. 6 -10. 9 RBC 2. 76 M/u. L 4. 69 -6. 13 Hgb 9. 8 g/d. L 14. 1 -18. 1 Hct 31. 2 % 43. 5 -53. 7 MCV 113 fl 80. 0 -97. 0 PLT 232 K/u. L 142 -424 % Lymphocytes 52. 6 % 10 -50 % Monocytes 6. 3 % 0 -15 % Granulocytes 41. 1 % 37. 80 LDH 844 units/liter 313 -618
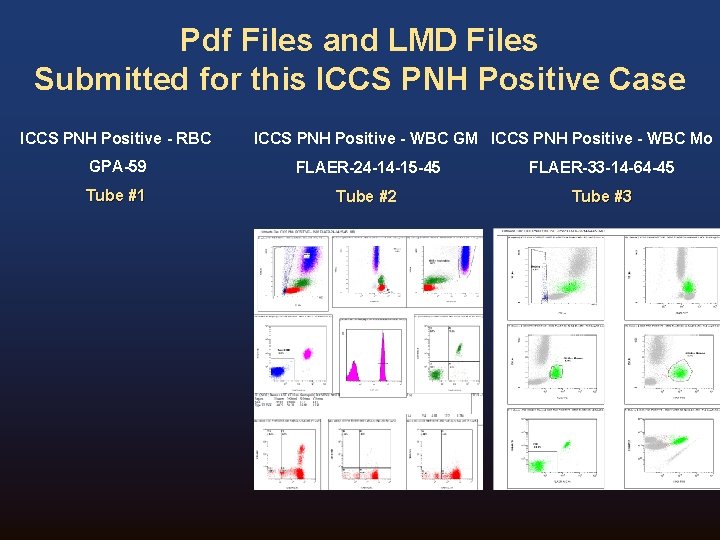
Pdf Files and LMD Files Submitted for this ICCS PNH Positive Case ICCS PNH Positive - RBC ICCS PNH Positive - WBC GM ICCS PNH Positive - WBC Mo GPA-59 FLAER-24 -14 -15 -45 FLAER-33 -14 -64 -45 Tube #1 Tube #2 Tube #3
The following slides will include: § Disease Overview and important preanalytical considerations for PNH Testing (slide 5 -13) § Case discussion of PNH Positive case – RBC Testing: Setup, analysis and QC (slide 14 -23) – WBC Testing: Setup, analysis and QC (slide 24 -31) § Interpretation and Reporting (slide 32 -33)
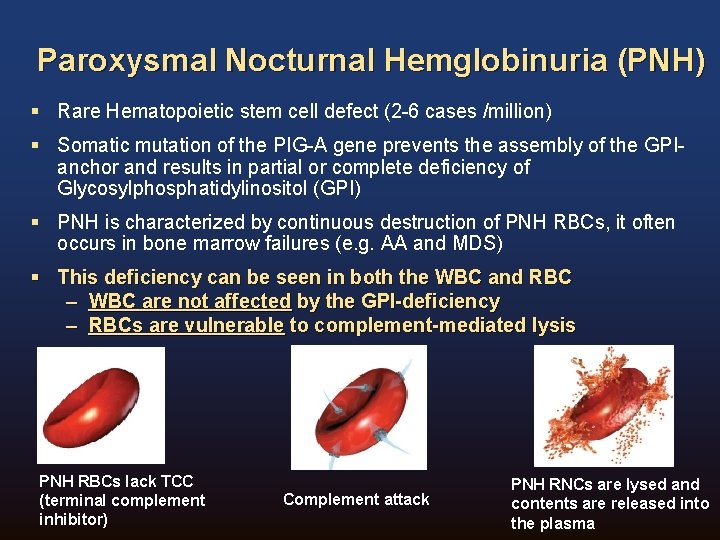
Paroxysmal Nocturnal Hemglobinuria (PNH) § Rare Hematopoietic stem cell defect (2 -6 cases /million) § Somatic mutation of the PIG-A gene prevents the assembly of the GPIanchor and results in partial or complete deficiency of Glycosylphosphatidylinositol (GPI) § PNH is characterized by continuous destruction of PNH RBCs, it often occurs in bone marrow failures (e. g. AA and MDS) § This deficiency can be seen in both the WBC and RBC – WBC are not affected by the GPI-deficiency – RBCs are vulnerable to complement-mediated lysis PNH RBCs lack TCC (terminal complement inhibitor) Complement attack PNH RNCs are lysed and contents are released into the plasma
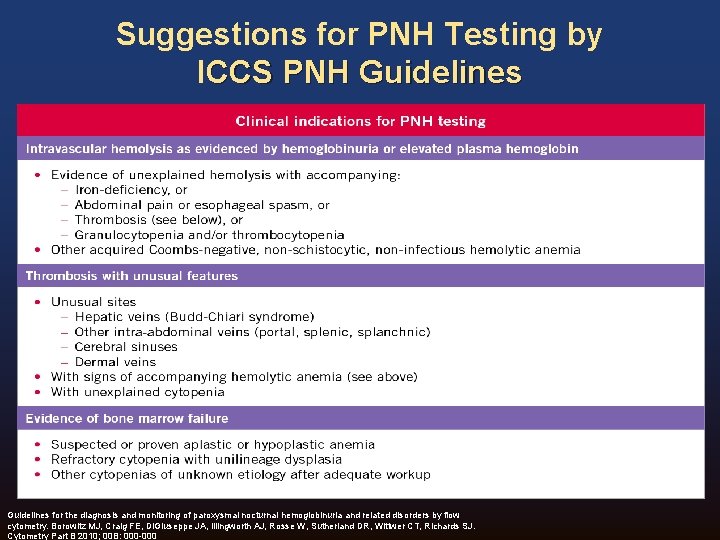
Suggestions for PNH Testing by ICCS PNH Guidelines for the diagnosis and monitoring of paroxysmal nocturnal hemoglobinuria and related disorders by flow cytometry. Borowitz MJ, Craig FE, Di. Giuseppe JA, Illingworth AJ, Rosse W, Sutherland DR, Wittwer CT, Richards SJ. Cytometry Part B 2010; 00 B: 000 -000
Diagnosis of PNH § Flow cytometry has become the “Method of Choice” in the “Method of Choice” detection of cells with GPI Deficiency (PNH clones) due its high accuracy and sensitivity down to 0. 01%) § Some GPI-linked antibodies are CD 55, CD 59, CD 14, CD 16, CD 24, CD 66 b and more recently FLAER § At least 2 GPI-linked antibodies must be absent for the diagnosis of PNH § Red blood cells, monocytes and granulocytes are mostly analyzed to detect PNH clones § Need for testing has become more important as there is an FDA-approved drug now to treat this disease
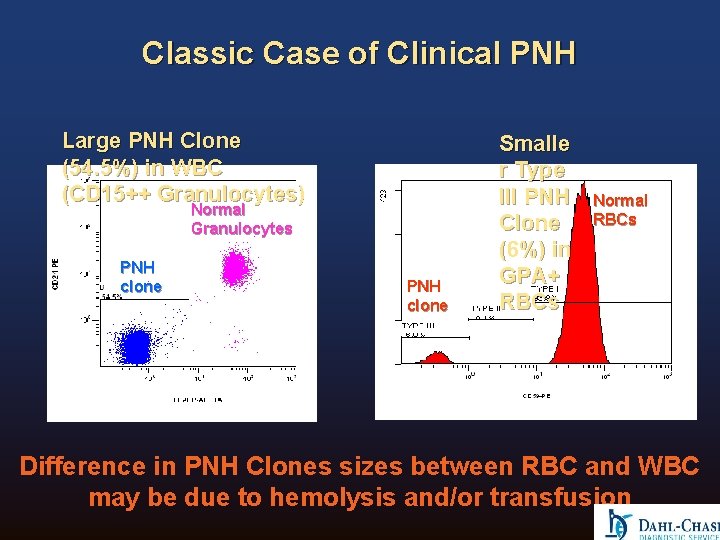
Classic Case of Clinical PNH Large PNH Clone (54. 5%) in WBC (CD 15++ Granulocytes) Normal Granulocytes PNH clone Smalle r Type III PNH Clone (6%) in GPA+ RBCs Normal RBCs Difference in PNH Clones sizes between RBC and WBC may be due to hemolysis and/or transfusion
Specimen Recommendations § Peripheral blood is the preferred specimen – Bone marrow is not desirable outside of the research setting because immature myeloid populations may express lower levels of GPI-anchored proteins making interpretation difficult § No data that any specific anticoagulant is necessary, though most experience has been with EDTA § Granulocyte analysis best performed in 24 -48 hrs because of degranulation; RBCs may be stable at 0 o for 7 days
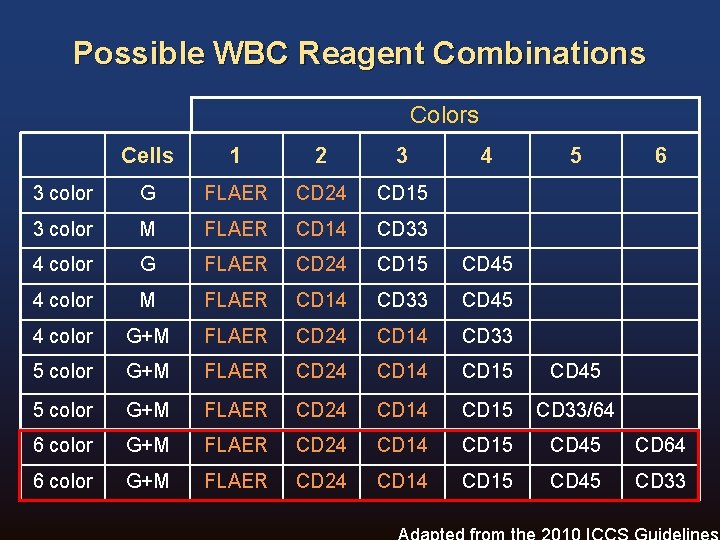
Possible WBC Reagent Combinations Colors Cells 1 2 3 4 5 6 3 color G FLAER CD 24 CD 15 3 color M FLAER CD 14 CD 33 4 color G FLAER CD 24 CD 15 CD 45 4 color M FLAER CD 14 CD 33 CD 45 4 color G+M FLAER CD 24 CD 14 CD 33 5 color G+M FLAER CD 24 CD 15 CD 45 5 color G+M FLAER CD 24 CD 15 CD 33/64 6 color G+M FLAER CD 24 CD 14 CD 15 CD 45 CD 33
Sensitive and Specific 5 -Color PNH Panel on 5 Color FC 500 in our Lab Current 5 C Panel Red Blood Cells: GPA-CD 59 Granulocytes and Monocytes: FLAER - CD 24 - CD 15 - CD 45 Monocytes only (Reflex): FLAER - CD 33 - CD 14 - CD 64 - CD 45 What are we looking for? What are we gating on to ensure high sensitivity and specificity? How many cells are typically counted? Red Blood Cells Absence of CD 59 expression GPA+ RBC’s only 50, 000 or more Granulocytes Absence of FLAER and CD 24 CD 15+ mature granulocytes/neutrophils 50, 000 or more Monocytes Absence of FLAER and CD 14 CD 64 or CD 33 Variable If a laboratory has 6 color capability, the following panels is suggested: FLAER / CD 24 / CD 15 / CD 45 / CD 64 (or CD 33) as it involves • FLAER/CD 24 to determine PNH cells (absence of both) in CD 15++ granulocytes/neutrophils • FLAER/CD 14 to determine PNH cells (absence of both) in CD 64++ (CD 33++) monocytes
Pre-analytical Considerations § Instrument Optimization – Appropriate Voltage adjustment • Cells positive for the antibody should show bright signal • Cells negative for the antibody need to be “on scale” – Optimize compensation settings • WBC: setting may be similar to Leukemia/lymphoma evals but need to be tweaked if using FLAER-Alexa 488 • RBC: need separation compensation setting § Reagent and Panel Selection – it is important to select the most Selection specific reagents with the best signal/noise ratio, e. g. – CD 59 is preferred over CD 55 for RBCs – FLAER/CD 24 for WBC-Granulocytes – FLAER/CD 14 for WBC-Monocytes – Antibodies should titered § Lineage specific gating increases sensitivity, e. g. gating – GPA (CD 235 a) for RBCs – CD 15 for granulocytes/neutrophils – CD 64 or CD 33 for monocytes
Pre-analytical Considerations – Quality Control § Validation of PNH Assay – Several normal peripheral blood samples should be run • To verify adequate staining of antibodies in normal cells • To determine the background and sensitivity of the Assay § PNH Surveys – NEQAS (UK) – CAP RBC and WBC Survey § Inter-laboratory comparisons of PNH+ samples (containing larger and Inter-laboratory comparisons smaller PNH clones) may help to improve confidence levels in the detection of PNH clones
PNH Testing - RBC Panel: CD 235 a(GPA)-FITC / CD 59 -PE (MEM 43 clone)
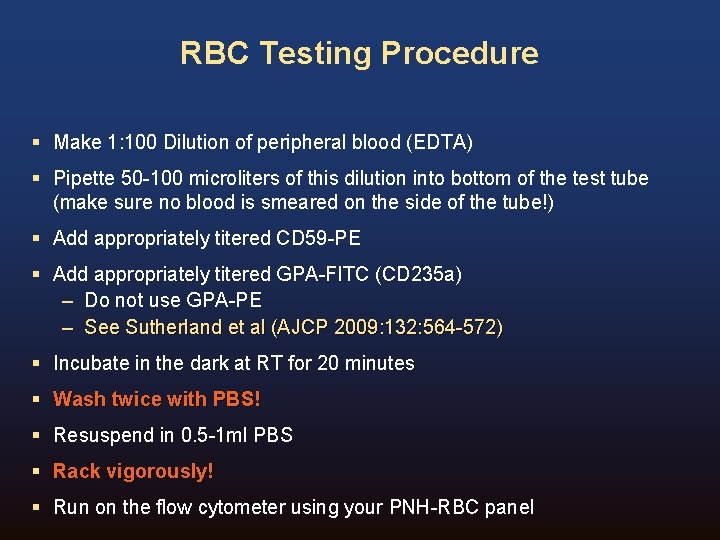
RBC Testing Procedure § Make 1: 100 Dilution of peripheral blood (EDTA) § Pipette 50 -100 microliters of this dilution into bottom of the test tube (make sure no blood is smeared on the side of the tube!) § Add appropriately titered CD 59 -PE § Add appropriately titered GPA-FITC (CD 235 a) – Do not use GPA-PE – See Sutherland et al (AJCP 2009: 132: 564 -572) § Incubate in the dark at RT for 20 minutes § Wash twice with PBS! § Resuspend in 0. 5 -1 ml PBS § Rack vigorously! § Run on the flow cytometer using your PNH-RBC panel
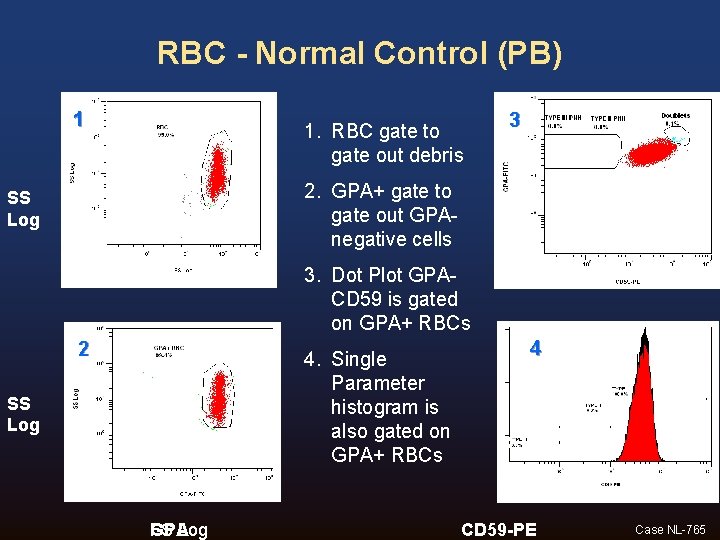
RBC - Normal Control (PB) 1 1. RBC gate to gate out debris 3 2. GPA+ gate to gate out GPAnegative cells SS Log 3. Dot Plot GPACD 59 is gated on GPA+ RBCs 2 4. Single Parameter histogram is also gated on GPA+ RBCs SS Log GPA FS Log 4 CD 59 -PE Case NL-765
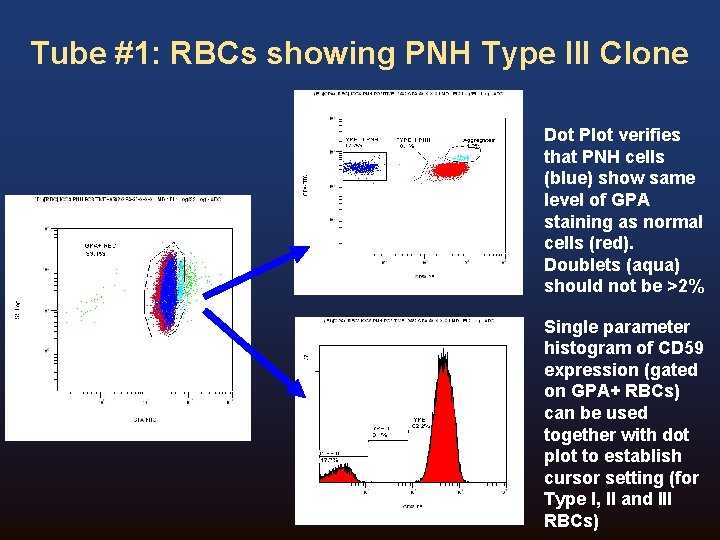
Tube #1: RBCs showing PNH Type III Clone Dot Plot verifies that PNH cells (blue) show same level of GPA staining as normal cells (red). Doublets (aqua) should not be >2% Single parameter histogram of CD 59 expression (gated on GPA+ RBCs) can be used together with dot plot to establish cursor setting (for Type I, II and III RBCs)
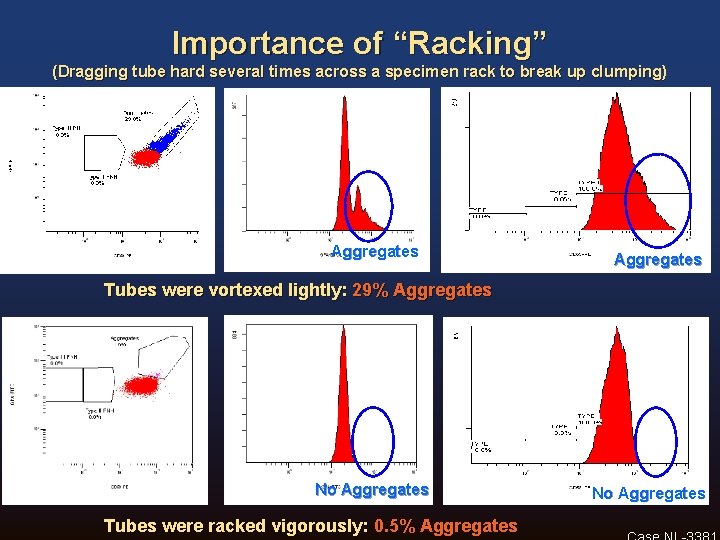
Importance of “Racking” (Dragging tube hard several times across a specimen rack to break up clumping) Aggregates Tubes were vortexed lightly: 29% Aggregates No Aggregates Tubes were racked vigorously: 0. 5% Aggregates No Aggregates
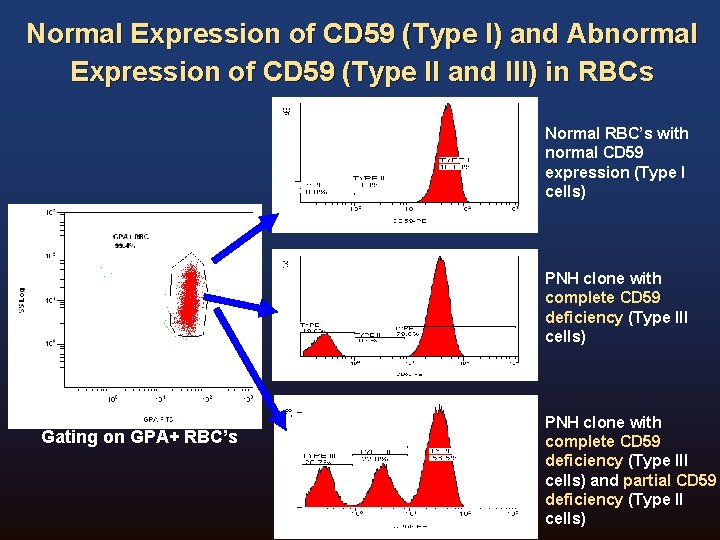
Normal Expression of CD 59 (Type I) and Abnormal Expression of CD 59 (Type II and III) in RBCs Normal RBC’s with normal CD 59 expression (Type I cells) PNH clone with complete CD 59 deficiency (Type III cells) Gating on GPA+ RBC’s PNH clone with complete CD 59 deficiency (Type III cells) and partial CD 59 deficiency (Type II cells)
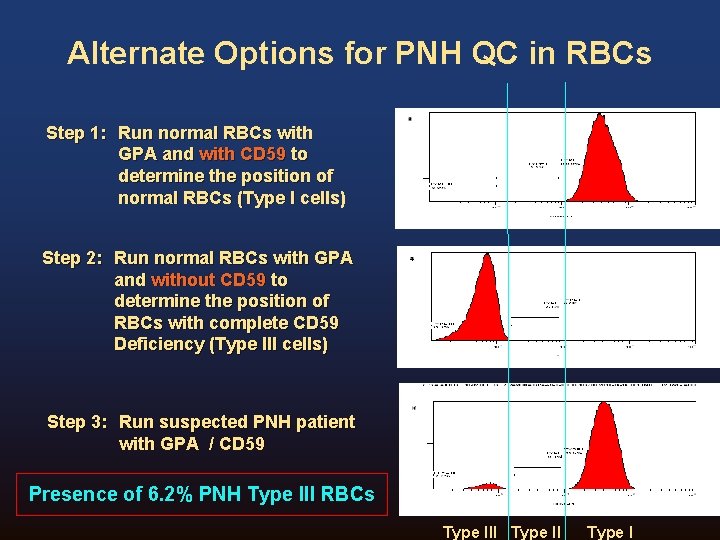
Alternate Options for PNH QC in RBCs Step 1: Run normal RBCs with GPA and with CD 59 to determine the position of normal RBCs (Type I cells) Step 2: Run normal RBCs with GPA and without CD 59 to determine the position of RBCs with complete CD 59 Deficiency (Type III cells) Step 3: Run suspected PNH patient with GPA / CD 59 Presence of 6. 2% PNH Type III RBCs Type III Type I
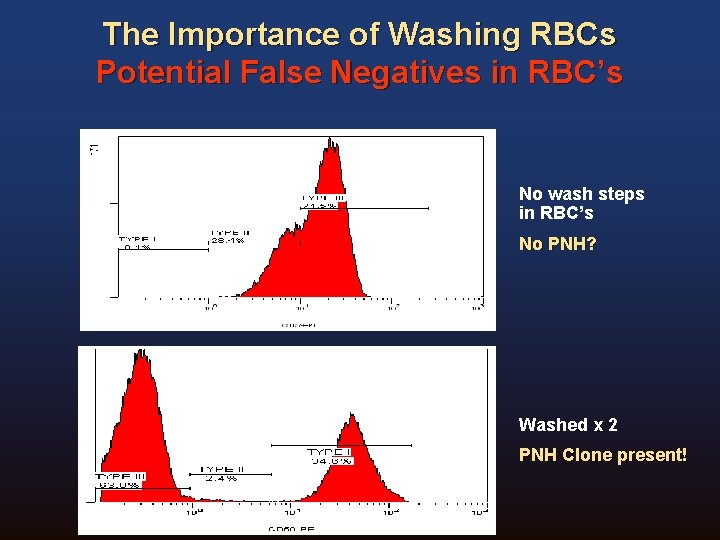
The Importance of Washing RBCs Potential False Negatives in RBC’s No wash steps in RBC’s No PNH? Washed x 2 PNH Clone present!
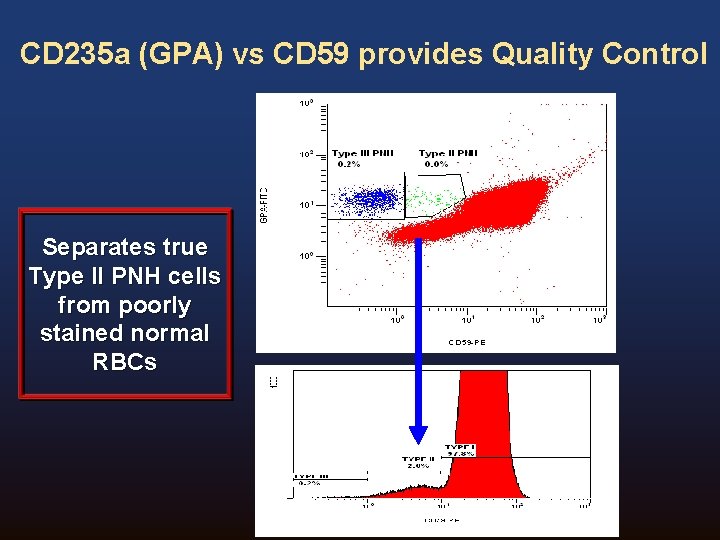
CD 235 a (GPA) vs CD 59 provides Quality Control Separates true Type II PNH cells from poorly stained normal RBCs
Summary - RBC § CD 235 a-FITC/CD 59 –PE is the preferred antibody combination with best signal/noise ratio – select most sensitive and specific clone (e. g. MEM 43 and p 282) – use CD 59 -PE preferably – addition of GPA (preferably FITC conjugate) results in higher sensitivities and cleaner RBC assays § Washing twice and “racking” is important! § Analysis of 50, 000 RBCs can result in sensitivity of 0. 05%-0. 1% (2550 PNH cells) in a clean assay § Difference in Clone size between RBC and WBC is important to determine hemolysis (RBC clone usually lower than WBC clone) § Report both Type II and Type III as the total PNH Clone if there is a separate Type II RBC population present
PNH Testing – WBC Panel • Granulocytes and Monocytes: FLAER - CD 24 - CD 14* - CD 15 - CD 45 • Monocytes only (Reflex): FLAER - CD 33** - CD 14 - CD 64** - CD 45
WBC Testing Procedure § Pipette 50 -100 microliters of peripheral blood (EDTA) into test tube § Add appropriately titered antibodies (rinse out antibody thoroughly) § Incubate in the dark at RT for 30 minutes § Lyse with your laboratory’s lysing reagent (e. g. Immunoprep, Optilyse, FACS Lyse, Ammonium Chloride etc. § Wash once with PBA § Resuspend in 0. 5 -1 ml of PBA § Run on the flow cytometer using your WBC-PNH panel
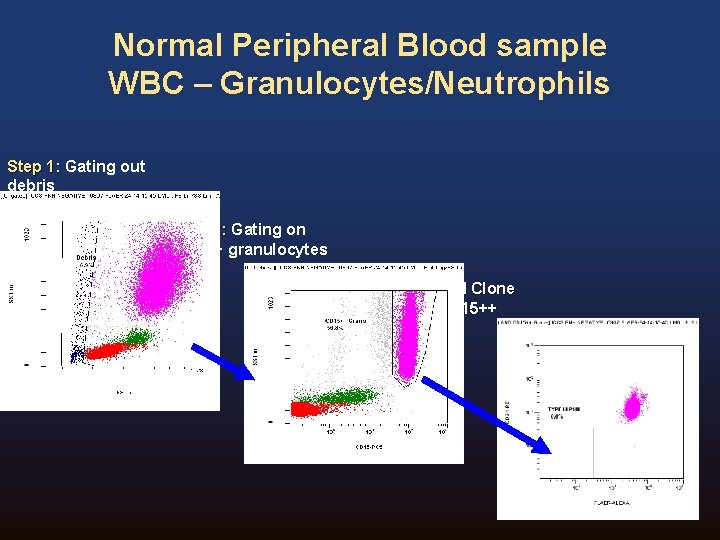
Normal Peripheral Blood sample WBC – Granulocytes/Neutrophils Step 1: Gating out debris Step 2: Gating on CD 15+ granulocytes Step 3: No PNH Clone detected in CD 15++ Granulocytes
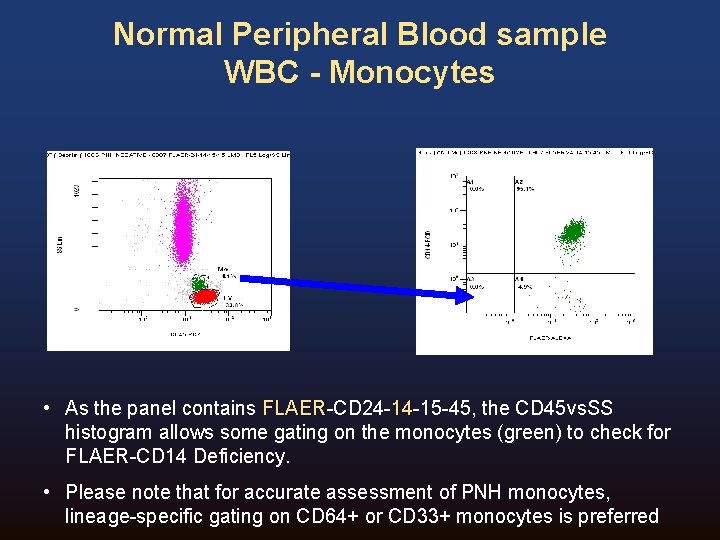
Normal Peripheral Blood sample WBC - Monocytes • As the panel contains FLAER-CD 2414 -15 -45, the CD 45 vs. SS FLAER 14 histogram allows some gating on the monocytes (green) to check for FLAER-CD 14 Deficiency. • Please note that for accurate assessment of PNH monocytes, lineage-specific gating on CD 64+ or CD 33+ monocytes is preferred
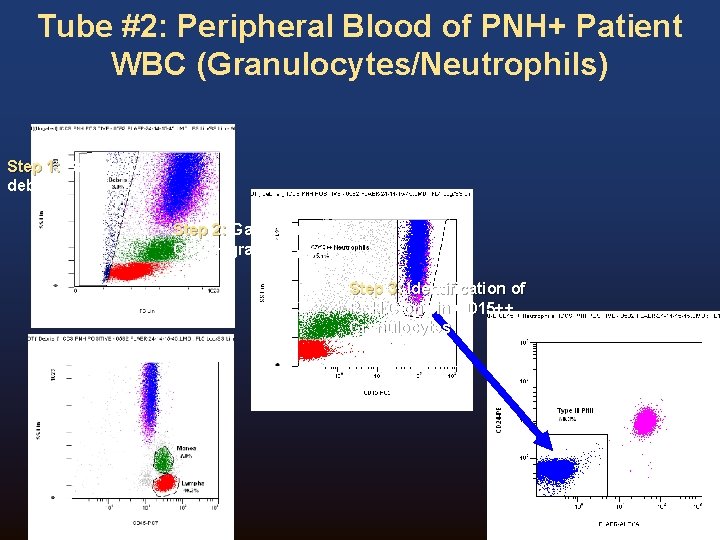
Tube #2: Peripheral Blood of PNH+ Patient WBC (Granulocytes/Neutrophils) Step 1: Gating out debris Step 2: Gating on CD 15+ granulocytes Step 3: Identification of PNH Clone in CD 15++ Granulocytes
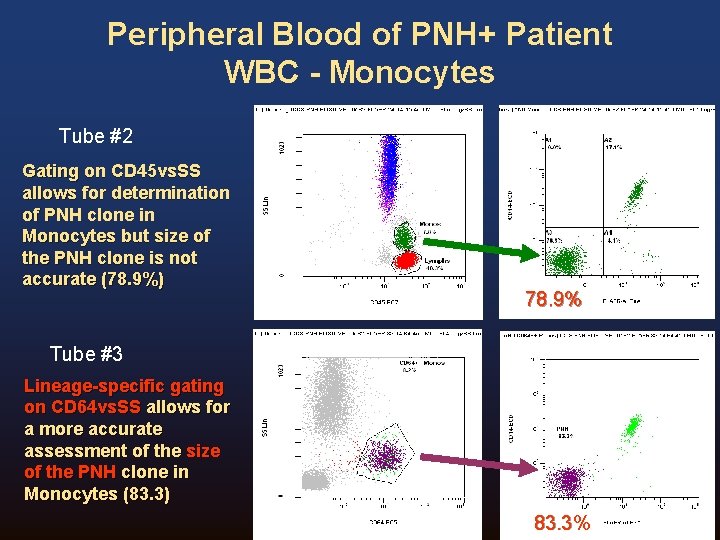
Peripheral Blood of PNH+ Patient WBC - Monocytes Tube #2 Gating on CD 45 vs. SS allows for determination of PNH clone in Monocytes but size of the PNH clone is not accurate (78. 9%) 78. 9% Tube #3 Lineage-specific gating on CD 64 vs. SS allows for a more accurate assessment of the size of the PNH clone in Monocytes (83. 3) 83. 3%
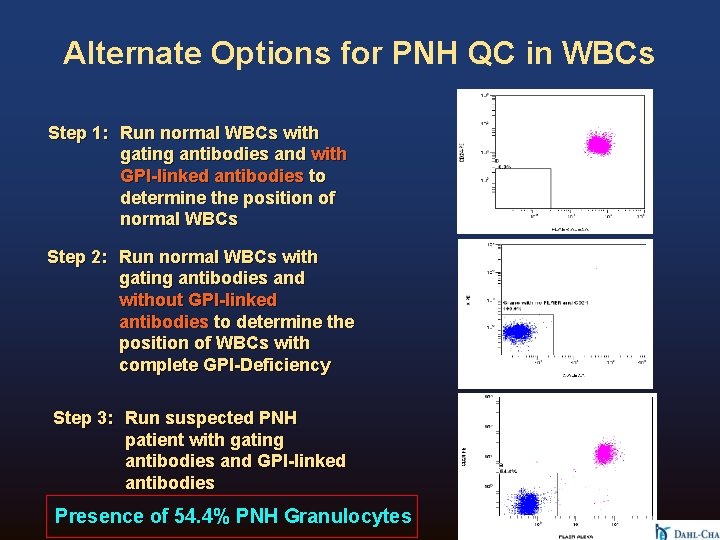
Alternate Options for PNH QC in WBCs Step 1: Run normal WBCs with gating antibodies and with GPI-linked antibodies to determine the position of normal WBCs Step 2: Run normal WBCs with gating antibodies and without GPI-linked antibodies to determine the position of WBCs with complete GPI-Deficiency Step 3: Run suspected PNH patient with gating antibodies and GPI-linked antibodies Presence of 54. 4% PNH Granulocytes
Summary - WBC § FLAER/CD 24 appears to be the preferred antibody combination to detect PNH clones in granulocytes § FLAER/CD 14 is most tested combination to detect PNH clones in monocytes § Lineage-specific gating results in higher sensitivities and cleaner WBC assays – CD 15 for granulocytes – CD 64 and/or CD 33 – CD 45 can be very useful for pattern-recognition (back-gating to see what the populations are, e. g. blasts, platelets, other immature cells, debris) § Analysis of 50, 000 granulocytes can result in sensitivity of 0. 05%-0. 1% (25 -50 PNH cells) in a clean assay § Report both Type II and Type III granulocytes and monocytes as the total PNH Clone if they are present
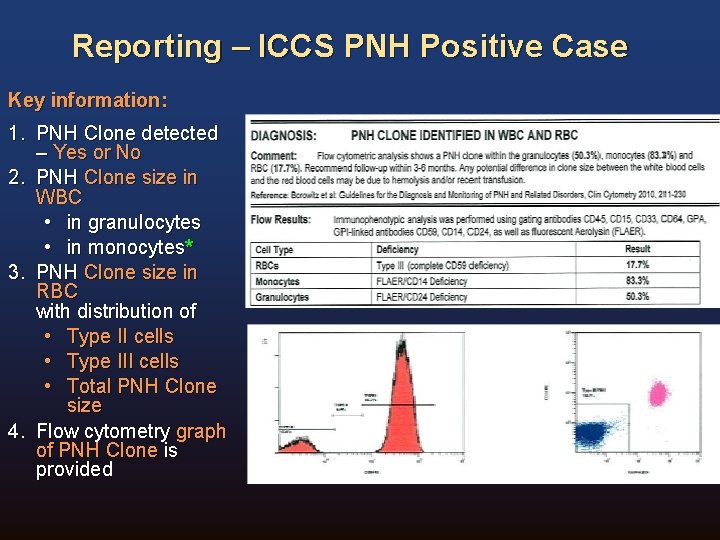
Reporting of PNH Results Recommended: § Report clone sizes in all populations tested (RBCs, granulocytes and possibly monocytes) § Report Type II and Type III RBCs as well as Type II and Type III granulocytes (even though their significance is not established) § Repeat samples on same patient should comment on change in size of PNH clone § Provide histograms if possible § Report level of sensitivity Avoid: § Reporting reactivity with each individual marker § Avoid ambiguous (“positive versus negative”) language – e. g. “CD 59 test is Negative” may mean to some that CD 59 is negative and therefore positive for PNH § Don’t over-interpret small clones as evidence of hemolytic PNH
Reporting – ICCS PNH Positive Case Key information: 1. PNH Clone detected – Yes or No 2. PNH Clone size in WBC • in granulocytes • in monocytes* 3. PNH Clone size in RBC with distribution of • Type II cells • Type III cells • Total PNH Clone size 4. Flow cytometry graph of PNH Clone is provided
Acknowledgements § To all the PNH Experts who have helped us along on this journey towards Best Practices in PNH Testing – Dr. Robert Sutherland – Dr. Stephen Richards – Dr. Michael Borowitz – Dr. Wendell Rosse – Dr. Bruce Davis – And many others…… Thank you!
The Flow Cytometry Team Back: Medical Technologists Ashley B, Tony K, Brie S, Neisha B and Monica G Front: Medical Director M Movalia MD, Operational Director A Illingworth and S Du. Fresne MD