I 1 Hemophilia Factor VIII def Classic Hemophilia




























- Slides: 39
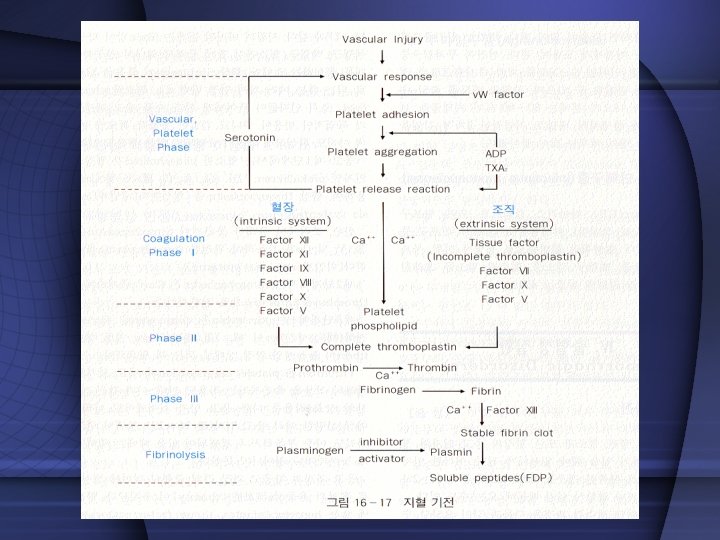
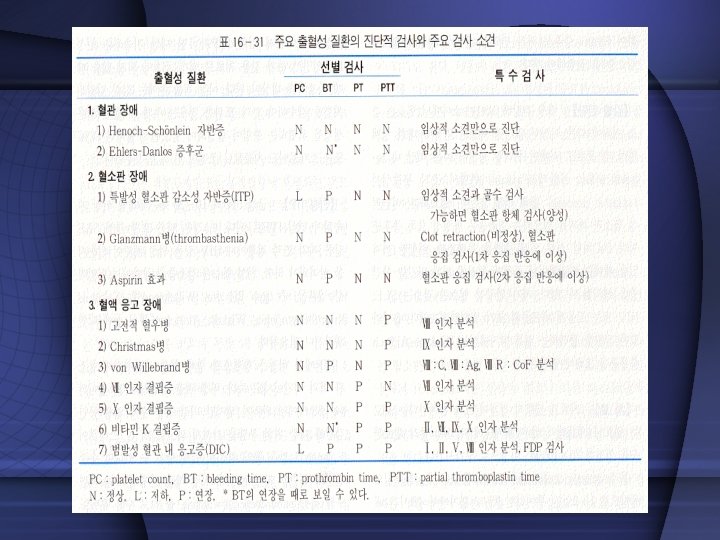
I. 선천성 혈액응고인자 결핍증 1. Hemophilia * Factor VIII def. ( Classic Hemophilia, Hemophilia A) * Factor IX def. ( Hemophilia B, Christmas dis. ) * Factor XI def. (Hemophilia C) 2. 기타 선천성 결핍증 1) Afibrinogenemia, Dysfibrinogenemia 2) Hypoprothrombinemia 3) factor V def. (Parahemophilia) 4) factor VII def. 5) factor X def. 6) factor XII def. 7) factor XIII def. 8) PK. HMWK 결핍증. II. 후천적 혈액응고인자 결핍증
Hemophilia • Cong. Coagulation disorder의 흔한 원인. • Factor VIII, IX, XI의 결핍과 관련.
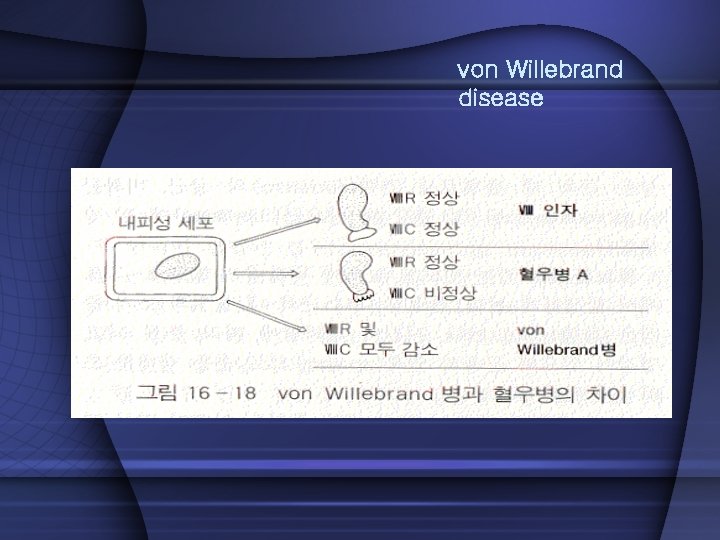
Hemophilia A (Factor VIII deficiency) • 전체 hemophilia중 80% • defective gene on the X chromosome • Pt with hemophilia and carrier women – reduced factor VIII activity • normal plasma level of von Willebrand protein – Cf. ) von Willebrand dis. 에선 둘다 감소. • normal person – plasma ratio of factor VIII activity to von Willebrand protein • most female carrier<1 • familial Hx: positive in 80%.
Hemophilia A Clinical severity • • Severe <1% of normal activity Moderate 1 -5% Mild 6 -30% Normal 50 -150%
Hemophilia A Clinical manifestation • ambulation을 시작하는 시기 severe case의 90%에서 1세전까지 clinical bleeding • hemarthrosis : hallmark of hemophilia • factor VIII activity > 6% -> no spontaneous symptoms
Hemophilia A Lab finding • PTT ↑ • PT, PLT count : normal • confirm : specific assay for factor VIII activity
Hemophilia A Treatment 1) prevention of trauma 2) aspirin and other drug that affect PLT function->avoid! 3) immunization against HBV 4) Replacement therapy
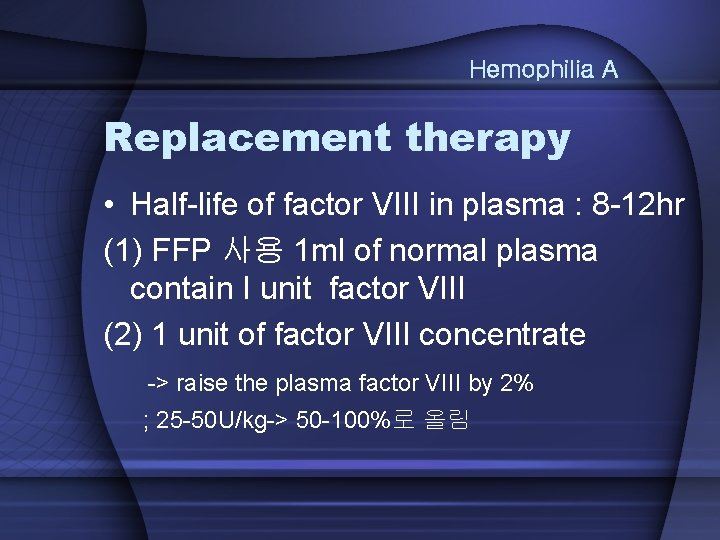
Hemophilia A Replacement therapy • Half-life of factor VIII in plasma : 8 -12 hr (1) FFP 사용 1 ml of normal plasma contain I unit factor VIII (2) 1 unit of factor VIII concentrate -> raise the plasma factor VIII by 2% ; 25 -50 U/kg-> 50 -100%로 올림
Hemophilia A (3) 1 bag of cryoprecipitate ; 75 -125 U of factor VIII – * New factor VIII concentrate prepared by monoclonal antibody technique and recombinant – More expensive – Safer with regard to transmission of infection
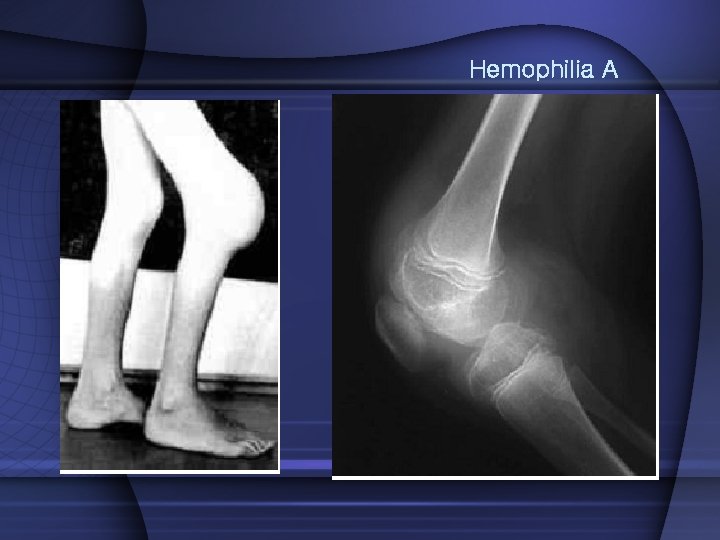
Hemophilia A (4) Hemarthrosis – factor VIII 50%로 올리고 48 -72 hr 동안 최소 5% 이 상으로 유지. – Initial immobilization ->passive exercise within 48 hr to prevent joint stiffness and fibrosis – hemorrhage in vital areas or prior to op. • : 2주 동안 50% 이상 올려서 유지해야. – oral mucosa의 출혈. Or tooth extraction • ; EACA( epsilon aminocaproic acid)를 50 -100 mg q 6 hr 로 같이 투여하여 응고 인자 투여량을 감량.
Hemophilia A Long term Cx. 1. 2. 3. 4. 5. abnormal Hepatic enzyme activity CAH and cirrhosis Hepatitis B & C AIDS HTN, renal dis.
Hemophilia A
Hemophilia A Prenatal Dx. • carrier mother -> male fetus ; 50% risk • fetal plasma assay. • Markedly higher von Willebrand protein level • compared to the factor VIIIc level.
Hemophilia B • • factor IX def. liver에서 생산. Vit K dependent 12 -15% of Hemophilia 임상적으로는 Hemophilia A 와 구분하기 어렵 다. • Joint와 muscle hemorrhage가 특징적. • Tx : 1 unit/Kg-> 1. 0 -1. 2%를 올림. -> 100%올리기 위해 100 unit/Kg
Hemophilia C • 2 -3% • incomplete autosomal recessive • Tx – 반감기 40 -80 hr. – FFP 10 -15 ml/Kg every 24 hr.
von Willebrand disease (pseudohemophilia, vascular hemophilia) • • H. A> v. WD> H. B Autosomal dominant caused by underproduction of von. Willebrand protein.
von Willebrand disease
Lab finding von Willebrand disease • BT – prolonged, • PTT – may be normal but usually mildly to moderately prolonged. • Type I – reduced plasma level of von-Willebrand protein, von. Willebrand's factor activity and factor VIII activity • platelet in von-Willebrand dis. – adhesiveness – Do not aggregate when the antibiotic ristocetin is added to platelet rich plasma
Tx. von Willebrand disease 1) FFP 2) cryoprecipitate (2 -4 bags/10 Kg every 12 -24 hrs) 3) DDAVP; in mild cases.
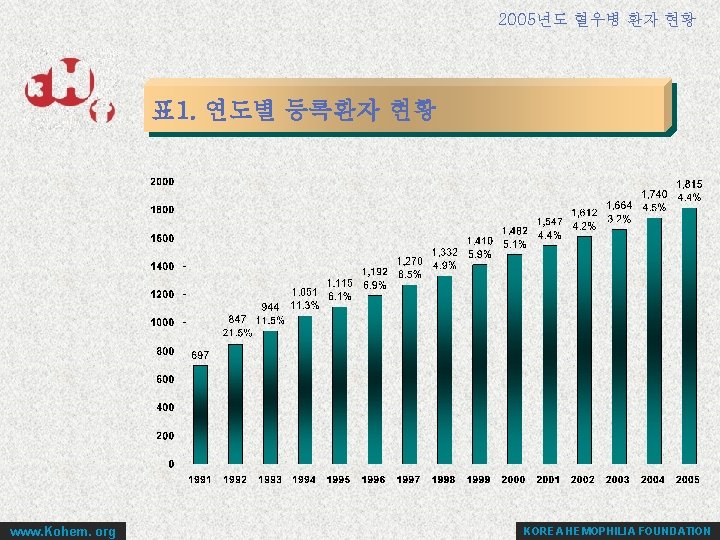
2005년도 혈우병 환자 현황 표 1. 연도별 등록환자 현황 www. Kohem. org KOREA HEMOPHILIA FOUNDATION
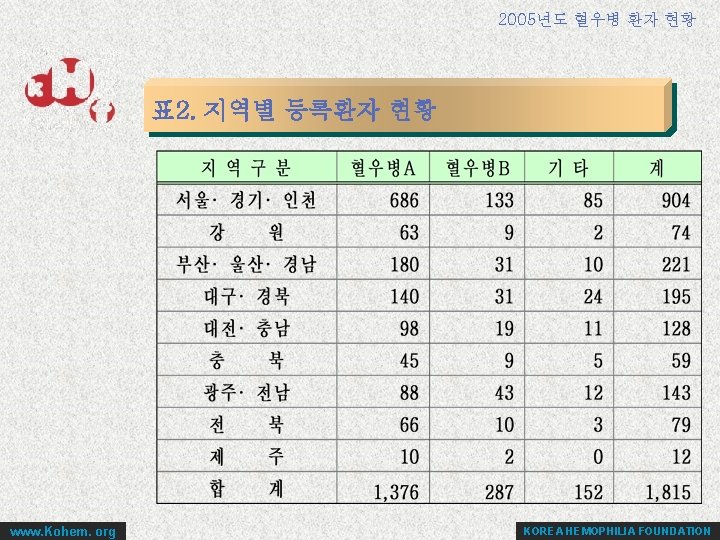
2005년도 혈우병 환자 현황 표 2. 지역별 등록환자 현황 www. Kohem. org KOREA HEMOPHILIA FOUNDATION
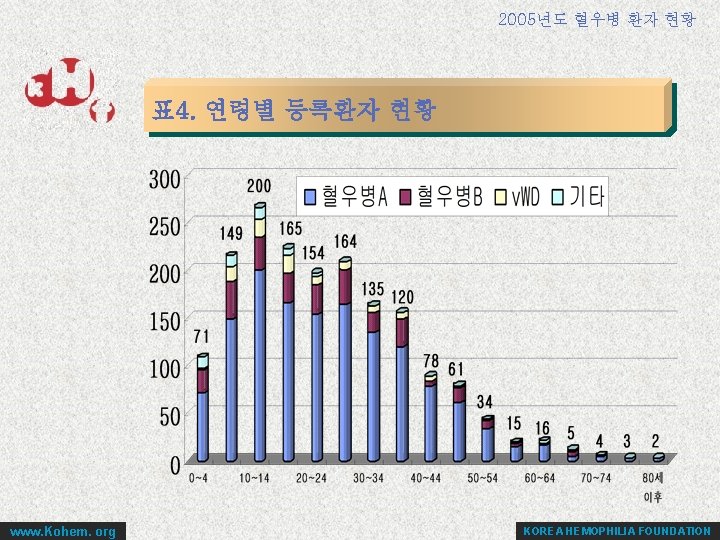
2005년도 혈우병 환자 현황 표 4. 연령별 등록환자 현황 www. Kohem. org KOREA HEMOPHILIA FOUNDATION
Congenital Afibrinogenemia • AR • no severe spontaneous hemorrhage or hemarthrosis but severe bleeding after trauma or surgery • fibrinogen < 100 mg/d 에서 출혈성 소인. • 이 병의 경우 대개 15 -20 mg/100 ml이하. • Tx ; – 100 mg/Kg of fibrinogen – half-life 3 -5 ds. – Cryoprecipitate a bag ; contain 225 -250 mg of fibrinogen
Factor V deficiency (parahemophilia) • 주로 비 출혈, 잇몸 출혈 혹은 발치 후 출 혈 등으로 시작. • AR. Incomplete • PT prolonged ; CT, PTT slightly prolonged • Tx ; 신선 혈장 or 혈액을 수혈, 반감기 10 -15 hr
Antithrombin III deficiency • • • AT III-응고 기전의 primaryinhibitor. 주로 II 인자 및 X 인자 작용의 억제. Liver 에서 합성 AD Dx. – AT III level • Tx. 1) 응급 ; 신선 냉동혈장 + Heparin 2) 예방 ; 1 unit/ Kg-> 2 -2. 5%로 활성도 증가.