Hypertension in a nutshell Sohil Rangwala MDCM CCFP


















- Slides: 25
Hypertension in a nutshell Sohil Rangwala MDCM, CCFP
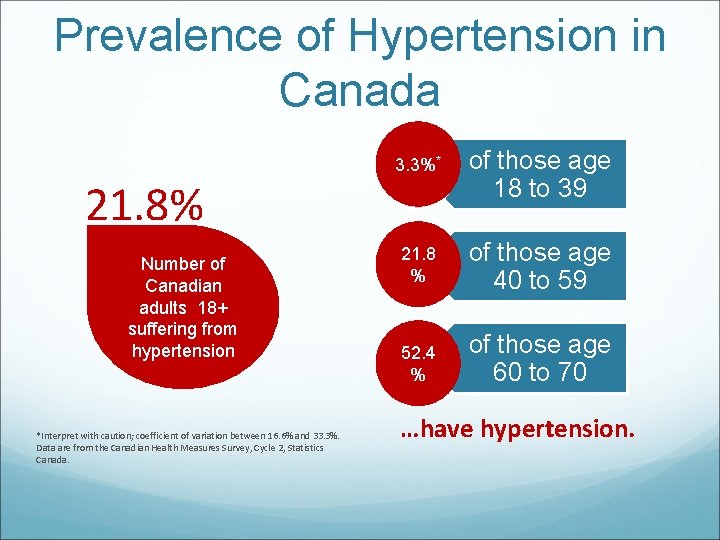
Quick facts 1 in 5 Canadians have hypertension Over 40% of Canadians aged 55 -65 have hypertension All adults with borderline BP 130 -139/80 -89 should get annual screening
Prevalence of Hypertension in Canada 3. 3%* 21. 8% Number of Canadian adults 18+ suffering from hypertension *Interpret with caution; coefficient of variation between 16. 6% and 33. 3%. Data are from the Canadian Health Measures Survey, Cycle 2, Statistics Canada. of those age 18 to 39 21. 8 % of those age 40 to 59 52. 4 % of those age 60 to 70 …have hypertension.
Questions to ask on history. Review of systems headache visual changes chest pain, dyspnea, PND leg swelling, exertional calf pain neurological deficits, vertigo Obstructive Sleep Apnea palpitations, excessive sweating, weight changes
Questions to ask on History PMHX CAD PAD CKD DM 2 dyslipidemia obesity cognitive changes
Questions to ask on history. Medications NSAID’s COX-2 inhibitors anabolic steroids SSRI’s, SNRI’s OCP’s decongestants
Questions to ask on history. Social/habits- i. e risk factors Age >55 Male Family history Smoker Obesity Poor diet, salt intake Diabetes/ Prediabetes Stress ETOH, drugs
Physical Exam- How to take a BP
Physical exam Neuro: check for abnormal cranial nerve exam , papilledema, cotton wool spots, retinal hemorrhages CVS: heart murmurs, renovascular bruits, carotid bruits, decreased or absent peripheral pulses, extremity swelling
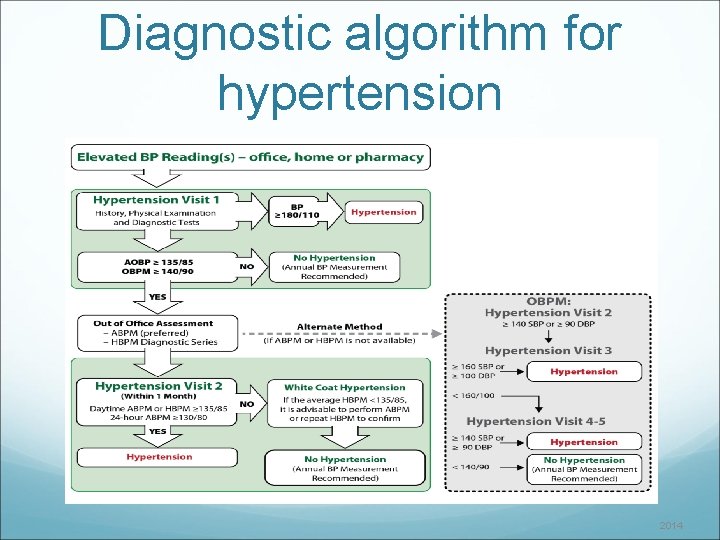
Diagnostic algorithm for hypertension 2014
Diagnostic tests after first visit Urinalysis Fasting blood sugar Electrolytes and creatinine Fasting lipid profile ECG ACR( only if DM)
End organ damage? Cerbrovascular disease (Stroke, TIA) Vascular Dementia Hypertensive retinopathy LVH CAD-MI, angina CKD -Egfr less than 60 or albuminuria PAD- intermittent claudication, ABI less than 0. 9
Hypertensive urgency and emergency Urgency: Asymptomatic diastolic BP ≥ 130 mm. Hg Emergency: Hypertensive encephalopathy Acute aortic dissection Acute left ventricular failure Acute myocardial ischemia
Secondary causes of Hypertension Renal artery stenosis Sleep apnea Hypothyroidism, Hyperthyroidism Coarctition of aorta Hyperaldosteronism Cushing’s disease Hyperparatyhroidism Drug side effects
Investigations for secondary HTN TSH Calcium, albumin, PTH Renal doppler Dexamethasone suppression test Sleep study Plasma aldosterone: plasma renin ratio Urine for metanephrines Echocardiogram
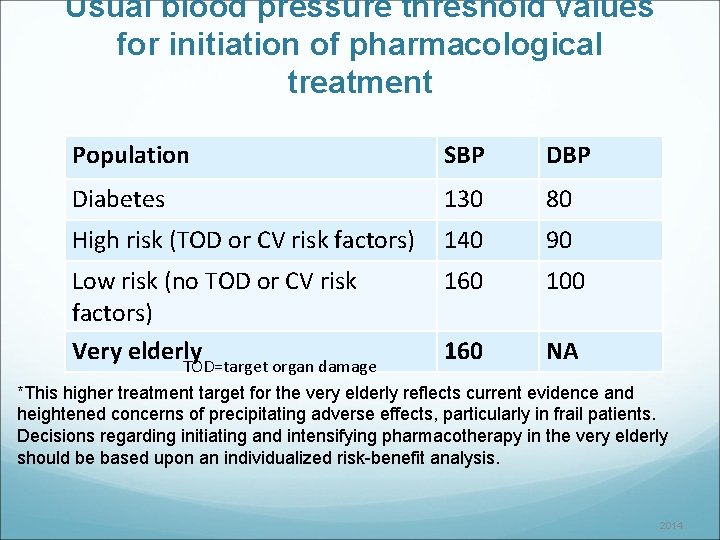
Usual blood pressure threshold values for initiation of pharmacological treatment Population SBP Diabetes 130 80 High risk (TOD or CV risk factors) 140 90 Low risk (no TOD or CV risk factors) Very elderly TOD=target organ damage 160 100 160 NA *This higher treatment target for the very elderly reflects current evidence and heightened concerns of precipitating adverse effects, particularly in frail patients. Decisions regarding initiating and intensifying pharmacotherapy in the very elderly should be based upon an individualized risk-benefit analysis. 2014
What are the Targets? Treatment consists of health behaviour ±pharmacological management Population SBP Diabetes <130 <80 All others < 80 y. a. (including CKD) Very elderly (≥ 80 years) <140 <90 <150* NA *This higher treatment target for the very elderly reflects current evidence and heightened concerns of precipitating adverse effects, particularly in frail patients. Decisions regarding initiating and intensifying pharmacotherapy in the very elderly should be based upon an individualized risk-benefit analysis. 2014
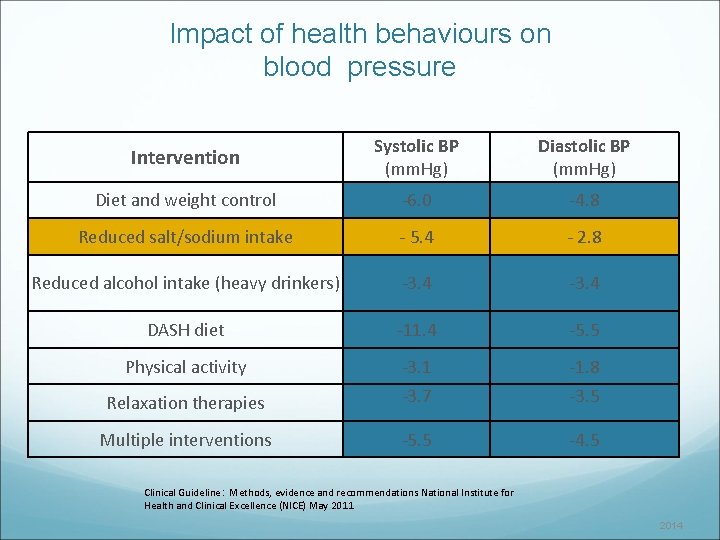
Impact of health behaviours on blood pressure Intervention Systolic BP (mm. Hg) Diastolic BP (mm. Hg) Diet and weight control -6. 0 -4. 8 Reduced salt/sodium intake - 5. 4 - 2. 8 Reduced alcohol intake (heavy drinkers) -3. 4 DASH diet -11. 4 -5. 5 Physical activity -3. 1 -1. 8 Relaxation therapies -3. 7 -3. 5 Multiple interventions -5. 5 -4. 5 Clinical Guideline : Methods, evidence and recommendations National Institute for Health and Clinical Excellence (NICE) May 2011 2014
Health Behaviours in Adults with Hypertension: Summary Intervention Target Reduce foods with added sodium Weight loss BMI <25 kg/m 2 Alcohol restriction < 2 drinks/day Physical activity Dietary patterns 30 -60 minutes 4 -7 days/week DASH diet Smoking cessation Smoke free environment Waist circumference Men <102 cm → 2000 mg /day Women <88 cm 2014
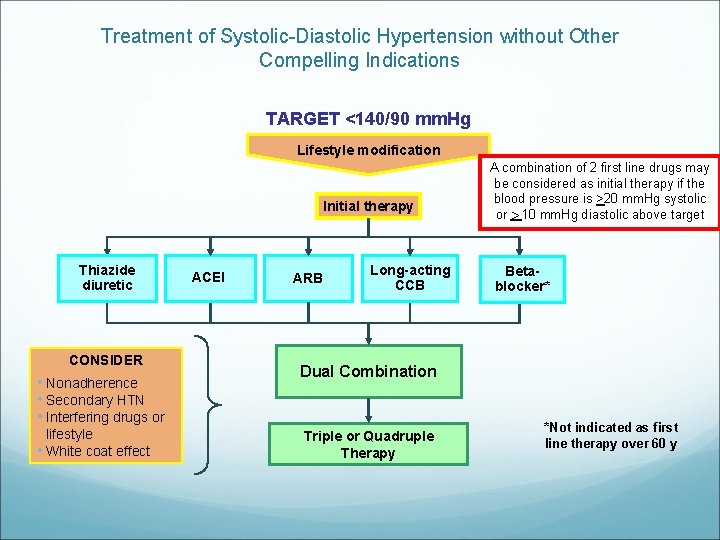
Treatment of Systolic-Diastolic Hypertension without Other Compelling Indications TARGET <140/90 mm. Hg Lifestyle modification Initial therapy Thiazide diuretic CONSIDER • Nonadherence • Secondary HTN • Interfering drugs or lifestyle • White coat effect ACEI ARB Long-acting CCB A combination of 2 first line drugs may be considered as initial therapy if the blood pressure is >20 mm. Hg systolic or >10 mm. Hg diastolic above target Betablocker* Dual Combination Triple or Quadruple Therapy *Not indicated as first line therapy over 60 y
Treatment Thiazide Diuretic HCTZ- risk Hypokalemia ACE Ramipril- cough, monitor renal function, can cause hyperkalemia ARB Telmesartan- , monitor renal function, can cause hyperkalemia CCB Amlodipine- Leg swelling, constipation B-Blocker metoprolol- fatigue, not generally for use over age 60
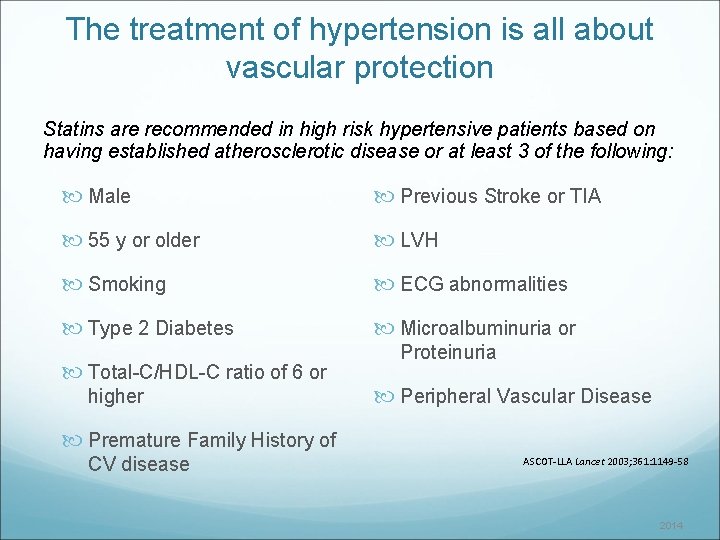
The treatment of hypertension is all about vascular protection Statins are recommended in high risk hypertensive patients based on having established atherosclerotic disease or at least 3 of the following: Male Previous Stroke or TIA 55 y or older LVH Smoking ECG abnormalities Type 2 Diabetes Microalbuminuria or Total-C/HDL-C ratio of 6 or higher Proteinuria Peripheral Vascular Disease Premature Family History of CV disease ASCOT-LLA Lancet 2003; 361: 1149 -58 2014
Vascular Protection for Hypertensive Patients: ASA Low dose ASA in patients >50 years Caution should be exercised if BP is not controlled. Hansson L, Zanchetti A, Carruthers SG, et al. Effects of intensive blood-pressure lowering and low-dose aspirin in patients with hypertension: principal results of the Hypertension Optimal Treatment (HOT) randomised trial. Lancet 1998; 351: 1755 -1762. 2014
Conclusion High prevalence, with significant mortality and morbidity Routine screening and monitoring is important Lifestyle and pharmacological therapies available!
References www. hypertension. ca- CHEP 2016 guidelines