DR KARANU JK Most It common primary malignancy







































- Slides: 53
DR KARANU JK
Ø Most Ø It common primary malignancy of bone is a plasma cell disorderØ monoclonal neoplasms related to each other by virtue of their development from common progenitors in the B lymphocyte lineage
Ø Thoughts that plamacytoma is simply an early, isolated form of multiple myeloma Ø There are two important variants of myeloma, solitary bone plasmacytoma Øextramedullary plasmacytoma Ø
Ø Solitary bone plasmacytoma is a single lytic bone lesion without marrow plasmacytosis Ø Extramedullary plasmacytomas usually involve the submuscosal lymphoid tissue of the nasopharynx or paranasal sinuses without marrow plasmacytosis.
Ø The cause of myeloma is not known Ø Incresed frequency in those exposed to radiation Ø Seen more frequently among farmers, wood workers, leather workers and those exposed to petroleum products
Ø Chromosomal alterations identified: Ø 13 q 14 deletions Ø 17 p 13 deletions Ø 11 q abnormalities Ø Common translocations Øt(11; 14)(q 13; q 32) and t(4; 14)(p 16; q 32)
ØOverexpression of myc or ras genes has been noted in some cases ØMutations in p 53 and Rb 1 have also been described
No common molecular pathogenesis has yet emerged
Ø Represents more than 40% of primary bone cancers Ø Peak Ø 2: 1 incidence is in 5 th to 7 th decades male predominance Ø Blacks have nearly twice the incidence of whites. Ø Yearly incidence is around 4 per 100000
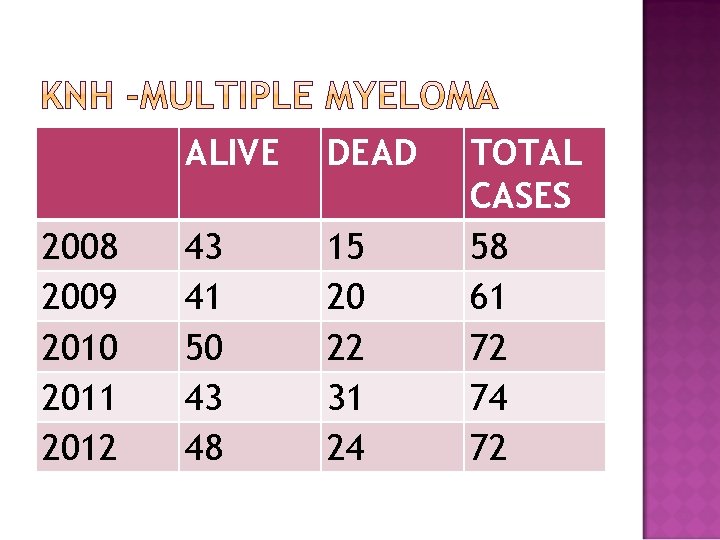
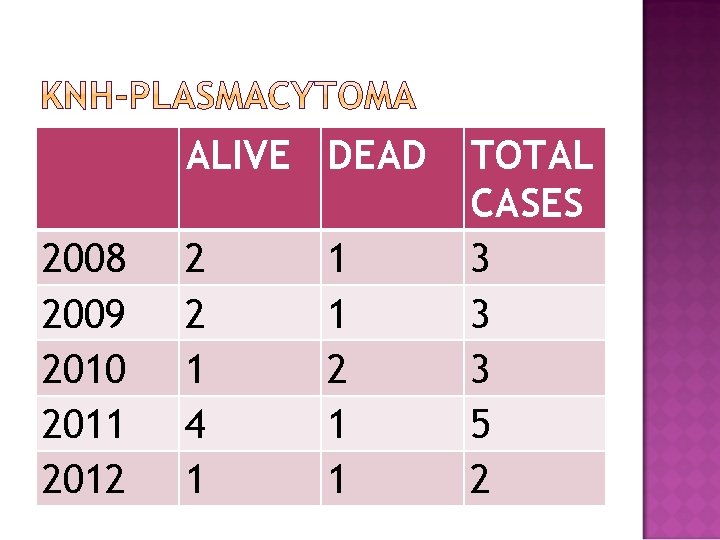
ØKnh multiple myeloma 337 cases in 5 years, average of 67 per year ØPlasmacytoma 16 cases in 5 years, average of 3 per year
Ø Multiple myeloma cells bind via cell surface adhesion molecules to bone marrow stromal cells and extracellular matrix. Ø This triggers multiple myeloma cell growth, survival, drug resistance and migration in the bone marrow milieu
Ø The cell effect is due to direct multiple myeloma and bone marrow stromal cell interaction , as well as induction of cytokines Ø Cytokines involved include IL 6, Øinsulin like growth factor 1, Øvascular endothelial growth factor Østromal cell derived growth factor Ø
Growth, drug resistance and migration are mediated via Ras/Raf/mitogen- activated protein kinase, PI 3 -K/Akt and protein kinase c signaling cascades
ØThe clinical manifestation of all the plasma cell disorders relate to Øexpansion of the neoplastic cells Øsecretion of cell productsimmunoglobulins, lymphokines ØHost’s response to the tumour
Ø Bone pain most common complaintprecipitated my movement Ø Weakness Ø Weight loss Ø Anaemia and thrombocytopenia Ø Peripheral neuropathy Ø Hypercalcaemia Ø Renal failure
Ø Pathological fractures Ø Symptoms are usually of short duration because of the aggressive nature of the disease Ø The spine is the most common location followed by the ribs and pelvis.
Ø Hypercalcaemia, osteoporosis, pathological fracture, lytic bone lesions, bone pain ØTumor expansion, osteoclast activating factor, osteoblast inhibitory factors Ø Renal failureØHypercalcaemia, light chain deposition, urate nephropathy, drugs
�Easy fatigue- anaemia �Bone marrow infiltration, haemolysis, decreased erythropoietin levels �Recurrent infections �Hypogammaglobulinaemia, low cd 4 count, decreased neutrophil migration
Ø Neurologic symptoms ØHyper viscosity, croglobulinemia, Hypercalcaemia, nerve compression, POEMS syndrome Ø Nausea and vomiting ØRenal failure, Hypercalcaemia
The classic triad of myeloma is i. Marrow plasmacytosis (>10%) - CD 138+, monoclonal ii. Lytic bone lesions iii. Serum and/ or urine M component
Monoclonal gammopathies of uncertain significance � 1% go on to develop myeloma �M protein in serum<30 g/l �Bone marrow clonal plasma cells<10% �No evidence of other B cell proliferative disorder
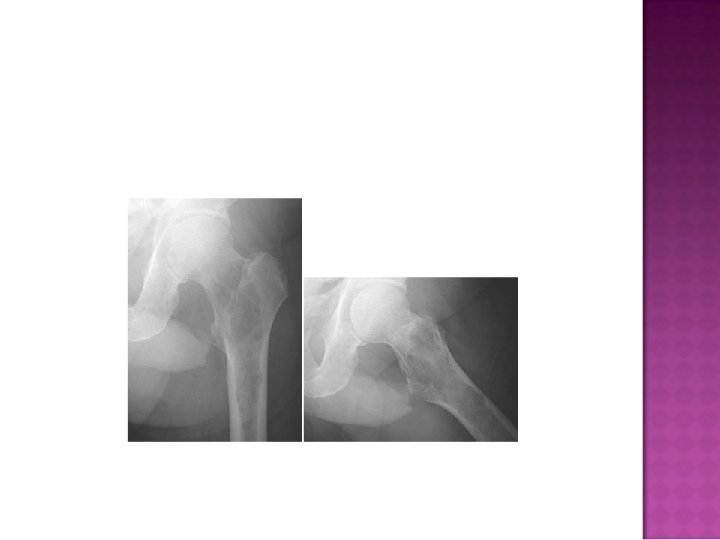
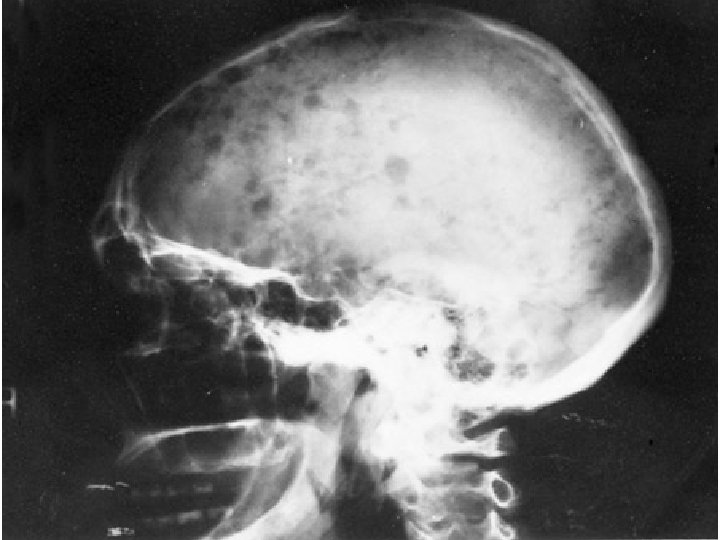
Ø Clinical evaluation of patients with myeloma includes a careful physical examination searching for tender bones and masses. Ø Chest and bone radiographs may reveal lytic lesions or diffuse osteopenia
Multiple ‘punched out’ sharply demarcated, purely lytic lesions without any surrounding reactive sclerosis
The lack of reactive bone formation is shown by the fact that most lesions are negative on bone scan
MRI offers a sensitive means to document extent of bone marrow infiltration and cord or root compression in patients with pain syndromes
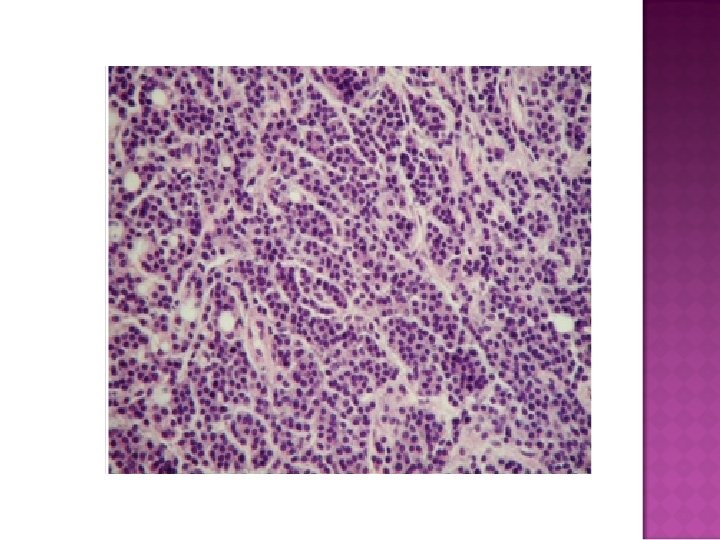
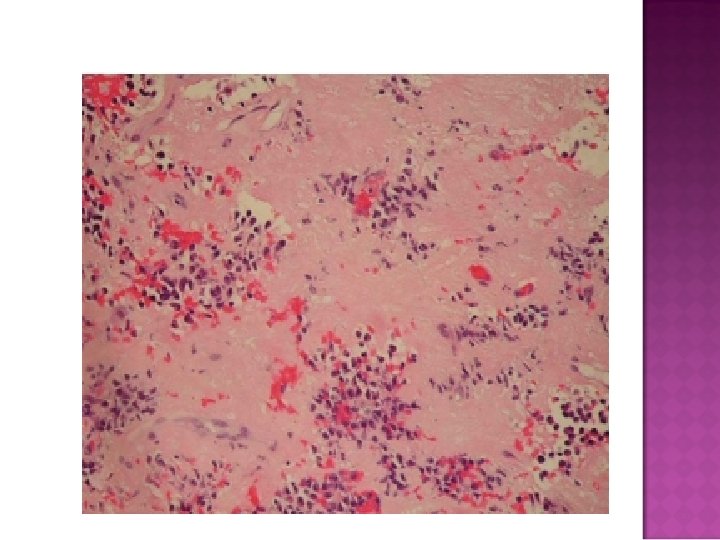
Ø Histologically multiple myeloma appears as sheets of plasma cells Ø These are Ø small round blue cells Ø clock face nuclei Ø abundant cytoplasm Ø perinuclearing or halo Ø Amyloid production can be abundant and may be pathognomonic for the disease
Ø Serum immunoelectrophoresis shows monoclonal gammopathy ØA 24 hr urine specimen quantitate protein excretion Øconcentrated aliquot is used for electrophoresis and immunologic typing of any M component Ø
Ø The serum M component will be Ig. G in 53%, Ig. A in 25%, and Ig. D in 1%. Ø 20% of patients will have only light chains in serum and urine.
Ø Fewer than 1% of patients will have no identifiable M component Ø The heat test for detecting Bence Jones proteins is falsely negative in 50% of patients with light chain myeloma
Ø Complete blood count with differential may reveal anaemia Ø ESR is elavated Ø Serum chemistries calcium, urea, nitrogen, creatinine and uric acid levels may be elevated.
Solitary plasmacytoma pathological differentials may include chronic osteomyelitis with abundant plasma cells �Plasmcytoma has monoclonal light chains whereas in COM they are polyclonal �Myeloma cells stain positive for natural killer antigen CD 56, whereas reactive cells do not
In poorly differentiated cases lymphoma could be a differential ØLymphoma cells usually stain positive for CD 45 (leukocyte common antigen) Ø and CD 20 ( a B cell marker),
�Stage 1 � Hb>10 g/dl, �serum calcium <3 mmol/l, �normal bone xray or solitary lesion, �low M component production
�Stage 2 - neither fitting stage 1 or 2 3 - one or more of the following: �Hb <8. 5 g/dl �Serum calcium >3 mmol/l �Advanced lytic bone lesion �High M component production
� 10% of patients will have an indolent course- slow progression �These patients only require antitumor therapy when the disease becomes symptomatic �anaemia, hypercalcaemia, progressive lytic bone lesions, progressive rise in serum myeloma protein levels or recurrent infections.
�Primary treatment of multiple myeloma is chemotherapy �Symptomatic bone lesions usually respond rapidly to radiation treatment 40 Gy �Treatment of impending or actual pathological fractures of the spine, acetabulum, proximal femur or proximal humerus
�Patients with symptomatic and/ or progressive myeloma require therapeutic intervention � 2 sorts of such therapy �Systemic therapy to control the progression of myeloma �Symptomatic supportive care to prevent serious morbidity from the complications of the disease
�Standard treatment for newly diagnosed cases depends on whether the patient is a candidate for high dose chemotherapy with autologous stem cell transplant �Transplant candidates avoid alkylating agents such as melphalan �Glucorticoids, thalidomide vincristine, doxorubicin,
�Supportive care directed at the anticipated complications �Hypercalcaemia-bisphonates, glucocorticoids, hydration, natriuresis �Prophylactic IV gamma globulin in recurrent serious infections �Anaemia- erythropoietin, along with haematinics
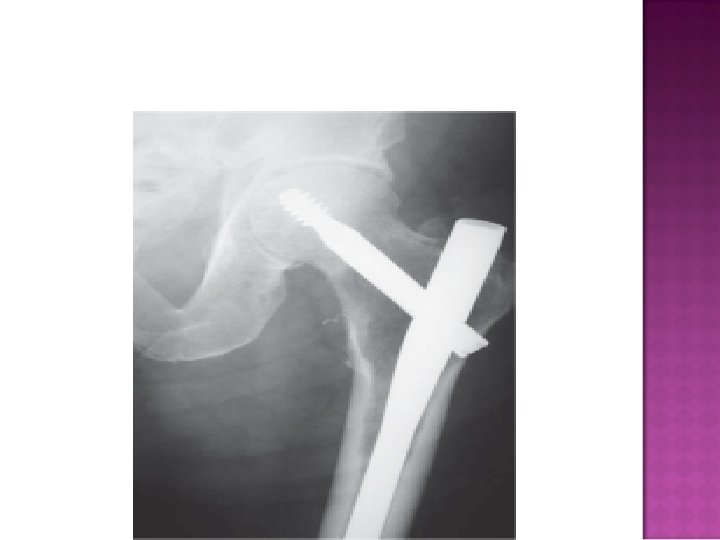
�Short life expectancy in these patients operations aimed to earliest resumption of full activity �Tumor debulking �Internal fixation augmented with methacrylate �Cemented total joint arthroplasty or hemiarthroplasty
In most patients local radiation treatment should be instituted approximately 3 weeks after surgery or when the wound appears to be healed.
Ø No conclusive evidence on the corelation Ø Aggressive course and worse prognosis in HIV Ø Multiple myeloma can accelerate progression of HIV infection Ø HIV plays a major role in the evolution of malignant plasma cell tumors
Ø Patients with solitary plasmacytoma without evidence of systemic involvement have a better prognosis Ø More than half of patients who present with a solitary plasmacytoma eventually go on to develop multiple myeloma.
Ø Patients in stage 1 A have a median survival of more than 5 years and those in 3 B about 15 months Ø The median overall survival is 5 -6 years with subsets of patients surviving over 10 years.
Ø The major causes of death are progressive myeloma, renal failure, sepsis or therapy related acute leukaemia or myelodysplasia. Ø Nearly a quarter die of myocardial infarction, chronic lung disease, diabetes or stroke.
2008 2009 2010 2011 2012 ALIVE DEAD 43 41 50 43 48 15 20 22 31 24 TOTAL CASES 58 61 72 74 72
ALIVE DEAD 2008 2009 2010 2011 2012 2 2 1 4 1 1 1 2 1 1 TOTAL CASES 3 3 3 5 2