Contraception GP update Dr Sue Mann Consultant Homerton














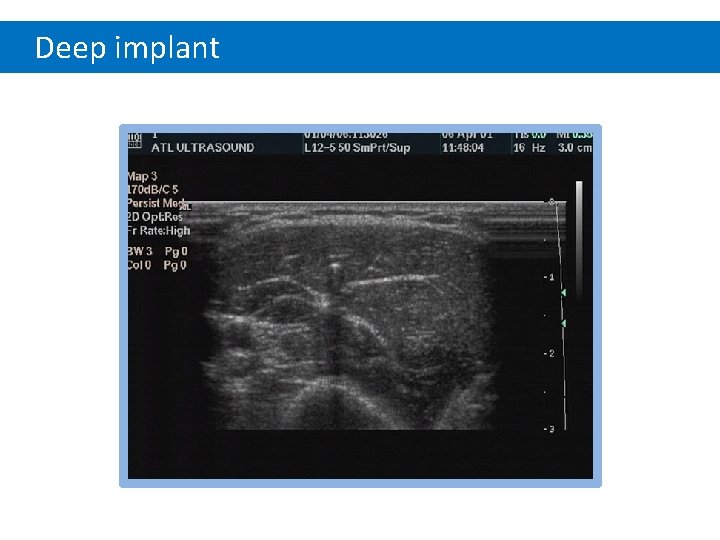





- Slides: 42
Contraception GP update Dr Sue Mann Consultant Homerton Hospital 28 th September 2018
Today’s audience • GPs/practice nurses/other • At individual and practice level, who prescribes…? • • only oral methods only non-LARC methods all except IUD all contraception
Overview of session • • • Background Non LARC methods Training Resources and contacts
Methods of contraception
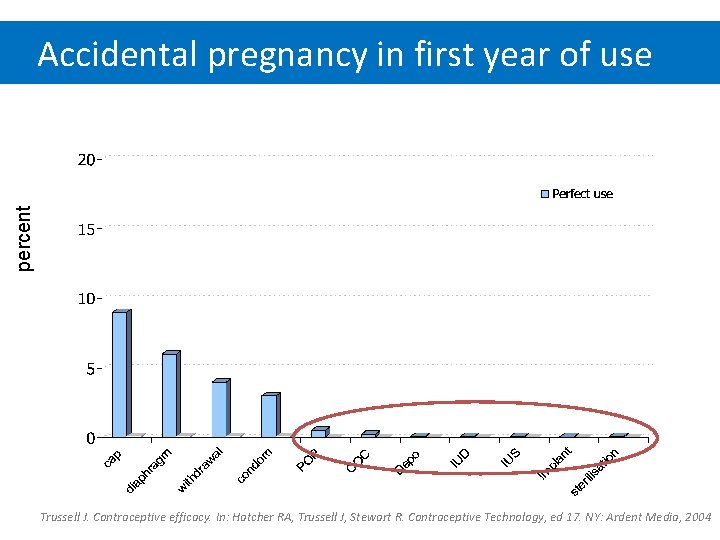
percent Accidental pregnancy in first year of use Trussell J. Contraceptive efficacy. In: Hatcher RA, Trussell J, Stewart R. Contraceptive Technology, ed 17. NY: Ardent Media, 2004
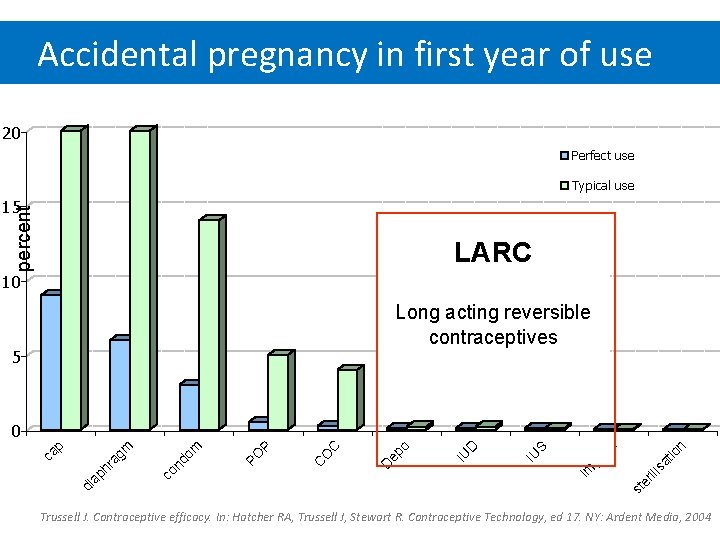
Accidental pregnancy in first year of use 20 Perfect use Typical use percent 15 LARC 10 Long acting reversible contraceptives 5 at io n nt st er il is pl a Im IU S IU D o D ep C C O P PO m nd o co gm ph ra di a ca p 0 Trussell J. Contraceptive efficacy. In: Hatcher RA, Trussell J, Stewart R. Contraceptive Technology, ed 17. NY: Ardent Media, 2004
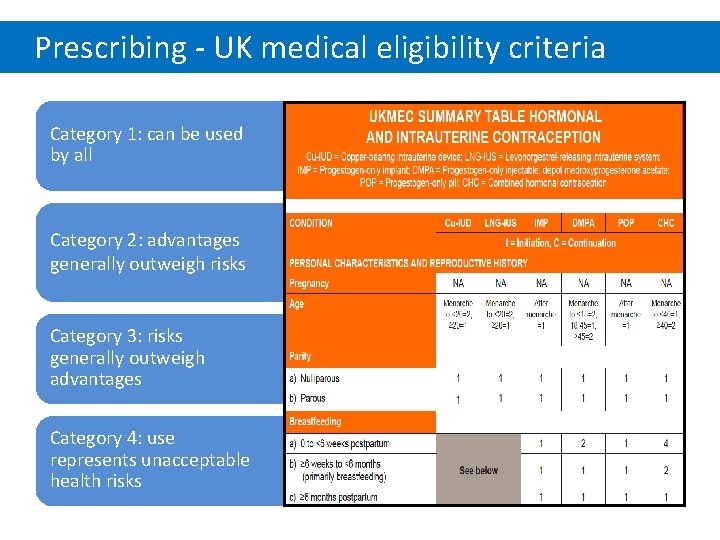
Prescribing - UK medical eligibility criteria Category 1: can be used by all Category 2: advantages generally outweigh risks Category 3: risks generally outweigh advantages Category 4: use represents unacceptable health risks
Non LARC hormonal – principles • Ensure aware LARC most effective – non-perfect use is main reason for difference • Hormones very safe in low risk women (P>E) • Unplanned pregnancy is almost always the greater risk – make it work for woman • Tailored regimes for CHC • Low threshold for quick-start (NB DMPA) – with EC if needed • Make follow-up easy - 12/12 supplies • Bridging supplies if no appointments/EC
Drug interactions • Non-enzyme inducing antibiotics – NO additional precautions • Enzyme inducers – IUS, IUD, DMPA, (CHC extended cycle, reduced PFI) • Lamotrigine • CHC reduces Lamotrigine levels by increasing clearance - UKMEC 3 • CHC does not have this effect when lamotrigine plus sodium valproate • Progestogen-only methods do not seem to affect Lamotrigine levels • Sodium valproate
Combined methods
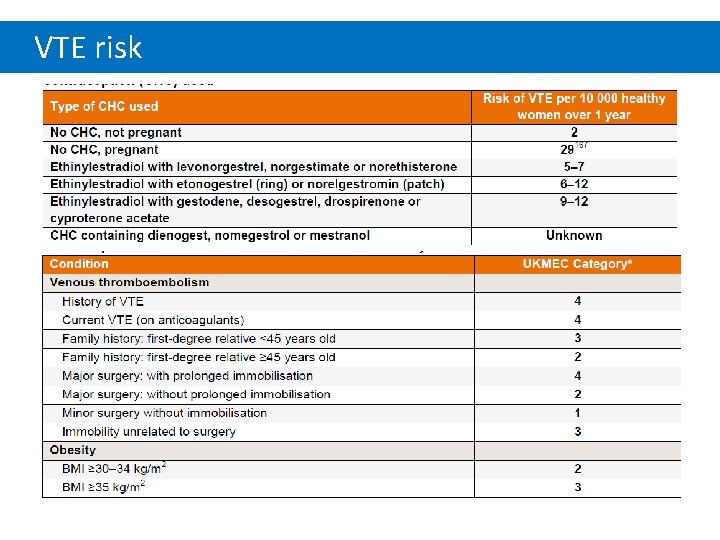
VTE risk
Cardiovascular disease and stroke • Older women – risk factors as increased baseline risk • Small increased risk in MI and stroke – rare events • VTE, Stroke and MI risk likely to be E 2 dose related – lower in 20 mcg pills. • Evidence for effect of P is conflicting
Mood and hormonal contraception • No evidence that causes or worsens or improves • Women report mood changes with and without • Women who report mood changes with one method will not necessarily report problems on another Worly BL, et al. The relationship between progestin hormonal contraception and depression: a systematic review. Contraception 2018. https: //doi. org/10. 1016/j. contraception. 2018. 010
COC and cancer • 12% decrease in the risk of developing cancer overall • Reduction large bowel, uterus and ovaries • Small increase in breast for current and recent users (RR 1. 24) up to 5 years after stopping. No differences between ever and never users • Small increased risk in cervical cancer in women using OC for 8 years (rate 38 per 100, 000 woman years)
Missed pills • Missed if >24 hrs late • Just keep going • If missed 2 or more pills • use condoms or abstain until taken 7 pills in a row • Missed pills in week 1: consider EC • Missed pills in week 3: omit PFI Missed pill recommendations May 2011 FSRH
Case study 1 Mary attends on Monday morning asking for emergency contraception. She went away at the weekend and forgot to take her Microgynon 30 packet. The last pill she took was on Thursday. She was mid way through her pill packet, having taken 10 pills correctly before she went away. She had intercourse on Saturday night without a condom. • What would you advise about when to restart her COC? • Does she need emergency contraception?
Case study 2 Fiona attends on Friday afternoon to get more supplies of Microgynon 30. She was supposed to restart her pills on Wednesday, after her 7 day pill-free interval. She had sex on Thursday night; she did not use a condom. • What would you advise about when to restart her COC? • Does she need emergency contraception? • What would you advise if she attended on the following Monday (day 13 of her extended pill free interval) having had intercourse on Thursday night? • What would you advise if she attended on the following Thursday (day 16 of her extended pill free interval) having had intercourse on the previous Thursday night?
DMPA: Late attenders • Up to 14 weeks – WHO & FSRH ; 12 weeks plus 5 days – manufacturers • Over 14 weeks, consider giving DMPA at same time as emergency contraception • Enzyme inducers – still give every 12 weeks Missed pill recommendations May 2011 FSRH
Newer products
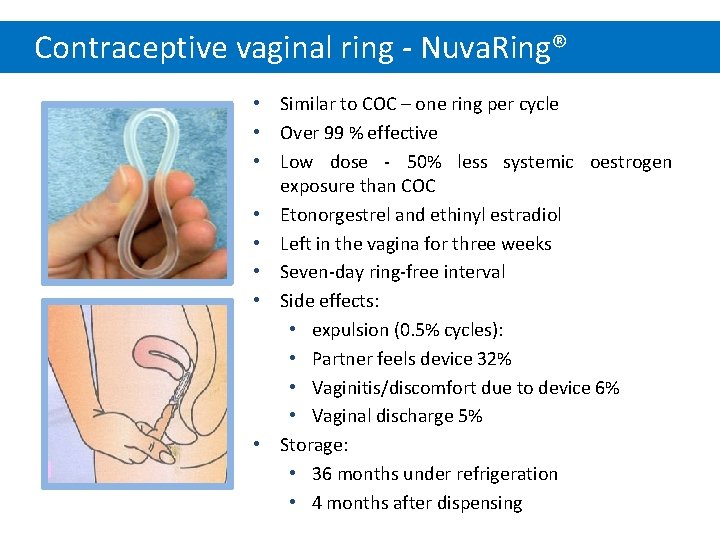
Contraceptive vaginal ring - Nuva. Ring® • Similar to COC – one ring per cycle • Over 99 % effective • Low dose - 50% less systemic oestrogen exposure than COC • Etonorgestrel and ethinyl estradiol • Left in the vagina for three weeks • Seven-day ring-free interval • Side effects: • expulsion (0. 5% cycles): • Partner feels device 32% • Vaginitis/discomfort due to device 6% • Vaginal discharge 5% • Storage: • 36 months under refrigeration • 4 months after dispensing
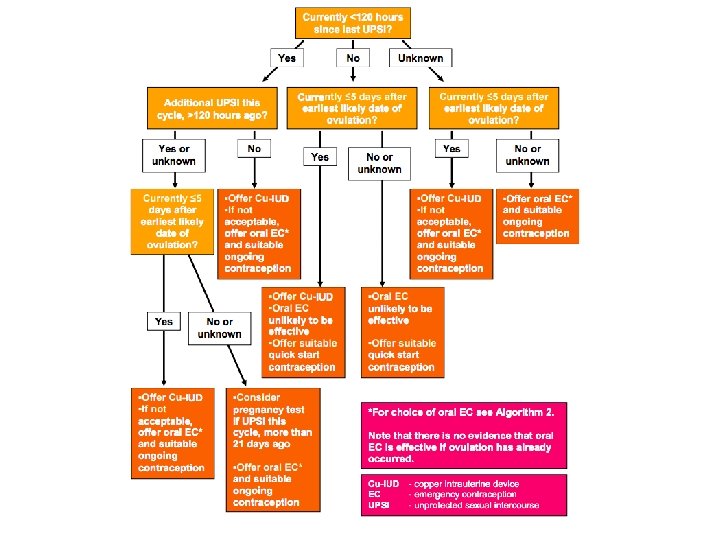
Emergency contraception • Timing (IUD and oral) • After pregnancy – abortion D 5, pregnancy D 21 • Ineffective after ovulation • Ella one > levonelle • Reduced effectiveness – P in last 7/7; enzyme inducers; weight • Repeat doses but not UPA before or after levonelle • Costs IUD; Levonelle; ullipristal
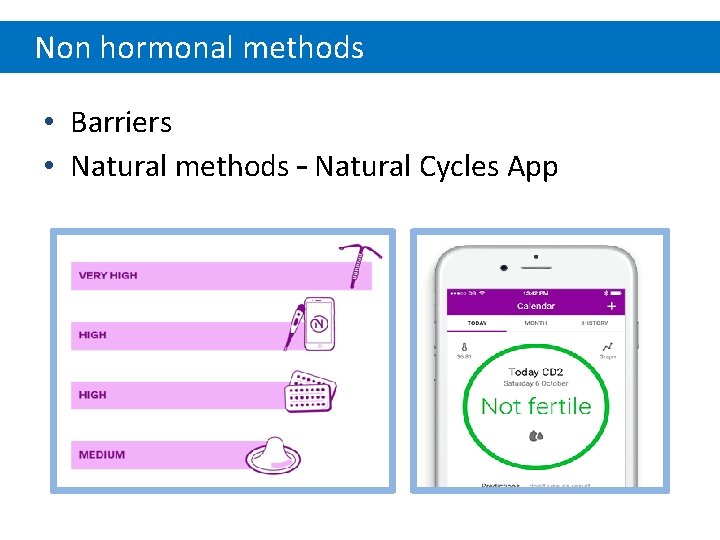
Non hormonal methods • Barriers • Natural methods – Natural Cycles App
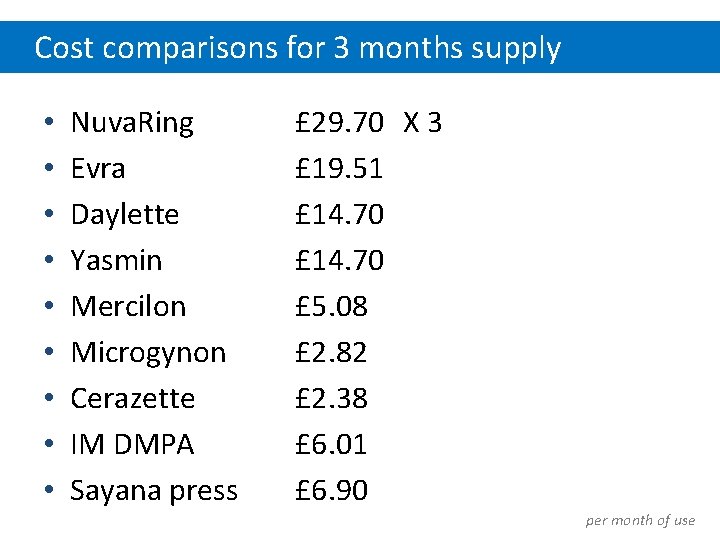
Cost comparisons for 3 months supply • • • Nuva. Ring Evra Daylette Yasmin Mercilon Microgynon Cerazette IM DMPA Sayana press £ 29. 70 X 3 £ 19. 51 £ 14. 70 £ 5. 08 £ 2. 82 £ 2. 38 £ 6. 01 £ 6. 90 per month of use
LARC Methods If 7% of women switched from the pill to LARC methods (doubling current usage to 15%) the NHS could save approx £ 100 million each year by reducing unplanned pregnancies by 73, 000
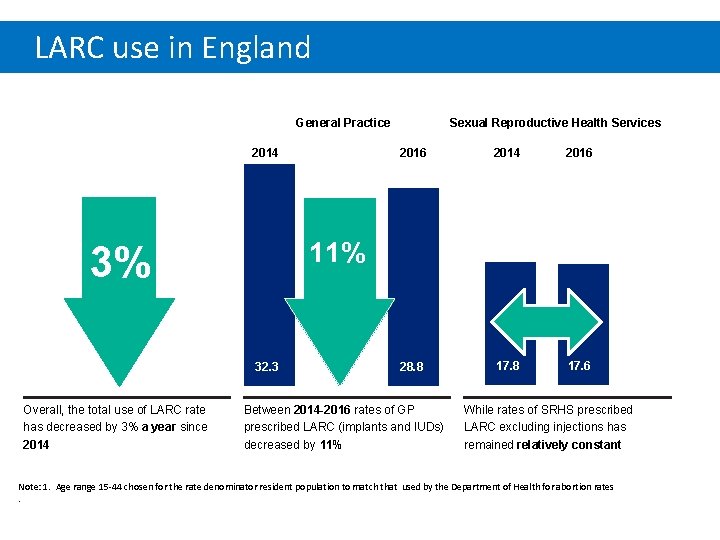
LARC use in England Sexual Reproductive Health Services General Practice 2014 2016 28. 8 17. 6 11% 3% 32. 3 Overall, the total use of LARC rate has decreased by 3% a year since Between 2014 -2016 rates of GP prescribed LARC (implants and IUDs) While rates of SRHS prescribed LARC excluding injections has 2014 decreased by 11% remained relatively constant Note: 1. Age range 15 -44 chosen for the rate denominator resident population to match that used by the Department of Health for abortion rates . Reproductive Health i a Public Health Issue: What does the data tell us?
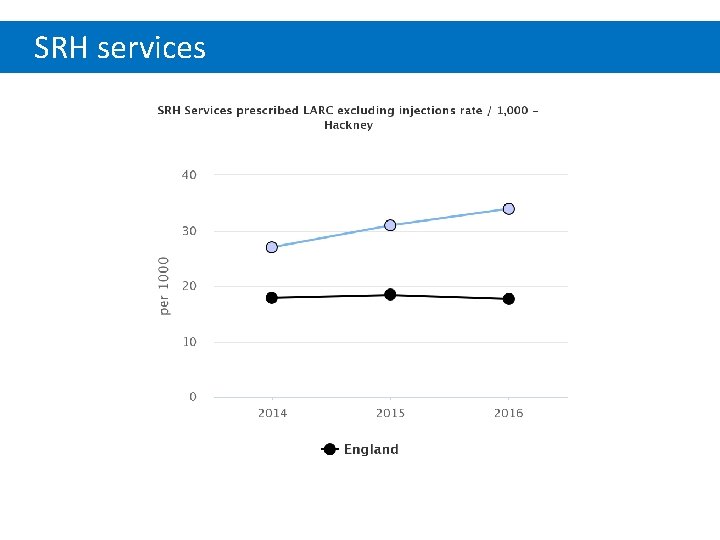
SRH services
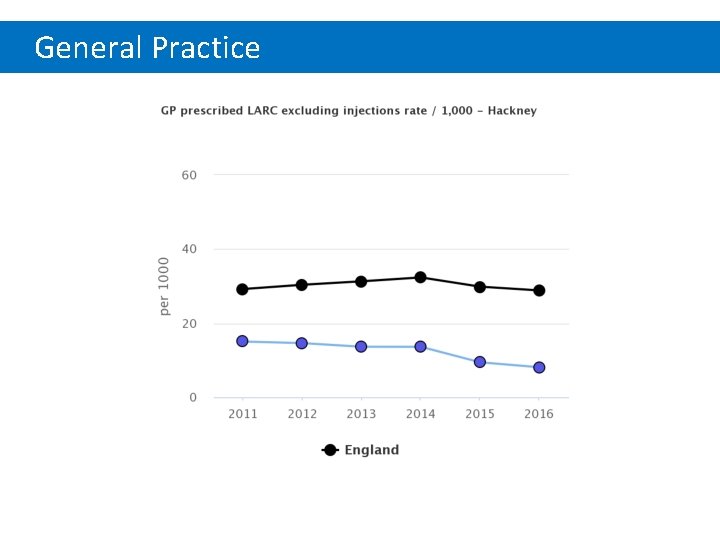
General Practice
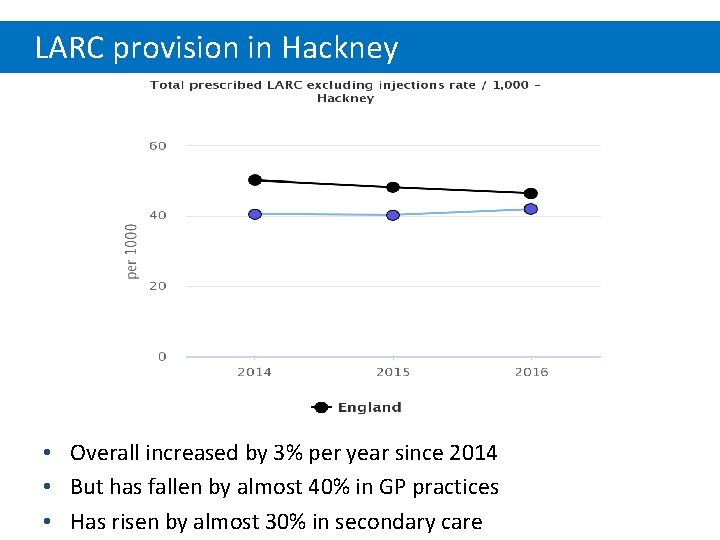
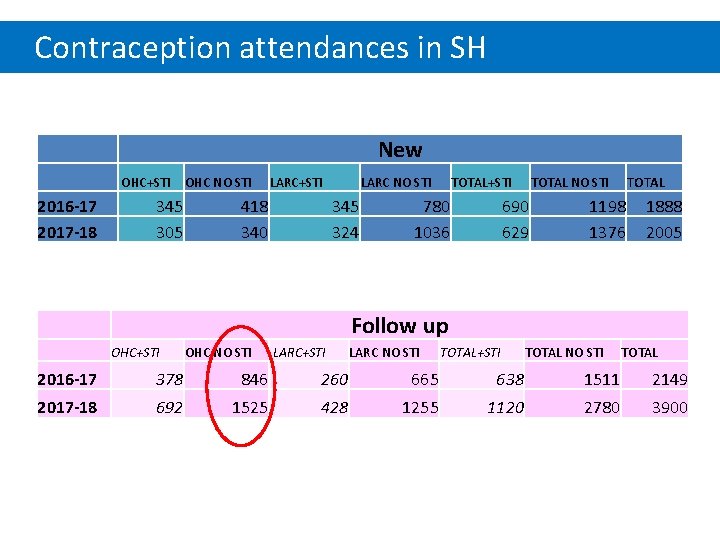
LARC provision in Hackney • Overall increased by 3% per year since 2014 • But has fallen by almost 40% in GP practices • Has risen by almost 30% in secondary care
Contraception attendances in SH New 2016 -17 2017 -18 OHC+STI 345 305 OHC NO STI LARC+STI 418 340 LARC NO STI 345 324 780 1036 TOTAL NO STI 690 629 TOTAL 1198 1376 1888 2005 Follow up TOTAL+STI OHC NO STI LARC+STI LARC NO STI TOTAL+STI TOTAL NO STI TOTAL 2016 -17 378 846 260 665 638 1511 2149 2017 -18 692 1525 428 1255 1120 2780 3900
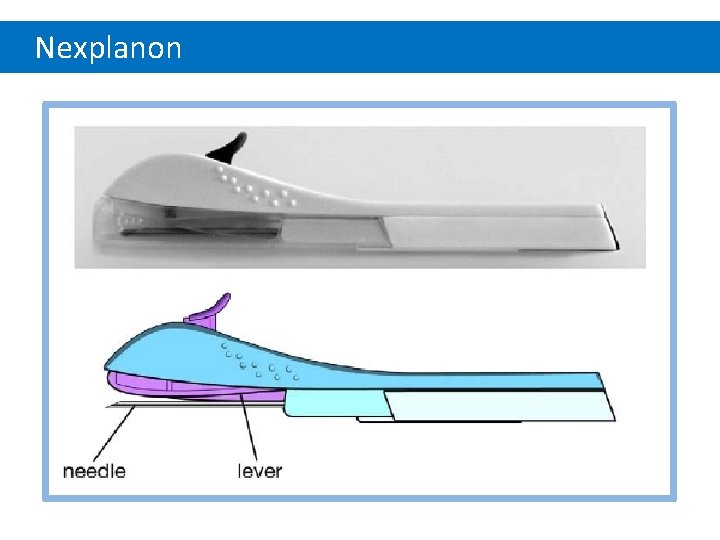
Nexplanon
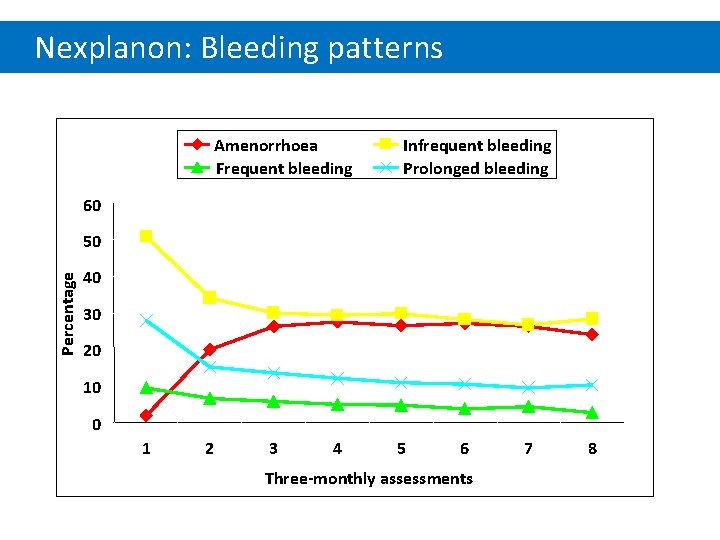
Nexplanon: Bleeding patterns Amenorrhoea Frequent bleeding Infrequent bleeding Prolonged bleeding 60 Percentage 50 40 30 20 10 0 1 2 3 4 5 6 Three-monthly assessments 7 8
Deep implant
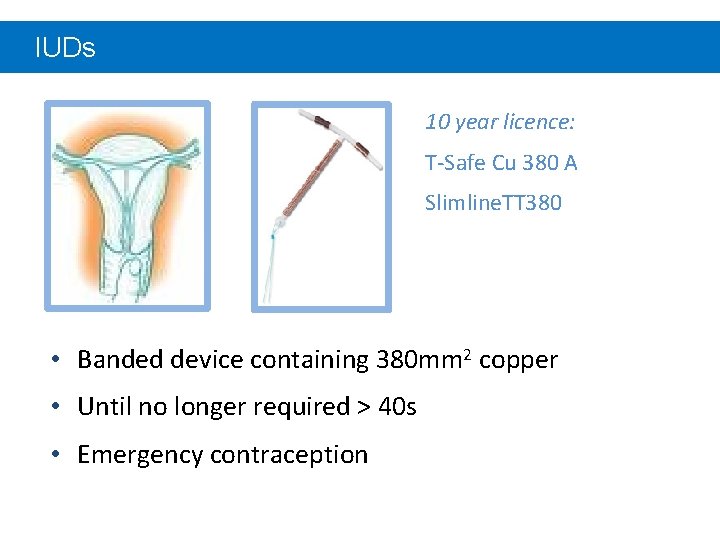
IUDs 10 year licence: T-Safe Cu 380 A Slimline. TT 380 • Banded device containing 380 mm 2 copper • Until no longer required > 40 s • Emergency contraception
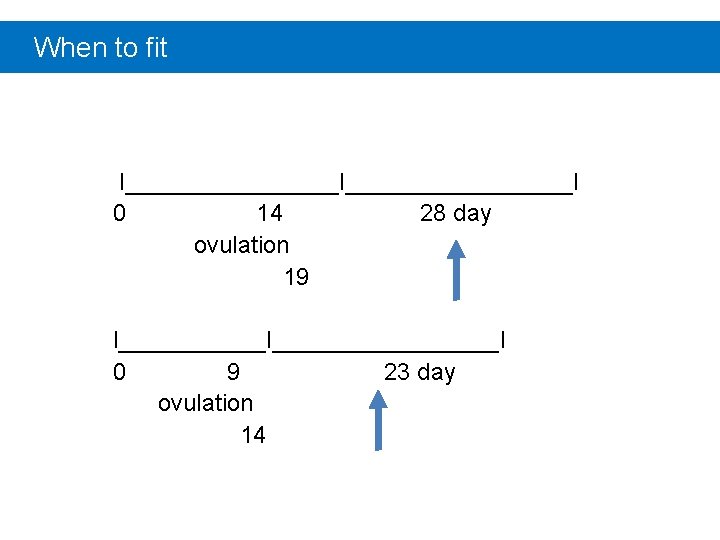
When to fit I_________________I 0 14 28 day ovulation 19 I_________________I 0 9 23 day ovulation 14
IUS • Effective & safe • Long lasting (5 years) & cheap • 7 years in over 45 s (unlicensed) • Beneficial effect on menstruation • Progestogen component of HRT • Not EC
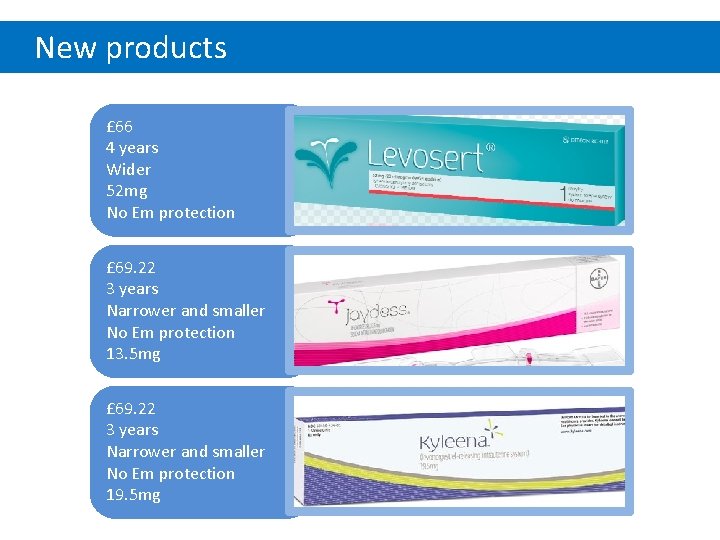
New products £ 66 4 years Wider 52 mg No Em protection £ 69. 22 3 years Narrower and smaller No Em protection 13. 5 mg £ 69. 22 3 years Narrower and smaller No Em protection 19. 5 mg
FSRH Training • Essentials • DFSRH/NDFSRH • Lo. C SDI and IUT
Complex contraception and community gynaecology • • Every week at Ivy, St Leonard’s GP Referral ERS – triage within a week – wait time 6/52 Complex contraception • Women with complex medical problems • IUD problems – difficult, non visible threads • Non palpable implants
National clinical guidance • • • SPC BNF NICE LARC www. fsrh. org • Guidance products • New method reviews • Clinical enquiries • UK MEC Guidelines
Sexwise video: https: //youtu. be/Lk. CQYa. Fl. Pz. Y