Cardiac Nervous System Review of Emergencies ECRN Mod






















































- Slides: 83
Cardiac & Nervous System Review of Emergencies ECRN Mod III CE 2010 Condell Medical Center EMS System Prepared by: FF/PMD Michael Mounts Lake Forest Fire Department Reviewed/revised by: Dr. Kent Bailey, EMS Medical Director
Objectives n n n Identify components of the nervous system Identify signs and symptoms of a patient with a CVA Identify assessment & field treatment of patient with a CVA Identify anatomy and physiology of the cardiopulmonary system Identify signs and symptoms of a patient with ACS Identify field treatment of patient with ACS
Objectives cont. n n n Discuss situations for using the RAD 57 tool Identify patient care based on RAD 57 readings Review documentation components for discussed conditions Identify a variety of ECG rhythm strips Review Region X SOP’s for various emergencies discussed
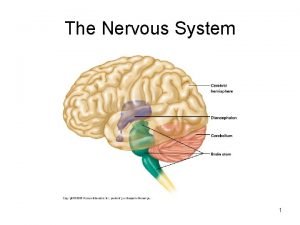
Components of the CNS n Brain - 3 major structures ¬ Cerebrum largest element of nervous system t occupies most of cranium t highest functional portion of brain t center of conscious thought, personality, speech, motor control, and visual, auditory, & tactile perception t Cerebellum fine tunes motor control, allows smooth motion from one position to another t responsible for balance & maintenance of muscle tone t
Components of the CNS cont. ® Brainstem • central processing center &communication junction • midbrain • hypothalamus • controls much of endocrine function, vomiting reflex, hunger, thirst, kidney function, body temperature
Components of the CNS cont. • Brainstem cont. • pons • medulla oblongata • respiratory center (depth, rate, rhythm) • cardiac center (rate & strength of cardiac contractions) • vasomotor center (control of distribution of blood and maintenance of blood pressure)
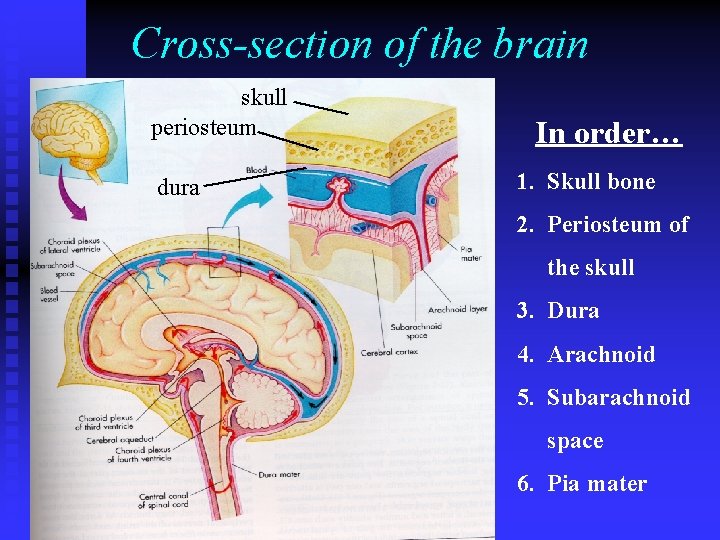
Cross-section of the brain skull periosteum dura In order… 1. Skull bone 2. Periosteum of the skull 3. Dura 4. Arachnoid 5. Subarachnoid space 6. Pia mater
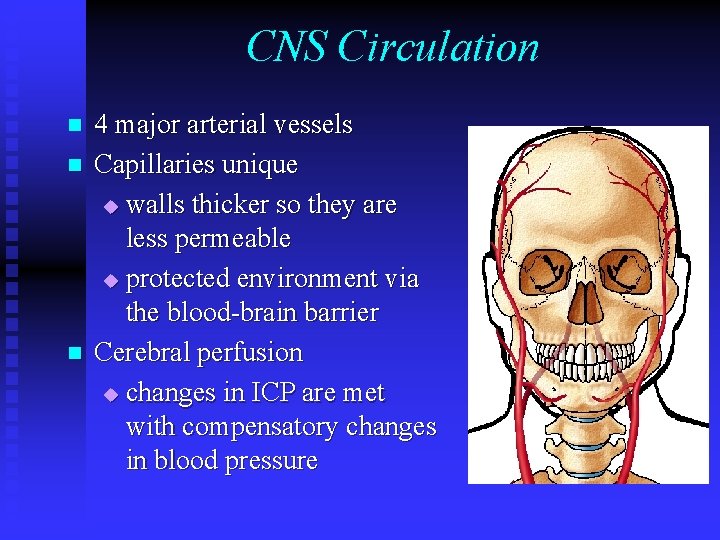
CNS Circulation n 4 major arterial vessels Capillaries unique u walls thicker so they are less permeable u protected environment via the blood-brain barrier Cerebral perfusion u changes in ICP are met with compensatory changes in blood pressure
Cerebral Perfusion Pressure n Intracranial pressure - pressure within cranium u u n 3 major cranial contents u n n pressures within cranium create a natural resistance to control the amount of cerebral blood flow to the brain remains adequate as long as pressures within the cranium are appropriate brain, blood, & cerebrospinal fluid Any changes in one of the 3 cranial contents is at the sacrifice to one of the others When ICP rises, the body increases the BP to maintain the cerebral perfusion (Cushing reflex)
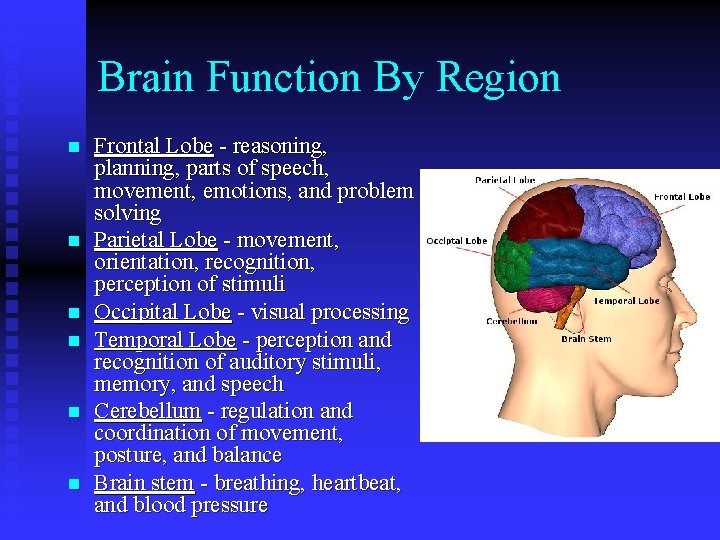
Brain Function By Region n n n Frontal Lobe - reasoning, planning, parts of speech, movement, emotions, and problem solving Parietal Lobe - movement, orientation, recognition, perception of stimuli Occipital Lobe - visual processing Temporal Lobe - perception and recognition of auditory stimuli, memory, and speech Cerebellum - regulation and coordination of movement, posture, and balance Brain stem - breathing, heartbeat, and blood pressure
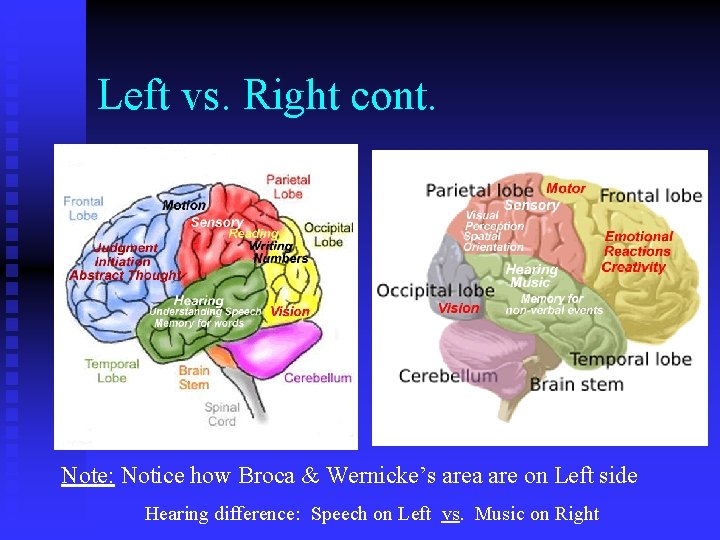
Remember n n Wernicke’s Area u Controls speech comprehension Broca’s Area u Controls speech production Both on left side of brain u If either of the above speech areas are noted to be affected, see if right sided weakness is also present Speech and motor problems will be reflected on opposite sides of the body
Left vs. Right n This theory of the structure and functions of the mind suggests that the two different sides of the brain control two different “modes” of thinking. It also suggests that each of us prefers one mode over the other. Left Brain Right Brain Logical Sequential Rational Analytical Objective Looks at parts Random Intuitive Holistic Synthesizing Subjective Looks at wholes
Left vs. Right cont. Note: Notice how Broca & Wernicke’s area are on Left side Hearing difference: Speech on Left vs. Music on Right
CVA Signs and Symptoms n n n Trouble with walking, sudden dizziness, loss of balance or loss of coordination. Trouble with speaking and/or understanding, confusion, slurred words or be unable to find the right words to explain what is happening (aphasia). Paralysis or numbness on one side of the body or face. Trouble with seeing in one or both eyes. Sudden blurred or blackened vision, or seeing double. Headache; a sudden, severe "bolt out of the blue" headache which may be accompanied by vomiting, dizziness or altered consciousness.
What to do… n Initial assessment u u u n AVPU, ABC’s, life threats, etc. Sample history Vitals Pupils Glasgow Time of onset VERY important! F. A. S. T. or Cincinnati Stroke Scale u Remember… you only need to have one of these signs for positive CVA identification.
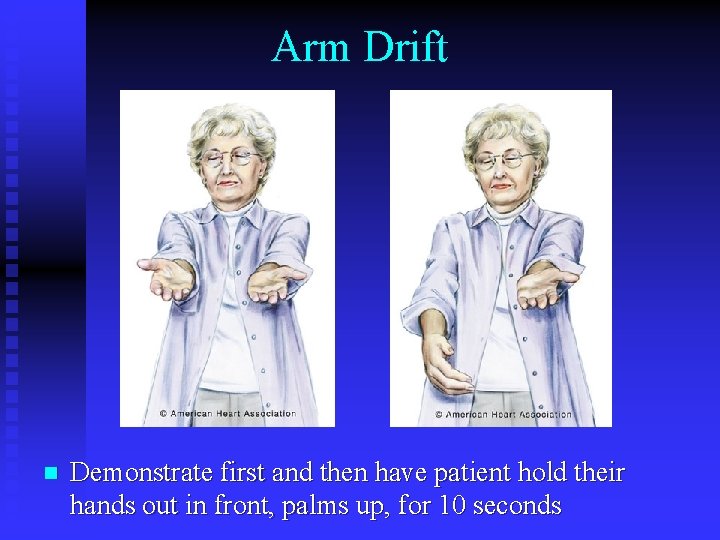
Cincinnati Stroke Scale or FAST F – look for facial drooping u Have patient smile large enough to see teeth n A – check for arm drift u Patient holds hands out in front for 10 seconds with eyes closed, palms up n S – check for slurred speech n T – teach patients to call 911 – time is essential n
Facial Drooping n Ask the patient to smile real big and show you their teeth u Best way to see if a droop is present
Arm Drift n Demonstrate first and then have patient hold their hands out in front, palms up, for 10 seconds
Clarity of Speech Most likely you’ll know by now if there is a speech problem n Can have the patient repeat after you any words or a sentence you give them n u “You can’t teach an old dog new tricks”
7 D’S Of Stroke Care Detection – of signs and symptoms n Dispatch – advise to call 911 n Delivery – to the appropriate facility n Door – emergent triage in the ED n Data – appropriate tests n Decision – to administer a fibrinolytic or not n Drug – must administer the fibrinolytic within 3 hours of onset of symptoms n
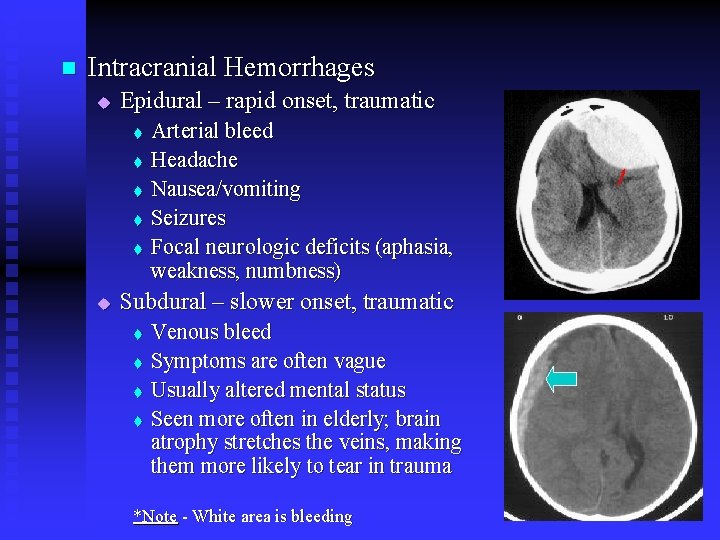
n Intracranial Hemorrhages u Epidural – rapid onset, traumatic t t t u Arterial bleed Headache Nausea/vomiting Seizures Focal neurologic deficits (aphasia, weakness, numbness) Subdural – slower onset, traumatic t t Venous bleed Symptoms are often vague Usually altered mental status Seen more often in elderly; brain atrophy stretches the veins, making them more likely to tear in trauma *Note - White area is bleeding
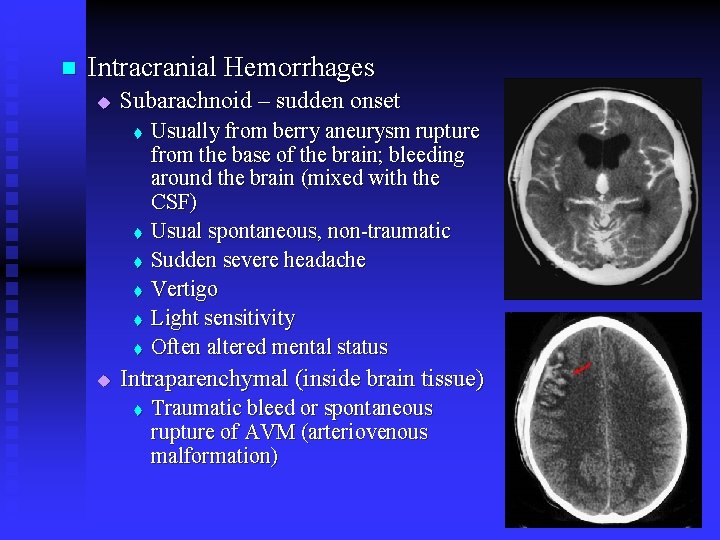
n Intracranial Hemorrhages u Subarachnoid – sudden onset t t t u Usually from berry aneurysm rupture from the base of the brain; bleeding around the brain (mixed with the CSF) Usual spontaneous, non-traumatic Sudden severe headache Vertigo Light sensitivity Often altered mental status Intraparenchymal (inside brain tissue) t Traumatic bleed or spontaneous rupture of AVM (arteriovenous malformation)
Region X EMS Protocol Stroke Brain Attack
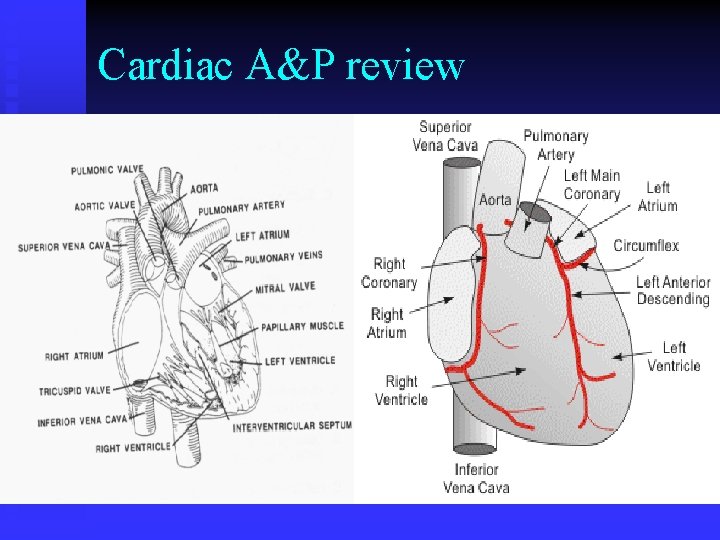
Cardio-Pulmonary A&P n n We need to know what is being affected and how that is shown as sign and/or symptoms Knowing the following general A&P will assist in assessment u Veins u Arteries u Other tissues
Cardiac A&P review
Coronary Circulation Coronary arteries and veins n Myocardium extracts the largest amount of oxygen as blood moves into general circulation n Oxygen uptake by the myocardium can only improve by increasing blood flow through the coronary arteries n If the coronary arteries are blocked, they must be reopened if circulation is going to be restored to that area of tissue supplied n
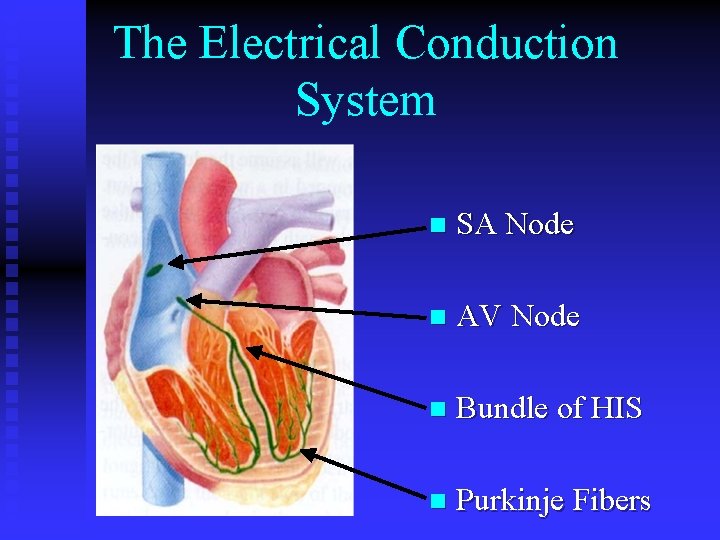
The Electrical Conduction System n SA Node n AV Node n Bundle of HIS n Purkinje Fibers
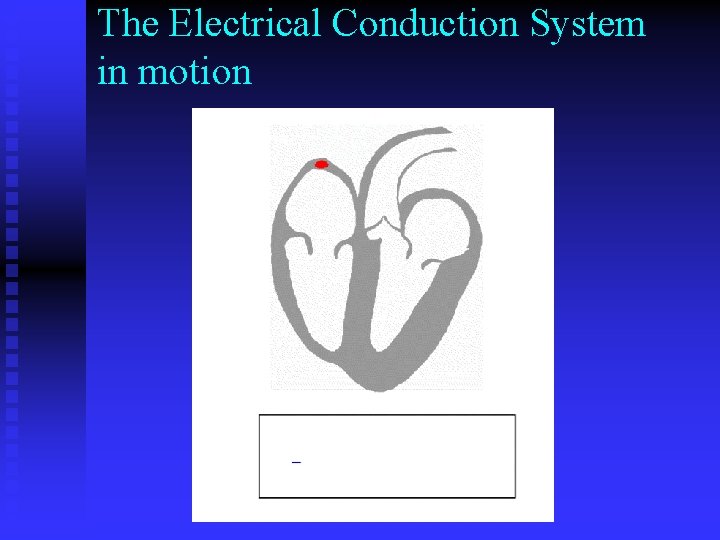
The Electrical Conduction System cont. n SA node: Fastest rate of automaticity. “Primary” pacemaker of the heart. Rate: 60 to 100 bpm n AV node: Has a delay which allows for atrial contraction and a more filling of the ventricles. Rate: 40 -60 bpm (if not driven by the rate above) n Bundle of His: Has the ability to self-initiate electrical activity Rate: 40 -60 bpm n Purkinje Fibers: Network of fibers that carry electrical impulses directly to ventricular muscle. Rate: 20 -40 bpm (if not driven by the rate above)
The Electrical Conduction System in motion
Electrocardiogram (ECG/EKG) n It’s name is made of 3 different parts: electro, because it is related to electrical activity u cardio, Greek for heart u gram, a Greek root meaning "to write" u
12 -Lead Electrodes n n A lead is a tracing of the electrical activity between 2 electrodes Leads view the heart from the front of the body u Top, bottom, right, and left side of heart Leads view the heart as if it were sliced in half horizontally u Front, back, right, and left sides of heart Each lead has a positive and a negative electrode
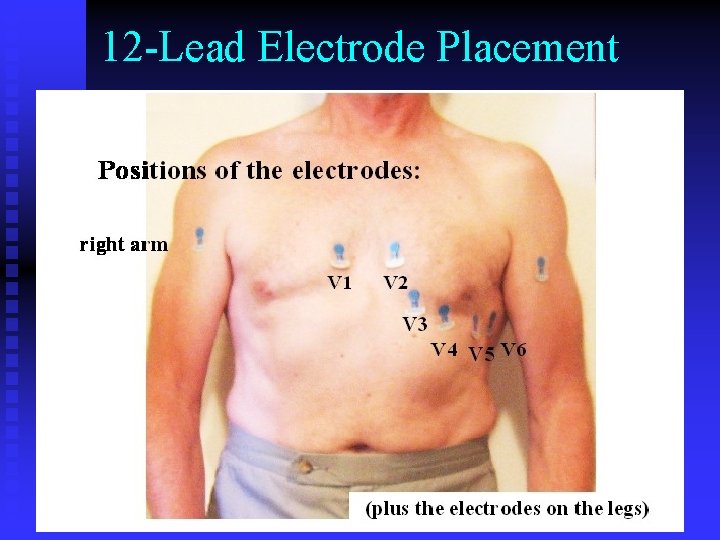
12 -lead ECG n A 12 -lead ECG is made up of a tracing of the electrical activity of the heart from 12 different points of view. The point of view comes from the location of the positive electrode of each lead. The positioning of these electrodes is broken down into 3 categories; The limb leads (lead I, II & III) u The augmented leads (a. VR, a. VL & a. VF) u The precordial/chest leads (V 1, V 2, V 3, V 4, V 5, V 6) u
Standard 12 -Lead EKG n Six limb leads u Leads I, III, a. VR, a. VL, a. VF n Six chest leads (precordial leads) u V 1, V 2, V 3, V 4, V 5, V 6 n Information from 12 leads obtained from the attachment of only 10 electrodes
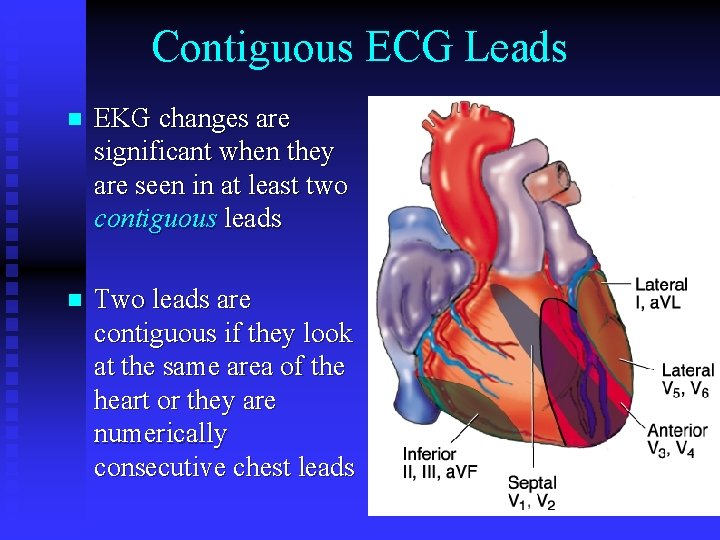
Contiguous ECG Leads n EKG changes are significant when they are seen in at least two contiguous leads n Two leads are contiguous if they look at the same area of the heart or they are numerically consecutive chest leads
12 -Lead Electrode Placement
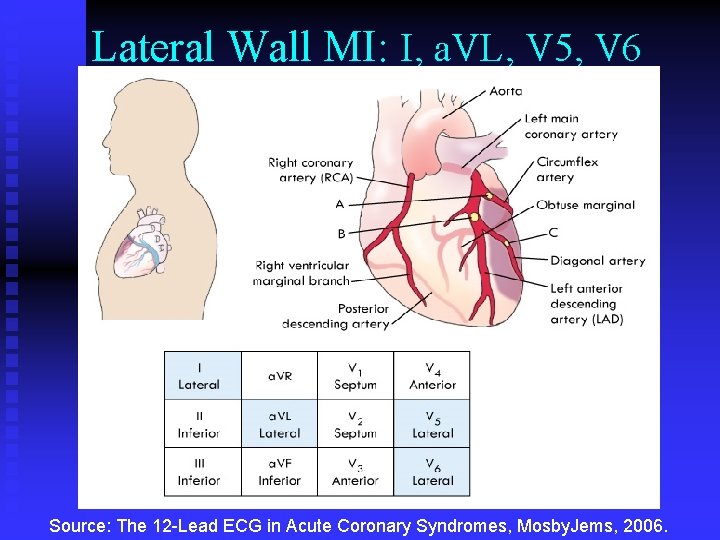
Lateral Wall MI: I, a. VL, V 5, V 6 Source: The 12 -Lead ECG in Acute Coronary Syndromes, Mosby. Jems, 2006.
Complications of Lateral Wall MI n I, a. VL, V 5, V 6 Complications arise due to the conduction components that are in the septum u Conduction dysrhythmias most common u Second degree Type II – classical t 3 rd degree – complete heart block t Bundle branch blocks t u Monitor patient closely for these blocks t 2 nd degree Type II and 3 rd degree are serious dysrhythmias that need to be treated aggressively with TCP
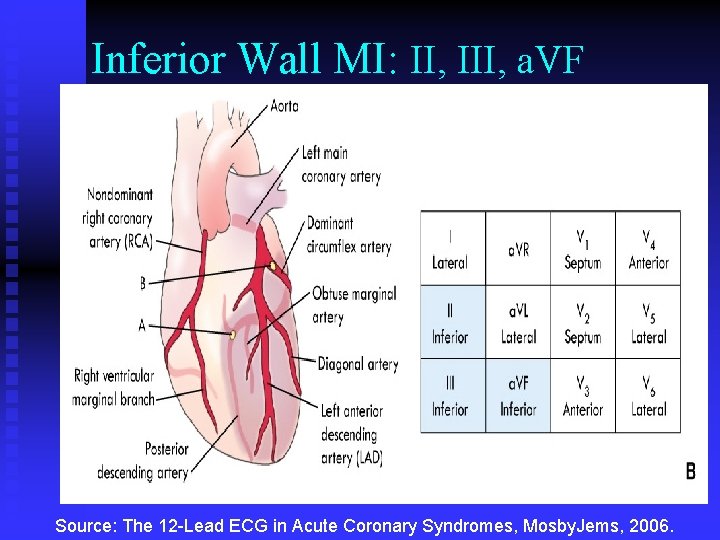
Inferior Wall MI: II, III, a. VF Source: The 12 -Lead ECG in Acute Coronary Syndromes, Mosby. Jems, 2006.
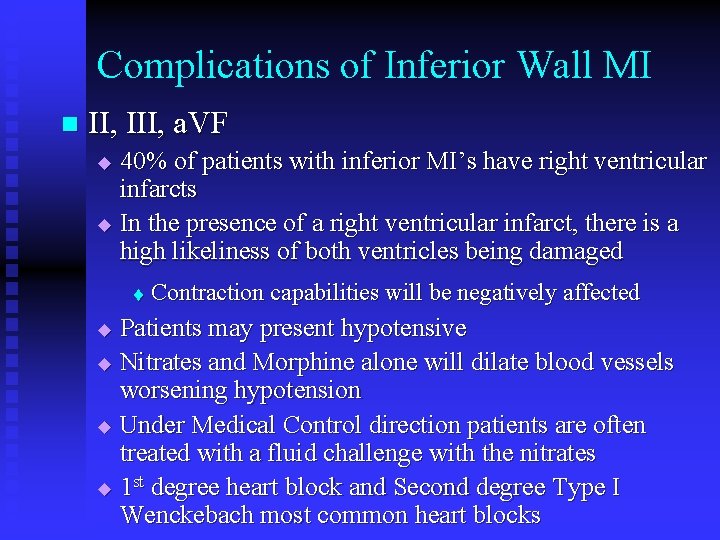
Complications of Inferior Wall MI n II, III, a. VF 40% of patients with inferior MI’s have right ventricular infarcts u In the presence of a right ventricular infarct, there is a high likeliness of both ventricles being damaged u t Contraction capabilities will be negatively affected Patients may present hypotensive u Nitrates and Morphine alone will dilate blood vessels worsening hypotension u Under Medical Control direction patients are often treated with a fluid challenge with the nitrates u 1 st degree heart block and Second degree Type I Wenckebach most common heart blocks u
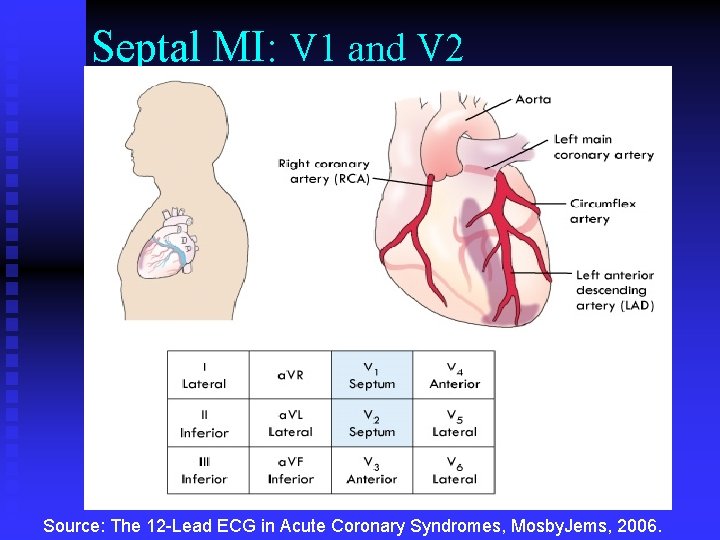
Septal MI: V 1 and V 2 Source: The 12 -Lead ECG in Acute Coronary Syndromes, Mosby. Jems, 2006.
Complications of Septal Wall MI V 1 and V 2 n Significant amount of conduction components are in the septal area n Patient predisposed to dysrhythmias n Second degree Type II – classical u 3 rd degree heart block u Bundle branch block u Lethal heart blocks treated aggressively - TCP n Rare to have a septal MI alone n u Common to have anterior or lateral involvement along with septal area
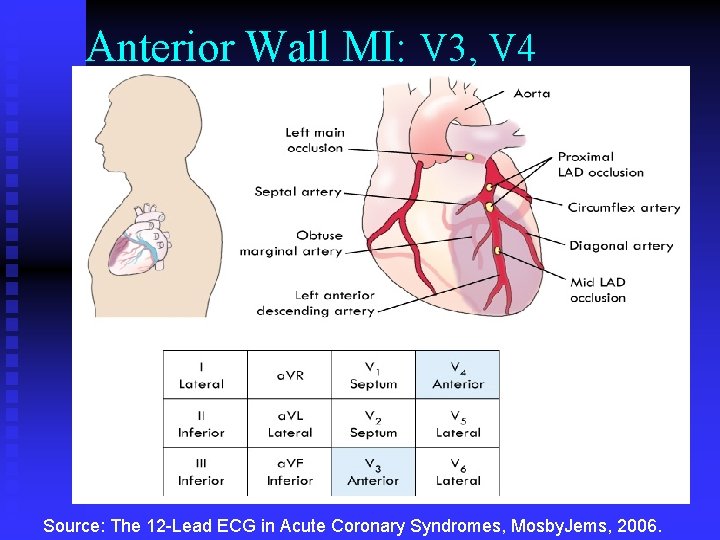
Anterior Wall MI: V 3, V 4 Source: The 12 -Lead ECG in Acute Coronary Syndromes, Mosby. Jems, 2006.
Complications of Anterior Wall MI V 3, V 4 n Known as the “widowmaker” due to the potential for a massive area of infarction from blockage of the large amount of myocardium supplied by the LAD (left anterior descending artery) n Often the septal or lateral walls are also involved n Watch for lethal ventricular dysrhythmias and cardiogenic shock n Second degree Type II and 3 rd degree heart block are more common than other blocks n
Anterior Wall MI cont. n n Early death within a few days often from CHF u Massive area of ventricular tissue infarcted if LAD totally occluded Important to obtain history of recent MI diagnosis and hospital discharge u Increased incidence of ventricular tachycardia (VT) and ventricular fibrillation (VF) up to 1 -2 weeks post acute anterior MI
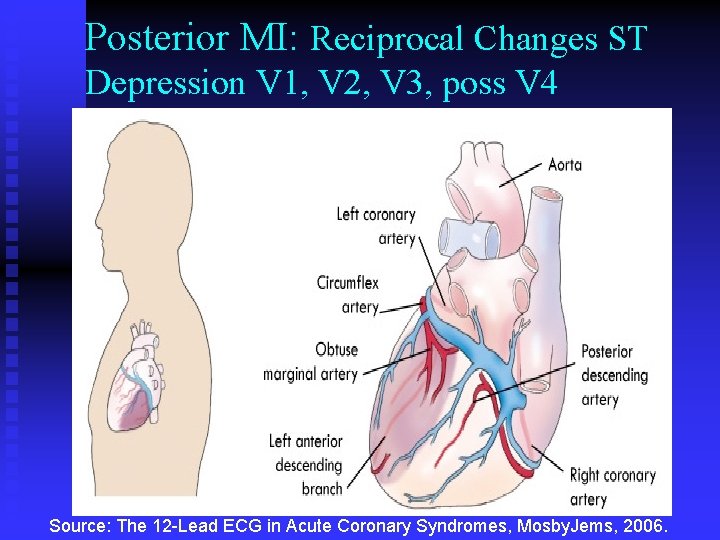
Posterior MI: Reciprocal Changes ST Depression V 1, V 2, V 3, poss V 4 Source: The 12 -Lead ECG in Acute Coronary Syndromes, Mosby. Jems, 2006.
Atypical Presentation in the Elderly n n n Most frequent symptoms of acute MI: Shortness of breath Fatigue and weakness (“I just don’t feel well”) Abdominal or epigastric discomfort Often have preexisting conditions making this an already vulnerable population Hypertension CHF Previous AMI Likely to delay seeking treatment
Atypical Presentation in Women n Discomfort described as: n Frequent acute symptoms: Aching Shortness of breath Tightness Weakness Pressure Unusual fatigue Sharpness Cold sweats Burning Dizziness Fullness Nausea/vomiting Tingling Often have no actual chest pain to offer as a complaint. Often the pain is in the back, shoulders, or neck
Atypical Presentation in the Patient With Diabetes n Atypical presentation due to autonomic dysfunction n Common signs/symptoms: Generalized weakness u Generalized feeling of not being well u Syncope u Lightheadedness u Change in mental status u
Remember… n Watch out for the “triple threat” Elderly Female Diabetic history n How many elderly women with diabetes do you see in your facility? t Probably lots!!!
Using Region X Cardiac SOP’s Care is initiated for all patients based on physical assessment n A pediatric patient is considered under the age of 16 (15 and less) n EMS is not to delay care to contact Medical Control – call after care initiated n But, prompt communication is encouraged n
Region X Cardiac SOP’s cont. Obtaining a history and performing an assessment can often provide valuable information n Consider underlying causes for all situations n In the cardiac SOP’s, think of the 6 H’s and 5 T’s as possible causes of the problem as you progress through assessment & treatment for the patient n
6 H’s n n n Ø Hypovolemia Ø Hypoxia Ø Hydrogen ion acidosis Hyper/hypokalemia Ø (high/low potassium levels) Hypothermia Ø Hypoglycemia Ø Give fluids (20 ml/kg) Provide supplemental O 2 Ventilate to blow off CO 2 Difficult to determine in the field; consider in diabetic ketoacidosis & renal dialysis Attempt rewarming Check blood glucose on all altered mental status pts
5 T’s Toxins (overdose) Tamponade, cardiac Tension pneumothorax Ø n Thrombosis, coronary (ACS) or Thrombosis, pulmonary (embolism) Ø n Trauma n n n Ø Ø Ø Think “out of the box” Check for JVD, B/P, absent/decreased breath sounds, difficulty bagging Obtain 12 lead when applicable; good history taking to lead to suspicions (travel, surgery, immobility) What is history of current status?
Region X Protocol Acute Coronary Syndrome
Assessment for CO Exposure n EMS may be summoned to monitor the air quality for the presence of carbon monoxide u n Airborne CO meters are used and documentation made whethere is a need for patient transport or not A more immediate concern is the level of CO in the patient’s blood RAD 57 monitors are a non-invasive tool that allows results in less than 30 seconds u Rapid diagnosis leads to rapid and appropriate treatment u
Signs and Symptoms CO Poisoning n Carboxyhemoglobin levels of <15 – 20% Mild severity Headache t Nausea and vomiting t Dizziness t Blurred vision t
Signs and Symptoms CO Poisoning n Carboxyhemoglobin levels of 21 – 40% Moderate severity Confusion t Syncope t Chest pain t Dyspnea t Tachycardia t Tachypnea t Weakness t
Signs and Symptoms CO Poisoning n Carboxyhemoglobin levels of 41 - 59% Severe Dysrhythmias t Hypotension t Cardiac ischemia t Palpitations t Respiratory arrest t Pulmonary edema t Seizures t Coma t Cardiac arrest t
Signs and Symptoms CO Poisoning n Carboxyhemoglobin levels of >60% Fatal n Cherry red skin is not listed as a sign u An unreliable finding
Increased Risks n Health and activity levels can increase the risk of signs and symptoms at lower concentrations of CO u u Infants Women who are pregnant t u u Elderly Physical conditions that limit the body’s ability to use oxygen t t u Fetus at greatest risk because fetal hemoglobin has a greater affinity for oxygen and CO compared to adult hemoglobin Emphysema, asthma Heart disease Physical conditions with decreased O 2 carrying capacity t Anemia – iron-deficiency & sickle cell
Patient Assessment Tools n Continuously monitor Sp. O 2 and Sp. CO levels Remember that Sp. O 2 may be falsely normal u If EMS has a CO-oximeter (ie: Rad 57), EMS will report the findings to the ED staff t Generally, results >3% indicate suspicion for CO exposure in non-smoker u Cardiac monitor n 12 lead EKG obtained and transmitted to ED n
Pulse Oximetry Device to analyze infrared signals n Measures the percentage of oxygenated hemoglobin (saturated Hgb) n Can mistake carboxyhemoglobin for oxyhemoglobin and give a false normal level of oxyhemoglobin n Never rely just on the pulse oximetry reading; always correlate with clinical assessment n
Pulse CO-oximeter Device (ie: RAD 57) n n n Hand-held device Attaches to a finger tip similar to pulse ox device Most commonly measured gases in commercial devices include Carbon monoxide (Sp. CO) u Oxygen (Sp. O 2) u Methemoglobin (Sp. Met) u u n Other combustible gases Without the device, need to draw a venous sample of blood to test for CO levels
Pulse CO-oximeter Tool n Firefighters have an increased exposure risk Active firefighting u Inhaled products of combustion in structure fire u Inhaled exhaust from vehicles and power tools u n Rehab operations more efficient when firefighter can be screened at the scene and released back to duty u Pulse rate, oxygen saturation, carboxyhemoglobin level evaluated
Treatment CO Poisoning Increasing the concentration of inhaled oxygen can help minimize the binding of CO to hemoglobin n Some CO may be displaced from hemoglobin when the patient increases their inhaled oxygen concentrations n Treatment begins with high index of suspicion and removal to a safer environment n Immediately begin 100% O 2 delivery n
Treatment CO Poisoning n Some guidelines indicate to initiate treatment when Sp. CO levels exceed 10%; some at 12% Treatment levels vary significantly u If you do not have a CO-oximeter to use, maintain a heightened level of suspicion and base treatment on symptoms u n Monitor for complications related to CO exposure Seizures u Cardiac dysrhythmias u Cardiac ischemia u
CO Poisoning and CPAP n CPAP could assist in fully oxygenating hemoglobin n If considered, EMS must call Medical Control for permission to use CPAP ECRN will obtain report with patient information u ECRN must discuss with ED MD to obtain order to use CPAP in the field u
Region X SOP CO / Smoke Inh
Additions to CO / Smoke Inhalation SOP n n Sp. CO levels < 5% 3 - not treatment Sp. CO levels ≥ 5% with symptoms 4 u 100% O 2; ED evaluation Sp. CO levels ≥ 10% u 100% O 2; ED evaluation Sp. CO levels ≥ 25% u 100% O 2; ED evaluation u Consider hyperbaric chamber Footnotes: see next page
Key Comments of CO / Smoke Inhalation SOP 2. Do not rely on pulse oximetry to indicate degree of hypoxia with CO exposure and consider cyanide poisoning in presence of smoke / fire situations. See Carbon Monoxide/Smoke Inhalation SOP. 3. A normal Sp. CO level does not negate the need for further management of the symptomatic patient as other diagnoses may still be present. 4. ≥ 5% Mild headache 6 -10% Mild headache, shortness of breath with exertion 11 -20% Moderate headache, shortness of breath 21 -30% Worsening headache, nausea, dizziness, fatigue 31 -40% Severe headache, vomiting, vertigo, altered judgment 41 -50% Confusion, syncope, tachycardia 51 -60% Seizures, shock, apnea, coma NOTE: If indicated, consider conscious sedation intubation. Consider cyanide poisoning in presence of smoke/fire situations.
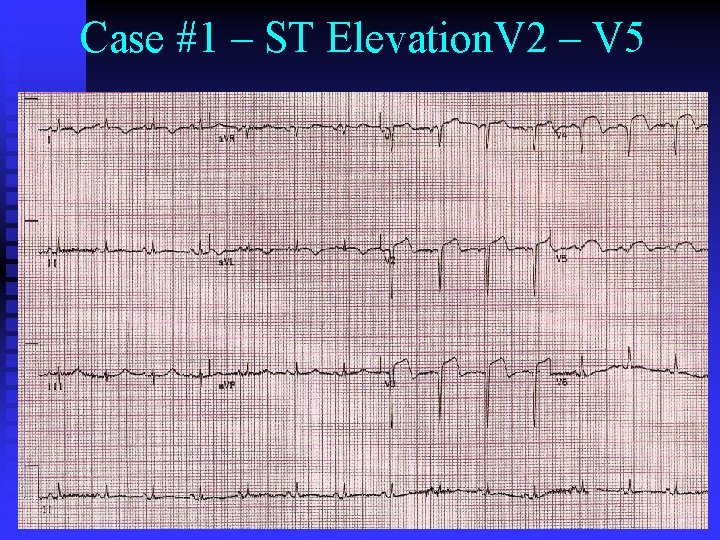
Case #1 45 year-old patient who complains of chest heaviness & lightheadedness n VS: 90/56; P – 86; R - 22 n Is there ST elevation (EKG next slide): u If so, where? n n What are you going to do for this patient?
Case #1 – ST Elevation. V 2 – V 5
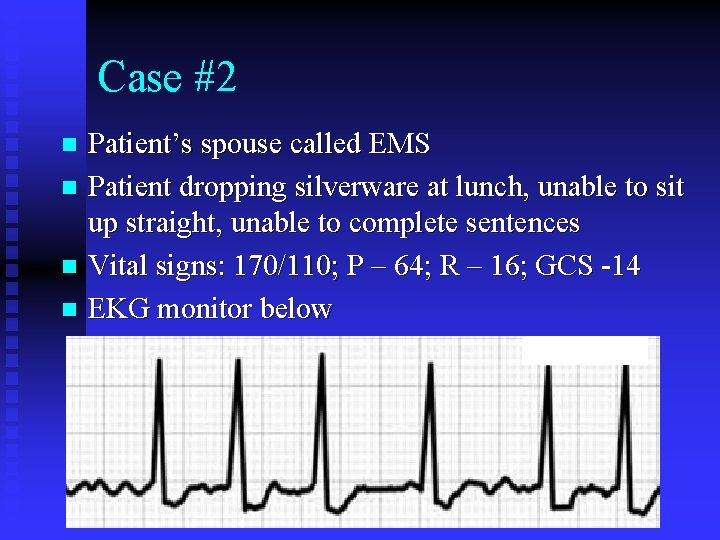
Case #2 Patient’s spouse called EMS n Patient dropping silverware at lunch, unable to sit up straight, unable to complete sentences n Vital signs: 170/110; P – 64; R – 16; GCS -14 n EKG monitor below n
Case #2 What is your impression? n What is the cardiac rhythm? n Atrial fibrillation u How does this rhythm relate to any impressions? u n What assessments need to be done? Blood sugar level for all patients with altered level of consciousness u Cincinnati stroke scale u
Case #2 n Cincinnati stroke scale Ask the patient to smile real big showing you their teeth u Ask the patient to put their hands out in front, palms up, and close their eyes u t u Hold the position for 10 seconds Ask the patient to repeat a saying t “You can’t teach an old dog new tricks”
Case #2 n What’s the most important question to ask the patient? n When did the symptoms begin?
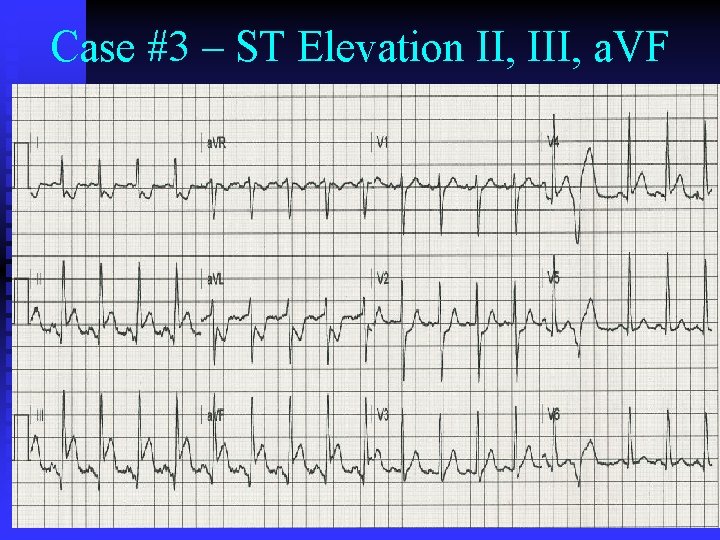
Case #3 58 year-old male patient who complains of chest pain radiating down the left arm after working out in the gym n VS: 110/72; P – 100; R - 18 n Is there ST elevation (EKG next slide): u If so, where? n n What are you going to do for this patient?
Case #3 – ST Elevation II, III, a. VF
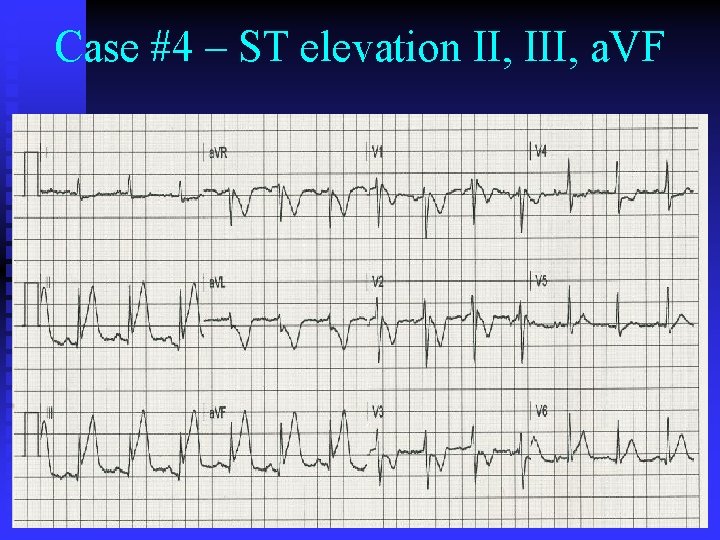
Case #4 36 year-old patient who passed out standing in line at a bank n VS: 128/78; P – 80; R - 20 n Is there ST elevation (EKG next slide): u If so, where? n n What are you going to do for this patient?
Case #4 – ST elevation II, III, a. VF
Case #5 n Received call from a 10 year-old child that he could not wake up his mother. On arrival the 34 year-old female was unconscious with signs of seizure activity. 2 other children are in the home. What are your general impressions/suspicions? n What is included in your assessment? n What is your treatment? n
Case #5 n n Upon scene arrival, a faint odor of exhaust was noted Evaluate the patient for normal reasons of altered level of consciousness including history of seizure disorder and suicide attempt After 5 minutes on scene, rescue personnel began complaining of headache A car was found running in the garage directly under the bedroom/bathroom
Bibliography n n n Various on-line photos e. How. com Previous EMS CE packets u u u n 2006 Condell CE Module February 2009 Condell CE February LFFD CE add-on (Jon Bardi) CMC SOP pages