The white cells 1 granulocy es monocytes and

















- Slides: 27
The white cells 1: granulocy es, monocytes and their benign disorders
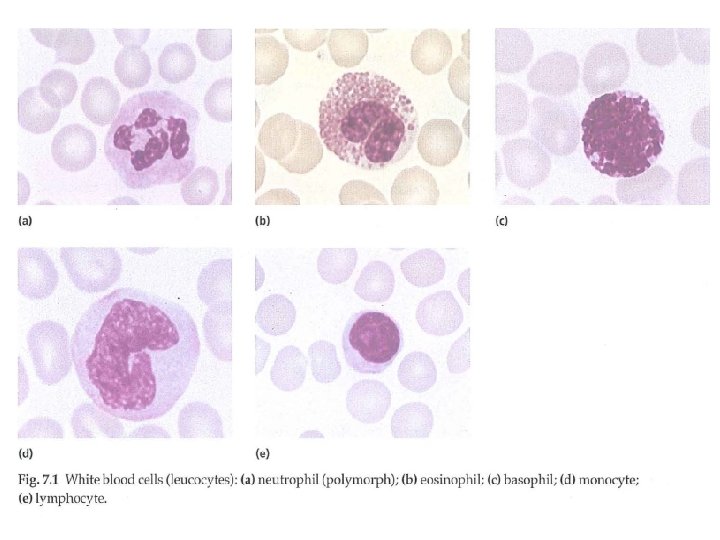
The white blood cells (leucocytes) may be divided into two broad groups: 1 -the phagocytes Granulocytes, which include three types of cell-neutrophils (polymorphs), eosinophils and basophils-together with monocytes comprise the phagocyte 2 -immunocytes Note : Only mature phagocytic cells and lymphocytes are found in normal peripheral blood
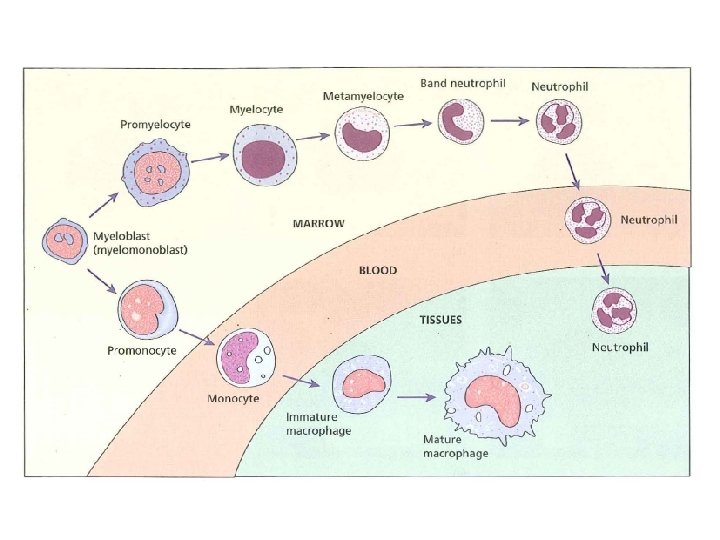
Granulopoiesis The blood granulocytes and monocytes are formed in the bone marrow from a common precursor cell In the granulopoietic series progenitor cells which are: myeloblasts, promyelocytes and myelocytes form a proliferative or mitotic pool of cells while the metamyelocytes, band segmented granulocytes make up a post-mitotic maturation compartment Large numbers of band segmented neutrophils are held in the marrow as a 'reserve pool' or storage compartment.
In the bone marrow normally contains more myeloid cells than erythroid cells in the ratio of 2 : 1 to 12 : 1 the largest proportion being neutrophils and metamyelocytes. In the stable or normal state, the bone marrow storage compartment contains 10 -15 times the number of granulocytes found in the peripheral blood. Following their release from the bone marrow, granulocytes spend only 6 -10 h in the circulation before moving into the tissues where they perform their phagocytic function
In the blood stream there are two pools usually of about equal size: the circulating pool (included in the blood count) and the marginating pool (not included in the blood count). It has been estimated that they spend on average 4 -5 days in the tissues before they are destroyed during defensive action or as the result of senescence.
Control of granulopoiesis: myeloid growth factors Many growth factors are involved in this maturation process including : interleukin-1 (IL-1) IL-3 IL-5 (for eosinophils), IL-6 IL-11 granulocytemacrophage colony stimulating factor (GM -CSF) granulocyte CSF (G-CSF) monocyte CSF (MCSF)
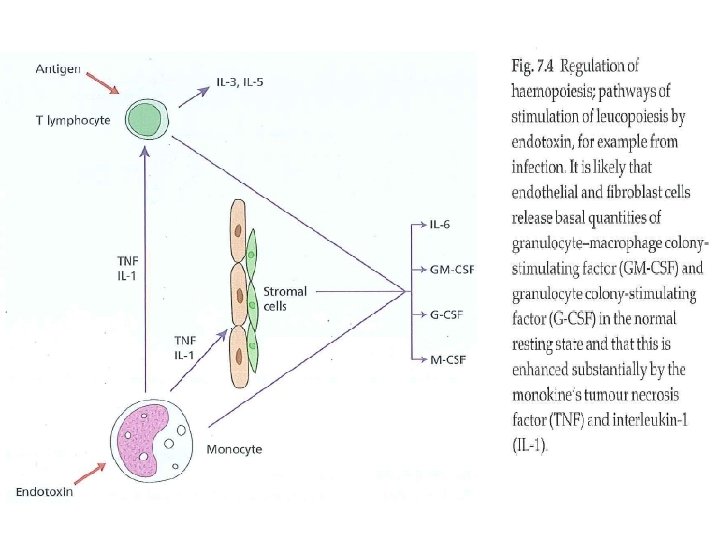
Function of growth factors The growth factors stimulate proliferation and differentiation and also affect the function of the mature cells on which they act e. g. Increased granulocyte and monocyte production in response to an infection is induced by increased production of growth factors from stromal cells and T lymphocytes, stimulated by endotoxin, IL-1 or tumour necrosis factor (TNF)
The normal function of neutrophils and monocytes may be divided into three phases: Chemotaxis (cell mobilization and migration) The phagocyte is attracted to bacteria or the site of inflammation by chemotactic substances. Phagocytosis The foreign material (e. g. bacteria, fungi) or dead or damaged cells of the host are Phagocytosed Killing and digestion This occurs by oxygen dependent and oxygen-independent pathways.
Functional Disorders of Phagocytic Leucocytes 12
Disorders characterised by neutrophil dysfunction in’s 1. Impaired adhesion: Congenital leucocyte adherence deficiency (Deficiency of CD 11/CD 18 surface glycoproteins) Drugs: corticosteroids, ency alcohol me 2. Impaired motility: Hyperimmunoglobulin E syndrome Chediak-Higashi syndrome 13
Benign disorders of granulocyte morphology 1 -Pelger-Huet anomaly In this uncommon condition bilobed neutrophils are found in the peripheral blood. Occasional unsegmented neutrophils are also seen. Inheritance is autosomal dominant.
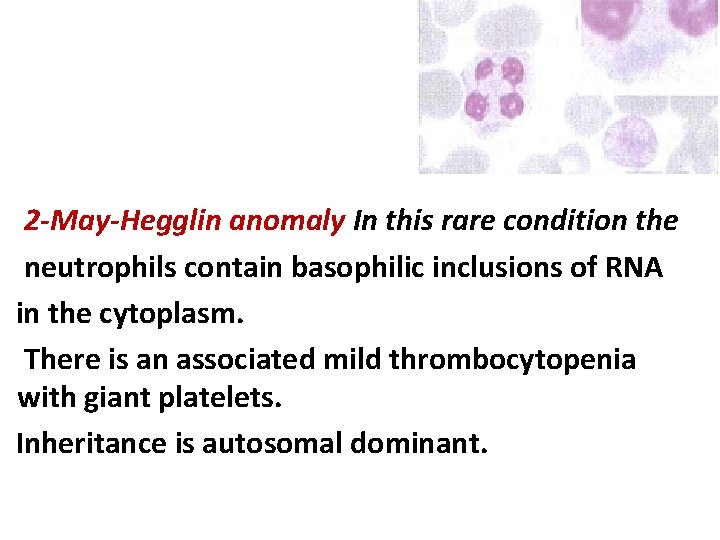
2 -May-Hegglin anomaly In this rare condition the neutrophils contain basophilic inclusions of RNA in the cytoplasm. There is an associated mild thrombocytopenia with giant platelets. Inheritance is autosomal dominant.
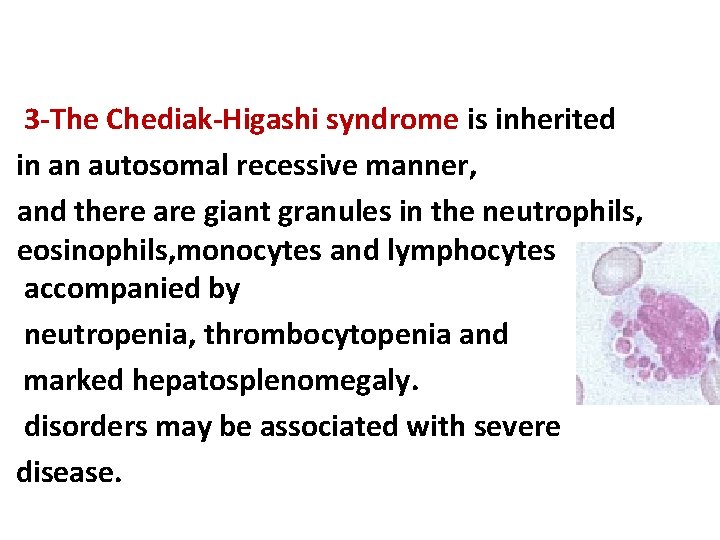
3 -The Chediak-Higashi syndrome is inherited in an autosomal recessive manner, and there are giant granules in the neutrophils, eosinophils, monocytes and lymphocytes accompanied by neutropenia, thrombocytopenia and marked hepatosplenomegaly. disorders may be associated with severe disease.
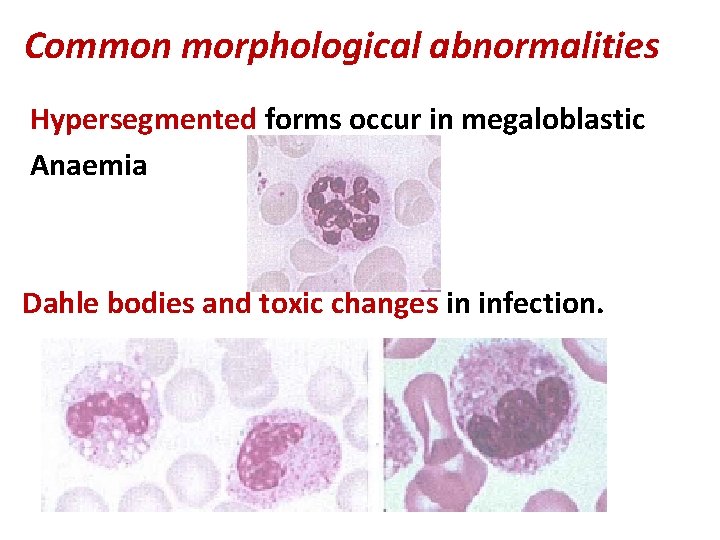
Common morphological abnormalities Hypersegmented forms occur in megaloblastic Anaemia Dahle bodies and toxic changes in infection.
The 'drumstick' appears on the nucleus of a proportion of the neutrophils in normal females and is caused by the presence of two X chromosomes. Pelger cells are seen in the benign congenital abnormality but also in patients with acute myeloid leukaemia or myelodysplasia
Shift to the left: increase in the number of band forms and the occasional presence of more primitive cells in the peripheral blood. Leukoerythroblastic picture: a presence of a shift to left plus nucleated RBC in the peripheral blood.
Causes of leucoerythroblastic blood film Metastatic neoplasm in the marrow Primary myelofi brosis Acute and chronic myeloid leukaemia Myeloma, lymphoma Miliary tuberculosis Severe megaloblastic anaemia Severe hemolysis Osteopetrosis 22
Causes of leucoerythroblastic blood film Metastatic neoplasm in the marrow Primary myelofi brosis Acute and chronic myeloid leukaemia Myeloma, lymphoma Miliary tuberculosis Severe megaloblastic anaemia Severe hemolysis Osteopetrosis 23
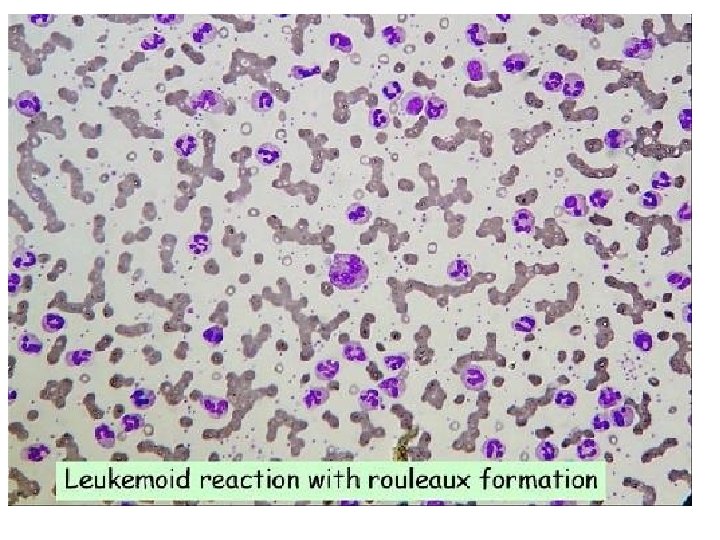
The Leukomoid Reaction a reactive excessive leukocytosis with the presence of immature cells (myeloblasts, promyelocytes and myelocyte) in the peripheral blood. In other words (leukocytosis + left shift). Usually it is a neutrophil leukocytosis. It can be lymphoid Causes : Severe infection Severe haemolysis