The Alternative Quality Contract Lisa Whittemore MSW MPH





- Slides: 37
The Alternative Quality Contract Lisa Whittemore, MSW, MPH Blue Cross Blue Shield of Massachusetts Presentation to Maine Accountable Care Innovation November 18, 2014
Agenda § Context for AQC Development § Overview of AQC Model § AQC Results: Initial Years § AQC Support and Improvement Analytics § Local and National Policy Context § Summary and Discussion Blue Cross Blue Shield of Massachusetts 2
Context for AQC Development Blue Cross Blue Shield of Massachusetts 3
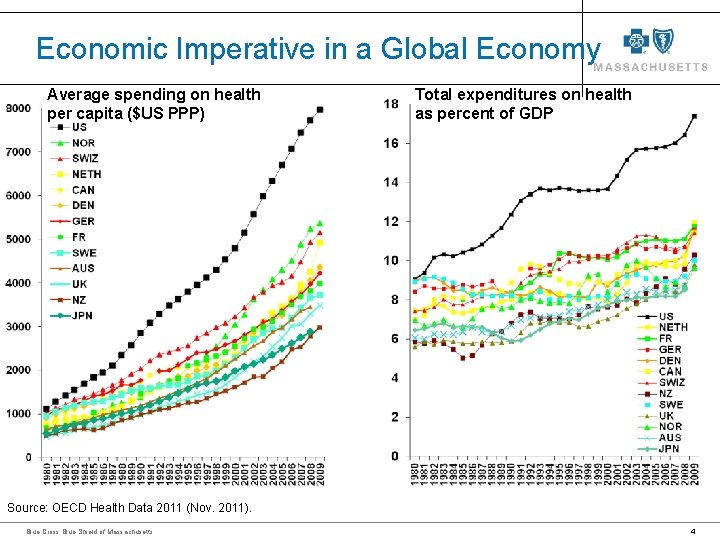
Economic Imperative in a Global Economy Average spending on health per capita ($US PPP) Total expenditures on health as percent of GDP Source: OECD Health Data 2011 (Nov. 2011). Blue Cross Blue Shield of Massachusetts 4
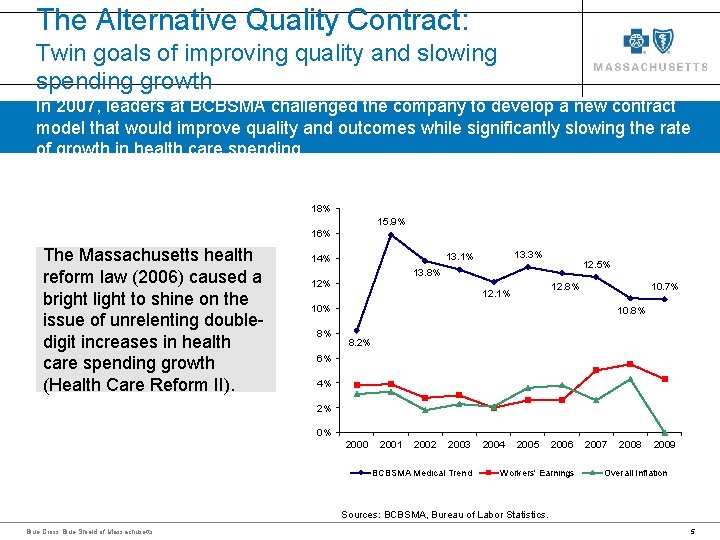
The Alternative Quality Contract: Twin goals of improving quality and slowing spending growth In 2007, leaders at BCBSMA challenged the company to develop a new contract model that would improve quality and outcomes while significantly slowing the rate of growth in health care spending. 18% 15. 9% 16% The Massachusetts health reform law (2006) caused a bright light to shine on the issue of unrelenting doubledigit increases in health care spending growth (Health Care Reform II). 13. 3% 13. 1% 14% 12. 5% 13. 8% 12% 10. 7% 12. 8% 12. 1% 10% 8% 10. 8% 8. 2% 6% 4% 2% 0% 2000 2001 2002 2003 BCBSMA Medical Trend 2004 2005 2006 Workers' Earnings 2007 2008 2009 Overall Inflation Sources: BCBSMA, Bureau of Labor Statistics. Blue Cross Blue Shield of Massachusetts 5
The AQC Model Blue Cross Blue Shield of Massachusetts 6
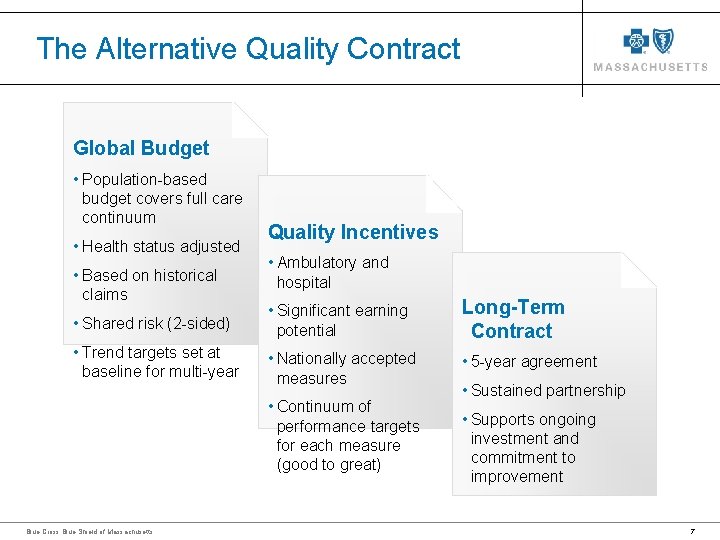
The Alternative Quality Contract Global Budget • Population-based budget covers full care continuum • Health status adjusted • Based on historical claims Quality Incentives • Ambulatory and hospital • Shared risk (2 -sided) • Significant earning potential Long-Term Contract • Trend targets set at baseline for multi-year • Nationally accepted measures • 5 -year agreement • Continuum of performance targets for each measure (good to great) Blue Cross Blue Shield of Massachusetts • Sustained partnership • Supports ongoing investment and commitment to improvement 7
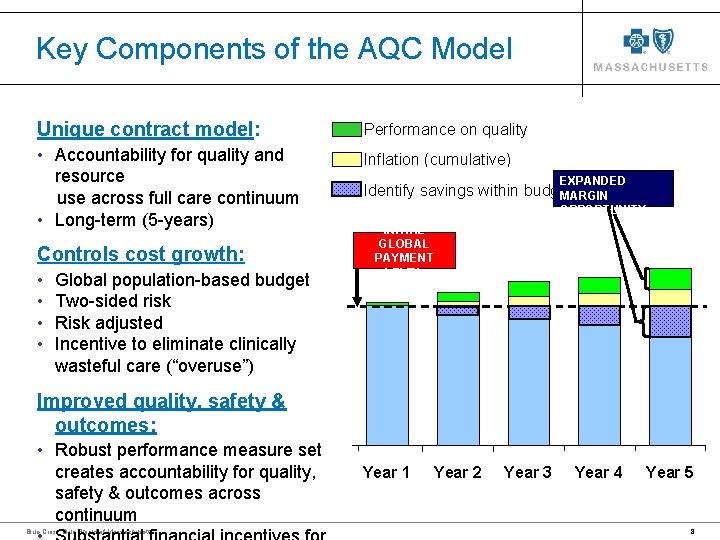
Key Components of the AQC Model Unique contract model: Performance on quality • Accountability for quality and resource use across full care continuum • Long-term (5 -years) Inflation (cumulative) Controls cost growth: • • Global population-based budget Two-sided risk Risk adjusted Incentive to eliminate clinically wasteful care (“overuse”) EXPANDED Identify savings within budget MARGIN OPPORTUNITY INITIAL GLOBAL PAYMENT LEVEL Improved quality, safety & outcomes: • Robust performance measure set creates accountability for quality, safety & outcomes across continuum Blue Cross Blue Shield of Massachusetts Year 1 Year 2 Year 3 Year 4 Year 5 8
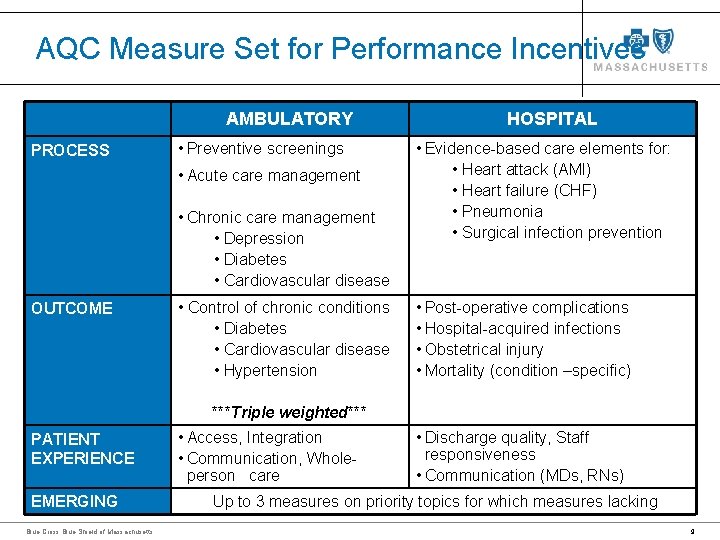
AQC Measure Set for Performance Incentives AMBULATORY PROCESS • Preventive screenings • Acute care management • Chronic care management • Depression • Diabetes • Cardiovascular disease OUTCOME • Control of chronic conditions • Diabetes • Cardiovascular disease • Hypertension HOSPITAL • Evidence-based care elements for: • Heart attack (AMI) • Heart failure (CHF) • Pneumonia • Surgical infection prevention • Post-operative complications • Hospital-acquired infections • Obstetrical injury • Mortality (condition –specific) ***Triple weighted*** PATIENT EXPERIENCE EMERGING Blue Cross Blue Shield of Massachusetts • Access, Integration • Communication, Wholeperson care • Discharge quality, Staff responsiveness • Communication (MDs, RNs) Up to 3 measures on priority topics for which measures lacking 9
Performance Payment Model: Original Blue Cross Blue Shield of Massachusetts 10
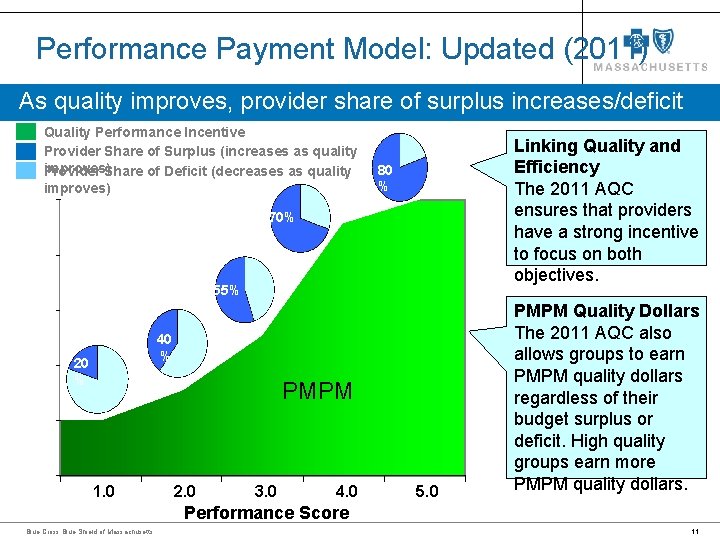
Performance Payment Model: Updated (2011) As quality improves, provider share of surplus increases/deficit Quality Performance Incentive decreases Provider Share of Surplus (increases as quality improves) Provider Share of Deficit (decreases as quality improves) Linking Quality and Efficiency The 2011 AQC ensures that providers have a strong incentive to focus on both objectives. 80 % 70% 55% 40 % 20 % PMPM 1. 0 2. 0 3. 0 4. 0 5. 0 PMPM Quality Dollars The 2011 AQC also allows groups to earn PMPM quality dollars regardless of their budget surplus or deficit. High quality groups earn more PMPM quality dollars. Performance Score Blue Cross Blue Shield of Massachusetts 11
AQC Results Blue Cross Blue Shield of Massachusetts 12
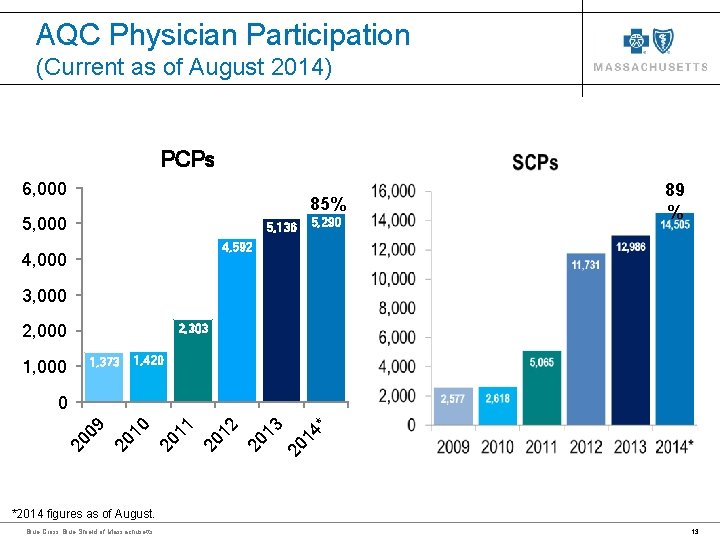
AQC Physician Participation (Current as of August 2014) PCPs 6, 000 85% 5, 000 5, 136 5, 290 89 % 4, 592 4, 000 3, 000 2, 000 1, 000 2, 303 1, 373 1, 420 20 13 20 14 * 20 12 20 11 20 10 20 09 0 *2014 figures as of August. Blue Cross Blue Shield of Massachusetts 13
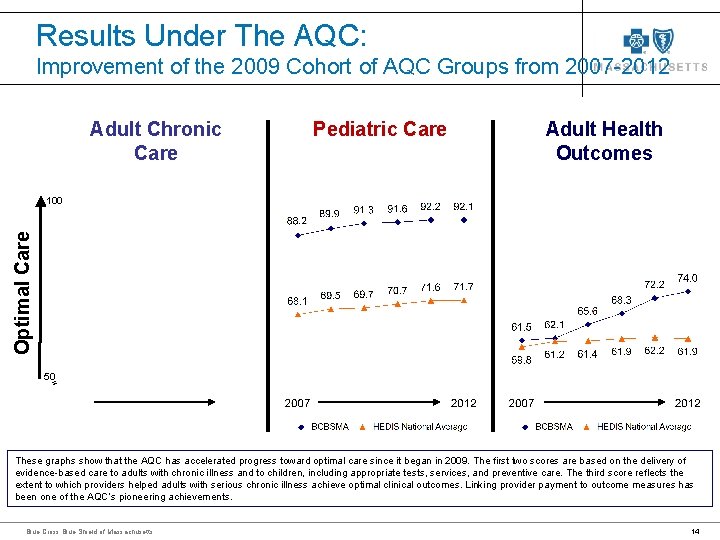
Results Under The AQC: Improvement of the 2009 Cohort of AQC Groups from 2007 -2012 Adult Chronic Care Pediatric Care Adult Health Outcomes Optimal Care 100 50 = These graphs show that the AQC has accelerated progress toward optimal care since it began in 2009. The first two scores are based on the delivery of evidence-based care to adults with chronic illness and to children, including appropriate tests, services, and preventive care. The third score reflects the extent to which providers helped adults with serious chronic illness achieve optimal clinical outcomes. Linking provider payment to outcome measures has been one of the AQC’s pioneering achievements. Blue Cross Blue Shield of Massachusetts 14
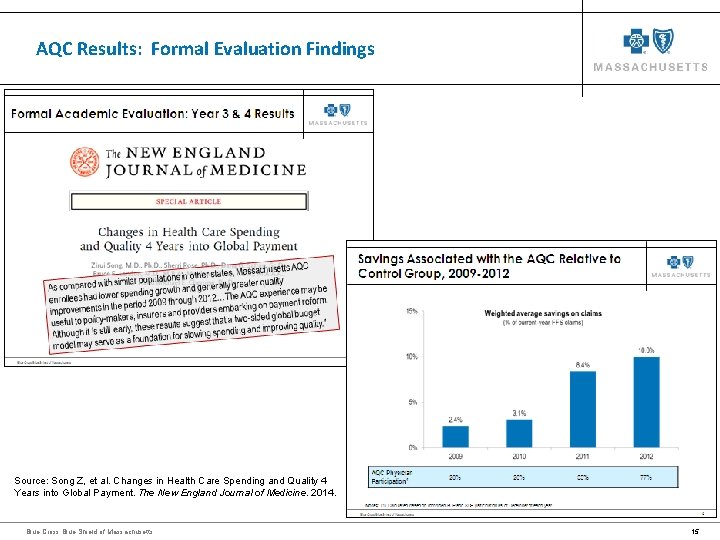
AQC Results: Formal Evaluation Findings Source: Song Z, et al. Changes in Health Care Spending and Quality 4 Years into Global Payment. The New England Journal of Medicine. 2014. Blue Cross Blue Shield of Massachusetts 15
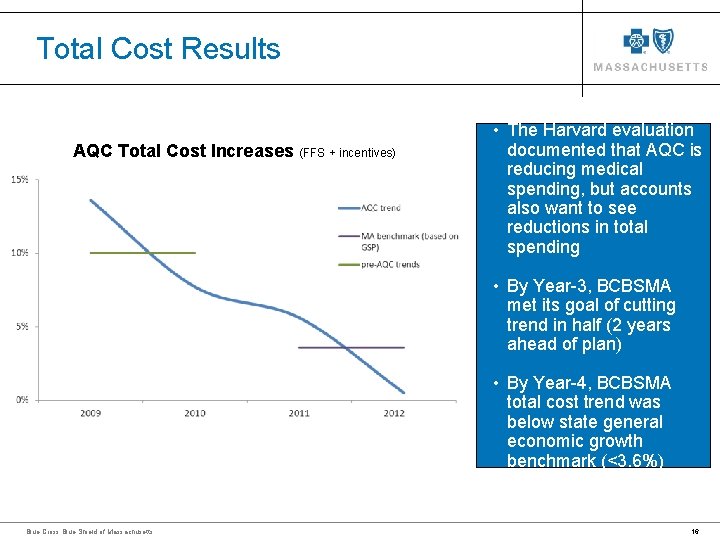
Total Cost Results • The Harvard evaluation AQC Total Cost Increases (FFS + incentives) documented that AQC is reducing medical spending, but accounts also want to see reductions in total spending • By Year-3, BCBSMA met its goal of cutting trend in half (2 years ahead of plan) • By Year-4, BCBSMA total cost trend was below state general economic growth benchmark (<3. 6%) Blue Cross Blue Shield of Massachusetts 16
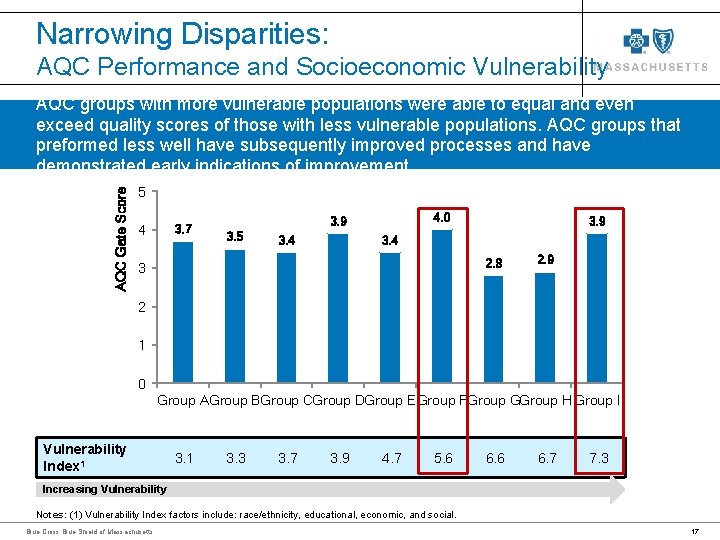
Narrowing Disparities: AQC Performance and Socioeconomic Vulnerability AQC Gate Score AQC groups with more vulnerable populations were able to equal and even exceed quality scores of those with less vulnerable populations. AQC groups that preformed less well have subsequently improved processes and have demonstrated early indications of improvement. 5 3. 7 4 4. 0 3. 9 3. 5 3. 4 3. 9 3. 4 2. 8 3 2. 9 2 1 0 Group AGroup BGroup CGroup DGroup EGroup FGroup GGroup H Group I Vulnerability Index 1 3. 3 3. 7 3. 9 4. 7 5. 6 6. 7 7. 3 Increasing Vulnerability Notes: (1) Vulnerability Index factors include: race/ethnicity, educational, economic, and social. Blue Cross Blue Shield of Massachusetts 17
Five Keys Ingredients to AQC Success 1 Measures. The measures are nationally accepted as clinically appropriate so there is wide support for improving performance on these indicators. 2 Financial Incentives. Real dollars are at stake for improvement. 3 Targets. For each measure, there is a range of performance targets representing a continuum from good care to outstanding care, so the model rewards both performance and performance improvement. Blue Cross Blue Shield of Massachusetts 4 5 Data , Reports, Advice. Dynamic/actionable data and reports made available daily, monthly and quarterly, helping organizations to identify efficiency opportunities at a patient, practice and organizational level. Leadership. Each group has strong engaged leadership driving to success on integrating care, significantly improving quality and reducing costs. 18
AQC Support & Improvement Analytics Blue Cross Blue Shield of Massachusetts 19
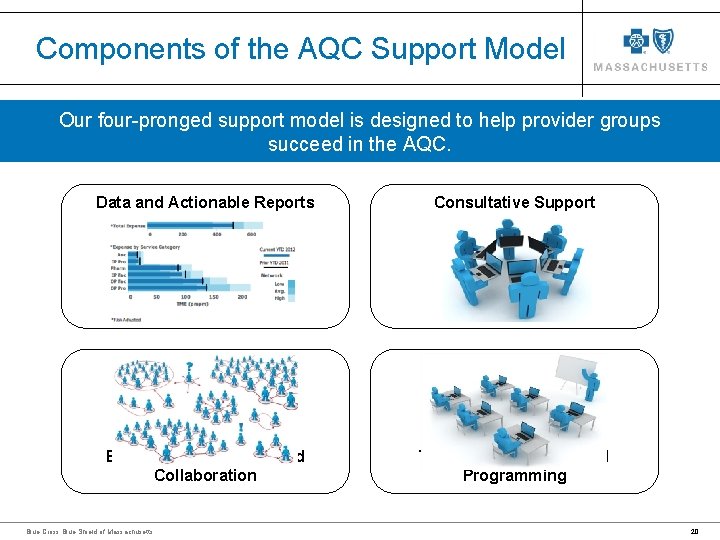
Components of the AQC Support Model Our four-pronged support model is designed to help provider groups succeed in the AQC. Data and Actionable Reports Consultative Support Best Practice Sharing and Collaboration Training and Educational Programming Blue Cross Blue Shield of Massachusetts 20
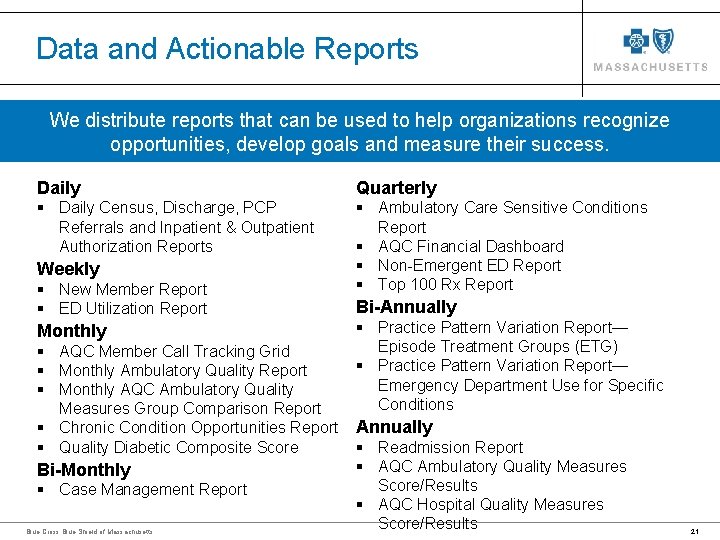
Data and Actionable Reports We distribute reports that can be used to help organizations recognize opportunities, develop goals and measure their success. Daily Quarterly § Daily Census, Discharge, PCP Referrals and Inpatient & Outpatient Authorization Reports § Ambulatory Care Sensitive Conditions Report § AQC Financial Dashboard § Non-Emergent ED Report § Top 100 Rx Report Weekly § New Member Report § ED Utilization Report Monthly § AQC Member Call Tracking Grid § Monthly Ambulatory Quality Report § Monthly AQC Ambulatory Quality Measures Group Comparison Report § Chronic Condition Opportunities Report § Quality Diabetic Composite Score Bi-Monthly § Case Management Report Blue Cross Blue Shield of Massachusetts Bi-Annually § Practice Pattern Variation Report— Episode Treatment Groups (ETG) § Practice Pattern Variation Report— Emergency Department Use for Specific Conditions Annually § Readmission Report § AQC Ambulatory Quality Measures Score/Results § AQC Hospital Quality Measures Score/Results 21
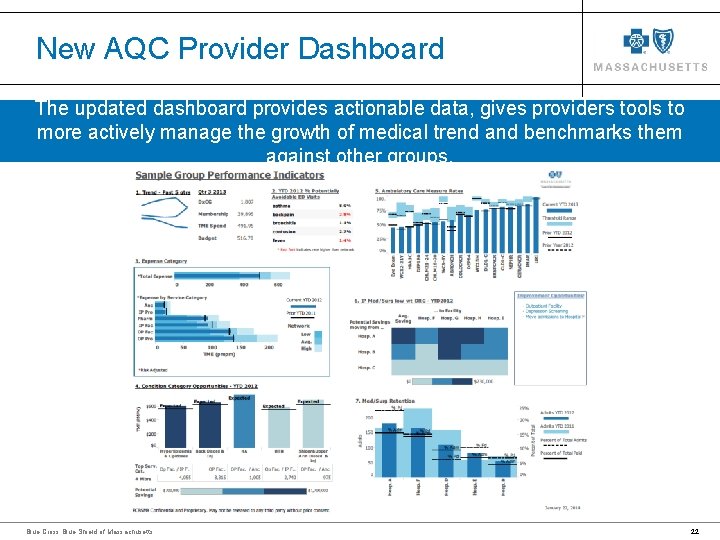
New AQC Provider Dashboard The updated dashboard provides actionable data, gives providers tools to more actively manage the growth of medical trend and benchmarks them against other groups. Blue Cross Blue Shield of Massachusetts 22
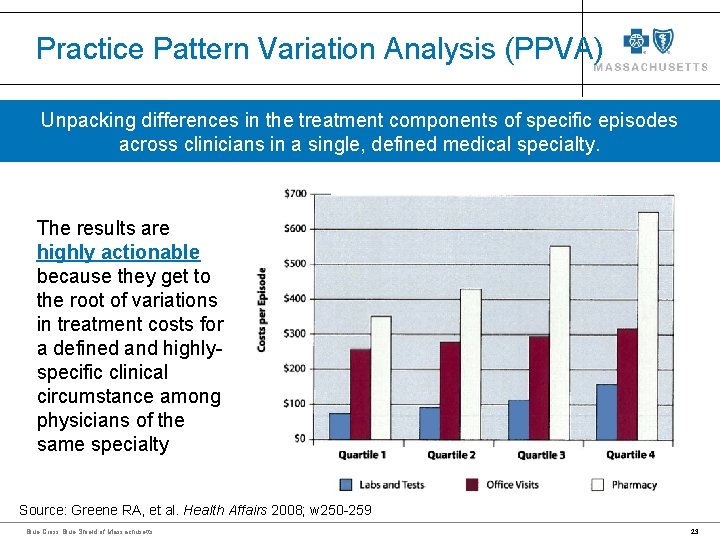
Practice Pattern Variation Analysis (PPVA) Unpacking differences in the treatment components of specific episodes across clinicians in a single, defined medical specialty. The results are highly actionable because they get to the root of variations in treatment costs for a defined and highlyspecific clinical circumstance among physicians of the same specialty Source: Greene RA, et al. Health Affairs 2008; w 250 -259 Blue Cross Blue Shield of Massachusetts 23
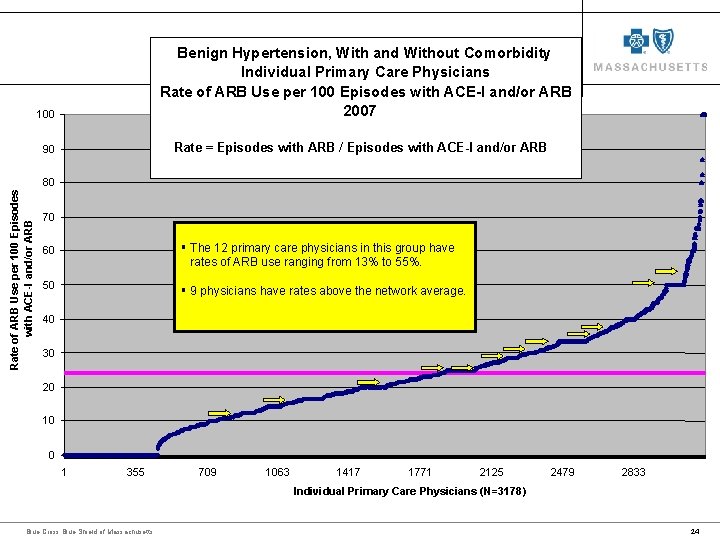
Benign Hypertension, With and Without Comorbidity Individual Primary Care Physicians Rate of ARB Use per 100 Episodes with ACE-I and/or ARB 2007 100 Rate = Episodes with ARB / Episodes with ACE-I and/or ARB 90 Rate of ARB Use per 100 Episodes with ACE-I and/or ARB 80 70 § The 12 primary care physicians in this group have § Theof 12 ARB primary care physicians in to this group have rates use ranging from 13% 55%. rates of ARB use ranging from 13% to 55%. § 9 physicians have rates above the network average. 60 50 40 30 20 10 0 1 355 709 1063 1417 1771 2125 2479 2833 Individual Primary Care Physicians (N=3178) Blue Cross Blue Shield of Massachusetts 24
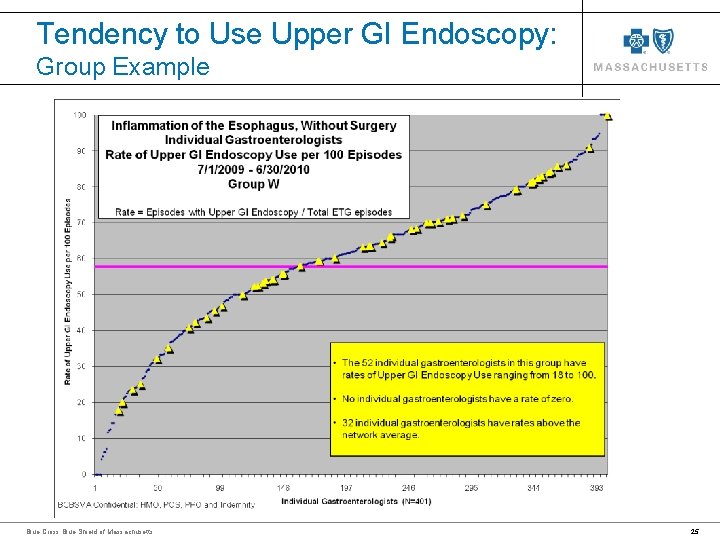
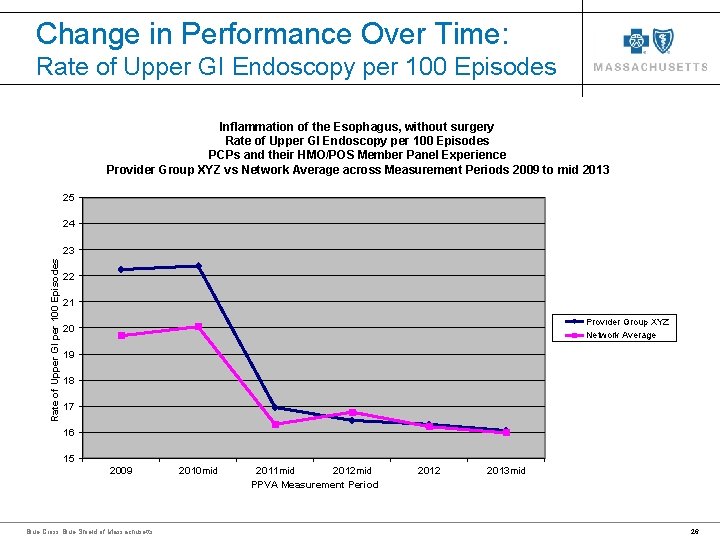
Tendency to Use Upper GI Endoscopy: Group Example Blue Cross Blue Shield of Massachusetts 25
Change in Performance Over Time: Rate of Upper GI Endoscopy per 100 Episodes Inflammation of the Esophagus, without surgery Rate of Upper GI Endoscopy per 100 Episodes PCPs and their HMO/POS Member Panel Experience Provider Group XYZ vs Network Average across Measurement Periods 2009 to mid 2013 25 24 Rate of Upper GI per 100 Episodes 23 22 21 Provider Group XYZ Network Average 20 19 18 17 16 15 2009 Blue Cross Blue Shield of Massachusetts 2010 mid 2011 mid 2012 mid PPVA Measurement Period 2012 2013 mid 26
Variation in PCP referral for Low Back Pain Blue Cross Blue Shield of Massachusetts 27
Variation in Days-to-MRI for Low Back Pain Blue Cross Blue Shield of Massachusetts 28
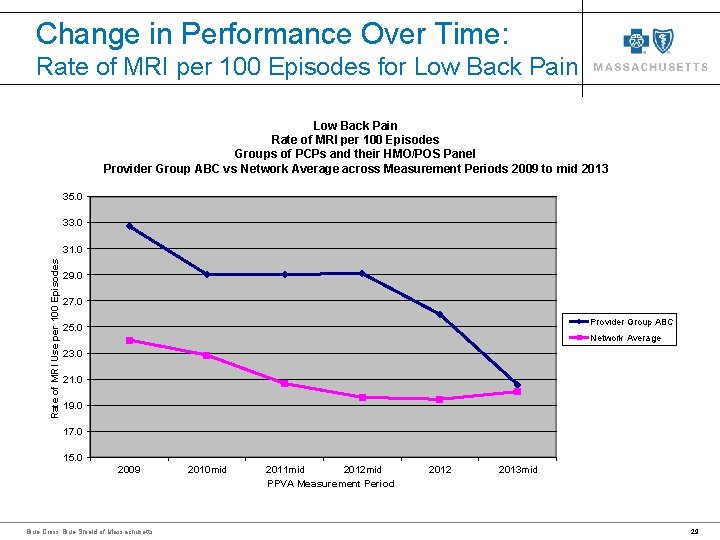
Change in Performance Over Time: Rate of MRI per 100 Episodes for Low Back Pain Rate of MRI per 100 Episodes Groups of PCPs and their HMO/POS Panel Provider Group ABC vs Network Average across Measurement Periods 2009 to mid 2013 35. 0 33. 0 Rate of MRI Use per 100 Episodes 31. 0 29. 0 27. 0 Provider Group ABC 25. 0 Network Average 23. 0 21. 0 19. 0 17. 0 15. 0 2009 Blue Cross Blue Shield of Massachusetts 2010 mid 2011 mid 2012 mid PPVA Measurement Period 2012 2013 mid 29
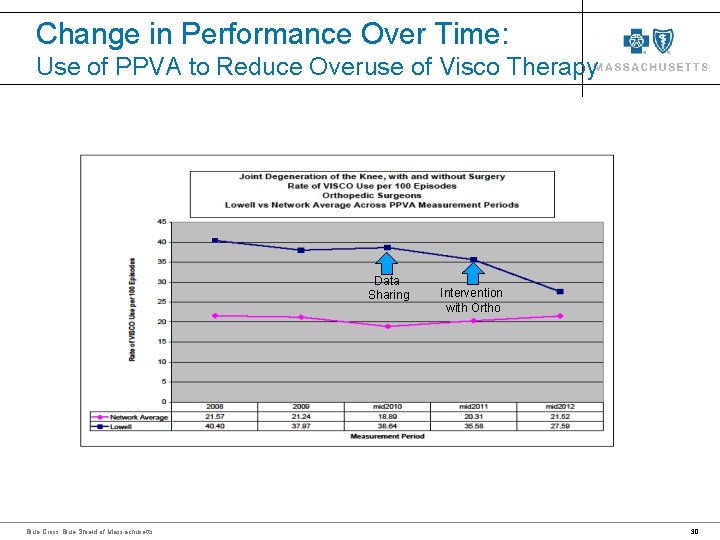
Change in Performance Over Time: Use of PPVA to Reduce Overuse of Visco Therapy Sample Group Data Sharing Intervention with Ortho Sample Group Blue Cross Blue Shield of Massachusetts 30
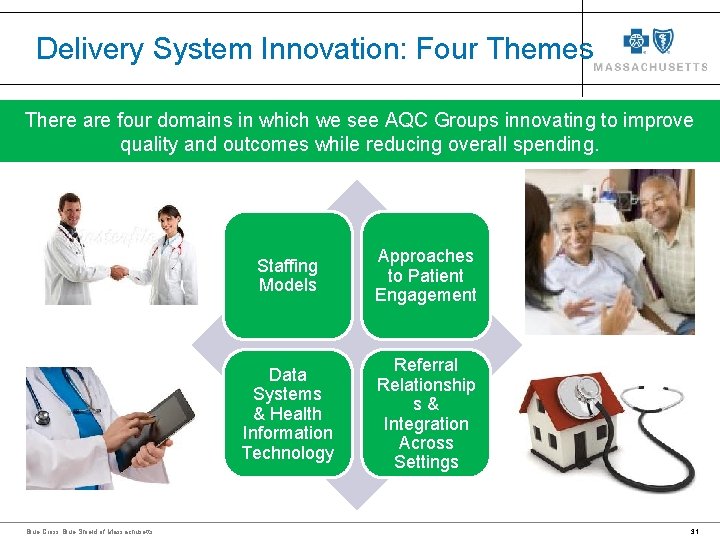
Delivery System Innovation: Four Themes There are four domains in which we see AQC Groups innovating to improve quality and outcomes while reducing overall spending. Blue Cross Blue Shield of Massachusetts Staffing Models Approaches to Patient Engagement Data Systems & Health Information Technology Referral Relationship s& Integration Across Settings 31
Local & National Policy Context Blue Cross Blue Shield of Massachusetts 32
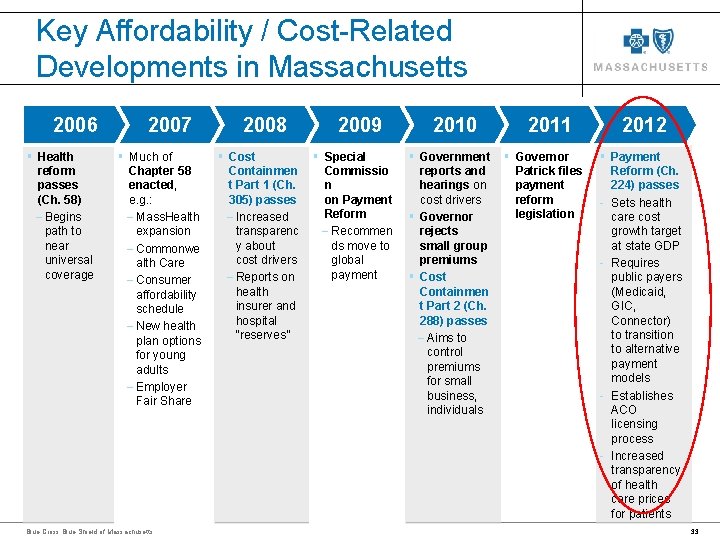
Key Affordability / Cost-Related Developments in Massachusetts 2006 § Health reform passes (Ch. 58) – Begins path to near universal coverage 2007 § Much of Chapter 58 enacted, e. g. : – Mass. Health expansion – Commonwe alth Care – Consumer affordability schedule – New health plan options for young adults – Employer Fair Share Blue Cross Blue Shield of Massachusetts 2008 § Cost Containmen t Part 1 (Ch. 305) passes – Increased transparenc y about cost drivers – Reports on health insurer and hospital “reserves” 2009 § Special Commissio n on Payment Reform – Recommen ds move to global payment 2010 § Government reports and hearings on cost drivers § Governor rejects small group premiums § Cost Containmen t Part 2 (Ch. 288) passes – Aims to control premiums for small business, individuals 2011 § Governor Patrick files payment reform legislation 2012 § Payment Reform (Ch. 224) passes - Sets health care cost growth target at state GDP - Requires public payers (Medicaid, GIC, Connector) to transition to alternative payment models - Establishes ACO licensing process - Increased transparency of health care prices for patients 33
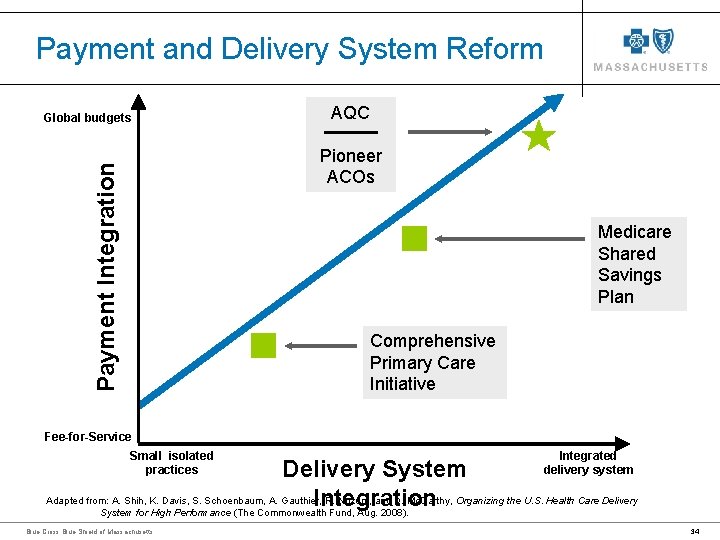
Payment and Delivery System Reform Global budgets AQC Payment Integration Pioneer ACOs Medicare Shared Savings Plan Comprehensive Primary Care Initiative Fee-for-Service Small isolated practices Integrated delivery system Delivery System Adapted from: A. Shih, K. Davis, S. Schoenbaum, A. Gauthier, R. Nuzum, and D. Mc. Carthy, Organizing the U. S. Health Care Delivery Integration System for High Performance (The Commonwealth Fund, Aug. 2008). Blue Cross Blue Shield of Massachusetts 34
Summary & Key Takeaways Blue Cross Blue Shield of Massachusetts 35
Summary and Priority Issues Ahead Summary § Payment reform gives rise to significant delivery system reform Priority Issues Ahead § Expanding payment reform to include PPO § § § Rapid and substantial performance improvements are possible in the context of: § § Meaningful financial incentives Rigorously validated measures & methods Ongoing and timely data sharing and engagement Committed leadership § For payment reform, deep provider relationships and significant market share advantageous For national payers, remote provider relationships pose engagement challenges; Blue Cross Blue Shield of Massachusetts member-facing incentives § Requires attribution model Requires national data exchange (multistate accounts) § Payment incentives to front line clinicians need continued attention § Continued evolution of performance measures § Focus on outcomes, including patient reported outcomes (functional status, well being) § Continued delivery system reform, including: § § Advancing innovations in virtual care Evolving the role of hospitals and hospital care 36