PROSTATE CANCER KNOWLEDGE ADVANCES ON ANDROGEN DEPRIVATION THERAPY














- Slides: 33
PROSTATE CANCER KNOWLEDGE ADVANCES ON ANDROGEN DEPRIVATION THERAPY RECENT INVESTIGATION TRENDS Francisco Madeira Pina XVI Workshop em Urologia Oncológica Carvoeiro, 28/29 de Outubro de 2011
M 0. HN. PC _ M 0 Hormone-Naive Prostate Cancer M 0. CR. PC _ M 0 Castration-Resistent Prostate Cancer M 1. HN. PC _ M 1 Hormone-Naive Prostate Cancer M 1. CR. PC _ M 1 Castration-Resistent Prostate Cancer
M 0. HN. PC M 0 Hormone-Naive Prostate Cancer PC median specific survival High risk PC Interm. risk PC Low risk PC 14 months 28 months 89 months
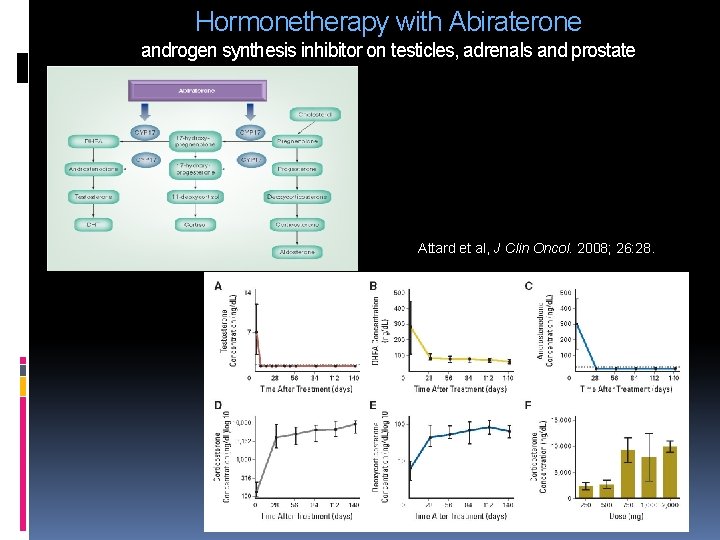
Hormonetherapy with Abiraterone androgen synthesis inhibitor on testicles, adrenals and prostate Attard et al, J Clin Oncol. 2008; 26: 28.
M 0 Hormone-Naive Prostate Cancer Abiraterone hormonetherapy trials NCT 01023061 Phase III trial for 25 patients with localized or locally advanced PCa Radiotherapy + Abiraterone + Leuprolide + Prednisone End points: safety, tolerability, T and DHT tissue levels Future Oncol. , 6 (5); 2010 NCT 00924469 Phase II trial for 58 patients with localized high-risk Pca Abiraterone + Leuprolide + Prednisone versus Leuprolide End points: T and DHT serum and tissue levels Future Oncol. , 6 (5); 2010
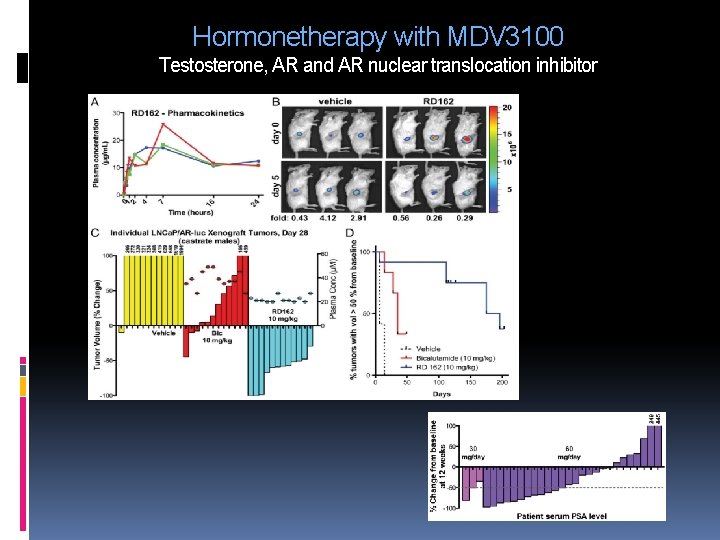
Hormonetherapy with MDV 3100 Testosterone, AR and AR nuclear translocation inhibitor
M 0 Hormone-Naive Prostate Cancer MDV 3100 hormonetherapy trials NCT xxxx Phase II trial for 60 patients with untreated PCa (enrollement) MDV 3100 160 mg/day momotherapy / 24 weeks End points: PSA response Nowak JT, 2011, Malecare's Advanced Prostate Cancer; clintrials. info@us. astellas. com.
M 0. CR. PC M 0 Castration-Resistent Prostate Cancer
M 0 Castration-Resistent Prostate Cancer PSA progression only and secondary hormone manipulation -glucocorticoids -estrogens / progestagens -ER antagonists -AR antagonists -5 alfa-reductase inibitors -cytocrom P 450 inibitors -Ketoconazol -Estramustin phosphate -Abiraterone acetate (CYP 17) -aminoglutetimide -somatuline/somatostatine analogues 1998 Joyce, J Urol; 2004 Small, J Clin Oncol; 2004 Siddiqui K, JAMA; 2005 Walsh, J Urol; 2007 Eisenberger MA, Campbell-Walsh; 2008 Urologic Oncology; 2011 Heidenreich A, Prostate Cancer _ EAU Guidelines
M 0 Castration-Resistent Prostate Cancer hormonetherapy with Abiraterone
M 0 Castration-Resistent Prostate Cancer hormonetherapy with TAK-700 _ orteronel, highly selective 17, 20 -lyase (CYP 17) inhibitor marked reduction of serum Testosterone and DHEA KAKU T. (Kanagawa, Japan), Biooig Med Chem 2011 Sep 1 NTC 01046916 Phase II trial CR. PC with biochemical recurrence enrollment goal: 42 patients safety and efficacy trial End ponts: % patients with PSA ≤ 0. 2 ng/ml after 3 m. TAK-700 Future Oncol. 6; 2010
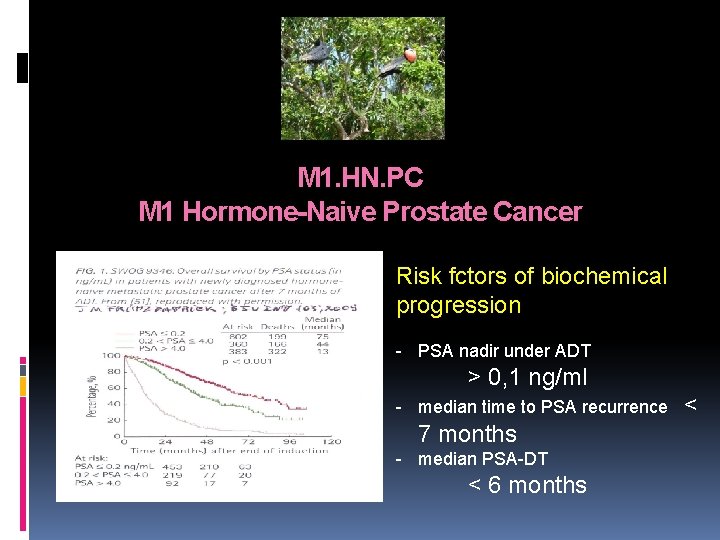
M 1. HN. PC M 1 Hormone-Naive Prostate Cancer Risk fctors of biochemical progression - PSA nadir under ADT > 0, 1 ng/ml - median time to PSA recurrence 7 months - median PSA-DT < 6 months <
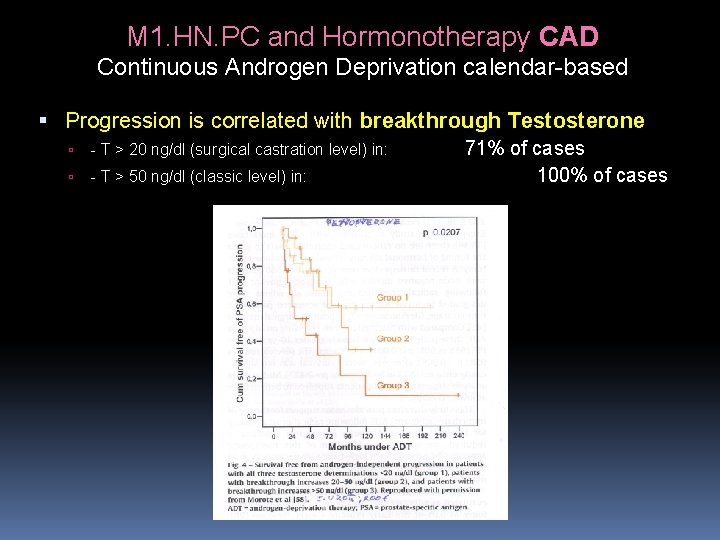
M 1. HN. PC and Hormonotherapy CAD Continuous Androgen Deprivation calendar-based Progression is correlated with breakthrough Testosterone - T > 20 ng/dl (surgical castration level) in: - T > 50 ng/dl (classic level) in: 71% of cases 100% of cases
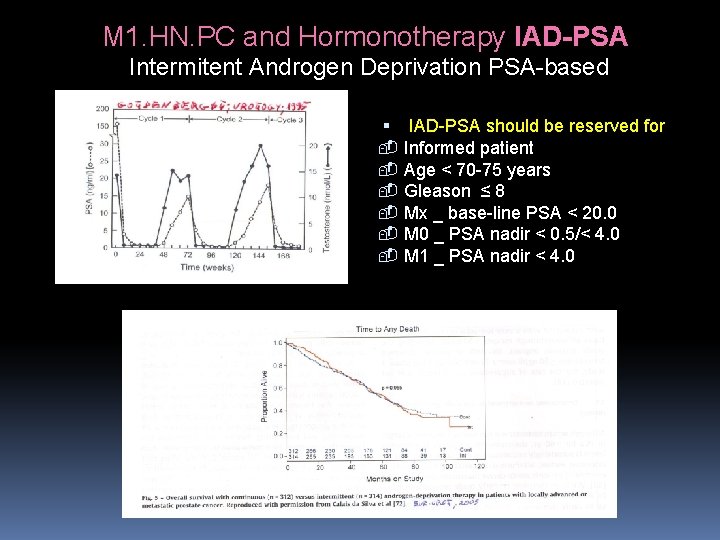
M 1. HN. PC and Hormonotherapy IAD-PSA Intermitent Androgen Deprivation PSA-based IAD-PSA should be reserved for - Informed patient - Age < 70 -75 years - Gleason ≤ 8 - Mx _ base-line PSA < 20. 0 - M 0 _ PSA nadir < 0. 5/< 4. 0 - M 1 _ PSA nadir < 4. 0
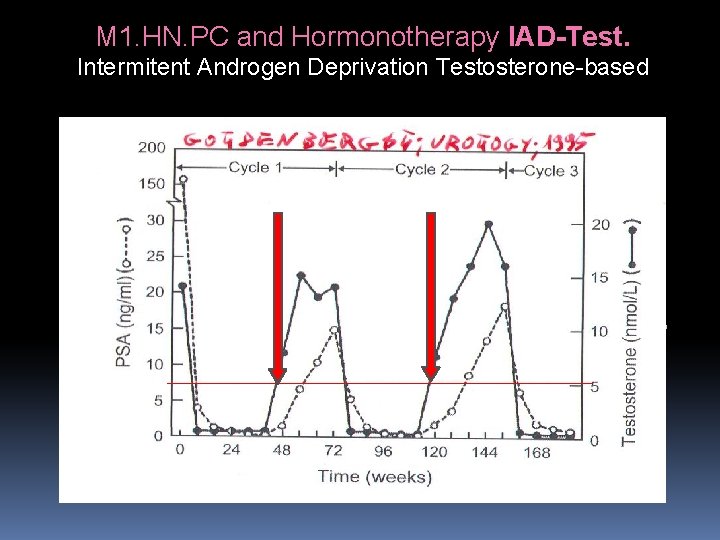
M 1. HN. PC and Hormonotherapy IAD-Test. Intermitent Androgen Deprivation Testosterone-based
M 1. HN. PC and Hormonotherapy IAD-Test. Intermitent Androgen Deprivation Testosterone-based
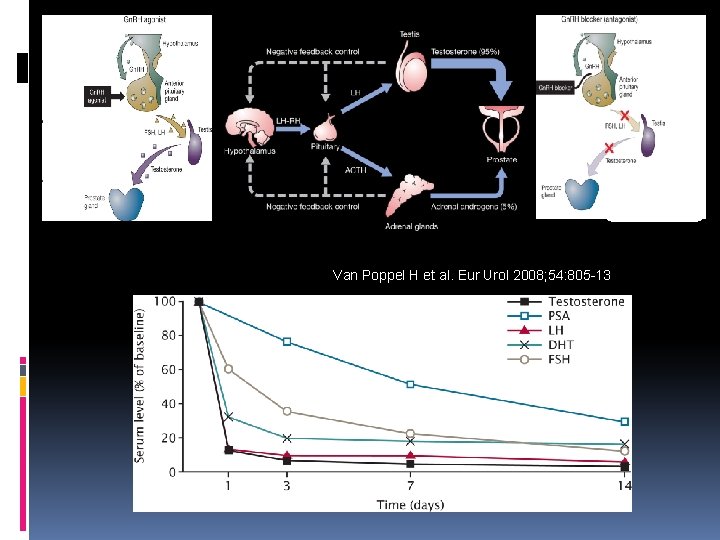
Van Poppel H et al. Eur Urol 2008; 54: 805 -13
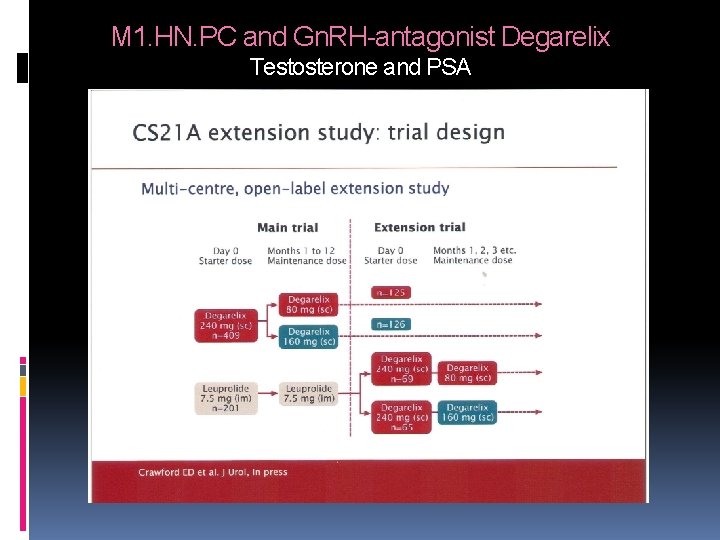
M 1. HN. PC and Gn. RH-antagonist Degarelix Testosterone and PSA
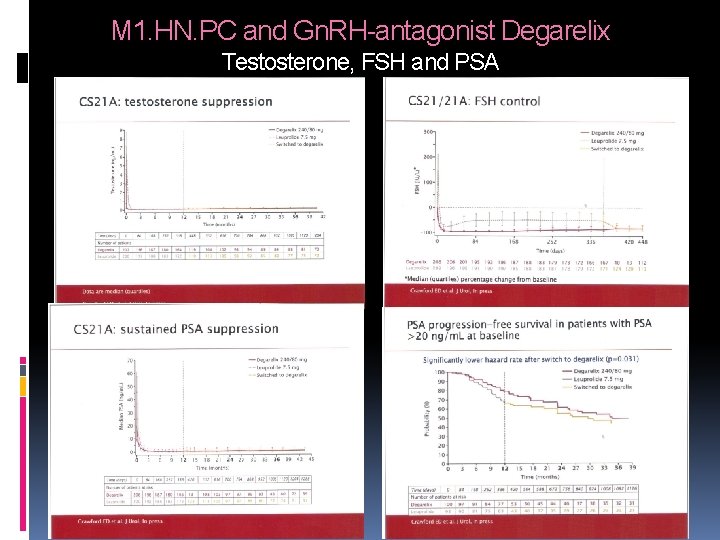
M 1. HN. PC and Gn. RH-antagonist Degarelix Testosterone, FSH and PSA
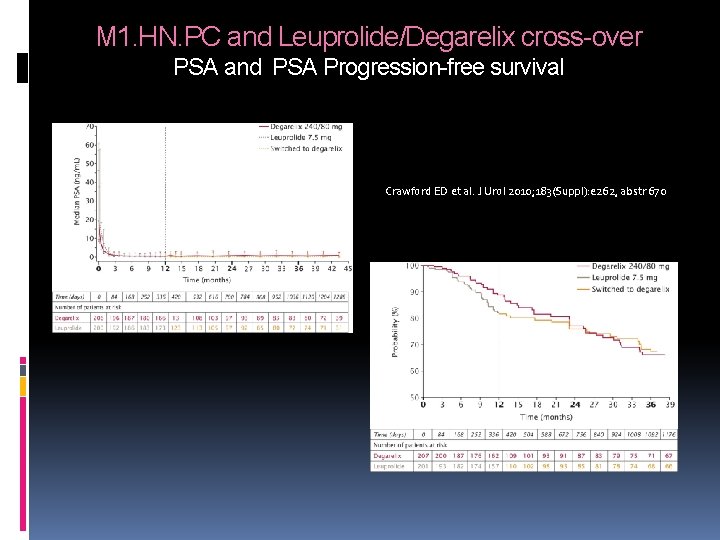
M 1. HN. PC and Leuprolide/Degarelix cross-over PSA and PSA Progression-free survival Crawford ED et al. J Urol 2010; 183(Suppl): e 262, abstr 670
M 1. CR. PC M 1 Castration-Resistent Prostate Cancer Survival predictive variables - Performance Status - LDH lactic dehidrogenase - ALKP alkaline phosphate - Hb hemoglobin - PSA prostatic specific antigen - Nomograms 2007 Eisenberger MA, Campbell-Walsh; 2008 Urologic Oncology - CTC count 2009 Sher HI Lancet Oncol; 2009 Helo P Clin Chem; 2009 Goodman OBJr Cancer Epidemiol Biomarkers Prev.
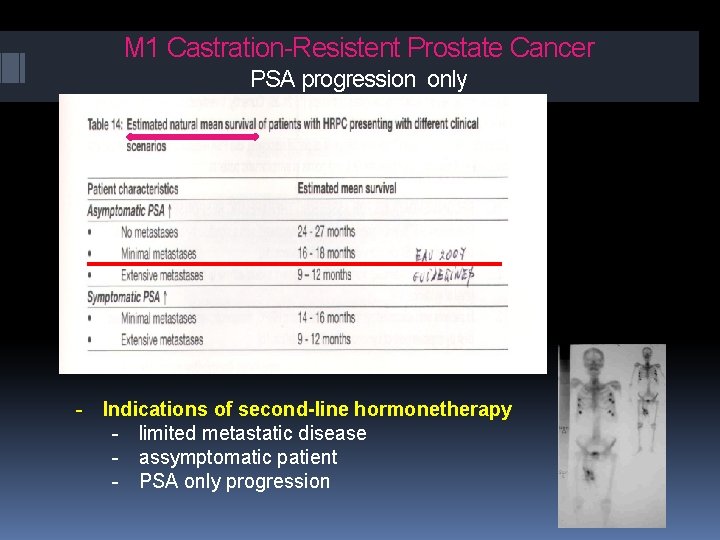
M 1 Castration-Resistent Prostate Cancer PSA progression only - Indications of second-line hormonetherapy - limited metastatic disease - assymptomatic patient - PSA only progression
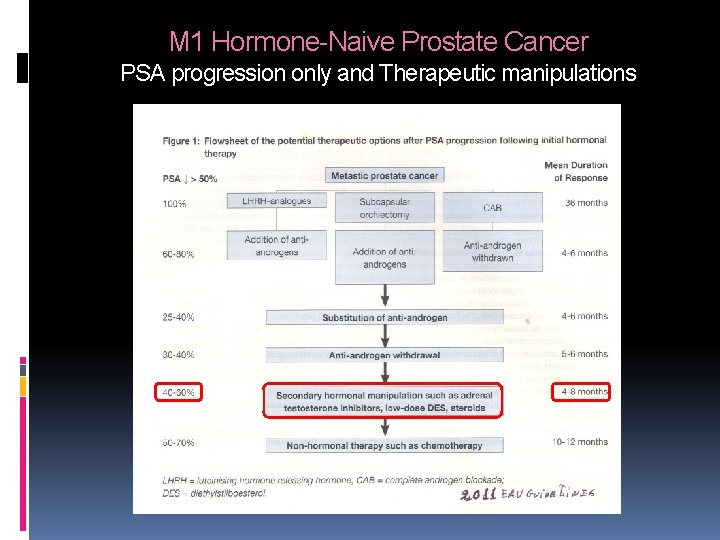
M 1 Hormone-Naive Prostate Cancer PSA progression only and Therapeutic manipulations
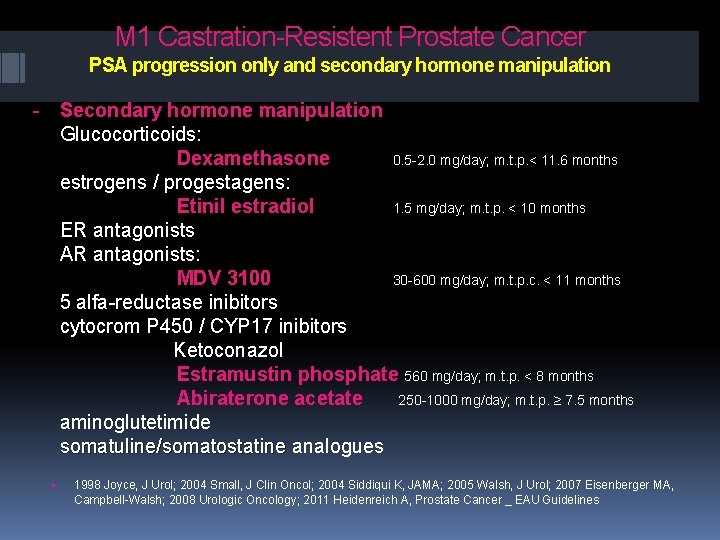
M 1 Castration-Resistent Prostate Cancer PSA progression only and secondary hormone manipulation - Secondary hormone manipulation Glucocorticoids: Dexamethasone 0. 5 -2. 0 mg/day; m. t. p. < 11. 6 months estrogens / progestagens: Etinil estradiol 1. 5 mg/day; m. t. p. < 10 months ER antagonists AR antagonists: MDV 3100 30 -600 mg/day; m. t. p. c. < 11 months 5 alfa-reductase inibitors cytocrom P 450 / CYP 17 inibitors Ketoconazol Estramustin phosphate 560 mg/day; m. t. p. < 8 months Abiraterone acetate 250 -1000 mg/day; m. t. p. ≥ 7. 5 months aminoglutetimide somatuline/somatostatine analogues 1998 Joyce, J Urol; 2004 Small, J Clin Oncol; 2004 Siddiqui K, JAMA; 2005 Walsh, J Urol; 2007 Eisenberger MA, Campbell-Walsh; 2008 Urologic Oncology; 2011 Heidenreich A, Prostate Cancer _ EAU Guidelines
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials in chemo-naive NCT 0087198 Phase III trial enrollment goal: 1000 patients (enrolling) asymptomatic or mildly sympt. M 1. CR. PC Abiraterone versus placebo end points: median OS Future Oncol. , 6 (5); 2010
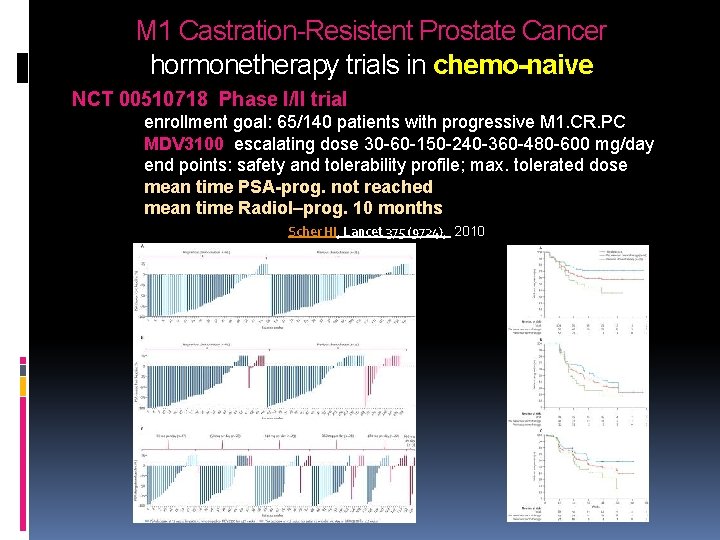
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials in chemo-naive NCT 00510718 Phase I/II trial enrollment goal: 65/140 patients with progressive M 1. CR. PC MDV 3100 escalating dose 30 -60 -150 -240 -360 -480 -600 mg/day end points: safety and tolerability profile; max. tolerated dose mean time PSA-prog. not reached mean time Radiol–prog. 10 months Scher HI, Lancet 375 (9724), 2010
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials in chemo-naive NCT xxxx Phase III trial enrollment goal: 1000 patients (enrolling) asymptomatic or mildly sympt. M 1. CR. PC MDV 3100 versus placebo end points: median OS Future Oncol. , 6 (5); 2010 NCT 00569153 Phase I/II trial enrollment goal: 61 patients M 1. CR. PC TAK-700 end points: safety and tolerability Future Oncol. , 6 (5); 2010
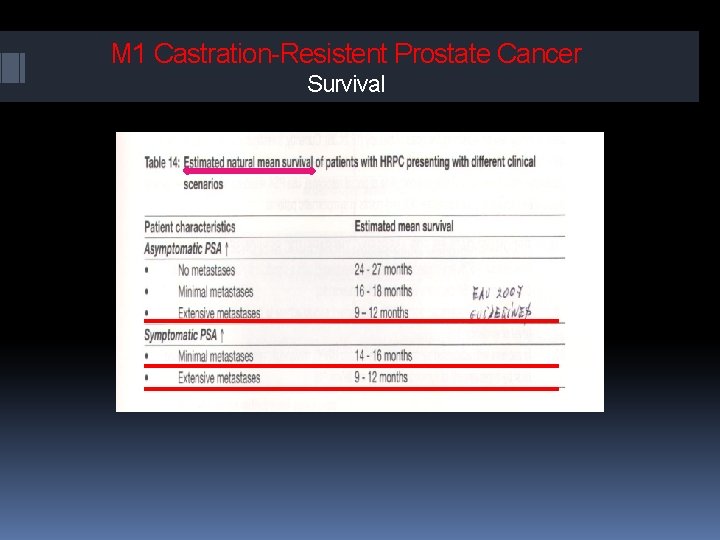
M 1 Castration-Resistent Prostate Cancer Survival
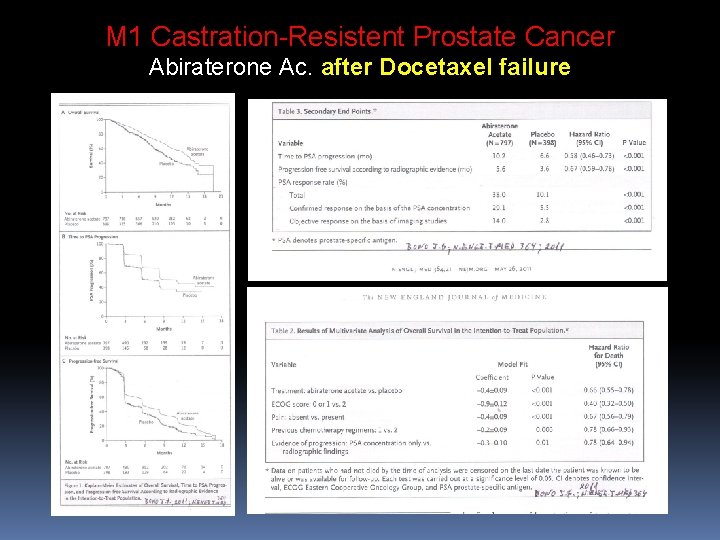
M 1 Castration-Resistent Prostate Cancer Abiraterone Ac. after Docetaxel failure
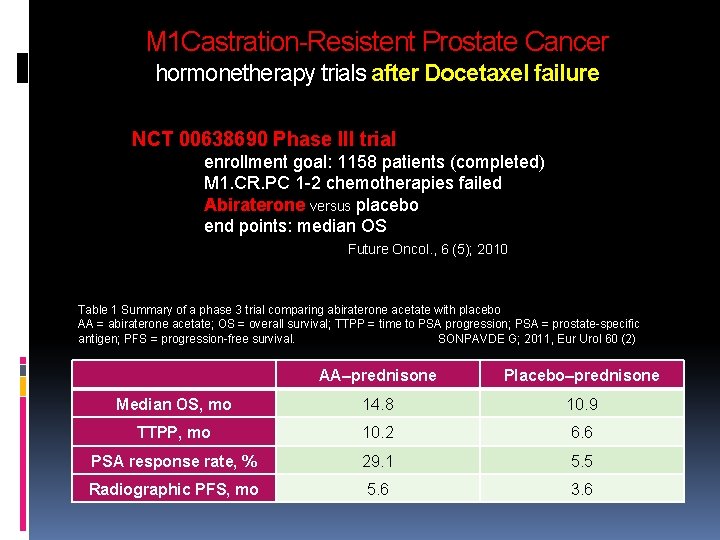
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials after Docetaxel failure NCT 00638690 Phase III trial enrollment goal: 1158 patients (completed) M 1. CR. PC 1 -2 chemotherapies failed Abiraterone versus placebo end points: median OS Future Oncol. , 6 (5); 2010 Table 1 Summary of a phase 3 trial comparing abiraterone acetate with placebo AA = abiraterone acetate; OS = overall survival; TTPP = time to PSA progression; PSA = prostate-specific antigen; PFS = progression-free survival. SONPAVDE G; 2011, Eur Urol 60 (2) AA–prednisone Placebo–prednisone Median OS, mo 14. 8 10. 9 TTPP, mo 10. 2 6. 6 PSA response rate, % 29. 1 5. 5 Radiographic PFS, mo 5. 6 3. 6
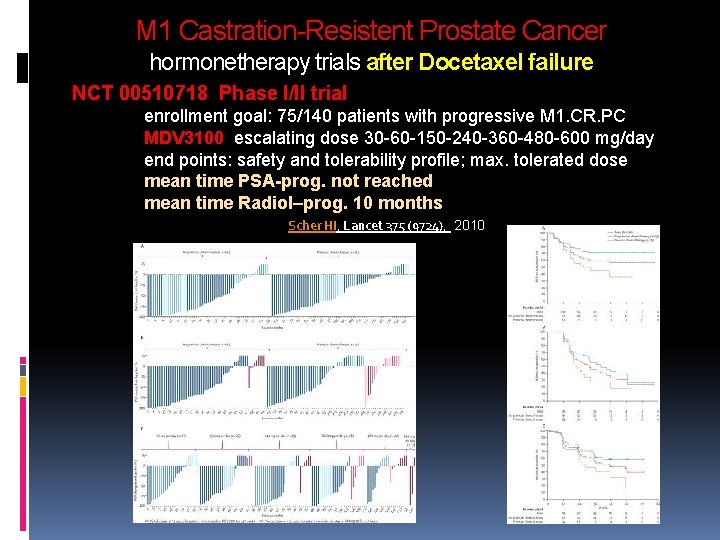
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials after Docetaxel failure NCT 00510718 Phase I/II trial enrollment goal: 75/140 patients with progressive M 1. CR. PC MDV 3100 escalating dose 30 -60 -150 -240 -360 -480 -600 mg/day end points: safety and tolerability profile; max. tolerated dose mean time PSA-prog. not reached mean time Radiol–prog. 10 months Scher HI, Lancet 375 (9724), 2010
M 1 Castration-Resistent Prostate Cancer hormonetherapy trials after Docetaxel failure NCT 00974311 (AFFIRM) Phase III trial enrollment goal: 1200 patients (enrolling) M 1. CR. PC 1 -2 chemotherapies failed MDV 3100 versus placebo end points: median OS Future Oncol. , 6 (5); 2010
New agents targeting AR signalling Table 3 Emerging novel agents targeting androgen signalling CRPC = castration-resistant prostate cancer; AR = androgen receptor; HSP 90 = heat shock protein-90; HDAC = histone deacetylase inhibitor; NTD = amino-terminal domain. SONPAVDE G; 2011, Eur Urol 60 (2) Mechanism of activity Drug Phase of development TAK-700 Placebo-controlled phase 3 clinical trials for chemonaïve and postdocetaxel metastatic CRPC AR nuclear translocation inhibitor MDV-3100 Placebo-controlled phase 3 clinical trials for chemonaïve and postdocetaxel metastatic CRPC AR nuclear translocation inhibitor ARN-509 Phase 1/2 clinical trial for metastatic CRPC CYP 17 inhibition and AR antagonist TOK-001 Phase 1/2 clinical trial for metastatic CRPC CYP 17 inhibition (nonsteroidal) 5 -α reductase inhibitor Dutasteride Phase 2 clinical trial for metastatic CRPC HSP 90 inhibitors IPI-493 Phase 1/2 clinical trial for metastatic CRPC HDAC inhibitors LAQ 824 Phase 1/2 clinical trial for metastatic CRPC AR NTD inhibitor EPI-001 Preclinical study