Cranium RTEC 233 Fall 2008 Week 1 2
















- Slides: 59
Cranium RTEC 233 Fall 2008 Week 1 & 2
Cranial Anatomy n Calvaria n Floor n Frontal n Ethmoid n Occipital n Sphenoid n Left Parietal n Left Temporal n Right Parietal n Right Temporal
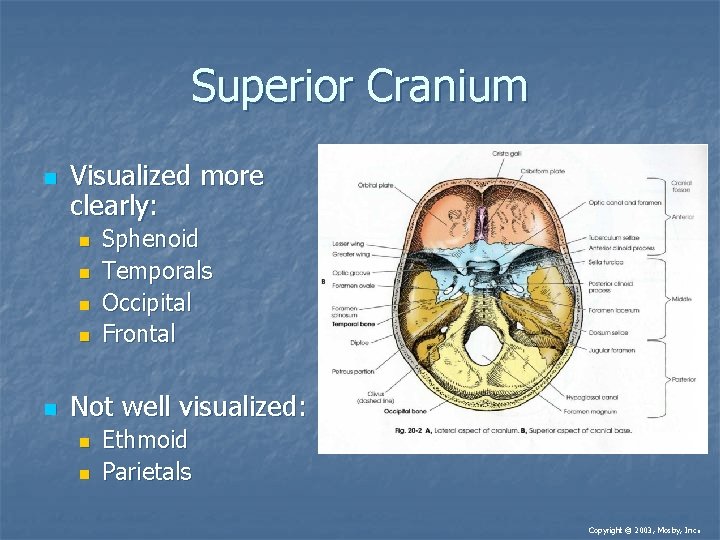
The regions of the Cranial Floor n Anterior: extends form anterior frontal bone to the lesser wings of the sphenoid n n Middle: Extends from lesser wings to the apices of petrous ridges of temporal bone n n It is associated with frontal lobes of cerebellum Accommodates temporal lobes and associated neurovascular structures Posterior: deep depression posterior to petrous ridge n which protects cerebellum, pons and medulla oblongata
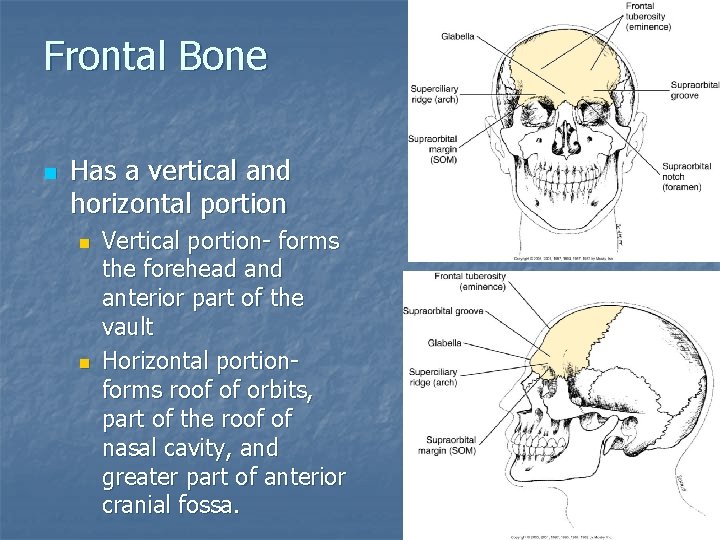
Frontal Bone n Has a vertical and horizontal portion n n Vertical portion- forms the forehead anterior part of the vault Horizontal portionforms roof of orbits, part of the roof of nasal cavity, and greater part of anterior cranial fossa.
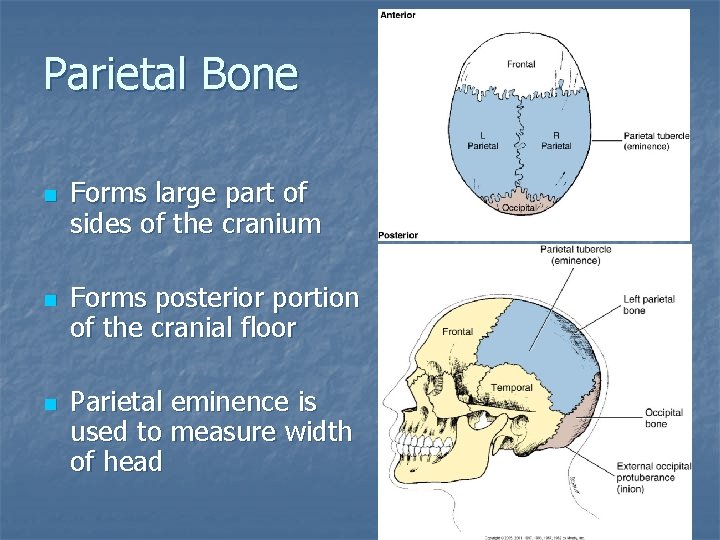
Parietal Bone n n n Forms large part of sides of the cranium Forms posterior portion of the cranial floor Parietal eminence is used to measure width of head
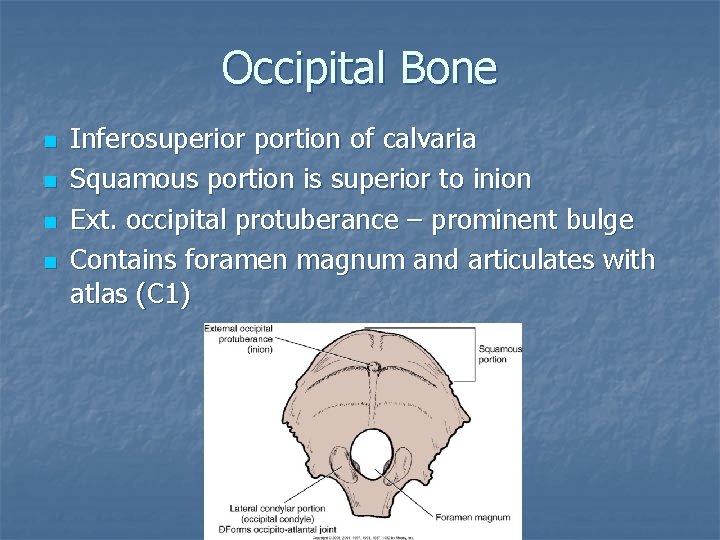
Occipital Bone n n Inferosuperior portion of calvaria Squamous portion is superior to inion Ext. occipital protuberance – prominent bulge Contains foramen magnum and articulates with atlas (C 1)
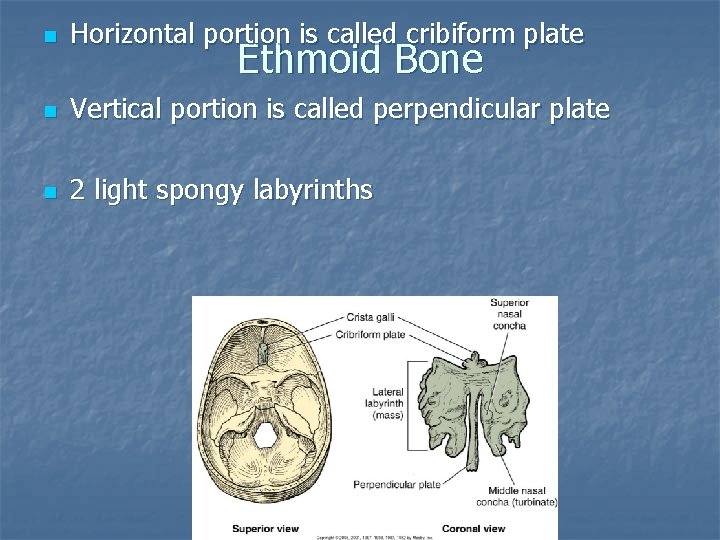
n Horizontal portion is called cribiform plate n Vertical portion is called perpendicular plate n 2 light spongy labyrinths Ethmoid Bone
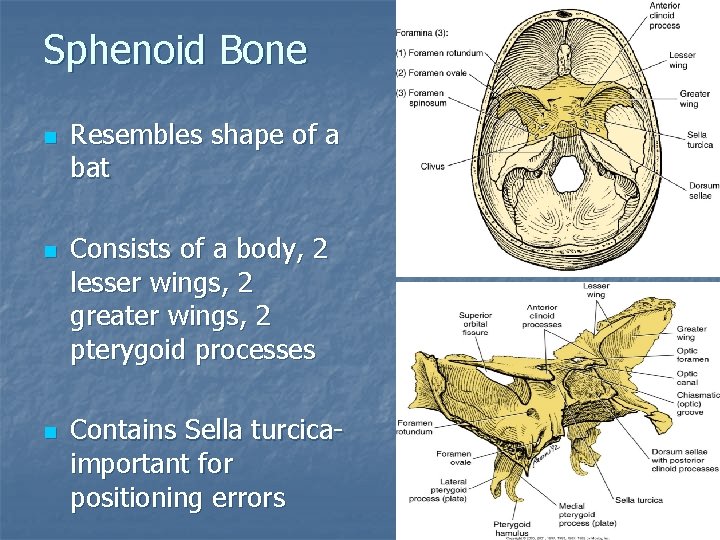
Sphenoid Bone n n n Resembles shape of a bat Consists of a body, 2 lesser wings, 2 greater wings, 2 pterygoid processes Contains Sella turcicaimportant for positioning errors
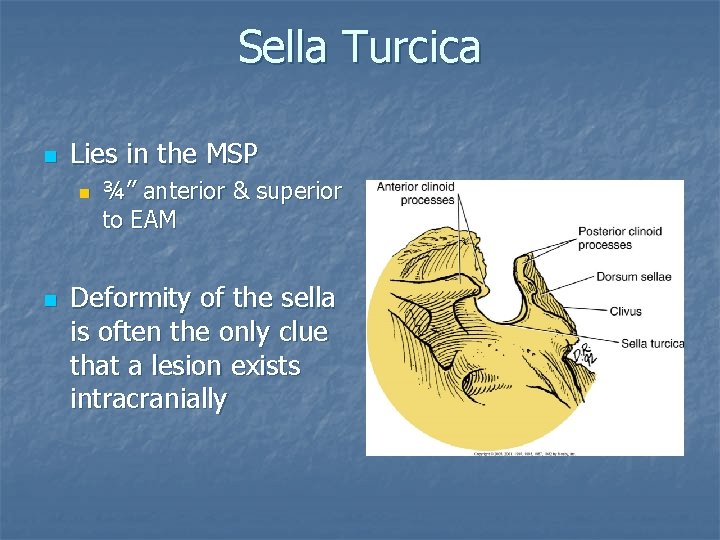
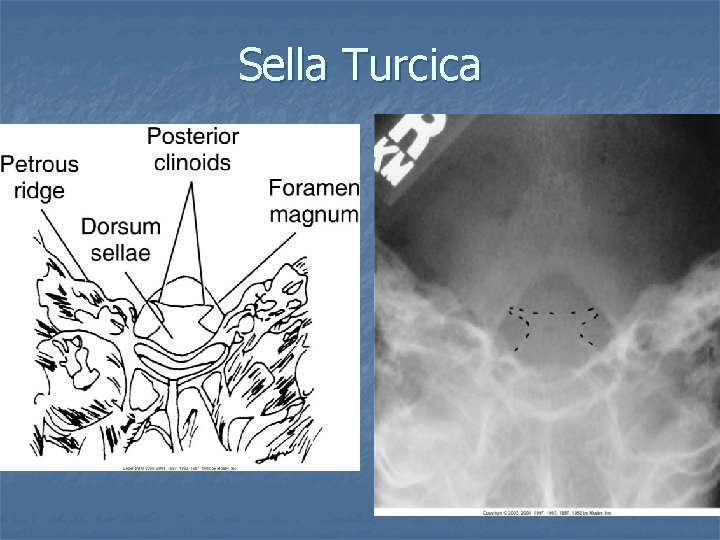
Sella Turcica n Lies in the MSP n n ¾” anterior & superior to EAM Deformity of the sella is often the only clue that a lesion exists intracranially
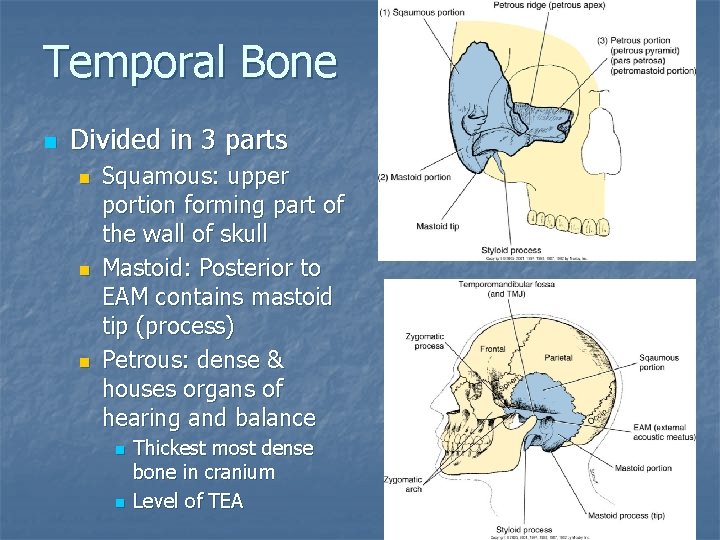
Temporal Bone n Divided in 3 parts n n n Squamous: upper portion forming part of the wall of skull Mastoid: Posterior to EAM contains mastoid tip (process) Petrous: dense & houses organs of hearing and balance n n Thickest most dense bone in cranium Level of TEA
Superior Cranium n Visualized more clearly: n n n Sphenoid Temporals Occipital Frontal Not well visualized: n n Ethmoid Parietals Copyright © 2003, Mosby, Inc .
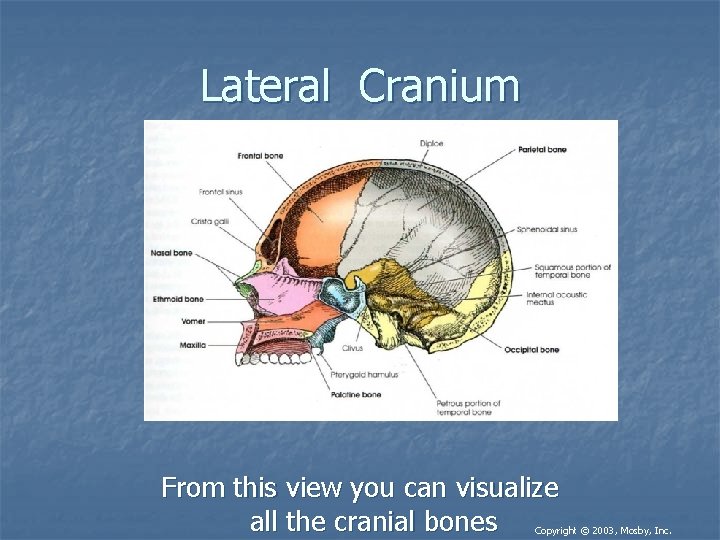
Lateral Cranium From this view you can visualize all the cranial bones Copyright © 2003, Mosby, Inc.
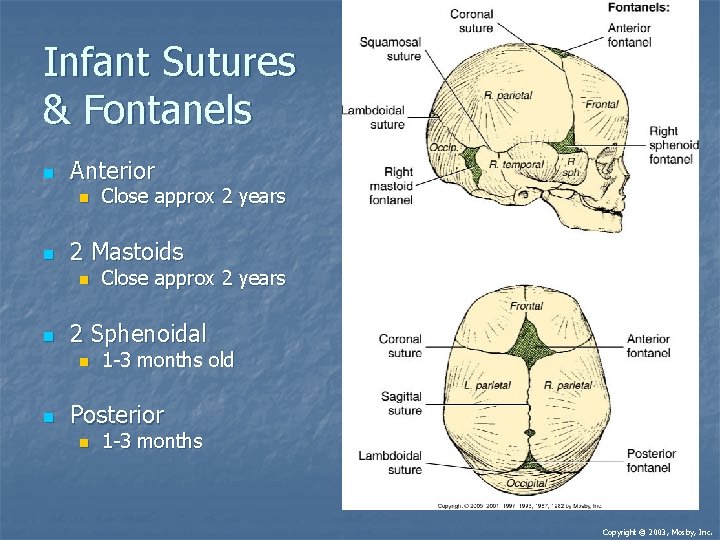
Infant Sutures & Fontanels n Anterior n n 2 Mastoids n n Close approx 2 years 2 Sphenoidal n n Close approx 2 years 1 -3 months old Posterior n 1 -3 months Copyright © 2003, Mosby, Inc.
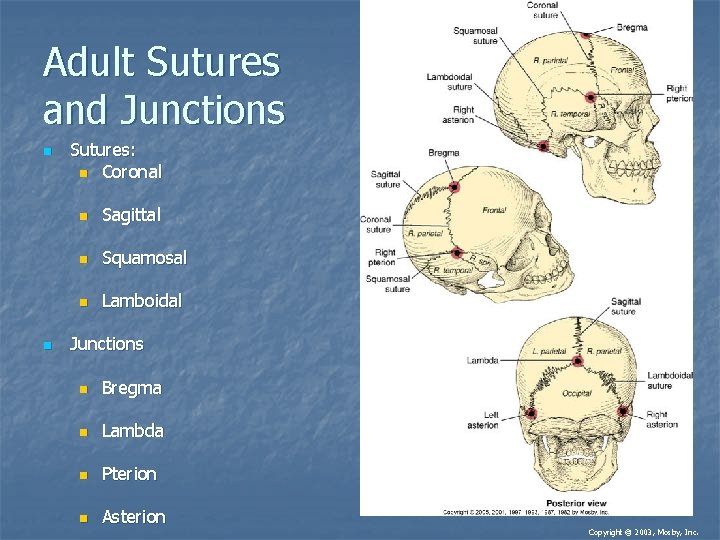
Adult Sutures and Junctions n n Sutures: n Coronal n Sagittal n Squamosal n Lamboidal Junctions n Bregma n Lambda n Pterion n Asterion Copyright © 2003, Mosby, Inc.
Lets compare Infant Adult n Anterior fontanel Bregma n Posterior fontanel Lambda n Sphenoidal fontanels Pterions n Mastoidal fontanels Asterions
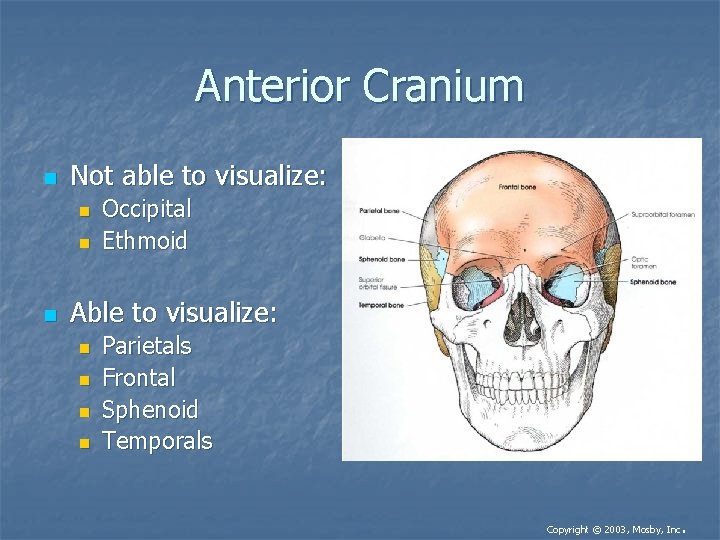
Anterior Cranium n Not able to visualize: n n n Occipital Ethmoid Able to visualize: n n Parietals Frontal Sphenoid Temporals Copyright © 2003, Mosby, Inc .
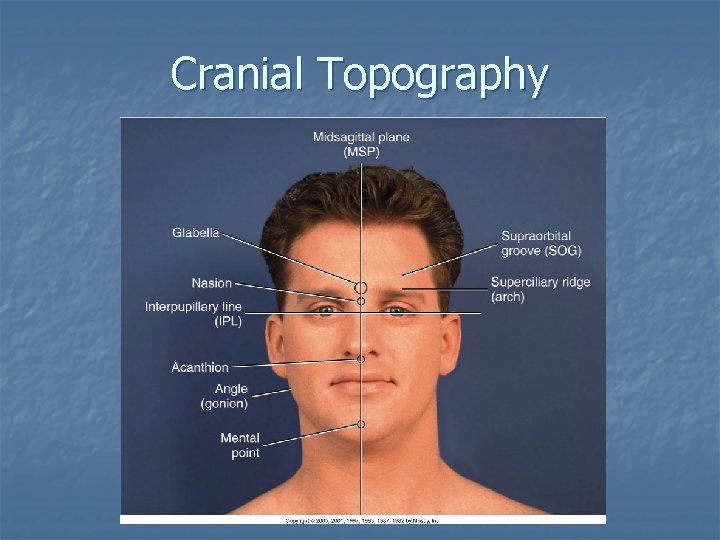
Cranial Topography
Surface Landmarks
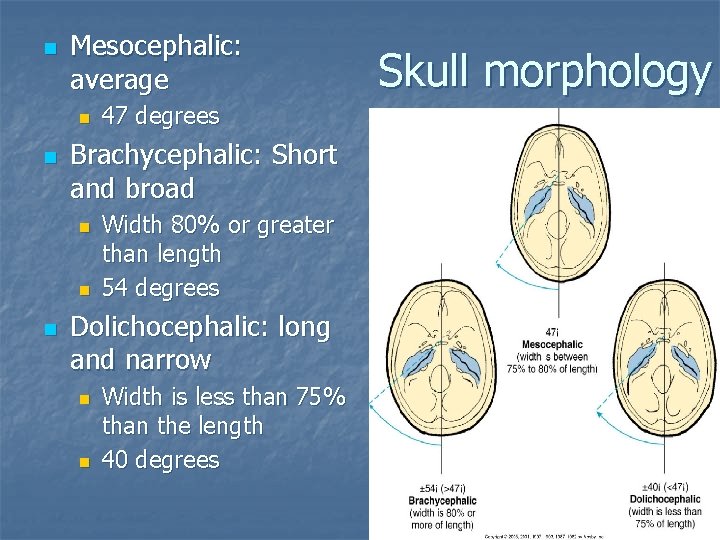
n Mesocephalic: average n n Brachycephalic: Short and broad n n n 47 degrees Width 80% or greater than length 54 degrees Dolichocephalic: long and narrow n n Width is less than 75% than the length 40 degrees Skull morphology
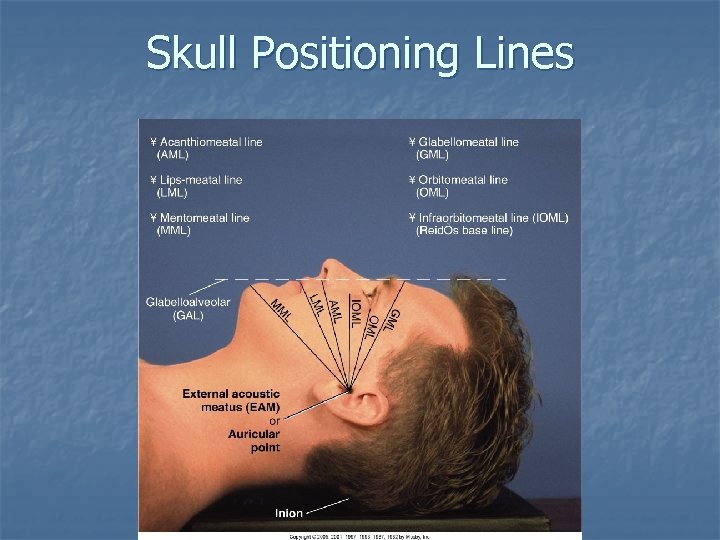
Skull Positioning Lines
Skull Topography Be able to locate the following landmarks: n n n Glabella Inner canthus Outer canthus Nasion Infraorbital margin Acanthion n n Gonion Mental point External auditory meatus (EAM) Auricular point Top of ear attachment (TEA)
Radiographic Landmarks n Interpupillary line (IPL) n n Acanthiomeatal line (AML) n n Perpendicular line between pupils of eyes From acanthion to EAM Mentomeatal line (MML) n From mental point (center of chin) to EAM
Radiographic Landmarks n Orbitomeatal line (OML) n n Infraorbitomeatal line (IOML) n n From outer canthus to EAM From infraorbital margin to EAM Glabellomeatal line (GML) n From glabella to EAM
Positioning Aids Use any straightedge: • Straw • Pen/pencil
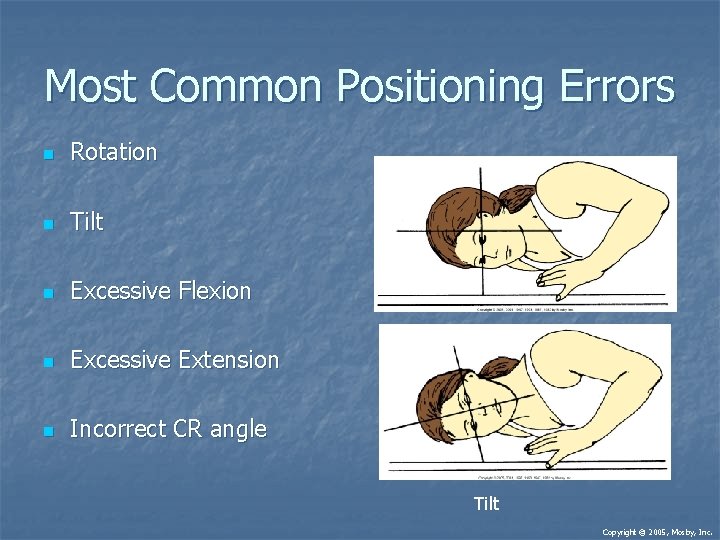
Most Common Positioning Errors n Rotation n Tilt n Excessive Flexion n Excessive Extension n Incorrect CR angle Rotation Tilt Copyright © 2005, Mosby, Inc.
Indications for Cranial Radiography n Skull fractures n Neoplasms n n Linear Depressed Basal skull Metastases n n n Osteolytic Osteoblastic Combo of both n Gunshot wounds n Multiple myeloma n Pituitary Adenomas n Paget’s Disease n Subdural hematoma n Acoustic neuroma
n n http: //www. skullbaseinstitute. com/video_p ituitary_tumor. htm http: //www. skullbaseinstitute. com/video_a coustic_neuroma. htm
Disinfect the Table or Bucky!!
Cleanliness n n Hair and skin of face are naturally oily; illness often increases oiliness Cranial procedures require direct contact of patient’s face with VBS Clean device after each patient Wash your hands!!!
Radiation Protection n n Collimate to anatomy of interest Shield gonads/abdomen of pediatric patients and those of reproductive age Shield thyroid and thymus of pediatric patient when doing so will not interfere with demonstration of anatomy of interest Good communication and positioning skills reduce chance of need for repeat radiographs
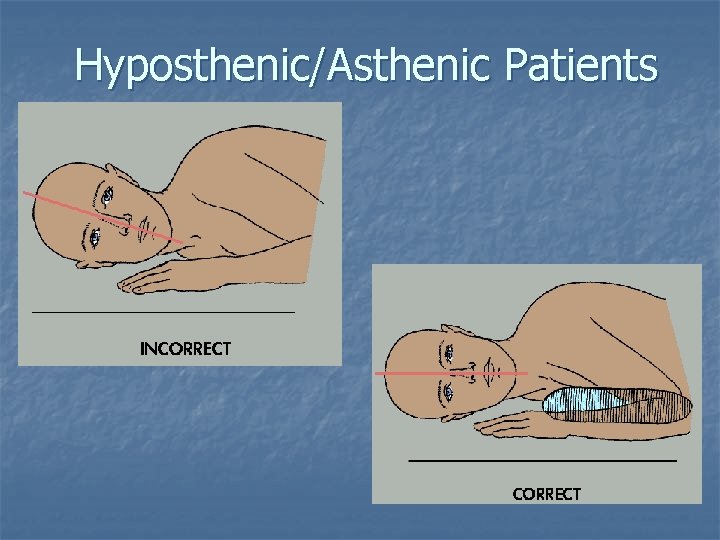
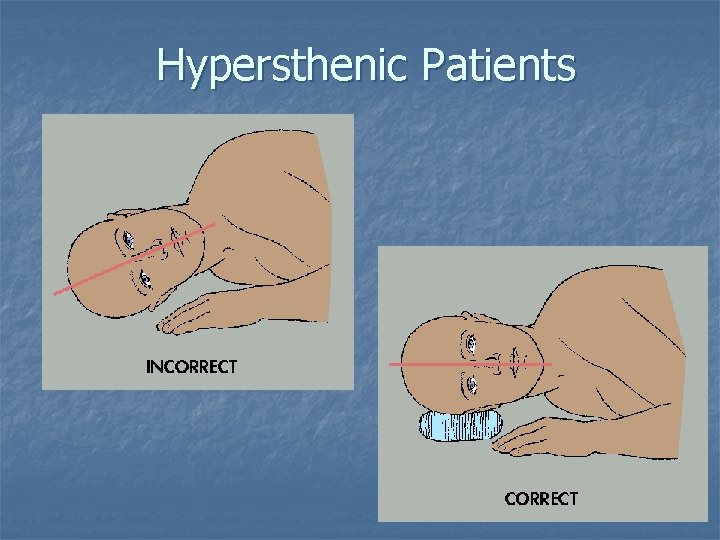
General Body Position n Hyposthenic/asthenic patients usually need support at chest to elevate C-spine n n Helps prevent downward tilt of MSP Hypersthenic patients require radiolucent support at head n Helps prevent upward tilt of MSP
Hyposthenic/Asthenic Patients
Hypersthenic Patients
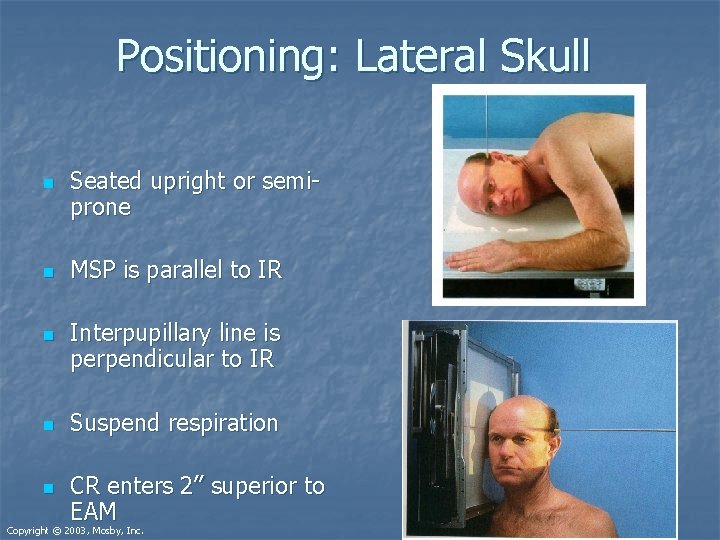
Positioning: Lateral Skull n n n Seated upright or semiprone MSP is parallel to IR Interpupillary line is perpendicular to IR Suspend respiration CR enters 2” superior to EAM Copyright © 2003, Mosby, Inc.
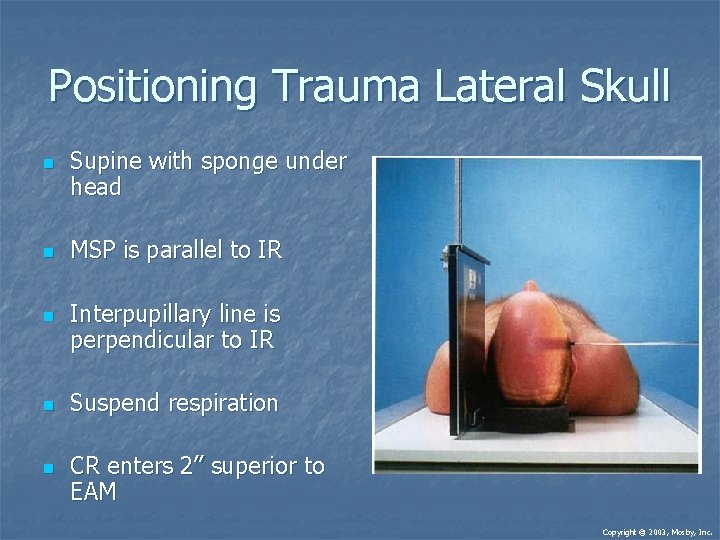
Positioning Trauma Lateral Skull n n n Supine with sponge under head MSP is parallel to IR Interpupillary line is perpendicular to IR Suspend respiration CR enters 2” superior to EAM Copyright © 2003, Mosby, Inc.
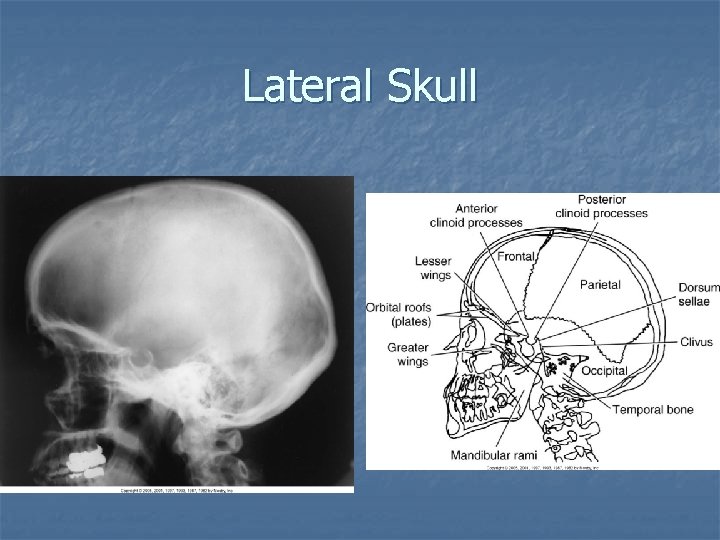
Lateral Skull
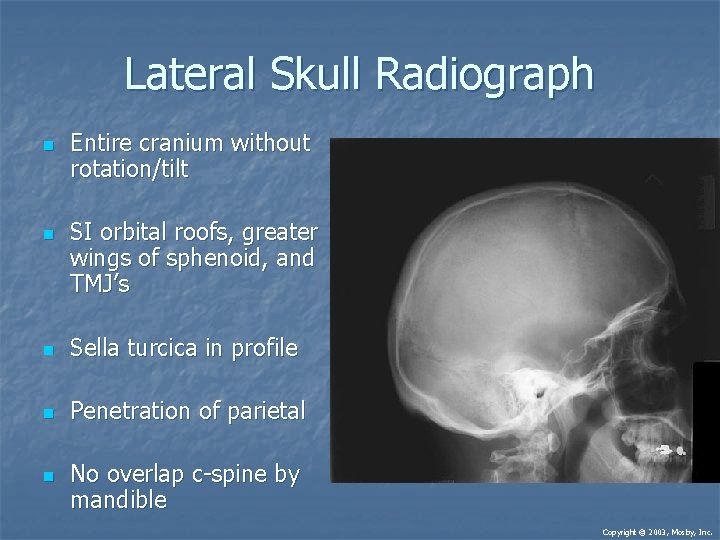
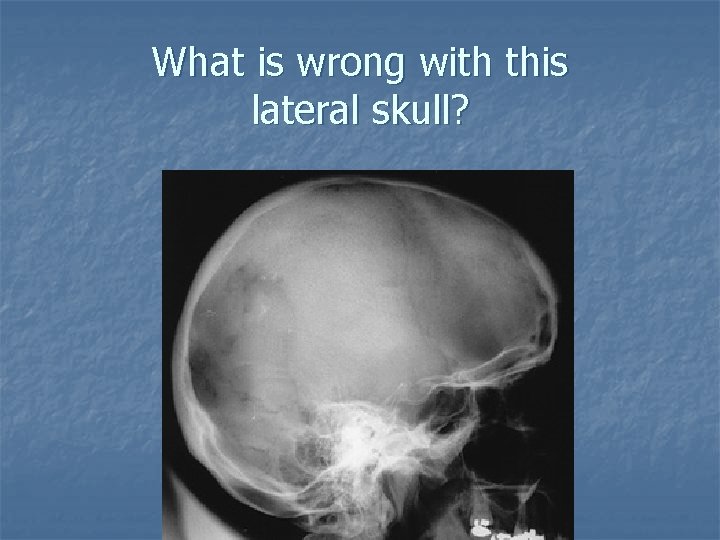
Lateral Skull Radiograph n n Entire cranium without rotation/tilt SI orbital roofs, greater wings of sphenoid, and TMJ’s n Sella turcica in profile n Penetration of parietal n No overlap c-spine by mandible Copyright © 2003, Mosby, Inc.
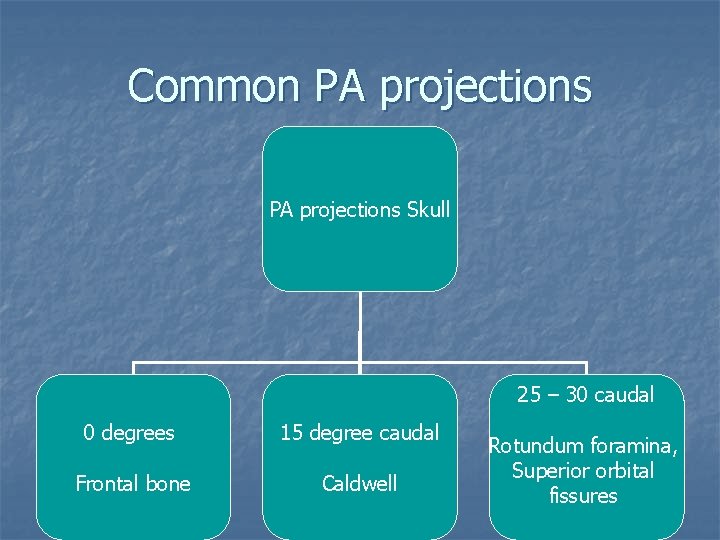
Common PA projections Skull 25 – 30 caudal 0 degrees 15 degree caudal Frontal bone Caldwell Rotundum foramina, Superior orbital fissures
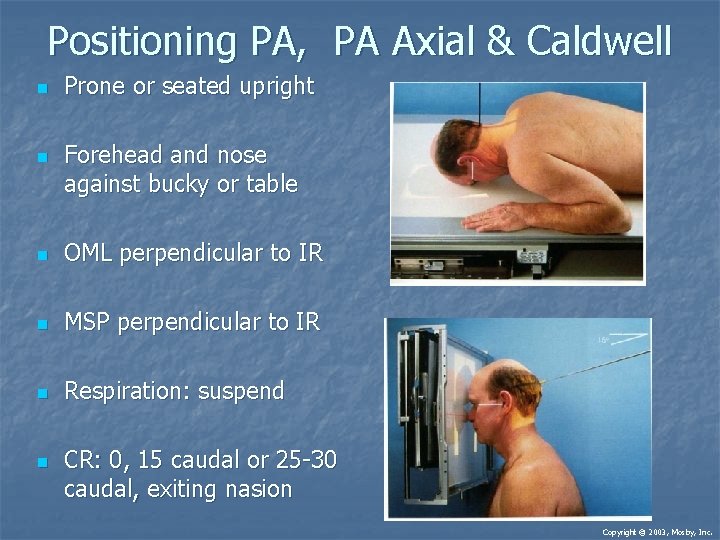
Positioning PA, PA Axial & Caldwell n n Prone or seated upright Forehead and nose against bucky or table n OML perpendicular to IR n MSP perpendicular to IR n Respiration: suspend n CR: 0, 15 caudal or 25 -30 caudal, exiting nasion Copyright © 2003, Mosby, Inc.
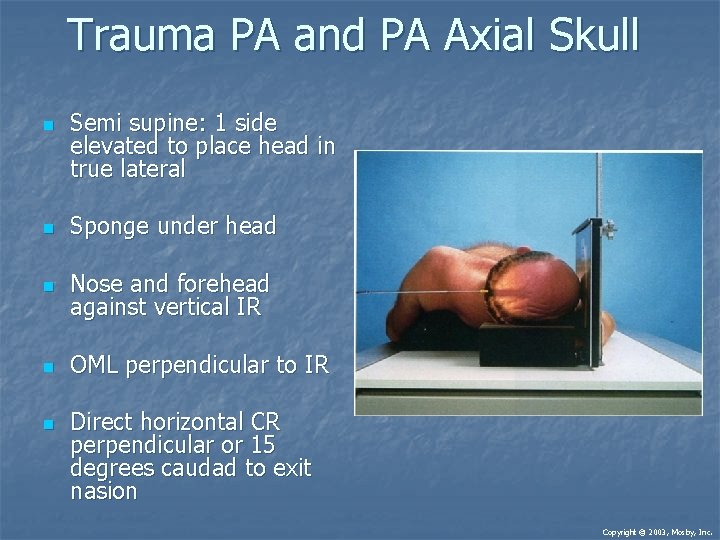
Trauma PA and PA Axial Skull n Semi supine: 1 side elevated to place head in true lateral n Sponge under head n Nose and forehead against vertical IR n OML perpendicular to IR n Direct horizontal CR perpendicular or 15 degrees caudad to exit nasion Copyright © 2003, Mosby, Inc.
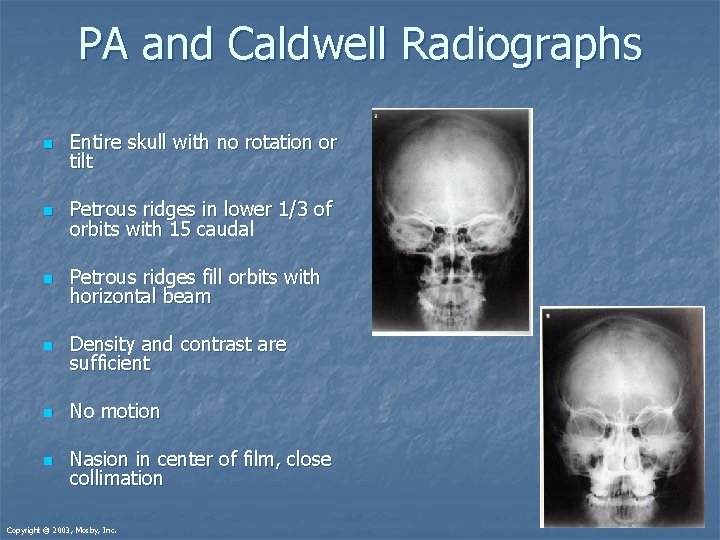
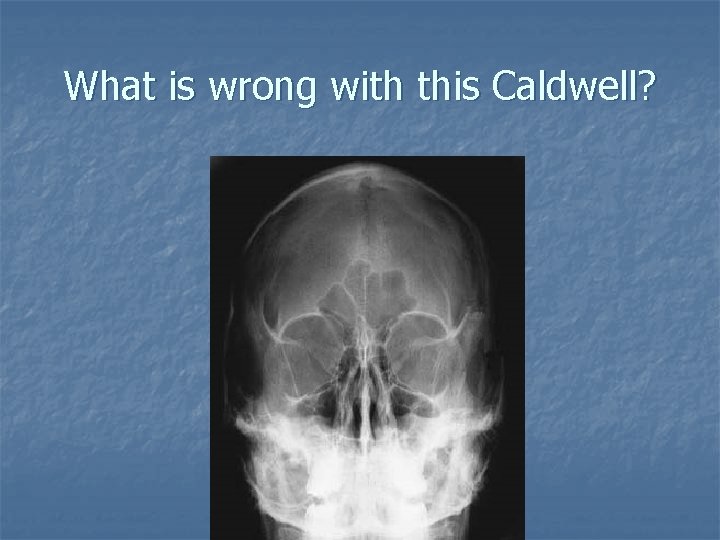
PA and Caldwell Radiographs n Entire skull with no rotation or tilt n Petrous ridges in lower 1/3 of orbits with 15 caudal n Petrous ridges fill orbits with horizontal beam n Density and contrast are sufficient n No motion n Nasion in center of film, close collimation Copyright © 2003, Mosby, Inc.
Similarities and Differences n n n Exit nasion Require close collimation n Position of petrous ridges OML is perpendicular to plane of IR n Best seen n Body position n Where the CR enters All axials have caudal angles Respiration suspended
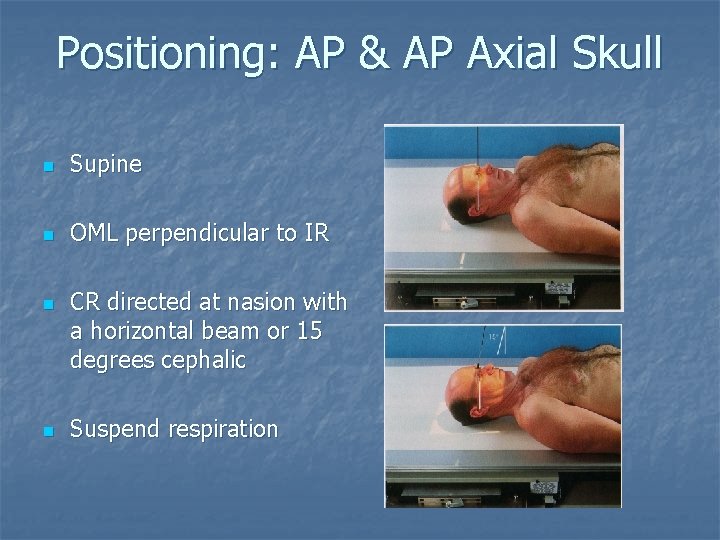
Positioning: AP & AP Axial Skull n Supine n OML perpendicular to IR n n CR directed at nasion with a horizontal beam or 15 degrees cephalic Suspend respiration
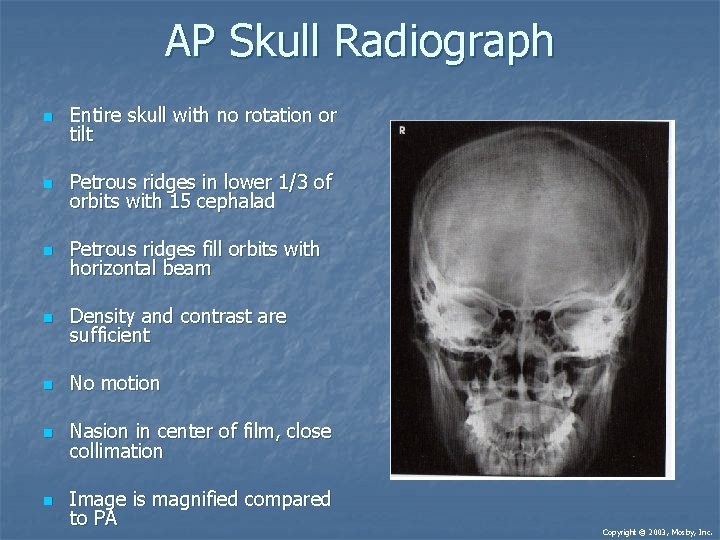
AP Skull Radiograph n Entire skull with no rotation or tilt n Petrous ridges in lower 1/3 of orbits with 15 cephalad n Petrous ridges fill orbits with horizontal beam n Density and contrast are sufficient n No motion n Nasion in center of film, close collimation n Image is magnified compared to PA Copyright © 2003, Mosby, Inc.
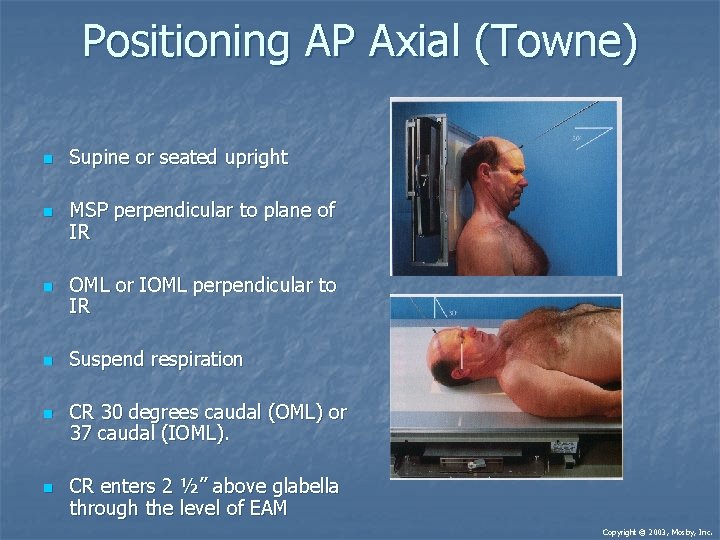
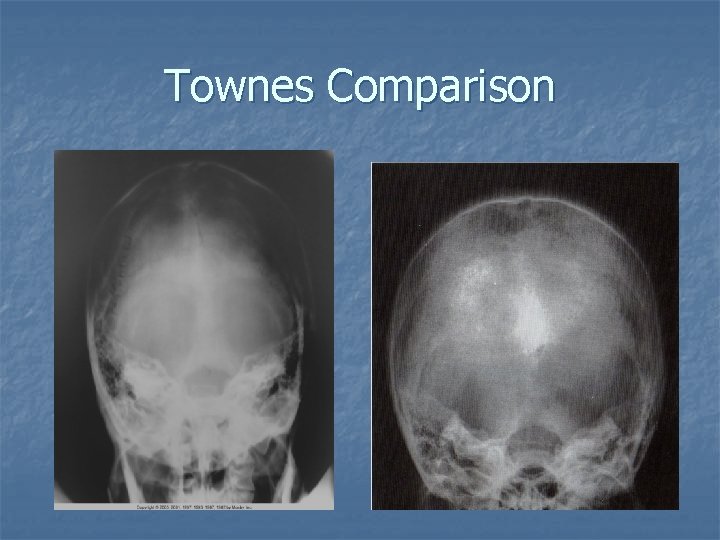
Positioning AP Axial (Towne) n n n Supine or seated upright MSP perpendicular to plane of IR OML or IOML perpendicular to IR Suspend respiration CR 30 degrees caudal (OML) or 37 caudal (IOML). CR enters 2 ½” above glabella through the level of EAM Copyright © 2003, Mosby, Inc.
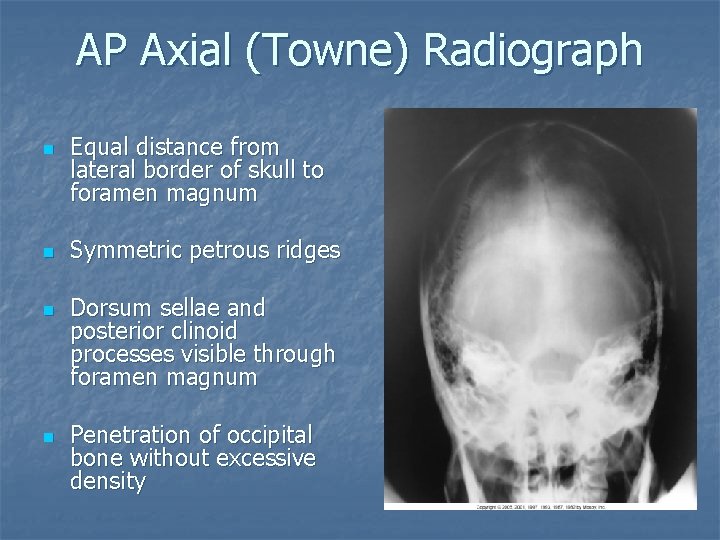
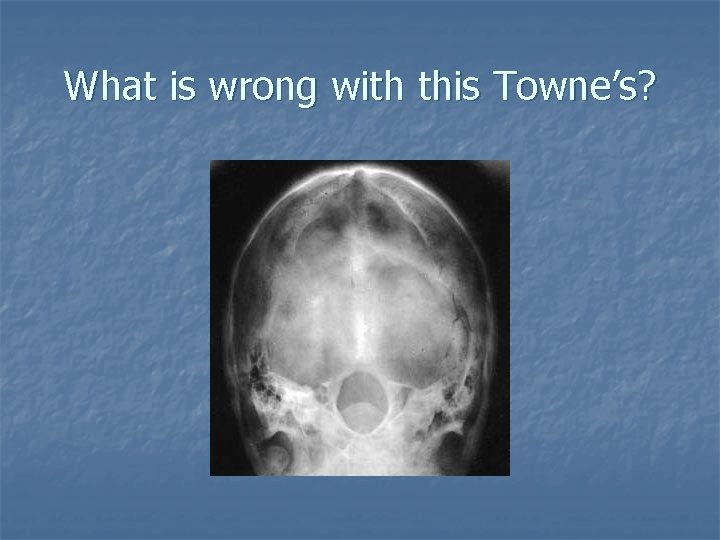
AP Axial (Towne) Radiograph n n Equal distance from lateral border of skull to foramen magnum Symmetric petrous ridges Dorsum sellae and posterior clinoid processes visible through foramen magnum Penetration of occipital bone without excessive density
Sella Turcica
Townes Comparison
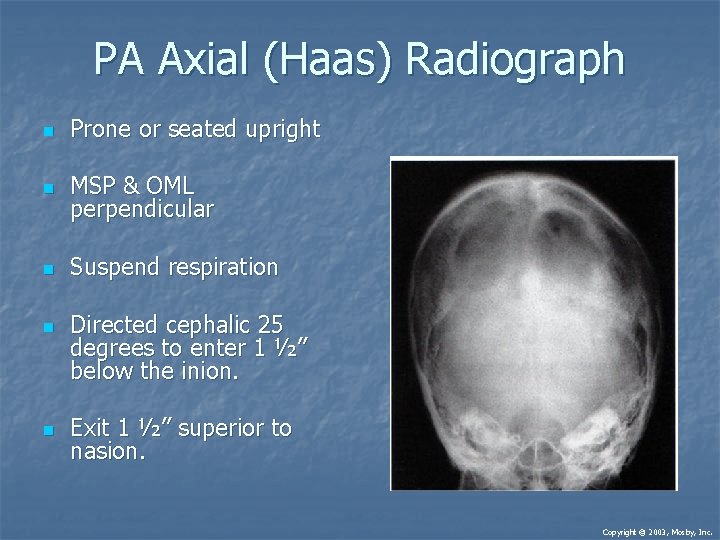
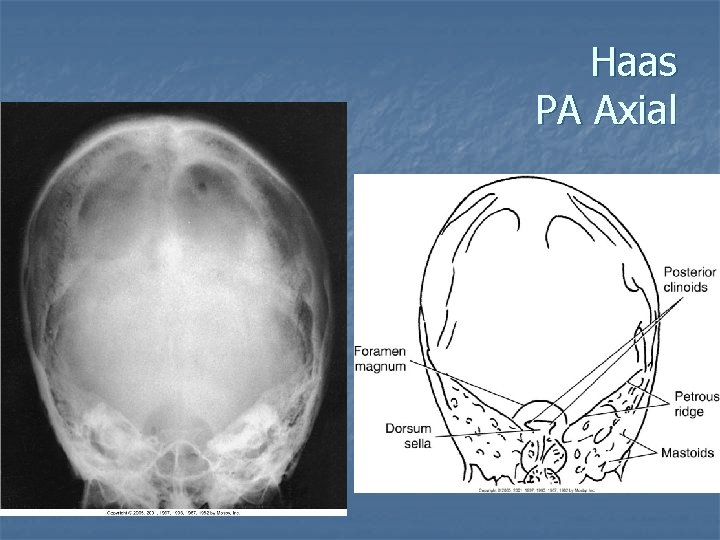
Positioning PA Axial (Haas) n n Prone or seated upright Forehead and nose on table or grid device n MSP perpendicular to the grid n OML perpendicular to IR n Suspend respiration n n CR 25 degrees cephalad entering 1 1/2 “ below occipital protuberance. R exits 1 ½” superior to nasion
PA Axial (Haas) Radiograph n Prone or seated upright n MSP & OML perpendicular n Suspend respiration n n Directed cephalic 25 degrees to enter 1 ½” below the inion. Exit 1 ½” superior to nasion. Copyright © 2003, Mosby, Inc.
Haas PA Axial
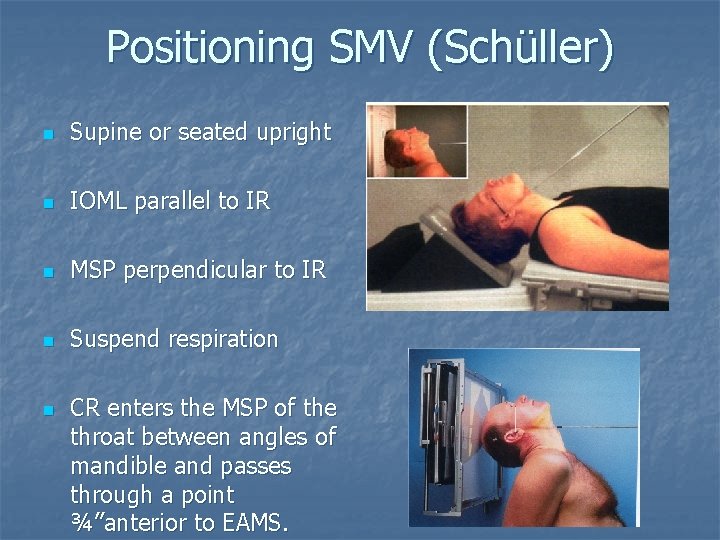
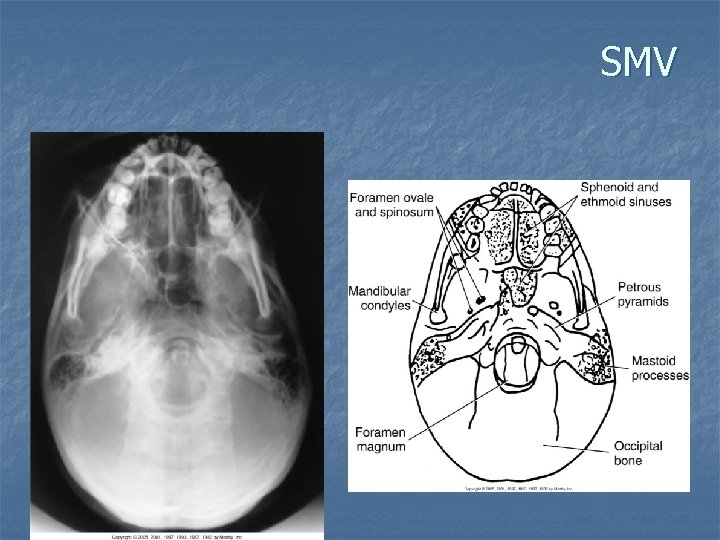
Positioning SMV (Schüller) n Supine or seated upright n IOML parallel to IR n MSP perpendicular to IR n Suspend respiration n CR enters the MSP of the throat between angles of mandible and passes through a point ¾”anterior to EAMS.
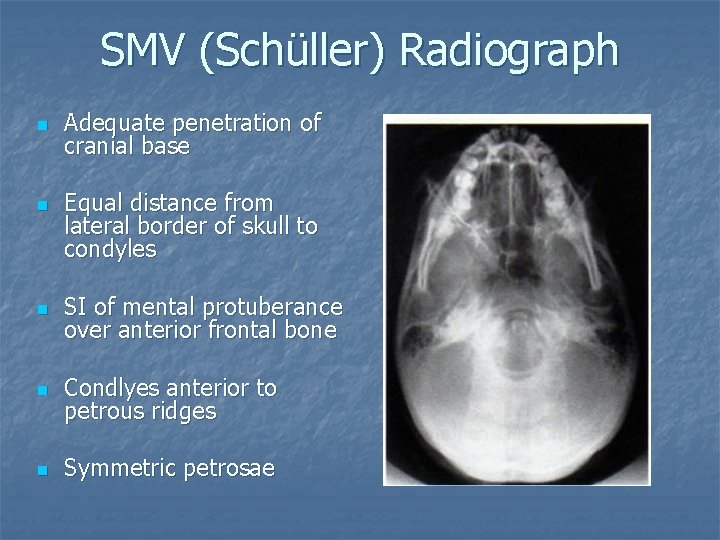
SMV (Schüller) Radiograph n n Adequate penetration of cranial base Equal distance from lateral border of skull to condyles n SI of mental protuberance over anterior frontal bone n Condlyes anterior to petrous ridges n Symmetric petrosae
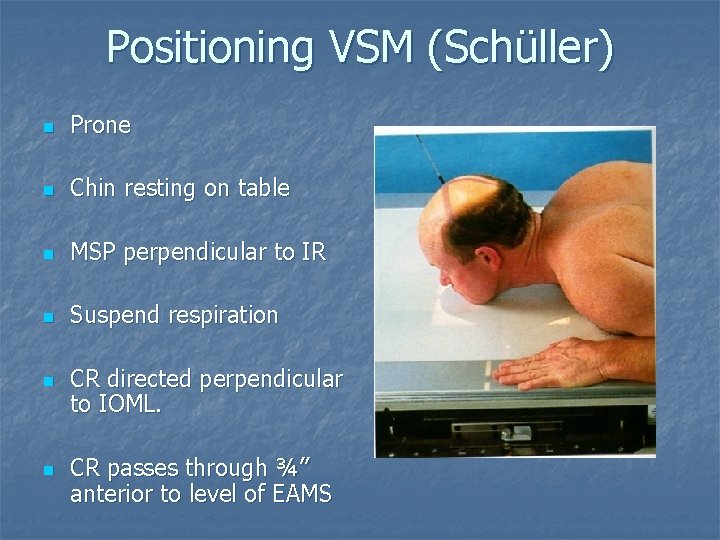
Positioning VSM (Schüller) n Prone n Chin resting on table n MSP perpendicular to IR n Suspend respiration n n CR directed perpendicular to IOML. CR passes through ¾” anterior to level of EAMS
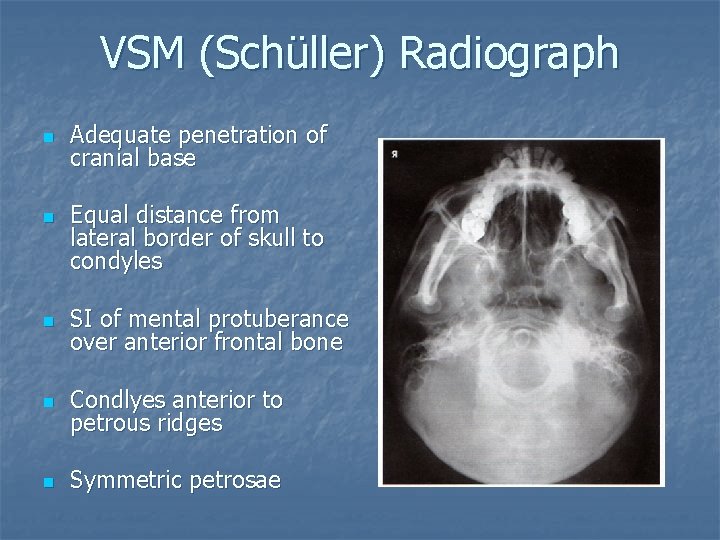
VSM (Schüller) Radiograph n n Adequate penetration of cranial base Equal distance from lateral border of skull to condyles n SI of mental protuberance over anterior frontal bone n Condlyes anterior to petrous ridges n Symmetric petrosae
SMV
What is wrong with this Caldwell?
What is wrong with this lateral skull?
What is wrong with this Towne’s?