Student Portfolio Paste student picture here Personal Information
























- Slides: 38
Student Portfolio Paste student picture here
Personal Information Sheet Name _____________________Grad. Date _________ Address ___________________________________ F M City, State, Zip code ____________________________ Birthdate ________________ Age ______ Sex _______ Phone Number ______________ SS # _________ High School Attended ______________ Yr. Graduated _____ Parents/Guardian Name ________________________ Is student conserved yes no Address if different than above ___________________________________________________________ Phone/Cell Number ___________________________ Medical Information: Mark all that apply q Glasses q Allergies ______________ q Seizures q Illnesses ______________ q Medications – List ___________________________ Primary Diagnosis _____________________________ Secondary Diagnosis ___________________________
Parent/Guardian Assessment 1. What chores or responsibilities does your student have at home? ______________________________________________________________________________ _ 2. What tasks would you like your student to be able to do at home? ______________________________________________________________________________ _ q Group home 3. After graduation from ABLE, what do you think your students q Other ___________ living situation will be? q At home q Apartment with support q Social skills q Sex education do you think your 4. In which of the following areas of independence q Organizational skills student needs help in: q Household management q Self-advocacy q Clothing care q Health/First aid q Consumer Case q Recreation/Leisure q Meal preparation q Other ___________ q Nutrition q Community awareness q Hygiene q Transportation q Safety
6. What leisure/recreational activities does your student do with family? __________________________________________________________________________ _ 7. What leisure/recreational activities does your student participate in with friends? _____________________________________________________________________ _ 8. What leisure/recreational activities would you like to see your student participate in? _________________________________________________________________ _ 9. Does your student transition well from one thing to another? _____ Have there been any problems? ____________________________________________________________ _ 10. What agencies currently provide service for your student? ___________________________________________ _ 11. What would you like the school to do to assist you with the planning of your students living, working and educational needs prior to graduation? ___________________________________________________________________ q Supported employment _ q Day program _______________________________________ q Home _
Personal Assessment 1. What chores or responsibilities do you have at home? ______________________________________________________________________________ _ 2. What tasks would you like to be able to do at home? _______________________________________ _ _______________________________________ q Group home _ q Other ___________ 3. After graduation, what do you think your living situation will be? q At home q Independent Living q Social skills q Sex education do you think you 4. In which of the following areas of independence q Organizational skills need help in: q Household management q Self-advocacy q Clothing care q Health/First aid q Consumer Case q Recreation/Leisure q Meal preparation q Other ___________ q Nutrition q Community awareness q Hygiene q Transportation q Safety 5. What leisure or recreational activities do you do when you’re
6. What leisure/recreational activities do you do with your family? ______________________________________________________________________________ _ 7. What leisure/recreational activities do you participate in with your friends? _______________________________________________________________________ _ 8. What leisure/recreational activities would you like to see yourself participating in? _____________________________________________________________________ _ 9. Do you transition well from one activity to another? _______ Have there been any problems? _______________________________________________________________ _ 10. What agencies currently provide service to you? _________________________________________________ _ 11. What would you like the school to do to assist you with your living, working and educational needs prior to graduating? q Supported employment _______________________________________ q Day program _ q Home _______________________________________ _ _______________________________________
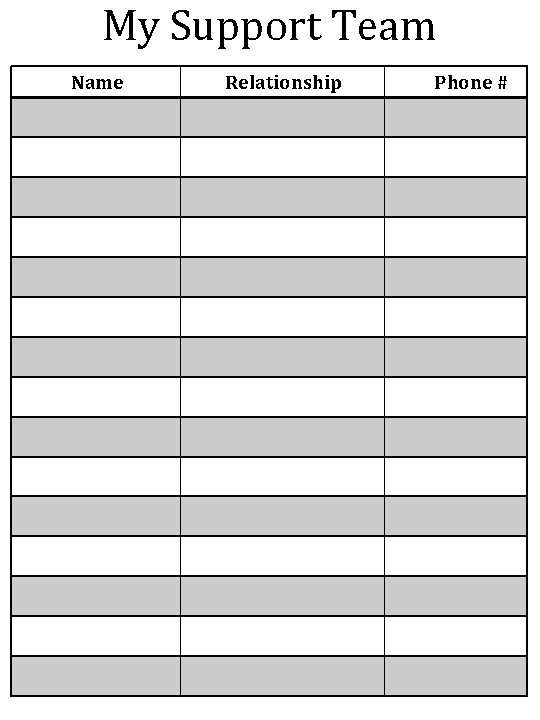
My Support Team Name Relationship Phone #
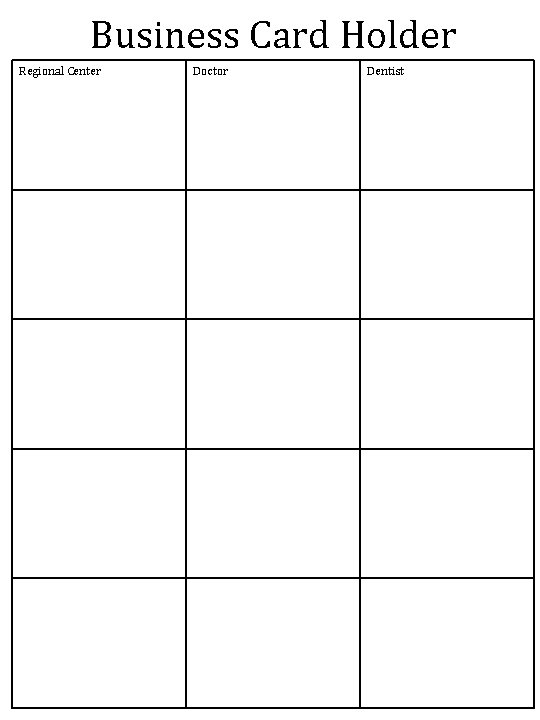
Business Card Holder Regional Center Doctor Dentist
Resume
Current IEP
Student Transcripts
Goal Log
Parent/Teacher/Student Goals Goal 1: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Goal met Not met _____ Date Goal 2: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Review Quarter ____ Notes: Goal met Not met _____ Date
Parent/Teacher/Student Goals Goal 3: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Goal met Not met _____ Date Goal 4: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Review Quarter ____ Notes: Goal met Not met _____ Date
Parent/Teacher/Student Goals Goal 5: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Goal met Not met _____ Date Goal 6: Home Procedures: Classroom Procedures: Progress Quarter ____ Notes: Review Quarter ____ Notes: Goal met Not met _____ Date
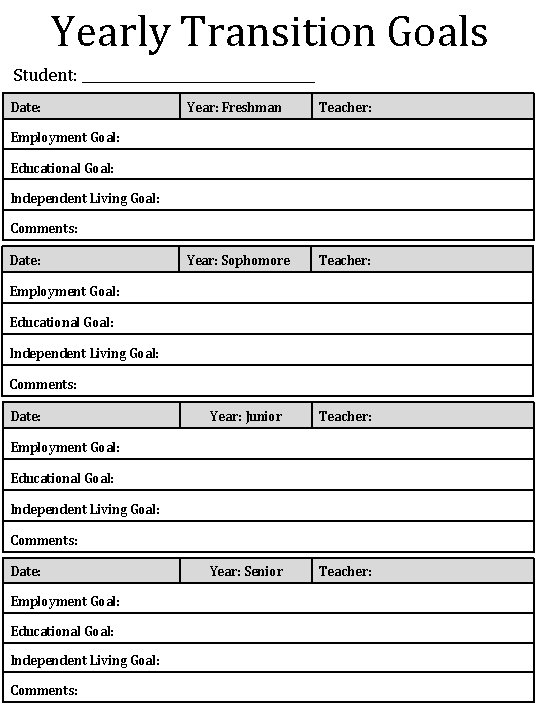
Yearly Transition Goals Student: __________________ Date: Year: Freshman Teacher: Year: Sophomore Teacher: Employment Goal: Educational Goal: Independent Living Goal: Comments: Date: Year: Junior Teacher: Year: Senior Teacher: Employment Goal: Educational Goal: Independent Living Goal: Comments: Date: Employment Goal: Educational Goal: Independent Living Goal: Comments:
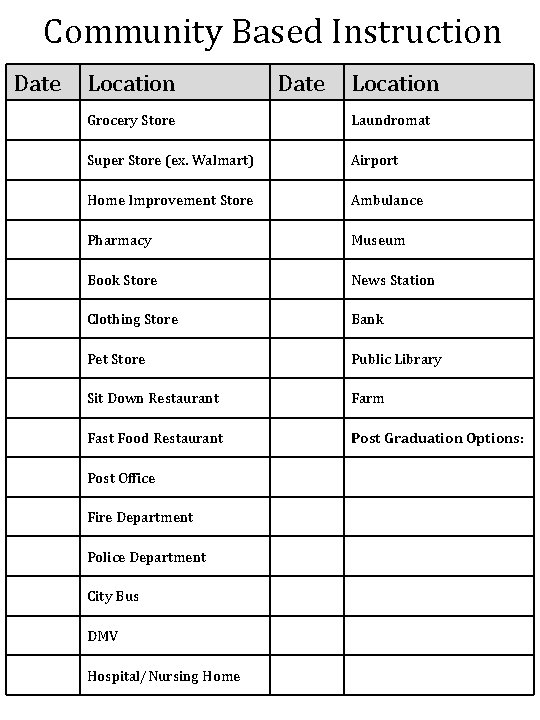
Community Based Instruction Date Location Grocery Store Laundromat Super Store (ex. Walmart) Airport Home Improvement Store Ambulance Pharmacy Museum Book Store News Station Clothing Store Bank Pet Store Public Library Sit Down Restaurant Farm Fast Food Restaurant Post Graduation Options: Post Office Fire Department Police Department City Bus DMV Hospital/Nursing Home
Student Pictures
Certificates of Achievement
Job Trainings Job Site Dates From: To: From: To: From: To: From: To: From: To: Work skills
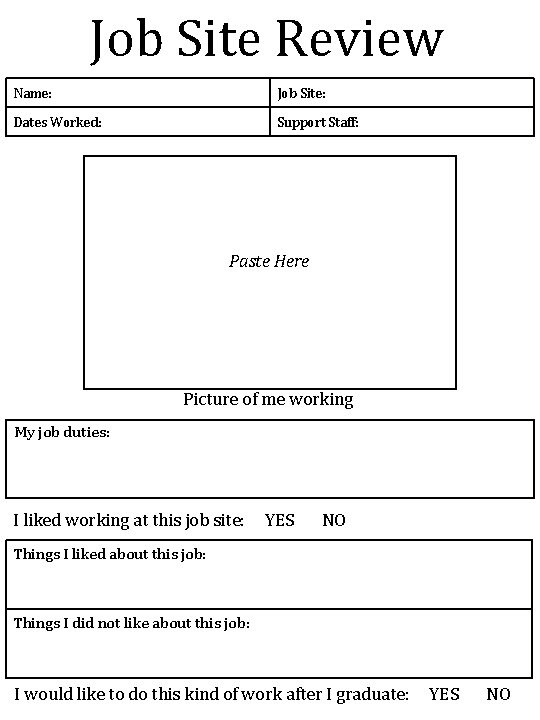
Job Site Review Name: Job Site: Dates Worked: Support Staff: Paste Here Picture of me working My job duties: I liked working at this job site: YES NO Things I liked about this job: Things I did not like about this job: I would like to do this kind of work after I graduate: YES NO
Job Site Evaluation Name: Job Site: Review Period: Support Staff: Job Duties: Student Strengths: Concerns: Excellent Personal - Satisfactory Poor Attendance Appropriate Clothing Hygiene Attitude Rate student 1 – 5 according to their work habits and abilities. 1 2 3 4 5 Poor Fair Satisfactory Good Excellent 1. Can follow simple one step tasks 1 2 3 4 5 2. Multiple tasks can be followed when given 1 2 3 4 5 3. Shows enthusiasm in his/her job 1 2 3 4 5 4. Can work without being supervised 1 2 3 4 5 5. Can stay on task without distraction 1 2 3 4 5 6. Asks for help when needed 1 2 3 4 5 7. Is knowledgeable about the job and tasks performed 1 2 3 4 5 8. Is friendly with customers and coworkers 1 2 3 4 5 9. Accepts criticism when presented properly 1 2 3 4 5 10. Follows safety rules while on the job 1 2 3 4 5 Signed: _____________ Support Staff / Teacher _____________ Student Date
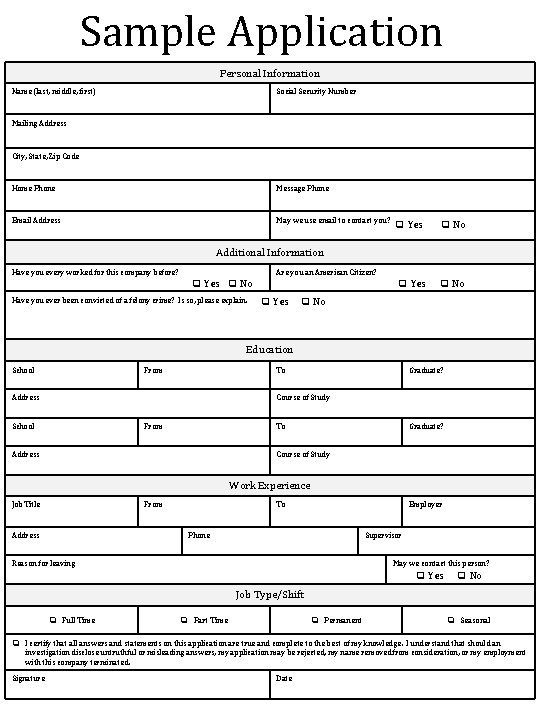
Sample Job Application
Sample Application Personal Information Name (last, middle, first) Social Security Number Mailing Address City, State, Zip Code Home Phone Message Phone Email Address May we use email to contact you? q Yes q No Additional Information Have you every worked for this company before? Are you an American Citizen? q Yes q No Have you ever been convicted of a felony crime? Is so, please explain. q Yes q No Education School From To Address Graduate? Course of Study Work Experience Job Title From Address To Employer Phone Supervisor Reason for leaving May we contact this person? q Yes q No Job Type/Shift q Full Time q Part Time q Permanent q Seasonal q I certify that all answers and statements on this application are true and complete to the best of my knowledge. I understand that should an investigation disclose untruthful or misleading answers, my application may be rejected, my name removed from consideration, or my employment with this company terminated. Signature Date
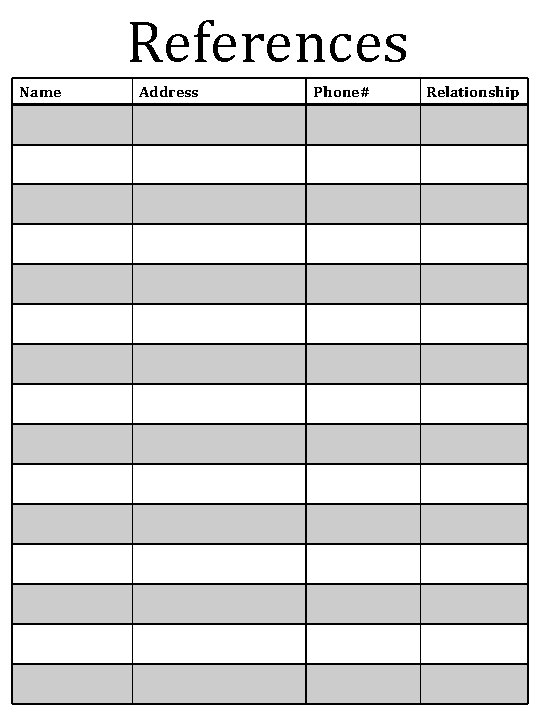
References Name Address Phone# Relationship
Letters of Recommendation
Student Assessments
Language Arts Assessment Write the letter that comes BEFORE the letters listed below: ____ C ____ G ____ E ____ J ____V ____ B ____ O ____ M ____ X ____ R ____ P ____ Z ____ U ____ S Write the letter that comes AFTER the letters listed below: A ____ S ____ Y ____ D ____ V ____ C ____ F ____ G ____ L ____ K ____ M ____ X ____ O ____ Y ____ Color each crayon to identify the correct color: Red Blue Brown Purple Yellow Black Green Pink Orange Put the following words in ABC order: 1. Dog 1. _______ 1. Pig 1. _______ 2. Bird 2. _______ 2. Hen 2. _______ 3. Mouse 3. _______ 3. Frog 3. _______ Draw a line to match the word to the picture: Book Fish Tree Stop Car Dog Sun Milk ©Empowered. By. THEM 2014
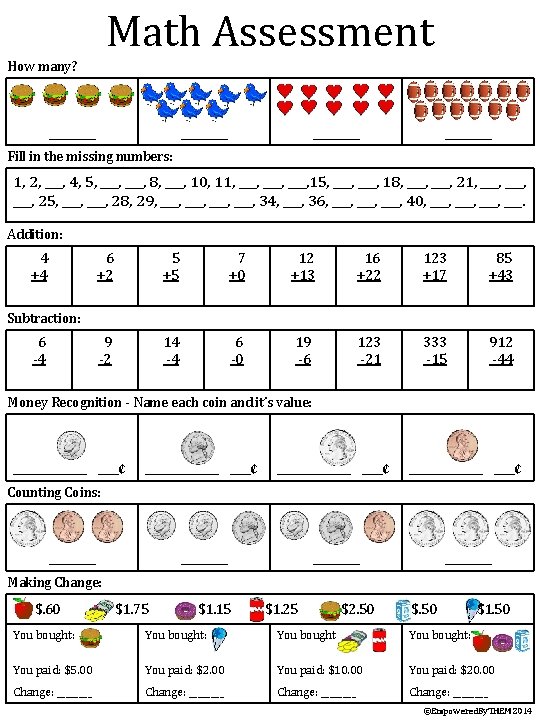
Math Assessment How many? _______ Fill in the missing numbers: 1, 2, ___, 4, 5, ___, 8, ___, 10, 11, ___, 15, ___, 18, ___, 21, ___, 25, ___, 28, 29, ___, 34, ___, 36, ___, 40, ___, ___. Addition: 4 +4 6 +2 5 +5 7 +0 12 +13 16 +22 123 +17 85 +43 9 -2 14 -4 6 -0 19 -6 123 -21 333 -15 912 -44 Subtraction: 6 -4 Money Recognition - Name each coin and it’s value: ___________ ___₵ _______ Counting Coins: _______ Making Change: $. 60 $1. 75 $1. 15 $1. 25 $2. 50 $1. 50 You bought: You paid: $5. 00 You paid: $2. 00 You paid: $10. 00 You paid: $20. 00 Change: ________ ©Empowered. By. THEM 2014
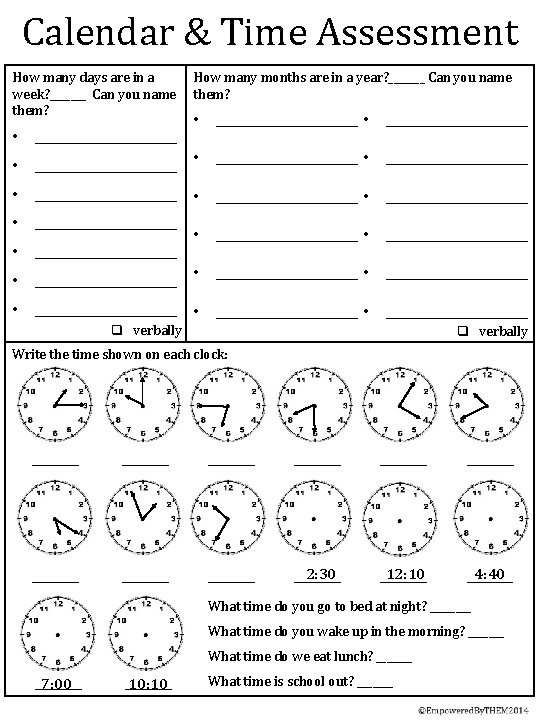
Calendar & Time Assessment How many days are in a week? _______ Can you name them? How many months are in a year? _______ Can you name them? • ________________________ • ________________________ • ________________________ • ________________________ • ________________________ • ____________ q verbally Write the time shown on each clock: _______ _______ _______ 2: 30 _______ 12: 10 _______ 4: 40 _______ What time do you go to bed at night? ____ What time do you wake up in the morning? _______ What time do we eat lunch? _______ 7: 00 _______ 10: 10 What time is school out? _______
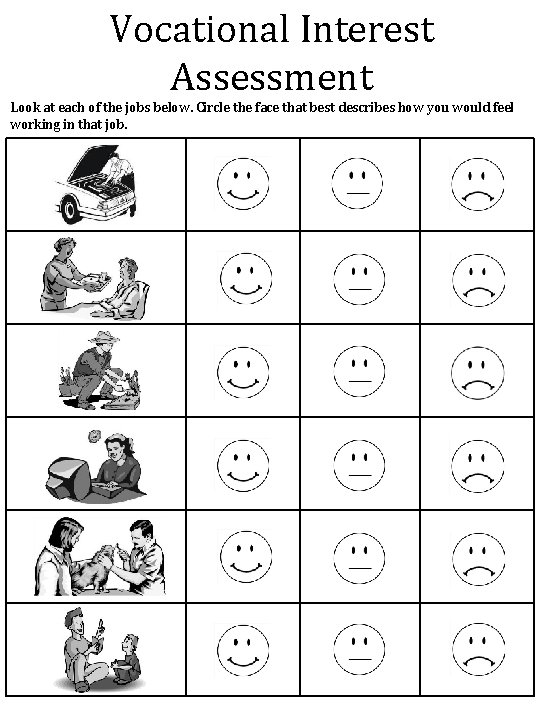
Vocational Interest Assessment Look at each of the jobs below. Circle the face that best describes how you would feel working in that job.
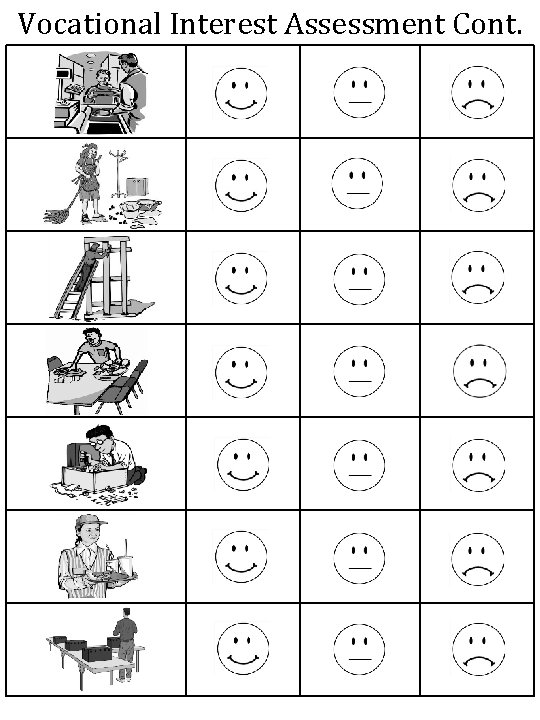
Vocational Interest Assessment Cont.
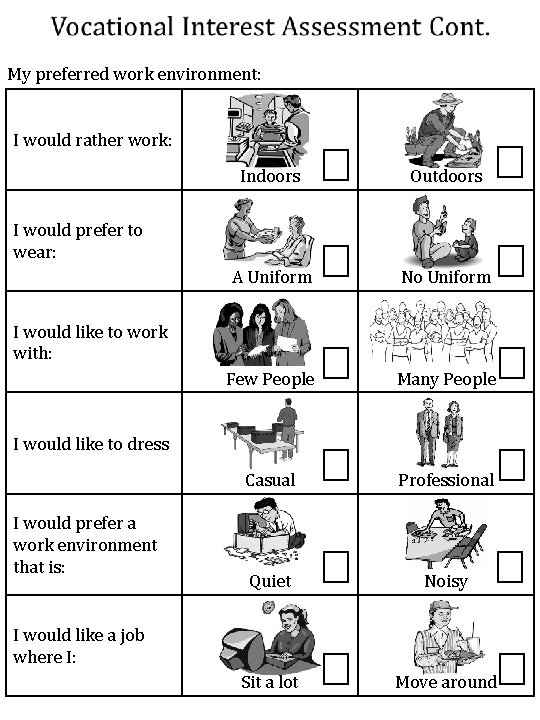
My preferred work environment: I would rather work: Indoors Outdoors A Uniform No Uniform Few People Many People Casual Professional Quiet Noisy Sit a lot Move around I would prefer to wear: I would like to work with: I would like to dress I would prefer a work environment that is: I would like a job where I:
Functional Academics Classwork
Vocational Skills Classwork
Independent Living Skills Classwork
Social Skills Classwork