Partnering for Maternal Data Quality Improvement Elliott Main





























- Slides: 40
Partnering for Maternal Data Quality Improvement Elliott Main, MD: CMQCC Medical Director Anne Castles, MPH, MA: CMDC Project Manager Barbara Murphy, RN, MS: CMQCC Administrative Director Supported with grants from: Centers for Disease Control California Health Care Foundation
Objectives: n n n Describe the initiatives in California to improve BC data quality Describe the national multi-organization effort to standardize maternity terminology Describe the importance of sharing data in order to improve the data quality Presenter Disclosure(s): n None
CMQCC and CPQCC Mission: Improving care for moms and newborns California Maternal Quality Care Collaborative (CMQCC) n n n Expertise in maternal data analysis Developer of QI toolkits Host of collaborative learning sessions California Perinatal Quality Care Collaborative (CPQCC) n n Expertise in data capture from hospitals Established secure data center Data use agreements in place with 130 hospitals with NICUs Model of working with state agencies to provide data of value Both are Multi-Stakeholder Public/Private Quality Collaboratives With DPH playing a leading role
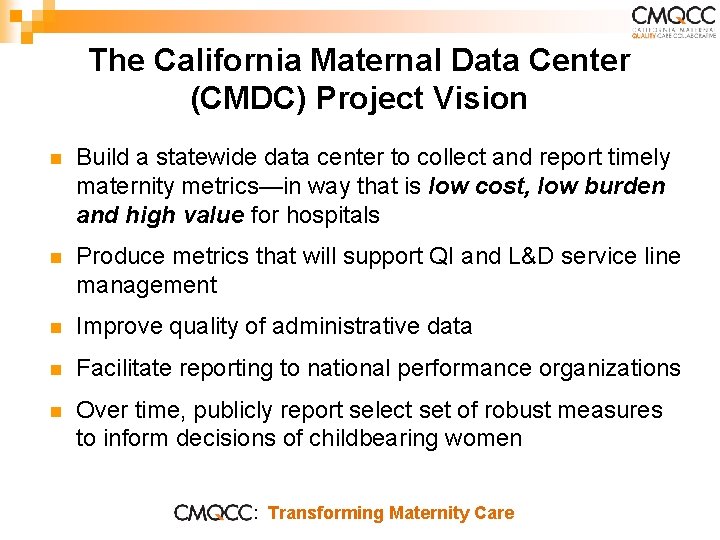
The California Maternal Data Center (CMDC) Project Vision n Build a statewide data center to collect and report timely maternity metrics—in way that is low cost, low burden and high value for hospitals n Produce metrics that will support QI and L&D service line management n Improve quality of administrative data n Facilitate reporting to national performance organizations n Over time, publicly report select set of robust measures to inform decisions of childbearing women : Transforming Maternity Care
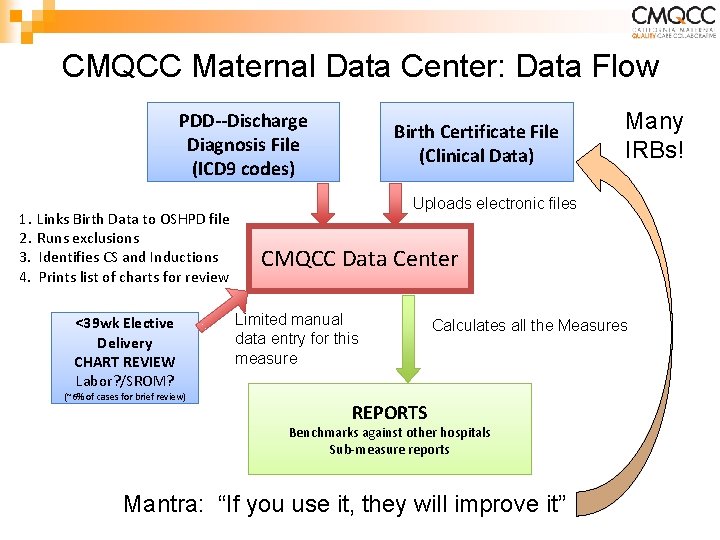
CMQCC Maternal Data Center: Data Flow PDD--Discharge Diagnosis File (ICD 9 codes) 1. 2. 3. 4. Links Birth Data to OSHPD file Runs exclusions Identifies CS and Inductions Prints list of charts for review <39 wk Elective Delivery CHART REVIEW Labor? /SROM? (~6% of cases for brief review) Birth Certificate File (Clinical Data) Many IRBs! Uploads electronic files CMQCC Data Center Limited manual data entry for this measure Calculates all the Measures REPORTS Benchmarks against other hospitals Sub-measure reports Mantra: “If you use it, they will improve it” : Transforming Maternity Care
Why Improve Maternity Data? n HISTORICALLY: Maternity data in PDD and BC used by researchers and public health professionals to track trends and practices n NOW: An additional focus on evaluating and improving the quality of maternity services Ø CMS Inpatient Quality Reporting Program: reporting of ED<39 weeks to start in 2013 Ø Medi-Cal: Developing quality dashboard; likely to include perinatal metrics Ø TJC to require reporting of perinatal set for hospitals that perform more than 1100 deliveries annually: to start 2014 Ø QI Collaboratives: Patient Safety First and HENs
How Many Horses Are At Your Data Trough?
Key Principle: The more users for the data, the greater the effort for improving data quality.
Maternal Data QI in California: 5 Components 1) 2) 3) 4) 5) Standardize Definitions Education (providers and staff) Redesign / System Changes Improving Data as QI Project Create Value for Maternal Data QI for hospitals
Maternal Data QI in California: 5 Components 1) Standardize Definitions Ø re. VITALize Project Ø GA Toolkit (work with ACOG and Hospitals)
Obstetric Data Definitions Initiative National Conference August 2 -3, 2012 Arlington, Virginia
Campaign Initiatives § To nationally standardize obstetric clinical data § § definitions. To educate and advocate for national implementation of the standardized obstetric data elements and definitions in electronic medical records, birth certificates, and data registries To increase and improve performance measurement and implementation of the national obstetric data standards and encourage data aggregation.
It’s the Language… The World of Clinical Obstetrics The World of Public and Admin Health Communications “Britain and America are two nations divided by a common language. ” --George Bernard Shaw
It’s the Language… § Different regions of the country may use terms differently … § Even within an OB department, not everyone uses the same terms for the same condition… § Different notes on the same patient, can have different terms used (induced vs augmented) § Birth clerks and coders have to read the notes and then…. guess? And then translate into their categorical systems
Timeline 1 Pre-Conference Preparation v. Identified data elements from various sources, including: • 2003 Birth Certificate • ACOG/National Committee for Quality Assurance/Physician Consortium for Performance Improvement – Maternity Care Set • Agency for Healthcare Research and Quality – Birth Trauma Injury Rate • California Maternity Quality Care Collaborative – Healthy Term Newborn • The Joint Commission – Perinatal Care Core Set v. Two rounds of surveys were completed by conference stakeholders to determine necessity of revision and priority v. Provided existing definitions from ACOG, ICD-09, Williams Obstetrics, the National Center for Health Statistics, and others to serve as a basis for revision discussion
3 Post-Conference Follow-Up v The data element definitions not reaching 85% of attendee support were brought back into workgroup conference calls for additional discussion and revision v 50 refined data element definitions were sent forward for Public Comment § Public Comment was open NOV 2012 to JAN 2013 § 625 individuals, representing over 450 organizations participated § Nearly 11, 000 responses were received in support of the revised definitions v Public Comment Review and Finalization (In Progress)
4 Implementation (In Progress) v. Publications § Data Dictionary § Articles v. Education v. Incorporation into Integrating the Healthcare Enterprise (IHE) profiles for EMR certification and Meaningful Use § Clinical decision support § EMR Patient Management Triggers § Data quality auditing logic models v. Incorporation into coding and nomenclature
Thank You, Workgroup Leaders! Jennifer Bailit, MD, MPH, FACOG Cleveland, OH Debra Bingham, Dr. Ph, RN Washington, DC Gerald Carrino, Ph. D, MPH White Plains, NY Suneet Chauhan, MD, FACOG Norfolk, VA Kimberly Gregory, MD, MPH, FACOG West Hollywood, CA Tina Groat, MD, MBA, FACOG Canton, MI Isabelle Horon, Dr. PH Baltimore, MD David La. Grew, MD, FACOG Fountain Valley, CA Rebekah Gee, MD, MPH, FACOG Baton Rouge, LA David Lakey, MD William Sappenfield, MD, MPH Tallahassee, FL Austin, TX
Maternal Data QI in California: 5 Components 1) Standardize Definitions 2) Education: Incent complete and accurate documentation among § Providers § Coders § Birth Clerks ØBirth Data Quality Training Sessions (Vital Records) ØGA Toolkit (CMQCC, ACOG and Hospitals)
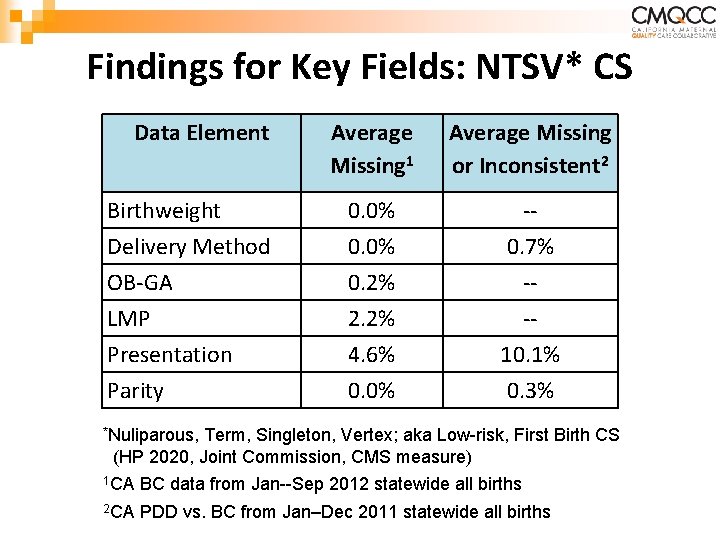
Findings for Key Fields: NTSV* CS Data Element Birthweight Delivery Method OB-GA LMP Presentation Parity Average Missing 1 Average Missing or Inconsistent 2 0. 0% 0. 2% 2. 2% 4. 6% 0. 0% -0. 7% --10. 1% 0. 3% *Nuliparous, Term, Singleton, Vertex; aka Low-risk, First Birth CS (HP 2020, Joint Commission, CMS measure) 1 CA BC data from Jan--Sep 2012 statewide all births 2 CA PDD vs. BC from Jan–Dec 2011 statewide all births
Conclusions for Key Fields Definite Area for Improvement n Fetal Presentation Ø Even though clerks score in medium range for ease of finding and frequency of contradictory information, large percentage of actual missing /contradictory suggest a problem Ø When asked to code less common clinical terminology (e. g. Occiput Anterior), BC clerks picked right answer only 14 -31% of time. (Report p. 6)
Conclusions for Key Fields n Fetal Presentation Terminology Ø Vertex = Occiput = Cephalic Ø OA, OT, OP Deep transverse arrest Face or compound n Presentation may be missing for CS deliveries
Birth Data Quality Improvement Project 2012
Tool Kit & Tip Sheets • Agenda & Letter from CMQCC & SCCPHD • AVSS Data (January-June 2012) • Tip sheets • Worksheet • CD of all files and tip sheets • Contact information
Maternal Data QI in California: 5 Components 1) Standardize Definitions 2) Education 3) Redesign / System Changes: Improve clinical documentation systems across hospital providers to facilitate complete and accurate data capture Ø Standard Locations for Key Data Ø Work with EMR vendors to generate worksheet Ø Develop and disseminate coding best practices Ø GA Toolkit (CMQCC, ACOG and Hospitals)
Data Issues for Gestational Age n No EDD or GA in Doctor’s note(s) n Multiple EDD / GA’s in L&D chart (which is best? ) n Multiple EDD’s in Prenatal chart (which is best? ) n Transcription errors when copying from prenatal n Delivery occurring many days after the admission GA n Revision of EDD / GA after admission n Lack of a standard approach for using US to confirm/establish best EDD. No wonder a Birth Certificate clerk may have difficulties! : Transforming Maternity Care
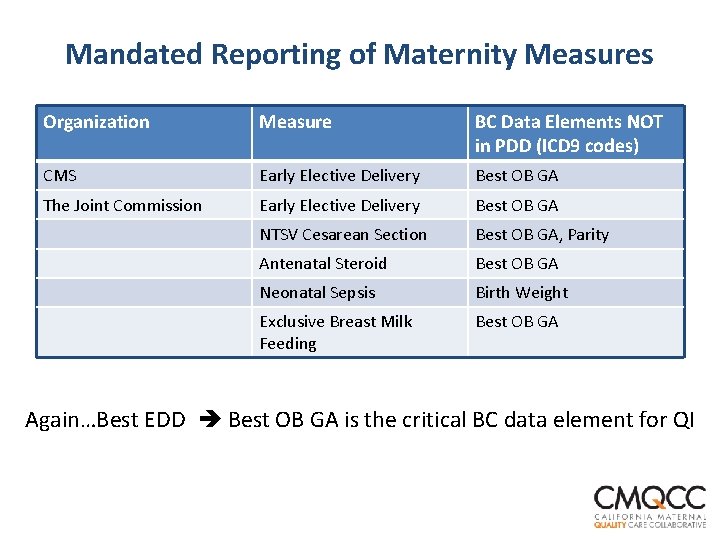
Mandated Reporting of Maternity Measures Organization Measure BC Data Elements NOT in PDD (ICD 9 codes) CMS Early Elective Delivery Best OB GA The Joint Commission Early Elective Delivery Best OB GA NTSV Cesarean Section Best OB GA, Parity Antenatal Steroid Best OB GA Neonatal Sepsis Birth Weight Exclusive Breast Milk Feeding Best OB GA Again…Best EDD Best OB GA is the critical BC data element for QI
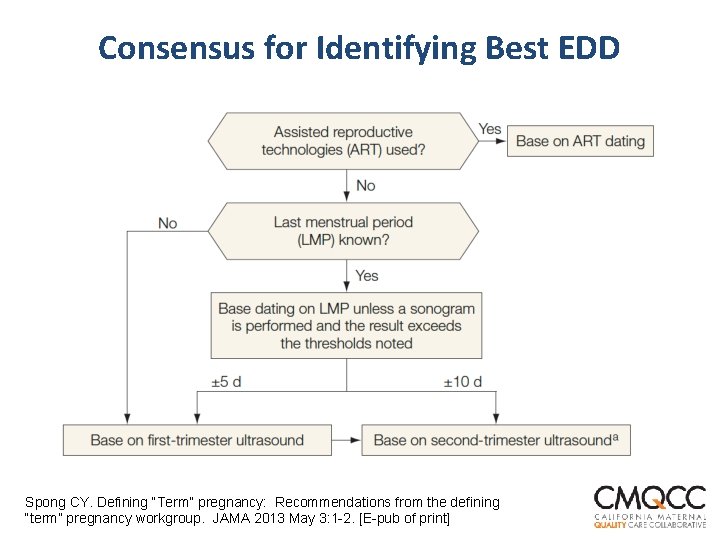
Consensus for Identifying Best EDD Spong CY. Defining “Term” pregnancy: Recommendations from the defining “term” pregnancy workgroup. JAMA 2013 May 3: 1 -2. [E-pub of print]
Most Important Single Data QI Project is: Best EDD n Medical Policy Issues ¨ When to change Best EDD based on US ¨ Criteria for US (sac <7 wks, CRL <14 wk, BPD <20 wk) ¨ How to reconcile multiple US reports ¨ Need to improve wording of US reports for EDD n Implementation/Process Issues ¨ Prenatal Best EDD Black Box on every record ¨ To be completed by 20 weeks ¨ Tweak new AMA/PCPI OB quality measure to capture this ¨ On admission, this EDD is transferred to a similar Hospital Best EDD Black Box used by all (including BC clerks)
Maternal Data QI in California: 5 Components 1) 2) 3) 4) Standardize Definitions Education Redesign / System Changes Improving Data as QI Project: Apply QI principles to improving accuracy/completeness of data ØHospital-BC Missing Data Reports ØComparisons of BC to PDD for audit and feedback ØQI Run Charts for Data Quality
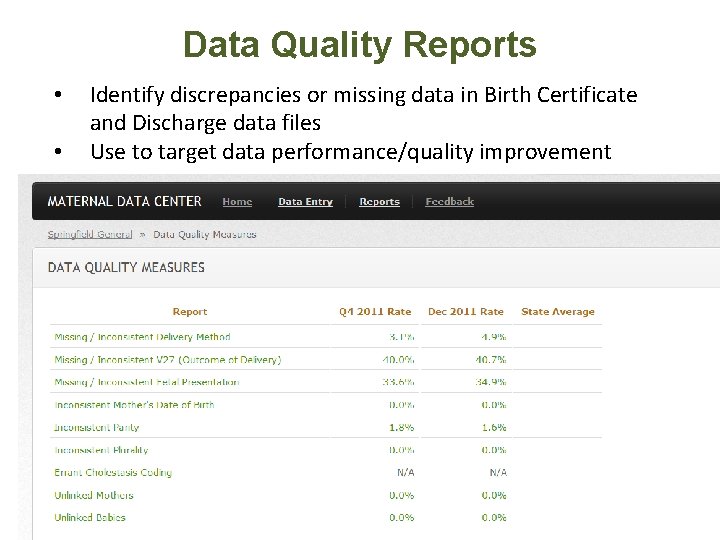
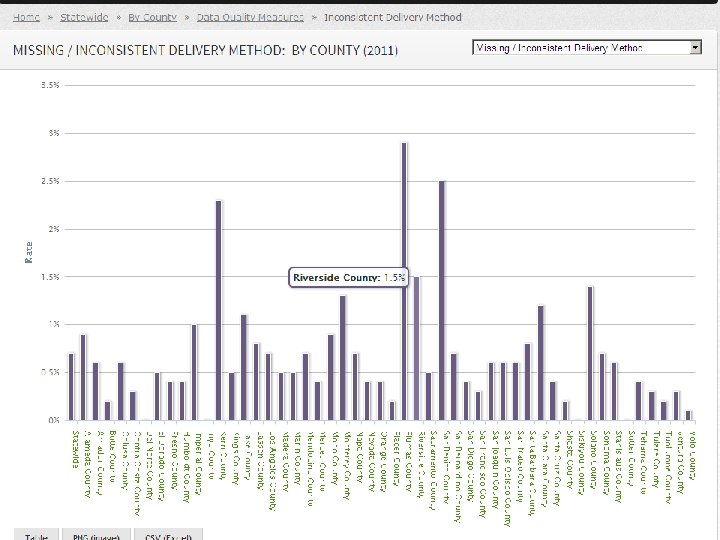
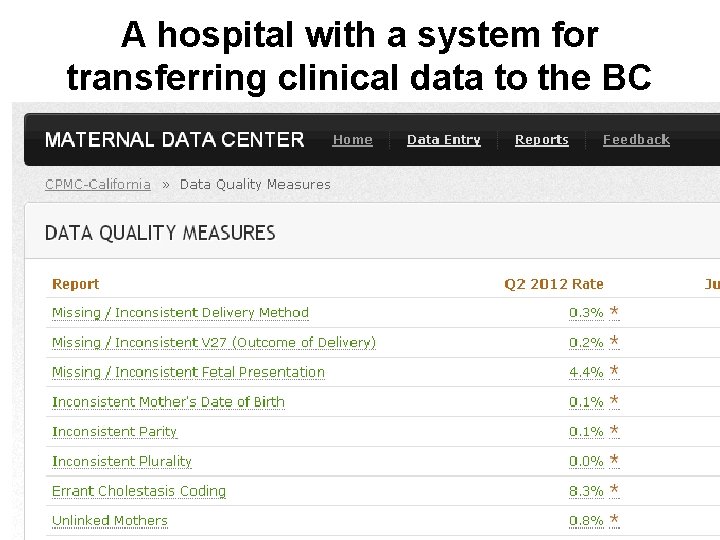
Data Quality Reports • • Identify discrepancies or missing data in Birth Certificate and Discharge data files Use to target data performance/quality improvement Screen shot from the California Maternal Data Center 34
35
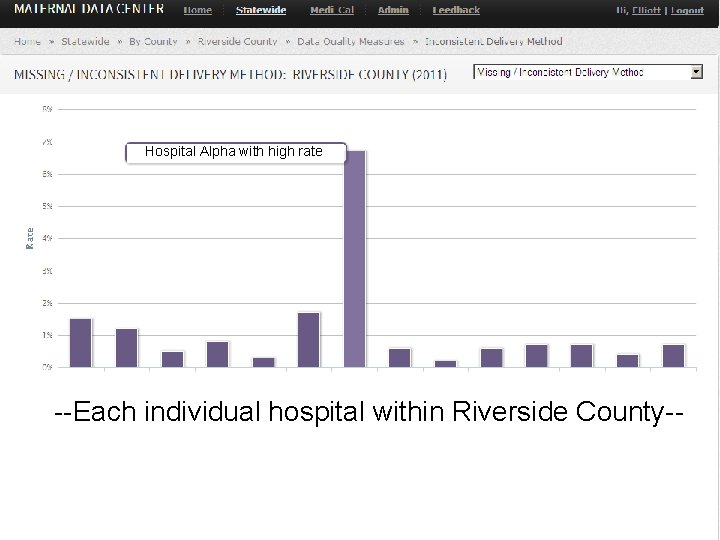
Hospital Alpha with high rate --Each individual hospital within Riverside County-- 36
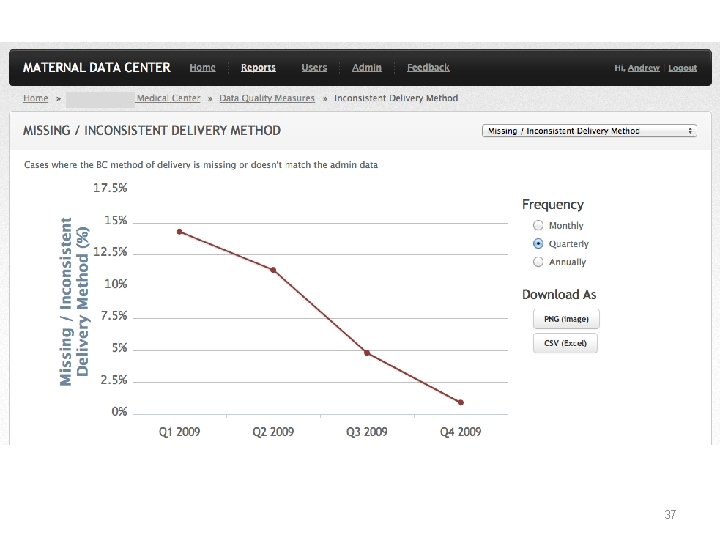
37
A hospital with a system for transferring clinical data to the BC
Maternal Data QI in California: 5 Components 1) 2) 3) 4) 5) Standardize Definitions Education Redesign / System Changes Improving Data as QI Project Create Value for Maternal Data QI for hospitals (“If you use it, they will improve it”) ØUse BC/PPD data for internal QI ØUse BC/PPD data for QI reporting (e. g. to TJC) ØUse BC/PPD data for Public Reporting
New Joint Commission Decision n As of July 2013, hospitals have option to use Birth Certificate data for TJC Perinatal Set for: q OB Estimate of GA q Birthweight q Parity n Implication Abstract one time (well!) and satisfy both Vital Records and TJC requirements Potential to make hospital data collection and reporting activities more efficient Ø Improves quality of data for use by state policymakers Ø : Transforming Maternity Care
A boy and his Killer Whale… Timely sharing of Vital Record data with partners invested in improving data quality is a winner for everyone! FREE the DATA
Thank You!