47 Year Old Male with Familial Hypertriglyceridemia History








- Slides: 16
47 Year Old Male with Familial Hypertriglyceridemia History of present illness: 47 year old male with familial hypertriglyceridemia and elevated liver enzymes.
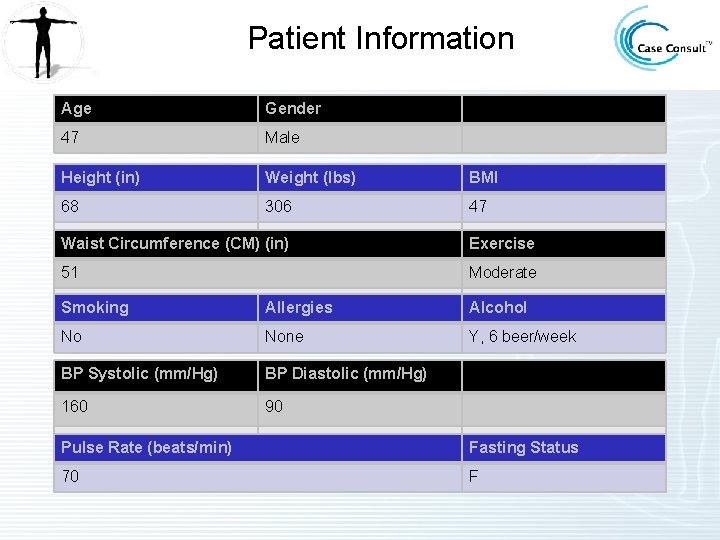
Patient Information Age Gender 47 Male Height (in) Weight (lbs) BMI 68 306 47 Waist Circumference (CM) (in) Exercise 51 Moderate Smoking Allergies Alcohol No None Y, 6 beer/week BP Systolic (mm/Hg) BP Diastolic (mm/Hg) 160 90 Pulse Rate (beats/min) Fasting Status 7 70 F
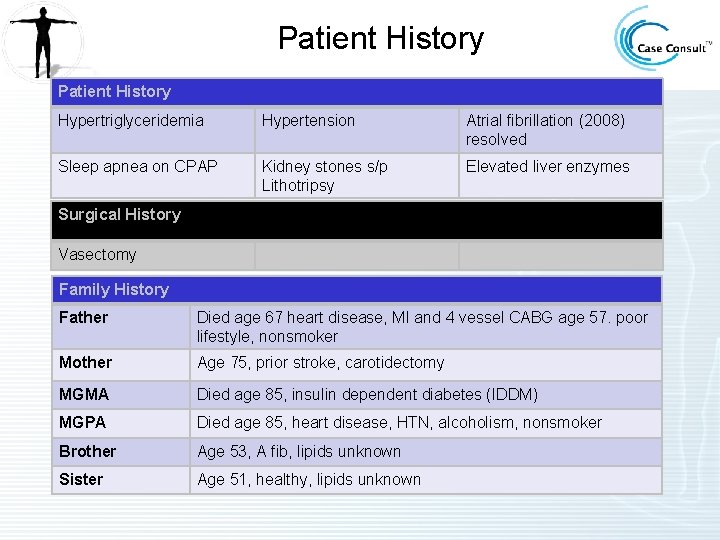
Patient History Hypertriglyceridemia Hypertension Atrial fibrillation (2008) resolved Sleep apnea on CPAP Kidney stones s/p Lithotripsy Elevated liver enzymes Surgical History Vasectomy Family History Father Died age 67 heart disease, MI and 4 vessel CABG age 57. poor lifestyle, nonsmoker Mother Age 75, prior stroke, carotidectomy MGMA Died age 85, insulin dependent diabetes (IDDM) MGPA Died age 85, heart disease, HTN, alcoholism, nonsmoker Brother Age 53, A fib, lipids unknown Sister Age 51, healthy, lipids unknown
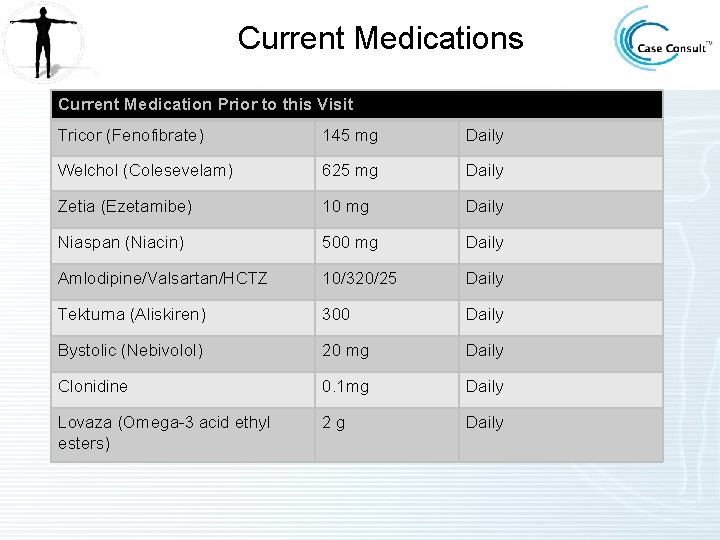
Current Medications Current Medication Prior to this Visit Tricor (Fenofibrate) 145 mg Daily Welchol (Colesevelam) 625 mg Daily Zetia (Ezetamibe) 10 mg Daily Niaspan (Niacin) 500 mg Daily Amlodipine/Valsartan/HCTZ 10/320/25 Daily Tekturna (Aliskiren) 300 Daily Bystolic (Nebivolol) 20 mg Daily Clonidine 0. 1 mg Daily Lovaza (Omega-3 acid ethyl esters) 2 g Daily
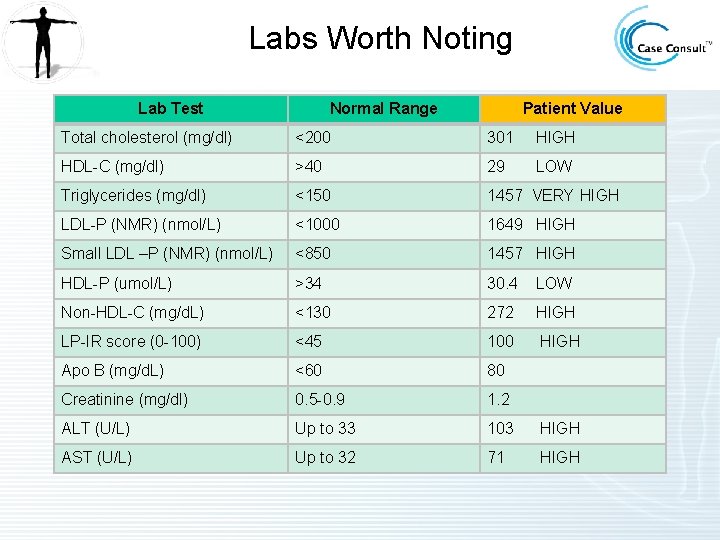
Labs Worth Noting Lab Test Normal Range Patient Value Total cholesterol (mg/dl) <200 301 HIGH HDL-C (mg/dl) >40 29 LOW Triglycerides (mg/dl) <150 1457 VERY HIGH LDL-P (NMR) (nmol/L) <1000 1649 HIGH Small LDL –P (NMR) (nmol/L) <850 1457 HIGH HDL-P (umol/L) >34 30. 4 LOW Non-HDL-C (mg/d. L) <130 272 HIGH LP-IR score (0 -100) <45 100 HIGH Apo B (mg/d. L) <60 80 Creatinine (mg/dl) 0. 5 -0. 9 1. 2 ALT (U/L) Up to 33 103 HIGH AST (U/L) Up to 32 71 HIGH
Questions to Consider • Question 1: Stain produced elevated LFTs in past, which statin and were LFTs>3 time upper limit normal? • Question 2: Have secondary causes of high triglycerides been ruled out? Diabetes, hypothyroidism, medications? • Question 3: Contraindications to current medications? • Question 4: Sub-therapeutic doses of Niacin and omega 3, is there a prior intolerance?
Labs
NMR Lipo. Profile • Insert NMR Lipo. Profile 12042010 CU 63 Insert
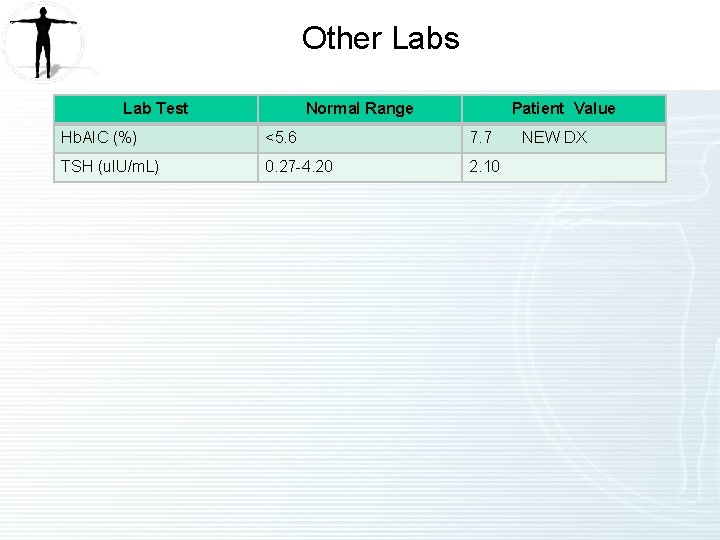
Other Labs Lab Test Normal Range Patient Value Hb. AIC (%) <5. 6 7. 7 TSH (u. IU/m. L) 0. 27 -4. 20 2. 10 NEW DX
Initial Treatment & Management • • • Advise low carb diet and increase exercise. Minimize alcohol. Stop Welchol (lowers LDL C but raises triglycerides) Stop Zetia Increase Niaspan to 1000 mg/day Stop Tricor (lack of efficacy as trigs still >1000 and Creatinine 1. 2) Start metformin ER 500 mg up to 4 tablets daily with slow titration as tolerated over the next few weeks • Increase Lovaza to 4 tablets/day • Advise home blood pressure meter • Start a statin: Crestor 20 mg/day (LFTs not > 3 times Upper limit normal, Crestor or Lipitor most efficacious statins for TG lowering) Note: Multiple treatment changes made in one visit due to patient willingness and also long distance from our clinic and interest in maximizing treatment quickly to minimize risk for complications from very high triglycerides >1000.
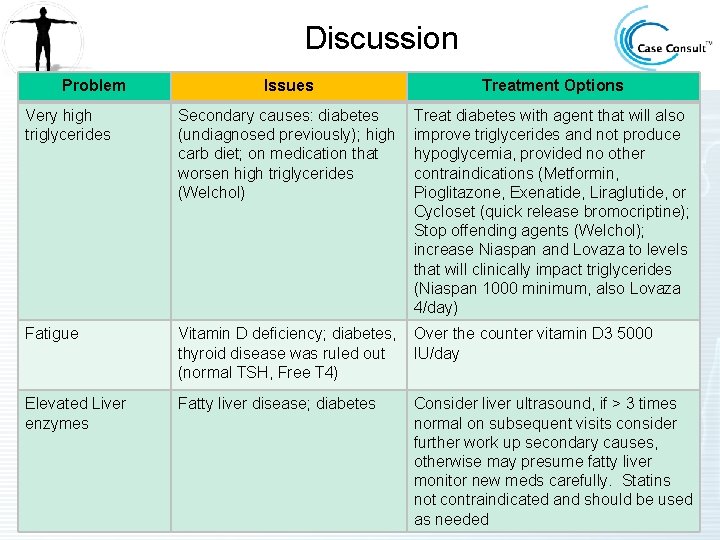
Discussion Problem Issues Treatment Options Very high triglycerides Secondary causes: diabetes (undiagnosed previously); high carb diet; on medication that worsen high triglycerides (Welchol) Treat diabetes with agent that will also improve triglycerides and not produce hypoglycemia, provided no other contraindications (Metformin, Pioglitazone, Exenatide, Liraglutide, or Cycloset (quick release bromocriptine); Stop offending agents (Welchol); increase Niaspan and Lovaza to levels that will clinically impact triglycerides (Niaspan 1000 minimum, also Lovaza 4/day) Fatigue Vitamin D deficiency; diabetes, thyroid disease was ruled out (normal TSH, Free T 4) Over the counter vitamin D 3 5000 IU/day Elevated Liver enzymes Fatty liver disease; diabetes Consider liver ultrasound, if > 3 times normal on subsequent visits consider further work up secondary causes, otherwise may presume fatty liver monitor new meds carefully. Statins not contraindicated and should be used as needed
Follow Up • Follow Up Visit: Last visit stopped zetia and tricor due to lack of efficacy. Raised Niaspan to 1000 mg, Lovaza to 4/day and added Metformin ER 1500 and Crestor 20 mg/day. • It is 2 months later and he also did start low carb diet as recommended. He lost weight 11 pounds (despite the holidays). Reports less fatigue. Last visit a Vitamin D level was drawn and noted to be very low at 23 (not yet treated). He is tolerating all medications. Niaspan caused some initial flushing when he first started higher dose but doing well. No side effects from statin to date. • Home BP checks performed and reports levels 130 s to 140 s over high 80 s.
Follow-Up NMR Lipo. Profile • Insert NMR Lipo. Profile 02042011 CU 63 Insert
Clinical Pearls When evaluating very abnormal lipid profile in the setting of multiple medications and apparent lack of efficacy consider stopping therapy in addition to adding any agents. In his case he is on several medications that were either contraindicated or may not have been needed and/or were not helping. (See discussion section). It may be very appropriate to add back Tricor in future if triglycerides increase further or fail to stabilize. His angiotensin receptor blocker (Valsartan) and Tekturna have recently been found to be contraindicated for use together especially in a patient with diabetes (Novartis Media Release dated 12/20/11). He will need work up for secondary causes of hypertension and should also have medications adjusted based on drug-drug interactions. Don’t be afraid to use statins in the setting of elevated liver enzymes. Many patients have fatty liver as cause of high ALT and usually will have improvement in LFTs with treatment of insulin resistance of dyslipidemia. If > 3 times normal additional work up for secondary causes of liver enzyme elevation may be appropriate.
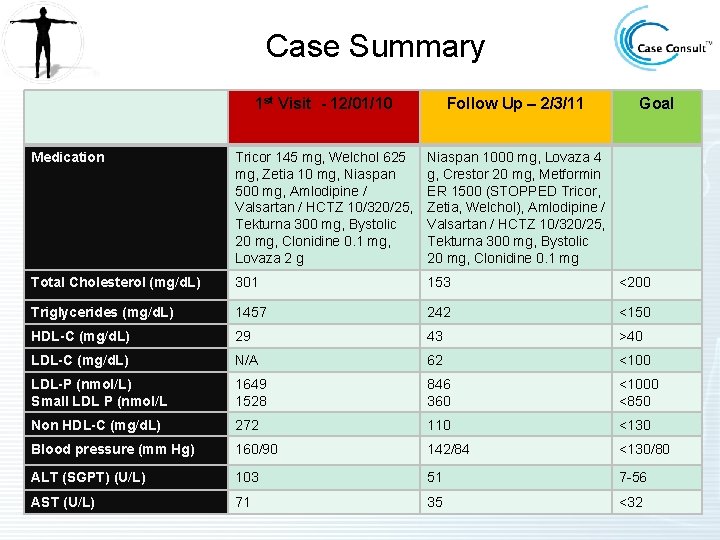
Case Summary 1 st Visit - 12/01/10 Follow Up – 2/3/11 Goal Medication Tricor 145 mg, Welchol 625 mg, Zetia 10 mg, Niaspan 500 mg, Amlodipine / Valsartan / HCTZ 10/320/25, Tekturna 300 mg, Bystolic 20 mg, Clonidine 0. 1 mg, Lovaza 2 g Niaspan 1000 mg, Lovaza 4 g, Crestor 20 mg, Metformin ER 1500 (STOPPED Tricor, Zetia, Welchol), Amlodipine / Valsartan / HCTZ 10/320/25, Tekturna 300 mg, Bystolic 20 mg, Clonidine 0. 1 mg Total Cholesterol (mg/d. L) 301 153 <200 Triglycerides (mg/d. L) 1457 242 <150 HDL-C (mg/d. L) 29 43 >40 LDL-C (mg/d. L) N/A 62 <100 LDL-P (nmol/L) Small LDL P (nmol/L 1649 1528 846 360 <1000 <850 Non HDL-C (mg/d. L) 272 110 <130 Blood pressure (mm Hg) 160/90 142/84 <130/80 ALT (SGPT) (U/L) 103 51 7 -56 AST (U/L) 71 35 <32
References • • • National Cholesterol Education Program. Executive Summary of The Third Report of The National Cholesterol Education Program (NCEP) Expert Panel on Detection, Evaluation, And Treatment of High Blood Cholesterol In Adults (Adult Treatment Panel III). JAMA. May 16 2001; 285(19): 2486 -97. Kolovou GD, Anagnostopoulou KK, Kostakou PM, et al. Primary and secondary hypertriglyceridaemia. Curr Drug Targets. Apr 2009; 10(4): 336 -43. Haffner SM. Secondary prevention of coronary heart disease: the role of fibric acids [editorial; comment]. Circulation. Jul 4 2000; 102(1): 2 -4. Mc. Kenney JM, Mc. Cormick LS, Weiss S. A randomized trial of the effects of atorvastatin and niacin in patients with combined hyperlipidemia or isolated hypertriglyceridemia. Collaborative Atorvastatin Study Group. Am J Med. Feb 1998; 104(2): 137 -43. Roth EM, Bays HE, Forker AD, et al. Prescription omega-3 fatty acid as an adjunct to fenofibrate therapy in hypertriglyceridemic subjects. J Cardiovasc Pharmacol. Jul 10 2009;