Maryland Pharmacy Programs Claims Processing Training January 2007
































































- Slides: 77
Maryland Pharmacy Programs Claims Processing Training January 2007
Affiliated Computer Services (ACS) Agenda n Implementation Information n Coordinated Pro. DUR – MCO/PBM Information n Call Center Information n Operational Information (All Programs) n Operational Information (By Program) n Clinical Information (By Program) n Conclusion
Program Learning Objectives n Understand explain how the POS system works. n Know the differences between the old and new POS processing system n Be able to operate the system at Provider level and educate Providers Staff n Understand processing procedures on PDL, Mental Health drugs, HIV, and drugs requiring PA
ACS Prescriptions Benefit Management (PBM) n Serve 32 programs nationwide – including Medicaid, senior programs, and workers’ compensation programs n Process more than 200 million pharmacy claims annually. n Manage States’ drug spend of more than $14 Billion. n Manage 14 million covered lives, or 1 in every 3 Medicaid eligibles nationwide.
ACS Prescriptions Benefit Management (PBM) n Process over 2 million calls and faxes in our call centers annually n Process an average of 100, 000 prior authorizations each month. n Manage a retail pharmacy network of 56, 000 providers, approximately 80% of all pharmacies nationwide. n Administer federal and supplemental rebate programs and collect over $100 million in manufacturer rebates
Implementation Information n February 4, 2007 is the official implementation date. n Down time – FH will cease processing at 11 PM February 3, 2007. n ACS will be processing no later than 3 PM on February 4, 2007. n Follow internal downtime procedures during this outage
Operational Program Changes General Information n Claims will only be accepted in the NCPDP Version 5. 1 Claim Format via POS n There is no batch claim submissions accepted
Coordinated Pro. DUR - MCO/PBM Information The ACS POS system has a mechanism, which at the pharmacy level, with one transmission, will electronically link the payer with all recipient drug information necessary to perform Coordinated Pro. DUR. n n n MCO Services Specialty Mental Health Services Medical Assistance Program Services Providers will submit a single transmission only. Coordinated Pro. DUR editing is “message only”
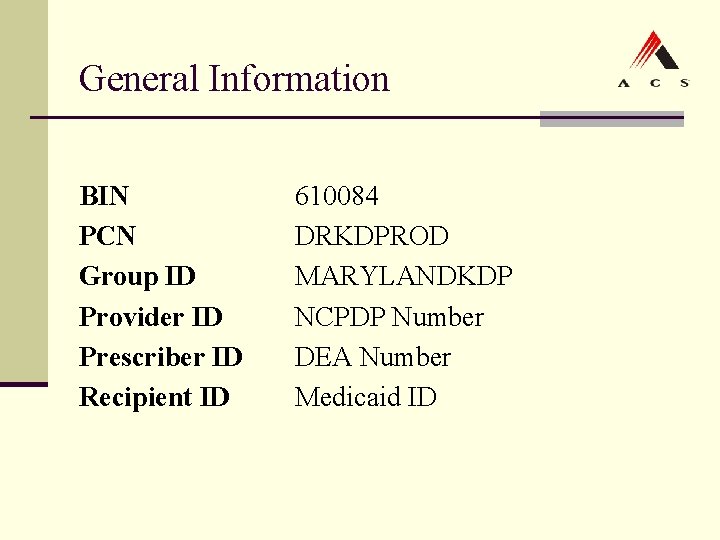
Coordinated Pro. DUR n ACS will process claims for the Mental Health Carve-out drugs then send any drug that are denied to the MCO for processing. All claims MUST be sent to the following: BIN: 610084 n PCN: Use current ACS code submitted n Group ID – Use current number submitted n
ACS Call Center All Programs n Call Center n PA Call Center number n Phone: 1 -800 -932 -3918 n Fax: 1 -866 -440 -9345 n Technical Call Center number Phone: 1 -800 -932 -3918 n Fax: 1 -866 -440 -9345 n Hours of Operation: 24/7/365 n Henderson facility handles overflow and after hours n
ACS Call Center n Staffed by Customer Service Representatives and Pharmacy Technicians n Pharmacist on site 8: 30 am to 5: 00 pm and on call 24 hours per day n Includes multi-lingual support services Will Handle: n Claims inquiries n Clinical inquiries n Program specific and general inquiries n Prior Authorizations
PAC Call Center n PAC Eligibility Services Call Center information n Call Center Number – (800) 226 -2142 n General questions about the PAC Program n Maryland residents requesting an application n Maryland residents who have applied but no decision has been made - questioning status of application n Applicant questioning a determination decision
Maryland Medicaid (OOEP)
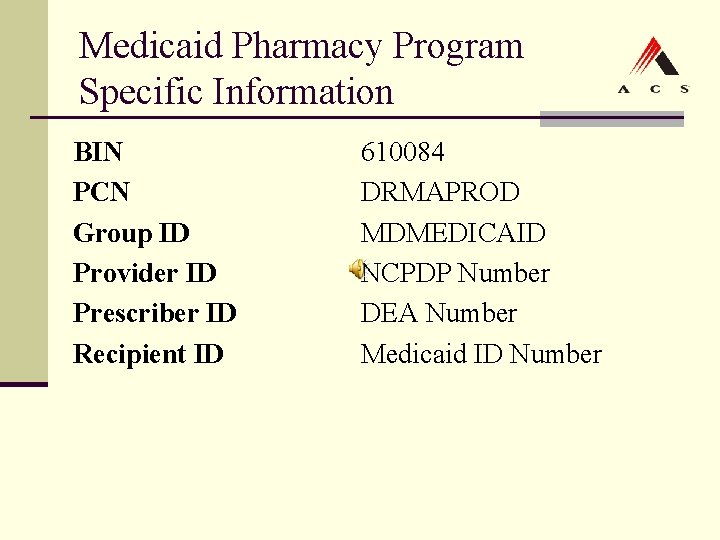
Medicaid Pharmacy Program Specific Information BIN PCN Group ID Provider ID Prescriber ID Recipient ID 610084 DRMAPROD MDMEDICAID NCPDP Number DEA Number Medicaid ID Number
Copays n Fee for Service = $1. 00 / 3. 00 PAC copays = up to $2. 50 for generics and up to $7. 50 for brand name drugs NH = NO copays; n Pregnancy = NO copays (PA type = 4) n Family Planning medications = NO copay MMI State Funded Foster copay = $1. 00 / 3. 00 (no exceptions) n MCO/HMO copay - up to $1. 00 for generics and up to $3. 00 for brand name drugs
Copay Exceptions Patient is pregnant n Patient drug is a family planning medication. n Long Term Care (LTC) claims n Preferred Drug List (PDL) – 3 day emergency supply n
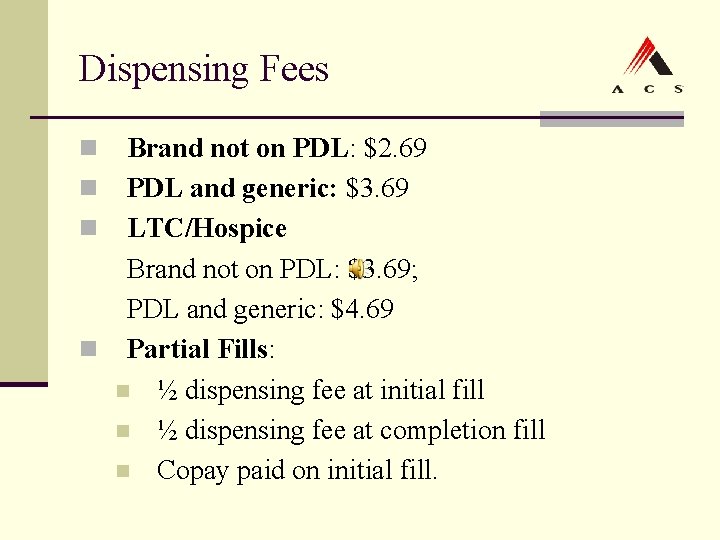
Dispensing Fees Brand not on PDL: $2. 69 n PDL and generic: $3. 69 n LTC/Hospice Brand not on PDL: $3. 69; PDL and generic: $4. 69 n Partial Fills: n ½ dispensing fee at initial fill n ½ dispensing fee at completion fill n Copay paid on initial fill. n
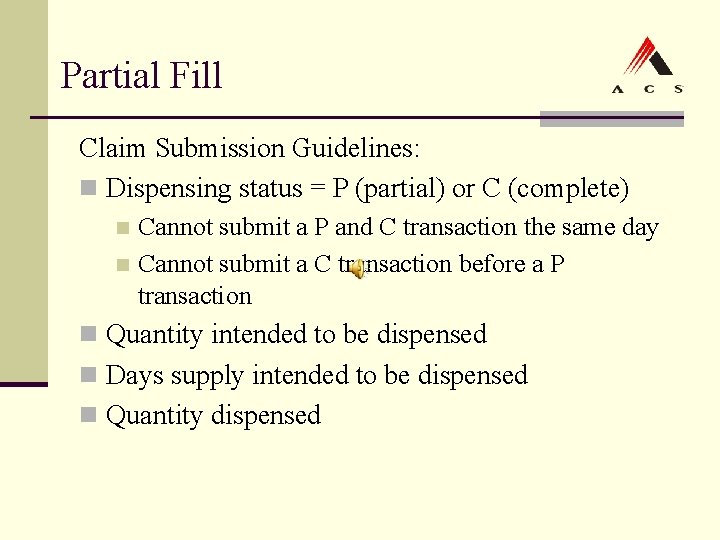
Partial Fill Claim Submission Guidelines: n Dispensing status = P (partial) or C (complete) Cannot submit a P and C transaction the same day n Cannot submit a C transaction before a P transaction n n Quantity intended to be dispensed n Days supply intended to be dispensed n Quantity dispensed
Compounds n Maryland Medicaid only accepts multi-line Compound claims. n If providers submit a compound claim with a single ingredient the claim will be denied. n The system will accept up to 40 line items (individual ingredients) in each compound claim. n The system will allow providers to use submission clarification code 8 (process compound for approved ingredients) to override denials for compound ingredients that are not covered.
Generic Mandatory § The system will deny brand drugs when a generic is available § Edit 22 (M/I /DAW code) and the message text: “Generic Available – Physician to call State at 410767 -1755, Medwatch form required” § When submitted as Brand Medically Necessary (DAW = 1) with the exception of the following (pay at EAC): § § Levothyroxine Brimonidine eye drops
Generic Mandatory n The system will cover brand drugs billed as generic with DAW=5 without preauthorization n Claims for brand drugs will be rejected with NCPDP edit 22 (M/I DAW code) and the message text: “Generic Available – Physician to call State at 410 -767 -1755, Medwatch form required” n The system will accept the following Dispense as Written (DAW) values (NCPDP field 408 -D 8): 0 - Default, no product selection 1 - Physician request 5 - Brand used as generic 6 - Override
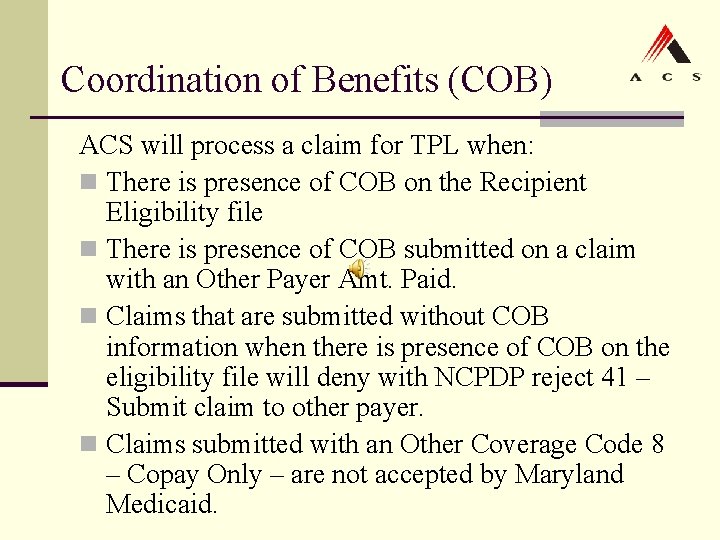
Coordination of Benefits (COB) ACS will process a claim for TPL when: n There is presence of COB on the Recipient Eligibility file n There is presence of COB submitted on a claim with an Other Payer Amt. Paid. n Claims that are submitted without COB information when there is presence of COB on the eligibility file will deny with NCPDP reject 41 – Submit claim to other payer. n Claims submitted with an Other Coverage Code 8 – Copay Only – are not accepted by Maryland Medicaid.
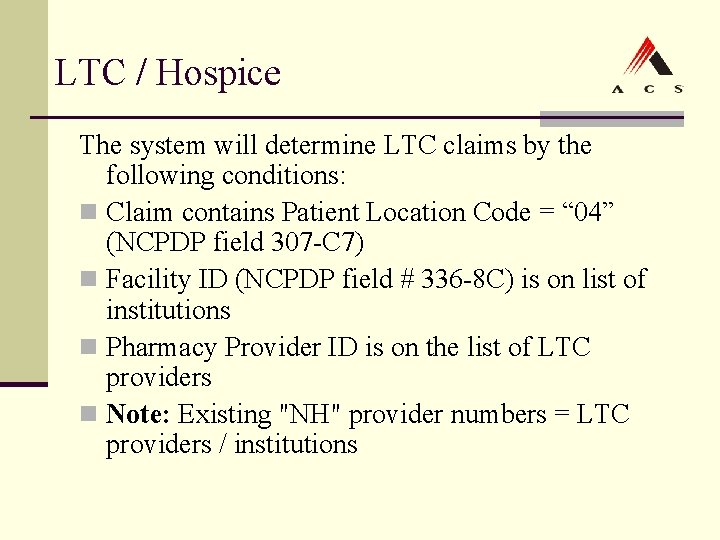
LTC / Hospice The system will determine LTC claims by the following conditions: n Claim contains Patient Location Code = “ 04” (NCPDP field 307 -C 7) n Facility ID (NCPDP field # 336 -8 C) is on list of institutions n Pharmacy Provider ID is on the list of LTC providers n Note: Existing "NH" provider numbers = LTC providers / institutions
LTC / Hospice The system will determine Hospice-Only claims by the following conditions: n Claim contains Patient Location Code = “ 11” (NCPDP n n field 307 -C 7) Client Specific Reporting field on Recipient Eligibility file = "HI" The Date of Service is within an active coverage span on the Recipient Eligibility file Facility ID (NCPDP field # 336 -8 C) is on list of institutions (see appendix in Provider Manual) Note: The system will deny Hospice claims that do not have both a Patient Location code = “ 11” and a Client Specific Reporting field on Recipient Eligibility file = "HI”
LTC / Hospice ACS will determine RECIPIENTS with BOTH LTC/HOSPICE LTC/Hospice claims will be determined by the following distinct conditions: n Client SPECIFIC REPORTING field = "HI" on the recipient's enrollment record with a date span that includes DOS, AND n PATIENT LOCATION (NCPDP field # 307 -C 7) = "11", AND n FACILITY ID (NCPDP field # 336 -8 C) any value on the list of institutions, AND
LTC / Hospice ACS will determine RECIPIENTS with BOTH LTC/HOSPICE LTC/Hospice claims will be determined by the following distinct conditions: (continued from previous slide) n Designated LTC providers in the SERVICE PROVIDER ID (NCPDP field # 201 -B 1) n The system will deny non-LTC claims for unit dose medications with certain exceptions; claims will deny with error 70 (drug not covered) and message text: “Unit Dose Package Size”
Age Limitations Maryland Medicaid will enforce the following age restrictions: n Ferrous sulfate covered for recipients < 12 years n Non-legend chewable tablets of any ferrous salt when combined with vitamin C, multivitamins and minerals, or other minerals in the formulation n Topical Vitamin A Derivatives
Prior Authorizations Methods to obtain a Prior Authorization: n Contact the Call Center or specified State office n Complete and fax a Prior Authorization request form n Smart PA
Prior Authorizations n Maryland Medicaid Staff n n n n n Days supply exceeding maximums Growth Hormones Synagis (Palivizumab) Female Hormones for a male and vice versa Nutritional supplements (see MD PA form for clinical criteria) Recipient Lock-In Price (long-term PAs only) Oxy. Contin Quantity (during business hours) Antihemophilic Drugs (claim pended in X 2 and evaluated manually by State)
Prior Authorizations n Maryland Medicaid Staff (continued) n Duragesic Patch excess quantity (during business hours) n Topical Vitamin A Derivatives n Opiate Agonists for Hospice and Hospice/LTC n Antiemetic excess quantities n Serostim n Botox n Orfadin n Revlimid n Revatio n Brand Medically Necessary
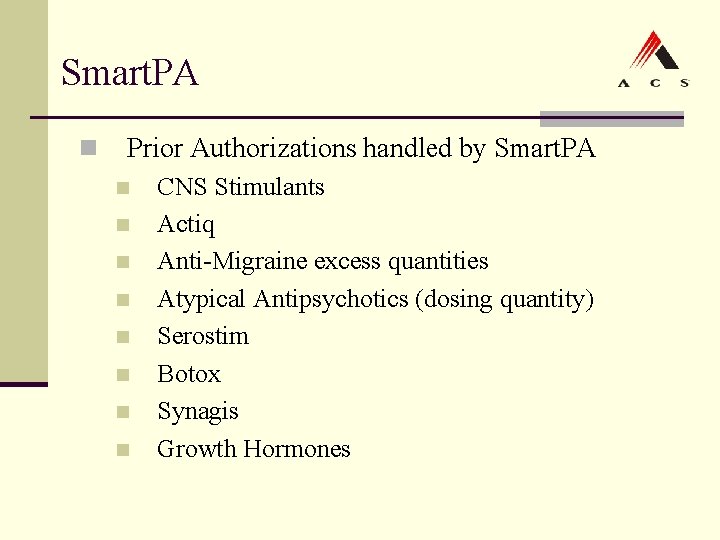
Prior Authorizations n ACS Pro. DUR Call Center Prior Authorizations n Oxycontin, Duragesic Patch Qty (for after hours/weekends only) n Quantity Limits (except Oxy. Contin & Duragesic Patch as noted above) CNS Stimulants n Actiq n Anti-Migraine excess quantities n Atypical Antipsychotics (dosing quantity) n
Prior Authorizations n ACS Technical Call Center n n n PDL - Non-Preferred drugs Early Refill Maximum dollar limit per claim ≥ $2, 500 Age Restrictions Maximum Quantity overrides
Prior Authorizations n Maryland CAMP Office n n Depo Provera Lupron Depot
Smart. PA New Clinical PA rules engine n ACS stores both medical and pharmacy claims history. n Claim is submitted, looks at both while reading the rule. Smart PA will issue a PA if claim and history meet criteria without pharmacy or physician intervention.
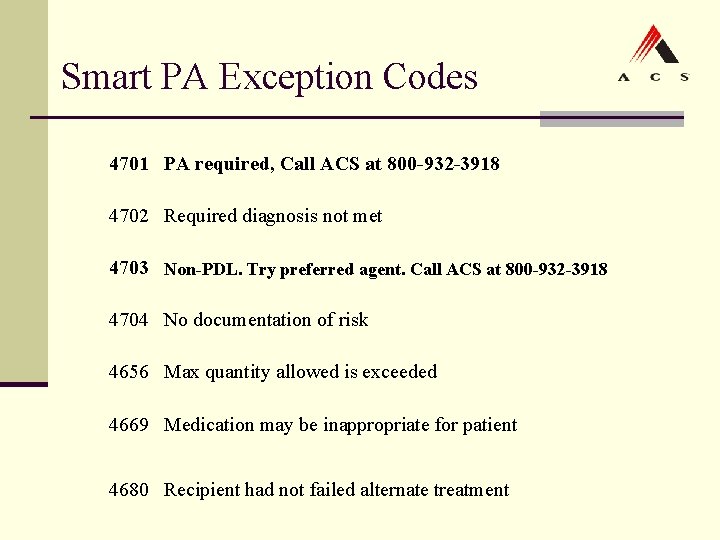
Smart PA Exception Codes 4701 PA required, Call ACS at 800 -932 -3918 4702 Required diagnosis not met 4703 Non-PDL. Try preferred agent. Call ACS at 800 -932 -3918 4704 No documentation of risk 4656 Max quantity allowed is exceeded 4669 Medication may be inappropriate for patient 4680 Recipient had not failed alternate treatment
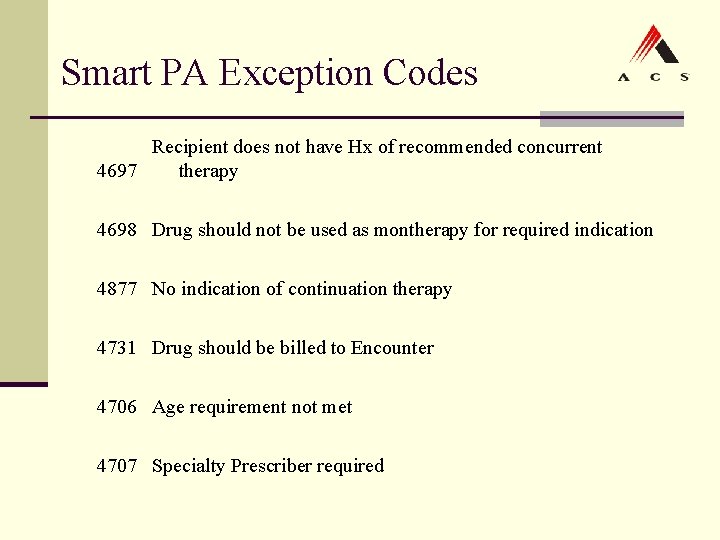
Smart PA Exception Codes Recipient does not have Hx of recommended concurrent 4697 therapy 4698 Drug should not be used as montherapy for required indication 4877 No indication of continuation therapy 4731 Drug should be billed to Encounter 4706 Age requirement not met 4707 Specialty Prescriber required
Smart. PA n Prior Authorizations handled by Smart. PA n n n n CNS Stimulants Actiq Anti-Migraine excess quantities Atypical Antipsychotics (dosing quantity) Serostim Botox Synagis Growth Hormones
Smart. PA n Prior Authorizations handled by Smart. PA n n n n Anti-emetic Topical Vitamin A Orfadin Revlamid Revatio Nutritional Supplements Oxycodone
Breast and Cervical Cancer Diagnosis and Treatment Program (BCCDT)
BCCDT Program Specific Information BIN PCN Group ID Provider ID Prescriber ID Recipient ID 610084 DRDTPROD MDBCCDT NCPDP ID Number DEA Number BCCDT Recipient ID
Copays / Dispensing Fee BCCDT Recipients do not have copays Dispensing fee structure: n BRAND products = $2. 69 n Generic Products = $3. 69 n Partial Fill n Dispensing fee will be paid ½ at the initial fill and ½ at the completion fill
Generic Mandatory n BCCDT has a generic mandatory program in place. n The system will deny brand drugs when a generic is available with NCPDP Reject 22 (M/I Dispense As Written/DAW code) when submitted as Brand Medically Necessary (DAW = 1). n The system will accept the following Dispense as Written (DAW) values (NCPDP field 408 -D 8): n n n 0 - Default, no product selection 1 - Physician request 5 - Brand used as generic
Coordination of Benefits / Copay Only Rules for copay only claim submission: n $60. 00 maximum on all copay only claims. Amounts greater than $60. 00 will have to be approved by BCCDT n BCCDT will pay copays for PAC recipients only if claims contain an "8" in NCPDP field 308 -C 8, Other Coverage Code. n The system will reject PAC claims where the Other Coverage Code is not equal to ‘ 8’ (Copay Only) with reject code edit 70 (Drug Not Covered) and the message text “BCCDT Only Reimburses Copayments – Please bill PAC”
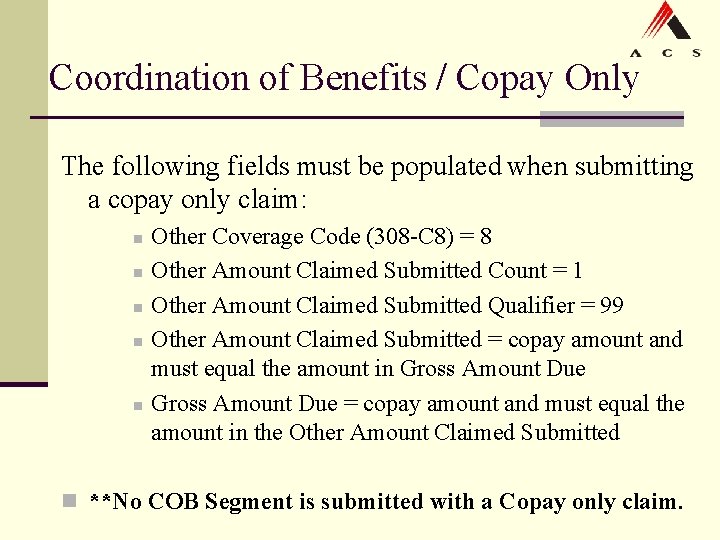
Coordination of Benefits / Copay Only The following fields must be populated when submitting a copay only claim: n n n Other Coverage Code (308 -C 8) = 8 Other Amount Claimed Submitted Count = 1 Other Amount Claimed Submitted Qualifier = 99 Other Amount Claimed Submitted = copay amount and must equal the amount in Gross Amount Due = copay amount and must equal the amount in the Other Amount Claimed Submitted n **No COB Segment is submitted with a Copay only claim.
Coordination of Benefits / Qualified Medicare Beneficiary (QMB) n BCCDT will pay coinsurance for QMB recipients if claims contain an other coverage code of 3 or 4 for Med-B covered drugs only. n The system will reject claims for Medicare B covered drugs for QMB recipients where the other coverage code is not equal to “ 3 or 4”; the response will contain reject code edit 70 (Drug Not Covered) and the message text “BCCDT Only Reimburses Non-Covered Medicare B covered drugs"
Coordination of Benefits / QMB & Medicare B n QMB recipients have pharmacy coverage except for drugs covered by Medicare B such as Xelodathen BCCDT pays only denied claims. Pharmacies must bill Medicare and then Medicaid and BCCDT will be the payer of last resort for coinsurance. n ACS will deny COB claims for Medicare B covered drugs such as Xeloda, if the Other Coverage Code (OCC) is not equal to “ 2” with edit 41 (bill other insurance) and the message text: “Bill Medicare B”.
Coordination of Benefits / Medicare D n BCCDT will cost avoid for Medicare D recipients n Providers are required to ensure COB claims for Medicare D to contain “ 77777” in the Other Payer ID (NCPDP field 340 -7 C). n The Other Payer ID is not required for non. Medicare D carriers
Drug Coverage (BCCDT) n OTC drugs are generally not covered except for the drug listed in the grid in your Pharmacy Provider Manual. n Unit dose drugs are generally not covered except for noted exceptions. n Don't cover meds for pts in LTC facilities
Prior Authorizations BCCDT providers can obtain prior authorizations from two sources: n BCCDT Office n ACS Technical Call Center
Prior Authorizations The MD BCCDT staff will handle the following prior authorization requests: n n Early Refill - For requests outside established criteria PA/Medical Certification - authorization based on diagnosis DME/DMS for HCFA 1500 billing - exception: needles, syringes that are paid through POS PA denials handled by MD BCCDT will return the following message text in the response: “Prior Authorization Required, call MD BCCDT (410) 7676787, M-F, 8: 30 am – 4: 30 pm”.
Prior Authorizations The ACS Call Center will handle the following prior authorization requests on behalf of MD BCCDT: n Early Refill n Maximum dollar amt ≥ $2, 500 n Brand Medically Necessary - DAW 1, with exceptions n Day supply for approved situations n PA denials handled by ACS will return the following message text in the response: “Prior Authorization Required, Call ACS at 1 -800 -932 -3918 (24/7/365)”
Maryland AIDS Drug Assistance Program (MADAP)
MADAP General Information BIN PCN Group ID Provider ID Prescriber ID Recipient ID 610084 DRMAPROD MADAP NCPDP ID Number DEA Number MADAP Recipient ID
Copay / Dispensing Fee MADAP recipients do NOT have a copay Dispensing Fee n Brand Products = $3. 69 n Generic Products = $4. 69 n Partial fills = ½ + ½ dispensing fee.
Coordination of Benefits / Copay only MADAP will allow the submission of copay only claims. The following guidelines must be followed in order for a claim to be processed correctly. If the guidelines are not followed, the claim will deny for one of many reasons.
Coordination of Benefits / Copay Only n n n NO COB SEGMENT SUBMITTED OCC = 8 Other Amount Claimed Qualifier = 99 Other Amount Claimed Submitted = copay amount and must equal the amount in Gross Amount Due = copay amount and must equal the amount in the Other Amount Claimed Submitted
Drug Coverage n The MADAP maintenance drug list = antiretroviral therapies (NNRTIs, PIs, Fusion Inhibitors). n Nutritional Supplies and OTC drugs are NOT covered. n All drugs included in the MADAP formulary are covered. This list can be found in the Pharmacy Provider Manual.
Prior Authorizations Providers can obtain a PA from one of the following entities, depending on the drug being denied: n ACS Technical Call Center n ACS PA Call Center n MADAP n Smart. PA
Prior Authorizations The ACS Technical Call Center will handle the following prior authorization requests for MADAP: n Early Refill n Quantity Limits n Price per claim limit ≥ $2, 500 The following drugs will be handled through Smart. PA first, then if more information is needed – the ACS PA Call Center will handle the request: n Epoetin Alpha (Epogen, Procrit) n Filgrastim (Neupogen) n Oxandrolone (Oxandrin) MADAP Handles all other PA requests.
Maryland Kidney Disease Program (KDP)
General Information BIN PCN Group ID Provider ID Prescriber ID Recipient ID 610084 DRKDPROD MARYLANDKDP NCPDP Number DEA Number Medicaid ID
Copays/Dispensing Fee Maryland KDP has NO copays for it’s recipients. Dispensing Fees: n Brand Products = $2. 69 n Generic Products = $3. 69 n Partials fills = ½ + ½ dispensing fee
Generic Mandatory KDP has a generic mandatory program in place that must be followed. When providers submit a claim for a drug that has a generic equivalent and there is no active PA on file or appropriate DAW code, the claim will deny with an NCPDP Reject code “ 22” – M/I DAW Code.
Generic Mandatory n KDP accepts the following DAW codes: n ACS will ensure that the only valid DAW codes will be 0, 1, 5 and 6: 0 - default, no product selection n 1 - Physician request n 5 - Brand used as generic n 6 - Client Override n
DAW 6 KDP allows the use of DAW 6 for medications determined by KDP as follows (pay at EAC): n Duragesic NDCs: 50458003305, 50458003405, 50458003505, 50458003605, 50458003705 n Rebetol NDCs: 00085119403, 00085132704, 00085135105, 00085138507 n Flonase NDCs: 00173045301
LTC n The KDP system has no LTC recipients n Claims will reject when submitted with LTC identifiers (NCPDP field 307 -C 7, Patient Location = 3 – Nursing Home or 4 -Long Term/Extended Care) with NCPDP edit 70 and message text: “LTC Claims Not Allowed for Reimbursement”.
Maximum Quantity A max quantity limit of 350 for the following Immunosuppressive oral tablets/capsules will be enforced. n Azathioprine n Cyclosporine n Mycophenolate Mofetil (Cellcept) n Sirolimus (Rapamume) n Tacrolimus (Prograf)
Maximum Quantity n The maximum quantity limit for Oxy. Contin is 120. n Note: This is a per fill quantity limit, not an accumulation limit.
Minimum Quantity n There is a minimum quantity limit of 100 tablets for Ferrous sulfate 325 mg tablets n A minimum quantity limit of 480 ml for ferrous sulfate elixir (220 mg/5 ml) will be applied. n KDP will enforce a minimum quantity limit of 60 tablets for non-legend chewable tablets of any ferrous salt when combined with vitamin C, multivitamins and minerals, or other minerals in the formulation
Unit Dose The system will deny claims for unit dose medications with the exception of drugs listed with error 70 (drug not covered) and message text: “Unit Dose Package Size”.
Prior Authorizations Providers can obtain a Prior Authorization from one of the entities listed below: n ACS Technical Call Center n KDP-Nutritional Supplements
Prior Authorizations The ACS Technical Call Center will handle the following prior authorization requests for KDP: n n n Early Refill Quantity Limits Price per claim limit ≥ $2, 500
Prior Authorizations The KDP staff will handle the following prior authorization requests: Nutritional supplements for specific NDCs n DME/DMS for HCFA 1500 billing - Exception: needles, syringes, blood glucose test strips n Providers can reach the KDP prior authorization staff at 410 -767 -5000 or 5002, M-F, 8: 30 am – 4: 30 pm.
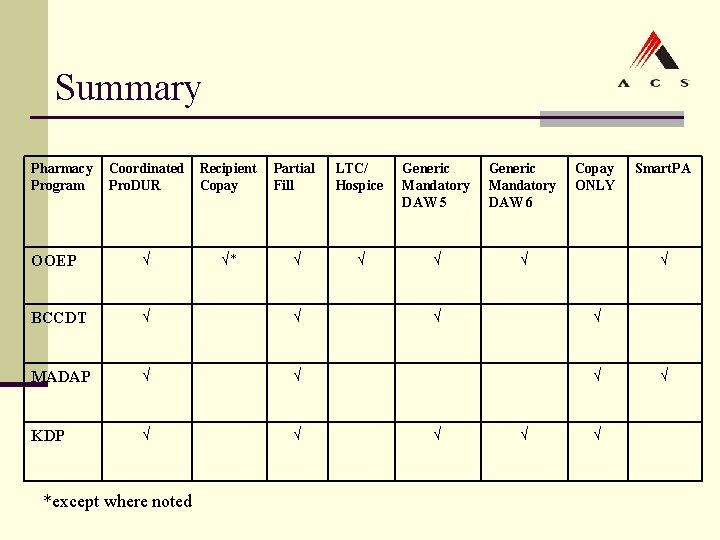
Summary Pharmacy Program Coordinated Pro. DUR Recipient Copay Partial Fill LTC/ Hospice Generic Mandatory DAW 5 Generic Mandatory DAW 6 OOEP √ √* √ √ BCCDT √ √ MADAP √ √ KDP √ √ *except where noted √ Copay ONLY √ √ Smart. PA √ √ √
Conclusion Maryland Pharmacy Programs Website: n http: //mdrxprograms. com n Available on the website: n Pharmacy Provider Manual n Forms to fax prior authorizations n n Maryland Medicaid MADAP
ACS looks forward to working with you and the programs of Maryland DHMH to make this a very successful program.
Questions ?