
HOSPITAL AT HOME ANETTE TANDERUP MD PH D













- Slides: 17
HOSPITAL AT HOME ANETTE TANDERUP MD, PH. D. STUDENT Denmark, Odense University Hospital, Department of Geriatric medicine
Hospital at Home Supervisors: Jesper Ryg, MD, Ph. D. , Post doc. Annmarie Touborg Lassen, MD, Ph. D. , Professor, Head of Research Unit of Emergency Medicine. Anne Lee, Executive Officer, MSc (Health), RN Jens-Ulrik Rosholm: MD, Ph. D. Clinical associate professor.
Hospital at Home Collaboration: Odense Municipality Department of Emergency Medicine Odense University Hospital Department of Health Science and Technology, Aalborg University Centre for Applied Health Services Research Systematic Anygroup Lindpro
Hospital at Home Funding: University of Southern Denmark Research Foundation of Odense University Hospital Patient@home The Velux Foundation No competing interests exist
Hospital at Home Introduction: In the future there will be an increasing number of acutely ill geriatric patients. There is some evidence that being treated in your own home instead of being admitted to the hospital is beneficial for some geriatric patients Caplan Age and Ageing 2006 Zisberg J Am Geriatr Soc 2011 Leff Ann Intern Med 2005 Leff J Am Geriatr Soc 2009
Hospital at Home Objectives: Feasibility of “Hospital at Home” (HH) supported by telemedicine
Hospital at Home Method: Within the first 24 hours after admittance to the medical emergency department (MED) geriatric patients are assessed for their appropriateness and willingness to continue the admission in their own home
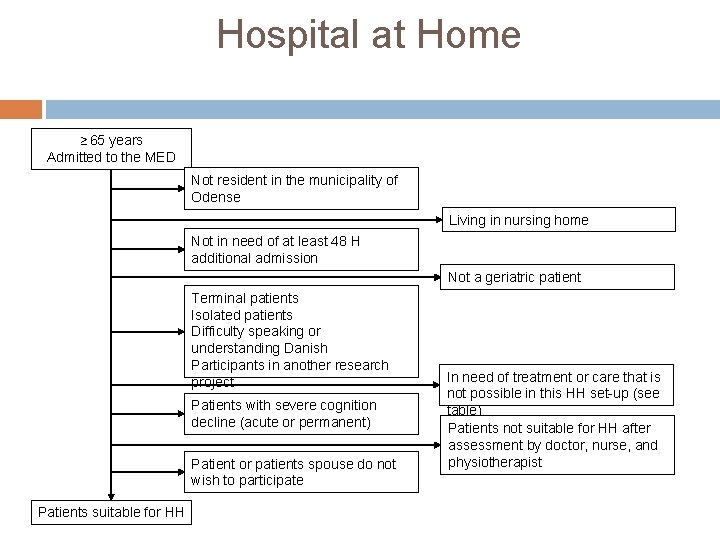
Hospital at Home ≥ 65 years Admitted to the MED Not resident in the municipality of Odense Living in nursing home Not in need of at least 48 H additional admission Not a geriatric patient Terminal patients Isolated patients Difficulty speaking or understanding Danish Participants in another research project Patients with severe cognition decline (acute or permanent) Patient or patients spouse do not wish to participate Patients suitable for HH In need of treatment or care that is not possible in this HH set-up (see table) Patients not suitable for HH after assessment by doctor, nurse, and physiotherapist
Hospital at Home HH Set-up: Nurses from the municipality perform daily care, security checks and triage Geriatric doctor and nurse do “ward round” daily Physiotherapist will attend when needed The patients can be transferred back to the hospital 24/7 in case of deterioration, technical breakdown etc.
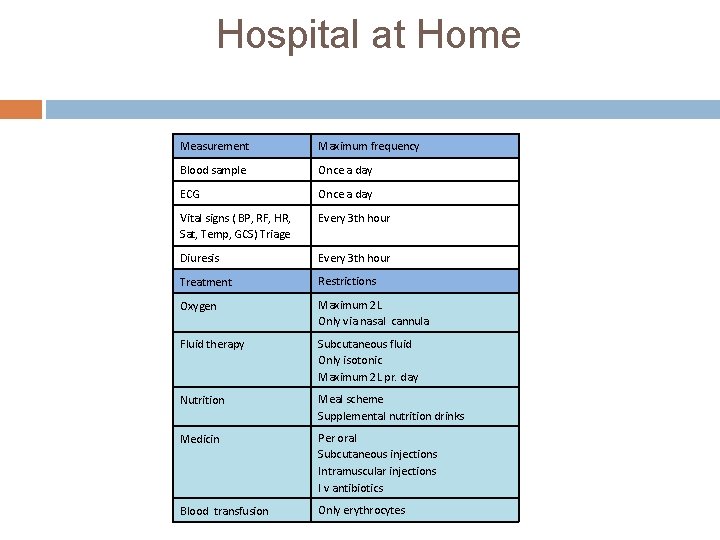
Hospital at Home Measurement Maximum frequency Blood sample Once a day ECG Once a day Vital signs ( BP, RF, HR, Sat, Temp, GCS) Triage Every 3 th hour Diuresis Every 3 th hour Treatment Restrictions Oxygen Maximum 2 L Only via nasal cannula Fluid therapy Subcutaneous fluid Only isotonic Maximum 2 L pr. day Nutrition Meal scheme Supplemental nutrition drinks Medicin Per oral Subcutaneous injections Intramuscular injections I v antibiotics Blood transfusion Only erythrocytes
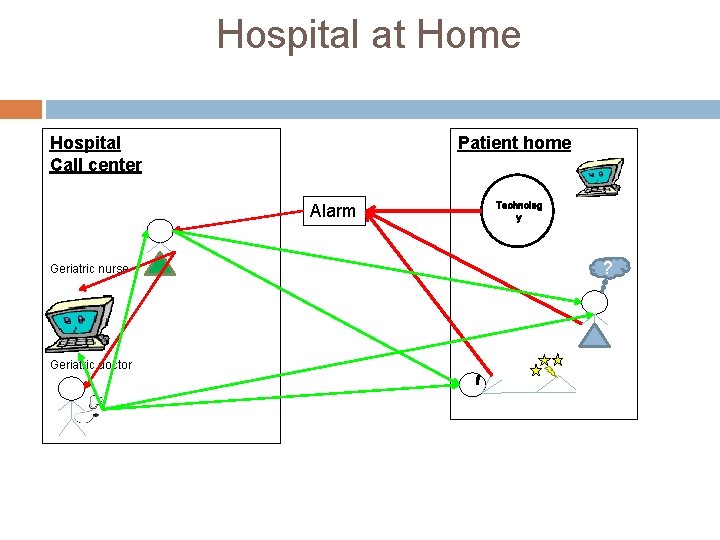
Hospital at Home Technical set-up: Telemedicine is used for safety and communication. An alarm is automatically generated by smoke/fire, falls, “leaving” the house, deterioration in vital signs, and unusual movement pattern at night. Patients, relatives, and personal can also activate the alarm. Alarms go to a call-center nurse who can contact the patient by a call-system where communication and visual inspection is possible. The right help can thus be provided
Hospital at Home Hospital Call center Patient home Alarm Geriatric nurse Geriatric doctor Technolog y ?
Hospital at Home Results: Inclusion is still running and the results are not yet analyzed. The acceptability, practicality, implementation, and demand for HH will be addressed
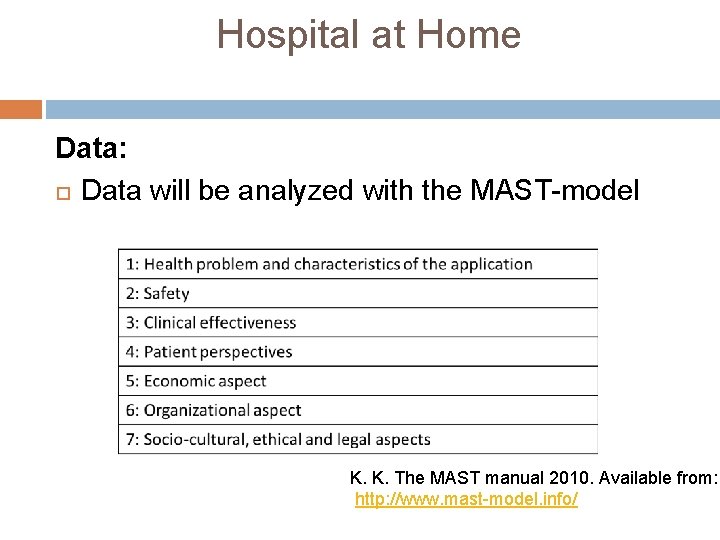
Hospital at Home Data: Data will be analyzed with the MAST-model K. K. The MAST manual 2010. Available from: http: //www. mast-model. info/
Hospital at Home Safety: Steering committee Safety committee Approval from ethical committee Approval from the Danish Data Protection Agency
Hospital at Home Ethic considerations Technology must not replace warm hands! ”You do not se the elderly, when they are ”set free” by welfaretechnology that removes human contact”. ”Technology can survey, but only humans can watch”. Birkler J, Politiken 090215
Hospital at Home Thank you For further information Anette. tanderup@rsyd. dk

















