
Disease review Hypothyroidism and pregnancy 2016 05 02







- Slides: 11
Disease review Hypothyroidism and pregnancy 2016. 05. 02 R 3 백상익
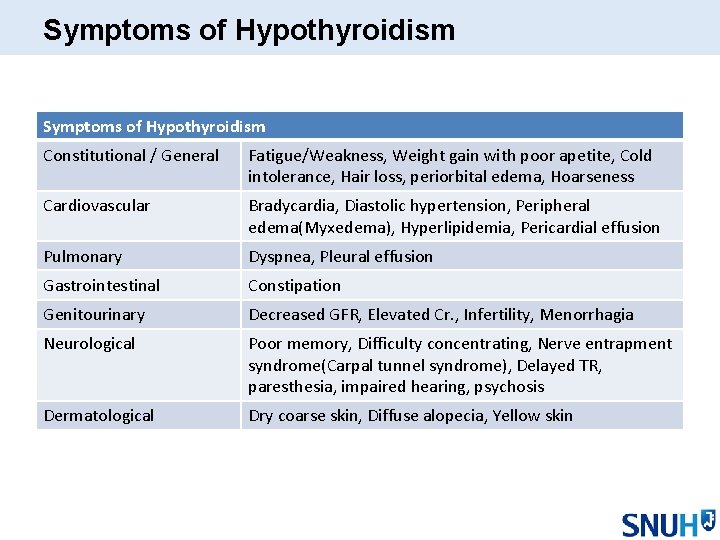
Symptoms of Hypothyroidism Constitutional / General Fatigue/Weakness, Weight gain with poor apetite, Cold intolerance, Hair loss, periorbital edema, Hoarseness Cardiovascular Bradycardia, Diastolic hypertension, Peripheral edema(Myxedema), Hyperlipidemia, Pericardial effusion Pulmonary Dyspnea, Pleural effusion Gastrointestinal Constipation Genitourinary Decreased GFR, Elevated Cr. , Infertility, Menorrhagia Neurological Poor memory, Difficulty concentrating, Nerve entrapment syndrome(Carpal tunnel syndrome), Delayed TR, paresthesia, impaired hearing, psychosis Dermatological Dry coarse skin, Diffuse alopecia, Yellow skin
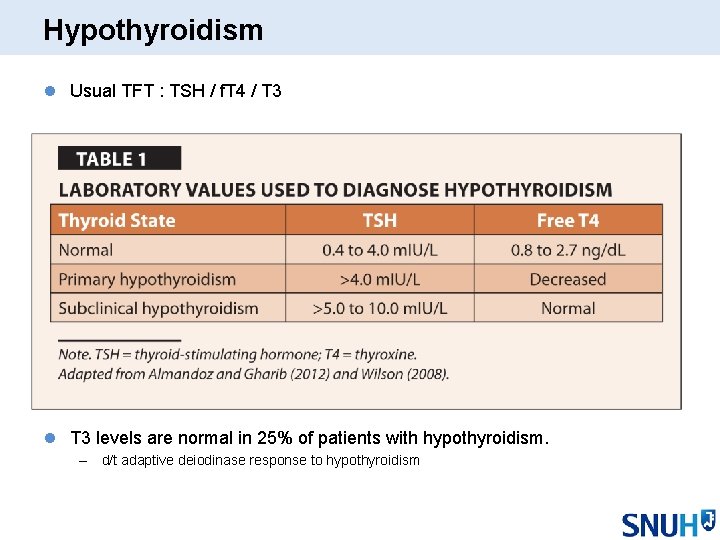
Hypothyroidism l Usual TFT : TSH / f. T 4 / T 3 levels are normal in 25% of patients with hypothyroidism. – d/t adaptive deiodinase response to hypothyroidism
l Worldwide common cause – Iodine deficiency l In Ioidine sufficient area – Autoimmune disease • Hashimotos’s Thyroiditis(90%) – Iatrogenic causes
Hypothyroidism in Pregnancy l 5 factors alter thyroid function in pregnancy – Transient ↑h. CG → stimulating TSH-R • → transient hyperthyroidism → Hyperemesis gravidarum(? ) – – Estrogen-induced ↑TBG Alterations in the immune system ↑ thyroid hormone metabolism by the placenta ↑ urinary iodine excretion → impaired thyroid hormone production in marginal ioidine sufficiency • WHO recommends Iodine intake of 250 ug during pregnancy l 2% of new subclinical hypothyroidism during pregnancy l Indication for screening – FHx of autoimmune thyroid disease – Priror preterm delivery or recurrent miscarriage – Signs or symptoms of hypothyroidism
Hypothyroidism in Pregnancy l Maternal hypothyroidism associated with increased fetal loss, IQ deficit and low birth weight l Both lower/upper normal limit of TSH are decreased by about 0. 1– 0. 2 /1. 0 m. IU/L
Hypothyroidism in Pregnancy l Target TSH level – <2. 5 m. U/L in 1 st trimester (0. 1– 2. 5 m. IU/L) – <3. 0 m. U/L in 2 nd trimester(0. 2– 3. 0 m. IU/L) – <3. 5 m. U/L in 3 rd trimester(0. 3– 3. 5 m. IU/L) l Thyroxine should be increased by 2550 ug/day(or 20 -50%) due to increased requirements and increased binding proteins l In pre-existing hypothyroidism, TFT should be done – First half : every 4 weeks – Latter half : every 6 -8 weeks
Hypothyroidism in Pregnancy l After delivery , thyroxine doses typically return to prepregnancy levels. l Separate ingestion of Vitamins / iron supplements from levothyroxine by at least 4 hr
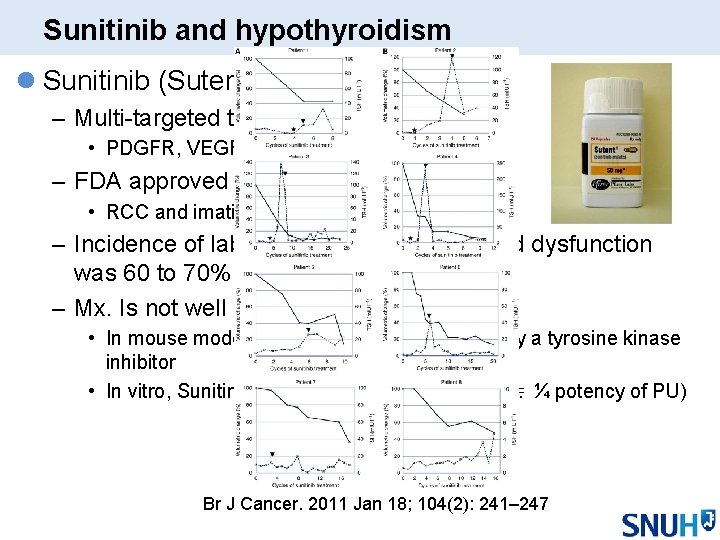
Sunitinib and hypothyroidism l Sunitinib (Sutent) – Multi-targeted tyrosine kinase inhibitor • PDGFR, VEGFR, c-KIT, RET. . – FDA approved (2006) • RCC and imatinib-resistant GIST – Incidence of laboratory evidence of thyroid dysfunction was 60 to 70% – Mx. Is not well known till now • In mouse model, Inhibition of vascularisation by a tyrosine kinase inhibitor • In vitro, Sunitinib had antiperoxidase activity (≒ ¼ potency of PU) Br J Cancer. 2011 Jan 18; 104(2): 241– 247











