IUFD Dr Sadiq Unnisa Associate Professor Definition IUFD




















- Slides: 23
IUFD Dr. Sadiq Unnisa Associate Professor
Definition : • IUFD is defined as delivery of a baby after the period of viability with no signs of life. • Death during labour results in delivery of fresh stillbirth. • Incidence : 35/1000 births
Causes • • Maternal 5 - 10 % Fetal 25 -40 % Placental 20 – 35% Unexplained 25 -35%
MATERNAL : • HTN, DM, IUGR, CRD • Heriditory thrombophilias –protein c, s def, hyperhomocysteinemia • Hyperpyrexia • Antiphosphid • SLE • Trauma, sepsis
MATERNAL • • • Postpartum preg. Labour complication Smoking Massive fetomaternal Hge. Maternal infections –malaria, hepatitis, toxo,
Fetal • • • Chromosomal Abnormalities Major structural anomalies Rh. ISO immunization Infection – CMV, toxoplasmosis parvo Non immune
Placental • abruption, • vasaprevia, • cord accidents - True knots, torsion, stricture, Hematoma, prolapse, cord around the neck. • Chorioamnionitis • TTTS
Iatrogenic /idiopathic • External cephalic version • Drugs - quinine
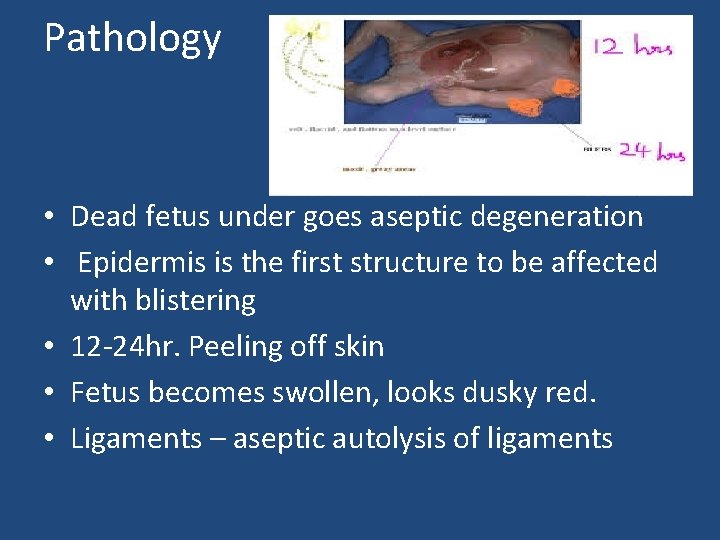
Pathology • Dead fetus under goes aseptic degeneration • Epidermis is the first structure to be affected with blistering • 12 -24 hr. Peeling off skin • Fetus becomes swollen, looks dusky red. • Ligaments – aseptic autolysis of ligaments
Diagnosis • • H/O loss of fetal movements Gradual regression of uterine height Uterine tone is diminished Fetal movements not felt Absent FHR Egg shell crackling feel of fetal head e/o macrosomia / polyhydramnios
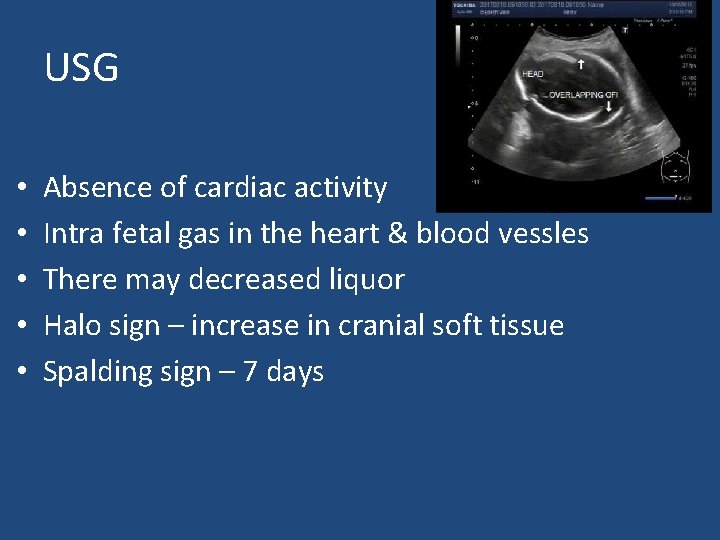
USG • • • Absence of cardiac activity Intra fetal gas in the heart & blood vessles There may decreased liquor Halo sign – increase in cranial soft tissue Spalding sign – 7 days
X-ray : • Crumpled up spine – ball sign • Presence of gas in fetal large vessel Robert’s sign (12 hrs) • Crowding of ribs
Complications • • DIC – 10% within 4 weeks Infection psychological upset Postpartum Hge.
Management • • • Immediate Termination of pregnancy Suppression of lactation Brief management Evaluation of the cause Subsequent pregnancy
• Late IUFD, sudden and unexpected – empathetic approach • Both partners should be involved in all decisions • Attempt to find the cause • Monitoring for coagulation failure
Termination of pregnancy • In case of abruption, PEC – Deliver immediately • Delay may not pose problems to mother. • Usefulness of autopsy may be reduced by undue prolonging • Test for coagulation failure • Cross match blood should be available • Vaginal delivery is preferred except in placenta previa transverse lie / previous 2 LSCS
Mode of Induction : • Combination mifepristone / PG • PGE 1100 mcg PV - 6 th hrly. (before 26 weeks) 25 -50 mcg - 4 th hrly. After 26 weeks Previous LSCS mifepristone 200 mg thrice x 2 day or 600 mg once daily x 2 day – With POG E 2
Suppression of lactation : • Cabergoline • Analgesics • Contraception
Grief management : • Mother partner, other children Evaluation of cause : • Maternal – ICT, bile acids, VDRL, FBS, PPBS, APLA – Placental biospy, fetal skin
• • • Parents willing – perinatal autopsy Baby weight, sex External appearance Any malformation Cord knots, no. of vessels • If cause is found – communicate to parents
Subsequent pregnancy : • Rh ISO immunization • Genetic cause – prenatal diagnosis • More frequent AN visits – pick PIH, IUGR early • GDM – Look in each trimester • Low dose aspirin to be started early • APLA – aspirin / heparin