
ECG Master Session SENIOR RESIDENT EDITION SHIVDA PANDEY


- Slides: 23
ECG Master Session SENIOR RESIDENT EDITION SHIVDA PANDEY, PGY-6 MARK VILLALON, PGY-6 BOSTON MEDICAL CENTER CARDIOVASCULAR FELLOWS
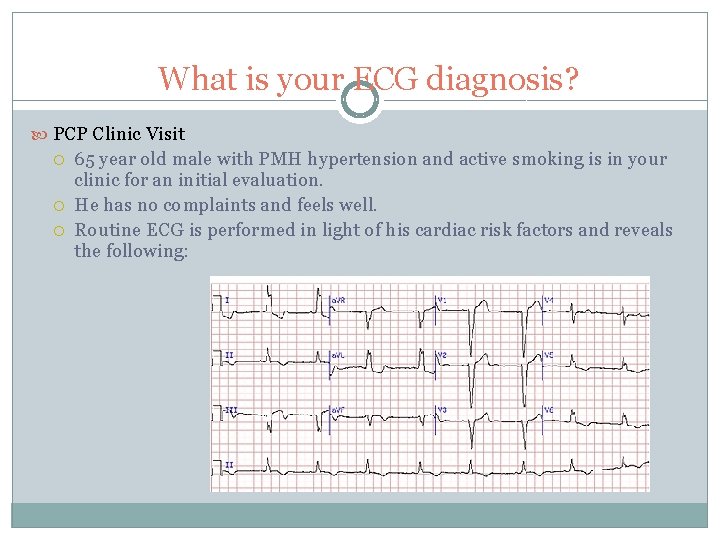
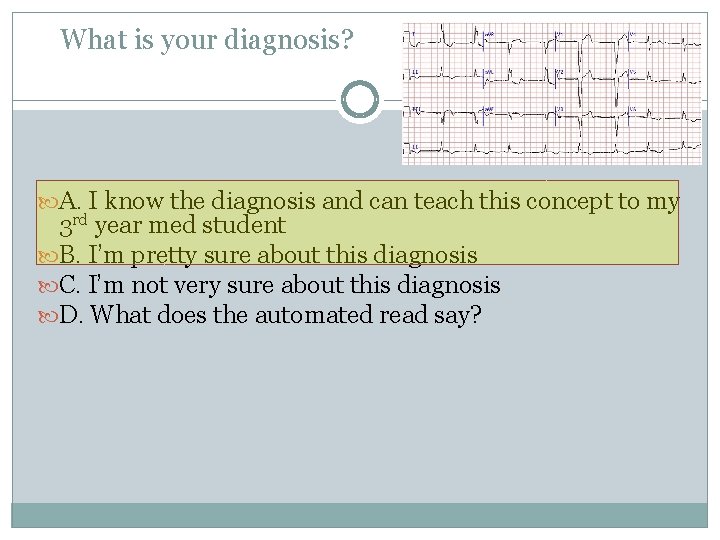
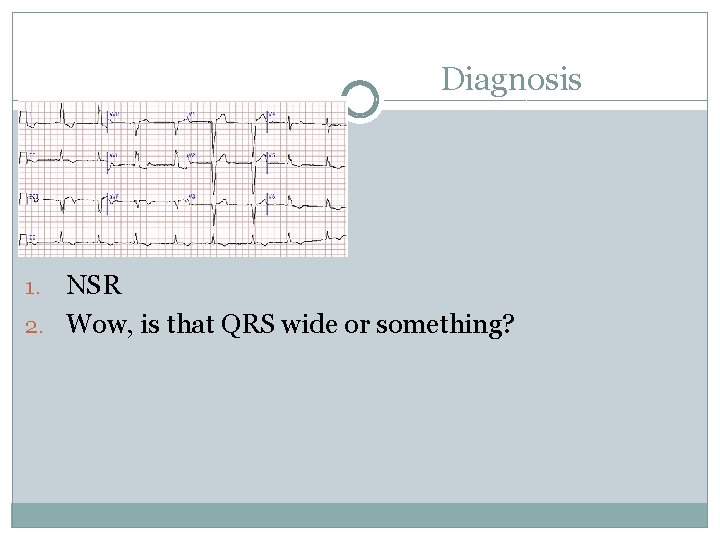
What is your ECG diagnosis? PCP Clinic Visit 65 year old male with PMH hypertension and active smoking is in your clinic for an initial evaluation. He has no complaints and feels well. Routine ECG is performed in light of his cardiac risk factors and reveals the following:
What is your diagnosis? A. I know the diagnosis and can teach this concept to my 3 rd year med student B. I’m pretty sure about this diagnosis C. I’m not very sure about this diagnosis D. What does the automated read say?
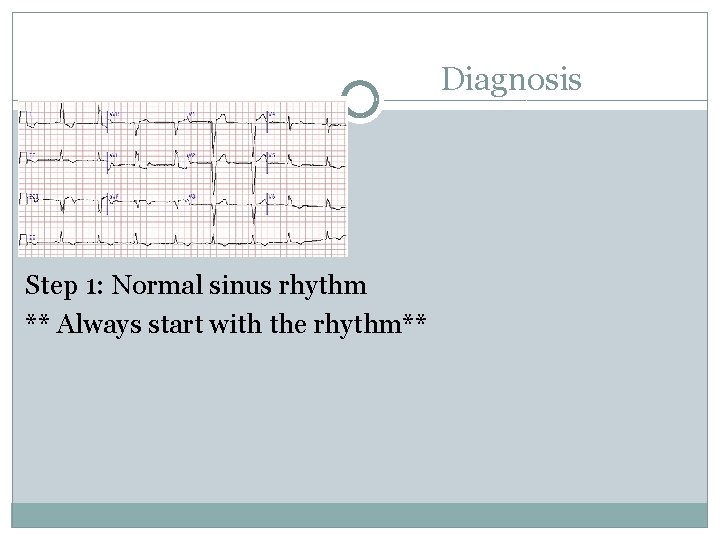
Diagnosis Step 1: Normal sinus rhythm ** Always start with the rhythm**
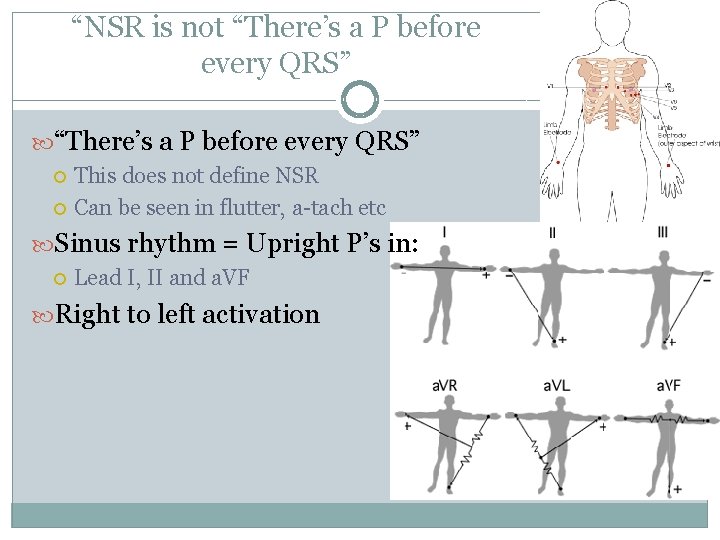
“NSR is not “There’s a P before every QRS” This does not define NSR Can be seen in flutter, a-tach etc Sinus rhythm = Upright P’s in: Lead I, II and a. VF Right to left activation
Diagnosis NSR 2. Wow, is that QRS wide or something? 1.
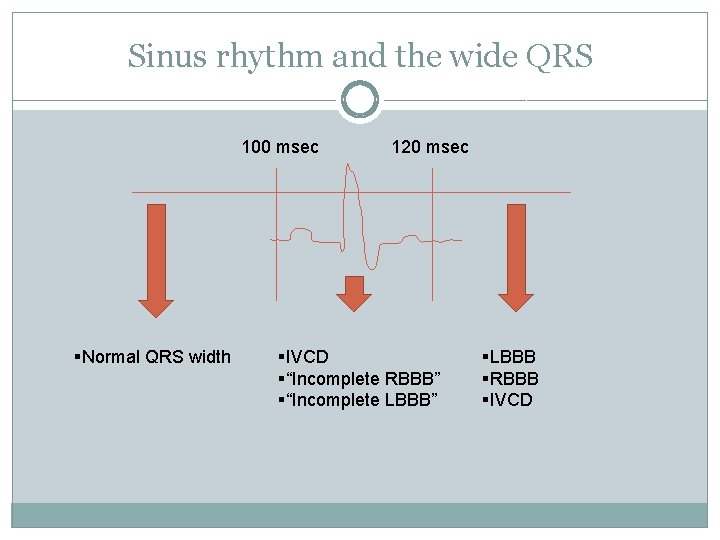
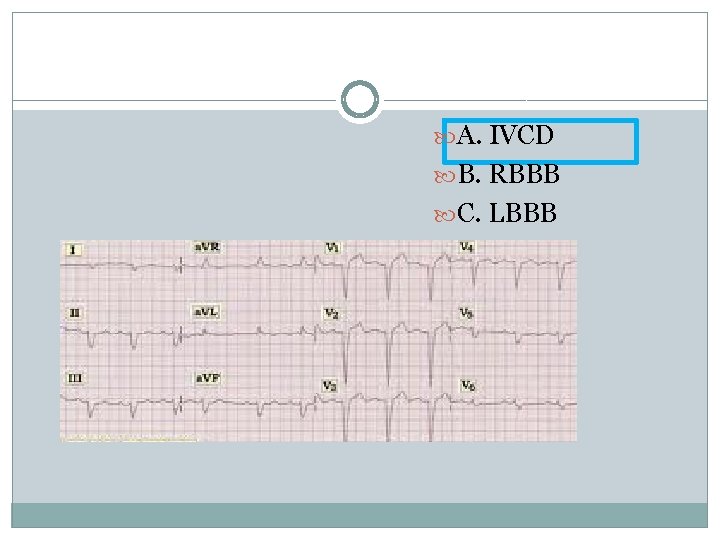
Sinus rhythm and the wide QRS 100 msec §Normal QRS width 120 msec §IVCD §“Incomplete RBBB” §“Incomplete LBBB” §LBBB §RBBB §IVCD
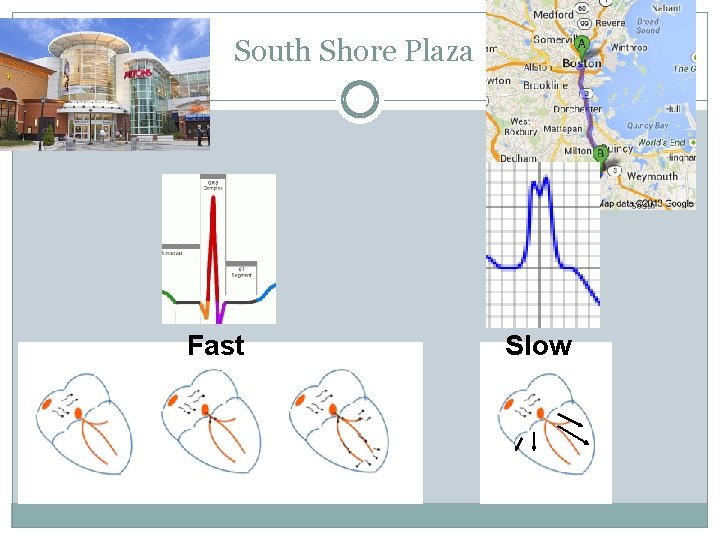
South Shore Plaza Fast Slow
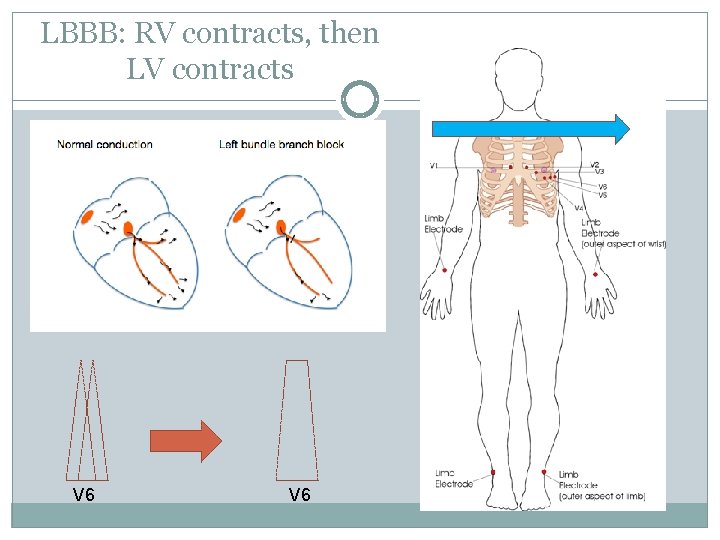
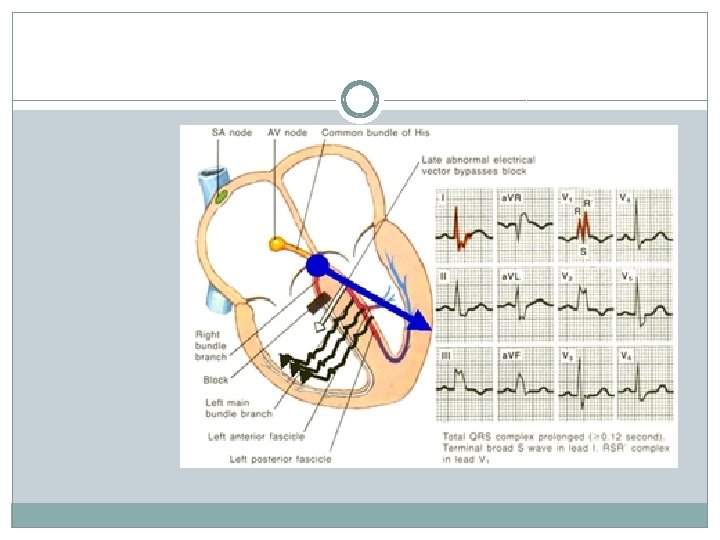
LBBB: RV contracts, then LV contracts V 6
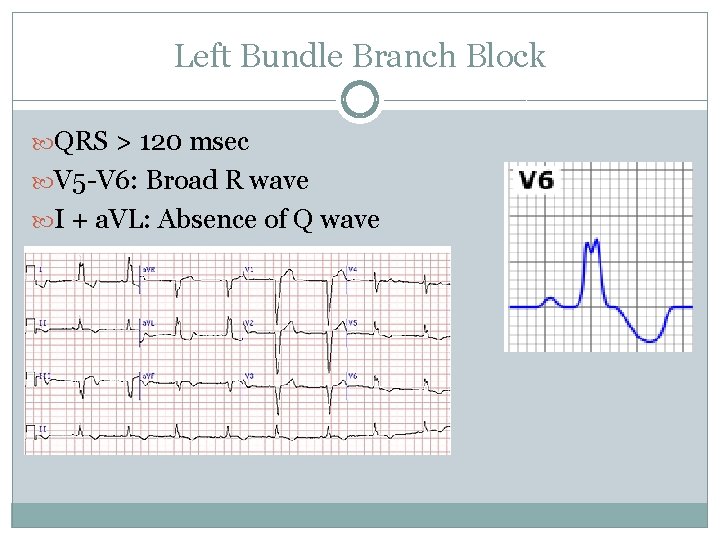
Left Bundle Branch Block QRS > 120 msec V 5 -V 6: Broad R wave I + a. VL: Absence of Q wave
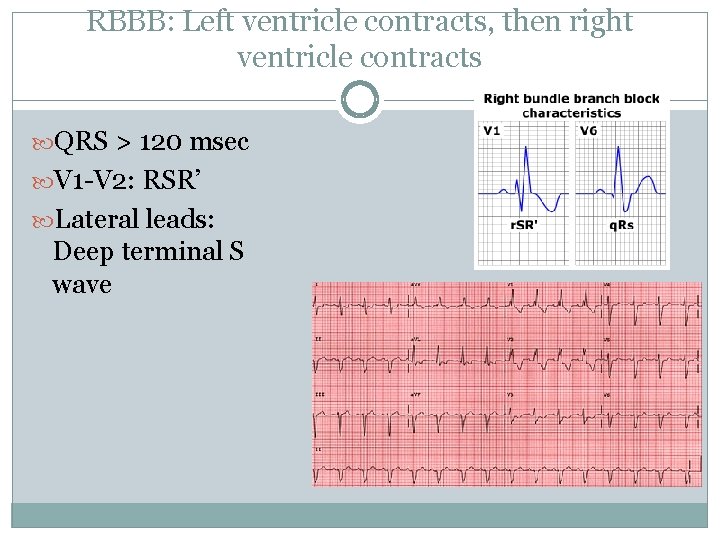
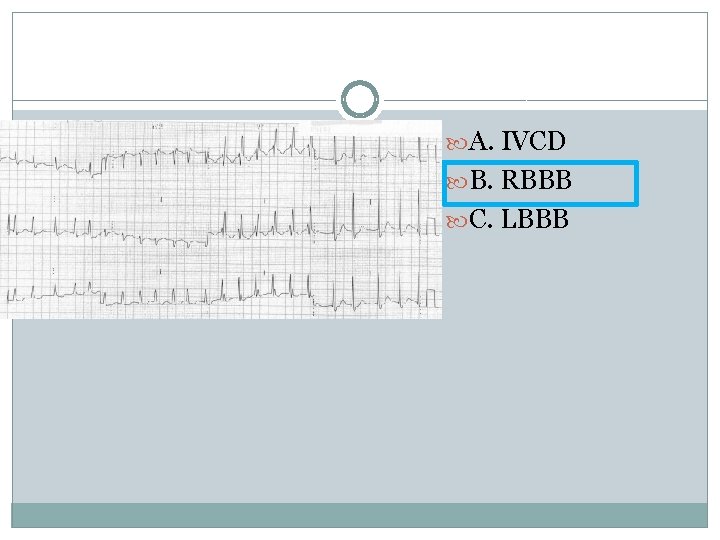
RBBB: Left ventricle contracts, then right ventricle contracts QRS > 120 msec V 1 -V 2: RSR’ Lateral leads: Deep terminal S wave
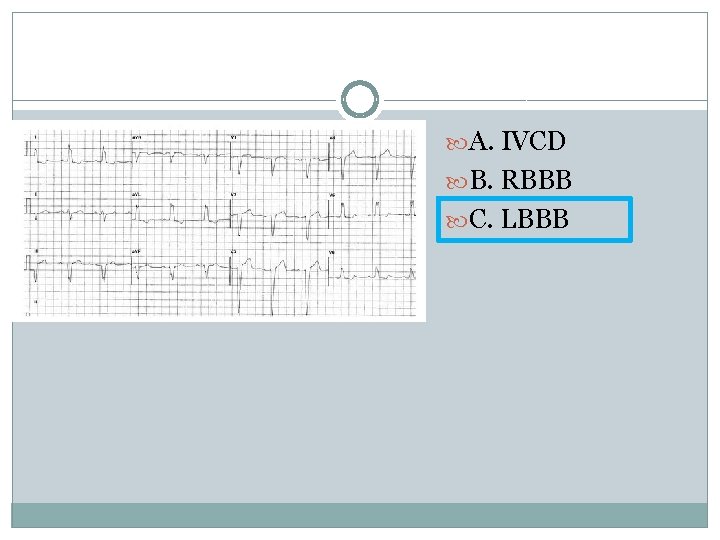
A. IVCD B. RBBB C. LBBB
A. IVCD B. RBBB C. LBBB
A. IVCD B. RBBB C. LBBB
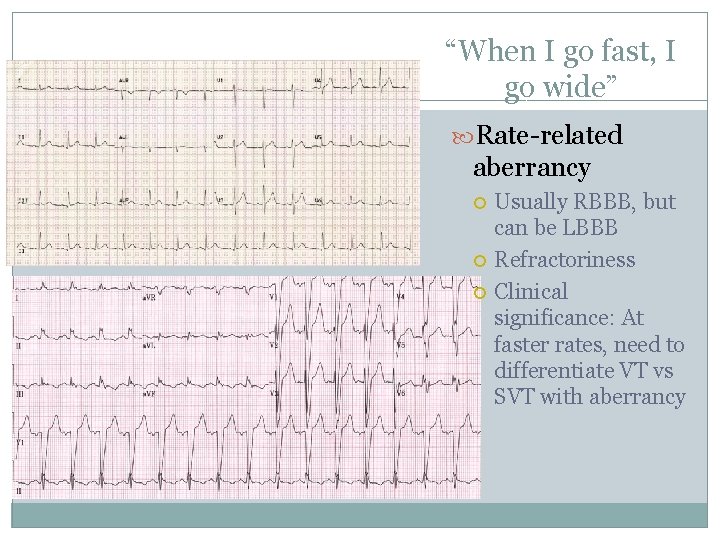
“When I go fast, I go wide” Rate-related aberrancy Usually RBBB, but can be LBBB Refractoriness Clinical significance: At faster rates, need to differentiate VT vs SVT with aberrancy
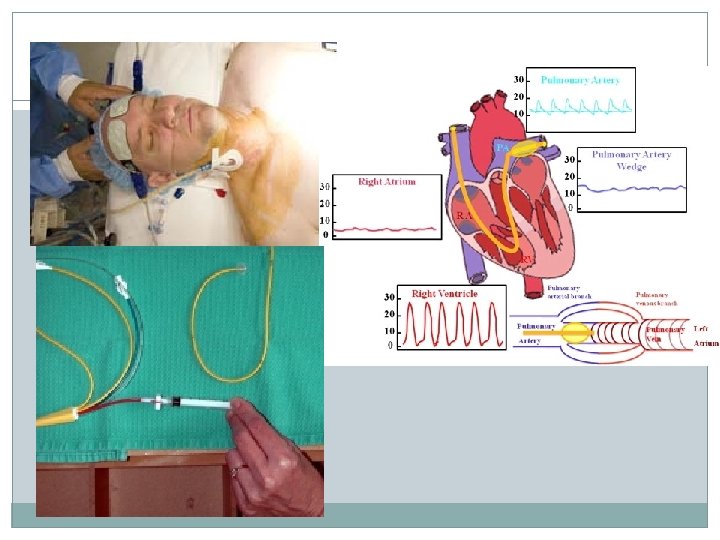
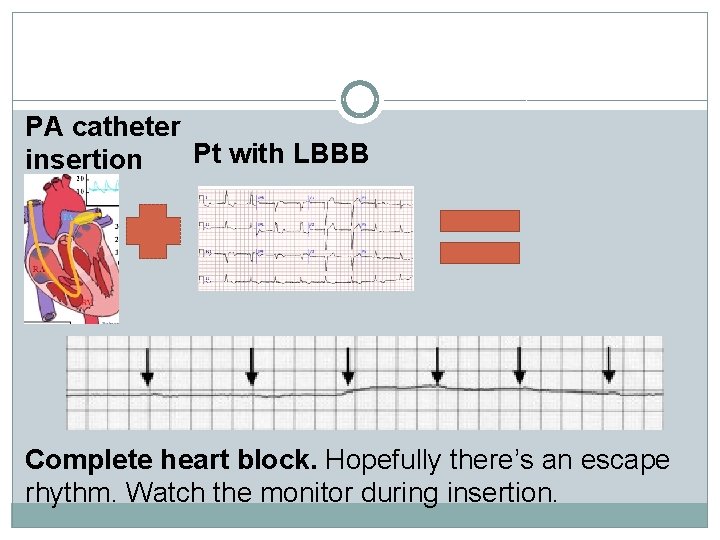
PA catheter Pt with LBBB insertion Complete heart block. Hopefully there’s an escape rhythm. Watch the monitor during insertion.
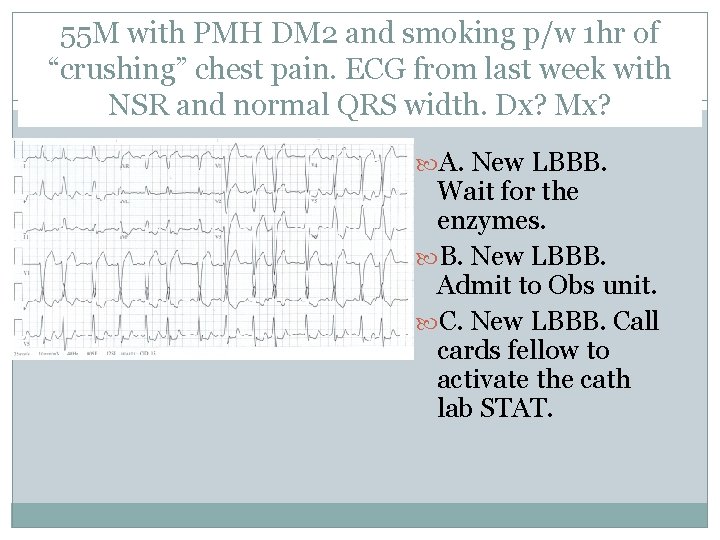
55 M with PMH DM 2 and smoking p/w 1 hr of “crushing” chest pain. ECG from last week with NSR and normal QRS width. Dx? Mx? A. New LBBB. Wait for the enzymes. B. New LBBB. Admit to Obs unit. C. New LBBB. Call cards fellow to activate the cath lab STAT.
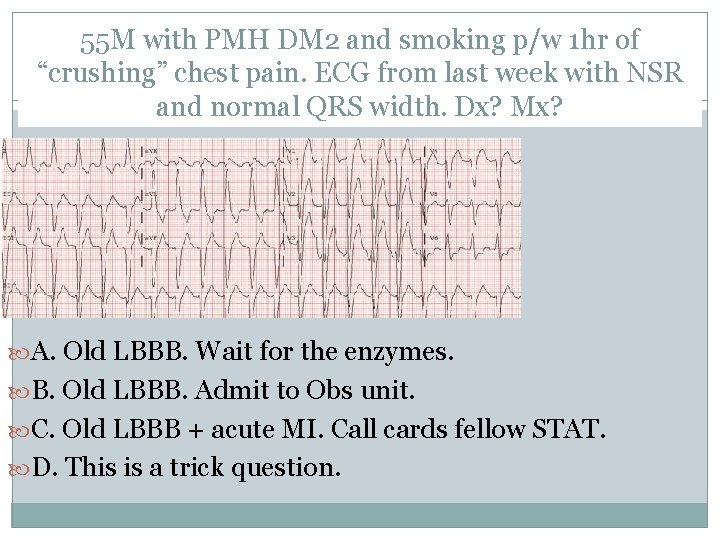
55 M with PMH DM 2 and smoking p/w 1 hr of “crushing” chest pain. ECG from last week with NSR and normal QRS width. Dx? Mx? A. Old LBBB. Wait for the enzymes. B. Old LBBB. Admit to Obs unit. C. Old LBBB + acute MI. Call cards fellow STAT. D. This is a trick question.
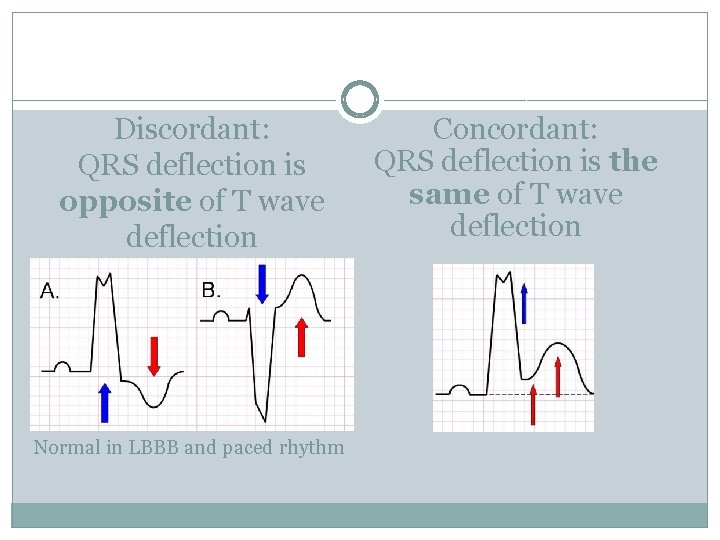
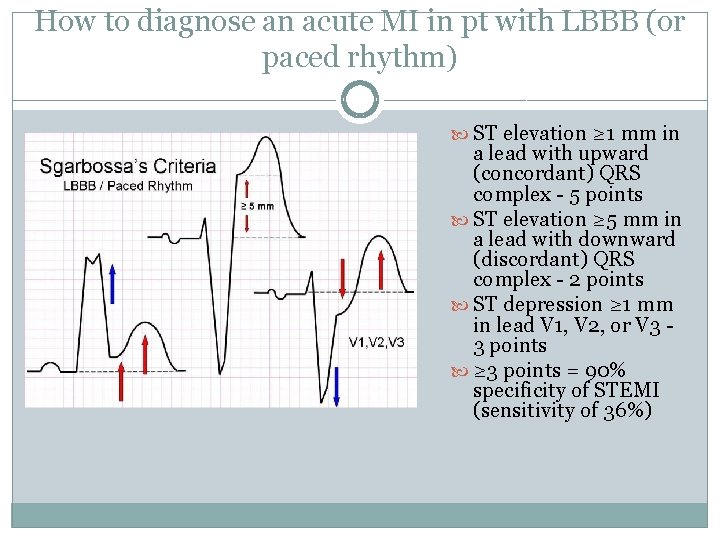
Discordant: QRS deflection is opposite of T wave deflection Normal in LBBB and paced rhythm Concordant: QRS deflection is the same of T wave deflection
How to diagnose an acute MI in pt with LBBB (or paced rhythm) ST elevation ≥ 1 mm in a lead with upward (concordant) QRS complex - 5 points ST elevation ≥ 5 mm in a lead with downward (discordant) QRS complex - 2 points ST depression ≥ 1 mm in lead V 1, V 2, or V 3 - 3 points ≥ 3 points = 90% specificity of STEMI (sensitivity of 36%)
Thank you























