Joint Hospital Surgical Grand Round Unusual cause of











- Slides: 22
Joint Hospital Surgical Grand Round Unusual cause of LGIB Jason LI
Case presentation ¥ M/55 ¥ Known child B cirrhosis, HBV related ¥ History of esophageal varices with EBL in 2014 ¥ Last surveillance OGD 1 month ago: minimal varices with no banding required ¥ Developed hematochezia (fresh blood + clots) ¥ Hemodynamically stable
¥ Proctoscopy: Few areas of active oozing around 5 cm from anal verge. Lots of blood with underlying pathology cannot be seen ¥ On call team impression: bleeding mucosal lesions (ulcers/haemorrhoids)
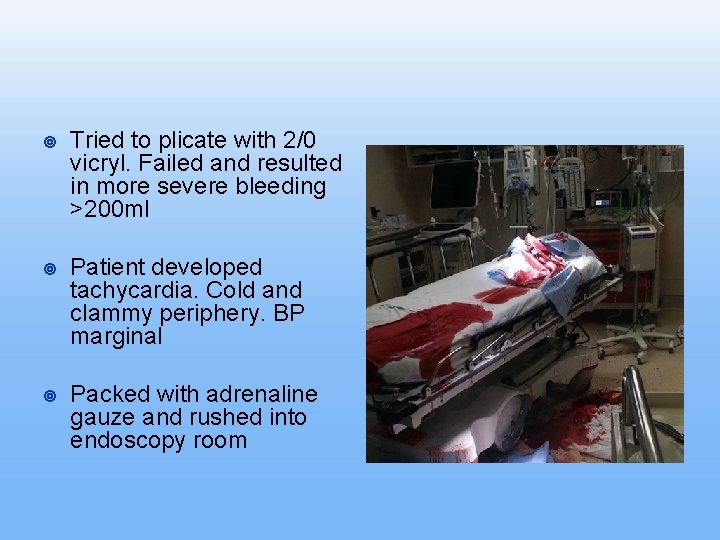
¥ Tried to plicate with 2/0 vicryl. Failed and resulted in more severe bleeding >200 ml ¥ Patient developed tachycardia. Cold and clammy periphery. BP marginal ¥ Packed with adrenaline gauze and rushed into endoscopy room
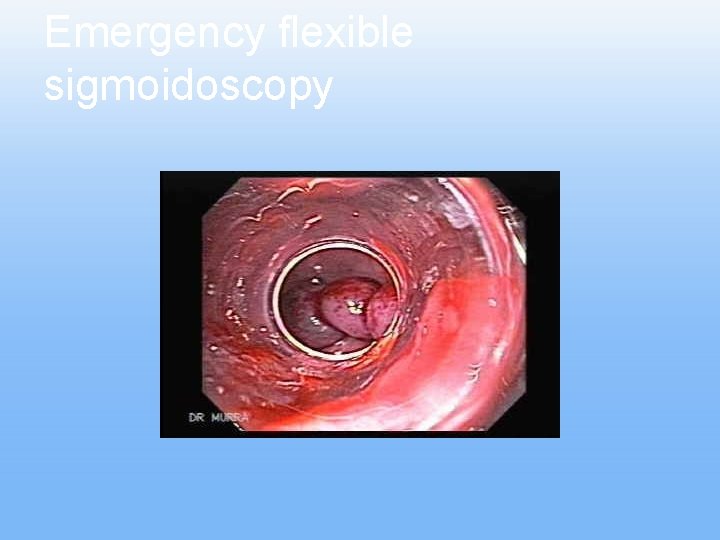
Emergency flexible sigmoidoscopy
Introduction ¥ Varices Commonest: Esophagogastric ¥ Others: small + large bowels, retroperitoneal ¥ ¥ Treatment for esophageal varices is well established Endoscopic band ligation (EBL) ¥ Endoscopic injection sclerotherapy (EIS) ¥ Garcia-Tsao G, Hepatology 2007
Rectal varices ¥ First reported case in 1954 ¥ Definition Dilated veins that originate > 4 cm above anal verge ¥ Not contiguous with anal columns or dentate line ¥ Cabot RC, N Engl J Med 1954 Ganguly S, Hepatology 1995
Epidemiology ¥ Prevalence Cirrhotic patient: 38 -56% ¥ Extrahepatic portal vein obstruction 63 -94% ¥ ¥ Clinically significant bleeding: 0. 5 -5% Misra SP, Endoscopy 2005 Shudo R, Endoscopy 2002
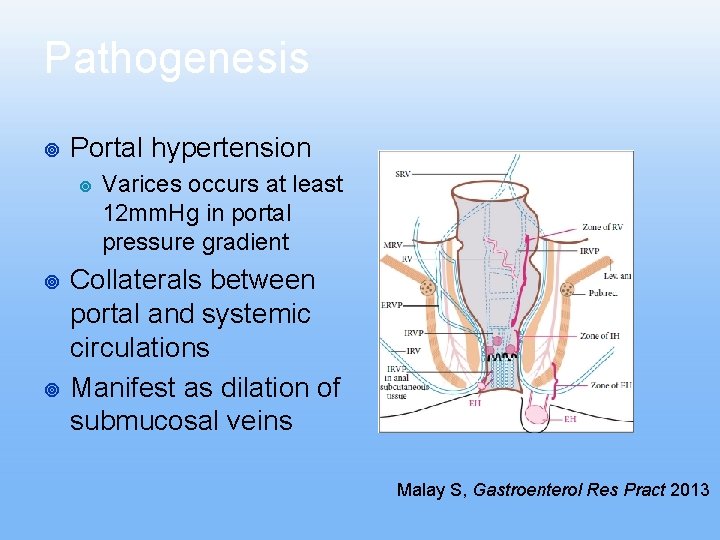
Pathogenesis ¥ Portal hypertension ¥ ¥ ¥ Varices occurs at least 12 mm. Hg in portal pressure gradient Collaterals between portal and systemic circulations Manifest as dilation of submucosal veins Malay S, Gastroenterol Res Pract 2013
Pathogenesis ¥ Correlated with severity of cirrhosis ¥ Correlated with esophageal varices Cirrhosis + NO esophageal varices: 19% ¥ Cirrhosis + esophageal varices: 39% ¥ Cirrhosis + bleeding esophageal varices: 59% ¥ Moller S, Gut 2011 Hosking SW, Lancet 1989
Pathogenesis ¥ Related to obliteration of esophageal varices 95%: history of esophgeal varices ¥ 87% of these patient had EBL or EIS ¥ Postulation: obliteration of shunts to superior mesenteric vein => development of shunt in inferior mesenteric vein ¥ Watanabe N, Hepatol Res 2010
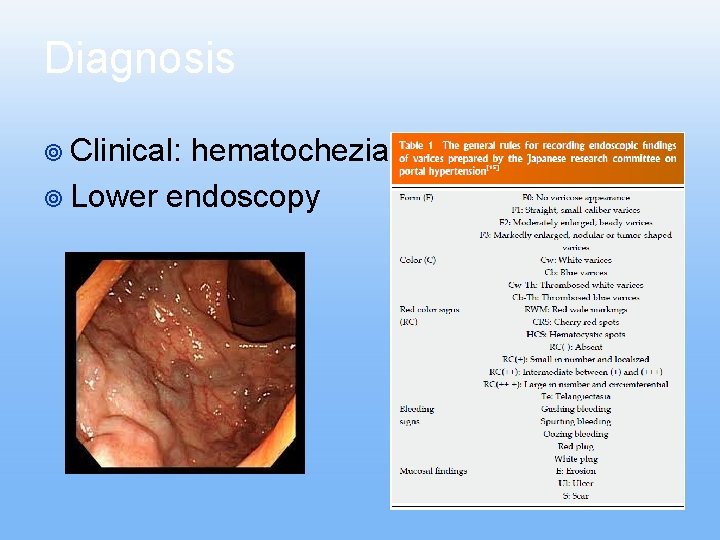
Diagnosis ¥ Clinical: hematochezia ¥ Lower endoscopy
Endoscopic ultrasound ¥ ¥ ¥ Echo-free structures in submucosa Perirectal collateral veins outside rectal wall Deep rectal varices not seen in endoscopy Better detection than endoscopy (85% vs 45%) Predicts risk of bleeding Identify proper site of intervention Dhiman RK, Gastrointest Endosc 1993 Sato T, Hepato Res 2003
Treatment ¥ Resuscitation +/- blood transfusion SBP 90 -100 mm. Hg ¥ Pulse < 100 bpm ¥ Hb ~8 g/d. L ¥ ¥ Correction of coagulopathy ¥ Prophylactic antibiotics: prevent hepatic encephalopathy + spontaneous bacterial peritonitis ¥ Role of vasoactive drugs?
Endoscopic treatment ¥ Endoscopic injection sclerotherapy First reported useful in 1985 ¥ 5% ethanolamine oleate ¥ Under fluoroscopic guidance ¥ Evaluate hemodyanmic before injection ¥ Recurrence rate: 24% during 1 year FU ¥ Sato T, Clin Exp Gastroenterol 2010
Endoscopic treatment ¥ Endoscopic ¥ band ligation Well established in esophageal varices ¥ Demonstrates less complication than EIS Several case reports: supportive ¥ Compared with EIS ¥ Recurrence rate is more (33. 3% vs 55. 6%) ¥ No complication in EIS ¥ One complication in EBL: bleeding rectal ulcer ¥ Sato T, Clin Exp Gastroenterol 2010
Interventional radiology ¥ Transjugular intrahepatic portosystemic shunt (TIPS) Bridge for transplant ¥ Avoid surgical shunting ¥ First used for rectal varices in 1993 ¥ Largest series in 2008 ¥ ¥ ¥ 67% successful rate Problem: larger vein in rectal varices => lower portal pressure needed? Kochar N, Aliment Pharmacol Ther 2008
Interventional radiology ¥ Embolisation (antegrade) Usually performed with TIPS ¥ Transhepatic approach: cannulation of right anterior branch of intrahepatic portal vein ¥ Angiogram demonstrates shunting ¥ Injection of occlusive materials in afferent veins ¥ ¥ ¥ Coils, gelfoam, thrombin, collagen, autologous blood clots CT: accumulation of lipiodol in. World rectal varices 2015 Ahn SS, J Gastroenterol
Interventional radiology ¥ Balloon occluded retrograde transvenous obliteration Occlude outflow of portosystemic shunt ¥ Compared with TIPS ¥ Less invasive ¥ Better in patient with poor liver reserve + HE ¥ ¥ Potential increase in portal pressure? ¥ One case report: worsening of pre-existing OV Yoshino K, Hepatol Res 2014
Surgical treatment ¥ Simple ¥ suture ligation Technically challenging + often not successful ¥ Inferior mesenteric vein occlusion ¥ Porto-caval shunt ¥ 80% mortality rate within 2 months Bittinger M, Gastrointest Endosc 2004
Surgical treatment ¥ Stapled device First reported in 2002 ¥ Successfully control bleeding after failure of EIS/EBL ¥ No further rebleeding in 2 years ¥ ¥ All are case report/series Kaul AK, Colorectal Dis 2009
Conclusion ¥ Important differential diagnosis for PR bleeding in cirrhotic patient ¥ Treatment is more or less like esophageal varices (though evidence is not well established) ¥ No head-to-head comparison between different treatment modalities ¥ Prophylactic treatment?